● LIVE #ESMO26 live from Madrid, Oct 23–27 — today’s highlights, trending trials and physician reactions Follow ESMO 2026 live →
KOL Pulse — Trial Profile

CheckMate-8HW Trial

CheckMate-8HW is a Phase 3 trial of nivolumab (Opdivo) plus ipilimumab (Yervoy) in microsatellite-instability-high or mismatch-repair-deficient (MSI-H/dMMR) metastatic colorectal cancer. As first-line therapy, nivolumab-ipilimumab dramatically improved progression-free survival versus chemotherapy (median not reached vs 5.8 months; HR 0.21). At the final analysis of overall survival, a key secondary endpoint (ESMO 2026; data cutoff May 28, 2026), nivolumab-ipilimumab significantly improved OS versus chemotherapy in the first line (HR 0.37) and versus nivolumab across all lines (HR 0.61) in patients with centrally confirmed MSI-H/dMMR status; the first-line comparison versus nivolumab (HR 0.66) did not meet its significance threshold. In April 2025 the FDA approved nivolumab plus ipilimumab for MSI-H/dMMR unresectable or metastatic colorectal cancer. Sponsor: Bristol Myers Squibb with Ono Pharmaceutical.

1L MSI-H/dMMR metastatic colorectal cancerOpdivo + YervoyASCO GI 2024 / 2025 / ESMO 2025 / ESMO 2026 (final OS)✓ FDA Approved (2025-04)
Discover KOL Sentiment on CheckMate-8HW →

Physician reactions to CheckMate-8HW

Posts by physicians about CheckMate 8HW, newest first: ESMO 2026 week (October 17–24, 2026), then earlier posts from the ASCO 2024, ASCO GI 2025 and ESMO 2025 readouts and the April 2025 FDA approval. Each post is shown in full and verbatim and linked to the original on X.

Arndt Vogel
Arndt Vogel@ArndtVogel
𝕏

Final OS results from CheckMate 8HW: Nivo plus ipi vs nivo or CTx in MSI-H/dMMR mCRC #ESMO26 #ESMOAmbassadors 👉ORR 72% 58% 👉mOS: NR --> NI vs N HR 0.66 👉5-yr for Nivo/Ipi: 77% 🧐Convincing, Nivo + Ipi as SOC in 1L MSI CRC @myESMO @ASCO https://t.co/ni6wO1FZAW

988 views 19 likes19 RT 2026-10-24
Paolo Ciracì
Paolo Ciracì@p_ciracimd
𝕏

Final overall survival results from the CheckMate 8HW in MSI-H/dMMRmCRC #ESMO26 @OncoAlert https://t.co/Bl7IAeSxpH

366 views 10 likes7 RT 2026-10-24
Dr Rishabh Jain
Dr Rishabh Jain@DrRishabhOnco
𝕏

🚨 CheckMate 8HW | #ESMO26 Dual immunotherapy delivers an OS win in MSI-H/dMMR metastatic CRC! NIVO + IPI vs NIVO (all lines): ✅ 5-year OS: 74% vs 62% ✅ OS HR 0.61 (P=0.0009) ✅ ORR: 72% vs 58% 🔥 First significant OS benefit of dual IO over single-agent IO in this setting. @ESMO_open @my_esmo @ASCO @oncoalert

174 views 1 likes1 RT 2026-10-24
Alan Tan
Alan Tan@alantanmd
𝕏

CheckMate 8HW final OS at #ESMO26: NIVO+IPI in centrally confirmed MSI-H/dMMR mCRC ▪️ All lines vs NIVO: HR 0.61 (0.46–0.82), p=0.0009; 5-yr OS 74% vs 62% ▪️ 1L vs NIVO: HR 0.66 (0.44–0.99), p=0.043, missed prespecified boundary (p<0.0058); 5-yr OS 77% vs 66% ▪️ 1L vs chemo: OS HR 0.37, p<0.0001 ▪️ Median f/u ~68 mo; safety stable, low grade 3/4 #CRCSM #MSIH

129 views 0 likes0 RT 2026-10-24
Arndt Vogel
Arndt Vogel@ArndtVogel

NIVO + IPI vs NIVO for MSI-H/dMMR mCRC: Health-related quality of life analysis
🔎CheckMate 8HW
👉mPFS clearly improved
👉 HRQoL, less symptoms
🧐 Supports use of Nivo IPI as 1st line treatment in MSI…

👁 3.1K ♡ 54 ↻ 25 Jul 3, 2025
Toni Choueiri, MD
Toni Choueiri, MD@DrChoueiri

JUST IN: The @US_FDA approves nivolumab with ipilimumab for unresectable or metastatic MSI-H or dMMR colorectal cancer!

News reported by @ASCO #FDAalerts https://t.co/SZySs7FXSp

👁 5.8K ♡ 91 ↻ 33 Apr 8, 2025
Oncology Brothers
Oncology Brothers@OncBrothers

Ipi/Nivo now @FDAOncology approved based off #Checkmate8HW: Ph 3, dMMR/MSI-H mCRC, Ipi (1mg/kg) + Nivo (240mg) Q3W for 4 cycles and then Nivo alone vs Nivo:

- mPFS NR for Ipi/Nivo vs 39·3 months
-…

👁 5.5K ♡ 73 ↻ 27 Apr 8, 2025
Yüksel Ürün
Yüksel Ürün@DrYukselUrun

✅Dual Immunotherapy Gets the Green Light
FDA fully approved nivolumab + ipilimumab for MSI-H/dMMR metastatic colorectal cancer — in adults and teens ≥12.
@US_FDA @OncoAlert @OncBrothers …

👁 3.6K ♡ 36 ↻ 7 Apr 8, 2025
Arndt Vogel
Arndt Vogel@ArndtVogel

🔥FDA approves nivolumab with ipilimumab for unresectable or metastatic MSI-H or dMMR colorectal cancer🔥
👉based on impressive efficacy in CHECKMATE-8HW
@myESMO https://t.co/8CbFUxwa9q

👁 3K ♡ 69 ↻ 21 Apr 8, 2025
Yakup Ergün
Yakup Ergün@dr_yakupergun

The New Standard of Care in MSI-H CRC: Nivolumab + Ipilimumab

The CM-8HW trial has provided us with some important insights:

1. Discrepancy between local and central MSI testing: In the CM-8HW…

👁 15.4K ♡ 120 ↻ 41 Jan 26, 2025
Dr Amol Akhade
Dr Amol Akhade@SuyogCancer

Another trial data with WIDE gap between PFS and PFS 2 curves .
Checkmate 8HW

And
Role of IO ( double vs Single IO ) in MSI high colon cancer, both metastatic and localized.
@asco #asco24…

👁 5.6K ♡ 43 ↻ 15 Jun 2, 2024

CheckMate-8HW Key Takeaways

Progression-Free Survival (PFS) — Primary Endpoint (NIVO+IPI vs. Chemo, 1L)

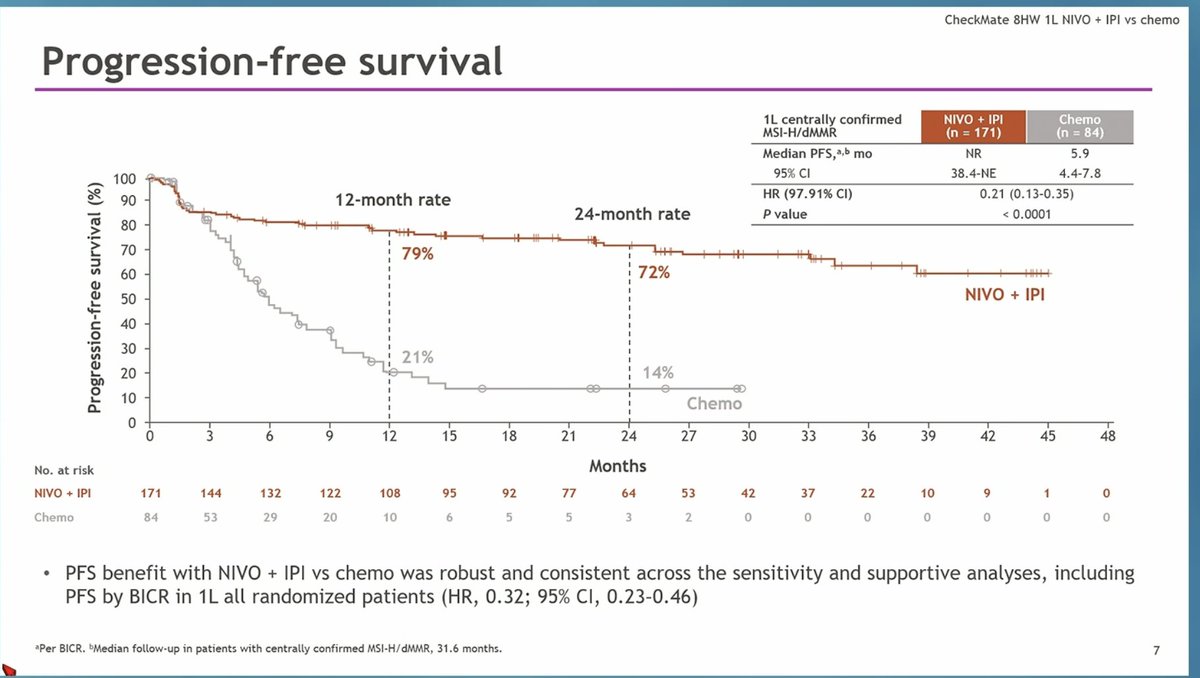
Median: not reached (NIVO + IPI, 95% CI 38.4-NE) vs. 5.8 months (chemotherapy, 95% CI 4.4-7.8). HR 0.21 (95% CI 0.14-0.32), P<0.0001 Median PFS not reached (95% CI: 38.4 to NE) with NIVO+IPI vs. 5.8 months (95% CI: 4.4-7.8) with chemotherapy — a 79% reduction in risk of progression or death (ASCO GI 2024/2025). Analysis conducted in 255 patients with centrally confirmed MSI-H/dMMR status (of 303 based on local testing). These are primary PFS analysis figures; at extended follow-up (data cutoff May 28, 2026; ESMO 2026, descriptive) the 1L PFS HR versus chemotherapy was 0.21 (95% CI 0.14-0.32).

✓ PFS HR 0.21 (95% CI 0.14-0.32)

📄 Source: KOL commentary on X →

Overall Survival (OS) — Key Secondary Endpoint, Final Analysis

Final OS analysis (initiated at 3 years of minimum follow-up; data cutoff May 28, 2026; median follow-up 68.1 months across all lines and 62.8 months in the centrally confirmed 1L population) in patients with centrally confirmed MSI-H/dMMR mCRC, presented at ESMO 2026: NIVO+IPI vs NIVO, all lines (n=296 vs 286): 78 (26%) vs 111 (39%) events; medians not reached; HR 0.61 (95% CI 0.46-0.82); P=0.0009 (boundary for significance 0.0058) — statistically significant; 5-year OS 74% vs 62%; consistent with the all-randomized locally tested population (HR 0.64, 95% CI 0.51-0.81). NIVO+IPI vs chemotherapy, 1L (n=171 vs 84): 39 (23%) vs 41 (49%) events; median not reached vs 50.1 months (95% CI 31.7-NE); HR 0.37 (95% CI 0.24-0.57); P<0.0001 (boundary 0.0059) — statistically significant; 5-year OS 77% vs 46%; 79.8% (67/84) of chemo-treated patients received subsequent immunotherapy. NIVO+IPI vs NIVO, 1L (n=171 vs 170): HR 0.66 (95% CI 0.44-0.99); P=0.0432 — the prespecified threshold for statistical significance (P<0.0058) was not met; 5-year OS 77% vs 66%. Earlier cut: the ESMO 2025 descriptive analysis (Sara Lonardi) reported NIVO+IPI vs NIVO across all lines HR 0.61 (95% CI 0.45-0.83) with OS still immature. FDA approval (April 2025) was based on PFS; OS data were not available at the time of the interim PFS analysis per the FDA approval document.

Final OS: HR 0.37 vs chemo (1L) · HR 0.61 vs NIVO (all lines)

📄 Source: ESMO 2026 final OS slides (all lines, design, summary) → · ESMO 2026 1L OS slides →

Safety & Tolerability

Grade ≥3 adverse events: 22.0% (nivo_ipi) vs. 14.0% (nivo_mono). Higher Grade ≥3 TRAE rate with NIVO+IPI than NIVO monotherapy but well-managed and consistent with established checkpoint inhibitor combinations. No new safety signals identified. (ASCO GI / ESMO)

Manageable — consistent with NIVO+IPI class profile

📄 Source →

Regulatory status & clinical implications — FDA APPROVED — NIVO+IPI for MSI-H/dMMR unresectable/metastatic CRC; CheckMate-8HW supported the April 2025 first-line approval; not indicated for MSS disease. (FDA.gov) New 1L SOC for MSI-H/dMMR mCRC: CheckMate-8HW establishes NIVO+IPI as a 1L standard for MSI-H/dMMR mCRC, building on KEYNOTE-177 (pembrolizumab monotherapy) benchmark. Superior PFS vs. both chemotherapy and NIVO alone. Choice between NIVO+IPI and pembrolizumab monotherapy in MSI-H mCRC balances efficacy depth vs. IR AE burden.

Sponsor / Drug — Bristol Myers Squibb with Ono Pharmaceutical; nivolumab (Opdivo, anti-PD-1) + ipilimumab (Yervoy, anti-CTLA-4). (FDA label)

Compiled and reviewed by the KOL Pulse research team, led by Brian Shields, Founder, KOL Pulse. Last updated October 24, 2026.

Top KOLs Discussing CheckMate-8HW

Arndt Vogel
Arndt Vogel
@ArndtVogel
37.2K impressions
Yakup Ergün
Yakup Ergün
@dr_yakupergun
16.4K impressions
Oncology Brothers
Oncology Brothers
@OncBrothers
13.6K impressions
Dr Amol Akhade
Dr Amol Akhade
@SuyogCancer
11.1K impressions
Toni Choueiri, MD
Toni Choueiri, MD
@DrChoueiri
5.8K impressions
Sharlene Gill, MD, MPH, MBA, FASCO
@GillSharlene
4.6K impressions

CheckMate-8HW Key Slides & Visuals

Official trial slides and relevant visuals shared by KOLs at ASCO GI 2024 / 2025 / ESMO 2025. Click any image to expand.

Presented at ESMO 2026 (October 24, 2026)

Arndt Vogel
Arndt Vogel @ArndtVogel
CheckMate 8HW · ESMO 2026 · Oct 24, 2026
Final overall survival analysis · Data cutoff May 28, 2026
View on X ↗
[Slide 1] CheckMate 8HW Study design: CheckMate 8HW • CheckMate 8HW is a randomized, multicenter, open-label phase 3 trial^a Key eligibility criteria: • Histologically confirmed unresectable or metastatic CRC • MSI-H/dMMR status by local testing • Immunotherapy-naïve • ECOG PS 0 or 1 Stratification factors: • Prior lines of treatment (0 vs 1 vs ≥ 2) • Primary tumor location (right vs left) R 2:2:1 n = 353: NIVO 240 mg Q2W for 6 doses, followed by NIVO 480 mg Q4W^b n = 354: NIVO 240 mg + IPI 1 mg/kg Q3W for 4 doses,^c followed by NIVO 480 mg Q4W^b n = 132: Investigator's choice of chemo^d (mFOLFOX6 and FOLFIRI ± bevacizumab or cetuximab) Treatment until disease progression, unacceptable toxicity, withdrawal of consent (all arms), or a maximum treatment duration of 2 years (NIVO and NIVO + IPI arms only) Dual primary endpoints in patients with centrally confirmed MSI-H/dMMR status^e: • PFS by BICR^f (NIVO + IPI vs chemo in 1L) • PFS by BICR^f (NIVO + IPI vs NIVO across all lines) Key secondary endpoints in patients with centrally confirmed MSI-H/dMMR status^e: • PFS by BICR^f (NIVO + IPI vs NIVO in 1L) • ORR • OS Other key endpoints in all treated patients • Safety • At data cutoff (May 28, 2026), median follow-up^g for all randomized patients was 68.1 (range, 37.6–81.4) months across all lines and 63.0 (range, 37.6–80.2) months in the 1L population • The final OS analysis was initiated based on achieving 3 years of minimum follow-up ^aClinicalTrials.gov. NCT04008030. ^bPatients with ≥ 2 prior lines are randomized only to the NIVO or NIVO + IPI arms. ^cPatients can continue NIVO treatment upon early IPI discontinuation. ^dPatients receiving investigator's choice of chemo are eligible to receive NIVO + IPI upon progression (crossover treatment). ^eConfirmed using either immunohistochemistry and/or polymerase chain reaction-based tests. ^fEvaluated using RECIST v1.1. ^gTime between randomization and data cutoff across all 3 treatment arms. 4 [Slide 2]
Survival data as printed on the slide — OS (centrally confirmed MSI-H/dMMR, all lines)
ArmNEvents (%)Median OS, mo (95% CI)12 mo OS24 mo OS36 mo OS48 mo OS60 mo OS
NIVO + IPI29678 (26)NR (NE-NE)90%85%81%77%74%
NIVO286111 (39)NR (NE-NE)83%72%69%65%62%
HR (95% CI): 0.61 (0.46-0.82); P = 0.0009
Landmark rates are the percentages printed on the curve; numbers-at-risk rows omitted. Data cutoff May 28, 2026 (per study design slide).
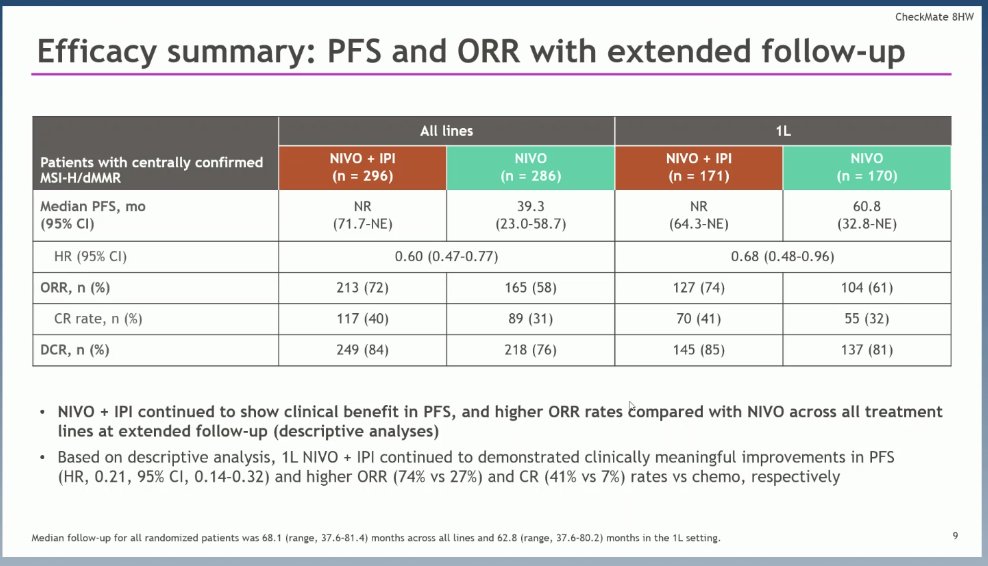
CheckMate 8HW Overall survival: NIVO+IPI vs NIVO across all lines Centrally confirmed MSI-H/dMMR | NIVO + IPI (n = 296) | NIVO (n = 286) Events (%) | 78 (26) | 111 (39) Median OS, mo 95% CI | NR (NE-NE) | NR (NE-NE) HR (95% CI) | 0.61 (0.46-0.82) P value | 0.0009^a • In patients with centrally confirmed MSI-H/dMMR mCRC, NIVO + IPI demonstrated statistically significant OS benefit vs NIVO across all lines (HR, 0.61, 95% CI, 0.46-0.82, P = 0.0009) — These data are consistent with those observed in the all-randomized population by local testing (HR, 0.64, [95% CI, 0.51-0.81]) — OS results were consistent across most prespecified subgroups Median follow-up for all randomized patients with centrally confirmed MSI-H/dMMR mCRC was 68.1 (range, 37.6-81.4) months. ^aStatistical boundary for significance, 0.0058. [Slide 3] CheckMate 8HW Efficacy summary: PFS and ORR with extended follow-up Patients with centrally confirmed MSI-H/dMMR | All lines: NIVO + IPI (n = 296) | All lines: NIVO (n = 286) | 1L: NIVO + IPI (n = 171) | 1L: NIVO (n = 170) Median PFS, mo (95% CI) | NR (71.7-NE) | 39.3 (23.0-58.7) | NR (64.3-NE) | 60.8 (32.8-NE) HR (95% CI) | 0.60 (0.47-0.77) [all lines] | 0.68 (0.48-0.96) [1L] ORR, n (%) | 213 (72) | 165 (58) | 127 (74) | 104 (61) CR rate, n (%) | 117 (40) | 89 (31) | 70 (41) | 55 (32) DCR, n (%) | 249 (84) | 218 (76) | 145 (85) | 137 (81) • NIVO + IPI continued to show clinical benefit in PFS, and higher ORR rates compared with NIVO across all treatment lines at extended follow-up (descriptive analyses) • Based on descriptive analysis, 1L NIVO + IPI continued to demonstrated clinically meaningful improvements in PFS (HR, 0.21, 95% CI, 0.14-0.32) and higher ORR (74% vs 27%) and CR (41% vs 7%) rates vs chemo, respectively Median follow-up for all randomized patients was 68.1 (range, 37.6-81.4) months across all lines and 62.8 (range, 37.6-80.2) months in the 1L setting. 9 [Slide 4] CheckMate 8HW Summary • CheckMate 8HW delivers 2 firsts in MSI-H/dMMR mCRC — The first significant OS benefit for an IO regimen over chemo in 1L (HR, 0.37, P < 0.0001) — The first significant OS benefit for dual IO over monotherapy across all lines (HR, 0.61, P = 0.0009) • The 1L NIVO + IPI vs NIVO comparison shows a durable, clinically meaningful, and consistent OS benefit (HR, 0.66, P=0.0432), with 5-year OS rates (77% vs 66%), despite not satisfying its prespecified survival statistical threshold (P = 0.0058) • With longer follow-up, descriptive analyses showed consistent PFS and ORR benefit with NIVO + IPI across all comparisons and treatment lines • The safety profile of NIVO + IPI remained stable with longer follow-up, with low frequency of grade 3/4 toxicity despite numerically higher incidence of any-grade TRAEs with the combination, confirming tolerability alongside efficacy • These results reinforce the durable, long-term clinical benefit of NIVO + IPI across all efficacy endpoints tested, supporting it as a global 1L standard of care in MSI-H/dMMR mCRC 11
Paolo Ciracì
Paolo Ciracì @p_ciracimd
CheckMate 8HW · ESMO 2026 · Oct 24, 2026
Final overall survival analysis · Data cutoff May 28, 2026
View on X ↗
[Slide 1]
Survival data as printed on the slide — Overall survival, 1L, centrally confirmed MSI-H/dMMR
ArmNEvents (%)Median OS, mo (95% CI)12 mo OS24 mo OS36 mo OS48 mo OS60 mo OS
NIVO + IPI17139 (23)NR (NE-NE)90%85%84%80%77%
Chemo8441 (49)50.1 (31.7-NE)78%66%57%51%46%
HR (95% CI): 0.37 (0.24-0.57); P < 0.0001
Landmark rates are the percentages printed on the curve; numbers-at-risk rows omitted. Data cutoff May 28, 2026 (per study design slide).
CheckMate 8HW Overall survival: NIVO+IPI vs chemo in 1L Centrally confirmed MSI-H/dMMR | NIVO + IPI (n = 171) | Chemo (n = 84) Events (%) | 39 (23) | 41 (49) Median OS, mo (95% CI) | NR (NE-NE) | 50.1 (31.7-NE) HR (95% CI) | 0.37 (0.24-0.57) P value | < 0.0001 - In patients with centrally confirmed MSI-H/dMMR mCRC, NIVO + IPI demonstrated statistically significant OS benefit vs chemo in the 1L (HR, 0.37, 95% CI, 0.24-0.57, P < 0.0001) - Benefit from 1L NIVO + IPI observed despite 79.8% (n=67/84) of patients treated with chemo receiving subsequent IO therapy Median follow-up for all randomized patients with centrally confirmed MSI-H/dMMR mCRC in the 1L setting was 62.8 (range, 37.6-80.2) months. aStatistical boundary for significance, 0.0059. [Slide 2]
Survival data as printed on the slide — Overall survival, 1L, centrally confirmed MSI-H/dMMR
ArmNEvents (%)Median OS, mo (95% CI)12 mo OS24 mo OS36 mo OS48 mo OS60 mo OS
NIVO + IPI17139 (23)NR (NE-NE)90%85%84%80%77%
NIVO170—NR (NE-NE)88%78%73%70%66%
HR (95% CI): 0.66 (0.44-0.99); P = 0.0432
NIVO events cell not reliably legible in the photo; omitted.
Landmark rates are the percentages printed on the curve; numbers-at-risk rows omitted. Data cutoff May 28, 2026 (per study design slide).
CheckMate 8HW Overall survival: NIVO+IPI vs NIVO in 1L Centrally confirmed MSI-H/dMMR | NIVO + IPI (n = 171) | NIVO (n = 170) Median OS, mo (95% CI) | NR (NE-NE) | NR (NE-NE) HR (95% CI) | 0.66 (0.44-0.99) P value | 0.0432a - OS favored NIVO+IPI vs NIVO in 1L (HR, 0.66, 95% CI, 0.44-0.99, P = 0.0432), however, the prespecified threshold for statistical significance (P < 0.0058) was not met - Lack of statistical significance likely reflects the smaller sample size and fewer events relative to the all-lines comparison - The 5-year OS rates (77% vs 66%) were consistent with the results across all lines (74% vs 62%) Median follow-up for all randomized patients with centrally confirmed MSI-H/dMMR mCRC in the 1L setting was 62.8 (range, 37.6-80.2) months. aStatistical boundary for significance, 0.0058.

ESMO 2026 slides

Slides from ESMO 2026 (Madrid) as photographed and shared on X by physicians, newest first. Each post is shown verbatim; click any slide to enlarge, and open the OCR text under each post. All ESMO 2026 CheckMate 8HW slides in the KOL Pulse slide library →

Nicholas Hornstein (@GIMedOnc)
Nicholas Hornstein @GIMedOnc
CheckMate 8HW · ESMO 2026 slides
Oct 25, 2026 · ESMO 2026
View on X ↗
For the final act of CheckMate 8HW, we finally have the significant OS data the doubters have been asking for. What happens when you have a great treatment and an even better one for a study (and almost everyone crosses over)? You have to wait a really, really long time for OS. Also, some thoughts on splitting the alpha I won’t get into here. Nivo/ipi vs nivo alone vs chemo, MSI-H/dMMR mCRC. Final OS analysis. Response rate 72% with nivo/ipi, 58% with nivo alone. 
Median OS still not reached. 
OS HR 0.66 for nivo/ipi over nivo, statistically significant. 
77% of nivo/ipi patients alive at 5 years. Three out of four patients alive at five years. In metastatic colorectal cancer. 🤯 Not even going to talk about the chemo arm. It's clearly worse, and there is never a time to give chemo in MSI-H unless someone has extreme, active autoimmune disease. “Debulking” is absolute nonsense. Bottom line: the doubters got their OS. Nivo/ipi is the first-line standard for MSI-H mCRC. Next steps: how do we decide length of therapy, and how do we manage oligometastatic progression? #ESMO26
@OncoAlert @TheGutOncLab @OncoAlert
14:45 - 16:15 Rapid oral: Gastrointestinal tumours, lower digestive CHAIRS: LISA SALVATORE, KAI-KEEN SHIU, RONA YAEGER CheckMate 8HW Overall survival: NIVO+IPI vs NIVO across all lines Centrally confirmed MSI-H/dMMR | NIVO + IPI (n = 296) | NIVO (n = 286) Events (%) | 78 (26) | 111 (39) Median OS, mo 95% CI | NR (NE-NE) | NR (NE-NE) HR (95% CI) | 0.61 (0.46-0.82) P value | 0.0009a Landmarks (NIVO+IPI / NIVO): 12 mo 90% / 83%; 24 mo 85% / 72%; 36 mo 81% / 69%; 48 mo 77% / 65%; 60 mo 74% / 62% No. at risk (months 0, 3, 6 ... 81) NIVO+IPI 296 279 273 267 264 260 257 255 251 247 245 239 238 226 216 209 199 186 176 166 151 141 114 78 62 31 3 0 NIVO 286 275 263 252 238 228 220 213 207 202 201 199 195 185 176 170 163 151 141 134 122 115 94 57 49 17 3 0 • In patients with centrally confirmed MSI-H/dMMR mCRC, NIVO + IPI demonstrated statistically significant OS benefit vs NIVO across all lines (HR, 0.61, 95% CI, 0.46-0.82, P = 0.0009) – These data are consistent with those observed in the all-randomized population by local testing (HR, 0.64, [95% CI, 0.51-0.81]) – OS results were consistent across most prespecified subgroups Median follow-up for all randomized patients with centrally confirmed MSI-H/dMMR mCRC was 68.1 (range, 37.6-81.4) months. aStatistical boundary for significance, 0.0058. Sara Lonardi Final overall survival results from CheckMate 8HW: Nivolumab plus ipilimumab versus nivolumab or chemotherapy in MSI-H/dMMR metastatic colorectal cancer ALICANTE AUDITORIUM - HALL 6 Survival table Endpoint: OS (centrally confirmed MSI-H/dMMR, NIVO+IPI vs NIVO, all lines) NIVO + IPI | 296 | NR | NE-NE NIVO | 286 | NR | NE-NE HR: 0.61 HR CI: 0.46-0.82 P: 0.0009 Landmark 12 mo | NIVO + IPI | 90% Landmark 12 mo | NIVO | 83% Landmark 24 mo | NIVO + IPI | 85% Landmark 24 mo | NIVO | 72% Landmark 36 mo | NIVO + IPI | 81% Landmark 36 mo | NIVO | 69% Landmark 48 mo | NIVO + IPI | 77% Landmark 48 mo | NIVO | 65% Landmark 60 mo | NIVO + IPI | 74% Landmark 60 mo | NIVO | 62%

More slides on this page

Arndt Vogel
Arndt Vogel @ArndtVogel
CheckMate-8HW Data
18.1K impressions · 128 likes · Jun 2, 2024
View on X ↗
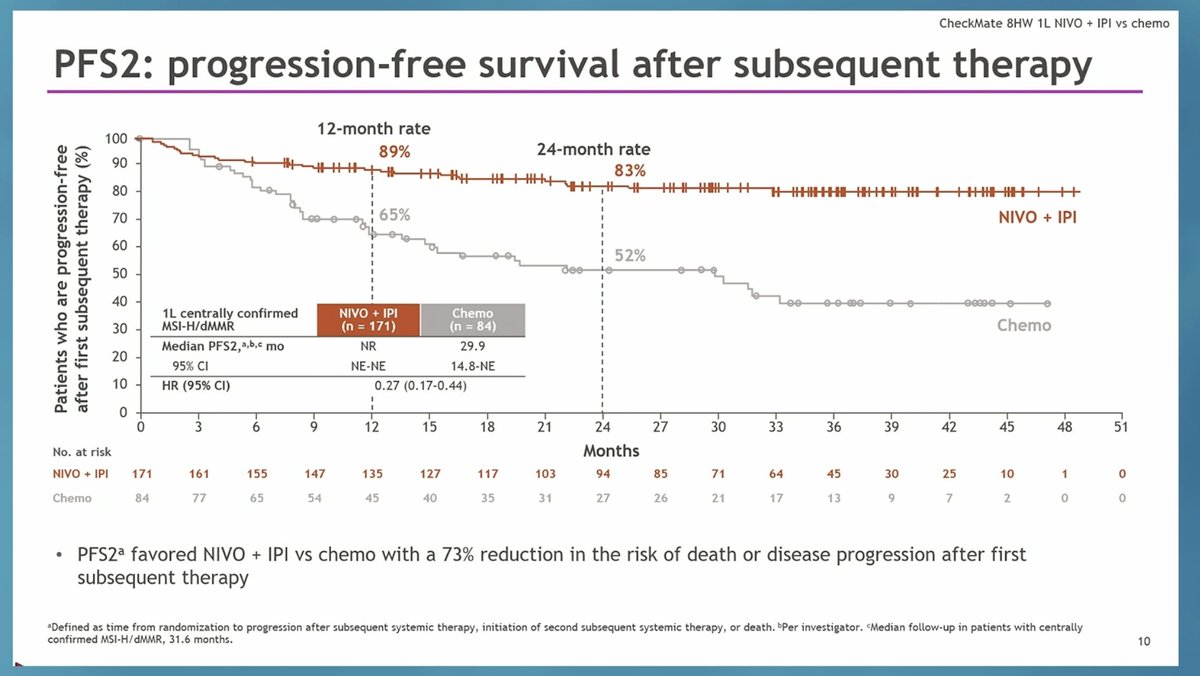
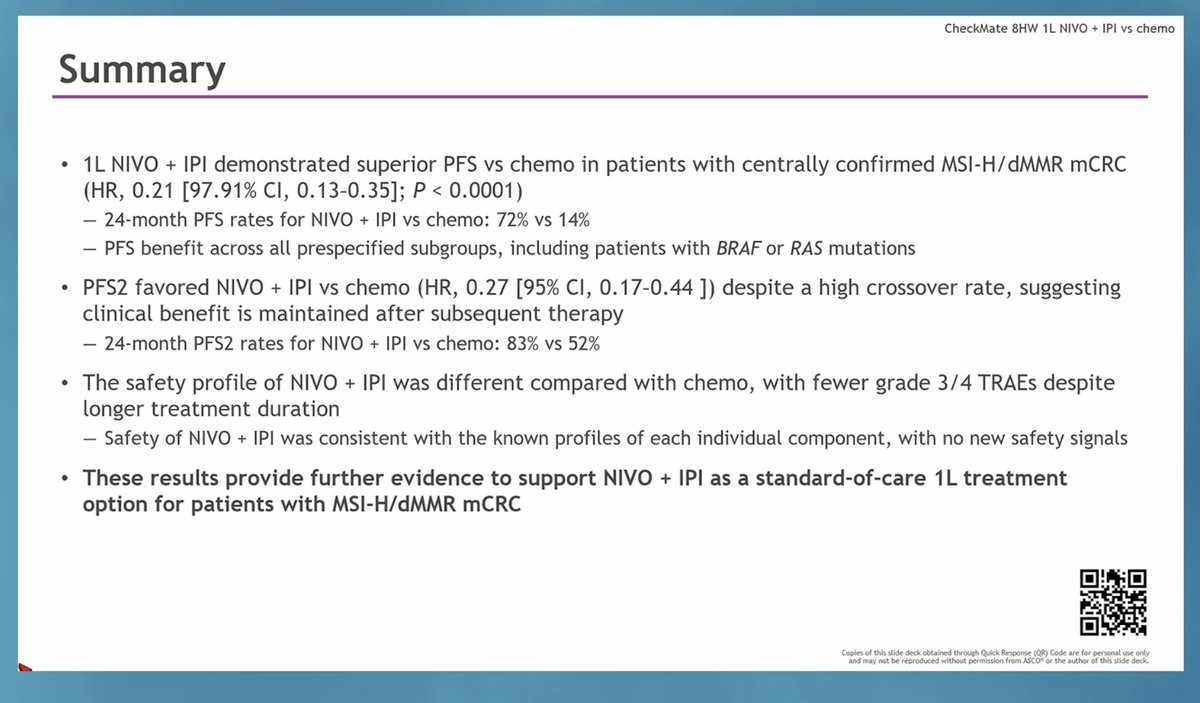
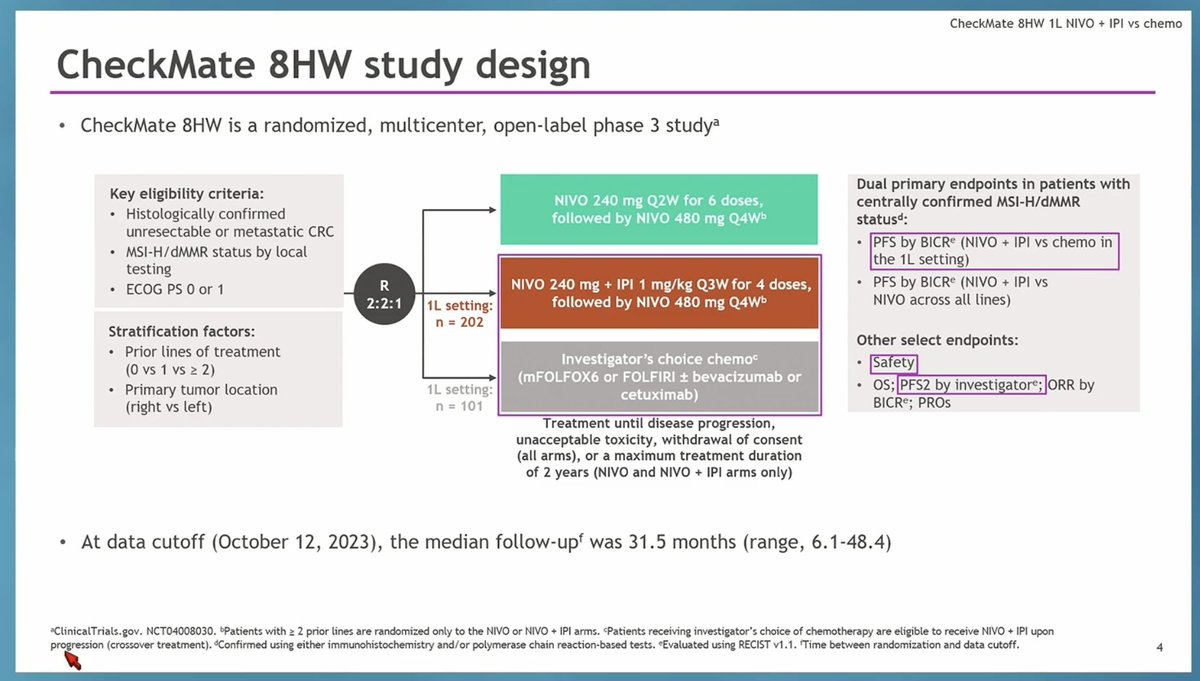
[Slide 1] CheckMate 8HW 1L NIVO + IPI vs chemo Summary 1L NIVO + IPI demonstrated superior PFS vs chemo in patients with centrally confirmed MSI-H/dMMR mCRC (HR, 0.21 [97.91% CI, 0.13-0.35]; P < 0.0001) - 24-month PFS rates for NIVO + IPI vs chemo: 72% vs 14% - PFS benefit across all prespecified subgroups, including patients with BRAF or RAS mutations PFS2 favored NIVO + IPI vs chemo (HR, 0.27 [95% CI, 0.17-0.44 ]) despite a high crossover rate, suggesting clinical benefit is maintained after subsequent therapy - 24-month PFS2 rates for NIVO + IPI vs chemo: 83% vs 52% The safety profile of NIVO + IPI was different compared with chemo, with fewer grade 3/4 TRAEs despite longer treatment duration - Safety of NIVO + IPI was consistent with the known profiles of each individual component, with no new safety signals These results provide further evidence to support NIVO + IPI as a standard-of-care 1L treatment option for patients with MSI-H/dMMR mCRC Copies of this slide deck obtained through Quick Response for personal and may not be reproduced without from ASCO this slide --- [Slide 2] CheckMate 8HW 1L NIVO + IPI vs chemo PFS2: progression-free survival after subsequent therapy 12-month rate 100 89% 24-month rate 90 83% 80 Patients who are progression-free after first subsequent therapy (%) 70 65% NIVO + IPI 60 52% 50 dee 40 1L centrally confirmed NIVO IPI Chemo 30 MSI-H/dMMR (n 171) (n 84) Chemo Median PFS2, a,b,c mo NR 29.9 20 95% CI NE-NE 14.8-NE 10 HR (95% CI) 0.27 (0.17-0.44) 0 0 3 6 9 12 15 18 21 24 27 30 33 36 39 42 45 48 51 No. at risk Months NIVO IPI 171 161 155 147 135 127 117 103 94 85 71 64 45 30 25 10 1 0 Chemo 84 77 65 54 45 40 35 31 27 26 21 17 13 9 7 2 0 0 PFS2ᵃ favored NIVO + IPI vs chemo with a 73% reduction in the risk of death or disease progression after first subsequent therapy "Defined as time from randomization to progression after subsequent systemic therapy, initiation of second subsequent systemic therapy, or death. Per investigator. Median follow-up in patients with centrally confirmed MSI-H/dMMR, 31.6 months. 10 --- [Slide 3] CheckMate 8HW 1L NIVO + IPI vs chemo Progression-free survival 1L centrally confirmed NIVO IPI Chemo MSI-H/dMMR (n 171) (n 84) Median PFS,ᵃ,ᵇ mo NR 5.9 100 95% CI 38.4-NE 4.4-7.8 90 12-month rate HR (97.91% CI) 0.21 (0.13-0.35) 24-month rate P value < 0.0001 80 Progression-free survival (%) 70 79% 60 72% 50 NIVO + IPI 40 30 21% 20 14% 60 10 Chemo 0 0 3 6 9 12 15 18 21 24 27 30 33 36 39 42 45 48 No. at risk Months NIVO IPI 171 144 132 122 108 95 92 77 64 53 42 37 22 10 9 1 0 Chemo 84 53 29 20 10 6 5 5 3 2 0 0 0 0 0 0 0 PFS benefit with NIVO + IPI vs chemo was robust and consistent across the sensitivity and supportive analyses, including PFS by BICR in 1L all randomized patients (HR, 0.32; 95% CI, 0.23-0.46) "Per BICR. Median follow-up in patients with centrally confirmed MSI-H/dMMR, 31.6 months. 7 --- [Slide 4] CheckMate 8HW 1L NIVO + IPI VS chemo CheckMate 8HW study design CheckMate 8HW is a randomized, multicenter, open-label phase 3 studyᵃ Dual primary endpoints in patients with Key eligibility criteria: NIVO 240 mg Q2W for 6 doses, centrally confirmed MSI-H/dMMR Histologically confirmed followed by NIVO 480 mg Q4Wb status: unresectable or metastatic CRC PFS by BICR (NIVO + IPI vs chemo in MSI-H/dMMR status by local the 1L setting) testing ECOG PS 0 or 1 R NIVO 240 mg + IPI 1 mg/kg Q3W for 4 doses, PFS by BICR (NIVO + IPI VS 2:2:1 1L setting: followed by NIVO 480 mg Q4Wb NIVO across all lines) n 202 Stratification factors: Other select endpoints: Prior lines of treatment Investigator's choice chemoc (0 VS 1 vs > 2) Safety (mFOLFOX6 or FOLFIRI + bevacizumab or Primary tumor location 1L setting: OS; PFS2 by investigatore; ORR by cetuximab) (right vs left) n = 101 BICRe; PROs Treatment until disease progression, unacceptable toxicity, withdrawal of consent (all arms), or a maximum treatment duration of 2 years (NIVO and NIVO + IPI arms only) At data cutoff (October 12, 2023), the median follow-up was 31.5 months (range, 6.1-48.4) ClinicalTrials.gov. NCT04008030. Patients with 2 2 prior lines are randomized only to the NIVO or NIVO IPI arms. Patients receiving investigator's choice of chemotherapy are eligible to receive NIVO IPI upon progression (crossover treatment). "Confirmed using either immunohistochemistry and/or polymerase chain reaction-based tests. "Evaluated using RECIST v1.1. Time between randomization and data cutoff. 4
Yakup Ergün
Yakup Ergün @dr_yakupergun
CheckMate-8HW Data
15.4K impressions · 120 likes · Jan 26, 2025
View on X ↗
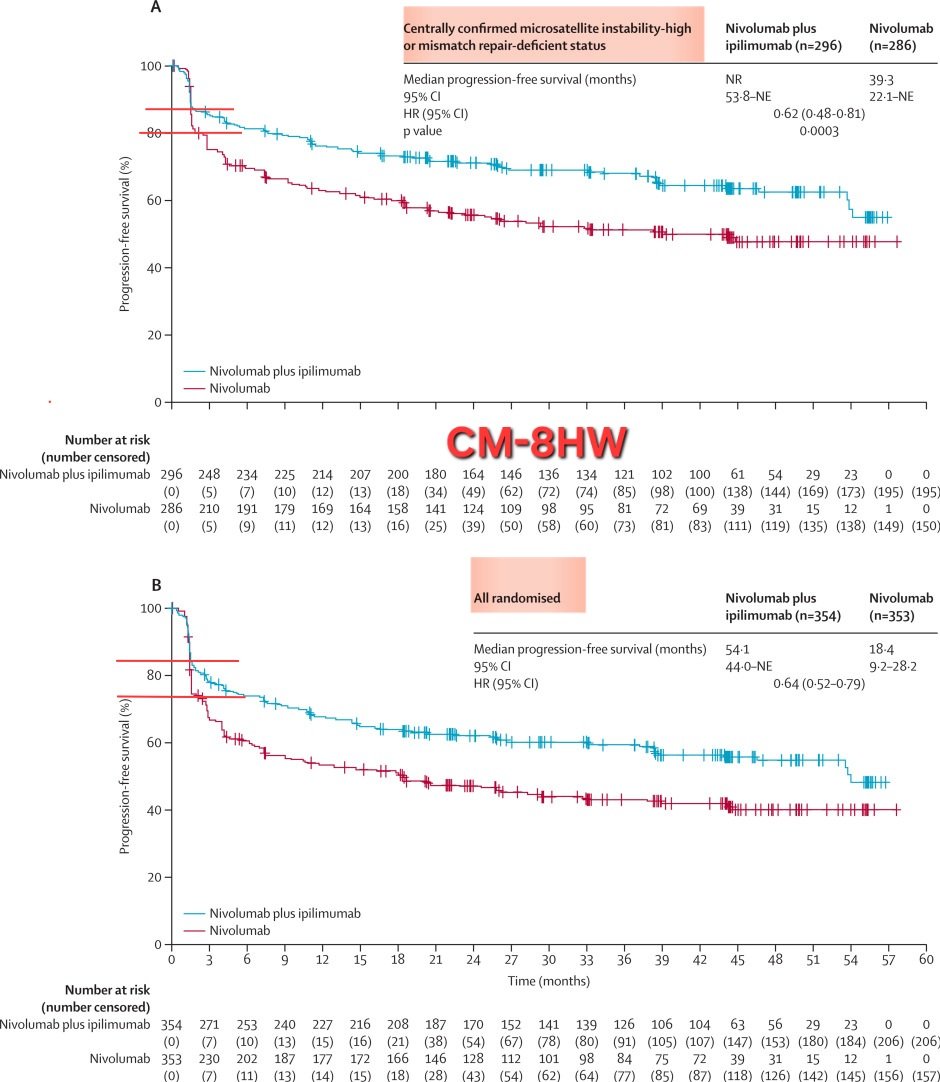
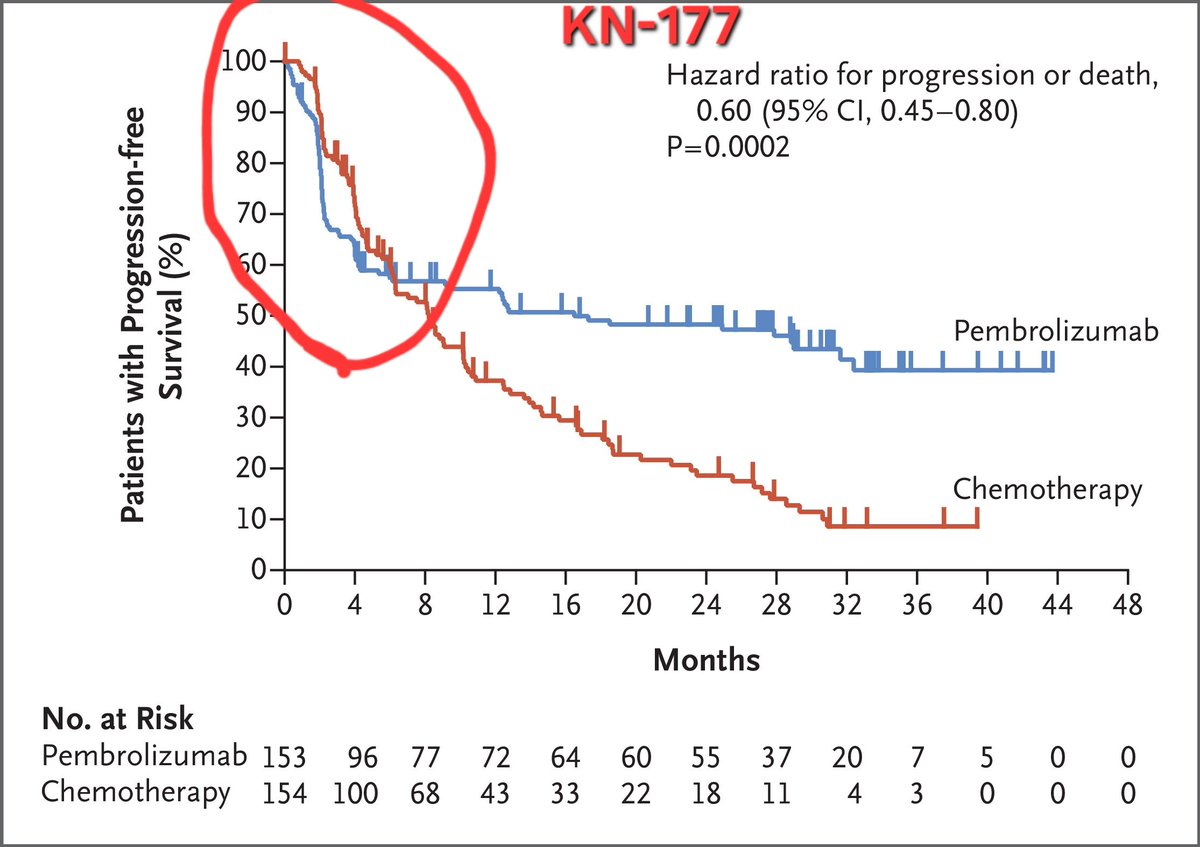
[Slide 1] A Centrally confirmed microsatellite instability-high Nivolumab plus Nivolumab or mismatch repair-deficient status ipilimumab (n=296) (n=286) 100 Median progression-free survival (months) NR 39-3 95% CI 53-8-NE 22-1-NE HR (95% CI) 0-62 (0-48-0-81) 80 P value 0.0003 Progression-free survival (%) 60 40 20 Nivolumab plus ipilimumab Nivolumab 0 Number at risk CM-8HW (number censored) Nivolumab plus ipilimumab 296 248 234 225 214 207 200 180 164 146 136 134 121 102 100 61 54 29 23 0 0 (0) (5) (7) (10) (12) (13) (18) (34) (49) (62) (72) (74) (85) (98) (100) (138) (144) (169) (173) (195) (195) Nivolumab 286 210 191 179 169 164 158 141 124 109 98 95 81 72 69 39 31 15 12 1 0 (0) (5) (9) (11) (12) (13) (16) (25) (39) (50) (58) (60) (73) (81) (83) (111) (119) (135) (138) (149) (150) B All randomised Nivolumab plus Nivolumab 100 ipilimumab (n=354) (n=353) Median progression-free survival (months) 54.1 18-4 95% CI 44-0-NE 9.2-28-2 80 HR (95% CI) 0.64 (0-52-0-79) Progression-free survival (%) 60 40 20 Nivolumab plus ipilimumab Nivolumab 0 0 3 6 9 12 15 18 21 24 27 30 33 36 39 42 45 48 51 54 57 60 Time (months) Number at risk (number censored) Nivolumab plus ipilimumab 354 271 253 240 227 216 208 187 170 152 141 139 126 106 104 63 56 29 23 0 0 (0) (7) (10) (13) (15) (16) (21) (38) (54) (67) (78) (80) (91) (105) (107) (147) (153) (180) (184) (206) (206 Nivolumab 353 230 202 187 177 172 166 146 128 112 101 98 84 75 72 39 31 15 12 1 0 (0) (7) (11) (13) (14) (15) (18) (28) (43) (54) (62) (64) (77) (85) (87) (118) (126) (142) (145) (156) (157) --- [Slide 2] KN-177 100 Hazard ratio for progression or death, 90 0.60 (95% CI, 0.45-0.80) P=0.0002 80 Patients with Progression-free 70 Survival (%) 60 50 Pembrolizumab 40 30 20 Chemotherapy 10 0 0 4 8 12 16 20 24 28 32 36 40 44 48 Months No. at Risk Pembrolizumab 153 96 77 72 64 60 55 37 20 7 5 0 0 Chemotherapy 154 100 68 43 33 22 18 11 4 3 0 0 0
Arndt Vogel
Arndt Vogel @ArndtVogel
CheckMate-8HW Data
11.9K impressions · 139 likes · Jan 25, 2025
View on X ↗
[Slide 1] Nivolumab plus ipilimumab versus nivolumab in W CrossMark microsatellite instability-high metastatic colorectal cancer (CheckMate 8HW): a randomised, open-label, phase 3 trial Thierry André, Elena Elez, Heinz-Josef Lenz, Lars Henrik Jensen, Yann Touchefeu, Eric Van Cutsem, Rocio Garcia-Carbonero, David Tougeron, Guillermo Ariel Mendez, Michael Schenker, Christelle de la Fouchardiere, Maria Luisa Limon, Takayuki Yoshino, Jin Li, Jose Luis Manzano Mozo, Laetitia Dahan, Giampaolo Tortora, Myriam Chalabi, Eray Goekkurt, Maria Ignez Braghiroli, Rohit Joshi, Timucin Cil, Francine Aubin, Elvis Cela, Tian Chen, Ming Lei, Lixian Jin, Steven Blum, Sara Lonardi A Centrally confirmed microsatellite instability-high Nivolumab plus Nivolumab or mismatch repair-deficient status ipilimumab (n=296) (n=286) 100 Median progression-free survival (months) NR 39-3 95% CI 53-8-NE 22-1-NE HR (95% CI) 0-62 (0-48-0-81) 80 P value 0.0003 Progression-free survival (%) 60 40 20 Nivolumab plus ipilimumab Nivolumab 0 Number at risk (number censored) Nivolumab plus ipilimumab 296 248 234 225 214 207 200 180 164 146 136 134 121 102 100 61 54 29 23 0 0 (0) (5) (7) (10) (12) (13) (18) (34) (49) (62) (72) (74) (85) (98) (100) (138) (144) (169) (173) (195) (195) Nivolumab 286 210 191 179 169 164 158 141 124 109 98 95 81 72 69 39 31 15 12 1 0 (0) (5) (9) (11) (12) (13) (16) (25) (39) (50) (58) (60) (73) (81) (83) (111) (119) (135) (138) (149) (150) B All randomised Nivolumab plus Nivolumab 100 ipilimumab (n=354) (n=353) Median progression-free survival (months) 54-1 18-4 95% CI 44-0-NE 9-2-28-2 80 HR (95% CI) 0-64 (0-52-0-79) Progression-free survival (%) 60 40 20 Nivolumab plus ipilimumab Nivolumab 0 0 3 6 9 12 15 18 21 24 27 30 33 36 39 42 45 48 51 54 57 60 Time (months) Number at risk (number censored) Nivolumab plus ipilimumab 354 271 253 240 227 216 208 187 170 152 141 139 126 106 104 63 56 29 23 0 0 (0) (7) (10) (13) (15) (16) (21) (38) (54) (67) (78) (80) (91) (105) (107) (147) (153) (180) (184) (206) (206) Nivolumab 353 230 202 187 177 172 166 146 128 112 101 98 84 75 72 39 31 15 12 1 0 (0) (7) (11) (13) (14) (15) (18) (28) (43) (54) (62) (64) (77) (85) (87) (118) (126) (142) (145) (156) (157)
Oncology Brothers
Oncology Brothers @OncBrothers
CheckMate-8HW Data
7.5K impressions · 49 likes · May 26, 2025
View on X ↗
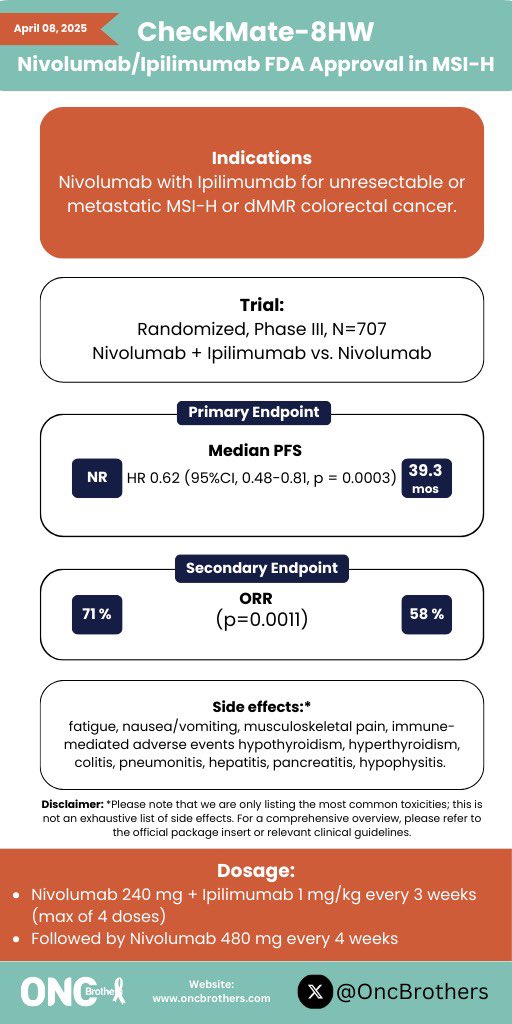
[Slide 1] April 08, 2025 CheckMate-8HW Nivolumab/Ipilimumab FDA Approval in MSI-H Indications Nivolumab with Ipilimumab for unresectable or metastatic MSI-H or dMMR colorectal cancer. Trial: Randomized, Phase III, N=707 Nivolumab + Ipilimumab VS. Nivolumab Primary Endpoint Median PFS NR HR 0.62 (95%CI, 0.48-0.81, p = 0.0003) 39.3 mos Secondary Endpoint ORR 71% (p=0.0011) 58 % Side effects:* fatigue, nausea/vomiting, musculoskeletal pain, immune- mediated adverse events hypothyroidism, hyperthyroidism, colitis, pneumonitis, hepatitis, pancreatitis, hypophysitis. Disclaimer: *Please note that we are only listing the most common toxicities; this is not an exhaustive list of side effects. For a comprehensive overview, please refer to the official package insert or relevant clinical guidelines. Dosage: Nivolumab 240 mg + Ipilimumab 1 mg/kg every 3 weeks (max of 4 doses) Followed by Nivolumab 480 mg every 4 weeks ONC othel Website: www.oncbrothers.com X @OncBrothers
Toni Choueiri, MD
Toni Choueiri, MD @DrChoueiri
CheckMate-8HW Data
5.8K impressions · 91 likes · Apr 8, 2025
View on X ↗
[Slide 1] ASCO FDA Alerts --- [Slide 2] On April 8, 2025, the Food and Drug Administration approved nivolumab (Opdivo, Bristol Myers Squibb Company) with ipilimumab (Yervoy, Bristol Myers Squibb Company) for adult and pediatric patients 12 years of age and older with unresectable or metastatic microsatellite instability-high (MSI-H) or mismatch repair deficient (dMMR) colorectal cancer (CRC). The FDA also converted the accelerated approval to regular approval for single agent nivolumab for adult and pediatric patients 12 years of age and older with MSI-H or dMMR metastatic CRC, that has progressed following fluoropyrimidine, oxaliplatin, and irinotecan. --- [Slide 3] The analysis of nivolumab + ipilimumab versus chemotherapy in the first line setting was conducted in 255 patients with centrally confirmed MSI-H/dMMR status of 303 patients based on local testing. Median PFS was not reached (NR) (95% Cl: 38.4, not estimable [NE]) in the nivolumab + ipilimumab arm and 5.8 months (95% Cl: 4.4, 7.8) in the chemotherapy arm (Hazard ratio 0.21 [95% Cl: 0.14, 0.32] p-value <0.0001). Comparative results of ORR and OS between arms were not available at the time of the interim PFS analysis due to statistical testing strategy.

CheckMate-8HW Trial Design

Design — Phase 3, randomized; nivolumab (Opdivo) + ipilimumab (Yervoy) vs chemotherapy (1L) and vs nivolumab monotherapy, MSI-H/dMMR metastatic colorectal cancer (NCT04008030). (ASCO GI 2024/2025; ESMO 2025)

Results, safety and regulatory status are in At a Glance.

FDA Approval

FDA APPROVED Opdivo + Yervoy — Nivolumab + ipilimumab for adult and pediatric (12+) patients with unresectable or metastatic microsatellite-instability-high (MSI-H) or mismatch-repair-deficient (dMMR) colorectal cancer.

FDA approval date: 2025-04-08.

📄 Source: FDA Press Release →

CheckMate-8HW FAQ

What is the CheckMate-8HW trial?

CheckMate-8HW (NCT04008030) is a Phase 3, randomized trial of nivolumab (Opdivo) plus ipilimumab (Yervoy) versus chemotherapy (first line) and versus nivolumab monotherapy in MSI-H/dMMR metastatic colorectal cancer, sponsored by Bristol Myers Squibb with Ono Pharmaceutical. See Trial Design.

What were the CheckMate-8HW results?

First-line nivolumab plus ipilimumab improved progression-free survival versus chemotherapy (HR 0.21). At the final overall survival analysis (ESMO 2026), it significantly improved OS versus chemotherapy in the first line and versus nivolumab across all lines; the first-line comparison versus nivolumab did not meet its significance threshold. Figures and sources: At a Glance.

Is nivolumab plus ipilimumab FDA approved for MSI-H/dMMR colorectal cancer?

Yes. CheckMate-8HW supported the April 2025 FDA approval of nivolumab plus ipilimumab for MSI-H/dMMR unresectable or metastatic colorectal cancer; it is not indicated for microsatellite-stable disease. See At a Glance.

How does CheckMate-8HW change first-line treatment of MSI-H/dMMR colorectal cancer?

It positions nivolumab plus ipilimumab as a first-line option alongside the pembrolizumab-monotherapy benchmark from KEYNOTE-177, with clinicians weighing depth of response against immune-related toxicity. See At a Glance.

What are the safety considerations with nivolumab plus ipilimumab in CheckMate-8HW?

Grade 3 or higher adverse events were more frequent with the combination than with nivolumab alone, with no new safety signals; immune-related adverse events need standard monitoring. Rates: At a Glance.

CheckMate-8HW in the News

Key KOL Sentiments — CheckMate-8HW

DoctorSentimentComment
Arndt Vogel ● POSITIVE NIVO + IPI vs NIVO for MSI-H/dMMR mCRC: Health-related quality of life analysis 🔎CheckMate 8HW 👉mPFS clearly improved 👉 HRQoL, less symptoms 🧐 Supports use of Nivo IPI as 1st line treatment in MSI CRC #ESMOAmbassadors #ESMOGI25 @myESMO https://t.co/ylVuhVquIp
Pashtoon Kasi MD, MS ● POSITIVE #ASCO25 More followup on IPI/NIVO 🆚 NIVO immunotherapy showing robust durable efficacy translating to “cures” for the patients with colorectal cancer whose tumors are mismatch repair deficient (🔴dMMR/MSI-High). @OncoAlert ❓Hard to tease out ALL-Lines 🆚1st line. Thoughts 💭 https://t.co/9vhwxTouew
Dr Amol Akhade ● POSITIVE CheckMate 8HW ASCO 2025 Update 🧬 🧱 1L MSI-H/dMMR mCRC: 💥 NIVO + IPI vs Chemo 🔹 Median PFS: 54.1 vs 5.9 mo 🔹 HR: 0.21 🔥 🔹 3-yr PFS: 69% vs 11% 📈 Plateauing curve = 🔐 durable control, potential cure 🟢 NIVO + IPI &gt; NIVO alone too HR: 0.62 | 3-yr PFS: 67% vs 51% 🧠 Dual IO https://t.co/xafHEpSiN7
Nicholas Hornstein ● POSITIVE I know it has probably made its way into clinical practice (at least it has for me), but Ipi-Nivo now has FDA approval based on CheckMate8HW for dMMR mCRC! Excited to have this for our patients! Key Points: Ipi (1mg/kg) + Nivo (240mg) Q3W for 4 cycles then Nivo alone Massive https://t.co/NfXXG9u63I
Ryan Huey, MD, MS ● POSITIVE CheckMate-8HW update from Dr. Sara Lonardi: Nivo/Ipi vs Nivo in 1L MSI-H mCRC, PFS NR vs 60.8 months, HR 0.69 (statistical significance not met), curves split early and are consistent. OS HR 0.61, data immature but curves look *awfully* good. #ESMO25 https://t.co/OX90ix7ySl
Nicholas Hornstein ● POSITIVE Had a great time discussing #CM8HW with the @OncBrothers last week. A major step forward for our dMMR CRC patients! https://t.co/6rNDBQukZ1
Arndt Vogel ● POSITIVE Precision Oncology in the First-Line Setting of Colorectal Cancer #ASCO25 👏Excellent discussion by Andrea Sartore-Bianchi 👉BREAKWATER and CHECKMATE 8HW are practice changing @myESMO https://t.co/05QaAEYe6y
Arndt Vogel ● NEUTRAL NIVO/IPI vs CTx in 1st line for MSI-H/dMMR mCRC #ASCO24 🔎CheckMate 8HW, 202 pts 👉PFS: nr vs 5.9mo, HR 0.21 👉Subsequent Tx: 12% vs 68%, in CTx arm: 67% ICI 👉mPFS2: nr vs 29.9, HR 0.27 👉24-mo PFS2: 83 vs 52% 🧐Impressive data -&gt; SOC for MSI CRC @myESMO https://t.co/WLvOqUEoyk
Yakup Ergün ● NEUTRAL The New Standard of Care in MSI-H CRC: Nivolumab + Ipilimumab The CM-8HW trial has provided us with some important insights: 1. Discrepancy between local and central MSI testing: In the CM-8HW study, 14% of patients who were initially classified as MSI-H based on local testing https://t.co/Ld0jY8jkRX
Arndt Vogel ● NEUTRAL Nivolumab/ipilimumab versus nivolumab in MSI mCRC (CheckMate 8HW): a randomised, open-label, phase 3 trial 👇Get the full paper in the @TheLancet https://t.co/BcTvHxv4Bu 👉Convincing activity with acceptable toxicity ❗️Practice-changing @myESMO https://t.co/Rk842Z4M6K
Oncology Brothers ● NEUTRAL One page takeaway from #CheckMate8HW study that resulted in Ipi + Nivo @FDAOncology approval on April 8, 2025 for dMMR/MSI-H metastatic colorectal cancer. More data on MSI-H in adj at #ASCO25! #OncTwitter #MedTwitter #gism @GIMedOnc https://t.co/tklmfZPpip https://t.co/uzvWkKzn1g
Toni Choueiri, MD ● NEUTRAL JUST IN: The @US_FDA approves nivolumab with ipilimumab for unresectable or metastatic MSI-H or dMMR colorectal cancer! News reported by @ASCO #FDAalerts https://t.co/SZySs7FXSp
Dr Amol Akhade ● NEUTRAL Another trial data with WIDE gap between PFS and PFS 2 curves . Checkmate 8HW And Role of IO ( double vs Single IO ) in MSI high colon cancer, both metastatic and localized. @asco #asco24 https://t.co/oZFit0JH6X
Oncology Brothers ● NEUTRAL Ipi/Nivo now @FDAOncology approved based off #Checkmate8HW: Ph 3, dMMR/MSI-H mCRC, Ipi (1mg/kg) + Nivo (240mg) Q3W for 4 cycles and then Nivo alone vs Nivo: - mPFS NR for Ipi/Nivo vs 39·3 months - ORR: 71% vs 58% - Any grade AEs 81% from Ipi/Nivo vs 71% Nivo alone. #OncTwitter https://t.co/FTPUsN39ro
Yüksel Ürün ● NEUTRAL ✅Dual Immunotherapy Gets the Green Light FDA fully approved nivolumab + ipilimumab for MSI-H/dMMR metastatic colorectal cancer — in adults and teens ≥12. @US_FDA @OncoAlert @OncBrothers https://t.co/FHxp9aOb5z https://t.co/hh0cBqQ39s
Arndt Vogel ● NEUTRAL 🔥FDA approves nivolumab with ipilimumab for unresectable or metastatic MSI-H or dMMR colorectal cancer🔥 👉based on impressive efficacy in CHECKMATE-8HW @myESMO https://t.co/8CbFUxwa9q
Sharlene Gill, MD, MPH, MBA, FASCO ● NEUTRAL #GI25 @ASCO #LBA🌟 🚨CM8HW in dMMR #mCRC - the awaited nivo/ipi1 vs nivo PFS 🙌 📌 N=707 across all lines, 55% 1L, centrally confirmed 📌 PFS HR 0.62, p0.0003 👉3 yr PFS 68% v 51% 📌 ORR 71% vs 58% - PD 10% w/ combo 📌 safely reassuring🤙 ➡️nivo/ipi is the new SOC for dMMR… https://t.co/dUtr4r0KYg https://t.co/KLpJoGYkam
Kristen Ciombor ● NEUTRAL Much awaited nivo/ipi vs nivo data from CheckMate 8HW in 1L MSI-H mCRC - nivo/ipi better in PFS and ORR across all lines of therapy with expected increase in toxicity #GI25 Concomitant publication in the Lancet today for more details! https://t.co/xXk0TaEbFC
Dr Amol Akhade ● NEUTRAL Nivo plus IPI gets approval for 1st line Metastatic MSI high CRC. Note that dose of IPI is 1 mg per kg. Also note the comparison table for quick review between key 🔑 finding of Keynote 177 and Checkmate 8HW Trial. Note that combination works better especially in KRas mutated https://t.co/g6PypQJZm9
Nieves Martinez Lago MD PhD ● NEUTRAL 📣FDA approves nivolumab with ipilimumab for unresectable or metastatic MSI-H or dMMR colorectal cancer https://t.co/bFdDWXjeuM https://t.co/D2Y0uD9Fwa
Bristol Myers Squibb ● NEUTRAL #MEDIA: Announcing the late-breaking first disclosure of results from an analysis of our dual immunotherapy combination versus our monotherapy for adult patients with microsatellite instability-high or mismatch repair deficient metastatic #CRC #GI25. https://t.co/6Mug6ZtL6E https://t.co/RfbKxWXJVi
Sharlene Gill, MD, MPH, MBA, FASCO ● NEUTRAL 1/10 – CM8HW #CRCsm @ASCO @NEJM #GI24 dMMR mCRC - nivo + ipi1 📌 n=303 centrally confirmed dMMR mCRC 1L ➡️ 2y PFS 72% nivo + ipi1 vs 14% chemo 🌟, PFS HR 0.21, p&lt;0.00 Per earlier BMS release, combo is superior to nivo arm but awaiting data - in whom? by how much? toxicity diff? https://t.co/0AF23qQ7Cj
Richard Dunne, MD ● NEUTRAL There remains a steep drop off in survival during the first three months for a subset of MSI-H patients receiving immunotherapy. There remains a lane for chemo+IO in this setting. Waiting on you COMMIT trial #GI25 https://t.co/DJtkzLH52s
Dr Amol Akhade ● NEUTRAL 🚨 #ESMO25 LBA29 – CheckMate 8HW 🧩 Nivolumab + Ipilimumab vs Nivolumab alone in MSI-H/dMMR mCRC 🕒 FU 55 mo | n = 341 (1L) 📈 PFS: NR vs 60.8 mo (HR 0.69 [0.48–0.99]; p = 0.0413) 🎯 ORR: 73 % vs 61 % 💀 OS: HR 0.61 (0.45–0.83) ⚠️ Gr 3-4 AEs: 24 % vs 17 % Critical take: – https://t.co/XDGanUzKVe
Erman Akkus ● NEUTRAL @dr_yakupergun @OncBrothers @SuyogCancer @DenizCanGuven1 @brunolarvol @UmutDisel @5_utr @BijoyTelivala @RenoHemonc Thanks for the great comments! For early progression, I have some questions in my mind. 1) Is there a tumor heterogeneity in terms of being MSI-H/dMMR among primary and metastatic sites? 2) Could we measure MSI-H burden via ctDNA?
Jun Gong ● NEUTRAL Dr. Lenz @KeckMedicineUSC updated results of CM-8HW in #MSI-H #mCRC (57-77% #1L) ➡️ #1L nivo/ipi w/superior PFS1 and PFS2 over chemo despite 71% in chemo arm receiving subsequent #IO ?sequence matters. G3/4 AEs associated w/38% CR rate with nivo/ipi #ASCO25 @OncoAlert https://t.co/GPSYE5q0GY
Tanios Bekaii-Saab, MD ● NEUTRAL @OncBrothers @FDAOncology @ARosen380 @pashtoonkasi @DrR_DUNNE @BijoyTelivala @RenoHemonc @dr_yakupergun @realbowtiedoc @MyriamChalabi @CathyEngMD Looking forward to 1L comparative data which has not been publicly disclosed - as such my conclusion remains the same : the doublet represents an additional standard but at this time is not the standard approach to MSIH CRC!
Yakup Ergün ● NEUTRAL @Erman_Akkus @OncBrothers @SuyogCancer @DenizCanGuven1 @brunolarvol @UmutDisel @5_utr @BijoyTelivala @RenoHemonc Valid questions. Studies have shown that MSI concordance is high in liver, lung, and lymph node metastases, but the concordance rate is low in peritoneal metastases. There is also a high concordance between liquid biopsy and tissue biopsy. However, peritoneal metastases may again
Oncology Brothers ● NEUTRAL 1. #CM8HW: PhIII, dMMR/MSI-H unresectable or mCRC, Ipi (1mg/kg) + Nivo Q3W - 4 cycles and then Nivo alone vs Nivo (vs chemo) - At 4yrs, mPFS 65% vs. 55%. Waiting more mature data (HR: 0.69) - At 4yrs, mOS 78% vs. 65%. Waiting more mature data (HR: 0.61) - Adding Ipi (to Nivo) https://t.co/j6wSJaI5Q4 https://t.co/YHE1iXseBE
Arndt Vogel ● NEUTRAL NIVO plus IPI vs CTx or NIVO for MSI-H/dMMR mCRC: #ASCO25 🔎Expanded analyses from CheckMate 8HW 👉ORR N/I vs N71 vs 58% 👉mPFS N/I vs CTx nr vs 30.8 mo 👉mPFS N/I vs N 54 vs 5.9 mo 🧐 Highly effective treatment, acceptable toxicity, supports N/I as SOC @myESMO https://t.co/qHSHAF4WYI
Arndt Vogel ● POSITIVE Final OS results from CheckMate 8HW: Nivo plus ipi vs nivo or CTx in MSI-H/dMMR mCRC #ESMO26 #ESMOAmbassadors 👉ORR 72% 58% 👉mOS: NR --> NI vs N HR 0.66 👉5-yr for Nivo/Ipi: 77% 🧐Convincing, Nivo + Ipi as SOC in 1L MSI CRC @myESMO @ASCO https://t.co/ni6wO1FZAW
Paolo Ciracì ● NEUTRAL Final overall survival results from the CheckMate 8HW in MSI-H/dMMRmCRC #ESMO26 @OncoAlert https://t.co/Bl7IAeSxpH
Dr Rishabh Jain ● POSITIVE 🚨 CheckMate 8HW | #ESMO26 Dual immunotherapy delivers an OS win in MSI-H/dMMR metastatic CRC! NIVO + IPI vs NIVO (all lines): ✅ 5-year OS: 74% vs 62% ✅ OS HR 0.61 (P=0.0009) ✅ ORR: 72% vs 58% 🔥 First significant OS benefit of dual IO over single-agent IO in this setting. @ESMO_open @my_esmo @ASCO @oncoalert
Alan Tan ● NEUTRAL CheckMate 8HW final OS at #ESMO26: NIVO+IPI in centrally confirmed MSI-H/dMMR mCRC ▪️ All lines vs NIVO: HR 0.61 (0.46–0.82), p=0.0009; 5-yr OS 74% vs 62% ▪️ 1L vs NIVO: HR 0.66 (0.44–0.99), p=0.043, missed prespecified boundary (p<0.0058); 5-yr OS 77% vs 66% ▪️ 1L vs chemo: OS HR 0.37, p<0.0001 ▪️ Median f/u ~68 mo; safety stable, low grade 3/4 #CRCSM #MSIH