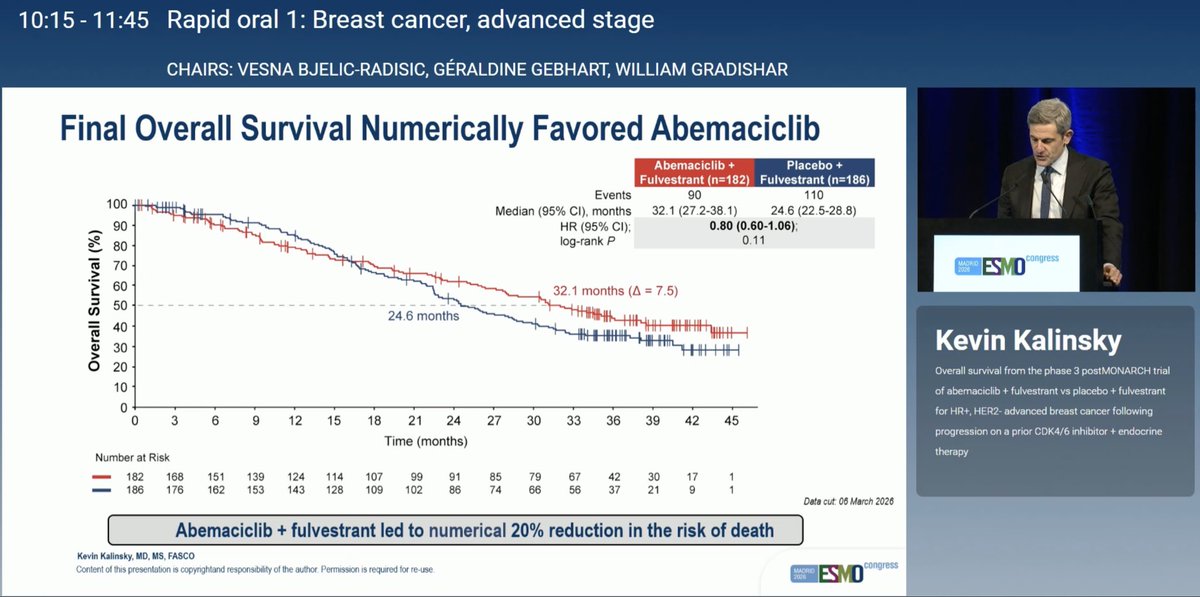
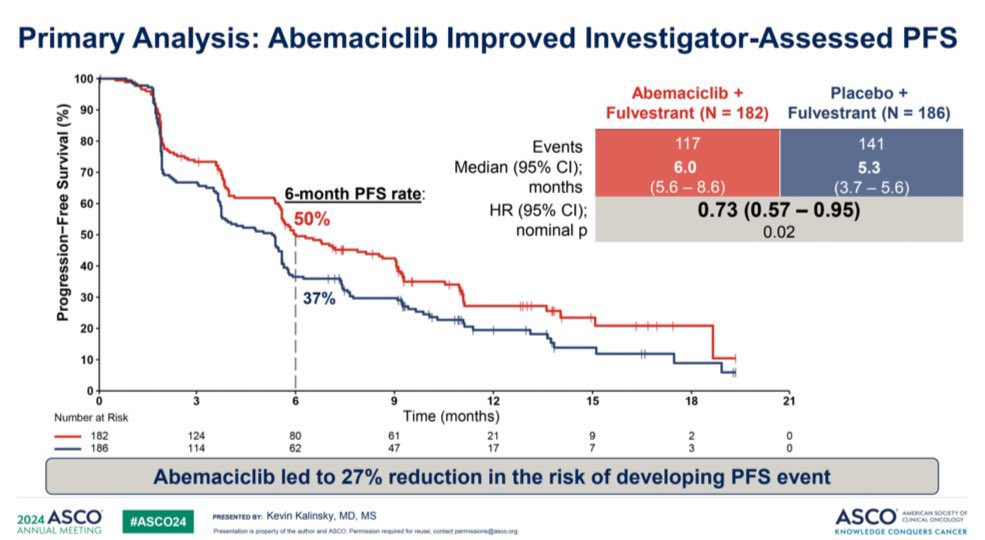
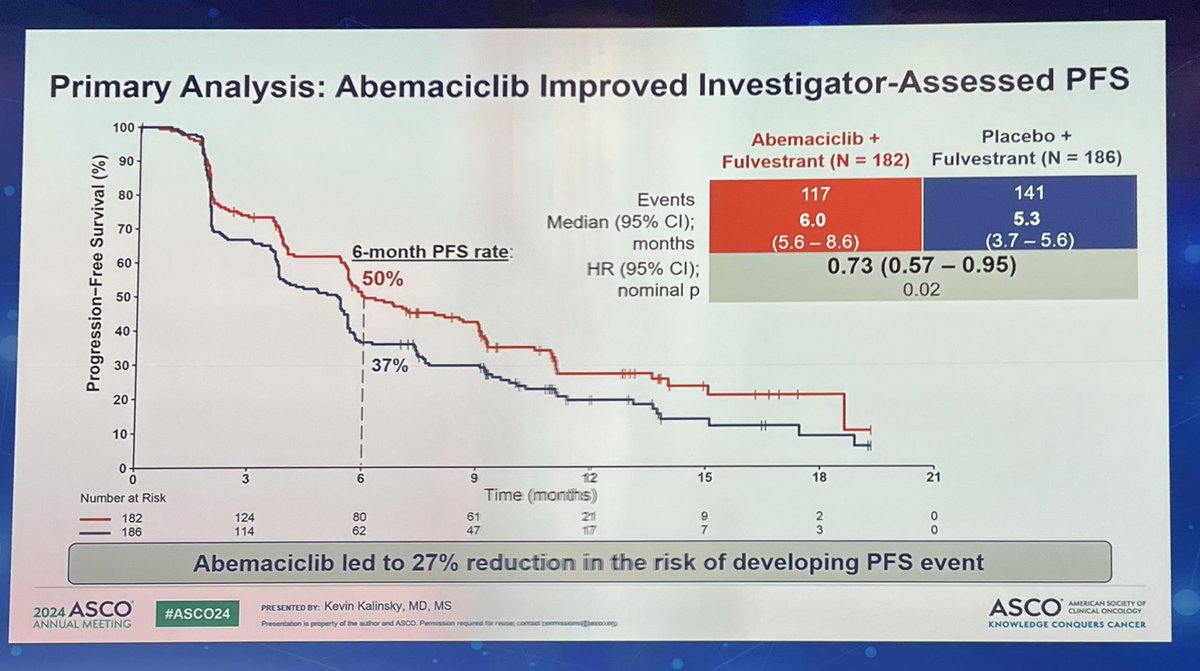
postMONARCH (NCT05169567, Lilly) is the Phase 3 trial of abemaciclib (Verzenio) plus fulvestrant versus placebo plus fulvestrant in HR+/HER2- advanced breast cancer after progression on a CDK4/6 inhibitor (N=368). It met its primary endpoint, investigator-assessed PFS (HR 0.73, 95% CI 0.57-0.95; primary analysis, ASCO 2024 / JCO 2025). The final analysis of overall survival, a secondary endpoint (ESMO 2026; data cut 6 March 2026), was not statistically significant: median 32.1 vs 24.6 months, HR 0.80 (95% CI 0.60-1.06), P=0.11.
Discover KOL Sentiment on postMONARCH →Posts by physicians about postMONARCH, newest first: ESMO 2026 week (October 17–24, 2026), then earlier posts from the ASCO 2024 primary readout and the JCO publication. Each post is shown in full and verbatim and linked to the original on X.
 𝕏
postMONARCH: Abemaciclib After CDK4/6 Inhibitor Progression — PFS Benefit Without a Statistically Significant OS Improvement @OncoAlert #BreastCancer #bcsm #ESMO26 https://t.co/qwKzc5cVZt
 𝕏
#ESMO26 | postMONARCH – Final OS Abemaciclib + fulvestrant 🆚 placebo + fulvestrant after prior CDK4/6i in HR+/HER2− advanced #BreastCancer : 🔹 mOS 32.1 🆚 24.6 mo (HR 0.80; p=0.11) - numeric benefit, not statistically significant. simultaneously published in @Annals_Oncology 👇 🔗 https://t.co/YzOZmhaxxn #bcsm @myESMO @OncoAlert
 𝕏
🔥 Abema + fulvestrant after 1L CDK4/6i/AI improves PFS, PFS2 & time to chemo; numerical ↑OS 👉 CDK targeting remains valid post-CDK4/6i, but NOT a class effect! ✅ Abema (postMONARCH, EMBER-3), atirmociclib (FourLight-1), ribo (MAINTAIN) ⛔ Palbo (PACE, PALMIRA) #ESMO26 https://t.co/KxHmObP6Oc
 𝕏
At #ESMO26 rapid oral session on advanced #breastcancer @KalinskyKevin presents results from postMONARCH Abema + fulvestrant showed numeric, non significant ⬆️ OS in aBC after PD to CDK4-6i Modest PFS improvement @OncoAlert
 𝕏
Overall survival from phIII postMONARCH trial of abemaciclib + fulvestrant v placebo + fulv for HR+ HER2- advanced breast cancer following progression on a prior CDK4/6 inhibitor plus endocrine therapy https://t.co/hYJPDj1XzG #ESMO26 @OncoAlert @KalinskyKevin @Annals_Oncology
 𝕏
Why does abemaciclib still work after CDK4/6i? #postMONARCH #ESMO26 • Resistance is mostly ER-driven (ESR1), so switching to fulvestrant helps • True CDK4/6 independence (RB1 loss) is rare • Abema ≠ palbo: CDK4-selective, some CDK2 activity, continuous dosing PFS2 & TTC HR 0.76. Modest but real. @OncoAlert @OncBrothers @Larvol
 𝕏
Phase III postMONARCH: Final OS Analysis #ESMO26 @KalinskyKevin Abemaciclib + fulvestrant numerically improved OS after CDK4/6i (32.1 vs 24.6 months; HR 0.80, P=0.11), without statistical significance. PFS (HR 0.78), PFS2 (HR 0.76), and time to chemotherapy (HR 0.76) favored abemaciclib.
 𝕏
📢 #ESMO26 | Phase III #postMONARCH 🔹 Median OS: 32.1 vs 24.6 months (+7.5 months) 🔹 HR 0.80 (95% CI 0.60–1.06) 🔹 OS numerically favored abemaciclib + fulvestrant, but did not reach statistical significance. 📌 Encouraging OS trend following CDK4/6i progression. #BreastCancer #HRpositive @KalinskyKevin
 𝕏
#ESMO2026 PostMonarch - change to Fulvestrant v placebo with Abema- continues to show better PFS and OS ➡️ results by ESR1 status eagerly awaited! #ESMOAmbassadors @OncoAlert Published online in @Annals_Oncology https://t.co/Bzolx5kqxi
 𝕏
📌 Overall survival from the phase 3 postMONARCH trial of abemaciclib + fulvestrant vs placebo + fulvestrant for HR+, HER2- advanced breast cancer following progression on a prior CDK4/6 inhibitor + endocrine therapy @KalinskyKevin #ESMO26 🇪🇸 @OncoAlert #OncoAlertAF https://t.co/BlMhps9Mw7
 𝕏
#ESMO26 | postMONARCH – Final OS After progression on CDK4/6i + ET, median OS with abemaciclib + fulvestrant was 32.1 vs 24.6 months, but statistical significance was not reached (HR 0.80; 95% CI 0.60–1.06; p=0.11). The 7.5-month difference in median OS is noteworthy, but these results do not make this combination a preferred second-line option for me, given the availability of biomarker-directed therapies.
 𝕏
Post-monarch continue to show improvement in PFS and numerically (NS) OS #ESMO26 #ESMOAmbassadors #ESMOcommunity @myESMO @KalinskyKevin https://t.co/kcc9NvB9Tv
 𝕏
🧬 Progression on a CDK4/6 inhibitor does not always mean the pathway is exhausted. @OncoAlert At #ESMO26, the final OS analysis of postMONARCH tested abemaciclib + fulvestrant after progression on prior CDK4/6i + endocrine therapy in HR+/HER2– advanced #BreastCancer. 📊 n=368 ➡️ Median OS: 32.1 vs 24.6 months HR 0.80 (0.60–1.06), p=0.1145 ➡️ Updated PFS: HR 0.78 (0.62–0.99) ➡️ No new safety signals The OS difference is numerically meaningful, but not statistically significant. 🎯 Why this matters: continuing CDK4/6 pathway suppression after progression may still have value — but not for every patient, and not with the same magnitude of benefit. For me, the real next step is to understand who remains biologically CDK-dependent after progression and who should instead switch to a different therapeutic pathway. That is the precision question behind postMONARCH. Excellent work from @KalinskyKevin @BianchiniGP @ErikaHamilton9 @DrSGraff @drsarahsam @MuozMateu and the investigators. Pinging @matteolambe @aftimosp @E_de_Azambuja @hoperugo @stolaney1 @kevinpunie @ElisaAgostinett @GaiaGriguolo @JankovicK @LoiSher #OncoAlert #ESMO26 #BreastCancer #CDK46 #EndocrineTherapy #PrecisionOncology
 𝕏
postMONARCH | ESMO 2026 CDK4/6 inhibition after progression? Abemaciclib + fulvestrant: • Original PFS: 6.0 vs 5.3 months. • Final OS: 32.1 vs 24.6 months; HR 0.80, p=0.1145. Modest PFS benefit; numerically longer OS without statistical significance. An option for selected patients. Reference: Kalinsky K et al. postMONARCH, ESMO 2026; original PFS publication, JCO. #MVOnco #ESMO2026 #BreastCancer #postMONARCH
𝕏🚨 @OncoAlert 4Sight Abstracts to be presented at #ESMO26 🇪🇸 | Final OS results from #postMONARCH ✨👀 👇 Abemaciclib + fulvestrant after progression on prior CDK4/6i: 🎀 OS: 32.1 🆚 24.6 months (HR 0.80; p=0.1145) 🎀 updated PFS (HR 0.78) https://t.co/3Pcy2YoIoT
 𝕏
postMONARCH 🦋 to be presented at #ESMO26 final OS: numerically longer (32.1 vs 24.6 mo) but not significant. Consistent PFS signal and no new safety concerns. Continuing CDK4/6i beyond progression still has a place, but patient selection is key. #BreastCancer https://t.co/Wjj3HESTWW
𝕏postMONARCH: CDK4/6 Inhibition Beyond Progression — Modest PFS Benefit, No Significant OS Benefit @OncoAlert #ESMO26 #BreastCancer https://t.co/9tp2n36twG
𝕏#ESMO26 | postMONARCH – Final OS After prior CDK4/6i, abemaciclib + fulvestrant showed a numerically notable OS difference (32.1 vs 24.6 months; HR 0.80; p=0.1), although not statistically significant. The median PFS gain was modest (6.0 vs 5.3 months, HR:0.78) https://t.co/LhhDmtDjFf

PostMONARCH out in @JCO_ASCO. Fulvestrant/abema beyond CDK4/6i progression (mostly beyond palbo) slightly improves PFS (6 vs 5.3 mo) over fulvestrant alone. Not the most active 2L combo,...
Some thoughts on postMONARCH - HR often provide a better estimate of benefit than medians. A 27% reduction in risk or progression or death is encouraging, as noted by many more patients free from...

Lisa A. Carey, MD, and Kevin Kalinsky, MD, on Advanced Breast Cancer: New Data on Abemaciclib and Fulvestrant From the postMONARCH Trial #bcsm #breastcancer...

postMONARCH primary endpoint = investigator assessed PFS : +0,7 Months secondary analysis = central review PFS = ... + 7.3 months !! How is this possible⁉️ short🧵1/

@Timothee_MD @VPrasadMDMPH @oncology_bg Any idea what's going on here?🤔 MPFS delta of 0.7months by local PFS assessment Vs 7.3months in BCIR? This a...
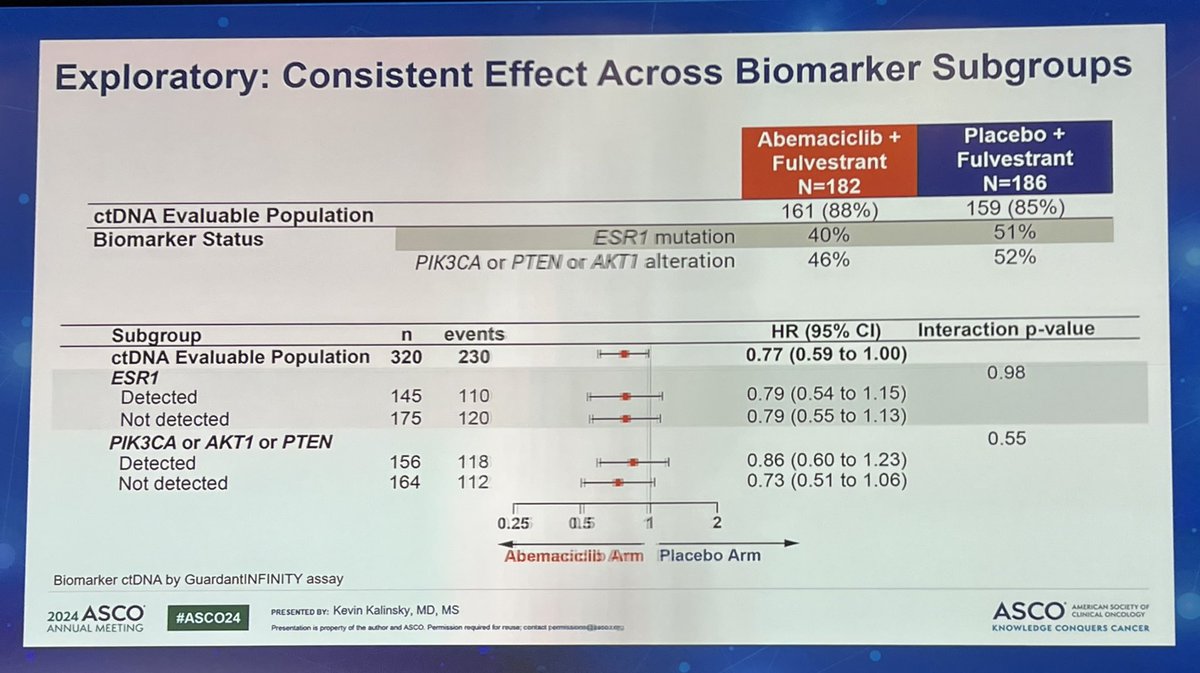
PostMonarch: Abemaciclib after progression on CDK4/6 inhib shows 27% reduction in PFS. All subgroups, all biomarkers seem to benefit. Valuable in the current landscape; sets the stage for EMBER-3...
Also, at #ASCO24 the long awaited #postmonarch trial (to extend or not to extend—that is the question) and more detail on how we may incorporate ctDNA into...
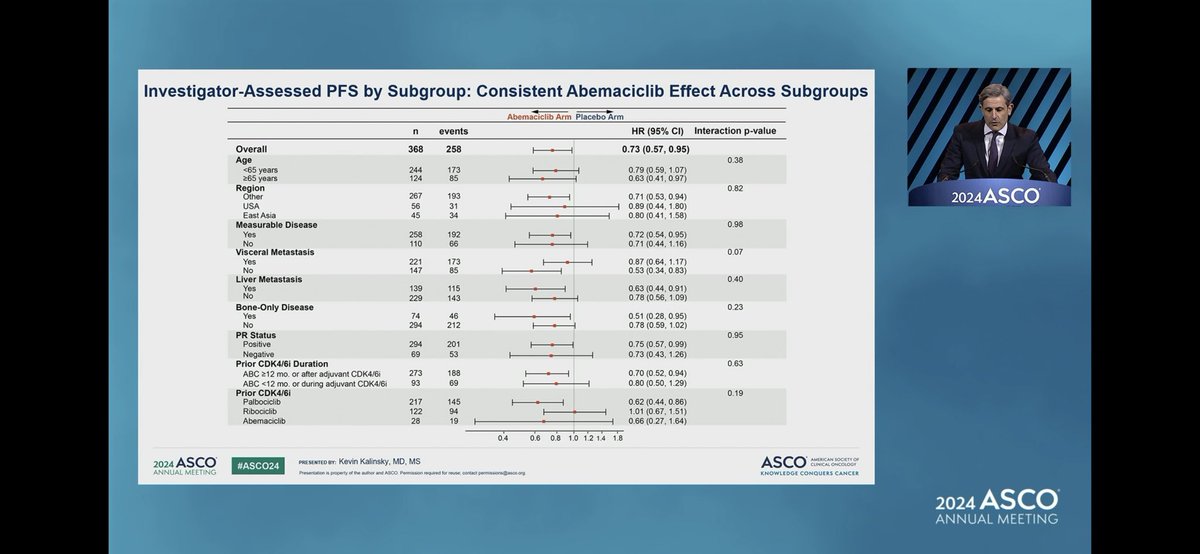
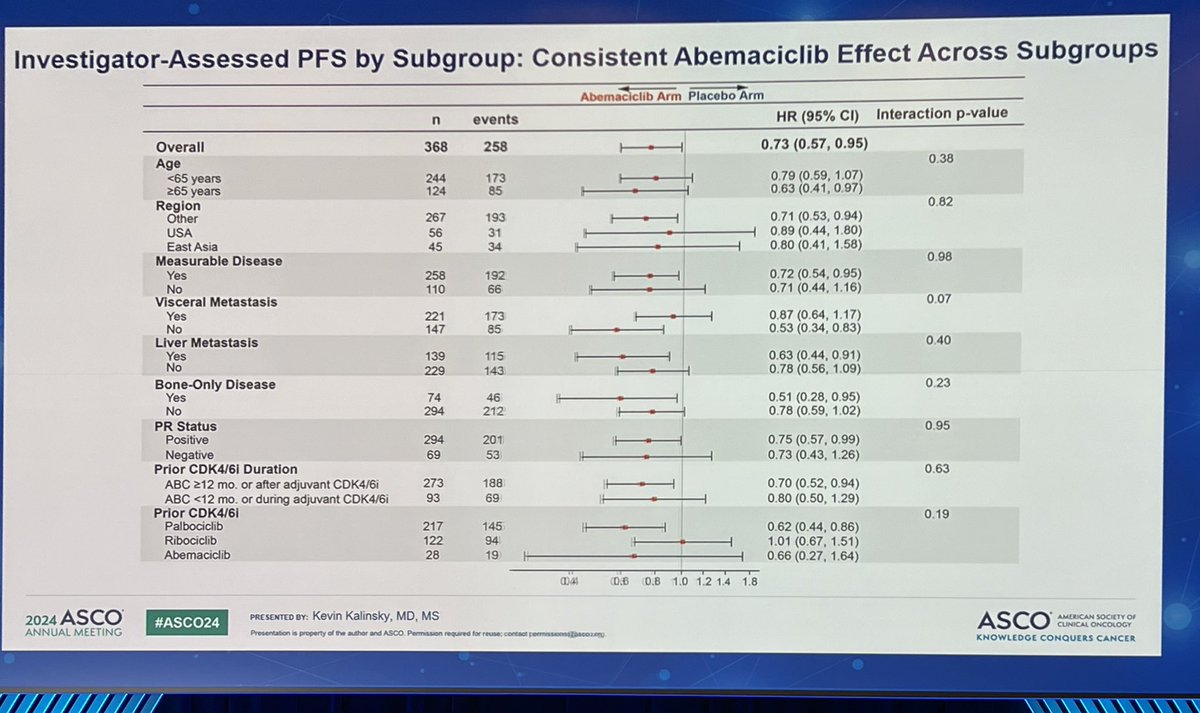
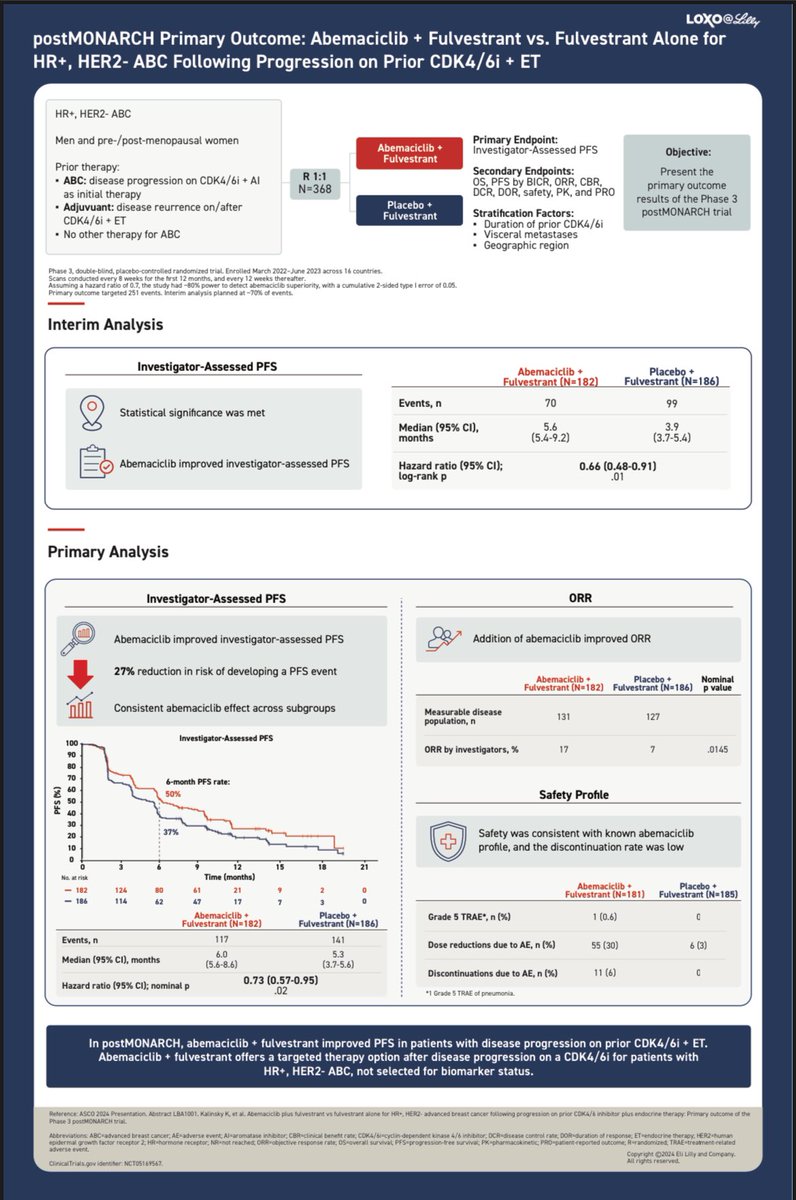
The primary endpoint was met. At the primary analysis (258 events), median PFS was 6.0 months (95% CI: 5.6-8.6) with abemaciclib versus 5.3 months (95% CI: 3.7-5.6) with placebo (HR 0.73; 95% CI: 0.57-0.95; p=0.02), a 27% risk reduction. The 6-month PFS rate was 50% versus 37%. BICR-assessed PFS showed a larger benefit: 12.9 months versus 5.6 months (HR 0.55; 95% CI: 0.39-0.77; p=0.0004). These are primary-analysis figures (ASCO 2024 presentation; the JCO 2025 publication reports nominal P=0.017 for investigator-assessed PFS). At the updated analysis (data cut 6 March 2026, ESMO 2026), investigator-assessed median PFS (primary endpoint) was 5.9 versus 5.3 months (HR 0.78; 95% CI 0.62-0.99; P=0.039; 145 vs 156 events) and BICR-assessed PFS (secondary endpoint) 13.8 versus 5.6 months (HR 0.60; 95% CI 0.44-0.83; P=0.0019; 69 vs 100 events), with BICR estimates impacted by informative censoring. Benefit was consistent across subgroups, including prior palbociclib (HR 0.62), bone-only disease (HR 0.51), liver metastases (HR 0.63), and prior CDK4/6i duration of 12+ months (HR 0.70).
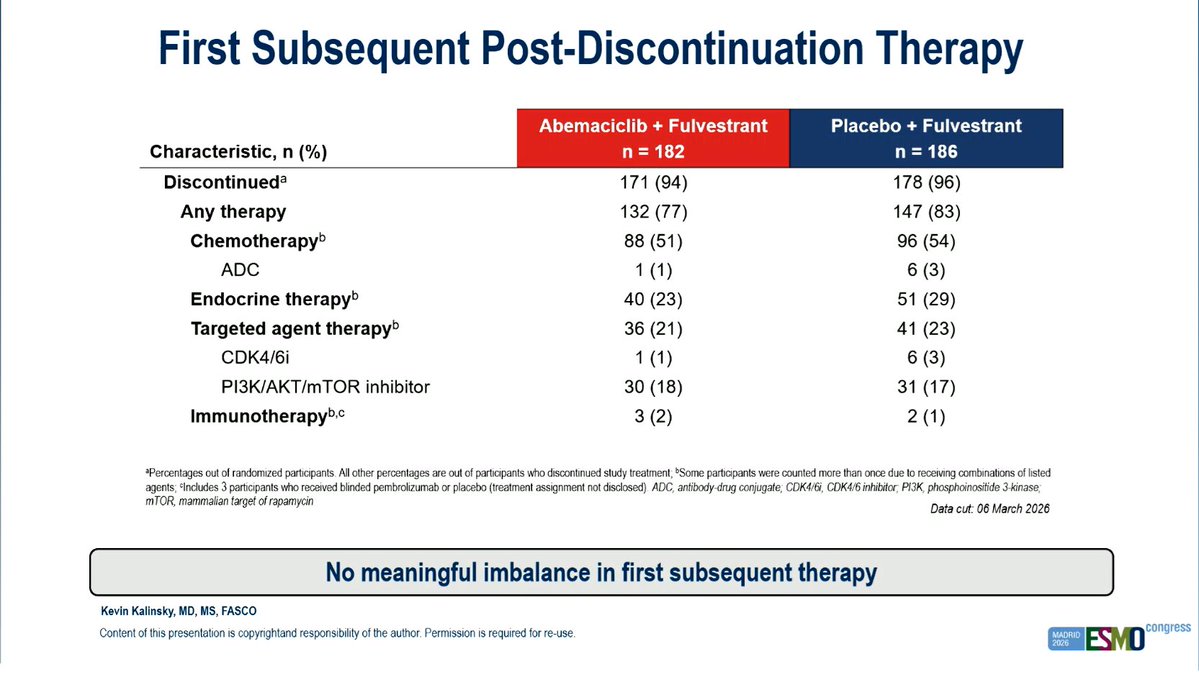
Overall survival (secondary endpoint) was immature at the primary analysis. The prespecified final OS analysis (200 events; median follow-up 37 months; data cut 6 March 2026) was presented at ESMO 2026 by Kevin Kalinsky: median OS 32.1 months (95% CI 27.2-38.1) with abemaciclib + fulvestrant versus 24.6 months (95% CI 22.5-28.8) with placebo + fulvestrant (90 vs 110 events); HR 0.80 (95% CI 0.60-1.06); log-rank P=0.11. The difference did not reach statistical significance. Exploratory endpoints (same data cut): PFS2 13.9 vs 12.3 months (HR 0.76; 95% CI 0.59-0.97; P=0.029) and time to chemotherapy 13.6 vs 9.7 months (HR 0.76; 95% CI 0.58-0.99; P=0.039). No new safety signals were identified.
The safety profile was consistent with known abemaciclib toxicity. Grade 3+ AEs in the abemaciclib arm included neutropenia (25%), anemia (11%), leukopenia (8%), AST elevation (6%), diarrhea (4%), thrombocytopenia (4%), ALT elevation (4%), fatigue (3%), and VTE (2%). One grade 5 treatment-related AE (pneumonia) occurred in the abemaciclib arm. AEs led to dose reductions in 30% versus 3% and discontinuation in 6% versus 0%.
Regulatory status & clinical implications - Investigational in the post-CDK4/6i setting; abemaciclib is FDA approved in other HR+/HER2- breast cancer settings.
postMONARCH establishes abemaciclib plus fulvestrant as a biomarker-unselected treatment option after CDK4/6 inhibitor progression, addressing a critical unmet need. The modest absolute PFS gain at the primary analysis (0.7 months by investigator, but 7.3 months by BICR) and the debate around the informative censoring discrepancy between investigator and BICR assessments are key discussion points. The trial supports CDK4/6i rechallenge with a switch strategy (especially from palbociclib to abemaciclib) but raises questions about whether ribociclib-pretreated patients benefit similarly (HR 1.01, wide CI). Clinical debate continues on optimal sequencing versus biomarker-directed therapies (ESR1: oral SERDs; PI3K: alpelisib/inavolisib) and ADCs.
Sponsor / drugs - Eli Lilly; abemaciclib (Verzenio) + fulvestrant (Faslodex).
Compiled and reviewed by the KOL Pulse research team, led by Brian Shields, Founder, KOL Pulse. Last updated October 24, 2026.




| Arm | N | Events | Median, months (95% CI) |
|---|---|---|---|
| Abemaciclib + Fulvestrant (INV-PFS) | 182 | 145 | 5.9 (5.5-8.6) |
| Placebo + Fulvestrant (INV-PFS) | 186 | 156 | 5.3 (3.7-5.6) |
| Abemaciclib + Fulvestrant (BICR-PFS) | 182 | 69 | 13.8 (9.5-NR) |
| Placebo + Fulvestrant (BICR-PFS) | 186 | 100 | 5.6 (4.6-9.2) |
| Landmark | Arm | Rate (printed) |
|---|---|---|
| 12 months | Abemaciclib + Fulvestrant (INV-PFS) | 28% |
| 12 months | Placebo + Fulvestrant (INV-PFS) | 22% |
| 24 months | Abemaciclib + Fulvestrant (INV-PFS) | 14% |
| 24 months | Placebo + Fulvestrant (INV-PFS) | 8% |
| 6 months | Abemaciclib + Fulvestrant (BICR-PFS) | 69% |
| 6 months | Placebo + Fulvestrant (BICR-PFS) | 46% |
| 12 months | Abemaciclib + Fulvestrant (BICR-PFS) | 53% |
| 12 months | Placebo + Fulvestrant (BICR-PFS) | 39% |
| 24 months | Abemaciclib + Fulvestrant (BICR-PFS) | 40% |
| 24 months | Placebo + Fulvestrant (BICR-PFS) | 26% |
| Arm | N | Events | Median, months (95% CI) |
|---|---|---|---|
| Abemaciclib + Fulvestrant | 182 | 90 | 32.1 (27.2-38.1) |
| Placebo + Fulvestrant | 186 | 110 | 24.6 (22.5-28.8) |


| Arm | N | Events | Median, months (95% CI) |
|---|---|---|---|
| Abemaciclib + Fulvestrant | 182 | 90 | 32.1 (27.2-38.1) |
| Placebo + Fulvestrant | 186 | 110 | 24.6 (22.5-28.8) |
| Arm | N | Events | Median, months (95% CI) |
|---|---|---|---|
| Abemaciclib + Fulvestrant (INV-PFS) | 182 | 145 | 5.9 (5.5-8.6) |
| Placebo + Fulvestrant (INV-PFS) | 186 | 156 | 5.3 (3.7-5.6) |
| Abemaciclib + Fulvestrant (BICR-PFS) | 182 | 69 | 13.8 (9.5-NR) |
| Placebo + Fulvestrant (BICR-PFS) | 186 | 100 | 5.6 (4.6-9.2) |
| Landmark | Arm | Rate (printed) |
|---|---|---|
| 12 months (INV-PFS) | Abemaciclib + Fulvestrant | 28% |
| 12 months (INV-PFS) | Placebo + Fulvestrant | 22% |
| 24 months (INV-PFS) | Abemaciclib + Fulvestrant | 14% |
| 24 months (INV-PFS) | Placebo + Fulvestrant | 8% |
| 6 months (BICR-PFS) | Abemaciclib + Fulvestrant | 69% |
| 6 months (BICR-PFS) | Placebo + Fulvestrant | 46% |
| 12 months (BICR-PFS) | Abemaciclib + Fulvestrant | 53% |
| 12 months (BICR-PFS) | Placebo + Fulvestrant | 39% |
| 24 months (BICR-PFS) | Abemaciclib + Fulvestrant | 40% |
| 24 months (BICR-PFS) | Placebo + Fulvestrant | 26% |
| Arm | N | Events | Median, months (95% CI) |
|---|---|---|---|
| Abemaciclib + Fulvestrant (PFS2) | 182 | 135 | 13.9 (11.8-17.2) |
| Placebo + Fulvestrant (PFS2) | 186 | 151 | 12.3 (10.7-13.8) |
| Abemaciclib + Fulvestrant (TTC) | 182 | 111 | 13.6 (9.7-17.2) |
| Placebo + Fulvestrant (TTC) | 186 | 132 | 9.7 (7.7-11.5) |



| Arm | N | Events | Median, months (95% CI) |
|---|---|---|---|
| Abemaciclib + Fulvestrant | 182 | 90 | 32.1 (27.2-38.1) |
| Placebo + Fulvestrant | 186 | 110 | 24.6 (22.5-28.8) |
| Arm | N | Events | Median, months (95% CI) |
|---|---|---|---|
| Abemaciclib + Fulvestrant | 182 | 145 | 5.9 (5.5-8.6) |
| Placebo + Fulvestrant | 186 | 156 | 5.3 (3.7-5.6) |
| Landmark | Arm | Rate (printed) |
|---|---|---|
| 12 mo | Abemaciclib + Fulvestrant | 28% |
| 12 mo | Placebo + Fulvestrant | 22% |
| 24 mo | Abemaciclib + Fulvestrant | 14% |
| 24 mo | Placebo + Fulvestrant | 8% |
| Arm | N | Events | Median, months (95% CI) |
|---|---|---|---|
| Abemaciclib + Fulvestrant | 182 | 135 | 13.9 (11.8-17.2) |
| Placebo + Fulvestrant | 186 | 151 | 12.3 (10.7-13.8) |


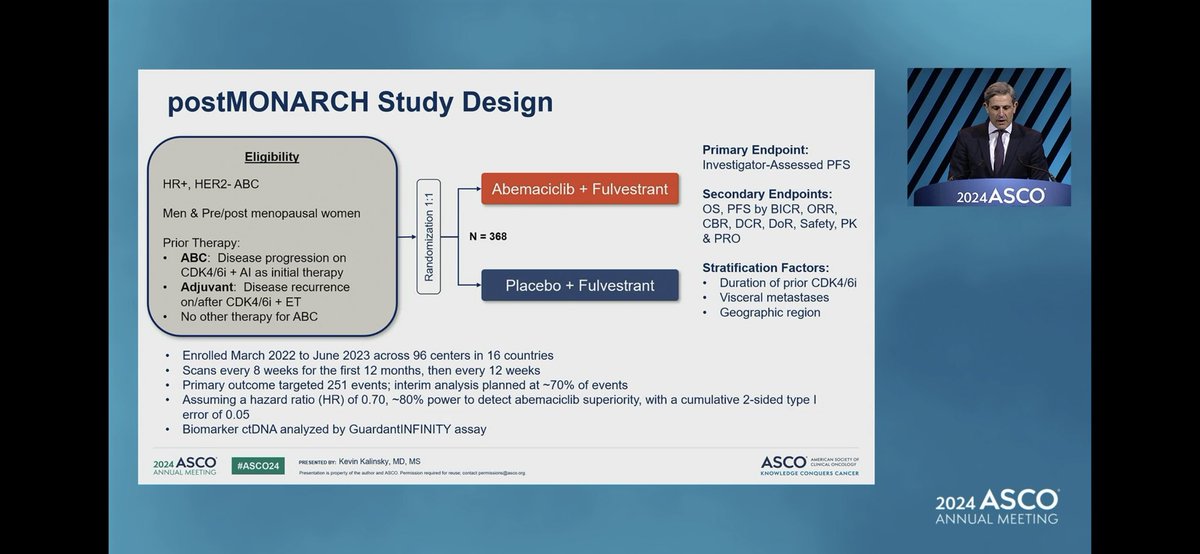







postMONARCH is a global, randomized, double-blind, placebo-controlled Phase III trial evaluating abemaciclib (Verzenio) plus fulvestrant versus placebo plus fulvestrant in patients with HR+/HER2- advanced breast cancer who progressed on a prior CDK4/6 inhibitor and endocrine therapy. It is the first Phase III, placebo-controlled study to demonstrate a statistically significant progression-free survival benefit of continued CDK4/6 inhibition beyond progression on a prior CDK4/6 inhibitor, regardless of biomarker status.
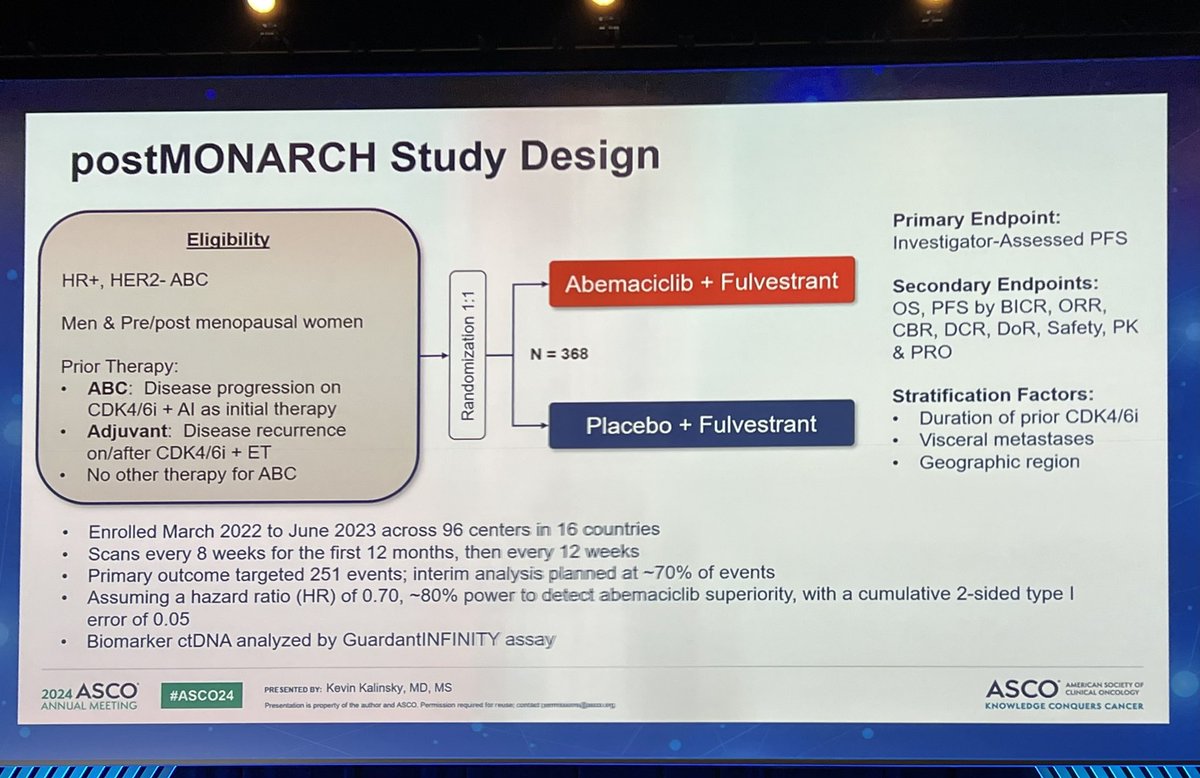
Phase III, global, randomized (1:1), double-blind, placebo-controlled trial (NCT05169567). Patients received abemaciclib 150 mg orally twice daily plus fulvestrant 500 mg IM, or placebo plus fulvestrant. Stratified by duration of prior CDK4/6 inhibitor, visceral metastases, and geographic region. Enrolled March 2022 to June 2023 across 96 centers in 16 countries.
Men and pre/postmenopausal women with HR+/HER2- advanced or metastatic breast cancer who experienced disease progression on CDK4/6 inhibitor plus aromatase inhibitor as initial advanced therapy, or disease recurrence on/after adjuvant CDK4/6 inhibitor plus ET. No prior chemotherapy, SERDs, or PI3K/mTOR/AKT inhibitors for advanced disease. ECOG PS 0-1. 368 patients randomized.
Abemaciclib 150 mg orally twice daily on Days 1-28 of a 28-day cycle plus fulvestrant 500 mg IM on Days 1 and 15 of Cycle 1, then Day 1 of subsequent cycles, versus matched placebo plus fulvestrant.
Primary endpoint: investigator-assessed PFS. Key secondary endpoints: overall survival (OS), BICR-assessed PFS, ORR, clinical benefit rate (CBR), disease control rate (DCR), duration of response, safety, pharmacokinetics, and patient-reported outcomes.
postMONARCH (NCT05169567) is a Lilly Phase 3 randomized trial of abemaciclib (Verzenio) plus fulvestrant versus placebo plus fulvestrant in HR-positive, HER2-negative advanced breast cancer that progressed on a prior CDK4/6 inhibitor; 368 patients were randomized. See Trial Design.
Yes. Investigator-assessed progression-free survival improved (HR 0.73). The final overall survival analysis (ESMO 2026) was not statistically significant. Figures, data cuts and sources: At a Glance.
No. The post-CDK4/6-inhibitor setting studied in postMONARCH is investigational; abemaciclib (Verzenio) is FDA approved in other HR-positive, HER2-negative breast cancer settings. See At a Glance.
Consistent with the known abemaciclib profile, led by neutropenia, with more dose reductions than placebo and one grade 5 event. Rates are in At a Glance.
It supports switching CDK4/6 inhibitors plus fulvestrant as a biomarker-unselected option, but the small investigator-assessed PFS gain, the larger BICR benefit with informative censoring, and the non-significant final OS keep it debated. See At a Glance.










