Phase 3 randomized double-blind study of perioperative apalutamide (Erleada) plus androgen deprivation therapy (ADT) versus placebo plus ADT — given before and after radical prostatectomy — in newly diagnosed high-risk localized or locally advanced prostate cancer. Presented as an ASCO 2026 Plenary by Mary-Ellen Taplin, MD (Dana-Farber). At 61.7-month median follow-up, PROTEUS met both dual primary endpoints: pCR/MRD 8.9% vs 1.0% (OR 10.17) and metastasis-free survival HR 0.80 (p=0.02). Overall survival, an exploratory measure, showed no benefit (HR 1.08).
Posts by physicians about PROTEUS, newest first: ESMO 2026 week (October 17–24, 2026), then earlier posts from the ASCO 2026 Plenary readout. Each post is shown in full and verbatim and linked to the original on X.
INVESTIGATIONAL · PERIOPERATIVE LOCALIZEDApalutamide (Erleada) is FDA-approved in nmCRPC and mCSPC, but perioperative use in localized/locally advanced disease is investigational
PROTEUS is the first Phase 3 trial to show that adding apalutamide to ADT before and after radical prostatectomy improves pathologic response and metastasis-free survival in high-risk localized prostate cancer. Johnson & Johnson has framed the data as supporting a potential new standard of care.
PROTEUS met the pCR/MRD co-primary endpoint. The pCR/MRD rate was 8.9% with apalutamide + ADT versus 1.0% with placebo + ADT — odds ratio 10.17 (95% CI 5.27–19.64), p<0.0001, a roughly nine-fold improvement after six cycles of neoadjuvant therapy. The stricter ypT0 (no residual tumor) rate was 5.1% vs 0.4%. Positive surgical margins at prostatectomy were present in 20.9% vs 42.7%, and an exploratory residual cancer burden response was reported in 30.6% vs 11.7% (OR 3.36, 95% CI 2.67–4.23, p<0.0001).
PROTEUS also met the MFS co-primary endpoint. By blinded independent central review, apalutamide + ADT produced a statistically significant 20% reduction in the risk of metastasis or death — HR 0.80 (95% CI 0.67–0.96), p=0.02, with five-year MFS rates of 78.2% vs 73.5%. Investigator-assessed MFS was directionally stronger (HR 0.74, 95% CI 0.62–0.87, p=0.0004). MFS was defined by conventional or PSMA-PET imaging. By conventional imaging alone, the difference was not statistically significant (HR 0.84, 95% CI 0.67–1.07); the significant primary result was driven substantially by PSMA-PET detection of distant metastases.
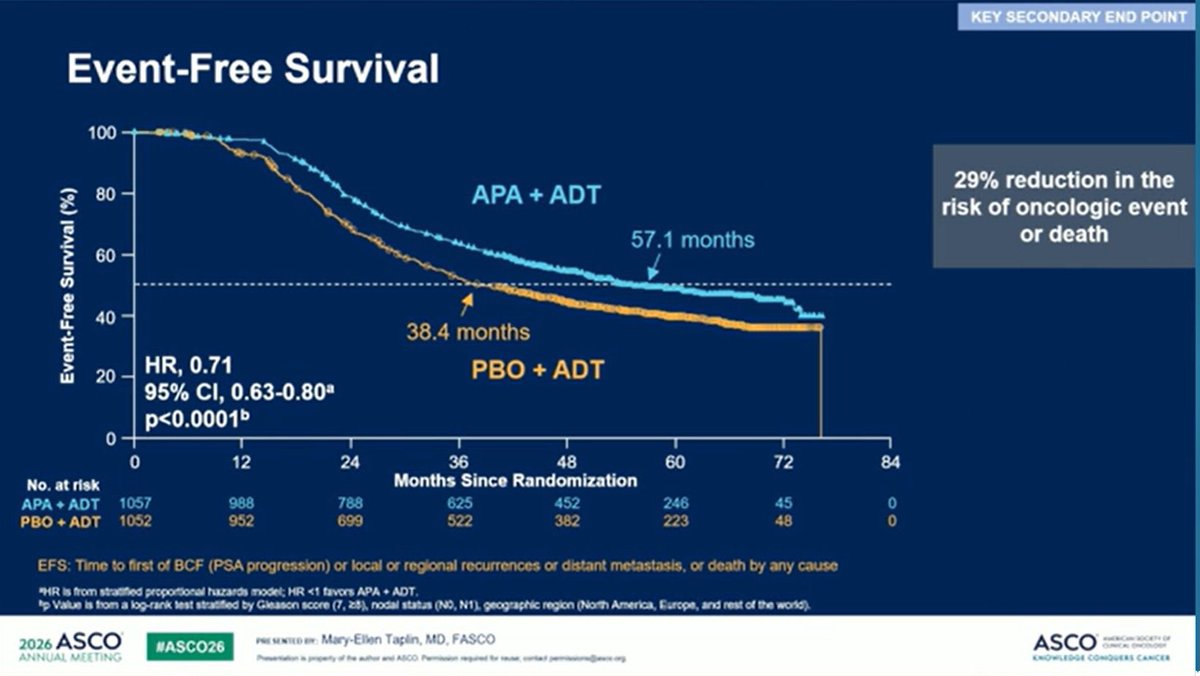
Time to distant metastasis (by conventional or PSMA-PET) favored apalutamide: HR 0.68 (95% CI 0.55–0.83), p=0.0002, with five-year distant-metastasis-free rates of 82.8% vs 76.2%. Investigators also reported a 29% reduction in prostate cancer recurrence (event-free survival HR 0.71, 95% CI 0.63–0.80, p<0.0001; median EFS 57.1 vs 38.4 months). Median time to first subsequent therapy was 74.2 vs 41.5 months (HR 0.65, 95% CI 0.57–0.73, p<0.0001). Fewer apalutamide patients required subsequent therapy of any kind (42.4% vs 56.7%), including less subsequent systemic therapy (26.7% vs 36.4%) and less postoperative radiotherapy (13.0% vs 18.4%).
Overall survival was an exploratory measure and the trial was not powered to detect it. At a median follow-up of five years with overall mortality of 8.5%, the hazard ratio for death was 1.08 — numerically unfavorable, though below the prespecified threshold for unacceptable detriment, and not a demonstration of survival benefit. The accompanying NEJM editorial stated that a confirmed OS benefit with longer follow-up has not been shown.
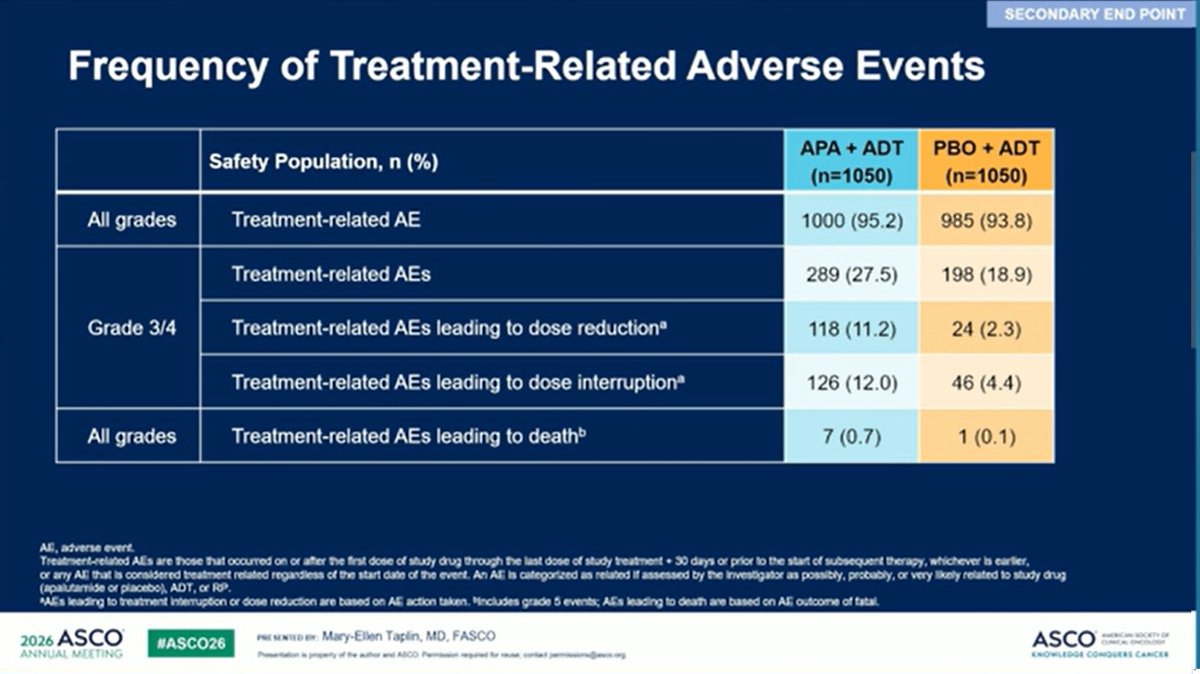
Grade 3 or 4 adverse events occurred in 39.6% of the apalutamide arm versus 31.0% of the placebo arm, with the difference driven primarily by rash (21.2% vs 10.0%) — a well-characterized apalutamide class effect. The overall profile was consistent with prior apalutamide experience (SPARTAN, TITAN), and no new safety signals were reported in the perioperative setting.
Apalutamide (Erleada) is currently FDA-approved in non-metastatic castration-resistant prostate cancer (nmCRPC) and metastatic castration-sensitive prostate cancer (mCSPC). PROTEUS provides the first Phase 3 evidence for perioperative apalutamide in localized/locally advanced disease — an investigational use. Johnson & Johnson has positioned the dual-primary win as supporting a paradigm shift toward systemic-plus-surgery intensification. The trial met both co-primary endpoints (pCR/MRD and MFS); overall survival was exploratory with HR 1.08 and is not yet a demonstration of benefit.
Presented at ESMO 2026 (October 24, 2026) — PROTEUS Substudy
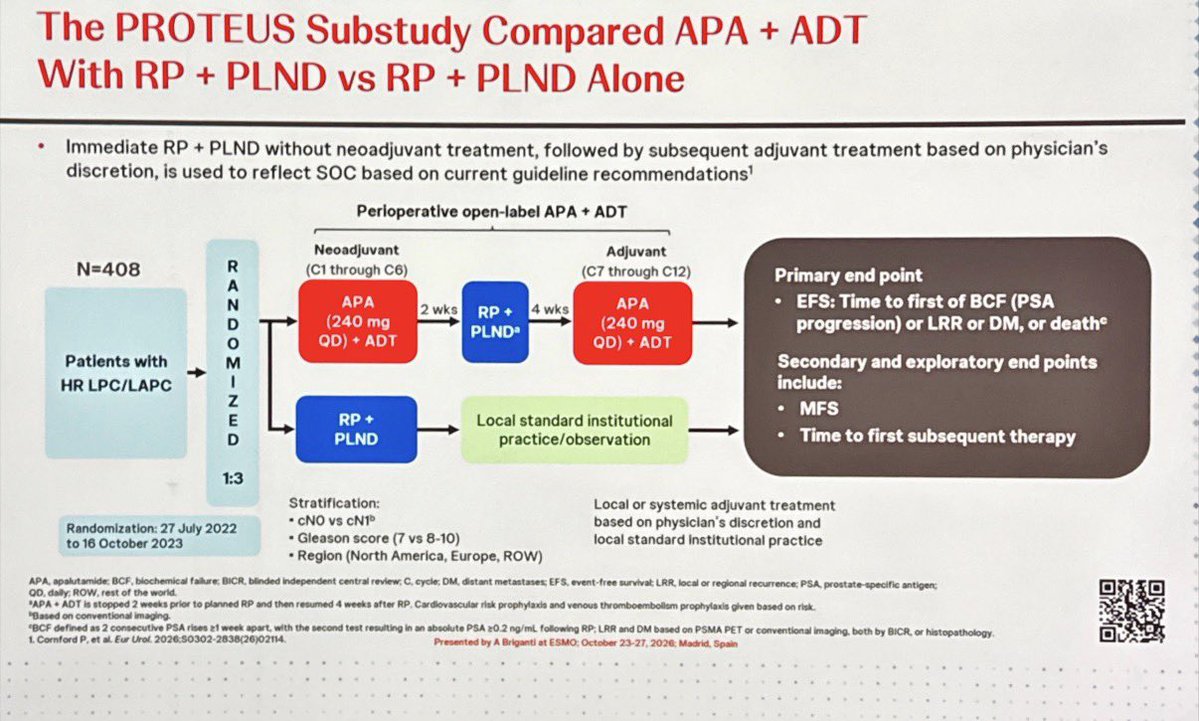
Slides shared by physicians from the PROTEUS Substudy (LBA53, presented by Alberto Briganti; discussant Nicholas van As). The Substudy is a separate open-label comparison, randomized 1:3 (N=408), of perioperative apalutamide + ADT with RP + PLND vs RP + PLND alone — distinct from the double-blind PROTEUS main trial (apalutamide + ADT vs placebo + ADT) whose ASCO 2026 slides follow below. Click any image to expand; “View OCR Text” shows the slide text, with survival curves summarized as numbers tables.
[Slide 1]
N=408
Patients with HR LPC/LAPC -> RANDOMIZED 1:3
Perioperative open-label APA + ADT
Neoadjuvant (C1 through C6): APA (240 mg QD) + ADT -> 2 wks -> RP + PLND(a) -> 4 wks -> Adjuvant (C7 through C12): APA (240 mg QD) + ADT
RP + PLND -> Local standard institutional practice/observation
Primary end point
- EFS: Time to first of BCF (PSA progression) or LRR or DM, or death(c)
Secondary and exploratory end points include:
- MFS
- Time to first subsequent therapy
Randomization: 27 July 2022 to 16 October 2023
Stratification:
- cN0 vs cN1(b)
- Gleason score (7 vs 8-10)
- Region (North America, Europe, ROW)
Local or systemic adjuvant treatment based on physician's discretion and local standard institutional practice
---
[Slide 2]
Event-Free Survival (%)
T recovery to >=200 ng/dL: Median 20.7 months (~9 months from EOT)
APA + ADT Median not reached | 63.0% (95% CI, 52.2-71.9)
RP + PLND alone Median 19.1 months | 41.4% (95% CI, 35.6-47.1)
HR, 0.38(a)
95% CI, 0.26-0.55
p<0.0001(b)
Event-free survival — values printed on the slide
Arm
N
Median (95% CI)
Rate at 36 months (95% CI)
APA + ADT
102
Not reached
63.0% (52.2-71.9)
RP + PLND alone
306
19.1 months
41.4% (35.6-47.1)
HR 0.38 (95% CI 0.26-0.55); p<0.0001
Numbers at risk and axis ticks omitted; landmark rates are the values printed at the slide’s dashed landmark line. Data cut-off is not printed on this slide (the PROTEUS Substudy baseline-characteristics slide presented by A Briganti states clinical cutoff 13 July 2026).
---
[Slide 3]
Metastasis-Free Survival (%)
APA + ADT
RP + PLND alone
HR, 0.49(a)
95% CI, 0.26-0.90
nominal p=0.0193(b)
Metastasis detection method, n (%) | APA + ADT | RP + PLND
PSMA PET | 9 (8.8) | 50 (16.3)
Conventional imaging | 1 (1.0) | 6 (2.0)
Histopathology | 1 (1.0) | 0
Metastasis-free survival — values printed on the slide
Arm
N
Median (95% CI)
APA + ADT
102
Not printed
RP + PLND alone
306
Not printed
HR 0.49 (95% CI 0.26-0.90); nominal p=0.0193
Numbers at risk and axis ticks omitted; landmark rates are the values printed at the slide’s dashed landmark line. Data cut-off is not printed on this slide (the PROTEUS Substudy baseline-characteristics slide presented by A Briganti states clinical cutoff 13 July 2026).
---
[Slide 4]
Time to First Subsequent Therapy (%)
APA + ADT
Median 46.0 months
64.6%
(95% CI, 54.1-73.3 )
RP + PLND alone
Median 12.3 months
32.0%
(95% CI, 26.7-37.5)
HR, 0.29a
95% CI, 0.20-0.43
nominal p<0.0001b
Time to first subsequent therapy — values printed on the slide
Arm
N
Median (95% CI)
Rate at 36 months (95% CI)
APA + ADT
102
46.0 months
64.6% (54.1-73.3)
RP + PLND alone
306
12.3 months
32.0% (26.7-37.5)
HR 0.29 (95% CI 0.20-0.43); nominal p<0.0001
Numbers at risk and axis ticks omitted; landmark rates are the values printed at the slide’s dashed landmark line. Data cut-off is not printed on this slide (the PROTEUS Substudy baseline-characteristics slide presented by A Briganti states clinical cutoff 13 July 2026).
[Slide 1]
PROTEUS: A Significant Advance in Surgery Outcomes in HR LPC/LAPC but No Surgery-Alone Comparator
• In HR LPC/LAPC, despite refinement of prostatectomy as an SOC,1 the frequency of disease recurrence is high and patients may be subject to additional morbidity from subsequent therapy2,3
• The PROTEUS main study, with a blinded design, demonstrated superior efficacy of 1-year perioperative apalutamide plus ADT compared with an active comparator4:
Unprecedented Study Design
• Largest size to date
• Novel end points
• PSMA PET inclusion
Enhanced Disease Control With Perioperative Apalutamide + ADT
Significant benefit:
• 9x greater pCR/MRD
• 20% lower hazard for metastasis or death
• 29% lower risk of recurrence or death
• ~3 years longer time to next treatment
Limitation
Control group did not receive SOC (surgery alone)
The PROTEUS Substudy was designed to compare perioperative apalutamide + ADT with RP + PLND versus SOC (surgery alone)
ADT, androgen deprivation therapy; HR LPC/LAPC, high-risk localized/locally advanced prostate cancer; pCR/MRD, pathologic complete response/minimal residual disease; PLND, pelvic lymph node dissection; PSMA PET, prostate-specific membrane antigen positron emission tomography; RP, radical prostatectomy; SOC, standard of care.
1. Cooley LF, Shore ND. Transl Androl Urol. 2025;14:493-495. 2. Eiber M, et al. J Clin Oncol. 2024;42:5027. 3. Stattin P, et al. BJU Int. 2024;134:96-102. 4. Taplin ME, et al. N Engl J Med. 2026;395:546-560.
Presented by A Briganti at ESMO; October 23-27, 2026; Madrid, Spain
---
[Slide 2]
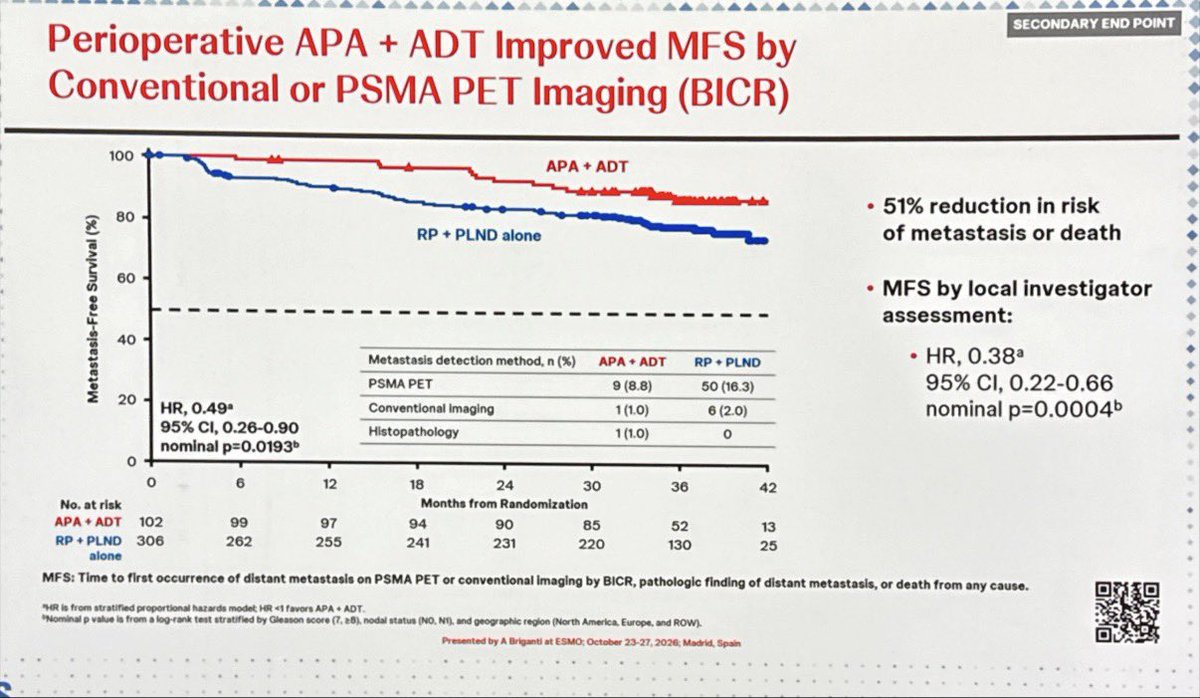
Perioperative APA + ADT Improved MFS by Conventional or PSMA PET Imaging (BICR)
SECONDARY END POINT
HR, 0.49a
95% CI, 0.26-0.90
nominal p=0.0193b
Metastasis detection method, n (%) | APA + ADT | RP + PLND
PSMA PET | 9 (8.8) | 50 (16.3)
Conventional Imaging | 1 (1.0) | 6 (2.0)
Histopathology | 1 (1.0) | 0
• 51% reduction in risk of metastasis or death
• MFS by local investigator assessment:
• HR, 0.38a 95% CI, 0.22-0.66 nominal p=0.0004b
MFS: Time to first occurrence of distant metastasis on PSMA PET or conventional imaging by BICR, pathologic finding of distant metastasis, or death from any cause.
aHR is from stratified proportional hazards model; HR <1 favors APA + ADT.
bNominal p value is from a log-rank test stratified by Gleason score (7, ≥8), nodal status (N0, N1), and geographic region (North America, Europe, and ROW).
Presented by A Briganti at ESMO; October 23-27, 2026; Madrid, Spain
Metastasis-free survival by BICR (secondary endpoint), PROTEUS substudy — values printed on the slide
Arm
N
Median (95% CI)
APA + ADT
102
Not printed
RP + PLND alone
306
Not printed
HR 0.49 (95% CI 0.26-0.90); nominal p=0.0193
Numbers at risk and axis ticks omitted; landmark rates are the values printed at the slide’s dashed landmark line. Data cut-off is not printed on this slide (the PROTEUS Substudy baseline-characteristics slide presented by A Briganti states clinical cutoff 13 July 2026).
[Slide 1]
The PROTEUS Substudy Compared APA + ADT With RP + PLND vs RP + PLND Alone
• Immediate RP + PLND without neoadjuvant treatment, followed by subsequent adjuvant treatment based on physician's discretion, is used to reflect SOC based on current guideline recommendations(1)
N=408 | Patients with HR LPC/LAPC → RANDOMIZED 1:3
Perioperative open-label APA + ADT: Neoadjuvant (C1 through C6) APA (240 mg QD) + ADT → 2 wks → RP + PLND(a) → 4 wks → Adjuvant (C7 through C12) APA (240 mg QD) + ADT
RP + PLND → Local standard institutional practice/observation
Primary end point
• EFS: Time to first of BCF (PSA progression) or LRR or DM, or death(c)
Secondary and exploratory end points include:
• MFS
• Time to first subsequent therapy
Randomization: 27 July 2022 to 16 October 2023
Stratification:
• cN0 vs cN1(b)
• Gleason score (7 vs 8-10)
• Region (North America, Europe, ROW)
Local or systemic adjuvant treatment based on physician's discretion and local standard institutional practice
APA, apalutamide; BCF, biochemical failure; BICR, blinded independent central review; C, cycle; DM, distant metastases; EFS, event-free survival; LRR, local or regional recurrence; PSA, prostate-specific antigen; QD, daily; ROW, rest of the world.
a APA + ADT is stopped 2 weeks prior to planned RP and then resumed 4 weeks after RP. Cardiovascular risk prophylaxis and venous thromboembolism prophylaxis given based on risk.
b Based on conventional imaging.
c BCF defined as 2 consecutive PSA rises ≥1 week apart, with the second test resulting in an absolute PSA ≥0.2 ng/mL following RP; LRR and DM based on PSMA PET or conventional imaging, both by BICR, or histopathology.
1. Cornford P, et al. Eur Urol. 2026;S0302-2838(26)02114.
Presented by A Briganti at ESMO; October 23-27, 2026; Madrid, Spain
---
[Slide 2]
Baseline Characteristics Were Well Balanced
ITT population | Perioperative APA + ADT (n=102) | RP + PLND alone (n=306)
Median age (range), years | 66.0 (51-82) | 66.0 (45-84)
≥75, n (%) | 9 (8.8) | 31 (10.1)
Gleason score at initial diagnosis, n (%) 7 | 4 (3.9) | 8 (2.6)
Gleason ≥8 | 98 (96.1) | 298 (97.4)
Baseline PSA(a) Median (range), ng/mL | 14.1 (1.4-422.6)(b) | 14.2 (1.5-384.3)(c)
Baseline PSA <20, n (%) | 66 (65.3) | 183 (64.0)
Baseline PSA ≥20, n (%) | 35 (34.7) | 103 (36.0)
Tumor stage at diagnosis, n (%)(d) ≤cT2 | 69 (67.6) | 217 (70.9)
≥cT3 | 31 (30.4) | 86 (28.1)
Regional lymph node stage at diagnosis, n (%) cN0 | 94 (92.2) | 285 (93.1)
cN1 | 8 (7.8) | 21 (6.9)
• At clinical cutoff on 13 July 2026:
– Median follow-up - 37.8 months
– Patients still on the study - 94% (perioperative APA + ADT, n=96) and 89% (RP + PLND alone, n=306)
ITT, intent to treat.
a PSA before first dose was the closest value assessment on or prior to the start date for ADT or APA and the closest value assessment on or prior to the date of randomization for the RP + PLND alone group.
b n101. c n=286. d TX n=2 (APA + ADT); n=3 (RP + PLND alone).
Presented by A Briganti at ESMO; October 23-27, 2026; Madrid, Spain
---
[Slide 3]
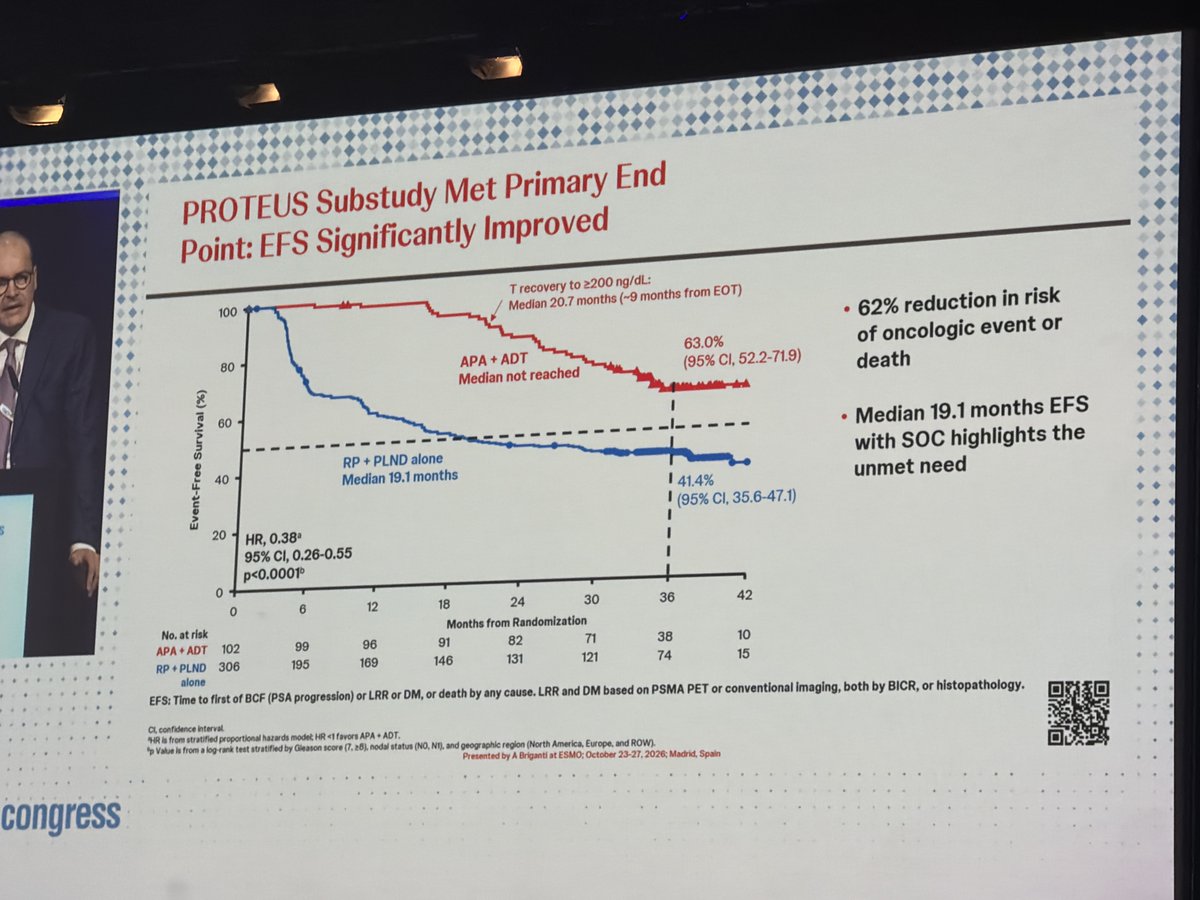
PROTEUS Substudy Met Primary End Point: EFS Significantly Improved
T recovery to ≥200 ng/dL: Median 20.7 months (~9 months from EOT)
APA + ADT Median not reached | 63.0% (95% CI, 52.2-71.9)
RP + PLND alone Median 19.1 months | 41.4% (95% CI, 35.6-47.1)
HR, 0.38(a) 95% CI, 0.26-0.55 p<0.0001(b)
• 62% reduction in risk of oncologic event or death
• Median 19.1 months EFS with SOC highlights the unmet need
EFS: Time to first of BCF (PSA progression) or LRR or DM, or death by any cause. LRR and DM based on PSMA PET or conventional imaging, both by BICR, or histopathology.
CI, confidence interval.
a HR is from stratified proportional hazards model; HR <1 favors APA + ADT.
b p Value is from a log-rank test stratified by Gleason score (7, ≥8), nodal status (N0, N1), and geographic region (North America, Europe, and ROW).
Presented by A Briganti at ESMO; October 23-27, 2026; Madrid, Spain
Event-free survival (EFS) — values printed on the slide
Arm
N
Median (95% CI)
Rate at 36 months (95% CI)
APA + ADT (perioperative)
102
Not reached
63.0% (52.2-71.9)
RP + PLND alone
306
19.1 months
41.4% (35.6-47.1)
HR 0.38 (95% CI 0.26-0.55); p<0.0001
Numbers at risk and axis ticks omitted; landmark rates are the values printed at the slide’s dashed landmark line. Data cut-off is not printed on this slide (the PROTEUS Substudy baseline-characteristics slide presented by A Briganti states clinical cutoff 13 July 2026).
---
[Slide 4]
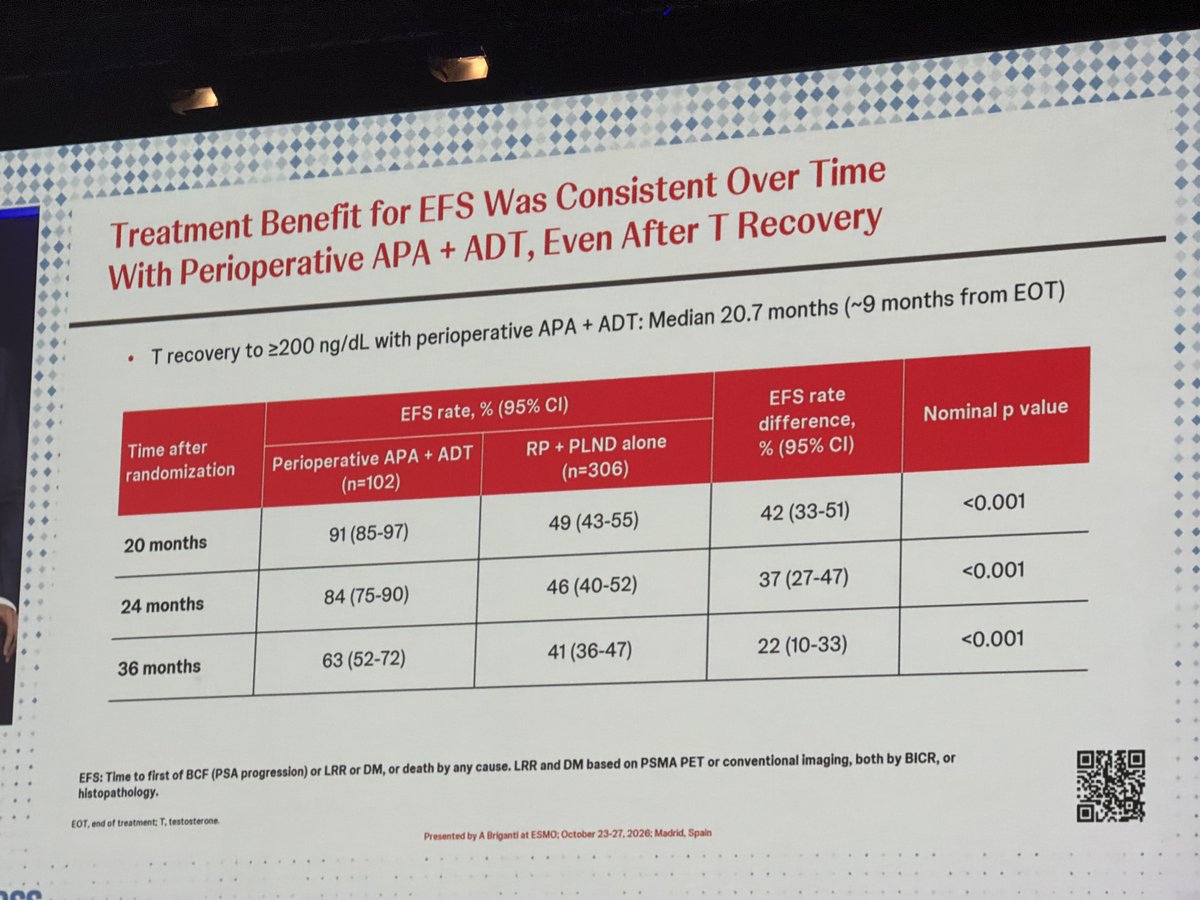
Treatment Benefit for EFS Was Consistent Over Time With Perioperative APA + ADT, Even After T Recovery
• T recovery to ≥200 ng/dL with perioperative APA + ADT: Median 20.7 months (~9 months from EOT)
Time after randomization | EFS rate, % (95% CI) Perioperative APA + ADT (n=102) | EFS rate, % (95% CI) RP + PLND alone (n=306) | EFS rate difference, % (95% CI) | Nominal p value
20 months | 91 (85-97) | 49 (43-55) | 42 (33-51) | <0.001
24 months | 84 (75-90) | 46 (40-52) | 37 (27-47) | <0.001
36 months | 63 (52-72) | 41 (36-47) | 22 (10-33) | <0.001
EFS: Time to first of BCF (PSA progression) or LRR or DM, or death by any cause. LRR and DM based on PSMA PET or conventional imaging, both by BICR, or histopathology.
EOT, end of treatment; T, testosterone.
Presented by A Briganti at ESMO; October 23-27, 2026; Madrid, Spain
[Slide 1]
No PSMA PET at diagnosis
EAU and ESMO recommendations for initial staging of prostate cancer
INITIAL STAGING BY RISK CATEGORY
Low / favourable intermediate: No routine metastatic imaging
Unfavourable intermediate: Consider PSMA PET/CT
High risk / locally advanced: PSMA PET/CT if available
WHY PSMA PET?
proPSMA: staging accuracy 92% PSMA PET vs 65% CT + bone scan
More sensitive detection of nodal and distant disease before radical treatment
PROTEUS enrolled conventionally staged M0 patients without baseline PSMA PET.
Nicholas van As
---
[Slide 2]
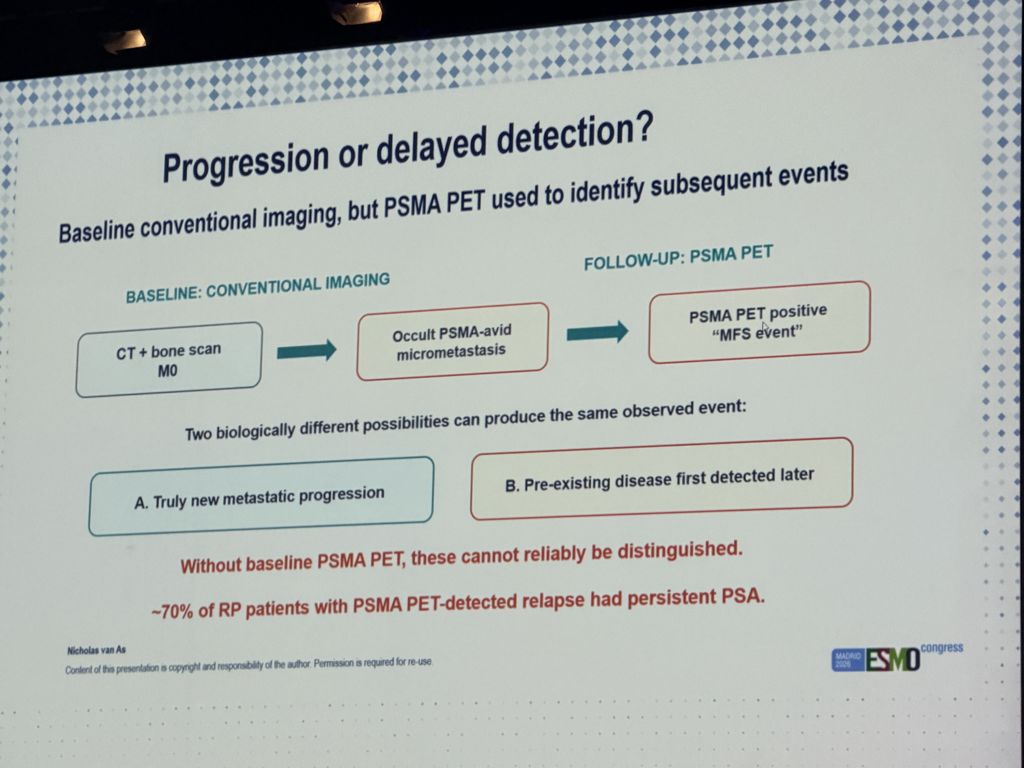
Progression or delayed detection?
Baseline conventional imaging, but PSMA PET used to identify subsequent events
BASELINE: CONVENTIONAL IMAGING | FOLLOW-UP: PSMA PET
CT + bone scan M0 → Occult PSMA-avid micrometastasis → PSMA PET positive "MFS event"
Two biologically different possibilities can produce the same observed event:
A. Truly new metastatic progression
B. Pre-existing disease first detected later
Without baseline PSMA PET, these cannot reliably be distinguished.
~70% of RP patients with PSMA PET-detected relapse had persistent PSA.
Nicholas van As
---
[Slide 3]
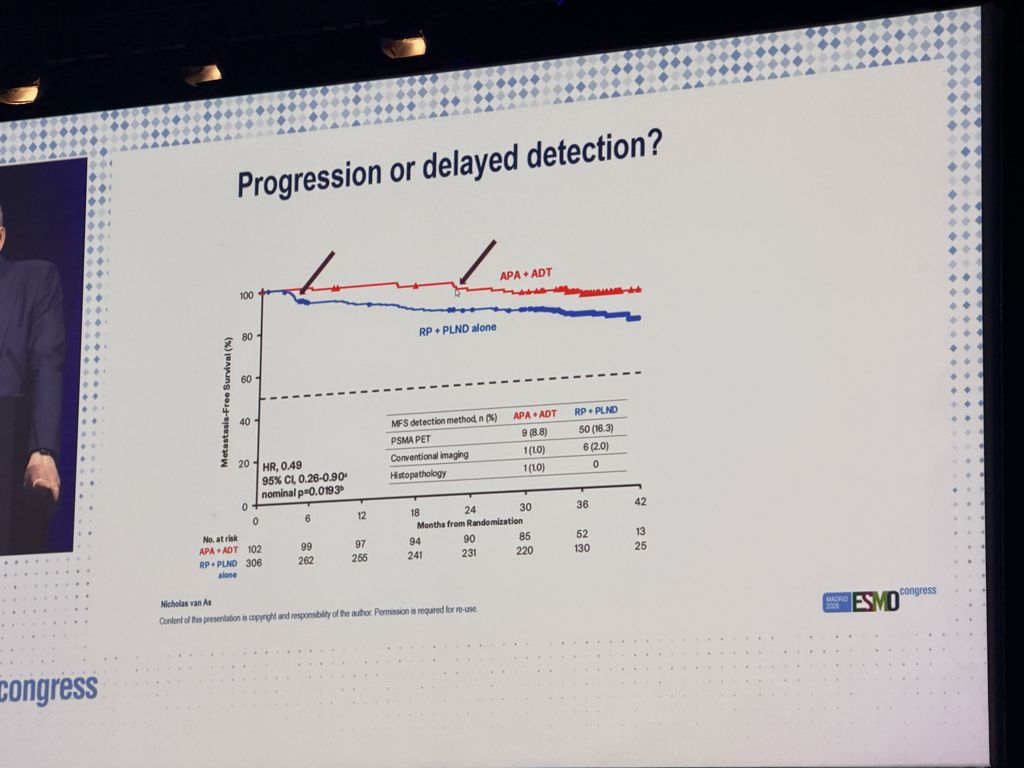
Progression or delayed detection?
APA + ADT
RP + PLND alone
Metastasis-Free Survival (%)
HR, 0.49
95% CI, 0.26-0.90^a
nominal p=0.0193^b
MFS detection method, n (%) | APA + ADT | RP + PLND
PSMA PET | 9 (8.8) | 50 (16.3)
Conventional imaging | 1 (1.0) | 6 (2.0)
Histopathology | 1 (1.0) | 0
Nicholas van As
Metastasis-free survival — values printed on the slide
Arm
N
Median (95% CI)
APA + ADT
102
Not printed
RP + PLND alone
306
Not printed
HR 0.49 (95% CI 0.26-0.90); nominal p=0.0193
Numbers at risk and axis ticks omitted; landmark rates are the values printed at the slide’s dashed landmark line. Data cut-off is not printed on this slide (the PROTEUS Substudy baseline-characteristics slide presented by A Briganti states clinical cutoff 13 July 2026).
---
[Slide 4]
Is avoiding subsequent treatment a patient benefit?
100% of these patients have already received a second + third treatment
Time to First Subsequent Therapy (%)
Median 46.0 months APA + ADT
Median 12.3 months RP + PLND alone
64.6% (95% CI, 54.1-73.3)
32.0% (95% CI, 26.7-37.5)
HR, 0.29
95% CI, 0.20-0.43
nominal p<0.001^b
• Postoperative RT is initiated by BCF
• 20% vs 43% at 3 years
• ....but there is an approximately 20 month lead time bias
Time to first subsequent therapy — values printed on the slide
Arm
N
Median (95% CI)
Rate at 36 mo (95% CI)
APA + ADT
102
46.0 months
64.6% (54.1-73.3)
RP + PLND alone
—
12.3 months
32.0% (26.7-37.5)
HR 0.29 (95% CI 0.20-0.43); nominal p<0.001
Numbers at risk and axis ticks omitted; landmark rates are the values printed at the slide’s dashed landmark line. Data cut-off is not printed on this slide (the PROTEUS Substudy baseline-characteristics slide presented by A Briganti states clinical cutoff 13 July 2026).
[Slide 1]
The PROTEUS Substudy Compared APA + ADT With RP + PLND vs RP + PLND Alone
• Immediate RP + PLND without neoadjuvant treatment, followed by subsequent adjuvant treatment based on physician's discretion, is used to reflect SOC based on current guideline recommendations1
N=408 | Patients with HR LPC/LAPC → RANDOMIZED 1:3
Perioperative open-label APA + ADT: Neoadjuvant (C1 through C6) APA (240 mg QD) + ADT → 2 wks → RP + PLNDa → 4 wks → Adjuvant (C7 through C12) APA (240 mg QD) + ADT
RP + PLND → Local standard institutional practice/observation
Randomization: 27 July 2022 to 16 October 2023
Stratification:
• cN0 vs cN1b
• Gleason score (7 vs 8-10)
• Region (North America, Europe, ROW)
Local or systemic adjuvant treatment based on physician's discretion and local standard institutional practice
Primary end point
• EFS: Time to first of BCF (PSA progression) or LRR or DM, or deathc
Secondary and exploratory end points include:
• MFS
• Time to first subsequent therapy
APA, apalutamide; BCF, biochemical failure; BICR, blinded independent central review; C, cycle; DM, distant metastases; EFS, event-free survival; LRR, local or regional recurrence; PSA, prostate-specific antigen; QD, daily; ROW, rest of the world.
aAPA + ADT is stopped 2 weeks prior to planned RP and then resumed 4 weeks after RP. Cardiovascular risk prophylaxis and venous thromboembolism prophylaxis given based on risk.
bBased on conventional imaging.
cBCF defined as 2 consecutive PSA rises ≥1 week apart, with the second test resulting in an absolute PSA ≥0.2 ng/mL following RP; LRR and DM based on PSMA PET or conventional imaging, both by BICR, or histopathology.
1. Cornford P, et al. Eur Urol. 2026;S0302-2838(26)02114.
Presented by A Briganti at ESMO; October 23-27, 2026; Madrid, Spain
---
[Slide 2]
PROTEUS Substudy Met Primary End Point: EFS Significantly Improved
T recovery to ≥200 ng/dL: Median 20.7 months (~9 months from EOT)
APA + ADT Median not reached | 63.0% (95% CI, 52.2-71.9) [at 36 months]
RP + PLND alone Median 19.1 months | 41.4% (95% CI, 35.6-47.1) [at 36 months]
HR, 0.38a
95% CI, 0.26-0.55
p<0.0001b
• 62% reduction in risk of oncologic event or death
• Median 19.1 months EFS with SOC highlights the unmet need
EFS: Time to first of BCF (PSA progression) or LRR or DM, or death by any cause. LRR and DM based on PSMA PET or conventional imaging, both by BICR, or histopathology.
CI, confidence interval.
aHR is from stratified proportional hazards model; HR <1 favors APA + ADT.
bp Value is from a log-rank test stratified by Gleason score (7, ≥8), nodal status (N0, N1), and geographic region (North America, Europe, and ROW).
Presented by A Briganti at ESMO; October 23-27, 2026; Madrid, Spain
Event-free survival (primary endpoint), PROTEUS substudy — values printed on the slide
Arm
N
Median (95% CI)
Rate at 36 months (95% CI)
APA + ADT (+ RP + PLND)
102
Not reached
63.0% (52.2-71.9)
RP + PLND alone
306
19.1
41.4% (35.6-47.1)
HR 0.38 (95% CI 0.26-0.55); p<0.0001
Numbers at risk and axis ticks omitted; landmark rates are the values printed at the slide’s dashed landmark line. Data cut-off is not printed on this slide (the PROTEUS Substudy baseline-characteristics slide presented by A Briganti states clinical cutoff 13 July 2026).
---
[Slide 3]
Perioperative APA + ADT Improved MFS by Conventional or PSMA PET Imaging (BICR)
SECONDARY END POINT
HR, 0.49a
95% CI, 0.26-0.90
nominal p=0.0193b
Metastasis detection method, n (%) | APA + ADT | RP + PLND
PSMA PET | 9 (8.8) | 50 (16.3)
Conventional imaging | 1 (1.0) | 6 (2.0)
Histopathology | 1 (1.0) | 0
• 51% reduction in risk of metastasis or death
• MFS by local investigator assessment:
• HR, 0.38a 95% CI, 0.22-0.66 nominal p=0.0004b
MFS: Time to first occurrence of distant metastasis on PSMA PET or conventional imaging by BICR, pathologic finding of distant metastasis, or death from any cause.
aHR is from stratified proportional hazards model; HR <1 favors APA + ADT.
bNominal p value is from a log-rank test stratified by Gleason score (7, ≥8), nodal status (N0, N1), and geographic region (North America, Europe, and ROW).
Presented by A Briganti at ESMO; October 23-27, 2026; Madrid, Spain
Metastasis-free survival by BICR (secondary endpoint), PROTEUS substudy — values printed on the slide
Arm
N
Median (95% CI)
APA + ADT
102
Not printed
RP + PLND alone
306
Not printed
HR 0.49 (95% CI 0.26-0.90); nominal p=0.0193
Numbers at risk and axis ticks omitted; landmark rates are the values printed at the slide’s dashed landmark line. Data cut-off is not printed on this slide (the PROTEUS Substudy baseline-characteristics slide presented by A Briganti states clinical cutoff 13 July 2026).
---
[Slide 4]
PROTEUS Substudy Conclusions
• Together with the PROTEUS main study, the PROTEUS Substudy supports 1-year perioperative APA + ADT as a treatment option for patients with HR LPC/LAPC fit for surgery and systemic therapy
• Perioperative APA + ADT improves disease control and gives patients a longer time before starting subsequent therapy
Enhanced Disease Control With Perioperative APA + ADT
• 62% lower risk of recurrence or death
• 51% lower risk of death or developing metastases over time
• ~50% fewer patients starting subsequent therapy by ~3 years
• >3× longer time to first subsequent therapy
Presented by A Briganti at ESMO: October 23-27, 2026; Madrid, Spain
[Slide 1]
Perioperative Apalutamide Plus Androgen Deprivation Therapy With Radical Prostatectomy Plus Pelvic Lymph Node Dissection (RP + PLND) vs RP + PLND Alone in Patients With High-Risk Localized or Locally Advanced Prostate Cancer (HR LPC/LAPC): PROTEUS Substudy
Alberto Briganti1, Thomas Steuber2, Neal D Shore3, Martin Gleave4, Alexander Kretschmer5, Lisa Wetherhold5, Eleni Efstathiou6, David J Cahn7, Ronaldo Damião8, Alexandre De La Taille9, Boris A Hadaschik10, Bernardo Herrera Imbroda11, Álvaro Juárez Soto12, Giuseppe Simone13, Zhuokai Li14, Sharon A McCarthy15, Mark Wildgust16, Suneel D Mundle16, Adam S Kibel17, Mary-Ellen Taplin18
[affiliations list - small print, largely illegible]
Presented by A Briganti at ESMO; October 23-27, 2026; Madrid, Spain
---
[Slide 2]
PROTEUS Substudy Met Primary End Point: EFS Significantly Improved
Event-Free Survival (%)
T recovery to ≥200 ng/dL: Median 20.7 months (~9 months from EOT)
APA + ADT
Median not reached
63.0%
(95% CI, 52.2-71.9)
RP + PLND alone
Median 19.1 months
41.4%
(95% CI, 35.6-47.1)
HR, 0.38a
95% CI, 0.26-0.55
p<0.0001b
• 62% reduction in risk of oncologic event or death
• Median 19.1 months EFS with SOC highlights the unmet need
EFS: Time to first of BCF (PSA progression) or LRR or DM, or death by any cause. LRR and DM based on PSMA PET or conventional imaging, both by BICR, or histopathology.
CI, confidence interval.
aHR is from stratified proportional hazards model; HR <1 favors APA + ADT.
bp Value is from a log-rank test stratified by Gleason score (7, ≥8), nodal status (N0, N1), and geographic region (North America, Europe, and ROW).
Presented by A Briganti at ESMO; October 23-27, 2026; Madrid, Spain
Event-free survival (primary endpoint) — values printed on the slide
Arm
N
Median (95% CI)
Rate at 36 months (95% CI)
APA + ADT (+ RP + PLND)
102
Not reached
63.0% (52.2-71.9)
RP + PLND alone
306
19.1 months
41.4% (35.6-47.1)
HR 0.38 (95% CI 0.26-0.55); p<0.0001
Numbers at risk and axis ticks omitted; landmark rates are the values printed at the slide’s dashed landmark line. Data cut-off is not printed on this slide (the PROTEUS Substudy baseline-characteristics slide presented by A Briganti states clinical cutoff 13 July 2026).
---
[Slide 3]
PROTEUS: a positive result, but significant limitations
EFS and MFS at 3 years median follow-up is too short
INITIAL STAGING | No baseline PSMA PET in a very-high-risk population
PRIMARY ENDPOINT | EFS includes biochemical failure during prolonged androgen suppression
MFS | PSMA PET-detected events complicate interpretation without baseline PET
TOXICITY | Significant increase in toxicity
COMPARATOR | RP alone versus multimodality care, or ADT +RT
Nicholas van As
---
[Slide 4]
Should practice change now?
I would not currently support perioperative apalutamide + ADT with radical prostatectomy in high-risk prostate cancer.
Longer follow-up, mature survival data and outcomes after salvage treatment are needed before changing practice.
Nicholas van As
[Slide 1]
Fewer Local/Regional Recurrence or Distant Metastasis Events With Perioperative APA + ADT
| Perioperative APA + ADT (n=102) | RP + PLND alone (n=306)
First event (denominator for events below), n (%) | 35/102 (34.3) | 172/306 (56.2)
Biochemical failure (BCF) | 27 (77.1) | 92 (53.5)
Local or regional recurrence by PSMA PET/conventional imaging | 4 (11.4) | 51 (29.7)
LRR by PSMA PET | 4 (11.4) | 50 (29.1)
LRR by PSMA PET without BCF | 4 (11.4) | 48 (27.9)
LRR by conventional imaging | 0 | 1 (0.6)
Distant metastasis by PSMA PET/conventional imaging/histopathology | 4 (11.4) | 28 (16.3)
DM by PSMA PET | 2 (5.7) | 24 (14.0)
DM by PSMA PET without BCF | 2 (5.7) | 23 (13.4)
DM by conventional imaging/histopathology | 2 (5.7) | 4 (2.3)
Death | 0 | 1 (0.6)
Censored, n (%) | 67/102 (65.7) | 134/306 (43.8)
• ~70% of PSMA PET–detected LRR/DM without BCF in the RP group were associated with PSA persistence (PSA ≥0.1 ng/mL) 3 months after RP
• Excluding patients (both arms) with PSMA PET–detected events (LRR or DM) without prior BCF: HR, 0.50; 95% CI, 0.33-0.76; p=0.001
Presented by A Briganti at ESMO; October 23-27, 2026; Madrid, Spain
---
[Slide 2]
SECONDARY END POINT
Perioperative APA + ADT Improved MFS by Conventional or PSMA PET Imaging (BICR)
HR, 0.49a 95% CI, 0.26-0.90 nominal p=0.0193b
Metastasis detection method, n (%) | APA + ADT | RP + PLND
PSMA PET | 9 (8.8) | 50 (16.3)
Conventional imaging | 1 (1.0) | 6 (2.0)
Histopathology | 1 (1.0) | 0
• 51% reduction in risk of metastasis or death
• MFS by local investigator assessment: HR, 0.38a 95% CI, 0.22-0.66 nominal p=0.0004b
MFS: Time to first occurrence of distant metastasis on PSMA PET or conventional imaging by BICR, pathologic finding of distant metastasis, or death from any cause.
aHR is from stratified proportional hazards model; HR <1 favors APA + ADT.
bNominal p value is from a log-rank test stratified by Gleason score (7, ≥8), nodal status (N0, N1), and geographic region (North America, Europe, and ROW).
Presented by A Briganti at ESMO; October 23-27, 2026; Madrid, Spain
Metastasis-free survival by BICR (secondary endpoint) — values printed on the slide
Arm
N
Median (95% CI)
Perioperative APA + ADT
102
Not printed
RP + PLND alone
306
Not printed
HR 0.49 (95% CI 0.26-0.90); nominal p=0.0193
Numbers at risk and axis ticks omitted; landmark rates are the values printed at the slide’s dashed landmark line. Data cut-off is not printed on this slide (the PROTEUS Substudy baseline-characteristics slide presented by A Briganti states clinical cutoff 13 July 2026).
---
[Slide 3]
EXPLORATORY END POINT
Time to First Subsequent Therapy Was Prolonged by ~3 Years With Perioperative APA + ADT
APA + ADT
Median 46.0 months
64.6%
(95% CI, 54.1-73.3 )
RP + PLND alone
Median 12.3 months
32.0%
(95% CI, 26.7-37.5)
HR, 0.29a
95% CI, 0.20-0.43
nominal p<0.0001b
• 71% reduced risk of starting subsequent therapy
• ~50% fewer patients started subsequent therapy by 3 years
Time to first subsequent therapy: Time from randomization to first local, regional, or systemic therapy, including reinitiation of ADT.
aHR is from stratified proportional hazards model; HR <1 favors APA + ADT.
bNominal p value is from a log-rank test stratified by Gleason score (7, ≥8), nodal status (N0, N1), and geographic region (North America, Europe, and ROW).
Presented by A Briganti at ESMO; October 23-27, 2026; Madrid, Spain
Time to first subsequent therapy (exploratory) — values printed on the slide
Arm
N
Median (95% CI)
Rate at 36 months (95% CI)
APA + ADT
—
46.0 months
64.6% (54.1-73.3)
RP + PLND alone
—
12.3 months
32.0% (26.7-37.5)
HR 0.29 (95% CI 0.20-0.43); nominal p<0.0001
Numbers at risk and axis ticks omitted; landmark rates are the values printed at the slide’s dashed landmark line. Data cut-off is not printed on this slide (the PROTEUS Substudy baseline-characteristics slide presented by A Briganti states clinical cutoff 13 July 2026).
KOL-Made Infographics
Summary graphics designed by physicians (secondary commentary, not presented slides). Click to expand.
Slides from ESMO 2026 (Madrid) as photographed and shared on X by physicians, newest first. Each post is shown verbatim; click any slide to enlarge, and open the OCR text under each post. All ESMO 2026 PROTEUS slides in the KOL Pulse slide library →
PROTEUS Substudy: Perioperative Apalutamide + ADT with RP + PLND vs RP + PLND Alone in
High-Risk Localized or Locally Advanced
Prostate Cancer. Presented by @Albert0Briganti . #ESMO26 https://t.co/zEHimrns6A
[Slide 1]
The PROTEUS Substudy Compared APA + ADT With RP + PLND vs RP + PLND Alone
• Immediate RP + PLND without neoadjuvant treatment, followed by subsequent adjuvant treatment based on physician's discretion, is used to reflect SOC based on current guideline recommendations
N=408
Patients with HR LPC/LAPC → RANDOMIZED 1:3
Perioperative open-label APA + ADT: Neoadjuvant (C1 through C6) APA (240 mg QD) + ADT → 2 wks → RP + PLNDa → 4 wks → Adjuvant (C7 through C12) APA (240 mg QD) + ADT
RP + PLND → Local standard institutional practice/observation
Local or systemic adjuvant treatment based on physician's discretion and local standard institutional practice
Primary end point: EFS: Time to first of BCF (PSA progression) or LRR or DM, or deathc
Secondary and exploratory end points include: MFS; Time to first subsequent therapy
Stratification: cN0 vs cN1b; Gleason score (7 vs 8-10); Region (North America, Europe, ROW)
Randomization: 27 July 2022 to 16 October 2023
Presented by A Briganti at ESMO; October 23-27, 2026; Madrid, Spain
More slides on this page
Slides shared by KOLs at the ASCO 2026 Plenary (presented by Mary-Ellen Taplin, MD — Dana-Farber). Click any image to expand; expand “View OCR Text” for the full slide text.
New · ASCO 2026 Plenary Readout
PROTEUS primary results presented May 31, 2026. Perioperative apalutamide + ADT met both dual primary endpoints — pCR/MRD 8.9% vs 1.0% (OR 10.17, p<0.0001) and MFS HR 0.80 (95% CI 0.67–0.96, p=0.02). Overall survival, an exploratory endpoint, showed no benefit (HR 1.08). The KOL slide decks below capture the schema, dual-primary, EFS/distant-metastasis, safety, and conclusions slides.
2026
ASCO
ANNUAL MEETING
Perioperative (Neoadjuvant and Adjuvant) Apalutamide
+ ADT vs Placebo + ADT With Radical Prostatectomy
in High-Risk Localized or Locally Advanced Prostate
2026
ASC
ANNUAL MEETI
Cancer: Final Analysis of the PROTEUS Phase 3 Study
Mary-Ellen Taplin1, Martin Gleave², Neal D Shore³, Angela Lopez⁴, Alexander Kretschmer⁵, Eleni Efstathiou®,
Ronaldo Damião⁷, Toshiyuki Kamoto®, Ashley Ross®, Alberto Briganti10, Boris A Hadaschik11, Axel Heidenreich12,
Alvaro Juarez Soto13, Brendan Rooney14, Shaozhou Ken Tian⁵, Lisa Wetherhold5, Branko Miladinovic15,
Sharon McCarthy5, Christopher P Evans16, Adam S Kibel17
Lank Center for Destroutery Cologe Institute, Beston, MA USA Department of of C,
Myttle
Beach,
SC,
Johnson
Admin,
LOS
Angeles,
CA,
I
1.
I
House,
PA,
I
8
Re
L
of
Consortium
Case, High Nycombe, UK Diego, CA USA, Remove NV, MA,
2026 ASCO
#ASCO26
Mary Elien Tapin MO, FASCO
ASCO
ANNUAL MEETING
- CONSULTS
Perioperative (Neoadjuvant and Adjuvant) Apalutamide
ADT vs Placebo + ADT With Radical Prostatectomy
in High-Risk Localized or Locally Advanced Prostate
Cancer: Final Analysis of the PROTEUS Phase 3 Study
0
ASCO
---
PROTEUS: A Randomized, Double-Blind, Placebo-
Controlled Phase 3 Study in HR-LPC
Post
N=2109
Neoadjuvant
Adjuvant
treatment
(C1 through C6)
(C7 through C12)
M A R D N D Z E I
2
4
APA
wks
wks
APA
(240 mg QD)
(240 mg QD)
+ ADT
+ ADT
PSMA-PET (3 months after EOT)
Patients With
RPª
PSA every 3 months
2026ASCO
HR-LPC
+
Conventional and PSMA-PET
ADT
ANNUAL MEETING
Imaging at BCF (PSA >0.2 ng/mL);
PBO + ADT
PBO + ADT
every 6 months thereafter
1:1
Stratification:
Adjuvant or salvage RT
cN0 vs N1
post-RP at investigator's
Gleason score (7 vs 8-10)
discretion
Region (North America, Europe, ROW)
To complement these data, a substudy is ongoing to further inform on the role of APA + ADT + RP versus RP alone
Patients randomized from July 15, 2019, to June 30, 2022.
Protocol Amendment 7 for including PSMA-PET into MFS assessment (April 14, 2022).
APA, apalutamide; BCF, biochemical failure; C, cycle; EOT, end of treatment; PBO, placebo; PSA, prostate-specific antigen; PSMA-PET, prostate-specific membrane antigen positron emission tomography, QD, daily;
ROW, rest of the world; RT, radiation therapy.
APA/PBO is stopped 2 weeks prior to planned RP and then resumed 4 weeks after RP. Cardiovascular risk prophylaxis and venous thromboembolism prophylaxis given based on risk,
2026 ASCO
#ASCO26
PRE SENTED BY: Mary-Ellen Taplin, MD, FASCO
ASCO
- SECETY OF
I
ANNUAL MEETING
the
registration
KNOWLEDGE CONQUERS CANCER
-
---
PRIMARY END POINT
Dual Primary End Point Met:
MFS by Conventional or PSMA-PET Imaging
100
APA + ADT
20% reduction in the
80
risk of metastasis or
MFS (%) Assessed by BICR
PBO + ADT
death after 1 year
60
of perioperative APA +
ADT with RP by BICR
2026ASCO
40
ANNUAL MEETING
20
HR, 0.80a
95% CI, 0.67-0.96
Investigator-assessed
p=0.02b
MFS was consistent:
0
0
12
24
36
48
60
72
84
HR, 0.74;
No. at risk
Months Since Randomization
95% Cl, 0.62-0.87;
APA + ADT
1057
992
922
837
659
382
62
0
p=0.0004
PBO + ADT
1052
1000
924
812
634
385
61
0
MFS: Time to first occurrence of radiographic distant metastasis based on conventional imaging or PSMA-PET imaging, pathologic finding of distant metastasis,
or death from any cause
Hazard ratio (HR) is from stratified proportional hazards model HR <1 favors APA ADT.
P Value is from a log-rank test stratified by Gleason score (7, 28), nodal status (NO, N1), geographic region (North America, Europe, and rest of the world).
2026 ASCO
PRESENTED en Mary-Ellen Taplin, MD, FASCO
ASCO
#ASCO26
ANNUAL MEETING
KNOWLEDGE CONDUERS CANCER
I
the
-
---
Conclusions
PROTEUS sets a new standard of care in HR-LPC
Unprecedented
Enhanced Disease
Known Safety
More to Come
Study Design
Control of RP
Profile
2026ASCO
Significant benefit:
Substudy comparing
ANNUAL MEETING
9x greater pCR/MRD
with direct RP
Largest size to date
20% less risk of MFS
Tolerability of
Biomarker
Novel end points
29% less risk of
APA+ADT consistent
assessment
PSMA-PET inclusion
recurrence or death
with prior studies
Surgical outcomes
3 years longer time
Pathology correlates
to next treatment
2026 ASCO
#ASCO26
PRESENTED am Mary-Ellen Taplin, MD, FASCO
ASCO
-
- INCOLOGY
ANNUAL MEETING
Presentation - of - euthor and ASCO - - for - contact -
KNOWLEDGE CONQUERS CANCER
Dual Primary End Point Met: pCR/MRD
PRIMARY END POINT
12
8.9%
9-fold improvement in
10
OR, 10.17
pCR/MRD at RP after
pCR/MRD (%) by Pathology-BICR
95% CI, 5.27-19.64
6-cycle neoadjuvant
8
p<0.0001a
APA + ADT
vs PBO + ADT
6
Exploratory end point of RCB
4
(SypT2, NO, ≤0.25 cm3)
5.1% ypTo
corroborates pCR/MRD:
2
1.0%
APA + ADT vs PBO + ADT,
T
30.6% vs 11.7%
0
0.4% Урто
APA + ADT
OR, 3.36;
PBO + ADT
94/1057
10/1052
95% CI, 2.67-4.23;
p<0.0001
pCR/MRD: Minimal residual tumor ≤5 mm (greatest dimension of largest tumor lesion) in prostate-confined disease (sypT2, NO) or no tumor identified (ypTo)
RCB: Residual cancer burden ≤0.25 cm3 in prostate-confined disease (sypT2, NO)
Error bars indicate 95% confidence intervals (Cls). Odds ratio (OR) is from a logistic regression adjusted for stratification factor, OR favors APA + ADT.
P Value is based on Cochran-Mantel-Haenszel test stratified by Gleason score (7, ≥8), nodal status (ND, N1), geographic region (North America, Europe, and rest of the world).
2026 ASCO
#ASCO26
PRESENTED BY: Mary-Ellen Taplin, MD, FASCO
ASCO
-
GREA -
ANNUAL MEETING
Presentation is property of to author and ASCO Permission required by INSI, contact
KNOWLEDGE CONDUERS CANCER
PROTEUS: A Randomized, Double-Blind, Placebo-
Controlled Phase 3 Study in HR-LPC
Post
N=2109
Neoadjuvant
Adjuvant
treatment
(C1 through C6)
(C7 through C12)
M A O N R D D Z E I
2
4
APA
wks
wks
APA
(240 mg QD)
(240 mg QD)
+ ADT
RPª
+ ADT
PSMA-PET (3 months after EOT)
Patients With
PSA every 3 months
HR-LPC
+
Conventional and PSMA-PET
ADT
imaging at BCF (PSA >0.2 ng/mL);
PBO + ADT
PBO + ADT
every 6 months thereafter
1:1
Stratification:
Adjuvant or salvage RT
cN0 vs N1
post-RP at investigator's
Gleason score (7 vs 8-10)
discretion
Region (North America, Europe, ROW)
To complement these data, a substudy is ongoing to further inform on the role of APA + ADT + RP versus RP alone
Patients randomized from July 15, 2019, to June 30, 2022.
Protocol Amendment 7 for including PSMA-PET into MFS assessment (April 14, 2022).
APA, apalutamide; BCF, biochemical failure; C, cycle; EOT, end of treatment; PBO, placebo; PSA, prostate-specific antigen; PSMA-PET, prostate-specific membrane antigen positron emission tomography; QD, daily;
ROW, rest of the world; RT, radiation therapy.
*APA/PBO is stopped 2 weeks prior to planned RP and then resumed 4 weeks after RP. Cardiovascular risk prophylaxis and venous thromboembolism prophylaxis given based on risk.
2026 ASCO
#ASCO26
PRESENTED BY: Mary-Ellen Taplin, MD, FASCO
ASCO
AMERICAN SOCIETY OF
CUNICAL ONCOLOGY
ANNUAL MEETING
Presentation is property of the author and ASCO Permission required for reuse, contact permissions@asco.org
KNOWLEDGE CONQUERS CANCER
---
KEY SECONDARY END POINT
Event-Free Survival
100
29% reduction in the
80
APA + ADT
risk of oncologic event
Event-Free Survival (%)
57.1 months
or death
60
40
38.4 months
20
HR, 0.71
PBO + ADT
95% CI, 0.63-0.80ᵃ
p<0.0001b
0
0
12
24
36
48
60
72
84
No. at risk
Months Since Randomization
APA + ADT
1057
988
788
625
452
246
45
0
PBO + ADT 1052
952
699
522
382
223
48
0
EFS: Time to first of BCF (PSA progression) or local or regional recurrences or distant metastasis, or death by any cause
"HR is from stratified proportional hazards model; HR <1 favors APA . ADT.
to Value is from a log-rank test stratified by Gleason score (7, 28), nodal status (NO, N1), geographic region (North America, Europe, and rest of the world).
2026 ASCO
#ASCO26
PRS SENTED - Mary-Ellen Taplin, MD, FASCO
ASCO
FUERCIAN OF
CURRICAL -
ANNUAL MEETING
Presentation a property of the - and ASCO Permission required for - contact
KNOWLEDGE CONQUERS CANCER
---
SECONDARY END POINT
Frequency of Treatment-Related Adverse Events
APA + ADT
PBO + ADT
Safety Population, n (%)
(n=1050)
(n=1050)
All grades
Treatment-related AE
1000 (95.2)
985 (93.8)
Treatment-related AEs
289 (27.5)
198 (18.9)
Grade 3/4
Treatment-related AEs leading to dose reduction
118 (11.2)
24 (2.3)
Treatment-related AEs leading to dose interruption®
126 (12.0)
46 (4.4)
All grades
Treatment-related AEs leading to deathᵇ
7 (0.7)
1 (0.1)
AC, adverse event.
Treatment-related AEs are those that occurred on or after the first dose of study drug through the last dose of study treatment . 30 days or prior to the start of subsequent therapy, whichever is earlier,
or any AR that is considered treatment related regardless of the start date of the event. An AE is categorized as related If assessed by the Investigator as possibly, probably, or very likely related to study drug
(apalutamide or placebo), ADT, or RP.
AES leading to treatment interruption or dose reduction are based on AE action taken. Pincludes grade 5 events; AEs leading to death are based on AS outcome of tatal.
2026 ASCO
#ASCO26
PRI SENTED - Mary-Ellen Taplin, MD. FASCO
ASCO
- OF
CERTICAL
ANNUAL MEETING
Presentation - property of the author and ASCO Permission required - - -
KNOWLEDGE CONQUERS CANCER
---
Conclusions
PROTEUS sets a new standard of care in HR-LPC
Unprecedented
Enhanced Disease
Known Safety
More to Come
Study Design
Control of RP
Profile
Significant benefit:
Substudy comparing
9x greater pCR/MRD
with direct RP
Largest size to date
20% less risk of MFS
Tolerability of
Biomarker
Novel end points
APA+ADT consistent
29% less risk of
assessment
PSMA-PET inclusion
recurrence or death
with prior studies
Surgical outcomes
3 years longer time
Pathology correlates
to next treatment
2026 ASCO
#ASCO26
PRI SENTED BY Mary-Ellen Taplin, MD. FASCO
ASCO
**** - SOCIETY or
CURRICAL -
ANNUAL MEETING
I a 1 I person . I I . I
KNOWLEDGE CONQUERS CANCER
High-risk MO prostate cancer: two intensification paths
PROTEUS vs STAMPEDE: informative, not head-to-head
PROTEUS
STAMPEDE
Aspect
Apalutamide + RP
Abiraterone + RT
Local therapy
Radical prostatectomy
Prostate ± pelvic radiotherapy
ARPI & duration
Apalutamide
Abiraterone (± enzalutamide)
~12 months perioperative
for 2 years
Population
High-risk localized / locally advanced
High-risk MO
surgery candidates
often N+ or very high PSA/T-stage/Gleason
MFS benefit
5-year: 78.2% vs 73.5%
6-year: 82% VS 69%
~4.7% absolute
~13% absolute; HR 0.53
os immature / not highlighted
Clear OS benefit
os benefit
EFS and delayed therapy improved
HR 0.60; ~9-10% absolute at 6 years
Other key win
Major pathological response
Strong gains in PCa-specific survival
8.9% vs 1.0%
and PFS
Toxicity
More grade 3-4 AEs
More grade 3-4 AEs
mainly rash
acceptable in context
Clinical take-home
Both trials support AR pathway intensification with definitive local therapy.
The key question is not which trial wins, but which path best fits which patient.
Not a head-to-head comparison: differences in design, risk, local therapy, drug duration, and follow-up limit direct comparison.
Trial Design
PROTEUS Trial Design
PROTEUS (NCT03767244) is a Johnson & Johnson / Janssen-sponsored Phase 3 randomized, double-blind, placebo-controlled study of the androgen receptor pathway inhibitor apalutamide (Erleada) plus ADT versus placebo plus ADT, administered before and after radical prostatectomy (perioperative) in patients with newly diagnosed high-risk localized or locally advanced prostate cancer. The rationale: combining intensified systemic androgen-pathway blockade with surgery — an approach already standard in other aggressive solid tumors — to deepen pathologic response and delay metastasis. The trial enrolled 2,109 patients across more than 200 sites in 18 countries. Principal investigator: Mary-Ellen Taplin, MD, FASCO (Dana-Farber Cancer Institute / Harvard); co-led with Adam Kibel, MD (Brigham). Presented at the ASCO 2026 Plenary Session on May 31, 2026, with simultaneous publication in the New England Journal of Medicine.
Study Design
Phase 3 randomized double-blind placebo-controlled multicenter study (200+ sites, 18 countries). Dual primary endpoints assessed by blinded independent central review. Both endpoints met. Median follow-up 61.7 months.
Population
Newly diagnosed high-risk localized or locally advanced prostate cancer, candidates for radical prostatectomy. n=2109. All participants underwent protocol-defined radical prostatectomy.
Dual primary: pathologic complete response/minimal residual disease (pCR/MRD, defined ypT0 or ypT2 with ≤5 mm residual) and metastasis-free survival (MFS, by conventional or PSMA-PET imaging, histopathology, or death). Exploratory: overall survival, safety. (MFS captured both conventional and PSMA-PET imaging, reflecting staging-technology evolution over the trial's long enrollment window.)
PROTEUS (NCT03767244) is a Phase 3 randomized, double-blind trial in 2,109 patients of perioperative apalutamide (Erleada) plus ADT versus placebo plus ADT around radical prostatectomy in high-risk localized or locally advanced prostate cancer, presented as an ASCO 2026 Plenary. See Trial Design.
What did PROTEUS show for its dual primary endpoints?
PROTEUS met both co-primary endpoints, pathologic complete response/MRD and metastasis-free survival (HR 0.80). Figures, secondary endpoints and sources: At a Glance.
Did PROTEUS improve overall survival?
No. Overall survival was an exploratory, non-powered endpoint and showed no benefit (HR 1.08). See At a Glance.
Is perioperative apalutamide FDA approved for localized prostate cancer?
No. Perioperative use in high-risk localized or locally advanced disease is investigational; apalutamide is FDA approved for nmCRPC and mCSPC. See At a Glance.
What is the safety profile in PROTEUS?
Grade 3 or 4 adverse events were more frequent with apalutamide, driven mainly by rash, a known apalutamide class effect; no new safety signals were reported. Rates: At a Glance.
Coverage
Media Coverage & Primary Sources
Primary publication and verified coverage of the PROTEUS ASCO 2026 Plenary readout. Sources reconciled against the trial’s clinical-intelligence notebook.
 𝕏
 𝕏
 𝕏
 𝕏
 𝕏
 𝕏
 𝕏
 𝕏
 𝕏
 𝕏