● LIVE #ESMO26 live from Madrid, Oct 23–27 — today’s highlights, trending trials and physician reactions Follow ESMO 2026 live →
KOL Pulse · AI-Native Trial Intelligence

DeLLphi-305 Trial

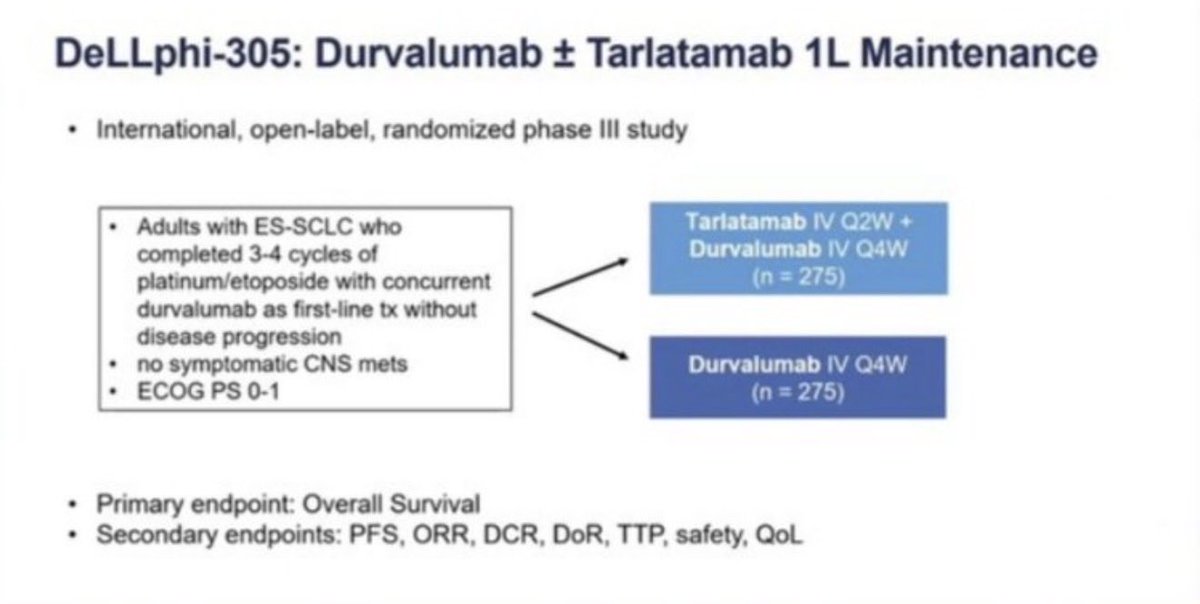
DeLLphi-305 (NCT06211036) is the global Phase 3 trial of tarlatamab (IMDELLTRA, Amgen) plus durvalumab (Imfinzi, AstraZeneca) versus durvalumab alone as first-line maintenance in extensive-stage small cell lung cancer (N=563). Primary analysis (ESMO 2026 LBA3 and NEJM, Oct 24, 2026): median overall survival 21.1 vs 12.7 months, HR 0.42 (95% CI 0.32–0.54), P<0.001, at a prespecified interim analysis (data cut-off July 7, 2026). The 1L combination is investigational; tarlatamab is FDA-approved in the second-line setting.

Phase 3 · NCT06211036 ES-SCLC · 1L maintenance ESMO 2026 LBA3: OS HR 0.42 (DCO Jul 7, 2026) ⚠ 1L combination investigational ✅ Tarlatamab FDA-approved 2L+ (full, Nov 2025)
See the KOL Reaction

ESMO 2026 physician reactions

Posts by physicians about DeLLphi-305 during ESMO 2026 week (October 17–25, 2026). Each post is shown in full and verbatim, newest first, and linked to the original on X.

Masahiro TORASAWA, MD. PhD.
Masahiro TORASAWA, MD. PhD.@M_Torasawa
𝕏

"Equitable access to cross-over: at time of POD, only 12.2% of ITT population in the durvalumab arm (34/278) and 18.9% (34/179) of those who received subsequent anti-cancer therapies had access to tarlatamab." @drshieldsmd https://t.co/PuYlaxfI4q https://t.co/RDMQKqGIMK

1.7K views 7 likes2 RT 2026-10-25
Misty Dawn Shields
Misty Dawn Shields@drshieldsmd
𝕏

Today, the Phase 3 results of DeLLphi-305 (@AmgenOncology @AstraZeneca) were presented by @sands_jacob at #ESMO26. DeLLphi-305 delivered an unprecedented OS improvement (21.1 vs 12.7 mo, HR 0.42) for patients receiving tarlatamab + durvalumab, compared to durvalumab alone, in 1L maintenance after chemoIO induction for ES-SCLC. Studies like these provide renewed hope. However, this data brings forth multiple concerns regarding international access to care, interpretation of contribution of parts, patient selection, and sequencing. 1️⃣ Equitable access to cross-over: at time of POD, only 12.2% of ITT population in the durvalumab arm (34/278) and 18.9% (34/179) of those who received subsequent anti-cancer therapies had access to tarlatamab. This speaks to the global need to expand access to this life-saving therapy, as DeLLphi-301 demonstrated this impact with accessibility promptly available here in the USA as early as May 2024. Yet, @SclcSMASHERS all over the world still do not have this option even at relapse. 2️⃣ Line of therapy: while attrition to 2L may be significant in some practices & highlights the need to maximize proactive support & early palliative care, is there clear evidence of synergy with ICI+DLL3 TCE to transform outcomes, or is the effect additive? Preclinical data suggested synergy with this combination approach. However, within subgroup analyses of those receiving tarlatamab in subsequent treatment, particularly in the USA, it appears there is signal of additivity, given the nullification of OS benefit with DLL3 TCE cross-over (in those receiving it as 2nd LOT). Outside of risk of attrition, what variables favor using tarlatamab in 1LM vs 2L? Is the NE biology still preserved? Is the function of the immune system equivalently preserved following <4 weeks post chemoIO with myelosuppression? 3️⃣ Patient selection: Stratification with effective predictive biomarkers are key to know who can avoid any intensification, as they may be a durable ICI responder to monotherapy ICI. Who can we avoid tarlatamab every 2 weeks indefinitely? Who should receive lurbi + atezo? Or durva + tarla? More translational SCLC based biomarkers, beyond DLL3, are clearly of high unmet need to guide strategies. 4️⃣ Sequencing: if we use tarlatamab+durvalumab in the 1LM, what’s next? At POD, what approved option remains? Lurbi remains approved in the 1LM, but not at relapse. I-DXd BLA was voluntarily withdrawn. Trials are key, but enrollment for most global studies is brisk, particularly in the USA where enrollment is ~20% or less of the total cohort. @SclcSMASHERS @LUNGevity @IASLC @ASCO @NCCN @LungCancerEu @lcrf_org @OncBrothers @OncoAlert @oncodaily @OncLive @lungoncdoc @RManochakian @LauraAlderMD @LaurenByersMD @Annechiangmd

2.8K views 27 likes12 RT 2026-10-24
Patrick Forde
Patrick Forde@FordePatrick
𝕏

DeLLphi-305 - tarlatamab added to durvalumab after initial chemo-immunotherapy for small lung cancer essentially doubles survival. Hope for all cancers here, if the right target & treatment modality can be refined. Unquestionably a new standard for this disease. #ESMO2026 https://t.co/8ovQ2yB6fr

1.2K views 31 likes11 RT 2026-10-24
Aakash Desai
Aakash Desai@ADesaiMD
𝕏

#ESMO26 DeLLphi-305: tarlatamab+durva vs durva, 1L maintenance ES-SCLC ➡️ OS 21.1 vs 12.7 mo, HR 0.42 ➡️ PFS 7.4 vs 1.9 mo, HR 0.34 ➡️ CRS 49.6% (G3+ 0.4%) Amazing to be part of this practice-changing study on the global steering committee!! @LungCancerRx @OncoAlert @oncodaily https://t.co/BfjokrDpim

1.2K views 31 likes14 RT 2026-10-24
Hidehito HORINOUCHI
Hidehito HORINOUCHI@HHorinouchi
𝕏

🆙#ESMO26 Presidential Symposium I: #LCSM 🔥DeLLphi-305: Tarlatamab Plus Durvalumab (Durva) vs Durva as 1L Maintenance (1LM) Therapy Following Durva, Platinum, and Etoposide in Extensive-Stage Small Cell Lung Cancer (ES-SCLC): Primary Analysis of the Phase 3 Trial 🎙️ @sands_jacob 🔢LBA3 🎯Met Primary Endpoint: Significantly Improved OS 🎯mOS 21.1 vs 12.7m, HR 0.42 🎯mPFS 7.4 vs 1.9m, HR 0.34 🎯ORR 26.4% vs 4.1% 🎯CRS 49.6% (Mostly Low Grade), No Fatal Events ☑️NCT06211036 🔗 https://t.co/Lb6tzuMm0z @OncoAlert @Larvol @myESMO @IASLC

1.1K views 15 likes4 RT 2026-10-24
Toni Choueiri, MD
Toni Choueiri, MD@DrChoueiri
𝕏

JUST IN: DeLLphi-305: Small Cell Lung Cancer Extensive-Stage Phase III (n=563): Tarlatamab + Durvalumab vs Durvalumab as 1L maintenance after chemo-IO, to be presented by our own @sands_jacob from @DanaFarber • Median OS: 21.1 vs 12.7 months (HR 0.42) • Median PFS: 7.4 vs 1.9 months (HR 0.34) • ORR: 26.4% vs 4.1% Grade ≥3 AEs: 46.8% vs 40.6%; CRS 49.6% (most low grade). Probably new standard of care in ES-SCLC. @OncoAlert @DanaFarberNews #ESMO26

983 views 17 likes13 RT 2026-10-24
Alfredo Addeo MD
Alfredo Addeo MD@Alfdoc2
𝕏

🔥 TODAY COULD BE ONE OF THE DEFINING MOMENTS OF #ESMO26! 🔥 The ESMO Presidential Symposium is always one of the highlights of the congress, and today’s session promises some truly extraordinary science! If I had to pick ONE study with the greatest potential to change clinical practice at ESMO 2026, my choice would be DeLLphi-305. For decades, SCLC has been one of the most challenging diseases in oncology, with far too little progress and far too few therapeutic breakthroughs. Could DeLLphi-305 finally represent the major leap forward we have been waiting for? We already know that adding tarlatamab to durvalumab as first-line maintenance significantly improves OS compared with durvalumab alone. But today, we will finally see the numbers. And I am genuinely excited to discover just how transformative this benefit might be! My personal bet for the biggest breakthrough of #ESMO26? DeLLphi-305. @StephenVLiu @sands_jacob Of course, the magnitude of survival benefit, safety and clinical applicability will ultimately determine its impact. But the potential is enormous. Don’t miss today’s Presidential Symposium! Madrid | 🕟 16:30 CEST Alicante auditorium #ESMO26 #ESMOAmbassador #SCLC #LungCancer #Immunotherapy #Oncology #PracticeChanging

896 views 20 likes5 RT 2026-10-24
MV Chandrakanth
MV Chandrakanth@ChandrakanthMv
𝕏

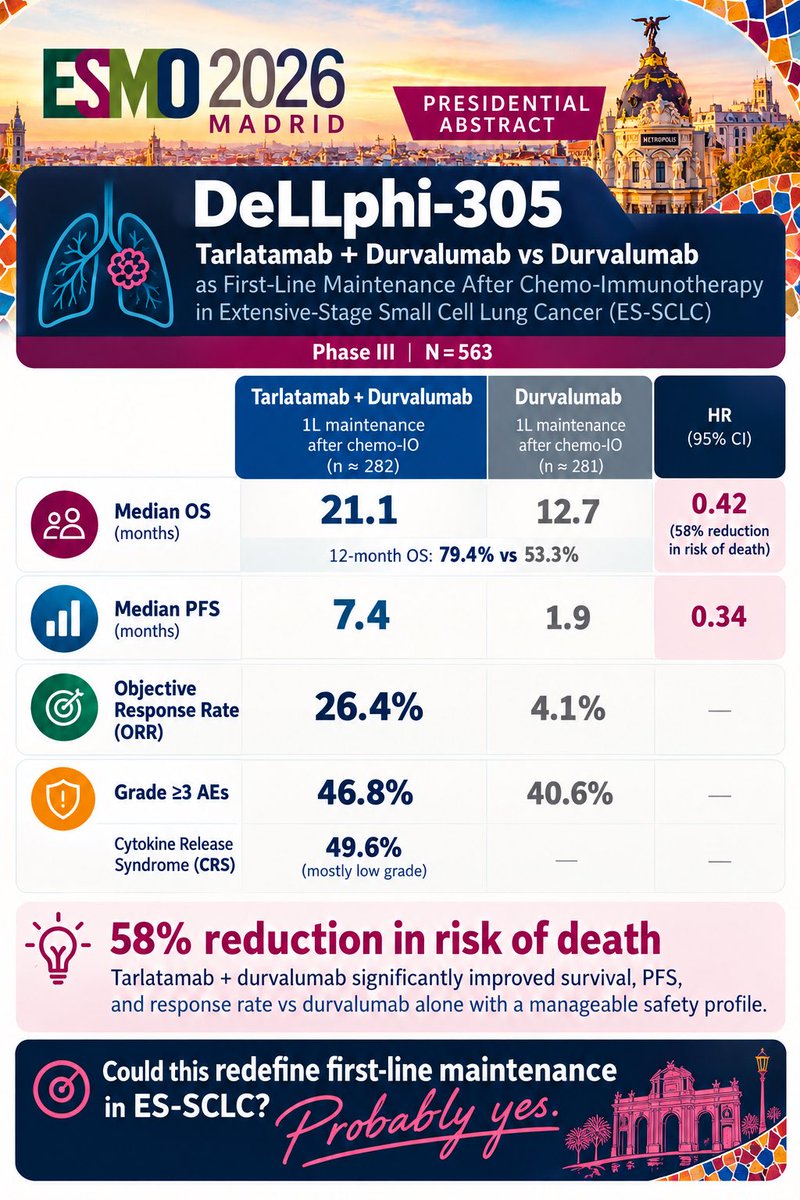
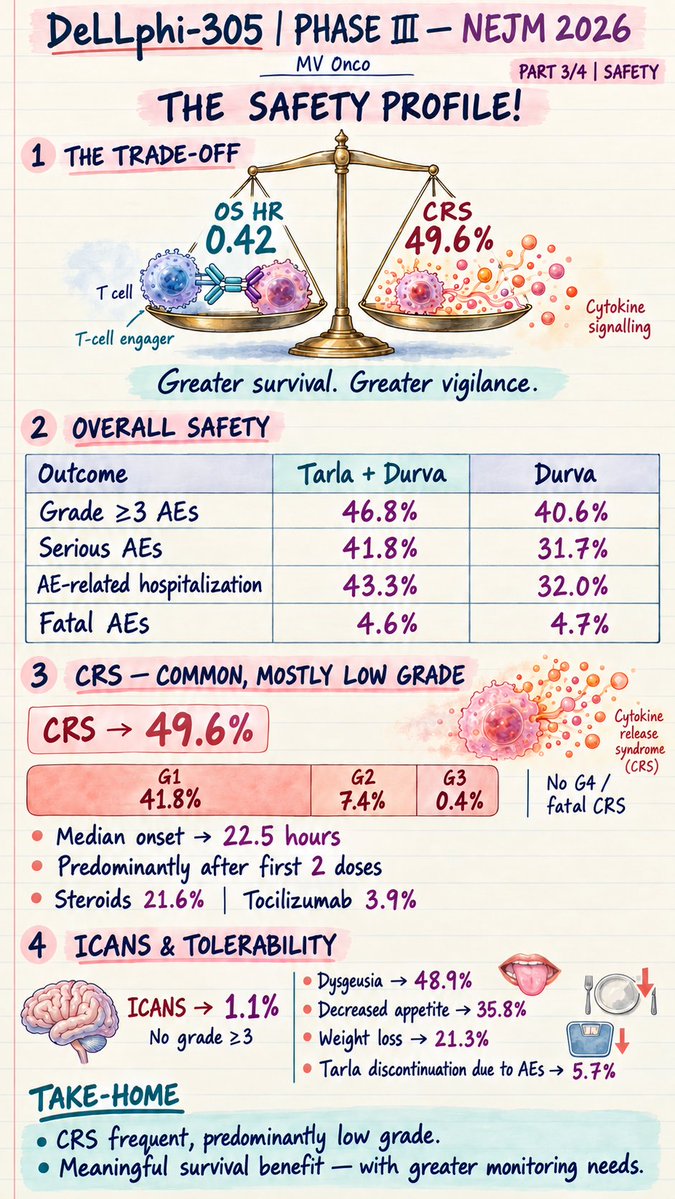
🚨 DeLLphi-305 | ESMO 2026 | LBA3 Tarlatamab enters FIRST-LINE MAINTENANCE in ES-SCLC! A remarkable phase III survival breakthrough following platinum–etoposide + durvalumab. 🔬 563 patients | Tarla + Durva vs Durva 📊 EFFICACY - Median OS: 21.1 vs 12.7 months | HR 0.42 - 12-month OS: 79.4% vs 53.3% - Median PFS: 7.4 vs 1.9 months | HR 0.34 - ORR: 26.4% vs 4.1% ⚠️ SAFETY - Grade ≥3 TEAEs: 46.8% vs 40.6% - CRS: 49.6%; grade ≥3 only 0.4% - ICANS: 1.1%; no grade ≥3 events 🔍 THREE CLINICAL PEARLS 1. Survival measured from maintenance randomization, NOT chemotherapy initiation. 2. Only patients without progression after durvalumab-based induction were randomized. 3. Maintenance tarlatamab was NOT directly compared with guaranteed tarlatamab at relapse. 💡 TAKE-HOME: A compelling OS-positive trial that could redefine ES-SCLC maintenance. Patient selection, CRS monitoring and access remain crucial. 📚 Reference: Sands J, et al. DeLLphi-305: Tarlatamab + durvalumab as first-line maintenance in ES-SCLC. ESMO 2026; LBA3. @myESMO @OncoAlert @Larvol #ESMO26 #DeLLphi305 #SCLC #Tarlatamab #MVOnco

490 views 2 likes1 RT 2026-10-24
Tejas Patil
Tejas Patil@TejasPatilMD
𝕏

🌟AND finally, #ESMO26 wouldn't be complete without some of the HEAVY hitters. I expect these data to change practice! 1⃣Tarlatamab plus durvalumab (durva) vs durva as 1L maintenance (1LM) therapy following durva, platinum, and etoposide (1L durva + EP) in extensive-stage small cell lung cancer (ES-SCLC): Primary analysis of the phase 3 DeLLphi-305 trial. I fully expect this trial to establish DLL3 TCE as the dominant first line strategy in SCLC and will likely be practice changing. 2⃣Krascendo 1: Efficacy and safety of divarasib (diva) vs sotorasib (soto) or adagrasib (ada) in previously treated locally advanced or metastatic KRAS G12C-mutated NSCLC. Given the evolution of KRAS G12Ci in this space, what is notable here is the direct prospective comparison to current KRAS G12Ci (adagrasib / sotorasib). Looking forward to ascertain magnitude of potential benefit and safety differences. 3⃣INTerpath-001: Phase 3 study of the mRNA-based individualized neoantigen therapy (INT) intismeran autogene (intismeran) plus pembrolizumab (pembro) vs pembro alone for adjuvant treatment of resected stage IIB-IV melanoma (MEL) Technically not a lung cancer study, but I believe this trial to be game-changing from a proof-of-concept approach. In my mind, this study establishes personalized mRNA-based approaches as a viable approach and worthy of research and clinical investment. @lcsmchat @OncoAlert @OncLive @Onco_Nexus @LungCancerEu @Lung_Cancers @LungCancerRx @MedwatchHQ @KRASKickers @SclcSMASHERS @YoungLungCancer

271 views 3 likes2 RT 2026-10-24
Rami Manochakian MD, FASCO
Rami Manochakian MD, FASCO@RManochakian
𝕏

🚨🔥@OncoAlert Hot off the press. Just published @NEJM in conjunction with presentation @myESMO #ESMO26 the long-awaited #PracticeChanging results of: ⭐️#DeLLphi305 phase 3 trial of: ❇️1st line maintenance #Tarlatamab + #Durvalumab) vs #Durvalumab alone in patients with #ExtensiveStage #SmallCell #LungCancer after initial induction Tx with #Chemo + Durvalumab. Study showed: ‼️#Impressive statistically significant & clinically meaningful ⬆️#OverallSurvival Benefit. ✅#mOS: 21.1 vs 12.7 months (HR 0.42) ✅12-month OS: 79.4% vs 53.3% ✅#mPFS: 7.4 vs 1.9 months (HR 0.34) ⚠️ Grade ≥3 #AEs: 46.8% vs 40.6% * In Tarlatamab arm: #CRS: 49.6% (Grade ≥3: 0.4%) #ICANS: 1.1% (Grade ≥3: 0%) 👇🏻 https://t.co/JoYBDSUAo9

2.1K views 40 likes21 RT 2026-10-24
Eric K. Singhi, MD
Eric K. Singhi, MD@lungoncdoc
𝕏

WOW! BIG news for our patients with extensive-stage small cell lung cancer! Phase 3 DeLLphi-305 trial, adding tarlatamab to durvalumab maintenance after initial chemoIO: ✅ OS: 21.1 vs 12.7 months (HR 0.42) ✅ PFS: 7.4 vs 1.9 months (HR 0.34) Practice-changed! #ESMO26 https://t.co/t23SBNzfUD

2.0K views 43 likes12 RT 2026-10-24
Anirban Maitra
Anirban Maitra@Aiims1742
𝕏

From #ESMO26 & @NEJM Tarlatamab–Durvalumab Maintenance for Extensive-Stage Small-Cell Lung Cancer https://t.co/locTy831XT Practice changing data for a terrible disease with hazard ratios that are unequivocal.

1.3K views 16 likes4 RT 2026-10-24
Giannis Mountzios
Giannis Mountzios@g_mountzios
𝕏

#ESMO26 Presidential 1 : #SCLC DeLLphi-305: Who would have imagined some years ago that median OS of SCLC would equal that of non-AGA NSCLC! #Tarlatamab as 1L maintenance with Durvalumab after induction chemoIO in ES-SCLC improved OS from 12.7 to an impressive 21.1m, corresponding to a HR of 0.42. 80% of patients alive and 38% progression-free at 12 months The dawn of a new era for thoracic oncology and for the lives of our patients 💫✨ @myESMO @SclcSMASHERS #ESMOAmbassadors

1.1K views 29 likes17 RT 2026-10-24
MV Chandrakanth
MV Chandrakanth@ChandrakanthMv
𝕏

🥊 ES-SCLC | THE POWER OF PARTNERSHIP! 2018: ATEZO opens the game! (IMpower133, OS HR 0.70) 2019: DURVA joins the fight! (CASPIAN, HR 0.73) 2025: ATEZO + LURBI enter maintenance! (IMforte, HR 0.73) 🔥 2026: DURVA + TARLA raise the stakes! (DeLLphi-305, HR 0.42) 🔮 NEXT: DeLLphi-312 takes TARLA into first line. Results awaited! 💡 A smart drug can change practice. The right partner, at the right time, can change the game! HRs reflect separate trials—not head-to-head comparisons. @myESMO @OncoAlert @larvol #ESMO26 #SCLC #Immunotherapy #Tarlatamab #MVOnco

1.0K views 12 likes4 RT 2026-10-24
Dr. Estela Rodriguez
Dr. Estela Rodriguez@Latinamd
𝕏

🔥🔥#ESMO26 Top Thoracic Abstracts: #DeLLphi305: Phase III (n=563): Tarlatamab + Durvalumab vs Durvalumab as 1L maintenance after chemo-IO in ES-SCLC Definitely practice changing if we are able to deliver to more pts in the community , moving tarlatamab 1L maintenance ▶️Median OS: 21.1 vs 12.7 months (HR 0.42) 🔥 ▶️12-month OS: 79.4% vs 53.3% ▶️Median PFS: 7.4 vs 1.9 months (HR 0.34) ▶️ORR: 26.4% vs 4.1% ⚠️ Grade ≥3 AEs: 46.8% vs 40.6%; CRS 49.6% (mostly low grade). #lcsm @SclcSMASHERS

983 views 17 likes10 RT 2026-10-24
gilberto lopes
gilberto lopes@GlopesMd
𝕏

🚨 Major SCLC results at #ESMO26! Phase III DeLLphi-305 (N=563): tarlatamab + durvalumab vs durvalumab 1L maintenance in ES-SCLC. Median OS: 21.1 vs 12.7 mo HR 0.42 (95% CI 0.32–0.54) 12-mo OS: 79.4% vs 53.3% An important survival advance. #LCSM https://t.co/WhlgNCfDyQ

948 views 26 likes13 RT 2026-10-24
Toni Choueiri, MD
Toni Choueiri, MD@DrChoueiri
𝕏

Outstanding presentation by our very own @DanaFarber @sands_jacob ! DeLLphi-305: tarlatamab + durvalumab vs durvalumab as 1L maintenance in ES-SCLC improved median OS to 21.1 vs 12.7 months (HR 0.42). A major advance for patients with SCLC! #ESMO26 @oncoalert @myESMO https://t.co/UxKz3Qgjp7

837 views 19 likes15 RT 2026-10-24
Hidehito HORINOUCHI
Hidehito HORINOUCHI@HHorinouchi
𝕏

🆙#ESMO26 Presidential Symposium I: #LCSM 🔥DeLLphi-305: Tarlatamab Plus Durvalumab (Durva) vs Durva as 1L Maintenance (1LM) Therapy Following Durva, Platinum, and Etoposide in Extensive-Stage Small Cell Lung Cancer (ES-SCLC): Primary Analysis of the Phase 3 Trial 🎙️ @sands_jacob 🔢LBA3 🎯Met Primary Endpoint: Significantly Improved OS 🎯mOS 21.1 vs 12.7m, HR 0.42 🎯mPFS 7.4 vs 1.9m, HR 0.34 🎯ORR 26.4% vs 4.1% 🎯CRS 49.6% (Mostly Low Grade), No Fatal Events ☑️NCT06211036 🔗 https://t.co/Lb6tzuMm0z @OncoAlert @Larvol @myESMO @IASLC

801 views 6 likes2 RT 2026-10-24
Hidehito HORINOUCHI
Hidehito HORINOUCHI@HHorinouchi
𝕏

🆙 Published @NEJM 🎊 🔥Presidential Symposium I: #LCSM 🔥DeLLphi-305: Tarlatamab + durvalumab vs durvalumab as 1L maintenance in ES-SCLC 🎙️ Dr. Maurice Pérol @sands_jacob 🎯Met Primary Endpoint: Significantly Improved OS 🎯mOS 21.1 vs 12.7m, HR 0.42 🎯mPFS 7.4 vs 1.9m, HR 0.34 🎯ORR 26.4% vs 4.1% 🎯CRS 49.6% (Mostly Low Grade), No Fatal Events ☑️NCT06211036 🔗 https://t.co/dVb8S7vWJk @OncoAlert @Larvol @myESMO @IASLC

788 views 12 likes4 RT 2026-10-24
Dr Amol Akhade
Dr Amol Akhade@SuyogCancer
𝕏

DeLLphi-305. Immpresive curves . Additional Toxicity and cost in real world needs to be seen . Good for patients with extensive SCLC @myESMO @OncoAlert #esmo26 https://t.co/V2CDG9m0ZR

703 views 11 likes7 RT 2026-10-24
Balazs Halmos
Balazs Halmos@BalazsHalmosMD
𝕏

Starlatamab takes a huge BiTE today out of small cell lung cancer! Amazing PFS (0.34) and OS (0.42) HR and truly manageable added tox- 50% CRS but almost uniformly gr 1/2 and near non-existent ICANS, no new safety signal w durva combo just makes this one of the most impressive SCLC trials/ cancer trials ever.. Given extreme need for better treatments for our pts w ES-SCLC, unprecedented benefit seen in DeLLphi-305 plus availability/experience with use already it is a no-brainer to incorporate into our practice as SOC maintenance therapy on Monday… well, not Mon- whenever your flight takes you back post-#ESMO26 Amazing job by @sands_jacob and Amgen/DeLLphi team- glad we had a chance to offer such a transformational trial to our pts as well at Monte/Einstein! With these extraordinary results starlatamab is likely to continue to expand into 1st line/LS-SCLC settings and lets just dream on- if we as a field have taken such a tasty first BiTE, can hardly wait for the next one! Standing ovation- well deserved! #lcsm

593 views 11 likes5 RT 2026-10-24
Abdulaziz AlJassim
Abdulaziz AlJassim@DrZ_84
𝕏

DeLLphi-305 a new standard of care in ES-SCLC Tarlatamab maintenance + Durvalumab after induction chemo-IO Huge win against SCLC! Congrats @sands_jacob and DeLLphi-305 group And a standing ovation! 👏🏼 https://t.co/a4380aJDuB

578 views 2 likes0 RT 2026-10-24
Dr. Antonio Calles 🫁🚭
Dr. Antonio Calles 🫁🚭@Tony_Calles
𝕏

📖 A new chapter in SCLC therapy has been written by @sands_jacob 💥 DeLLphi-305 sets a new standard of care in maintenance after induction chemo-io for patients with ES-SCLC #ESMO26 @myESMO https://t.co/vVhg7SmgsL

484 views 22 likes6 RT 2026-10-24
Toni Choueiri, MD
Toni Choueiri, MD@DrChoueiri
𝕏

JUST Ian: DeLLphi-305: Phase III (n=563): Tarlatamab + Durvalumab vs Durvalumab as 1L maintenance after chemo-IO, to be presented by our own @sands_jacob from @DanaFarber • Median OS: 21.1 vs 12.7 months (HR 0.42) • Median PFS: 7.4 vs 1.9 months (HR 0.34) • ORR: 26.4% vs 4.1% Grade ≥3 AEs: 46.8% vs 40.6%; CRS 49.6% (most low grade). Probably new standard of care in ES-SCLC. @OncoAlert @DanaFarberNews #ESMO26

477 views 8 likes4 RT 2026-10-24
Noemi Reguart
Noemi Reguart@NReguart
𝕏

Looking forward to the #ESMO26 Presidential Symposium! Exciting DeLLphi-305 data in ES-SCLC, presented by @JacobSandsMD, followed by what promises to be an insightful discussion from Dr. Stephen Liu @StephenVLiu Auditorium packed! #ESMO26 https://t.co/2U2JJj4T82

468 views 15 likes4 RT 2026-10-24
Alfredo Addeo MD
Alfredo Addeo MD@Alfdoc2
𝕏

🔥 DeLLphi-305 shook the room at #ESMO26 and what a spectacular discussion by @StephenVLiu Outstanding data deserve an equally outstanding discussion, and Stephen delivered! 👏 💥 OS HR 0.42 , unprecedented impact in ES-SCLC! Key questions: CNS efficacy, long-term survival, predictive biomarkers and optimal treatment sequencing. Encouraging outpatient feasibility and improved monitoring requirements. And one crucial message: global access to this breakthrough treatment must become a priority. Spectacular science, spectacular discussion! A truly unforgettable ESMO Plenary! #ESMOAmbassadors #ESMO26 #DeLLphi305 #SCLC #LungCancer

464 views 19 likes7 RT 2026-10-24
Noemi Reguart
Noemi Reguart@NReguart
𝕏

Impressive results from phase III DeLLphi-305 at #ESMO26 @sands_jacob: Adding tarlatamab to durvalumab maintenance in ES-SCLC 1-y OS nearly 80%!!! 🔹 OS: 21.1 vs 12.7 mo (HR 0.42) 🔹 PFS: 7.4 vs 1.9 mo (HR 0.34) A standing ovation!” 👏👏👏👏A major step forward for SCLC! @NEJM https://t.co/DLSwuhPS9W

406 views 11 likes6 RT 2026-10-24
Dr Riyaz Shah
Dr Riyaz Shah@DrRiyazShah
𝕏

DeLLphi-305; ES-SCLC; nearly 2y mOS; Strong PFS signal; this is about the strongest data I’ve seen in this space. @BTOGORG #ESMO26 https://t.co/rukehL59lQ

382 views 6 likes1 RT 2026-10-24
Alfredo Addeo MD
Alfredo Addeo MD@Alfdoc2
𝕏

🚨🔥 ABSOLUTELY STUNNING! DeLLphi-305 at #ESMO26! @sands_jacob presents remarkable phase III results in ES-SCLC! 💥 Tarlatamab + durvalumab vs durvalumab maintenance 🔥 Median OS: 21.1 vs 12.7 months 🔥 HR 0.42 (95% CI 0.32–0.54), p<0.001 🔥 12-month OS: 79% vs 53% 58% reduction in the hazard of death! These are extraordinary results in a disease where meaningful survival advances have been so difficult to achieve. 👏 Congratulations and I welcome A new benchmark for ES-SCLC maintenance therapy #ESMOAmbassadors #ESMO26 #SCLC #LungCancer #DeLLphi305

357 views 9 likes4 RT 2026-10-24
Uğur Özkerim
Uğur Özkerim@UOzkerim
𝕏

🚨 Impressive results from #ESMO2026! Phase III DeLLphi-305: Tarlatamab + durvalumab vs durvalumab alone as 1L maintenance in ES-SCLC: 🔹 Median OS: 21.1 vs 12.7 months (HR 0.42) 🔹 Median PFS: 7.4 vs 1.9 months (HR 0.34) 🔹 ORR: 26.4% vs 4.1% 🔥 Practice-changing potential! #LungCancer #SCLC @OncoAlert @weoncologists @StephenVLiu @GlopesMd @ManuelDomine

346 views 7 likes5 RT 2026-10-24
Tian Zhang, MD, MHS, FASCO (@tiansterzhangmd.bsky)
Tian Zhang, MD, MHS, FASCO (@tiansterzhangmd.bsky)@TiansterZhang
𝕏

with Dellphi305 — tarlatamab w durvalumab vs durvalumab for small cell lung cancer — almost doubling of overall survival w manageable CRS & outpatient treatment. Standing ovation for small cell! @nejm concurrent pub today. @oncoalert @myESMO #ESMO26 https://t.co/Z25EA6hQL2

285 views 11 likes7 RT 2026-10-24
Philippe Aftimos, MD 
Philippe Aftimos, MD @aftimosp
𝕏

I very much enjoyed the discussion by @StephenVLiu of DeLLphi-305 (tarlatamab + durvalumab as maintenance therapy in ES-SCLC at #ESMO26 👏👏👏 #ESMOAmbassadors https://t.co/Wl31gpUtEu

284 views 5 likes4 RT 2026-10-24
Oriol Mirallas MD
Oriol Mirallas MD@DrMirallas
𝕏

🔥 Presidential Symposium I #ESMO26 🗣️ @sands_jacob @DanaFarber DeLLphi-305 trial evaluating tarlatamab + durva vs durva as 1LM therapy for ES-SCLC. ✔️ mOS 21.1 vs 12.7m HR 0.42 ✔️ mPFS 7.4 vs 1.9m HR 0.34 ✔️ ORR 26.4 vs 4.1% ☣️ 46.8 vs 40.6% grade 3 or higher @OncoAlert @myESMO @ASCO @_SEOM @UTMDAnderson @NEJM @brunolarvol 👇🏽👇🏽

277 views 7 likes7 RT 2026-10-24
Leonardo Brunetti
Leonardo Brunetti@Brunet3Leon
𝕏

Striking results from DeLLphi-305 in SCLC topped with an emotional standing ovation. Mainteinance Tarlatamab is actually more like a second induction-treatment rather than a proper mainteinance! Kudos to @sands_jacob for the magistral presentation #ESMO26 #ESMOAmbassadors https://t.co/2w1PXt8jLu

266 views 4 likes3 RT 2026-10-24
Carlo Genova
Carlo Genova@CarloGenova5
𝕏

Standing ovation at #ESMO2026 for DELLPHI-305. It is heart-warming to see a meaningful survival advantage in ED-SCLC. https://t.co/ZkEwRPh2v6

241 views 4 likes1 RT 2026-10-24
Dr Riyaz Shah
Dr Riyaz Shah@DrRiyazShah
𝕏

Great DeLLphi-305 discussion by @StephenVLiu ; let’s not forget the drop off post induction; seems to trump lurbi; ICANS and CRS noted but manageable. #ESMO26 https://t.co/9rY5N8188X

218 views 3 likes2 RT 2026-10-24
Ryan Gentzler, MD
Ryan Gentzler, MD@ryangentzler
𝕏

Expert discussion of DeLLphi-305 by @StephenVLiu. Bringing tarlatamab to maintenance is major advance as second line tarlatamab is often “a promise we cannot keep.” Many patients never receive 2nd line. #ESMO26 https://t.co/T6IRxIS8ev

179 views 5 likes2 RT 2026-10-24
Elvina Almuradova
Elvina Almuradova@Dr_ElvinaA
𝕏

#ESMO26 | DeLLphi-305 Maintenance tarlatamab + durvalumab prolonged median OS to 21.1 vs 12.7 months with durvalumab alone in ES-SCLC at the prespecified interim analys @NEJM @myESMO @Larvol https://t.co/5YjJCDcyNi

161 views 4 likes1 RT 2026-10-24
Alan Tan
Alan Tan@alantanmd
𝕏

DeLLphi-305 at #ESMO26, presented by Jacob Sands, got a standing ovation. An important advance in very aggressive biology. Tarlatamab + durvalumab vs durvalumab as 1L maintenance in ES-SCLC: ▪️ OS HR 0.42, median 21.1 vs 12.7 mo ▪️ PFS HR 0.34 ▪️ ORR 26.4% vs 4.1% Important to study in NEPC and small cell bladder.

153 views 1 likes0 RT 2026-10-24
OsmanKostekMD
OsmanKostekMD@OncologyMarwarD
𝕏

🚨 ESMO 2026 | DeLLphi-305 Tarlatamab + durvalumab delivers impressive survival benefits in 1L maintenance ES-SCLC! ✅ OS: 21.1 vs 12.7 mo (HR 0.42) ✅ PFS: 7.4 vs 1.9 mo (HR 0.34) Benefits maintained across key subgroups, including brain and liver metastases. 🔥 New SOC 💫💫 https://t.co/bEhzHFst9o

129 views 2 likes0 RT 2026-10-24
Guilherme S. C. Correia, MD
Guilherme S. C. Correia, MD@guicorreiamd
𝕏

Real-time first-line updates in ES-SCLC! Getting closer and closer to a 2yr mOS. Tarlatamab + Durvalumab maintenance improved mOS to 21.1 months compared to 12.7 months with single agent Durva. New standard of care in this space! https://t.co/9kDH9ap8HL

125 views 4 likes2 RT 2026-10-24
Martín Angel
Martín Angel@Martin_AngelMD
𝕏

Presidential symposium 1️⃣!! DeLLphi-305 study: Tarlatamab + durva significantly improved ✅ OS, PFS, and ORR ‼️ in 1LM ES-SCLC @myESMO #ESMO26 a 🆕 standard of care! https://t.co/TJw3Q74PNE

101 views 1 likes0 RT 2026-10-24
Ryan Gentzler, MD
Ryan Gentzler, MD@ryangentzler
𝕏

Excited to see the highly anticipated DeLLphi-305 at #ESMO26. First line maintenance tarlatamab + durvalumab improves PFS and OS. Updated label for outpt monitoring hopefully make this more accessible for all #SCLC patients. The next frontier: Limited Stage consolidation https://t.co/GaX09tjke2

72 views 0 likes0 RT 2026-10-24
Abeid Athman (Omar).
Abeid Athman (Omar).@bin_abeid
𝕏

In DeLLphi-305: The combination of Tarlatamab+ Durvalumab improves both OS (21 vs 12 months HR 0.42) and PFS in ES-SCLC. This is remarkable in such a lethal disease with high recurrence rates and mortality. #ESMO2026 #ESMOAmbassadors @myESMO @StephenVLiu @tompowles1 @FAndreMD https://t.co/fE2K7k2Jha

71 views 1 likes0 RT 2026-10-24
Dr. Estela Rodriguez
Dr. Estela Rodriguez@Latinamd
𝕏

🔥🔥#DeLLPhi305 concurrent @NEJM publication Tarlatamab–Durvalumab Maintenance for Extensive-Stage Small-Cell Lung Cancer | New England Journal of Medicine https://t.co/PJCEjJ0QMk

68 views 0 likes1 RT 2026-10-24
Dipesh Uprety MD FACP
Dipesh Uprety MD FACP@DipeshUpretyMD
𝕏

DeLLphi-305 @NEJM #ESMO26 ➡️Pts with ES-SCLC without progression after initial chemo-IO randomized to tarlatamab–durvalumab with durvalumab as 1L maintenance therapy ➡️ Md OS 21.1 mo (tarla arm) vs 12.7 months ➡️Md PFS 7.4 mo (tarla arm) vs 1.9 mo Practice changing and now a new standard of care #LCSM @OncoAlert https://t.co/BM6jNTyFw6

67 views 0 likes0 RT 2026-10-24
Peter Grell MD
Peter Grell MD@GrellMd
𝕏

Standing ovation at #ESMO26! 👏 Practice-changing Phase 3 results from DeLLphi-305 (LBA3) for maintenance tarlatamab + durvalumab in 1L ES-SCLC: mOS: 21.1 vs 12.7 mo (HR 0.42; p < 0.001) A new standard of care with BiTE + ICI💥 https://t.co/2TAEwtvbnY

52 views 0 likes0 RT 2026-10-24
Pablo Flores
Pablo Flores@PabloFlores95
𝕏

🔥 Hot off the press! 📄! Tarlatamab–Durvalumab Maintenance for Extensive-Stage Small-Cell Lung Cancer | New England Journal of Medicine https://t.co/mgUWrdUWme

33 views 0 likes0 RT 2026-10-24
David Heredia.
David Heredia.@HerediaOncologo
𝕏

Dellphi 305 Tarlatamab in Combination With Durvalumab vs Durvalumab Alone in Subjects With Extensive-Stage Small-Cell Lung Cancer Following Platinum, Etoposide and Durvalumab Are we changing prognosis of SCLC? Yes we are. Results speak for themselves. OS 21.1m vs 12.7 m https://t.co/7KAfEx4Nlv

32 views 0 likes0 RT 2026-10-24
Dr Amol Akhade
Dr Amol Akhade@SuyogCancer
𝕏

🚨 ESMO 2026 presidential | DeLLphi-305: Phase III (n=563): Tarlatamab + Durvalumab vs Durvalumab as 1L maintenance after chemo-IO. 📊 Key results: • Median OS: 21.1 vs 12.7 months (HR 0.42) 🔥 • 12-month OS: 79.4% vs 53.3% • Median PFS: 7.4 vs 1.9 months (HR 0.34) • ORR: 26.4% vs 4.1% ⚠️ Grade ≥3 AEs: 46.8% vs 40.6%; CRS 49.6% (mostly low grade). 💡 58% reduction in risk of death! Could this redefine first-line maintenance in ES-SCLC? Probably yes. Looking forward towards full data set . @OncoAlert @esmo #esmo26 #SCLC #DeLLphi305

3.2K views 34 likes13 RT 2026-10-23
Yakup Ergün
Yakup Ergün@dr_yakupergun
𝕏

#ESMO26 | DeLLphi-305 – Phase III | Presidential Symposium-1 In ES-SCLC, tarlatamab + durvalumab maintenance significantly improved outcomes vs durvalumab alone following first-line chemotherapy + durvalumab: OS: 21.1 vs 12.7 months (HR 0.42) PFS: 7.4 vs 1.9 months (HR 0.34) CRS: 49.6%; grade ≥3: 0.4%. An impressive OS benefit! Atezolizumab + lurbinectedin maintenance also demonstrated an OS benefit in IMforte (HR 0.73). Although cross-trial comparisons are inappropriate, the magnitude of the OS benefit with tarlatamab appears numerically much greater.

1.4K views 21 likes10 RT 2026-10-23
Aakash Desai
Aakash Desai@ADesaiMD
𝕏

3/ DeLLphi-305 (LBA3), Oct 24, 17:18 CEST Tarlatamab + durvalumab as 1L maintenance in ES-SCLC. Amgen reports an OS win at interim. How large, and can clinics deliver T-cell engager monitoring in maintenance? @LungCancerRx @OncoAlert @oncodaily https://t.co/g8um5k4dwG

504 views 1 likes0 RT 2026-10-23
Jeff Ryckman
Jeff Ryckman@jryckman3
𝕏

DeLLphi-305 (LBA3): tarlatamab + durva vs durva maintenance in ES-SCLC without progression after durva + platinum-etoposide. OS HR 0.42 (CI 0.32-0.54); 12-mo OS 79% vs 53%, median OS 21 vs 13 mo. Impressive OS signal. Was thoracic consolidation RT allowed? The abstract doesn't say. If so, would be interested to see fractionation/dosing schemes and how RT was interdigitated. #ESMO26 #radonc https://t.co/wazLJ6ejpv

396 views 4 likes0 RT 2026-10-23
Gil Morgan, MD
Gil Morgan, MD@weoncologists
𝕏

Ten abstracts that will shape lung cancer practice, picked by our faculty 🫁 Stand-outs for me: DeLLphi-305 moving tarlatamab into 1L maintenance, and the head-to-head KRAS G12C data in Krascendo 1. Do not skip DIAL either: it asks whether we can safely stop IO at 6 months 👇 #ESMO26 #LCSM #LungCancer

617 views 8 likes6 RT 2026-10-21
Mustafa Özdoğan, MD
Mustafa Özdoğan, MD@ozdogan_md
𝕏

DeLLphi-305 moves tarlatamab earlier into first-line maintenance for ES-SCLC. Tarlatamab + durvalumab has met OS, PFS and ORR versus durvalumab alone. The key question now: how large is the benefit, and does it justify the added CRS/ICANS monitoring burden? Presented by @sands_jacob @myESMO #ESMO26 #SCLC

400 views 8 likes6 RT 2026-10-20
Yakup Ergün
Yakup Ergün@dr_yakupergun
𝕏

I’d applaud these trials, but I’d remain seated 😅😅 INTerpath-001 is an innovative treatment approach. However, there is no comparison with neoadjuvant nivo + ipi, a strong option particularly in macroscopic stage III melanoma. DeLLphi-305 showed a survival benefit with maintenance tarlatamab + durvalumab. But the comparator is durvalumab monotherapy. We also have positive results from IMforte with maintenance atezo + lurbinectedin. So this is another potential maintenance option; its place among the existing options remains to be defined. In HARMONi-GI1, even if not one but three trucks could fit between the Kaplan–Meier curves, global validation will still be expected because the trial was conducted exclusively in China 🫣 For me, VOLGA’s most interesting feature is the omission of adjuvant EV. As for the survival benefit of perioperative EV + immunotherapy, we already have strong data.

999 views 9 likes1 RT 2026-10-19
MV Chandrakanth
MV Chandrakanth@ChandrakanthMv
𝕏

DeLLphi-305 | Can We Delay Relapse in ES-SCLC? A potential shift: Tarlatamab in first-line maintenance, before relapse. 🔹 563 patients randomized 1:1 after platinum–etoposide + durvalumab. 🔹 Maintenance: Tarlatamab + durvalumab vs durvalumab alone. 🔹 Mechanism: DLL3 × CD3 T-cell engagement + PD-L1 blockade. 🔹 Topline: Sponsor reports improved OS, PFS and response. 🔹 ESMO 2026: Awaiting detailed efficacy, CRS, neurological toxicity and QoL data. 🎯 Take-home: Could earlier tarlatamab redefine ES-SCLC maintenance? Promising, but full results are needed. 📚 Reference: DeLLphi-305, Phase III (NCT06211036). #DeLLphi305 #Tarlatamab #SCLC #ESMO2026 #LungCancer #MVOnco

993 views 8 likes3 RT 2026-10-19
MV Chandrakanth
MV Chandrakanth@ChandrakanthMv
𝕏

Tarlatamab in SCLC: Decoding the Phase III DeLLphi Programme 🔹 304: Second line—vs chemotherapy 🔹 305: First-line maintenance—adding tarlatamab to durvalumab 🔹 306: Limited stage—after concurrent chemoradiotherapy 🔹 312: First line—adding tarlatamab during induction and maintenance 🔹 315: Subcutaneous vs intravenous delivery 📌 Different trials, different questions—not all have reported results. #MVOnco #SCLC #Tarlatamab #DeLLphi #DLL3 #LungCancer #ThoracicOncology #ClinicalTrials

981 views 12 likes2 RT 2026-10-18

DeLLphi-305 Key Takeaways

Efficacy — primary analysis (ESMO 2026 LBA3, Oct 24, 2026; NEJM)

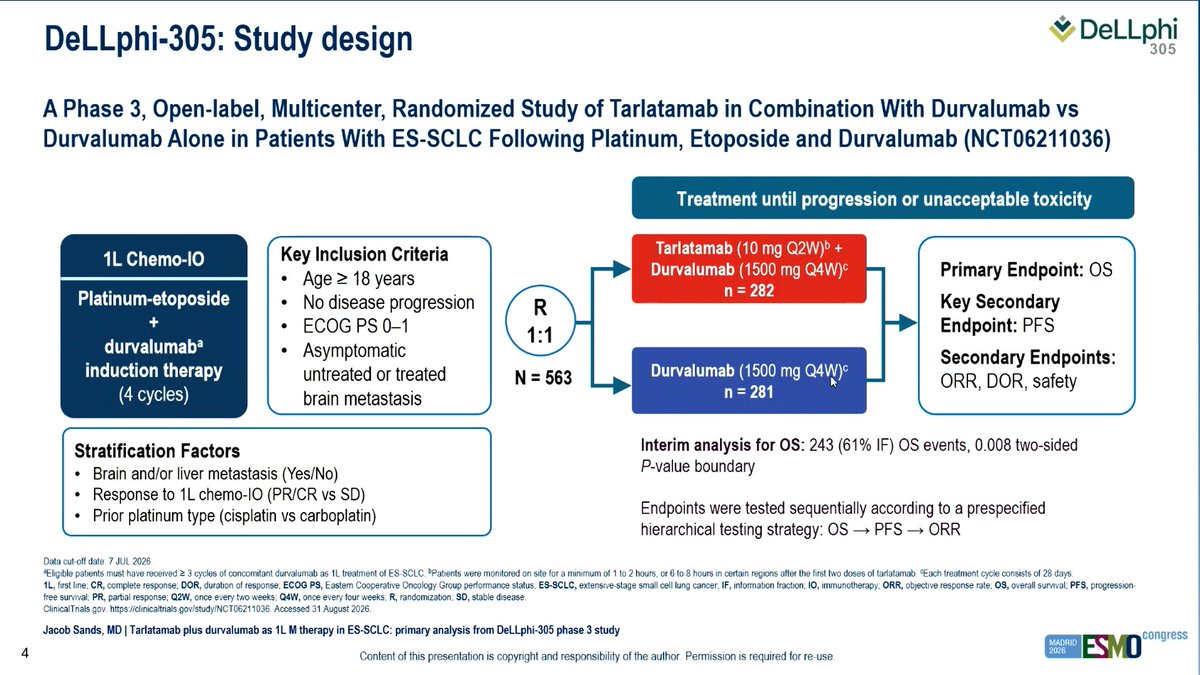
Data cut-off July 7, 2026; prespecified OS interim analysis (243 events, 61% information fraction, two-sided boundary 0.008). Overall survival (primary): median 21.1 (95% CI 20.8–NE) vs 12.7 (11.2–14.8) months; HR 0.42 (0.32–0.54); two-sided P<0.001; 87 vs 156 events; median follow-up 15.9 vs 16.1 months. 12-month OS 79.4% vs 53.3% (LBA3 abstract; slide curve labels 79% vs 53%). PFS (key secondary, investigator-assessed): median 7.4 (5.6–9.1) vs 1.9 (1.9–2.0) months; HR 0.34 (0.28–0.42); P<0.001; 182 vs 250 events. ORR (secondary): 26.4% (20.9–32.5) vs 4.1% (2.0–7.4), P<0.001, in patients with measurable disease at baseline (n=235 vs 244); confirmed CR 0.9% vs 0.4%; median duration of response 12.7 (7.4–NE) vs 5.6 (3.6–NE) months. At data cut-off, 43.6% vs 11.4% of patients remained on treatment. Topline (Sept 8, 2026): Amgen announced the OS endpoint was met at the interim analysis, with significant PFS and ORR improvements — the first Phase 3 study of a bispecific T-cell engager to show an OS benefit in 1L maintenance ES-SCLC (Amgen).

OS HR 0.42 · PFS HR 0.34 · ORR 26.4% vs 4.1% (DCO Jul 7, 2026)
Source: ESMO 2026 LBA3 slides (Sands), DCO Jul 7, 2026 · LBA3 abstract · NEJM (Pérol et al., Oct 24, 2026) Amgen press release, Sept 8, 2026

Safety

Safety population 282 (tarlatamab + durvalumab) vs 278 (durvalumab). Any-grade TEAEs 99.6% vs 92.8%; grade ≥3 TEAEs 46.8% vs 40.6% (LBA3 abstract). Cytokine release syndrome 49.6% vs 1.4%: grade 2 7.4%, grade 3 0.4%, no grade 4 or 5; serious CRS 12.8%; CRS led to tarlatamab discontinuation in 1 patient (0.4%). CRS interventions were used in 23.0% (corticosteroids 21.6%, tocilizumab 3.9%, low-flow oxygen 1.4%). ICANS 1.1% vs 0%, none grade ≥3. No fatal CRS or ICANS events (LBA3 slides, DCO Jul 7, 2026). The trial design used post-infusion monitoring of 1–2 hours (6–8 hours in certain regions including Europe) on Cycle 1 Day 1 and Day 8 — shorter than the 22–24 hour monitoring tarlatamab’s US label originally required. On September 11, 2026 (BLA 761344/S-002) the FDA reduced the label’s routine monitoring for Cycle 1 Day 1 and Day 8 to 6–8 hours, with patients remaining within 1 hour of an appropriate healthcare setting for 48 hours total; 22–24-hour monitoring is retained after certain Grade ≥2 CRS/ICANS events (FDA label, Sept 2026). Source: ESMO 2026 LBA3 CRS/ICANS slide · LBA3 abstract · Source: IMDELLTRA USPI s002 (Sept 11, 2026) →

Source: Amgen press release, Sept 8, 2026

Regulatory status & clinical implications

⚠ The 1L maintenance combination is investigational — not FDA-approved for this setting. ✅ Tarlatamab (IMDELLTRA) holds full FDA approval (Nov 19, 2025, converted from May 2024 accelerated approval on DeLLphi-304 confirmatory data: OS 13.6 vs 8.3 months, HR 0.60) for ES-SCLC progressing on or after platinum-based chemotherapy, and is NCCN Category 1 preferred in that setting. Amgen will engage regulators with the interim data. If registered on DeLLphi-305, DLL3-targeted BiTE therapy would move a line earlier — changing 1L maintenance from passive checkpoint continuation to active immune redirection, with the rest of the DeLLphi program (306 in LS-SCLC, 312 in 1L induction+maintenance) testing even earlier use. Amgen: full approval (Nov 2025) · Targeted Oncology (DeLLphi-304 numbers)

Free Access · KOL Pulse Intelligence

Track oncology’s top KOLs in your specialty

Create a free account, pick the tumor types you cover, and go beyond the tweet — the intelligence pharma teams use to map influence and prepare for engagement:

  • ✓Enhanced KOL profiles
  • ✓Pharma influence & potential advisory-board patterns
  • ✓2025 Open Payments financial analysis
  • ✓Social-media sentiment & trend signals
Get free access — pick your specialty
Choose the tumor types you follow. No cost, unsubscribe anytime.

Top KOLs Discussing DeLLphi-305

Jacob Sands, MD
Jacob Sands, MD
Trial lead · Dana-Farber
Aakash Desai
Aakash Desai
1.3K impressions
Rami Manochakian MD, FASCO
1.2K impressions
Dr Amol Akhade
Dr Amol Akhade
436 impressions
Yakup Ergün
Yakup Erg n
319 impressions
Balazs Halmos
Balazs Halmos
300 impressions
Toni Choueiri, MD
Toni Choueiri, MD
177 impressions
Uğur Özkerim
U ur zkerim
123 impressions
Dr. Antonio Calles 🫁🚭
Dr. Antonio Calles
100 impressions

DeLLphi-305 Key Slides & Visuals

Presented at ESMO 2026 (October 24, 2026) — LBA3, Presidential Symposium I

Slides from the primary analysis presented by Jacob Sands, MD (data cut-off 7 JUL 2026), the LBA3 abstract, the concurrent NEJM publication, and the discussion by Stephen Liu, MD, as shared by physicians on X. Survival curves are summarized in a numbers table built only from values printed on the slide. Full slide text via the OCR toggle on each card.

Hidehito HORINOUCHI @HHorinouchi · 2026-10-24
DeLLphi-305 · ESMO 2026 · Oct 24, 2026
Presenter slides: design, OS, PFS, response (Jacob Sands, MD)
View on X
DeLLphi-305 ESMO 2026 conference slide — trial design schema: study design, N = 563 randomized 1:1, primary endpoint OS (shared by Hidehito HORINOUCHI)DeLLphi-305 ESMO 2026 conference slide — Kaplan-Meier survival data: overall survival, median 21.1 vs 12.7 months, HR 0.42 (shared by Hidehito HORINOUCHI)DeLLphi-305 ESMO 2026 conference slide — Kaplan-Meier survival data: progression-free survival, median 7.4 vs 1.9 months, HR 0.34 (shared by Hidehito HORINOUCHI)DeLLphi-305 ESMO 2026 conference slide — response data: objective response rate 26.4% vs 4.1% and duration of response (shared by Hidehito HORINOUCHI)
ArmNEventsMedian (95% CI)6 mo rate (curve label)12 mo rate (curve label)
Tarlatamab + Durvalumab2828721.1 mo (20.8–NE)92%79%
Durvalumab28115612.7 mo (11.2–14.8)75%53%

[Slide 2] OS · data cut-off 7 JUL 2026 · values as printed on the slide. HR 0.42 (95% CI 0.32–0.54); P < 0.001 (2-sided, stratified log-rank).

ArmNEventsMedian (95% CI)6 mo rate (curve label)12 mo rate (curve label)
Tarlatamab + Durvalumab2821827.4 mo (5.6–9.1)53%38%
Durvalumab2812501.9 mo (1.9–2.0)17%10%

[Slide 3] PFS · data cut-off 7 JUL 2026 · values as printed on the slide. HR 0.34 (95% CI 0.28–0.42); P < 0.001 (2-sided, stratified log-rank).

[Slide 1] DeLLphi-305: Study design A Phase 3, Open-label, Multicenter, Randomized Study of Tarlatamab in Combination With Durvalumab vs Durvalumab Alone in Patients With ES-SCLC Following Platinum, Etoposide and Durvalumab (NCT06211036) 1L Chemo-IO: Platinum-etoposide + durvalumab(a) induction therapy (4 cycles) Key Inclusion Criteria: - Age ≥ 18 years - No disease progression - ECOG PS 0–1 - Asymptomatic untreated or treated brain metastasis R 1:1, N = 563 Treatment until progression or unacceptable toxicity Tarlatamab (10 mg Q2W)(b) + Durvalumab (1500 mg Q4W)(c) n = 282 Durvalumab (1500 mg Q4W)(c) n = 281 Primary Endpoint: OS Key Secondary Endpoint: PFS Secondary Endpoints: ORR, DOR, safety Stratification Factors: - Brain and/or liver metastasis (Yes/No) - Response to 1L chemo-IO (PR/CR vs SD) - Prior platinum type (cisplatin vs carboplatin) Interim analysis for OS: 243 (61% IF) OS events, 0.008 two-sided P-value boundary Endpoints were tested sequentially according to a prespecified hierarchical testing strategy: OS → PFS → ORR Data cut-off date: 7 JUL 2026. (a)Eligible patients must have received ≥ 3 cycles of concomitant durvalumab as 1L treatment of ES-SCLC. (b)Patients were monitored on site for a minimum of 1 to 2 hours, or 6 to 8 hours in certain regions after the first two doses of tarlatamab. (c)Each treatment cycle consists of 28 days. ClinicalTrials.gov. https://clinicaltrials.gov/study/NCT06211036. Accessed 31 August 2026. Jacob Sands, MD | Tarlatamab plus durvalumab as 1L M therapy in ES-SCLC: primary analysis from DeLLphi-305 phase 3 study --- [Slide 2] Tarlatamab plus durvalumab significantly improved overall survival versus durvalumab alone as first-line maintenance therapy | Tarlatamab + Durvalumab (n = 282) | Durvalumab (n = 281) Median OS, months (95% CI) | 21.1 (20.8–NE) | 12.7 (11.2–14.8) Median FU, months | 15.9 | 16.1 HR (95% CI); P-value (2-sided)(a) | 0.42 (0.32–0.54); P < 0.001 Curve labels: Tarlatamab + Durvalumab 92% (6 mo), 79% (12 mo); Durvalumab 75% (6 mo), 53% (12 mo) Data cut-off date: 7 JUL 2026. At the time of data cut-off, 87 events had occurred in the tarlatamab-durvalumab arm, and 156 events had occurred in the durvalumab arm. (a)P value was calculated using a stratified log-rank test. CI, confidence interval; FU, follow-up; HR, hazard ratio; NE, not estimable; OS, overall survival. Jacob Sands, MD | Tarlatamab plus durvalumab as 1L M therapy in ES-SCLC: primary analysis from DeLLphi-305 phase 3 study --- [Slide 3] Tarlatamab plus durvalumab significantly improved PFS versus durvalumab | Tarlatamab + Durvalumab (n = 282) | Durvalumab (n = 281) Median PFS, months (95% CI) | 7.4 (5.6–9.1) | 1.9 (1.9–2.0) Median FU, months | 13.9 | 13.9 HR (95% CI); P-value (2-sided)(a) | 0.34 (0.28–0.42); P < 0.001 Curve labels: Tarlatamab + Durvalumab 53% (6 mo), 38% (12 mo); Durvalumab 17% (6 mo), 10% (12 mo) Data cut-off date: 7 JUL 2026. At the time of data cut-off, 182 events had occurred in the tarlatamab-durvalumab arm, and 250 events had occurred in the durvalumab arm. (a)P-value was calculated using a stratified log-rank test. CI, confidence interval; FU, follow-up; HR, hazard ratio; PFS, progression-free survival. Jacob Sands, MD | Tarlatamab plus durvalumab as 1L M therapy in ES-SCLC: primary analysis from DeLLphi-305 phase 3 study --- [Slide 4] Tarlatamab plus durvalumab demonstrated significantly improved objective response rate versus durvalumab | Tarlatamab + Durvalumab (n = 235)(a) | Durvalumab (n = 244)(a) BOR, n (%)(a,b) Confirmed CR(c) | 2 (0.9) | 1 (0.4) Confirmed PR(c) | 60 (25.5) | 9 (3.7) Stable disease | 127 (54.0) | 74 (30.3) Progressive disease | 43 (18.3) | 150 (61.5) ORR, % (95% CI) | 26.4 (20.9–32.5) | 4.1 (2.0–7.4) P-value (2-sided) | < 0.001 Median DOR, months (95% CI) | 12.7 (7.4–NE) | 5.6 (3.6–NE) Duration of response [KM curve]: Responders Without Progression or Death (%) vs Months 0-18 Curve labels: Tarlatamab + Durvalumab 70% (6 mo), 52% (12 mo); Durvalumab 38% (6 mo) Number of patients at risk: Months | 0 | 3 | 6 | 9 | 12 | 15 | 18 Tarlatamab + Durvalumab | 62 | 58 | 36 | 27 | 11 | 5 | 0 Durvalumab | 10 | 10 | 3 | 0 As of data cut-off, 43.6% and 11.4% of patients remained on treatment in tarlatamab plus durvalumab and durvalumab arm, respectively Data cut-off date: 7 JUL 2026. Median follow-up: 10.2 months (tarlatamab + durvalumab arm); 8.3 months (durvalumab arm). (a)Based on RECIST 1.1 per investigator assessment in patients with measurable disease at baseline at the time of randomization. (b)Postbaseline scan data was not available for 3 (1.3%) patients in tarlatamab + durvalumab arm and 10 (4.1%) in durvalumab arm. (c)Confirmation of a CR or a PR was required and had to take place no fewer than 4 weeks after the initial documentation of a CR or a PR. 1L, first line; BOR, best overall response; CI, confidence interval; CR, complete response; DOR, duration of response; NE, not estimable; ORR, objective response rate; PR, partial response; RECIST, Response Evaluation Criteria in Solid Tumors. Jacob Sands, MD | Tarlatamab plus durvalumab as 1L M therapy in ES-SCLC: primary analysis from DeLLphi-305 phase 3 study
Dr Amol Akhade @SuyogCancer · 2026-10-24
DeLLphi-305 · ESMO 2026 · Oct 24, 2026
Presenter slide: CRS and ICANS safety (Jacob Sands, MD)
View on X
DeLLphi-305 ESMO 2026 conference slide — safety data: CRS any grade 49.6% and ICANS 1.1% with tarlatamab plus durvalumab (shared by Dr Amol Akhade)
[Slide 1] On-screen broadcast chrome: '16:30 - 18:15 Presidential Symposium I'; 'CHAIRS: FABRICE ANDRÉ, JAMES LARKIN'; speaker card 'Jacob Sands'; 'ALICANTE AUDITORIUM - HALL 6'. CRS and ICANS events profile is consistent with the known safety profile of tarlatamab CRSa,b, n (%) | Tarlatamab + Durvalumab (n = 282) | Durvalumab (n = 278) Any grade | 140 (49.6) | 4 (1.4) Grade 2 | 21 (7.4) | 2 (0.7) Grade 3 | 1 (0.4) | 0 (0.0) Grade 4 | 0 (0.0) | 0 (0.0) Serious adverse events | 36 (12.8) | 2 (0.7) Leading to discontinuation of tarlatamab | 1 (0.4) | NA Fatal adverse events | 0 (0.0) | 0 (0.0) Utilization of any CRS interventionsc | 65 (23.0) | 2 (0.7) ICANSd, n (%) | Tarlatamab + Durvalumab (n = 282) | Durvalumab (n = 278) Any grade | 3 (1.1) | 0 (0.0) Grade 2 | 1 (0.4) | 0 (0.0) Grade 3 | 0 (0.0) | 0 (0.0) Grade 4 | 0 (0.0) | 0 (0.0) Serious adverse events | 0 (0.0) | 0 (0.0) Leading to discontinuation of tarlatamab | 0 (0.0) | NA Fatal adverse events | 0 (0.0) | 0 (0.0) • Most CRS events resolved with supportive care (and antipyretics) – Interventions included corticosteroids (21.6%), tocilizumab (3.9%), and low-flow oxygen (1.4%) Data cut-off date: 7 JUL 2026. aCRS events included one patient with cytokine storm. bCRS and ICANS events were graded using ASTCT 2019 criteria. cOther supportive care interventions included intravenous fluids, vasopressor, and supplemental (low-flow [≤ 6 L/min]) oxygen. dPotentially associated neurologic events (including ICANS) occurred in 27 (9.6%) and 19 (6.8%) patients, respectively. Events were predominantly grade 1 or 2 and no fatal events occurred. [footnote very small; figures 27 (9.6%) / 19 (6.8%) read with moderate confidence] ASTCT, American Society for Transplantation and Cellular Therapy; CRS, cytokine release syndrome; ICANS, immune effector cell-associated neurotoxicity syndrome; NA, not applicable. Jacob Sands, MD | Tarlatamab plus durvalumab as 1L M therapy in ES-SCLC: primary analysis from DeLLphi-305 phase 3 study
Dr Riyaz Shah @DrRiyazShah · 2026-10-24
DeLLphi-305 · ESMO 2026 · Oct 24, 2026
Presenter slides: baseline characteristics and OS subgroups (Jacob Sands, MD)
View on X
DeLLphi-305 ESMO 2026 conference slide — baseline characteristics: baseline characteristics by arm (shared by Dr Riyaz Shah)DeLLphi-305 ESMO 2026 conference slide — subgroup analysis: OS forest plot across prespecified subgroups (shared by Dr Riyaz Shah)
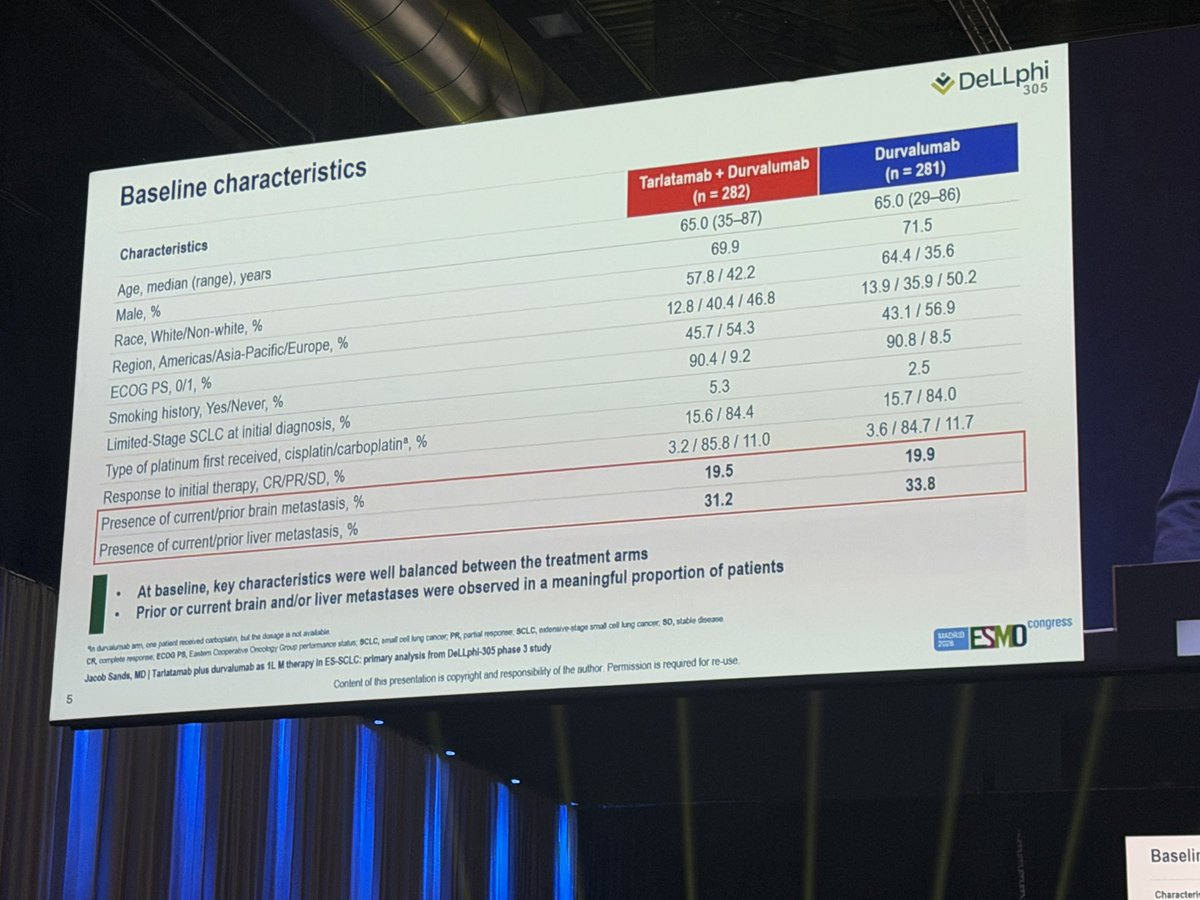
[Slide 1] Baseline characteristics Characteristics | Tarlatamab + Durvalumab (n = 282) | Durvalumab (n = 281) Age, median (range), years | 65.0 (35–87) | 65.0 (29–86) Male, % | 69.9 | 71.5 Race, White/Non-white, % | 57.8 / 42.2 | 64.4 / 35.6 Region, Americas/Asia-Pacific/Europe, % | 12.8 / 40.4 / 46.8 | 13.9 / 35.9 / 50.2 ECOG PS, 0/1, % | 45.7 / 54.3 | 43.1 / 56.9 Smoking history, Yes/Never, % | 90.4 / 9.2 | 90.8 / 8.5 Limited-Stage SCLC at initial diagnosis, % | 5.3 | 2.5 Type of platinum first received, cisplatin/carboplatin(a), % | 15.6 / 84.4 | 15.7 / 84.0 Response to initial therapy, CR/PR/SD, % | 3.2 / 85.8 / 11.0 | 3.6 / 84.7 / 11.7 Presence of current/prior brain metastasis, % | 19.5 | 19.9 Presence of current/prior liver metastasis, % | 31.2 | 33.8 - At baseline, key characteristics were well balanced between the treatment arms - Prior or current brain and/or liver metastases were observed in a meaningful proportion of patients (a)In durvalumab arm, one patient received carboplatin, but the dosage is not available. CR, complete response; ECOG PS, Eastern Cooperative Oncology Group performance status; SCLC, small cell lung cancer; PR, partial response; SCLC, extensive-stage small cell lung cancer; SD, stable disease. Jacob Sands, MD | Tarlatamab plus durvalumab as 1L M therapy in ES-SCLC: primary analysis from DeLLphi-305 phase 3 study --- [Slide 2] OS benefit was consistent across all key prespecified subgroups Subgroup | Tarlatamab + Durvalumab (no. of events / no. of patients) | Durvalumab (no. of events / no. of patients) | Hazard Ratio for Death (95% CI) Age < 65 years | 34 / 139 | 69 / 133 | 0.36 (0.24–0.54) ≥ 65 years | 53 / 143 | 87 / 148 | 0.48 (0.34–0.67) Sex Male | 64 / 197 | 120 / 201 | 0.38 (0.28–0.51) Female | 23 / 85 | 36 / 80 | 0.56 (0.33–0.94) Race White | 54 / 163 | 108 / 181 | 0.40 (0.29–0.56) Black | 0 / 4 | 0 / 4 | - Asian | 31 / 109 | 45 / 92 | 0.47 (0.30–0.74) Other | 2 / 6 | 3 / 4 | - Region Americas | 13 / 36 | 16 / 39 | 0.82 (0.39–1.71) Asia-Pacific | 32 / 114 | 51 / 101 | 0.43 (0.28–0.67) Europe | 42 / 132 | 89 / 141 | 0.36 (0.25–0.52) Presence (previous or current) of brain metastases Yes | 15 / 55 | 26 / 56 | 0.49 (0.26–0.93) No | 72 / 227 | 130 / 225 | 0.41 (0.30–0.54) Presence (previous or current) of liver metastases Yes | 43 / 88 | 69 / 95 | 0.41 (0.28–0.61) No | 44 / 194 | 87 / 186 | 0.40 (0.28–0.57) Response to initial therapy CR/PR | 77 / 251 | 135 / 248 | 0.42 (0.32–0.56) SD | 10 / 31 | 21 / 33 | 0.40 (0.19–0.85) Type of platinum first received for ES-SCLC Cisplatin | 11 / 44 | 23 / 44 | 0.33 (0.16–0.67) Carboplatin | 76 / 238 | 132 / 236 | 0.44 (0.34–0.59) X axis: 0.1 0.2 0.5 1 1.5 2 — Tarlatamab + Durvalumab Better ← → Durvalumab Better Data cut-off date: 7 JUL 2026. Median follow-up: 15.9 months (tarlatamab + durvalumab arm); 16.1 months (durvalumab arm). CI, confidence interval; ES-SCLC, extensive-stage small cell lung cancer; CR, complete response; OS, overall survival; PR, partial response; SD, stable disease. Jacob Sands, MD | Tarlatamab plus durvalumab as 1L M therapy in ES-SCLC: primary analysis from DeLLphi-305 phase 3 study
Toni Choueiri, MD @DrChoueiri · 2026-10-24
DeLLphi-305 · ESMO 2026 · Oct 24, 2026
Presenter slide: conclusions (Jacob Sands, MD)
View on X
DeLLphi-305 ESMO 2026 conference slide — conclusions: OS, PFS and ORR improved; proposed new first-line maintenance standard (shared by Toni Choueiri, MD)
[Slide 1] Conclusions - Tarlatamab plus durvalumab significantly improved OS, PFS, and ORR versus durvalumab in patients with ES-SCLC without progression after initial chemo plus durvalumab - 58% reduction in the risk of death; P < 0.001 - 66% reduction in the risk of disease progression or death; P < 0.001 - ORR: 26.4% vs 4.1%; P < 0.001 - Survival benefit extended to all pre-defined subgroups including patients with brain metastases, liver metastases, or minimal response to initial chemo plus durvalumab - Tarlatamab plus durvalumab demonstrated a manageable safety profile with low rates of treatment discontinuation due to adverse events DeLLphi-305 outcomes support tarlatamab plus durvalumab as a new standard of care first-line maintenance therapy in ES-SCLC Chemo, chemotherapy; CRS, cytokine release syndrome; DOR, duration of response; ES-SCLC, extensive-stage small cell lung cancer; ICANS, immune effector cell-associated neurotoxicity syndrome; ORR, objective response rate; OS, overall survival; PFS, progression-free survival. Jacob Sands, MD | Tarlatamab plus durvalumab as 1L M therapy in ES-SCLC: primary analysis from DeLLphi-305 phase 3 study
Patrick Forde @FordePatrick · 2026-10-24
DeLLphi-305 · ESMO 2026 · Oct 24, 2026
LBA3 abstract (ESMO 2026 programme)
View on X
DeLLphi-305 ESMO 2026 conference slide — conclusions: LBA3 abstract with OS, PFS, ORR and safety results (shared by Patrick Forde)
[Slide 1] Proffered Paper session LBA3 - Tarlatamab plus durvalumab (durva) vs durva as 1L maintenance (1LM) therapy following durva, platinum, and etoposide (1L durva + EP) in extensive-stage small cell lung cancer (ES-SCLC): Primary analysis of the phase 3 DeLLphi-305 trial Speakers Jacob Sands (Boston, United States of America) Lecture Time 17:18 - 17:30 Abstract Background Adding tarlatamab to 1L ES-SCLC therapy showed encouraging efficacy in the phase 1b DeLLphi-303 study (NCT05361395). We report the primary analysis of the randomized phase 3 DeLLphi-305 trial evaluating tarlatamab + durva vs durva as 1LM therapy for ES-SCLC. Methods 563 patients (pts) with ES-SCLC without progression after 1L durva + EP were randomized (1:1) to receive either tarlatamab + durva (n = 282) or durva (n = 281) until progression or unacceptable toxicity. Tarlatamab was given 1 mg IV cycle 1 day 1 (C1D1); 10 mg IV C1D8, C1D15, then 10 mg IV Q2W; durva was given 1500 mg IV Q4W. The primary endpoint was overall survival (OS) with key secondary endpoint progression-free survival (PFS) per investigator assessment, each measured from time of randomization. Additional secondary endpoints were objective response rate (ORR) and safety. Results With median (m) follow-up time of 15.9 and 16.1 months (mo), respectively, tarlatamab + durva significantly improved OS (HR: 0.42; 95% CI 0.32, 0.54; P <0.001; mOS: 21.1 [95% CI, 20.8 to NE] vs 12.7 mo [95% CI, 11.2 to 14.8]). Tarlatamab + durva significantly improved PFS (HR: 0.34; 95% CI 0.28, 0.42; P < 0.001; mPFS: 7.4 vs 1.9 mo). ORR was 26.4% (95% CI 20.9%, 32.5%) for tarlatamab + durva and 4.1% (95% CI 2.0%, 7.4%) for durva (P < 0.001). Grade ≥ 3 TEAEs occurred in 46.8% (tarlatamab + durva) and 40.6% (durva) of pts. Cytokine release syndrome (CRS) and immune-effector cell-associated neurotoxicity syndrome (ICANS) occurred in 49.6% and 1.1% of tarlatamab + durva pts and were mostly low grade (Table). Table: LBA3 | | Tarlatamab + durva (n = 282) | Durva (n = 281) | OS mOS, mo (95% CI) | 21.1 (20.8, NE) | 12.7 (11.2, 14.8) HR (95% CI); P value | 0.42 (0.32, 0.54); P < 0.001 | 12 mo OS rate, % (95% CI) | 79.4 (74.2, 83.7) | 53.3 (47.3, 59.0) Median follow-up, mo | 15.9 | 16.1 PFS mPFS | 7.4 (5.6, 9.1) | 1.9 (1.9, 2.0) HR (95% CI); P value | 0.34 (0.28, 0.42); P < 0.001 | ORR, % (95% CI) | 26.4 (20.9, 32.5) | 4.1 (2.0, 7.4) P value | P < 0.001 | TEAEs, n (%) | (n = 282) | (n = 278) Any grade | 281 (99.6) | 258 (92.8) Gr ≥ 3 | 132 (46.8) | 113 (40.6) CRS^a, n (%) Any grade | 140 (49.6) | 4 (1.4) Gr ≥ 3 | 1 (0.4) | 0 ICANS^a, n (%) Any grade | 3 (1.1) | 0 Gr ≥ 3 | 0 | 0 ^aNo fatal events occurred. NE, not estimable; Gr, grade; TEAE, treatment-emergent adverse event. Conclusions Tarlatamab + durva significantly improved OS, PFS, and ORR in 1LM ES-SCLC. The overall incidence of adverse events was comparable between groups. CRS and ICANS events were primarily low grade and no fatal events occurred. These results establish tarlatamab + durva as a new standard of care 1LM therapy for ES-SCLC.
Rami Manochakian MD, FASCO @RManochakian · 2026-10-24
DeLLphi-305 · ESMO 2026 · Oct 24, 2026
NEJM simultaneous publication (Perol et al., Oct 24, 2026)
View on X
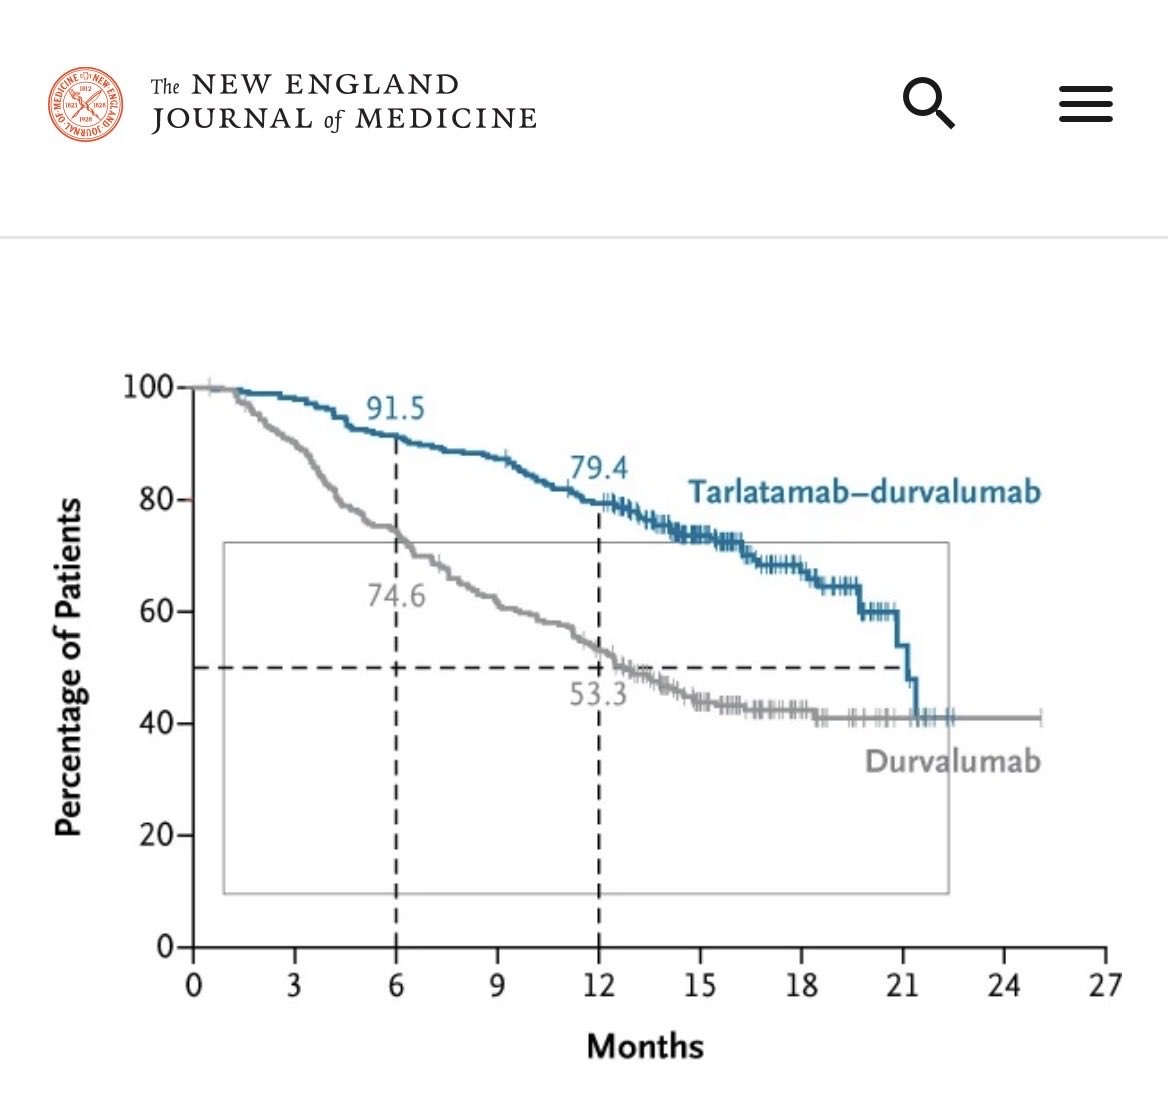
DeLLphi-305 ESMO 2026 conference slide — conclusions: NEJM original article header, published October 24, 2026 (shared by Rami Manochakian MD, FASCO)DeLLphi-305 ESMO 2026 conference slide — Kaplan-Meier survival data: NEJM figure with 6- and 12-month landmark rates (shared by Rami Manochakian MD, FASCO)
ArmNEventsMedian (95% CI)6 months rate (curve label)12 months rate (curve label)
Tarlatamab–durvalumabnot shownnot shownnot shown91.5%79.4%
Durvalumabnot shownnot shownnot shown74.6%53.3%

[Slide 2] Not printed on crop (DeLLphi-305 NEJM figure; endpoint label not visible) · values as printed on the slide.

[Slide 1] The NEW ENGLAND JOURNAL of MEDICINE ORIGINAL ARTICLE Tarlatamab–Durvalumab Maintenance for Extensive-Stage Small-Cell Lung Cancer Authors: Maurice Pérol, M.D., Tatsuya Yoshida, M.D., Ph.D., Myung-Ju Ahn, M.D., Ph.D., Carl M. Gay, M.D., Ph.D., Martin Schuler, M.D., Haifeng Liu, M.D., Ahmet Sezer, M.D., +16, for the DeLLphi-305 Investigators* Author Info & Affiliations Published October 24, 2026 | Copyright © 2026 --- [Slide 2] The NEW ENGLAND JOURNAL of MEDICINE
Dr Amol Akhade @SuyogCancer · 2026-10-24
DeLLphi-305 · ESMO 2026 · Oct 24, 2026
Discussant: Stephen Liu, MD (LBA3)
View on X
DeLLphi-305 ESMO 2026 conference slide — Kaplan-Meier survival data: DeLLphi-305 vs IMforte cross-trial efficacy comparison (shared by Dr Amol Akhade)DeLLphi-305 ESMO 2026 conference slide — safety data: discussant review of DeLLphi-305 CRS rates (shared by Dr Amol Akhade)DeLLphi-305 ESMO 2026 conference slide — conclusions: open questions for tarlatamab in ES-SCLC (shared by Dr Amol Akhade)
[Slide 1] 16:30 - 18:15 Presidential Symposium I CHAIRS: FABRICE ANDRÉ, JAMES LARKIN Tarlatamab: DeLLphi-305: Efficacy [Thumbnail of DeLLphi-305 OS KM curve: 21.1 (20.8–NE) vs 12.7 (11.2–14.8); HR 0.42 (0.32–0.54); P < 0.001; 92%/75% at 6 mo, 79%/53% at 12 mo] | DeLLphi-305 (Tarla/Durva vs Durva) | IMforte (Lurbi/Atezo vs Atezo) Median OS | 21.1 vs 12.7m | 13.2 vs 10.6m 1y OS rate | 79% vs 53% | 56% vs 44% OS HR | 0.42 | 0.73 Median PFS | 7.4 vs 1.9m | 5.4 vs 2.1m 1y PFS rate | 38% vs 10% | 21% vs 12% PFS HR | 0.34 | 0.54 • Real signs of durable benefit • With 16m median follow up • 79% of patients alive at 1 year • 44% of patients remain on tarlatamab • Is tarlatamab changing SCLC biology? • Treatment beyond progression permitted • Local therapy could be employed to address oligoprogression • CNS efficacy? • QoL, PROs? • Long-term, landmark survival? Sands, ESMO 2026 Stephen Liu, MD Stephen Liu — Invited Discussant LBA3 ALICANTE AUDITORIUM - HALL 6 --- [Slide 2] 16:30 - 18:15 Presidential Symposium I CHAIRS: FABRICE ANDRÉ, JAMES LARKIN Tarlatamab: DeLLphi-305: Safety CRSa,b, n (%) | Tarlatamab + Durvalumab (n = 282) | Durvalumab (n = 278) Any grade | 140 (49.6) | 4 (1.4) Grade 2 | 21 (7.4) | 2 (0.7) Grade 3 | 1 (0.4) | 0 (0.0) Grade 4 | 0 (0.0) | 0 (0.0) Serious adverse events | 36 (12.8) | 2 (0.7) Leading to discontinuation of tarlatamab | 1 (0.4) | NA Fatal adverse events | 0 (0.0) | 0 (0.0) Utilization of any CRS interventionsc | 65 (23.0) | 2 (0.7) • CRS seen in 50% of patients • 84% of CRS cases were grade 1 • Likely under-reporting with less observation but did not translate into high grade CRS • CRS leading to discontinuation of tarlatamab in one patient (0.4%) • Due to less disease burden? Sands, ESMO 2026 Stephen Liu, MD [Speaker panel] Stephen Liu | Invited Discussant LBA3 ALICANTE AUDITORIUM - HALL 6 --- [Slide 3] 16:30 - 18:15 Presidential Symposium I CHAIRS: FABRICE ANDRÉ, JAMES LARKIN Other Questions • Should we be starting even earlier? • Integration into induction could increase impact but does it impact efficacy/safety? • Limited stage consolidation? • Would other induction strategies be more effective? • Antibody drug conjugates can induce very deep responses • Better partners for T-cell engagers? • Role for bispecific antibodies to replace checkpoint inhibitors? • Optimal dosing schedule and duration of therapy? • Patient selection and biomarkers Stephen Liu, MD [Speaker panel] Stephen Liu | Invited Discussant LBA3 ALICANTE AUDITORIUM - HALL 6
Hidehito HORINOUCHI @HHorinouchi · 2026-10-24
DeLLphi-305 · ESMO 2026 · Oct 24, 2026
Discussant: Stephen Liu, MD (LBA3) - context slides
View on X
DeLLphi-305 ESMO 2026 conference slide — trial design schema: attrition and rationale for maintenance strategies in SCLC (shared by Hidehito HORINOUCHI)DeLLphi-305 ESMO 2026 conference slide — subgroup analysis: DLL3 expression as a potential predictive biomarker for tarlatamab (shared by Hidehito HORINOUCHI)DeLLphi-305 ESMO 2026 conference slide — trial design schema: select T-cell engager trials in development for SCLC (shared by Hidehito HORINOUCHI)
[Slide 1] Attrition and the Rationale for Maintenance Strategies • Despite high rates of relapse, most patients do not receive any second-line therapy • Prospective LALUCA registry • 203 patients with ES-SCLC • 37% received second-line therapy • Maintenance strategies appealing in SCLC • Expect deepening of RR & prolongation of PFS at the cost of added toxicity • Relevant endpoint is survival [Sankey chart: N patients by treatment line 1–3; line 1: Chemoimmunotherapy (88.7%), Chemotherapy (11.3%); line 2: Anthracycline combination (57.3%), Chemo+/-immunotherapy (16.0%), Topotecan (26.7%); line 3: Anthracycline combination (32.1%), Chemo+/-immunotherapy (32.1%), Topotecan (28.6%), Other (7.2%)] Trial | Maintenance Agent | Overall Survival E7593 (Schiller, JCO 2001) | Topotecan | OS 8.9 vs 9.3m (ns) NCIC BR.20 (Arnold, JCO 2007) | Vandetanib | OS HR 1.43 (ns) CALGB 30504 (Ready, JCO 2015) | Sunitinib | OS HR 1.28 (ns) CheckMate 451 (Owonikoko, JCO 2021) | Nivolumab / Nivolumab + Ipilimumab | OS HR 0.84 (ns) / OS HR 0.92 (ns) STOMP (Woll, Lung Cancer 2022) | Olaparib bid / Olaparib tid | OS HR 0.85 (ns) / OS HR 1.03 (ns) Moser, Lung Cancer 2026 Stephen Liu, MD --- [Slide 2] Tarlatamab: Predictive Biomarkers? • Positive or negative predictive biomarkers could help guide strategies • DLL3 expression has potential in this setting • DeLLphi-304: 2L tarlatamab vs chemotherapy [DeLLphi-304 OS KM inset: Tarlatamab (n = 254) vs Chemotherapy (n = 255); Median OS, months 13.6 vs 8.3; HR (Tarlatamab/Chemotherapy) (95% CI) 0.60 (0.47, 0.77); p-value (2-sided) p < 0.001; labels 76% / 62% at 6 months, 53% / 37% at 12 months; Number at risk: Tarlatamab 254, 220, 192, 131, 60, 17, 0; Chemotherapy 255, 210, 156, 97, 42, 9, 2, 0] DLL3 IHC | Tarlatamab OS | Chemo OS | OS HR < 25% | 7.8 months | 7.9 months | 0.954 ≥ 25% | 17.1 months | 9.6 months | 0.505 • DLL3 expression on CTCs being explored • DLL3 high: RR 75% • DLL3 low: RR 11% [Waterfall plot: RECIST change from baseline by patient with DLL3 % row] Rudin, ASCO 2025; EMA EPAR; Mishra, Cancer Disc 2026 Stephen Liu, MD --- [Slide 3] Select T-Cell Engagers in Development for SCLC Trial | T-Cell Engager | Study Phase | Description DeLLphi-312 | Tarlatamab | Phase III | First-line carboplatin + etoposide + durvalumab +/- tarlatamab DeLLphi-306 | Tarlatamab | Phase III | Consolidation tarlatamab vs placebo post chemoradiation DeLLphi-315 | Tarlatamab | Phase III | Second-line subcutaneous vs IV DAREON-Lung-1 | Obrixtamig | Phase III | First-line carboplatin + etoposide + atezolizumab +/- obrixtamig DAREON-Rosetta35 | Obrixtamig | Phase Ib/II | Obrixtamig + pumitamig +/- carboplatin + etoposide MK-6070-003 | Gocatamig | Phase Ib/II | Gocatamig + I-DXd +/- atezolizumab vs chemo-IO MK-6070-002 | Gocatamig | Phase Ib/II | Gocatamig, gocatamig + I-DXd, gocatamig + durvalumab Stephen Liu, MD
KOL-Made Infographics
Physician-made summaries of DeLLphi-305 (LBA3) — secondary commentary, not presented slides
DeLLphi-305 ESMO 2026 KOL-made infographic summarizing LBA3 results (shared by Aakash Desai)@ADesaiMDDeLLphi-305 ESMO 2026 KOL-made infographic summarizing LBA3 results (shared by gilberto lopes)@GlopesMdDeLLphi-305 ESMO 2026 KOL-made infographic summarizing LBA3 results (shared by MV Chandrakanth)@ChandrakanthMvDeLLphi-305 ESMO 2026 KOL-made infographic summarizing LBA3 results (shared by MV Chandrakanth)@ChandrakanthMvDeLLphi-305 ESMO 2026 KOL-made infographic summarizing LBA3 results (shared by MV Chandrakanth)@ChandrakanthMvDeLLphi-305 ESMO 2026 KOL-made infographic summarizing LBA3 results (shared by Dr. Estela Rodriguez)@Latinamd

ESMO 2026 slides

Slides from ESMO 2026 (Madrid) as photographed and shared on X by physicians, newest first. Each post is shown verbatim; click any slide to enlarge, and open the OCR text under each post. All ESMO 2026 DeLLphi-305 slides in the KOL Pulse slide library →

Raffaele Giusti (@oncoblogger)
Raffaele Giusti @oncoblogger
DeLLphi-305 · ESMO 2026 slides
Oct 25, 2026 · ESMO 2026
View on X ↗
DeLLphi-305 appendix @NEJM : a DLL3 T-cell engager was given at progression to 64% of control patients in the USA vs 5% in Europe. OS HR: Americas 0.82 (0.39–1.71) vs Europe 0.36. Small subgroups, but in the TCE era OS depends on 2L access. Same trial, different answer. #ESMO26 https://t.co/GwhlVg8T1x
Table S4. Subsequent Anti-Cancer Treatment by Region | Tarlatamab + Durvalumab: USA (N = 16) | Japan (N = 28) | EU (N = 132) | Others (N = 106) | Durvalumab: USA (N = 22) | Japan (N = 21) | EU (N = 140) | Others (N = 95) Patients reporting subsequent anti-cancer treatment, n (%) | 8 (50.0) | 17 (60.7) | 35 (26.5) | 44 (41.5) | 16 (72.7) | 17 (81.0) | 85 (60.7) | 61 (64.2) All chemotherapy | 5 (31.3) | 15 (53.6) | 31 (23.5) | 40 (37.7) | 5 (22.7) | 14 (66.7) | 69 (49.3) | 47 (49.5) Anti DLL3 Therapy | 0 (0.0) | 3 (10.7) | 1 (0.8) | 2 (1.9) | 14 (63.6) | 8 (38.1) | 10 (7.1) | 8 (8.4) T cell engager | 0 (0.0) | 3 (10.7) | 0 (0.0) | 0 (0.0) | 14 (63.6) | 8 (38.1) | 7 (5.0) | 5 (5.3) ADC | 0 (0.0) | 0 (0.0) | 1 (0.8) | 1 (0.9) | 0 (0.0) | 0 (0.0) | 1 (0.7) | 0 (0.0) Unspecified | 0 (0.0) | 0 (0.0) | 0 (0.0) | 1 (0.9) | 0 (0.0) | 0 (0.0) | 2 (1.4) | 3 (3.2) Radiation | 2 (12.5) | 3 (10.7) | 4 (3.0) | 8 (7.5) | 1 (4.5) | 2 (9.5) | 7 (5.0) | 10 (10.5) Other | 1 (6.3) | 2 (7.1) | 0 (0.0) | 1 (0.9) | 0 (0.0) | 2 (9.5) | 0 (0.0) | 3 (3.2) ADC other than DLL3 | 0 (0.0) | 0 (0.0) | 2 (1.5) | 5 (4.7) | 0 (0.0) | 2 (9.5) | 3 (2.1) | 16 (16.8) PD-(L)1 Checkpoint Inhibitor | 1 (6.3) | 1 (3.6) | 4 (3.0) | 6 (5.7) | 2 (9.1) | 0 (0.0) | 5 (3.6) | 13 (13.7) Tyrosine Kinase Inhibitor | 0 (0.0) | 0 (0.0) | 0 (0.0) | 7 (6.6) | 0 (0.0) | 0 (0.0) | 1 (0.7) | 20 (21.1) The subsequent anti-cancer therapy was based on pre-defined list of categories and preferred terms. Some of the treatments were given in combination but listed separately. Concomitant medications were coded using the WHO Drug Dictionary version GLOBALB3Mar26. ADC, antibody-drug conjugate; DLL3, Delta-like ligand 3; EU, Europe; N, number of patients in the analysis set; n, number of patients with observed data; PD-(L)1, programmed cell death-(ligand) 1; USA, United States of America; WHO, World Health Organization. Figure S3. Overall Survival Analysis in Prespecified Subgroups Subgroup | Tarlatamab + Durvalumab no. of events / no. of patients | Durvalumab | Hazard Ratio for Death (95% CI) Age < 65 years | 34 / 139 | 69 / 133 | 0.36 (0.24-0.54) Age ≥ 65 years | 53 / 143 | 87 / 148 | 0.48 (0.34-0.67) Sex Male | 64 / 197 | 120 / 201 | 0.38 (0.28-0.51) Sex Female | 23 / 85 | 36 / 80 | 0.56 (0.33-0.94) Race White | 54 / 163 | 108 / 181 | 0.40 (0.29-0.56) Race Black | 0 / 4 | 0 / 4 | - Race Asian | 31 / 109 | 45 / 92 | 0.47 (0.30-0.74) Race Other | 2 / 6 | 3 / 4 | - Region Americas | 13 / 36 | 16 / 39 | 0.82 (0.39-1.71) Region Asia-Pacific | 32 / 114 | 51 / 101 | 0.43 (0.28-0.67) Region Europe | 42 / 132 | 89 / 141 | 0.36 (0.25-0.52) Presence (previous or current) of brain metastases Yes | 15 / 55 | 26 / 56 | 0.49 (0.26-0.93) Presence (previous or current) of brain metastases No | 72 / 227 | 130 / 225 | 0.41 (0.30-0.54) Presence (previous or current) of liver metastases Yes | 43 / 88 | 69 / 95 | 0.41 (0.28-0.61) Presence (previous or current) of liver metastases No | 44 / 194 | 87 / 186 | 0.40 (0.28-0.57) Presence (previous or current) of brain metastases and/or liver metastases Yes | 52 / 131 | 84 / 134 | 0.45 (0.32-0.64) Presence (previous or current) of brain metastases and/or liver metastases No | 35 / 151 | 72 / 147 | 0.38 (0.25-0.57) Response to initial therapy CR/PR | 77 / 251 | 135 / 248 | 0.42 (0.32-0.56) Response to initial therapy SD | 10 / 31 | 21 / 33 | 0.40 (0.19-0.85) Type of platinum first received for ES-SCLC Cisplatin | 11 / 44 | 23 / 44 | 0.33 (0.16-0.67) Type of platinum first received for ES-SCLC Carboplatin | 76 / 238 | 132 / 236 | 0.44 (0.34-0.59) Number of durvalumab cycles prior to enrollment 3 | 13 / 56 | 27 / 51 | 0.36 (0.19-0.70) Number of durvalumab cycles prior to enrollment 4 | 74 / 226 | 129 / 230 | 0.44 (0.33-0.58) Received prophylactic cranial irradiation (PCI) Yes | 3 / 14 | 1 / 4 | - Received prophylactic cranial irradiation (PCI) No | 84 / 268 | 155 / 277 | 0.42 (0.32-0.55) Disease stage at diagnosis Stage IV | 87 / 269 | 151 / 269 | 0.44 (0.33-0.57) Disease stage at diagnosis Non-Stage IV | 0 / 13 | 5 / 12 | - Tarlatamab + Durvalumab Better | Durvalumab Better
OncoHULA (@OncoHULA)
OncoHULA @OncoHULA
DeLLphi-305 · ESMO 2026 slides
Oct 24, 2026 · ESMO 2026
View on X ↗
A new SoC in extensive disease small cell lung cancer: Durvalumab plus Tarlatamab. 79% patients alive at 1 year. #ESMO26 #LungCancer @myESMO @_SEOM @gecp_org https://t.co/4rU7MpgZoh
[Slide 1] Tarlatamab: DeLLphi-305: Efficacy [KM curve legend] Tarlatamab + Durvalumab (n = 282) | Durvalumab (n = 281) Median OS, months (95% CI) | 21.1 (20.8–NE) | 12.7 (11.2–14.8) Median FU, months | 15.9 | 16.1 HR (95% CI); P-value (2-sided)a | 0.42 (0.32–0.54); P < 0.001 Curve labels: 92% | 75% (6 months); 79% | 53% (12 months) Tarlatamab + Durvalumab Durvalumab Percentage of Patients Months: 0 3 6 9 12 15 18 21 24 27 Number of patients at risk: Tarlatamab + Durvalumab | 282 | 276 | 258 | 246 | 222 | 132 | 55 | 9 | 0 Durvalumab | 281 | 252 | 208 | 171 | 146 | 81 | 33 | 8 | 1 | 0 [Table] | DeLLphi-305 Tarla/Durva vs Durva | IMforte Lurbi/Atezo vs Atezo Median OS | 21.1 vs 12.7m | 13.2 vs 10.6m 1y OS rate | 79% vs 53% | 56% vs 44% OS HR | 0.42 | 0.73 Median PFS | 7.4 vs 1.9m | 5.4 vs 2.1m 1y PFS rate | 38% vs 10% | 21% vs 12% PFS HR | 0.34 | 0.54 • Real signs of durable benefit • With 16m median follow up • 79% of patients alive at 1 year • 44% of patients remain on tarlatamab • Is tarlatamab changing SCLC biology? • Treatment beyond progression permitted • Local therapy could be employed to address oligoprogression • CNS efficacy? • QoL, PROs? • Long-term, landmark survival? Sands, ESMO 202[cut off] Stephen Liu, MD Survival table Endpoint: Overall survival Arm | N | Median | Median CI Tarlatamab + Durvalumab | 282 | 21.1 months | 20.8–NE Durvalumab | 281 | 12.7 months | 11.2–14.8 HR: 0.42 HR CI: 0.32–0.54 P: P < 0.001 (2-sided) Landmark rates: 6 months: Tarlatamab + Durvalumab 92% | Durvalumab 75% 12 months: Tarlatamab + Durvalumab 79% | Durvalumab 53% [Slide 2] Tarlatamab: DeLLphi-305: Delivery • Initial tarlatamab package insert required 22-24h observation C1D1 and C1D8 • Significant barrier to access; many sites lack experience and infrastructure • Updated tarlatamab package insert reduces observation to 6-8 hours • DeLLphi-305 • Tarlatamab given C1D1, C1D8, C1D15 and then Q2W • Premedication with dexamethasone 8mg IV C1D1 and C1D8 only • Hydration with 1L NS after tarlatamab C1D1 and C1D8 • All treatment delivered as an outpatient • Post-infusion monitoring for 1-2 hours (6-8 hours in EU) Sands, ESMO 2026 and author communication Stephen Liu, MD
C. Michael Gibson MD (@CMichaelGibson)
C. Michael Gibson MD @CMichaelGibson
DeLLphi-305 · ESMO 2026 slides
Oct 24, 2026 · ESMO 2026
View on X ↗
In a prespecified interim analysis of a phase 3 trial involving patients with extensive-stage SCLC, the median overall survival was 21.1 months with #Tarlatamab maintenance therapy and 12.7 months with durvalumab alone. #ESMO26 https://t.co/xuqEkJZSSn https://t.co/FBAHoeWXyv
Fred R. Hirsch (@fred_hirsch)
Fred R. Hirsch @fred_hirsch
DeLLphi-305 · ESMO 2026 slides
Oct 24, 2026 · ESMO 2026
View on X ↗
Amazing result from Delphi 305 study in SCLC presented at ESMO! Tarlatamab plus Durvalumab as maintenance in 1.line treatment most likely new standard. However, better than Tarlatamab in 2.line, which is current SOC? https://t.co/61P4GpLYgx
[Slide 1] Tarlatamab: DeLLphi-305: Survival | Tarlatamab + Durvalumab (n = 282) | Durvalumab (n = 281) Median OS, months (95% CI) | 21.1 (20.8–NE) | 12.7 (11.2–14.8) Median FU, months | 15.9 | 16.1 HR (95% CI); P-value (2-sided)a | 0.42 (0.32–0.54); P < 0.001 Curve labels: 92% / 79% (Tarlatamab + Durvalumab); 75% / 53% (Durvalumab) at dashed reference lines (~6 and ~12 months) Percentage of Patients; Months (0, 3, 6, 9, 12, 15, 18, 21, 24, 27) Number of patients at risk: Tarlatamab + Durvalumab | 282 | 276 | 258 | 246 | 222 | 132 | 55 | 9 | 0 Durvalumab | 281 | 252 | 208 | 171 | 146 | 81 | 33 | 8 | 1 | 0 Stephen Liu, MD Sands, ESMO 2026 Survival table Endpoint: Overall survival Arm | N | Median | Median CI Tarlatamab + Durvalumab | 282 | 21.1 months | 20.8–NE Durvalumab | 281 | 12.7 months | 11.2–14.8 HR: 0.42 HR CI: 0.32–0.54 P: P < 0.001 (2-sided) Landmark rates: 6 months (dashed line; inferred): Tarlatamab + Durvalumab 92% | Durvalumab 75% 12 months (dashed line; inferred): Tarlatamab + Durvalumab 79% | Durvalumab 53%
Giannis Mountzios (@g_mountzios)
Giannis Mountzios @g_mountzios
DeLLphi-305 · ESMO 2026 slides
Oct 24, 2026 · ESMO 2026
View on X ↗
#ESMO26 Presidential 1 Excellent state-of-the art discussion on #Dellphi-305 by the 1@only @StephenVLiu emphasizing on: ➡️ 1L maintenance Tarla setting a new SoC with a mOS of>20 months ❓High attrition rate from induction to maintenance, need for earlier TCE ( Dellphi-312) ❌Only 19% of pts in control arm received 2L Tarla post-progression reflecting access hurdles ✅ Global access to Tarla will make innovation meaningful for our patients @@myESMO #ESMOAmbassadors
[Slide 1] Small Cell Lung Cancer • Multiple randomized phase III trials have reinforced these results Trial | Agent | mOS | OS HR | FDA approval | EMA approval IMpower 133 | Atezolizumab | 12.3m | 0.70 | March 18, 2019 | September 6, 2019 CASPIAN | Durvalumab | 13.0m | 0.73 | March 27, 2020 | September 1, 2020 ASTRUM-005 | Serplulimab | 15.4m | 0.63 | N/A | February 3, 2025 • Long-term survival possible for a small subset of patients [Inset KM curve, small print:] | Atezo + CP/ET (n=201) | Placebo + CP/ET (n=202) OS events, n (%) | 159 (79.1) | 169 (83.7) Median OS (95% CI), months | 12.3 (10.8, 15.8) | 10.3 (9.3, 11.3) Atezo + CP/ET median follow-up: 59.4 months (range, 0.0-72.6) Placebo + CP/ET median follow-up: 26.4 months (range, 0.0-34.4) 5-year OS, 12% [Number-at-risk rows too small to read reliably — [illegible]] OS rate (95% CI), % | IMpower133 and IMbrella Aᵃ Atezolizumab + CE (n=201)ᵇ | IMpower133 only Placebo + CE (n=202) 1 yearᵇ,⁶ | 51.9 (44.6, 59.1) | 39.0 (32.1, 45.9) 2 yearsᵇ,¹² | 21.6 (15.5, 27.6) | 16.1 (10.8, 21.3) 3 yearsᶜ,¹³ | 15.9 (10.5, 21.3) | NE 4 yearsᶜ,¹³ | 12.8 (7.7, 17.9) | NE 5 yearsᶜ,¹³ | 11.9 (6.8, 16.9) | NE 6 yearsᶜ,¹⁴ | 10.8 (5.8, 15.8) | NE 7 yearsᶜ | 10.8 (5.8, 15.8) | NE Stephen Liu, MD Horn, NEJM 2018; Paz-Ares, Lancet 2019; Cheng, JAMA 2022; Liu, WCLC 2023; Reck, ELCC 2026 [Slide 2] Conclusions • Adding tarlatamab to maintenance durvalumab significantly improves survival • Better safety profile and monitoring requirements in the maintenance setting • Global access to agents like tarlatamab will be critical Stephen Liu, MD
Oncology Brothers (@OncBrothers)
Oncology Brothers @OncBrothers
DeLLphi-305 · ESMO 2026 slides
Oct 24, 2026 · ESMO 2026
View on X ↗
4. DeLLphi305: PhIII, Tarlatamab + Durva vs Durva alone as 1L maintenance after chemo-IO in ES-SCLC (n=563): - mOS: 21.1 vs 12.7 mos (HR 0.42) - 12-mo OS: 79.4% vs 53.3% - mPFS: 7.4 vs 1.9 mo (HR 0.34) - ORR: 26.4% vs 4.1% - G≥3 AEs: 46.8% vs 40.6%; CRS 49.6% - New SoC! 5/5 https://t.co/NQmSyXYXJl https://t.co/I3fXwYlX48
Renee Maria Saliby (@ReneeSaliby)
Renee Maria Saliby @ReneeSaliby
DeLLphi-305 · ESMO 2026 slides
Oct 24, 2026 · ESMO 2026
View on X ↗
✨✨Hope alert: @sands_jacob shows that adding tarla to durva for maintenance therapy significantly improves survival to 21.1mo! Followed by a masterful discussion by @StephenVLiu integrating clinical outcomes including tox, translational thoughts, and accessibility! "We cannot allow the inequities in the delivery of our care be our legacy" #ESMO26 @OncoAlert
Enes Erul MD (@ErulEnes)
Enes Erul MD @ErulEnes
DeLLphi-305 · ESMO 2026 slides
Oct 24, 2026 · ESMO 2026
View on X ↗
The moment I saw the overall survival curves, I wanted to stand up and applaud! 👏 40,000 of us at #ESMO26, sharing the same excitement and hope not for ourselves, but for our patients. ❤️ A truly emotional moment in #SCLC. #DeLLphi305 @StephenVLiu @sands_jacob @lungoncdoc https://t.co/FxDFvv1EMP
Tian Zhang, MD, MHS, FASCO (@tiansterzhangmd.bsky) (@TiansterZhang)
DeLLphi-305 · ESMO 2026 slides
Oct 24, 2026 · ESMO 2026
View on X ↗
Learning about small cell lung from thoughtful discussant @StephenVLiu — new group of non smokers w small cell & w high clinical need for new treatments. Always mindful on patient access turning advances into impact. @oncoalert #ESMO26 @myESMO https://t.co/ICIlQB7mgz
[Slide 1] Tarlatamab: DeLLphi-305: Safety ICANSa, n (%) | Tarlatamab + Durvalumab (n = 282) | Durvalumab (n = 27[?]) Any grade | 3 (1.1) | 0 (0.0) Grade 2 | 1 (0.4) | 0 (0.0) Grade 3 | 0 (0.0) | 0 (0.0) Grade 4 | 0 (0.0) | 0 (0.0) Serious adverse events | 0 (0.0) | 0 (0.0) Leading to discontinuation of tarlatamab | 0 (0.0) | NA Fatal adverse events | 0 (0.0) | 0 (0.0) • ICANS seen in 1% of patients • Only 3 cases (2 grade 1 and 1 grade 2 with no grade 3+) • Due to less disease burden? • Due to omitting hospitalization? Stephen Liu, MD Sands, ESMO 2026 [Slide 2] Tarlatamab: DeLLphi-305: Safety CRSa,b, n (%) | Tarlatamab + Durvalumab | Durvalumab Any grade | [illegible] | [illegible] Grade 2 | [illegible] | [illegible] Grade 3 | 1 (0.4) | [illegible] Grade 4 | 0 (0.0) | 0 (0.0) Serious adverse events | 36 (12.8) | 2 (0.7) Leading to discontinuation of tarlatamab | 1 (0.4) | NA Fatal adverse events | 0 (0.0) | 0 (0.0) Utilization of any CRS interventionsc | 65 (23.0) | 2 (0.7) • CRS seen in 50% of patients • 84% of CRS cases were grade 1 • Likely under-reporting with less observation but did not translate into high grade CRS • CRS leading to discontinuation of tarlatamab in one patient (0.4%) • Due to less disease burden? Sands, ESMO 2026
Noemi Reguart (@NReguart)
Noemi Reguart @NReguart
DeLLphi-305 · ESMO 2026 slides
Oct 24, 2026 · ESMO 2026
View on X ↗
Outstanding discussion by @StephenVLiu on the practice-changing DeLLphi-305 trial @sands_jacob . A new chapter in the treatment of ES-SCLC! #ESMO26. One year ago, we anticipated that we might finally be bending gravity. Today, that vision is becoming a reality!!!!!!👏👏👏👏👏 https://t.co/QDMrTH5l8L
[Vision transcription of the photographed slide; small print not legible] Small Cell Lung Cancer — SCLC characterized by initial response to therapy and predictable relapse • CASPIAN: durvalumab — OS HR 0.73, mOS 13.0m • IMpower 133: atezolizumab Discussant: Stephen Liu, MD
Philippe Aftimos, MD  (@aftimosp)
DeLLphi-305 · ESMO 2026 slides
Oct 24, 2026 · ESMO 2026
View on X ↗
I very much enjoyed the discussion by @StephenVLiu of DeLLphi-305 (tarlatamab + durvalumab as maintenance therapy in ES-SCLC at #ESMO26 👏👏👏 #ESMOAmbassadors https://t.co/Wl31gpUtEu
[Slide 1] Other Questions • Should we be starting even earlier? • Integration into induction could increase impact but does it impact efficacy/safety? • Limited stage consolidation? • Would other induction strategies be more effective? • Antibody drug conjugates can induce very deep responses • Better partners for T-cell engagers? • Role for bispecific antibodies to replace checkpoint inhibitors? • Optimal dosing schedule and duration of therapy? • Patient selection and biomarkers Stephen Liu, MD [Slide 2] Tarlatamab: Predictive Biomarkers? • Positive or negative predictive biomarkers could help guide strategies • DLL3 expression has potential in this setting • DeLLphi-304: 2L tarlatamab vs chemotherapy [Small embedded DeLLphi-304 OS KM curve, tarlatamab vs chemotherapy — values too small to read] DLL3 IHC | Tarlatamab OS | Chemo OS | OS HR < 25% | 7.8 months | 7.9 months | 0.954 ≥ 25% | 17.1 months | 9.6 months | 0.505 • DLL3 expression on CTCs being explored • DLL3 high: RR 75% • DLL3 low: RR 11% [Small embedded waterfall plot with DLL3% row — values too small to read] Rudin, ASCO 2025; EMA EPAR; Mishra, Cancer Disc 2026 Stephen Liu, MD
Balazs Halmos (@BalazsHalmosMD)
Balazs Halmos @BalazsHalmosMD
DeLLphi-305 · ESMO 2026 slides
Oct 24, 2026 · ESMO 2026
View on X ↗
@StephenVLiu highlights the profound/fundamental benefits of starlatamab in DeLLphi in an exceptional discussion: ☑️PFS ☑️OS ☑️manageable tox ☑️changing biology And sounding and looking like the best ever sports broadcaster- lets just say it in sports terms: This study achieved a real grand slam against SCLC! #lcsm #ESMO26
[Slide 2] Bispecific T-Cell Engagers • Strong rationale that BiTEs perform better in low disease burden states • Greater effector molecule to target ratio • Greater tumor accessibility for T-cells • Less antigen mass may decrease CRS and ICANS • Less T-cell exhaustion from chronic antigen stimulation • Decreased heterogeneity and potentially fewer antigen-negative clone [Diagram: T cell – CD3 – DLL3 – SCLC cell] Goebeler, Nat Rev Clin Oncol 2020; Owonikoko, ASCO 2021 Stephen Liu, MD
Tian Zhang, MD, MHS, FASCO (@tiansterzhangmd.bsky) (@TiansterZhang)
DeLLphi-305 · ESMO 2026 slides
Oct 24, 2026 · ESMO 2026
View on X ↗
@sands_jacob with Dellphi305 — tarlatamab w durvalumab vs durvalumab for small cell lung cancer — almost doubling of overall survival w manageable CRS & outpatient treatment. Standing ovation for small cell! @nejm concurrent pub today. @oncoalert @myESMO #ESMO26 https://t.co/Z25EA6hQL2
Dr Amol Akhade (@SuyogCancer)
Dr Amol Akhade @SuyogCancer
DeLLphi-305 · ESMO 2026 slides
Oct 24, 2026 · ESMO 2026
View on X ↗
Great discussion as always by great orator of our times . This gives great hope in disease where hope is in short supply. @StephenVLiu 👍 @myESMO #ESMO26 @OncoAlert https://t.co/I614b8cVpm
[Slide 1] 16:30 - 18:15 Presidential Symposium I CHAIRS: FABRICE ANDRÉ, JAMES LARKIN Tarlatamab: DeLLphi-304 • Cytokine release syndrome (CRS) • Immune effector cell neurotoxicity syndrome (ICANS) • Initial recommendation for 22-24h observation on cycle 1, days 1 and 8 [Bar chart] Percentage of patients, % | CRS | ICANS Overall* | 56 | 6 Grade 1 | 42 | 3 Grade 2 | 13 | 3 Grade 3 | 1 | 0 Serious | 17 | 4 Discontinuations | 0.4 | 0.4 Fatal | 0 | 0.4 Table 1. Recommended Dosage and Schedule of IMDELLTRA Dosing Schedule | Day | Dose of IMDELLTRA | Administration Instructions | Recommended Monitoring Step-up Dosing Schedule Cycle 1 | Day 1a | Step-up dosea 1 mg | Administer IMDELLTRA as a 1-hour intravenous infusion in an appropriate healthcare setting. | Monitor patients from the start of the IMDELLTRA infusion for 22 to 24 hours on Cycle 1 Day 1 and Cycle 1 Day 8 in an appropriate healthcare setting. Recommend that patients remain within 1-hour of an appropriate healthcare setting for a total of 48 hours from start of the infusion with IMDELLTRA, accompanied by a caregiver. | Day 8a | 10 mga | | | Day 15 | 10 mg | | Observe patients for 6-8 hours post IMDELLTRA infusiona. Rudin, ASCO 2025; FDA.gov Stephen Liu, MD [Speaker panel] Stephen Liu | Invited Discussant LBA3 ALICANTE AUDITORIUM - HALL 6
Alfredo Addeo MD (@Alfdoc2)
Alfredo Addeo MD @Alfdoc2
DeLLphi-305 · ESMO 2026 slides
Oct 24, 2026 · ESMO 2026
View on X ↗
🔥 DeLLphi-305 shook the room at #ESMO26 and what a spectacular discussion by @StephenVLiu Outstanding data deserve an equally outstanding discussion, and Stephen delivered! 👏 💥 OS HR 0.42 , unprecedented impact in ES-SCLC! Key questions: CNS efficacy, long-term survival, predictive biomarkers and optimal treatment sequencing. Encouraging outpatient feasibility and improved monitoring requirements. And one crucial message: global access to this breakthrough treatment must become a priority. Spectacular science, spectacular discussion! A truly unforgettable ESMO Plenary! #ESMOAmbassadors #ESMO26 #DeLLphi305 #SCLC #LungCancer
Leonardo Brunetti (@Brunet3Leon)
Leonardo Brunetti @Brunet3Leon
DeLLphi-305 · ESMO 2026 slides
Oct 24, 2026 · ESMO 2026
View on X ↗
Striking results from DeLLphi-305 in SCLC topped with an emotional standing ovation. Mainteinance Tarlatamab is actually more like a second induction-treatment rather than a proper mainteinance! Kudos to @sands_jacob for the magistral presentation #ESMO26 #ESMOAmbassadors https://t.co/2w1PXt8jLu
Noemi Reguart (@NReguart)
Noemi Reguart @NReguart
DeLLphi-305 · ESMO 2026 slides
Oct 24, 2026 · ESMO 2026
View on X ↗
Impressive results from phase III DeLLphi-305 at #ESMO26 @sands_jacob: Adding tarlatamab to durvalumab maintenance in ES-SCLC 1-y OS nearly 80%!!! 🔹 OS: 21.1 vs 12.7 mo (HR 0.42) 🔹 PFS: 7.4 vs 1.9 mo (HR 0.34) A standing ovation!” 👏👏👏👏A major step forward for SCLC! @NEJM https://t.co/DLSwuhPS9W
[Slide 2] Tarlatamab plus durvalumab significantly improved PFS versus durvalumab DeLLphi 305 | Tarlatamab + Durvalumab (n = 282) | Durvalumab (n = 281) Median PFS, months (95% CI) | 7.4 (5.6–9.1) | 1.9 (1.9–2.0) Median FU, months | 13.9 | 13.9 HR (95% CI); P-value (2-sided)a | 0.34 (0.28–0.42); P < 0.001 Curve labels: 53% (Tarlatamab + Durvalumab, 6 mo) | 17% (Durvalumab, 6 mo) | 38% (Tarlatamab + Durvalumab, 12 mo) | 10% (Durvalumab, 12 mo) Percentage of Patients; Months 0 3 6 9 12 15 18 21 24 Number of patients at risk: Tarlatamab + Durvalumab | 282 | 225 | 147 | 122 | 86 | 32 | 14 | 1 | 0 Durvalumab | 281 | 106 | 46 | 36 | 18 | 8 | 2 | 0 Data cut-off date: 7 JUL 2026. At the time of data cut-off, 182 events had occurred in the tarlatamab-durvalumab arm, and 250 events had occurred in the durvalumab arm. aP-value was calculated using a stratified log-rank test. CI, confidence interval; FU, follow-up; HR, hazard ratio; PFS, progression-free survival. Jacob Sands, MD | Tarlatamab plus durvalumab as 1L M therapy in ES-SCLC: primary analysis from DeLLphi-305 phase 3 study [Side panel] Jacob Sands | Tarlatamab plus durvalumab (durva) vs durva as 1L maintenance (1LM) therapy following durva, platinum, and etoposide (1L durva + EP) in extensive-stage small cell lung cancer (ES-SCLC): Primary analysis of the phase 3 DeLLphi-305 trial Survival table Endpoint: Progression-free survival (PFS) Arm | N | Median | Median CI Tarlatamab + Durvalumab | 282 | 7.4 months | 5.6–9.1 Durvalumab | 281 | 1.9 months | 1.9–2.0 HR: 0.34 HR CI: 0.28–0.42 P: P < 0.001 (2-sided, stratified log-rank) Landmark rates: 6 months: Tarlatamab + Durvalumab 53% | Durvalumab 17% 12 months: Tarlatamab + Durvalumab 38% | Durvalumab 10%
Ryan Gentzler, MD (@ryangentzler)
Ryan Gentzler, MD @ryangentzler
DeLLphi-305 · ESMO 2026 slides
Oct 24, 2026 · ESMO 2026
View on X ↗
Expert discussion of DeLLphi-305 by @StephenVLiu. Bringing tarlatamab to maintenance is major advance as second line tarlatamab is often “a promise we cannot keep.” Many patients never receive 2nd line. #ESMO26 https://t.co/T6IRxIS8ev
Tarlatamab: DeLLphi-305: Study Design • Patients screened and enrolled after induction • PFS/OS does not include induction • Selected population – met inclusion criteria post-induction with no progression [Embedded study-design schematic:] 1L Chemo-IO: Platinum-etoposide + durvalumaba induction therapy (4 cycles) Key Inclusion Criteria: Age ≥ 18 years; No disease progression; ECOG PS 0–1; Asymptomatic untreated or treated brain metastasis R 1:1, N = 563 Treatment until progression or unacceptable toxicity Tarlatamab (10 mg Q2W)b + Durvalumab (1500 mg Q4W)c, n = 282 Durvalumab (1500 mg Q4W)c, n = 281 Primary Endpoint: OS | Key Secondary Endpoint: PFS | Secondary Endpoints: ORR, DOR, safety Stratification Factors: Brain and/or liver metastasis (Yes/No); Response to 1L chemo-IO (PR/CR vs SD); Prior platinum type (cisplatin vs carboplatin) Interim analysis for OS: 243 (61% IF) OS events, 0.008 two-sided P-value boundary Endpoints were tested sequentially according to a prespecified hierarchical testing strategy: OS → PFS → ORR Sands, ESMO 2026 Stephen Liu, MD
Uğur Özkerim (@UOzkerim)
Uğur Özkerim @UOzkerim
DeLLphi-305 · ESMO 2026 slides
Oct 24, 2026 · ESMO 2026
View on X ↗
🚨 Impressive results from #ESMO2026! Phase III DeLLphi-305: Tarlatamab + durvalumab vs durvalumab alone as 1L maintenance in ES-SCLC: 🔹 Median OS: 21.1 vs 12.7 months (HR 0.42) 🔹 Median PFS: 7.4 vs 1.9 months (HR 0.34) 🔹 ORR: 26.4% vs 4.1% 🔥 Practice-changing potential! #LungCancer #SCLC @OncoAlert @weoncologists @StephenVLiu @GlopesMd @ManuelDomine
MADRID 2026 ESMO congress Tarlatamab plus durvalumab vs durvalumab as first-line maintenance therapy following first-line durvalumab, platinum, and etoposide in extensive-stage small cell lung cancer: primary analysis of the phase 3 DeLLphi-305 trial Jacob Sands, Tatsuya Yoshida, Myung-Ju Ahn, Carl M. Gay, Martin Schuler, Haifeng Liu, Ahmet Sezer, Ahmet Bilici, Ippokratis Korantzis, Sun Min Lim, Isamu Okamoto, Oscar Juan-Vidal, Yuanbin Chen, Gustavo Schvartsman, Anne-Marie C. Dingemans, Jeffrey M. Clarke, Miguel Marigil, Yuyang Zhang, Bazle Abidi, Maurice Pérol Presenter: Jacob Sands, MD Dana-Farber Cancer Institute Boston, MA, United States of America 24 October 2026
Abeid Athman (Omar). (@bin_abeid)
DeLLphi-305 · ESMO 2026 slides
Oct 24, 2026 · ESMO 2026
View on X ↗
In DeLLphi-305: The combination of Tarlatamab+ Durvalumab improves both OS (21 vs 12 months HR 0.42) and PFS in ES-SCLC. This is remarkable in such a lethal disease with high recurrence rates and mortality. #ESMO2026 #ESMOAmbassadors @myESMO @StephenVLiu @tompowles1 @FAndreMD https://t.co/fE2K7k2Jha
Shankar Siva (@_ShankarSiva)
Shankar Siva @_ShankarSiva
DeLLphi-305 · ESMO 2026 slides
Oct 24, 2026 · ESMO 2026
View on X ↗
💥Game-changer in small cell #lungcancer! #ESMO26 LBA3 DeLLphi-305: Tarlatamab + durvalumab vs durvalumab 1L maintenance in ES-SCLC (n=563) after chemo-IO. Median OS ⬆️ 21.1 vs 12.7 mo (HR 0.42), PFS ⬆️7.4 vs 1.9 mo (HR 0.34), ORR 26% vs 4%. ☢️44% of pts still on T+D due to #radiotherapy of oligoprogressive sites? #SCLC #LCSM @NEJM ➡️ https://t.co/nhVH10CQZG
[Slide 1] Tarlatamab plus durvalumab significantly improved overall survival versus durvalumab alone as first-line maintenance therapy | Tarlatamab + Durvalumab (n = 282) | Durvalumab (n = 281) Median OS, months (95% CI) | 21.1 (20.8-NE) | 12.7 (11.2-14.8) Median FU, months | 15.9 | 16.1 HR (95% CI); P-value (2-sided)(a) | 0.42 (0.32-0.54); P < 0.001 Curve labels: 6 mo: 92% (T+D), 75% (D); 12 mo: 79% (T+D), 53% (D) Number of patients at risk: Months | 0 | 3 | 6 | 9 | 12 | 15 | 18 | 21 | 24 | 27 Tarlatamab + Durvalumab | 282 | 276 | 258 | 246 | 222 | 132 | 55 | 9 | 0 | Durvalumab | 281 | 252 | 208 | 171 | 146 | 81 | 33 | 8 | 1 | 0 Data cut-off date: 7 JUL 2026. At the time of data cut-off, 87 events had occurred in the tarlatamab-durvalumab arm, and 156 events had occurred in the durvalumab arm. (a)P value was calculated using a stratified log-rank test. Jacob Sands, MD | Tarlatamab plus durvalumab as 1L M therapy in ES-SCLC: primary analysis from DeLLphi-305 phase 3 study Survival table Endpoint: OS Tarlatamab + Durvalumab | 282 | 21.1 | 20.8-NE Durvalumab | 281 | 12.7 | 11.2-14.8 HR: 0.42 HR CI: 0.32-0.54 P: < 0.001 (2-sided, stratified log-rank) Landmark 6 months | Tarlatamab + Durvalumab | 92% Landmark 6 months | Durvalumab | 75% Landmark 12 months | Tarlatamab + Durvalumab | 79% Landmark 12 months | Durvalumab | 53%
Dr Amol Akhade (@SuyogCancer)
Dr Amol Akhade @SuyogCancer
DeLLphi-305 · ESMO 2026 slides
Oct 24, 2026 · ESMO 2026
View on X ↗
DeLLphi-305. Immpresive curves . Additional Toxicity and cost in real world needs to be seen . Good for patients with extensive SCLC @myESMO @OncoAlert #esmo26 https://t.co/V2CDG9m0ZR
[Slide 2] On-screen broadcast chrome: '16:30 - 18:15 Presidential Symposium I'; 'CHAIRS: FABRICE ANDRÉ, JAMES LARKIN'; speaker card 'Jacob Sands'; 'ALICANTE AUDITORIUM - HALL 6'. Tarlatamab plus durvalumab significantly improved overall survival versus durvalumab alone as first-line maintenance therapy DeLLphi 305 | Tarlatamab + Durvalumab (n = 282) | Durvalumab (n = 281) Median OS, months (95% CI) | 21.1 (20.8–NE) | 12.7 (11.2–14.8) Median FU, months | 15.9 | 16.1 HR (95% CI); P-value (2-sided)a | 0.42 (0.32–0.54); P < 0.001 Curve labels: Tarlatamab + Durvalumab 92% (6 mo), 79% (12 mo); Durvalumab 75% (6 mo), 53% (12 mo) Percentage of Patients / Months (0–27) Number of patients at risk: Months | 0 | 3 | 6 | 9 | 12 | 15 | 18 | 21 | 24 | 27 Tarlatamab + Durvalumab | 282 | 276 | 258 | 246 | 222 | 132 | 55 | 9 | 0 | Durvalumab | 281 | 252 | 208 | 171 | 146 | 81 | 33 | 8 | 1 | 0 Data cut-off date: 7 JUL 2026. At the time of data cut-off, 87 events had occurred in the tarlatamab-durvalumab arm, and 156 events had occurred in the durvalumab arm. aP value was calculated using a stratified log-rank test. CI, confidence interval; FU, follow-up; HR, hazard ratio; NE, not estimable; OS, overall survival. Jacob Sands, MD | Tarlatamab plus durvalumab as 1L M therapy in ES-SCLC: primary analysis from DeLLphi-305 phase 3 study Survival table Endpoint: Overall survival (ITT) Arm | N | Median | Median CI Tarlatamab + Durvalumab | 282 | 21.1 months | 20.8–NE Durvalumab | 281 | 12.7 months | 11.2–14.8 HR: 0.42 HR CI: 0.32–0.54 P: P < 0.001 (2-sided, stratified log-rank) Landmark rates: 6 months: Tarlatamab + Durvalumab 92% | Durvalumab 75% 12 months: Tarlatamab + Durvalumab 79% | Durvalumab 53%
Yago Garitaonaindía (@YGaritaonaindia)
Yago Garitaonaindía @YGaritaonaindia
DeLLphi-305 · ESMO 2026 slides
Oct 24, 2026 · ESMO 2026
View on X ↗
🔥🔥🔥 #ESMO26 DeLLphi-305 in @NEJM Tarlatamab + durva vs durva as 1L maintenance in ES-SCLC (n=563) ➡️ mOS 21.1 vs 12.7 mo | HR 0.42 ➡️ mPFS 7.4 vs 1.9 mo | HR 0.34 ➡️ ORR 26% vs 4% | CR 0.9% | mDoR 12.7 mo ➡️ G≥3 AEs 47% vs 41% | CRS in ~50%, mostly G1-2, manageable 🔍 OS here is a game changer. New 1L maintenance standard, ahead of lurbi-atezo. 🙋CRs almost absent and DoR ~1 year. Still far from the long-term tail we see with PD-1 blockade in other tumour types. We can’t cure without CRs @myESMO @_SEOM @OncoAlert @Larvol #LCSM #SCLC
[Slide 1] DeLLphi-305: Study design DeLLphi 305 A Phase 3, Open-label, Multicenter, Randomized Study of Tarlatamab in Combination With Durvalumab vs Durvalumab Alone in Patients With ES-SCLC Following Platinum, Etoposide and Durvalumab (NCT06211036) 1L Chemo-IO: Platinum-etoposide + durvalumab induction therapy (4 cycles) Key Inclusion Criteria • Age ≥ 18 years • No disease progression • ECOG PS 0–1 • Asymptomatic untreated or treated brain metastasis R 1:1 N = 563 Treatment until progression or unacceptable toxicity Tarlatamab (10 mg Q2W) + Durvalumab (1500 mg Q4W) n = 282 Durvalumab (1500 mg Q4W) n = 281 Primary Endpoint: OS Key Secondary Endpoint: PFS Secondary Endpoints: ORR, DOR, safety Stratification Factors • Brain and/or liver metastasis (Yes/No) • Response to 1L chemo-IO (PR/CR vs SD) • Prior platinum type (cisplatin vs carboplatin) Interim analysis for OS: 2[illegible]3 (61% IF) OS events, 0.00[illegible] two-sided P-value boundary Endpoints were tested sequentially according to a prespecified hierarchical testing strategy: OS → PFS → ORR [footnotes illegible] [footer, blurry:] Jacob Sands, MD | Tarlatamab plus durvalumab as 1L M therapy in ES-SCLC: primary analysis from DeLLphi-305 phase 3 study 4 [Slide 2] Tarlatamab plus durvalumab significantly improved overall survival versus durvalumab alone as first-line maintenance therapy DeLLphi 305 Tarlatamab + Durvalumab (n = 2[illegible]) | Durvalumab (n = 281) Median OS, months (95% CI): 21.1 (20.8–NE) | 12.7 (11.2–14.8) Median FU, months: [illegible] | [illegible] HR (95% CI); P-value (2-sided)a: 0.42 (0.32–0.5[illegible]); P < 0.001 Curve labels: Tarlatamab + Durvalumab 92% (6 mo), 79% (12 mo); Durvalumab 75% (6 mo), 53% (12 mo) Percentage of Patients / Months Number of patients at risk: Tarlatamab + Durvalumab: 282, 276, 258, 246, 222, 132, 55, 9, 0 Durvalumab: 281, 252, 208, 171, 146, 81, 33, 8, 1, 0 [footnotes illegible: data cut-off date, event counts] [footer, blurry:] Jacob Sands, MD | Tarlatamab plus durvalumab as 1L M therapy in ES-SCLC: primary analysis from DeLLphi-305 phase 3 study 6 Survival table Endpoint: OS Arm | N | Median | Median CI Tarlatamab + Durvalumab | 282 | 21.1 months | 20.8–NE Durvalumab | 281 | 12.7 months | 11.2–14.8 HR: 0.42 P: P < 0.001 (2-sided) Landmark rates: 6 mo: Tarlatamab + Durvalumab 92% | Durvalumab 75% 12 mo: Tarlatamab + Durvalumab 79% | Durvalumab 53% [Slide 3] Tarlatamab plus durvalumab significantly improved PFS versus durvalumab DeLLphi 305 Tarlatamab + Durvalumab (n = 282) | Durvalumab (n = 281) Median PFS, months (95% CI): 7.4 (5.6–9.1) | 1.9 (1.9–2.0) Median FU, months: 13.9 | 13.9 HR (95% CI); P-value (2-sided)a: 0.34 (0.28–0.42); P < 0.001 Curve labels: Tarlatamab + Durvalumab 53% (6 mo), 38% (12 mo); Durvalumab 17% (6 mo), 10% (12 mo) Number of patients at risk: Tarlatamab + Durvalumab: 282, 225, 147, 122, 86, 32, 14, 1, 0 Durvalumab: 281, 106, 46, 36, 18, 8, 2, 0 [footnotes illegible] [footer, blurry:] Jacob Sands, MD | Tarlatamab plus durvalumab as 1L M therapy in ES-SCLC: primary analysis from DeLLphi-305 phase 3 study 8 Survival table Endpoint: PFS Arm | N | Median | Median CI Tarlatamab + Durvalumab | 282 | 7.4 months | 5.6–9.1 Durvalumab | 281 | 1.9 months | 1.9–2.0 HR: 0.34 HR CI: 0.28–0.42 P: P < 0.001 (2-sided) Landmark rates: 6 mo: Tarlatamab + Durvalumab 53% | Durvalumab 17% 12 mo: Tarlatamab + Durvalumab 38% | Durvalumab 10%
Dr Riyaz Shah (@DrRiyazShah)
Dr Riyaz Shah @DrRiyazShah
DeLLphi-305 · ESMO 2026 slides
Oct 24, 2026 · ESMO 2026
View on X ↗
https://t.co/5qfQqQe9Yp
Toni Choueiri, MD (@DrChoueiri)
Toni Choueiri, MD @DrChoueiri
DeLLphi-305 · ESMO 2026 slides
Oct 24, 2026 · ESMO 2026
View on X ↗
Outstanding presentation by our very own @DanaFarber @sands_jacob ! DeLLphi-305: tarlatamab + durvalumab vs durvalumab as 1L maintenance in ES-SCLC improved median OS to 21.1 vs 12.7 months (HR 0.42). A major advance for patients with SCLC! #ESMO26 @oncoalert @myESMO https://t.co/UxKz3Qgjp7
Toni Choueiri, MD (@DrChoueiri)
Toni Choueiri, MD @DrChoueiri
DeLLphi-305 · ESMO 2026 slides
Oct 24, 2026 · ESMO 2026
View on X ↗
Our @DanaFarber own @sands_jacob changing Standard of Care in small cell lung cancer @myESMO #ESMO26 @OncoAlert https://t.co/qfUL9stJkr
[Slide 1] [Kaplan-Meier slide — raw curve OCR not published; values captured from legible slide text only] Tarlatamab plus durvalumab significantly improved overall survival versus durvalumab alone as first-line maintenance therapy (DeLLphi-305) Arm | N | Median OS | 6-mo OS | 12-mo OS Tarlatamab + durvalumab | 282 | 21.1 mo | 92% | 79% Durvalumab | 281 | 12.7 mo | 75% | 53% HR 0.42; P < 0.001 (2-sided) Presenter: Jacob Sands, MD
Hidehito HORINOUCHI (@HHorinouchi)
Hidehito HORINOUCHI @HHorinouchi
DeLLphi-305 · ESMO 2026 slides
Oct 24, 2026 · ESMO 2026
View on X ↗
🆙 Published @NEJM 🎊 🔥Presidential Symposium I: #LCSM 🔥DeLLphi-305: Tarlatamab + durvalumab vs durvalumab as 1L maintenance in ES-SCLC 🎙️ Dr. Maurice Pérol @sands_jacob 🎯Met Primary Endpoint: Significantly Improved OS 🎯mOS 21.1 vs 12.7m, HR 0.42 🎯mPFS 7.4 vs 1.9m, HR 0.34 🎯ORR 26.4% vs 4.1% 🎯CRS 49.6% (Mostly Low Grade), No Fatal Events ☑️NCT06211036 🔗 https://t.co/dVb8S7vWJk @OncoAlert @Larvol @myESMO @IASLC
[NEJM figure — raw curve OCR not published; values captured from legible figure text only] The New England Journal of Medicine — Original Article (Meeting of the European Society for Medical Oncology) Tarlatamab–Durvalumab in Small-Cell Lung Cancer — M. Pérol and Others Overall survival landmarks: 6 months 91.5% (tarlatamab–durvalumab) vs 74.6% (durvalumab); 12 months 79.4% vs 53.3% "In a prespecified interim analysis of a phase 3 trial involving patients with extensive-stage SCLC, the median overall survival was 21.1 months with tarlatamab–durvalumab maintenance therapy and 12.7 months with durvalumab alone."
Dr Amol Akhade (@SuyogCancer)
Dr Amol Akhade @SuyogCancer
DeLLphi-305 · ESMO 2026 slides
Oct 23, 2026 · ESMO 2026
View on X ↗
🚨 ESMO 2026 presidential | DeLLphi-305: Phase III (n=563): Tarlatamab + Durvalumab vs Durvalumab as 1L maintenance after chemo-IO. 📊 Key results: • Median OS: 21.1 vs 12.7 months (HR 0.42) 🔥 • 12-month OS: 79.4% vs 53.3% • Median PFS: 7.4 vs 1.9 months (HR 0.34) • ORR: 26.4% vs 4.1% ⚠️ Grade ≥3 AEs: 46.8% vs 40.6%; CRS 49.6% (mostly low grade). 💡 58% reduction in risk of death! Could this redefine first-line maintenance in ES-SCLC? Probably yes. Looking forward towards full data set . @OncoAlert @esmo #esmo26 #SCLC #DeLLphi305
[Slide 1] Proffered Paper session LBA3 - Tarlatamab plus durvalumab (durva) vs durva as 1L maintenance (1LM) therapy following durva, platinum, and etoposide (1L durva + EP) in extensive-stage small cell lung cancer (ES-SCLC): Primary analysis of the phase 3 DeLLphi-305 trial Speakers Jacob Sands (Boston, United States of America) Lecture Time 17:18 - 17:30 [Abstract button] Background Adding tarlatamab to 1L ES-SCLC therapy showed encouraging efficacy in the phase 1b DeLLphi-303 study (NCT05361395). We report the primary analysis of the randomized phase 3 DeLLphi-305 trial evaluating tarlatamab + durva vs durva as 1LM therapy for ES-SCLC. [Slide 2] Conclusions Tarlatamab + durva significantly improved OS, PFS, and ORR in 1LM ES-SCLC. The overall incidence of adverse events was comparable between groups. CRS and ICANS events were primarily low grade and no fatal events occurred. These results establish tarlatamab + durva as a new standard of care 1LM therapy for ES-SCLC. [Slide 3] low grade (Table). Table: LBA3 | Tarlatamab + durva (n = 282) | Durva (n = 281) OS mOS, mo (95% CI) | 21.1 (20.8, NE) | 12.7 (11.2, 14.8) HR (95% CI); P value | 0.42 (0.32, 0.54); P < 0.001 12 mo OS rate, % (95% CI) | 79.4 (74.2, 83.7) | 53.3 (47.3, 59.0) Median follow-up, mo | 15.9 | 16.1 PFS mPFS | 7.4 (5.6, 9.1) | 1.9 (1.9, 2.0) HR (95% CI); P value | 0.34 (0.28, 0.42); P < 0.001 ORR, % (95% CI) | 26.4 (20.9, 32.5) | 4.1 (2.0, 7.4) P value | P < 0.001 TEAEs, n (%) | (n = 282) | (n = 278) Any grade | 281 (99.6) | 258 (92.8) Gr ≥ 3 | 132 (46.8) | 113 (40.6) CRS^a, n (%) Any grade | 140 (49.6) | 4 (1.4) Gr ≥ 3 | 1 (0.4) | 0 ICANS^a, n (%) Any grade | 3 (1.1) | 0 Gr ≥ 3 | 0 | 0 ^aNo fatal events occurred. NE, not estimable; Gr, grade; TEAE, treatment-emergent adverse event. [Slide 4] Methods 563 patients (pts) with ES-SCLC without progression after 1L durva + EP were randomized (1:1) to receive either tarlatamab + durva (n = 282) or durva (n = 281) until progression or unacceptable toxicity. Tarlatamab was given 1 mg IV cycle 1 day 1 (C1D1); 10 mg IV C1D8, C1D15, then 10 mg IV Q2W; durva was given 1500 mg IV Q4W. The primary endpoint was overall survival (OS) with key secondary endpoint progression-free survival (PFS) per investigator assessment, each measured from time of randomization. Additional secondary endpoints were objective response rate (ORR) and safety. Results With median (m) follow-up time of 15.9 and 16.1 months (mo), respectively, tarlatamab + durva significantly improved OS (HR: 0.42; 95% CI 0.32, 0.54; P <0.001; mOS: 21.1 [95% CI, 20.8 to NE] vs 12.7 mo [95% CI, 11.2 to 14.8]). Tarlatamab + durva significantly improved PFS (HR: 0.34; 95% CI 0.28, 0.42; P < 0.001; mPFS: 7.4 vs 1.9 mo). ORR was 26.4% (95% CI 20.9%, 32.5%) for tarlatamab + durva and 4.1% (95% CI 2.0%, 7.4%) for durva (P < 0.001). Grade ≥ 3 TEAEs occurred in 46.8% (tarlatamab + durva) and 40.6% (durva) of pts. Cytokine release syndrome (CRS) and immune-effector cell-associated neurotoxicity syndrome (ICANS) occurred in 49.6% and 1.1% of tarlatamab + durva pts and were mostly low grade (Table). Table: LBA3
KOL-Made Infographics
Physician-authored summary graphics from ESMO 2026 · click to enlarge
@ChandrakanthMv · Oct 24, 2026 · ESMO 2026

More slides on this page

Topline-day captures (Sept 8, 2026): the study-design slide, the Amgen press release, and the Imdelltra Phase 3 program landscape. Full text via the OCR toggle on each card. Efficacy numbers were first presented at ESMO 2026 (LBA3, Oct 24, 2026) — see the ESMO 2026 slides above.

Toni Choueiri, MD @DrChoueiri · 2026-09-08
Study design + press-release headline
Topline-day design slide (planned n=275 per arm; 563 actually randomized, 282 vs 281) shared by Dr. Toni Choueiri; OCR = design slide
View Post
DeLLphi-305 — Study design + press-release headline (1)DeLLphi-305 — Study design + press-release headline (2)
DeLLphi-305: Durvalumab ± Tarlatamab 1L Maintenance - International, open-label, randomized phase III study - Adults with ES-SCLC who completed 3-4 cycles of platinum/etoposide with concurrent durvalumab as first-line tx without disease progression - no symptomatic CNS mets - ECOG PS 0-1 → Tarlatamab IV Q2W + Durvalumab IV Q4W (n = 275) → Durvalumab IV Q4W (n = 275) - Primary endpoint: Overall Survival - Secondary endpoints: PFS, ORR, DCR, DoR, TTP, safety, QoL
Aakash Desai @ADesaiMD · 2026-09-08
Amgen press release — full capture
Press release, Sept 8, 2026
View Post
DeLLphi-305 — Amgen press release — full capture
IMDELLTRA® IN COMBINATION WITH IMFINZI® DEMONSTRATED LANDMARK IMPROVEMENT IN OVERALL SURVIVAL IN FIRST-LINE EXTENSIVE STAGE SMALL CELL LUNG CANCER Phase 3 DeLLphi-305 Study Delivered Highly Significant and Clinically Meaningful Overall Survival Benefit Versus Durvalumab Alone Study Also Met Secondary Progression-Free Survival and Objective Response Rate Endpoints THOUSAND OAKS, Calif., Sept. 8, 2026 /PRNewswire/ -- Amgen (NASDAQ: AMGN) today announced landmark results from the Phase 3 DeLLphi-305 study, which met its primary endpoint at a pre-specified interim analysis, demonstrating a statistically significant and clinically meaningful improvement in overall survival with IMDELLTRA (tarlatamab-dlle) in combination with AstraZeneca's Imfinzi (durvalumab) compared to durvalumab alone. This study tested IMDELLTRA as a first-line maintenance treatment for people with extensive stage small cell lung cancer (ES-SCLC) whose disease had not progressed following initial treatment with durvalumab, platinum-based chemotherapy and etoposide. The study also demonstrated a statistically significant and clinically meaningful improvement in progression-free survival (PFS) and objective response rate (ORR) among patients treated with IMDELLTRA in combination with durvalumab. Overall, the safety profile of IMDELLTRA in combination with durvalumab was consistent with the known safety profiles of the individual medicines. No new or unexpected safety signals were identified in DeLLphi-305. The study design included monitoring in a healthcare setting for 1 to 2 hours (6 to 8 hours in certain regions including Europe) following IMDELLTRA infusion on Cycle 1 Day 1 and Cycle 1 Day 8. "IMDELLTRA has already revolutionized the standard of survival for patients with extensive stage small cell lung cancer whose disease progressed on or after prior treatment. These landmark results from DeLLphi-305 suggest IMDELLTRA will further revolutionize the standard for survival earlier in the treatment journey and meaningfully shift the treatment paradigm for people facing this devastating disease," said Jay Bradner, M.D., executive vice president, Research and Development, Artificial Intelligence and Data at Amgen. "Despite clinical advances, extensive stage small cell lung cancer remains one of the most aggressive and difficult-to-treat cancers, and substantial improvements in survival are rare, underscoring the importance of these findings." This marks the first Phase 3 study including a Bispecific T-cell Engager (BiTE) therapy to demonstrate an overall survival benefit in the first-line maintenance setting for ES-SCLC.
Madeleine Armstrong @ByMadeleineA · 2026-09-08
Phase 3 trials of Imdelltra — program landscape
OncologyPipeline table shared by Madeleine Armstrong
View Post
DeLLphi-305 — Phase 3 trials of Imdelltra — program landscape
Phase 3 trials of Imdelltra Trial | Setting | Regimen | Primary endpoint(s) | Note Dellphi-304 | 2nd-line ES-SCLC | IV Imdelltra, vs chemo | OS | Supported full approval Nov 2025 Dellphi-305 | 1st-line ES-SCLC (maintenance) | IV Imdelltra + Imfinzi, vs Imfinzi | OS | Completes Jul 2027 (annotated "Win") Dellphi-306 | 1st-line LS-SCLC (maintenance) | IV Imdelltra, vs placebo | PFS & OS (originally PFS only) | Completes Apr 2030 (originally Oct 2026; Imfinzi was approved in this setting in Dec 2024) Dellphi-312 | 1st-line ES-SCLC | IV Imdelltra + Imfinzi + chemo (induction) then Imdelltra + Imfinzi (maintenance), vs Imfinzi + chemo (induction) then Imfinzi (maintenance) | PFS & OS (originally OS only) | Completes Jan 2029 Dellphi-315 | 2nd-line ES-SCLC | SC vs IV Imdelltra | AUC & Ctrough | Estimated start date 31 Aug 2026; completes Sep 2027 Notes: ES=extensive stage; LS=limited stage. Source: OncologyPipeline.

DeLLphi-305 Trial Design

Extensive-stage small cell lung cancer almost always relapses after first-line platinum–etoposide plus a PD-L1 inhibitor, and frontline survival gains have been rare. DeLLphi-305 tests whether introducing tarlatamab — a DLL3-targeted Bispecific T-cell Engager (BiTE) — during the maintenance phase, in combination with continued durvalumab, extends survival before relapse occurs.

The program builds on DeLLphi-301 (accelerated approval, May 2024), the confirmatory DeLLphi-304 (full FDA approval in 2L+, Nov 2025), and the Phase 1b DeLLphi-303, which reported median OS of 25.3 months for tarlatamab plus anti–PD-L1 maintenance at WCLC 2025 — Phase 1b data reported separately from this Phase 3 readout. Physicians on this page framed the readout as a landmark for a disease where, as trial lead Jacob Sands' colleagues note, substantial survival improvements are rare.

Study Design

Global (international), randomized (1:1), open-label Phase 3; 563 patients randomized (282 tarlatamab + durvalumab, 281 durvalumab; ESMO 2026 LBA3). Stratified by brain and/or liver metastases, response to 1L chemo-IO, and prior platinum type.

Population

Adults with ES-SCLC who completed 3–4 cycles of platinum/etoposide with concurrent durvalumab as first-line treatment without disease progression; no symptomatic CNS metastases; ECOG PS 0–1.

Interventions

Tarlatamab 1 mg IV on Cycle 1 Day 1, 10 mg on Days 8 and 15, then 10 mg every 2 weeks + durvalumab 1500 mg IV every 4 weeks vs durvalumab 1500 mg IV every 4 weeks, until progression or unacceptable toxicity (LBA3 abstract).

Endpoints

Primary: overall survival. Key secondary: PFS (investigator-assessed). Secondary: ORR, DoR, safety. Hierarchical testing OS → PFS → ORR; OS interim at 243 events (61% information fraction), two-sided boundary 0.008 (LBA3 design slide). ClinicalTrials.gov also lists DCR, TTP and quality of life.

Mechanism

Tarlatamab directs cytotoxic T cells to DLL3-expressing SCLC cells (BiTE platform); durvalumab maintains PD-L1 checkpoint blockade from induction.

Sponsors

Amgen (tarlatamab); durvalumab supplied as AstraZeneca’s Imfinzi.

Design sources: Amgen PR · OncoDaily (563 randomized) · ClinicalTrials.gov

DeLLphi-305 in the News

Earlier: WCLC 2026 and topline reactions (Sept 2026)

WCLC 2026: Live KOL Reaction

Physician posts from the September 8, 2026 topline announcement and the IASLC 2026 World Conference on Lung Cancer (Seoul, September 12–15), including the posts previously listed as this page’s Top Tweets. Quotes are verbatim, newest first; each card links to the original post.

Laura Alder, MD@LauraAlderMD
𝕏

📣 Changes and progress for tarlatamab in SCLC! ✅ FDA has approved REDUCED monitoring time for the first two doses: 22–24h on C1D1 and C1D8 ➡️ 6–8h. Easing this lowers a key barrier to outpatient and community administration. 🔜 Coming soon: positive overall survival results from the phase III maintenance DeLLphi-305 trial ➡️ soon moving into 1L. 📄 To help teams operationalize all of this, our recent multi-institutional perspective on tarlatamab administration and management of CRS/ICANS provides practical, real-world guidance for safe delivery. 👀 Stay tuned for outpatient-focused delivery and risk management strategies. https://t.co/zXL70ok6Gj @BZhangMD @ADesaiMD @alissajcooper @MehmetAltanMD @Annechiangmd @LaurenByersMD @Sonampuri

1.3K views 20 likes6 RT 2026-09-21
Manuel Dómine, MD, PhD
Manuel Dómine, MD, PhD@ManuelDomine

MERLIN, Tarlatamab treatment for limited small cell lung cancer in patients in maintenance; a phase II clinical trial in progress. WORLD CONFERENCE ON LUNG CANCER 2026 SEOUL @gecp_org @Hospital_FJD @quironsalud @UAM_Madrid #IIS-FJD @OncoAlert @AEACaP #LCSM #WCLC26 @SCLC https://t.co/lzb9Zxatfl

256 impressions4 likes2026-09-14
Misty Dawn Shields
Misty Dawn Shields@drshieldsmd

Thank you Dr. Anne Chiang @Annechiangmd @YaleCancer here at @IASLC #WCLC26 for highlighting our recent biomarker research on durable responders of lurbinectedin that identified ISL1 dependency as a novel neuroendocrine subtype in SCLC that predicts response, published in @MCT_AACR. Given the following growing evidence: 1) the press release with positive OS outcomes with DeLLphi-305 in the 1LM 2) negative confirmatory study with LAGOON (although multiple study design concerns existed, including pts with hx of tx brain mets) 3) sponsor withdrawal of lurbinectedin in the relapsed/refractory setting of ES-SCLC 4) risk for relapsed SCLC treatment gap while awaiting ADC approvals that are limited by ILD, myelosuppression, GI toxicity and acquired resistance development. … the prospective need to apply proposed biomarkers like ISL1 is important to understand who ultimately will benefit from lurbinectedin in their treatment of SCLC. @SclcSMASHERS @LUNGevity @lungoncdoc @weldeiry @OTtheScientist @PareshKumaaar @ktgminton @IUCancerCenter @MoffittNews @OncLive @OncoAlert @oncodaily @LungCancerRx @triparnasen @AparGanti @StephenVLiu

462 impressions9 likes2026-09-13
Dra. María Natalia Gandur Quiroga
Dra. María Natalia Gandur Quiroga@nataliagandur

🚨 Too much oncology news. Too little time. That’s where the @OncoAlert Newsletter really delivers value: filtering the noise and surfacing the data most worth knowing each week. This edition brings together: 🔴 LUNG: DeLLphi-305 with tarlatamab + durvalumab in ES-SCLC, plus new data on lazertinib resistance/ctDNA clearance and osimertinib in uncommon EGFR mutations 🟠 GI: early Phase 1 data with L-glutamine + gemcitabine/nab-paclitaxel in advanced pancreatic cancer 🔵 GU: perioperative strategies in high-risk #ProstateCancer and fracture risk with abiraterone 🟣 BREAST: pCR with neoadjuvant THP in HER2+ disease and biomarkers in stage I TNBC 🌍 And this week also features AcuVox — helping colleagues track the trials, treatments, and topics generating the most attention at major cancer congresses. What I value most is the format: high-yield, clinically relevant, and easy to scan in minutes. 👉 REGISTER TO GET IT: https://t.co/NFi1ia6FQt Stay informed. Focus on what matters. @matteolambe @aftimosp @E_de_Azambuja @DrSGraff @ErikaHamilton9 @double_whammied @maryam_lustberg @raalbany @hoperugo @stolaney1 @LoiSher @JaniceTNBCmets @montypal @DrDanielHeng @apolo_andrea @DrChoueiri @PGrivasMDPhD @TiansterZhang @neerajaiims @amerseburger @sonpavde @drenriquegrande @tompowles1 @cdanicas @nataliagandur @realbowtiedoc @Onco_Cifu88 @scocmem @FernandoOnco @ElisaAgostinett @to_be_elizabeth @Erman_Akkus @MarioBalsaMD @DrMirallas @GIMedOnc @UOzkerim @DrRishabhOnco @PaulJiL @DaisukeKotani @DraMartinezLago @p_ciracimd @BenWestphalen @CentralParkWMD @graokane @amandaNizamMD @DrVilmaPBarcia #OncoAlert #Oncology #CancerResearch #LungCancer #BreastCancer #ProstateCancer #PancreaticCancer

1.4K impressions8 likes2026-09-10
Oncology Tube
Oncology Tube@oncologytube

DeLLphi-305 met its overall-survival endpoint in 1L ES-SCLC maintenance. Full read: https://t.co/wbcDvWKbYi https://t.co/5l6H3fhneX

1.1K impressions8 likes2026-09-10
The Pharma Letter
The Pharma Letter@ThePharmaLetter

Phase III DeLLphi-305 met its primary endpoint at interim analysis: @Amgen's Imdelltra (tarlatamab-dlle) with @AstraZeneca's Imfinzi (durvalumab) significantly improved overall survival versus durvalumab alone. https://t.co/YD4eIALIKr #Oncology #ClinicalTrials

400 impressions3 likes2026-09-10
FJ ⭐️⭐️+⭐️
FJ ⭐️⭐️+⭐️@pistoto2017

@care_natureme @OncLive @drshieldsmd @IUCancerCenter Considering the potential introduction of #tarlatamab in the 1lm, what would be the optimal treatment regimen—particularly regarding the best use of all available therapeutic options (which are limited)? 1. #Imforte in 1lm + Tarla in 2l 2. #DeLLphi-305 in 1lm + Topotecan in 2l

393 impressions0 likes2026-09-10
EuropePharmaToday
EuropePharmaToday@eu_pharmatoday

Amgen 8 Sep: DeLLphi-305 topline — tarlatamab + durvalumab beat durvalumab on OS as 1L ES-SCLC maintenance. No numbers. Not a CHMP opinion. EU Imdylltra stays later-line monotherapy.

13 impressions0 likes2026-09-10
MV Chandrakanth
MV Chandrakanth@ChandrakanthMv

TWO IOs. TWO MAINTENANCE STRATEGIES. ES-SCLC maintenance is evolving. IMforte: Atezolizumab → add lurbinectedin DeLLphi-305: Durvalumab → add tarlatamab Different IO backbones. Different maintenance partners. Different biology. But one emerging strategy: don’t wait for relapse — intensify while the disease is still controlled. Is maintenance becoming the new battleground in ES-SCLC? Cross-trial comparison is conceptual; these strategies were not directly compared. #MVOnco #SCLC #ES_SCLC #IMforte #DeLLphi305 #Lurbinectedin #Tarlatamab #LungCancer #ThoracicOncology

3.5K impressions53 likes2026-09-09
Dr Rishabh Jain
Dr Rishabh Jain@DrRishabhOnco

🚨 DeLLphi-305: Tarlatamab enters 1L maintenance in ES-SCLC Who was treated? Patients with extensive-stage SCLC who had not progressed after platinum + etoposide + durvalumab. Phase 3 design 563 patients randomized 1:1: Tarlatamab + durvalumab vs Durvalumab alone Primary endpoint: OS Key secondary endpoints: PFS, ORR What was announced? ✅ Statistically significant and clinically meaningful OS benefit ✅ Significant improvement in PFS ✅ Significant improvement in ORR ✅ No new unexpected safety signals reported Why it matters This is the first Phase 3 study of a BiTE therapy to demonstrate an OS benefit in first-line maintenance ES-SCLC. That is a major milestone in a disease where many patients relapse early and never reach second-line therapy. But we still need the numbers • OS hazard ratio • Median OS • Median PFS • Detailed CRS/ICANS rates • Discontinuation and treatment-related mortality data Clinical verdict 🔥 Potentially practice-changing. If the magnitude of OS benefit is substantial and toxicity remains manageable, tarlatamab + durvalumab could become a new first-line maintenance standard in ES-SCLC. #SCLC #LungCancer #Oncology @ASCO @oncoalert

2.7K impressions37 likes2026-09-09
MedChemExpress
MedChemExpress@MedChemExpress

🚨Oncology Breakthrough | Can a new combination change the first-line treatment landscape for extensive-stage small cell lung cancer? Phase 3 DeLLphi-305 showed that #tarlatamab-dlle (#IMDELLTRA, Amgen) + #durvalumab (#IMFINZI, AstraZeneca) significantly improved overall survival versus durvalumab alone in the first-line maintenance setting. The combination also improved progression-free survival (PFS) and objective response rate (ORR), marking the first Phase 3 study of a BiTE® therapy to demonstrate an overall survival benefit in this setting. 📰Read more: https://t.co/reOrh9YJJi #SCLC #SmallCellLungCancer #LungCancer #Oncology #CancerResearch #Immunotherapy

319 impressions8 likes2026-09-09
Mason Berger
Mason Berger@biotech_leads

1/5 Amgen says tarlatamab plus durvalumab improved overall survival versus durvalumab alone in first-line extensive stage small cell lung cancer. Phase 3, DeLLphi-305. If it holds up at full presentation, it is the first T-cell engager to win on OS in frontline lung.

46 impressions0 likes2026-09-09
MV Chandrakanth
MV Chandrakanth@ChandrakanthMv

A NEW MAINTENANCE ERA IN ES-SCLC? DeLLphi-305 brings tarlatamab earlier in the treatment journey. After platinum–etoposide + durvalumab induction, patients without progression were randomized to durvalumab alone vs tarlatamab + durvalumab maintenance. The topline result: OS improved — with PFS and ORR improving too. The key shift? Don’t wait for relapse. Target residual disease during 1L maintenance. Full numerical data awaited. #MVOnco #DeLLphi305 #Tarlatamab #SCLC #LungCancer #ThoracicOncology #MedicalOncology

1.1K impressions6 likes2026-09-09
Dr. Estela Rodriguez
Dr. Estela Rodriguez@Latinamd

📣 Big news in Small Cell Lung Cancer! #DeLLphi305, a Phase 3 study of #tarlatamab maintenance with chemo-IO + durvalumab in #SCLC 🫁, met its primary endpoint. Bringing tarlatamab to the frontline could improve survival in a disease long marked by therapeutic nihilism. ❓🙋🏽‍♀️how to improve access and ease of administration ( check out #WCLC26 abstract ) ❓how to improve patient selection and minimize toxicity

1.9K impressions16 likes2026-09-08
Masahiro TORASAWA, MD. PhD.
Masahiro TORASAWA, MD. PhD.@M_Torasawa

🚨 DeLLphi-305 is positive! Tarlatamab + durvalumab as 1L maintenance in ES-SCLC significantly improved: 🫁 OS (primary endpoint) 📈 PFS 🎯 ORR vs durvalumab alone, with no new safety signals. 🔥 First Phase 3 BiTE study to show an OS benefit in 1L maintenance ES-SCLC. 🔗 https://t.co/y9NRAeMirT

10.5K impressions70 likes2026-09-08
Hidehito HORINOUCHI
Hidehito HORINOUCHI@HHorinouchi

🔥DeLLphi-305: "Statistically significant and highly clinically meaningful improvement in overall survival (OS)" 🆙 @Amgen @AstraZeneca 👥Patients: Extensive-stage small cell lung cancer (ES-SCLC), no progression after 1st-line induction with durvalumab + platinum chemotherapy + etoposide 3⃣Phase III ⚖️Tarlatamab + durvalumab ⚖️Durvalumab alone 🔢NCT06211036 #LCSM @OncoAlert @Larvol 🔗 https://t.co/4tFnvnm3UA 🔗 https://t.co/rhf7IGZ1lN

6.0K impressions50 likes2026-09-08
Stephen V Liu, MD
Stephen V Liu, MD@StephenVLiu

Very excited to see the full dataset - addition of tarlatamab as first-line maintenance therapy to ES-SCLC in DeLLphi-305 improves PFS and OS. Focus now has to be on implementation, patient selection, and removing barriers. https://t.co/l02noCZ3G5

3.3K impressions51 likes2026-09-08
ilyas sahin, MD
ilyas sahin, MD@ilyassahinMD

Potentially practice-changing phase III news in extensive-stage small cell lung cancer. * In DeLLphi-305, adding the DLL3xCD3 T-cell engager tarlatamab to durvalumab maintenance after platinum/etoposide + durvalumab significantly improved overall survival and progression-free survival versus durvalumab alone. Interesting to see T-cell engagers moving earlier in treatment, rather than being reserved for relapse. For now, these are topline results from a company announcement, so the actual hazard ratios, survival curves, and detailed safety data will matter. Looking forward to seeing the full results.

2.3K impressions45 likes2026-09-08
Noemi Reguart
Noemi Reguart@NReguart

A great day for our patients and the entire #SCLC community! 👏👏👏 Thrilled to see the positive results from DeLLphi-305. A landmark achievement in #SCLC! 🎉 https://t.co/DVDlycnuQC

2.2K impressions26 likes2026-09-08
gilberto lopes
gilberto lopes@GlopesMd

Visual summary of today’s phase 3 DeLLphi-305 update in ES-SCLC: tarlatamab + durvalumab maintenance improved OS vs durvalumab alone after induction durvalumab + platinum/etoposide. PFS and ORR also positive. Full data still needed. #SCLC #LCSM https://t.co/pyeQbPyoRc

1.6K impressions22 likes2026-09-08
Gil Morgan, MD
Gil Morgan, MD@weoncologists

JUST OUT 🚨 DeLLphi-305 Update in #SCLC 🫁 To Be Presented Soon! Ping @COR2EDMedEd @gotoPER @mirrorsmed @VJOncology @high5md https://t.co/er7POxdu3m

1.1K impressions10 likes2026-09-08
Giannis Mountzios
Giannis Mountzios@g_mountzios

🌟Time to move T-cell engagers to 1st-L maintenance ? A new era is dawning for our patients with #SCLC The much-awaited press-release from DeLLphi-305 confirms that analysis has demonstrated a statistically significant and clinically meaningful improvement in overall survival with tarlatamab in combination with durvalumab compared to durvalumab alone. Full data coming soon! https://t.co/IQnZmYfSuh @SclcSMASHERS @myESMO @IASLC @ASCO @LungCancerEu @OncoAlert @OncBrothers @YoungLungCancer @lcrf_org @PeerView @oncodaily

1.1K impressions19 likes2026-09-08
Targeted Oncology
Targeted Oncology@TargetedOnc

🔬 DeLLphi-305 data show tarlatamab plus durvalumab significantly improved overall survival as first-line maintenance in extensive stage small cell #LungCancer. Read more: https://t.co/UEmrS0Tcti #SCLC #Oncology #ThoracicOncology #ClinicalTrials #CancerTreatment

847 impressions9 likes2026-09-08
Dipesh Uprety MD FACP
Dipesh Uprety MD FACP@DipeshUpretyMD

DeLLphi-305 — A Phase III study comparing tarlatamab + durvalumab versus durvalumab alone after chemo-IO in ES-SCLC. Per the press release, the study delivered a highly significant and clinically meaningful overall survival benefit with tarlatamab + durvalumab versus durvalumab. A big win and a major milestone for the field of lung cancer #LCSM @OncoAlert https://t.co/wXZq6IxKoS

410 impressions4 likes2026-09-08
BiotechReality
BiotechReality@biotechreality

Clinical Intelligence | Amgen: IMDELLTRA Imfinzi Combination Delivers Landmark Survival Gain in DeLLphi-305 Trial Full data analysis on BiotechReality: https://t.co/zOsmnF0RCl #Amgen #AstraZeneca #IMDELLTRA #Tarlatamab #Imfinzi #Durvalumab #DeLLphi305 #Phase3Trial #SCLC

59 impressions0 likes2026-09-08
Morning Glory Sciences
Morning Glory Sciences@MorningGlorySci

First OS win for a T-cell engager in first-line ES-SCLC maintenance: phase 3 DeLLphi-305, 563 randomized, primary endpoint met at a prespecified interim analysis. No median, no hazard ratio, no event count, no data cutoff. #LungCancer #ClinicalTrials https://t.co/pWKgfWSQM4

42 impressions0 likes2026-09-08
Wajahat Afaq
Wajahat Afaq@TheWajSpeaks

In late-stage trial results, AstraZeneca’s block-buster cancer drug Imfinzi, combined with Amgen’s targeted immunotherapy Imdelltra, demonstrated a landmark, statistically significant improvement in overall survival for patients with first-line extensive-stage small cell lung cancer. The Phase III DeLLphi-305 study tested this combo therapy as a maintenance treatment following standard chemotherapy. Results showed that the dual-action regimen significantly prolonged patient lives while boosting progression-free survival compared to Imfinzi alone. Crucially, no new safety concerns emerged. Given the historically low survival rates associated with aggressive lung cancers, this break-through marks a pivotal clinical milestone that provides fresh hope to millions worldwide.

21 impressions0 likes2026-09-08
Masahiro TORASAWA, MD. PhD.
Masahiro TORASAWA, MD. PhD.@M_Torasawa

A striking timeline in ES-SCLC: 💉 Early 1980s: Platinum–etoposide ⏳ ~4 decades... ✨ 2018–2019: IMpower133 / CASPIAN ⌛️ only ~7–8 years 🔥 2026: DeLLphi-305 — tarlatamab + durvalumab maintenance The pace of progress in SCLC is accelerating!🚀 https://t.co/o8zZAoh6Oc

5.0K impressions34 likes2026-09-08
gilberto lopes
gilberto lopes@GlopesMd

1/3 Big news in #SCLC today. Phase III DeLLphi-305: tarlatamab + durvalumab maintenance improved OS vs durvalumab alone after first-line platinum/etoposide + durvalumab in ES-SCLC. PFS and ORR also positive. Very encouraging—full data will matter.

1.4K impressions15 likes2026-09-08
Aakash Desai@ADesaiMD
𝕏

🚨Hot off the press! In #SCLC, tarlatamab plus durvalumab in 1L ES-SCLC shows OS improvement! Looking forward to the full data! @LungCancerRx https://t.co/H4sBvgIkm0

1.3K views 0 likes0 RT 2026-09-08
Rami Manochakian MD, FASCO@RManochakian
𝕏

🚨🔥‼️@OncoAlert Hot off the press. #BigNews #PressRelease by @Amgen ⭐️ #DeLLphi305 phase 3 trial of: ❇️1st line maintenance #Tarlatamab + #Durvalumab) vs #Durvalumab alone in patients with #ExtensiveStage #SmallCell #LungCancer after initial induction Tx with Chemo + Durvalumab. Showed: ✅Statistically Significant & Clinically meaningful ⬆️#OverallSurvival (#OS) Benefit. 👇🏻 https://t.co/qOh6UPlvaU

1.2K views 0 likes0 RT 2026-09-08
Madeleine Armstrong@ByMadeleineA
𝕏

Dellphi-305 trial of Imfinzi + Imdelltra in 1L ES-SCLC maintenance toplined positive. What are the odds this'll be at ESMO? $AZN $AMGN https://t.co/6YObwpSGZ3 https://t.co/rWA8SmpDJw

1.2K views 0 likes0 RT 2026-09-08
Dr Amol Akhade@SuyogCancer
𝕏

🚨 Landmark development in ES-SCLC! Phase 3 DeLLphi-305 has shown a statistically significant and clinically meaningful OS benefit with tarlatamab (IMDELLTRA) + durvalumab versus durvalumab alone as 1L maintenance after platinum–etoposide + durvalumab. PFS and ORR also improved. A potentially important new chapter in ES-SCLC maintenance therapy. Looking forward to full data @StephenVLiu @TejasPatilMD @LauraAlderMD @IASLC

436 views 0 likes0 RT 2026-09-08
Yakup Ergün@dr_yakupergun
𝕏

The kind of news we’ve been waiting for in ES-SCLC: an OS benefit ✅️ First-line maintenance tarlatamab + durvalumab 🔥 https://t.co/yDa6acdBeT

319 views 0 likes0 RT 2026-09-08
Balazs Halmos@BalazsHalmosMD
𝕏

Just one word - starlatamab! A star was born last year at #ASCO25 and looks like now found a steady partner in durvalumab! https://t.co/7YSywJwf60 https://t.co/DAHOJUitwq

300 views 0 likes0 RT 2026-09-08
Toni Choueiri, MD@DrChoueiri
𝕏

JUST IN: DeLLphi-305 study met its primary endpoint of overall survival combining tarlatamab (DLL3 BiTE) with PDL1 inhibitor Durvalumab as maintenance after 1L chemotherapy for extensive-stage small cell lung cancer ! Also RR/PFS significant Trial led by @DanaFarber @sands_jacob ! Via @PRNews https://t.co/mbVxkzeAmz

177 views 0 likes0 RT 2026-09-08
Uğur Özkerim@UOzkerim
𝕏

📢Very exciting news for ES-SCLC! 🔥 DeLLphi-305 meets its primary OS endpoint with tarlatamab + durvalumab as first-line maintenance, with significant improvements also reported in PFS and ORR. Looking forward to seeing the full results! 👀 @OncoAlert @ManuelDomine @GlopesMd @weoncologists @MedwatchHQ @OpenMedKate

123 views 0 likes0 RT 2026-09-08
Dr. Antonio Calles 🫁🚭@Tony_Calles
𝕏

Just received this. The golden era in SCLC! The DeLLphi-305 (Phase 3 Study in First-Line ES-SCLC Following Platinum, Etoposide and Durvalumab) OS Interim Analysis has been conducted. The analysis has demonstrated a statistically significant and clinically meaningful improvement in overall survival with IMDELLTRA® (tarlatamab-dlle) in combination with AstraZeneca's Imfinzi® (durvalumab) compared to durvalumab alone. https://t.co/DXLmkDT5Yz

100 views 0 likes0 RT 2026-09-08

DeLLphi-305 FAQ

What is the DeLLphi-305 trial?

DeLLphi-305 (NCT06211036) is a global, randomized, open-label Phase 3 trial of tarlatamab (IMDELLTRA, Amgen) plus durvalumab (Imfinzi, AstraZeneca) versus durvalumab alone as first-line maintenance for extensive-stage small cell lung cancer; 563 patients were randomized. The primary endpoint is overall survival. Full design: Trial Design.

What were the DeLLphi-305 results?

At the prespecified interim analysis presented at ESMO 2026 (LBA3) and published in NEJM, tarlatamab plus durvalumab improved overall survival versus durvalumab alone (HR 0.42), with PFS and ORR also improved. All figures, with sources and the data cut-off, are in At a Glance.

Is tarlatamab plus durvalumab FDA approved for first-line ES-SCLC?

No. The first-line maintenance combination is investigational. Tarlatamab (IMDELLTRA) holds full FDA approval (November 19, 2025) for ES-SCLC that progressed on or after platinum-based chemotherapy, based on DeLLphi-304. See At a Glance.

How is tarlatamab given in DeLLphi-305, and what about safety?

Tarlatamab is given IV every two weeks after step-up doses, with durvalumab IV every four weeks (schedule in Trial Design). Cytokine release syndrome was the main added toxicity, mostly low grade, with no fatal CRS or ICANS events; rates and monitoring requirements are in At a Glance.

Why does DeLLphi-305 matter for small cell lung cancer?

ES-SCLC almost always relapses after first-line chemo-immunotherapy. DeLLphi-305 is the first Phase 3 trial to show that adding a DLL3-targeted bispecific T-cell engager during maintenance extends overall survival before relapse; physicians on this page called it a landmark for 1L maintenance therapy. See At a Glance.

Key KOL Sentiments — DeLLphi-305

KOLComment (verbatim)Sentiment
Aakash Desai 🚨Hot off the press! In #SCLC, tarlatamab plus durvalumab in 1L ES-SCLC shows OS improvement! Looking forward to the full data! @LungCancerRx https://t.co/H4sBvgIkm0 Positive
Dr Amol Akhade 🚨 Landmark development in ES-SCLC! Phase 3 DeLLphi-305 has shown a statistically significant and clinically meaningful OS benefit with tarlatamab (IMDELLTRA) + durvalumab versus durvalumab alone as 1L maintenance after platinum–etoposide + durvalumab. PFS and ORR also improved. A potentially important new chapter in ES-SCLC maintenance therapy. Looking forward to full data @StephenVLiu @TejasPatilMD @LauraAlderMD @IASLC Positive
Yakup Ergün The kind of news we’ve been waiting for in ES-SCLC: an OS benefit ✅️ First-line maintenance tarlatamab + durvalumab 🔥 https://t.co/yDa6acdBeT Positive
Balazs Halmos Just one word - starlatamab! A star was born last year at #ASCO25 and looks like now found a steady partner in durvalumab! https://t.co/7YSywJwf60 https://t.co/DAHOJUitwq Positive
Uğur Özkerim 📢Very exciting news for ES-SCLC! 🔥 DeLLphi-305 meets its primary OS endpoint with tarlatamab + durvalumab as first-line maintenance, with significant improvements also reported in PFS and ORR. Looking forward to seeing the full results! 👀 @OncoAlert @ManuelDomine @GlopesMd @weoncologists @MedwatchHQ @OpenMedKate Positive
Dr. Antonio Calles 🫁🚭 Just received this. The golden era in SCLC! The DeLLphi-305 (Phase 3 Study in First-Line ES-SCLC Following Platinum, Etoposide and Durvalumab) OS Interim Analysis has been conducted. The analysis has demonstrated a statistically significant and clinically meaningful improvement in overall survival with IMDELLTRA® (tarlatamab-dlle) in combination with AstraZeneca's Imfinzi® (durvalumab) compared to durvalumab alone. https://t.co/DXLmkDT5Yz Positive
Rami Manochakian MD, FASCO 🚨🔥‼️@OncoAlert Hot off the press. #BigNews #PressRelease by @Amgen ⭐️ #DeLLphi305 phase 3 trial of: ❇️1st line maintenance #Tarlatamab + #Durvalumab) vs #Durvalumab alone in patients with #ExtensiveStage #SmallCell #LungCancer after initial induction Tx with Chemo + Durvalumab. Showed: ✅Statistically Significant & Clinically meaningful ⬆️#OverallSurvival (#OS) Benefit. 👇🏻 https://t.co/qOh6UPlvaU Neutral
Toni Choueiri, MD JUST IN: DeLLphi-305 study met its primary endpoint of overall survival combining tarlatamab (DLL3 BiTE) with PDL1 inhibitor Durvalumab as maintenance after 1L chemotherapy for extensive-stage small cell lung cancer ! Also RR/PFS significant Trial led by @DanaFarber @sands_jacob ! Via @PRNews https://t.co/mbVxkzeAmz Neutral
Dr Amol Akhade 🚨 ESMO 2026 presidential | DeLLphi-305: Phase III (n=563): Tarlatamab + Durvalumab vs Durvalumab as 1L maintenance after chemo-IO. 📊 Key results: • Median OS: 21.1 vs 12.7 months (HR 0.42) 🔥 • 12-month OS: 79.4% vs 53.3% • Median PFS: 7.4 vs 1.9 months (HR 0.34) • ORR: 26.4% vs 4.1% ⚠️ Grade ≥3 AEs: 46.8% vs 40.6%; CRS 49.6% (mostly low grade). 💡 58% reduction in risk of death! Could this redefine first-line maintenance in ES-SCLC? Probably yes. Looking forward towards full data set . @OncoAlert @esmo #esmo26 #SCLC #DeLLphi305 Positive
Yakup Ergün #ESMO26 | DeLLphi-305 – Phase III | Presidential Symposium-1 In ES-SCLC, tarlatamab + durvalumab maintenance significantly improved outcomes vs durvalumab alone following first-line chemotherapy + durvalumab: OS: 21.1 vs 12.7 months (HR 0.42) PFS: 7.4 vs 1.9 months (HR 0.34) CRS: 49.6%; grade ≥3: 0.4%. An impressive OS benefit! Atezolizumab + lurbinectedin maintenance also demonstrated an OS benefit in IMforte (HR 0.73). Although cross-trial comparisons are inappropriate, the magnitude of the OS benefit with tarlatamab appears numerically much greater. Positive
Patrick Forde DeLLphi-305 - tarlatamab added to durvalumab after initial chemo-immunotherapy for small lung cancer essentially doubles survival. Hope for all cancers here, if the right target & treatment modality can be refined. Unquestionably a new standard for this disease. #ESMO2026 https://t.co/8ovQ2yB6fr Positive
Aakash Desai #ESMO26 DeLLphi-305: tarlatamab+durva vs durva, 1L maintenance ES-SCLC ➡️ OS 21.1 vs 12.7 mo, HR 0.42 ➡️ PFS 7.4 vs 1.9 mo, HR 0.34 ➡️ CRS 49.6% (G3+ 0.4%) Amazing to be part of this practice-changing study on the global steering committee!! @LungCancerRx @OncoAlert @oncodaily https://t.co/BfjokrDpim Positive
Hidehito HORINOUCHI 🆙#ESMO26 Presidential Symposium I: #LCSM 🔥DeLLphi-305: Tarlatamab Plus Durvalumab (Durva) vs Durva as 1L Maintenance (1LM) Therapy Following Durva, Platinum, and Etoposide in Extensive-Stage Small Cell Lung Cancer (ES-SCLC): Primary Analysis of the Phase 3 Trial 🎙️ @sands_jacob 🔢LBA3 🎯Met Primary Endpoint: Significantly Improved OS 🎯mOS 21.1 vs 12.7m, HR 0.42 🎯mPFS 7.4 vs 1.9m, HR 0.34 🎯ORR 26.4% vs 4.1% 🎯CRS 49.6% (Mostly Low Grade), No Fatal Events ☑️NCT06211036 🔗 https://t.co/Lb6tzuMm0z @OncoAlert @Larvol @myESMO @IASLC Positive
Yakup Ergün I’d applaud these trials, but I’d remain seated 😅😅 INTerpath-001 is an innovative treatment approach. However, there is no comparison with neoadjuvant nivo + ipi, a strong option particularly in macroscopic stage III melanoma. DeLLphi-305 showed a survival benefit with maintenance tarlatamab + durvalumab. But the comparator is durvalumab monotherapy. We also have positive results from IMforte with maintenance atezo + lurbinectedin. So this is another potential maintenance option; its place among the existing options remains to be defined. In HARMONi-GI1, even if not one but three trucks could fit between the Kaplan–Meier curves, global validation will still be expected because the trial was conducted exclusively in China 🫣 For me, VOLGA’s most interesting feature is the omission of adjuvant EV. As for the survival benefit of perioperative EV + immunotherapy, we already have strong data. Neutral
MV Chandrakanth DeLLphi-305 | Can We Delay Relapse in ES-SCLC? A potential shift: Tarlatamab in first-line maintenance, before relapse. 🔹 563 patients randomized 1:1 after platinum–etoposide + durvalumab. 🔹 Maintenance: Tarlatamab + durvalumab vs durvalumab alone. 🔹 Mechanism: DLL3 × CD3 T-cell engagement + PD-L1 blockade. 🔹 Topline: Sponsor reports improved OS, PFS and response. 🔹 ESMO 2026: Awaiting detailed efficacy, CRS, neurological toxicity and QoL data. 🎯 Take-home: Could earlier tarlatamab redefine ES-SCLC maintenance? Promising, but full results are needed. 📚 Reference: DeLLphi-305, Phase III (NCT06211036). #DeLLphi305 #Tarlatamab #SCLC #ESMO2026 #LungCancer #MVOnco Positive
Toni Choueiri, MD JUST IN: DeLLphi-305: Small Cell Lung Cancer Extensive-Stage Phase III (n=563): Tarlatamab + Durvalumab vs Durvalumab as 1L maintenance after chemo-IO, to be presented by our own @sands_jacob from @DanaFarber • Median OS: 21.1 vs 12.7 months (HR 0.42) • Median PFS: 7.4 vs 1.9 months (HR 0.34) • ORR: 26.4% vs 4.1% Grade ≥3 AEs: 46.8% vs 40.6%; CRS 49.6% (most low grade). Probably new standard of care in ES-SCLC. @OncoAlert @DanaFarberNews #ESMO26 Positive
MV Chandrakanth Tarlatamab in SCLC: Decoding the Phase III DeLLphi Programme 🔹 304: Second line—vs chemotherapy 🔹 305: First-line maintenance—adding tarlatamab to durvalumab 🔹 306: Limited stage—after concurrent chemoradiotherapy 🔹 312: First line—adding tarlatamab during induction and maintenance 🔹 315: Subcutaneous vs intravenous delivery 📌 Different trials, different questions—not all have reported results. #MVOnco #SCLC #Tarlatamab #DeLLphi #DLL3 #LungCancer #ThoracicOncology #ClinicalTrials Neutral
Alfredo Addeo MD 🔥 TODAY COULD BE ONE OF THE DEFINING MOMENTS OF #ESMO26! 🔥 The ESMO Presidential Symposium is always one of the highlights of the congress, and today’s session promises some truly extraordinary science! If I had to pick ONE study with the greatest potential to change clinical practice at ESMO 2026, my choice would be DeLLphi-305. For decades, SCLC has been one of the most challenging diseases in oncology, with far too little progress and far too few therapeutic breakthroughs. Could DeLLphi-305 finally represent the major leap forward we have been waiting for? We already know that adding tarlatamab to durvalumab as first-line maintenance significantly improves OS compared with durvalumab alone. But today, we will finally see the numbers. And I am genuinely excited to discover just how transformative this benefit might be! My personal bet for the biggest breakthrough of #ESMO26? DeLLphi-305. @StephenVLiu @sands_jacob Of course, the magnitude of survival benefit, safety and clinical applicability will ultimately determine its impact. But the potential is enormous. Don’t miss today’s Presidential Symposium! Madrid | 🕟 16:30 CEST Alicante auditorium #ESMO26 #ESMOAmbassador #SCLC #LungCancer #Immunotherapy #Oncology #PracticeChanging Positive
Gil Morgan, MD Ten abstracts that will shape lung cancer practice, picked by our faculty 🫁 Stand-outs for me: DeLLphi-305 moving tarlatamab into 1L maintenance, and the head-to-head KRAS G12C data in Krascendo 1. Do not skip DIAL either: it asks whether we can safely stop IO at 6 months 👇 #ESMO26 #LCSM #LungCancer Neutral
Aakash Desai 3/ DeLLphi-305 (LBA3), Oct 24, 17:18 CEST Tarlatamab + durvalumab as 1L maintenance in ES-SCLC. Amgen reports an OS win at interim. How large, and can clinics deliver T-cell engager monitoring in maintenance? @LungCancerRx @OncoAlert @oncodaily https://t.co/g8um5k4dwG Neutral
MV Chandrakanth 🚨 DeLLphi-305 | ESMO 2026 | LBA3 Tarlatamab enters FIRST-LINE MAINTENANCE in ES-SCLC! A remarkable phase III survival breakthrough following platinum–etoposide + durvalumab. 🔬 563 patients | Tarla + Durva vs Durva 📊 EFFICACY - Median OS: 21.1 vs 12.7 months | HR 0.42 - 12-month OS: 79.4% vs 53.3% - Median PFS: 7.4 vs 1.9 months | HR 0.34 - ORR: 26.4% vs 4.1% ⚠️ SAFETY - Grade ≥3 TEAEs: 46.8% vs 40.6% - CRS: 49.6%; grade ≥3 only 0.4% - ICANS: 1.1%; no grade ≥3 events 🔍 THREE CLINICAL PEARLS 1. Survival measured from maintenance randomization, NOT chemotherapy initiation. 2. Only patients without progression after durvalumab-based induction were randomized. 3. Maintenance tarlatamab was NOT directly compared with guaranteed tarlatamab at relapse. 💡 TAKE-HOME: A compelling OS-positive trial that could redefine ES-SCLC maintenance. Patient selection, CRS monitoring and access remain crucial. 📚 Reference: Sands J, et al. DeLLphi-305: Tarlatamab + durvalumab as first-line maintenance in ES-SCLC. ESMO 2026; LBA3. @myESMO @OncoAlert @Larvol #ESMO26 #DeLLphi305 #SCLC #Tarlatamab #MVOnco Positive
Mustafa Özdoğan, MD DeLLphi-305 moves tarlatamab earlier into first-line maintenance for ES-SCLC. Tarlatamab + durvalumab has met OS, PFS and ORR versus durvalumab alone. The key question now: how large is the benefit, and does it justify the added CRS/ICANS monitoring burden? Presented by @sands_jacob @myESMO #ESMO26 #SCLC Neutral
Jeff Ryckman DeLLphi-305 (LBA3): tarlatamab + durva vs durva maintenance in ES-SCLC without progression after durva + platinum-etoposide. OS HR 0.42 (CI 0.32-0.54); 12-mo OS 79% vs 53%, median OS 21 vs 13 mo. Impressive OS signal. Was thoracic consolidation RT allowed? The abstract doesn't say. If so, would be interested to see fractionation/dosing schemes and how RT was interdigitated. #ESMO26 #radonc https://t.co/wazLJ6ejpv Positive
Tejas Patil 🌟AND finally, #ESMO26 wouldn't be complete without some of the HEAVY hitters. I expect these data to change practice! 1⃣Tarlatamab plus durvalumab (durva) vs durva as 1L maintenance (1LM) therapy following durva, platinum, and etoposide (1L durva + EP) in extensive-stage small cell lung cancer (ES-SCLC): Primary analysis of the phase 3 DeLLphi-305 trial. I fully expect this trial to establish DLL3 TCE as the dominant first line strategy in SCLC and will likely be practice changing. 2⃣Krascendo 1: Efficacy and safety of divarasib (diva) vs sotorasib (soto) or adagrasib (ada) in previously treated locally advanced or metastatic KRAS G12C-mutated NSCLC. Given the evolution of KRAS G12Ci in this space, what is notable here is the direct prospective comparison to current KRAS G12Ci (adagrasib / sotorasib). Looking forward to ascertain magnitude of potential benefit and safety differences. 3⃣INTerpath-001: Phase 3 study of the mRNA-based individualized neoantigen therapy (INT) intismeran autogene (intismeran) plus pembrolizumab (pembro) vs pembro alone for adjuvant treatment of resected stage IIB-IV melanoma (MEL) Technically not a lung cancer study, but I believe this trial to be game-changing from a proof-of-concept approach. In my mind, this study establishes personalized mRNA-based approaches as a viable approach and worthy of research and clinical investment. @lcsmchat @OncoAlert @OncLive @Onco_Nexus @LungCancerEu @Lung_Cancers @LungCancerRx @MedwatchHQ @KRASKickers @SclcSMASHERS @YoungLungCancer Positive
Rami Manochakian MD, FASCO 🚨🔥@OncoAlert Hot off the press. Just published @NEJM in conjunction with presentation @myESMO #ESMO26 the long-awaited #PracticeChanging results of: ⭐️#DeLLphi305 phase 3 trial of: ❇️1st line maintenance #Tarlatamab + #Durvalumab) vs #Durvalumab alone in patients with #ExtensiveStage #SmallCell #LungCancer after initial induction Tx with #Chemo + Durvalumab. Study showed: ‼️#Impressive statistically significant & clinically meaningful ⬆️#OverallSurvival Benefit. ✅#mOS: 21.1 vs 12.7 months (HR 0.42) ✅12-month OS: 79.4% vs 53.3% ✅#mPFS: 7.4 vs 1.9 months (HR 0.34) ⚠️ Grade ≥3 #AEs: 46.8% vs 40.6% * In Tarlatamab arm: #CRS: 49.6% (Grade ≥3: 0.4%) #ICANS: 1.1% (Grade ≥3: 0%) 👇🏻 https://t.co/JoYBDSUAo9 Positive
Eric K. Singhi, MD WOW! BIG news for our patients with extensive-stage small cell lung cancer! Phase 3 DeLLphi-305 trial, adding tarlatamab to durvalumab maintenance after initial chemoIO: ✅ OS: 21.1 vs 12.7 months (HR 0.42) ✅ PFS: 7.4 vs 1.9 months (HR 0.34) Practice-changed! #ESMO26 https://t.co/t23SBNzfUD Positive
Anirban Maitra From #ESMO26 & @NEJM Tarlatamab–Durvalumab Maintenance for Extensive-Stage Small-Cell Lung Cancer https://t.co/locTy831XT Practice changing data for a terrible disease with hazard ratios that are unequivocal. Positive
Giannis Mountzios #ESMO26 Presidential 1 : #SCLC DeLLphi-305: Who would have imagined some years ago that median OS of SCLC would equal that of non-AGA NSCLC! #Tarlatamab as 1L maintenance with Durvalumab after induction chemoIO in ES-SCLC improved OS from 12.7 to an impressive 21.1m, corresponding to a HR of 0.42. 80% of patients alive and 38% progression-free at 12 months The dawn of a new era for thoracic oncology and for the lives of our patients 💫✨ @myESMO @SclcSMASHERS #ESMOAmbassadors Positive
MV Chandrakanth 🥊 ES-SCLC | THE POWER OF PARTNERSHIP! 2018: ATEZO opens the game! (IMpower133, OS HR 0.70) 2019: DURVA joins the fight! (CASPIAN, HR 0.73) 2025: ATEZO + LURBI enter maintenance! (IMforte, HR 0.73) 🔥 2026: DURVA + TARLA raise the stakes! (DeLLphi-305, HR 0.42) 🔮 NEXT: DeLLphi-312 takes TARLA into first line. Results awaited! 💡 A smart drug can change practice. The right partner, at the right time, can change the game! HRs reflect separate trials—not head-to-head comparisons. @myESMO @OncoAlert @larvol #ESMO26 #SCLC #Immunotherapy #Tarlatamab #MVOnco Positive
Dr. Estela Rodriguez 🔥🔥#ESMO26 Top Thoracic Abstracts: #DeLLphi305: Phase III (n=563): Tarlatamab + Durvalumab vs Durvalumab as 1L maintenance after chemo-IO in ES-SCLC Definitely practice changing if we are able to deliver to more pts in the community , moving tarlatamab 1L maintenance ▶️Median OS: 21.1 vs 12.7 months (HR 0.42) 🔥 ▶️12-month OS: 79.4% vs 53.3% ▶️Median PFS: 7.4 vs 1.9 months (HR 0.34) ▶️ORR: 26.4% vs 4.1% ⚠️ Grade ≥3 AEs: 46.8% vs 40.6%; CRS 49.6% (mostly low grade). #lcsm @SclcSMASHERS Positive
gilberto lopes 🚨 Major SCLC results at #ESMO26! Phase III DeLLphi-305 (N=563): tarlatamab + durvalumab vs durvalumab 1L maintenance in ES-SCLC. Median OS: 21.1 vs 12.7 mo HR 0.42 (95% CI 0.32–0.54) 12-mo OS: 79.4% vs 53.3% An important survival advance. #LCSM https://t.co/WhlgNCfDyQ Neutral
Toni Choueiri, MD Outstanding presentation by our very own @DanaFarber @sands_jacob ! DeLLphi-305: tarlatamab + durvalumab vs durvalumab as 1L maintenance in ES-SCLC improved median OS to 21.1 vs 12.7 months (HR 0.42). A major advance for patients with SCLC! #ESMO26 @oncoalert @myESMO https://t.co/UxKz3Qgjp7 Positive
Hidehito HORINOUCHI 🆙#ESMO26 Presidential Symposium I: #LCSM 🔥DeLLphi-305: Tarlatamab Plus Durvalumab (Durva) vs Durva as 1L Maintenance (1LM) Therapy Following Durva, Platinum, and Etoposide in Extensive-Stage Small Cell Lung Cancer (ES-SCLC): Primary Analysis of the Phase 3 Trial 🎙️ @sands_jacob 🔢LBA3 🎯Met Primary Endpoint: Significantly Improved OS 🎯mOS 21.1 vs 12.7m, HR 0.42 🎯mPFS 7.4 vs 1.9m, HR 0.34 🎯ORR 26.4% vs 4.1% 🎯CRS 49.6% (Mostly Low Grade), No Fatal Events ☑️NCT06211036 🔗 https://t.co/Lb6tzuMm0z @OncoAlert @Larvol @myESMO @IASLC Positive
Hidehito HORINOUCHI 🆙 Published @NEJM 🎊 🔥Presidential Symposium I: #LCSM 🔥DeLLphi-305: Tarlatamab + durvalumab vs durvalumab as 1L maintenance in ES-SCLC 🎙️ Dr. Maurice Pérol @sands_jacob 🎯Met Primary Endpoint: Significantly Improved OS 🎯mOS 21.1 vs 12.7m, HR 0.42 🎯mPFS 7.4 vs 1.9m, HR 0.34 🎯ORR 26.4% vs 4.1% 🎯CRS 49.6% (Mostly Low Grade), No Fatal Events ☑️NCT06211036 🔗 https://t.co/dVb8S7vWJk @OncoAlert @Larvol @myESMO @IASLC Positive
Dr Amol Akhade DeLLphi-305. Immpresive curves . Additional Toxicity and cost in real world needs to be seen . Good for patients with extensive SCLC @myESMO @OncoAlert #esmo26 https://t.co/V2CDG9m0ZR Neutral
Balazs Halmos Starlatamab takes a huge BiTE today out of small cell lung cancer! Amazing PFS (0.34) and OS (0.42) HR and truly manageable added tox- 50% CRS but almost uniformly gr 1/2 and near non-existent ICANS, no new safety signal w durva combo just makes this one of the most impressive SCLC trials/ cancer trials ever.. Given extreme need for better treatments for our pts w ES-SCLC, unprecedented benefit seen in DeLLphi-305 plus availability/experience with use already it is a no-brainer to incorporate into our practice as SOC maintenance therapy on Monday… well, not Mon- whenever your flight takes you back post-#ESMO26 Amazing job by @sands_jacob and Amgen/DeLLphi team- glad we had a chance to offer such a transformational trial to our pts as well at Monte/Einstein! With these extraordinary results starlatamab is likely to continue to expand into 1st line/LS-SCLC settings and lets just dream on- if we as a field have taken such a tasty first BiTE, can hardly wait for the next one! Standing ovation- well deserved! #lcsm Positive
Abdulaziz AlJassim DeLLphi-305 a new standard of care in ES-SCLC Tarlatamab maintenance + Durvalumab after induction chemo-IO Huge win against SCLC! Congrats @sands_jacob and DeLLphi-305 group And a standing ovation! 👏🏼 https://t.co/a4380aJDuB Positive
Dr. Antonio Calles 🫁🚭 📖 A new chapter in SCLC therapy has been written by @sands_jacob 💥 DeLLphi-305 sets a new standard of care in maintenance after induction chemo-io for patients with ES-SCLC #ESMO26 @myESMO https://t.co/vVhg7SmgsL Positive
Toni Choueiri, MD JUST Ian: DeLLphi-305: Phase III (n=563): Tarlatamab + Durvalumab vs Durvalumab as 1L maintenance after chemo-IO, to be presented by our own @sands_jacob from @DanaFarber • Median OS: 21.1 vs 12.7 months (HR 0.42) • Median PFS: 7.4 vs 1.9 months (HR 0.34) • ORR: 26.4% vs 4.1% Grade ≥3 AEs: 46.8% vs 40.6%; CRS 49.6% (most low grade). Probably new standard of care in ES-SCLC. @OncoAlert @DanaFarberNews #ESMO26 Positive
Noemi Reguart Looking forward to the #ESMO26 Presidential Symposium! Exciting DeLLphi-305 data in ES-SCLC, presented by @JacobSandsMD, followed by what promises to be an insightful discussion from Dr. Stephen Liu @StephenVLiu Auditorium packed! #ESMO26 https://t.co/2U2JJj4T82 Positive
Alfredo Addeo MD 🔥 DeLLphi-305 shook the room at #ESMO26 and what a spectacular discussion by @StephenVLiu Outstanding data deserve an equally outstanding discussion, and Stephen delivered! 👏 💥 OS HR 0.42 , unprecedented impact in ES-SCLC! Key questions: CNS efficacy, long-term survival, predictive biomarkers and optimal treatment sequencing. Encouraging outpatient feasibility and improved monitoring requirements. And one crucial message: global access to this breakthrough treatment must become a priority. Spectacular science, spectacular discussion! A truly unforgettable ESMO Plenary! #ESMOAmbassadors #ESMO26 #DeLLphi305 #SCLC #LungCancer Positive
Noemi Reguart Impressive results from phase III DeLLphi-305 at #ESMO26 @sands_jacob: Adding tarlatamab to durvalumab maintenance in ES-SCLC 1-y OS nearly 80%!!! 🔹 OS: 21.1 vs 12.7 mo (HR 0.42) 🔹 PFS: 7.4 vs 1.9 mo (HR 0.34) A standing ovation!” 👏👏👏👏A major step forward for SCLC! @NEJM https://t.co/DLSwuhPS9W Positive
Dr Riyaz Shah DeLLphi-305; ES-SCLC; nearly 2y mOS; Strong PFS signal; this is about the strongest data I’ve seen in this space. @BTOGORG #ESMO26 https://t.co/rukehL59lQ Positive
Alfredo Addeo MD 🚨🔥 ABSOLUTELY STUNNING! DeLLphi-305 at #ESMO26! @sands_jacob presents remarkable phase III results in ES-SCLC! 💥 Tarlatamab + durvalumab vs durvalumab maintenance 🔥 Median OS: 21.1 vs 12.7 months 🔥 HR 0.42 (95% CI 0.32–0.54), p<0.001 🔥 12-month OS: 79% vs 53% 58% reduction in the hazard of death! These are extraordinary results in a disease where meaningful survival advances have been so difficult to achieve. 👏 Congratulations and I welcome A new benchmark for ES-SCLC maintenance therapy #ESMOAmbassadors #ESMO26 #SCLC #LungCancer #DeLLphi305 Positive
Uğur Özkerim 🚨 Impressive results from #ESMO2026! Phase III DeLLphi-305: Tarlatamab + durvalumab vs durvalumab alone as 1L maintenance in ES-SCLC: 🔹 Median OS: 21.1 vs 12.7 months (HR 0.42) 🔹 Median PFS: 7.4 vs 1.9 months (HR 0.34) 🔹 ORR: 26.4% vs 4.1% 🔥 Practice-changing potential! #LungCancer #SCLC @OncoAlert @weoncologists @StephenVLiu @GlopesMd @ManuelDomine Positive
Tian Zhang, MD, MHS, FASCO (@tiansterzhangmd.bsky) with Dellphi305 — tarlatamab w durvalumab vs durvalumab for small cell lung cancer — almost doubling of overall survival w manageable CRS & outpatient treatment. Standing ovation for small cell! @nejm concurrent pub today. @oncoalert @myESMO #ESMO26 https://t.co/Z25EA6hQL2 Neutral
Philippe Aftimos, MD  I very much enjoyed the discussion by @StephenVLiu of DeLLphi-305 (tarlatamab + durvalumab as maintenance therapy in ES-SCLC at #ESMO26 👏👏👏 #ESMOAmbassadors https://t.co/Wl31gpUtEu Positive
Oriol Mirallas MD 🔥 Presidential Symposium I #ESMO26 🗣️ @sands_jacob @DanaFarber DeLLphi-305 trial evaluating tarlatamab + durva vs durva as 1LM therapy for ES-SCLC. ✔️ mOS 21.1 vs 12.7m HR 0.42 ✔️ mPFS 7.4 vs 1.9m HR 0.34 ✔️ ORR 26.4 vs 4.1% ☣️ 46.8 vs 40.6% grade 3 or higher @OncoAlert @myESMO @ASCO @_SEOM @UTMDAnderson @NEJM @brunolarvol 👇🏽👇🏽 Positive
Leonardo Brunetti Striking results from DeLLphi-305 in SCLC topped with an emotional standing ovation. Mainteinance Tarlatamab is actually more like a second induction-treatment rather than a proper mainteinance! Kudos to @sands_jacob for the magistral presentation #ESMO26 #ESMOAmbassadors https://t.co/2w1PXt8jLu Neutral
Carlo Genova Standing ovation at #ESMO2026 for DELLPHI-305. It is heart-warming to see a meaningful survival advantage in ED-SCLC. https://t.co/ZkEwRPh2v6 Neutral
Dr Riyaz Shah Great DeLLphi-305 discussion by @StephenVLiu ; let’s not forget the drop off post induction; seems to trump lurbi; ICANS and CRS noted but manageable. #ESMO26 https://t.co/9rY5N8188X Neutral
Ryan Gentzler, MD Expert discussion of DeLLphi-305 by @StephenVLiu. Bringing tarlatamab to maintenance is major advance as second line tarlatamab is often “a promise we cannot keep.” Many patients never receive 2nd line. #ESMO26 https://t.co/T6IRxIS8ev Positive
Elvina Almuradova #ESMO26 | DeLLphi-305 Maintenance tarlatamab + durvalumab prolonged median OS to 21.1 vs 12.7 months with durvalumab alone in ES-SCLC at the prespecified interim analys @NEJM @myESMO @Larvol https://t.co/5YjJCDcyNi Neutral
Alan Tan DeLLphi-305 at #ESMO26, presented by Jacob Sands, got a standing ovation. An important advance in very aggressive biology. Tarlatamab + durvalumab vs durvalumab as 1L maintenance in ES-SCLC: ▪️ OS HR 0.42, median 21.1 vs 12.7 mo ▪️ PFS HR 0.34 ▪️ ORR 26.4% vs 4.1% Important to study in NEPC and small cell bladder. Neutral
OsmanKostekMD 🚨 ESMO 2026 | DeLLphi-305 Tarlatamab + durvalumab delivers impressive survival benefits in 1L maintenance ES-SCLC! ✅ OS: 21.1 vs 12.7 mo (HR 0.42) ✅ PFS: 7.4 vs 1.9 mo (HR 0.34) Benefits maintained across key subgroups, including brain and liver metastases. 🔥 New SOC 💫💫 https://t.co/bEhzHFst9o Positive
Guilherme S. C. Correia, MD Real-time first-line updates in ES-SCLC! Getting closer and closer to a 2yr mOS. Tarlatamab + Durvalumab maintenance improved mOS to 21.1 months compared to 12.7 months with single agent Durva. New standard of care in this space! https://t.co/9kDH9ap8HL Positive
Martín Angel Presidential symposium 1️⃣!! DeLLphi-305 study: Tarlatamab + durva significantly improved ✅ OS, PFS, and ORR ‼️ in 1LM ES-SCLC @myESMO #ESMO26 a 🆕 standard of care! https://t.co/TJw3Q74PNE Positive
Ryan Gentzler, MD Excited to see the highly anticipated DeLLphi-305 at #ESMO26. First line maintenance tarlatamab + durvalumab improves PFS and OS. Updated label for outpt monitoring hopefully make this more accessible for all #SCLC patients. The next frontier: Limited Stage consolidation https://t.co/GaX09tjke2 Positive
Abeid Athman (Omar). In DeLLphi-305: The combination of Tarlatamab+ Durvalumab improves both OS (21 vs 12 months HR 0.42) and PFS in ES-SCLC. This is remarkable in such a lethal disease with high recurrence rates and mortality. #ESMO2026 #ESMOAmbassadors @myESMO @StephenVLiu @tompowles1 @FAndreMD https://t.co/fE2K7k2Jha Positive
Dr. Estela Rodriguez 🔥🔥#DeLLPhi305 concurrent @NEJM publication Tarlatamab–Durvalumab Maintenance for Extensive-Stage Small-Cell Lung Cancer | New England Journal of Medicine https://t.co/PJCEjJ0QMk Positive
Dipesh Uprety MD FACP DeLLphi-305 @NEJM #ESMO26 ➡️Pts with ES-SCLC without progression after initial chemo-IO randomized to tarlatamab–durvalumab with durvalumab as 1L maintenance therapy ➡️ Md OS 21.1 mo (tarla arm) vs 12.7 months ➡️Md PFS 7.4 mo (tarla arm) vs 1.9 mo Practice changing and now a new standard of care #LCSM @OncoAlert https://t.co/BM6jNTyFw6 Positive
Peter Grell MD Standing ovation at #ESMO26! 👏 Practice-changing Phase 3 results from DeLLphi-305 (LBA3) for maintenance tarlatamab + durvalumab in 1L ES-SCLC: mOS: 21.1 vs 12.7 mo (HR 0.42; p < 0.001) A new standard of care with BiTE + ICI💥 https://t.co/2TAEwtvbnY Positive
Pablo Flores 🔥 Hot off the press! 📄! Tarlatamab–Durvalumab Maintenance for Extensive-Stage Small-Cell Lung Cancer | New England Journal of Medicine https://t.co/mgUWrdUWme Positive
David Heredia. Dellphi 305 Tarlatamab in Combination With Durvalumab vs Durvalumab Alone in Subjects With Extensive-Stage Small-Cell Lung Cancer Following Platinum, Etoposide and Durvalumab Are we changing prognosis of SCLC? Yes we are. Results speak for themselves. OS 21.1m vs 12.7 m https://t.co/7KAfEx4Nlv Neutral