Physician reactions to DeLLphi-304
Posts by physicians about DeLLphi-304, newest first: ESMO 2026 week (October 17–26, 2026), then reactions to the ASCO 2026 CNS post hoc analysis (Abstract 8006). Each post is shown in full and verbatim and linked to the original on X.
 𝕏
Tarlatamab produces sustained survival benefits in relapsed-refractory SCLC in long-term follow-up from the DeLLphi-304 trial presented at @myESMO #ESMO26. I’m sounding like a broken record here, but we have to get all patients with SCLC access to tarlatamab. @SclcSMASHERS https://t.co/69idgFy8Nf
 𝕏
Important longer follow up from DeLLphi-304 (2L tarlatamab vs SCLC) presented by Dr. @charlesrudin at #ESMO26 simultaneously published @Annals_Oncology. Median PFS 4.2 vs 3.2m, mOS 13.6 vs 8.4m, 2y OS 30% vs 15%, RR 35% vs 20% #ESMOAmbassadors https://t.co/2kvS0rW3ug
 𝕏
#ESMO26 Does Tarlatamab provide long term benefit to responding patients? ✅The answer is Yes! ➡️Extended F-UP of the Dellphi-304 trial shows that after 22m of F-UP Landmark 2-year OS was 30% vs 15% and sustained disease control in 24% of patients at > 52 weeks ❓We need to investigate the characteristics of those patients to understand how we can improve the outcomes of the 70% of patients who do not make it to two years @myESMO #ESMOAmbassadors
 𝕏
🔥DeLLphi-304: Extended follow-up of tarlatamab vs chemo in 2L SCLC 🆙 @Annals_Oncology #ESMO26 🎙 @charlesrudin 🎯Durable OS Benefit at 23-Mo Median Follow-Up 🎯mOS 13.6 vs 8.4mo (HR 0.62); 18-Mo OS 42% vs 24% 🎯Grade≥3 TRAEs 28% vs 63% ☑️NCT05740566 @OncoAlert @Larvol @myESMO @IASLC https://t.co/Z0q2VGcYv3
 𝕏
DeLLphi 304 update; extended FU of 23m; tantalising prospect of a landmark survival tail? mDOR 7.1m ; no new tox signals; #ESMO26 https://t.co/qHp3LVCbDs
 𝕏
DeLLphi-304: 🫁 Tarlatamab sustained its OS benefit at 23-month follow-up, improving median OS to 13.6 vs 8.4 months (HR 0.62) @OncoAlert #ESMO26 @ESMO_Open #ESMOAmbassadors #LungCancer #ESMOcommunity @myESMO https://t.co/tqxtg7Mg1p
𝕏🆙#ESMO26 Proffered Paper: #LCSM Non-Mets 🔥DeLLphi-304: Tarlatamab in Previously Treated SCLC: Extended Follow-Up of Overall Survival From the Phase 3 Trial 🎙️ @charlesrudin 🔢3808O 🎯Durable OS Benefit at 23-Mo Median Follow-Up 🎯mOS 13.6 vs 8.4mo (HR 0.62); 18-Mo OS 42% vs 24% 🎯Grade≥3 TRAEs 28% vs 63% ☑️NCT05740566 🔗 https://t.co/grEfaUchKN @OncoAlert @Larvol @myESMO @IASLC
 𝕏
Tarlatamab in previously treated SCLC: extended OS follow-up from DeLLphi-304, featured in a Proffered Paper Session at #ESMO26. Primary analysis: median OS 13.6 vs 8.3 months with chemotherapy (HR 0.60). @Larvol @myESMO @OncoAlert https://t.co/3sDJHIG4FX
 𝕏
🚨 This is the kind of survival signal that changes the conversation in relapsed SCLC. @OncoAlert At #ESMO26, extended follow-up from phase III DeLLphi-304 strengthens the case for tarlatamab after first-line platinum-based chemotherapy. 🫁 n=509 | median follow-up 23 months ➡️ Median OS: 13.6 vs 8.4 months HR 0.62 (0.51–0.76) ➡️ 18-month OS: 42% vs 24% ➡️ In patients with baseline brain metastases: OS HR 0.52 (0.38–0.70) And importantly: ⚠️ Grade ≥3 TRAEs: 28% vs 63% with chemotherapy 🎯 Why this matters: in a disease where durable second-line benefit has historically been difficult to achieve, tarlatamab is delivering both meaningful survival improvement and a more favorable high-grade toxicity profile. For me, the brain-metastases subgroup is especially compelling and deserves close attention as we refine where DLL3-targeted therapy fits in the treatment pathway. Excellent work from @charlesrudin @g_mountzios @cbcbc1971 @JulienMazieres @teekayowo @LuisPaz_Ares and the DeLLphi-304 investigators. Pinging @christine_lovly @GlopesMd @DrSanjayPopat @StephenVLiu @jillfeldman4 @UOzkerim @DrMirallas @MartinReck2 @CharuAggarwalMD @peters_solange #OncoAlert #ESMO26 #LungCancer #SCLC #Tarlatamab #DLL3 #Immunotherapy
𝕏🆙#ESMO26 Proffered Paper: #LCSM Non-Mets 🔥DeLLphi-304: Tarlatamab in Previously Treated SCLC: Extended Follow-Up of Overall Survival From the Phase 3 Trial 🎙️ @charlesrudin 🔢3808O 🎯Durable OS Benefit at 23-Mo Median Follow-Up 🎯mOS 13.6 vs 8.4mo (HR 0.62); 18-Mo OS 42% vs 24% 🎯Grade≥3 TRAEs 28% vs 63% ☑️NCT05740566 🔗 https://t.co/grEfaUbJVf @OncoAlert @Larvol @myESMO @IASLC
 𝕏
Tarlatamab in SCLC: Decoding the Phase III DeLLphi Programme 🔹 304: Second line—vs chemotherapy 🔹 305: First-line maintenance—adding tarlatamab to durvalumab 🔹 306: Limited stage—after concurrent chemoradiotherapy 🔹 312: First line—adding tarlatamab during induction and maintenance 🔹 315: Subcutaneous vs intravenous delivery 📌 Different trials, different questions—not all have reported results. #MVOnco #SCLC #Tarlatamab #DeLLphi #DLL3 #LungCancer #ThoracicOncology #ClinicalTrials

Tarlatamab n=254 vs chemo n=255. 🧠Takeaway: meaningful CNS benefit. CNS PFS, all patients (RECIST, ITT): 🧠median NE (95% CI 13.7–NE) with tarlatamab vs 7.2 mo with chemo. 🧠HR 0.54 (0.39–0.75) 🧠a 46% lower risk of CNS progression or death. #ASCO26 @SclcSMASHERS @ASCO
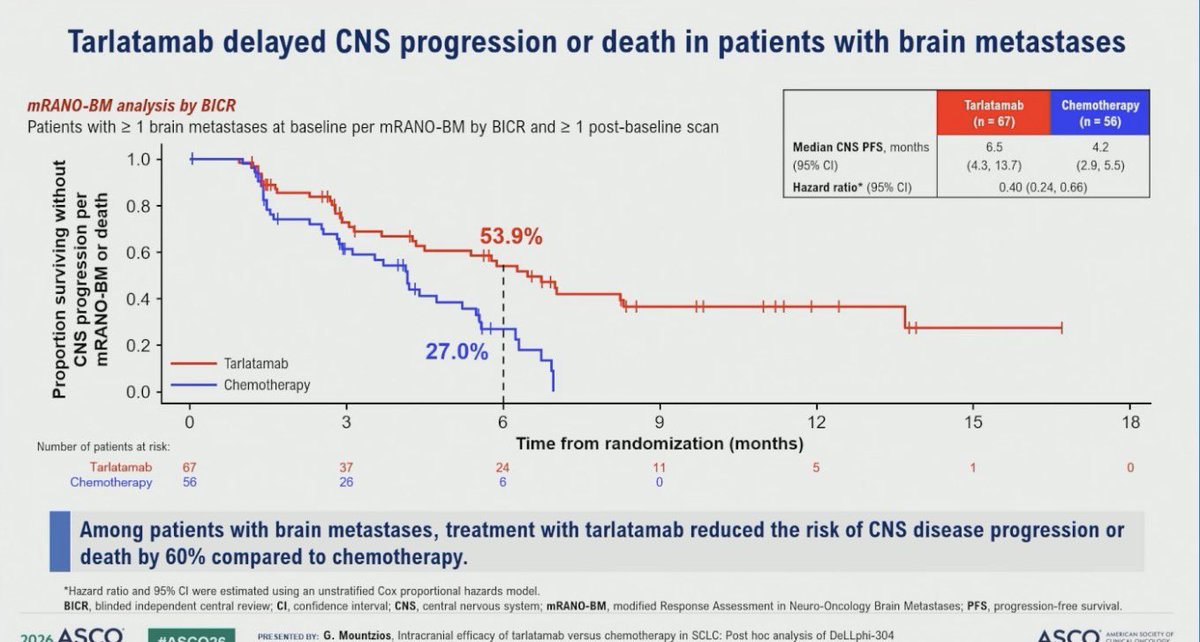
In patients WITH baseline brain mets (mRANO-BM/BICR, tarlatamab n=67 vs chemo n=56): median CNS PFS 6.5 vs 4.2 mo, HR 0.40 (0.24–0.66) 6-mo CNS PFS 53.9% vs 27.0% Small subsets but a 60% risk reduction @ASCO #ASCO26 #LCSM @SclcSMASHERS
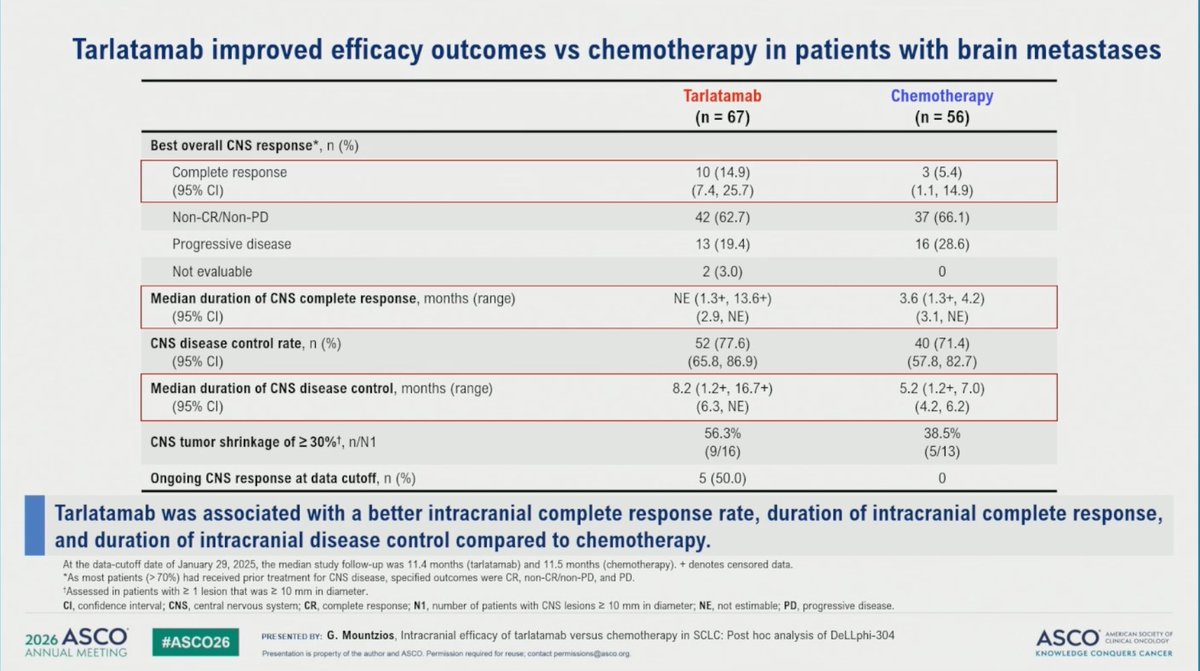
OS in patients with brain mets: 13.9 vs 6.8 mo, HR 0.51 (0.34–0.74) 🧠tarlatamab cut risk of death by 49% vs chemo. 🧠Intracranial CR rate and duration of intracranial disease control also favored tarlatamab. #ASCO26 @ASCO #LCSM @SclcSMASHERS #medED

Day 3 & 4 #ASCO26 highlights: 1. #evERA: Giredestrant in mHR+ BC 2. #ASCENT03/04: Saci 1L mTNBC 3. #CIRCULATE: ctDNA in CRC 4. #EPISODE3: Adj Aspirin in CRC 5. #EMERALD3: STRIDE + TACE + Len in HCC 6. #DeLLphi304: Tarla in SCLC @ASCO #OncTwitter @OncoAlert 1/7
What a happy coincidence! While presenting intracranial efficacy data from DeLLphi-304 in #ASCO26, #Tarlatamab was officially approved in EU!! ✅ In ITT: CNS mPFS NR vs 7.8 m, HR=0.54 ✅ In BM per mRANO: CNS mPFS 6.5 vs 4.2m, HR=0.4 ✅ mOS=13.9 vs 6.8, HR=0.51, independent

🚨 #ASCO26 | DeLLphi-304 post hoc analysis #️⃣Abstr 8006 🧠 Tarlatamab vs chemotherapy in 2L SCLC with brain metastases ✅ All patients Tarlatamab delayed CNS progression/death CNS PFS: NE vs 7.2 mo, HR 0.54 🧠 Patients with brain metastases ・Median CNS PFS: 6.5 vs 4.2 mo,
Dr. @g_mountzios #ASCO26 presents CNS outcomes with 2L tarlatamab in DeLLphi-304. Improved time to CNS progression overall (HR 0.54). In pts with brain nets, tarlatamab vs chemo CNS CR rate 15% vs 5% with DCR 78% vs 71% and time to CBS progression 6.5m vs 4.2m, HR 0.40

ASCO26 DeLLphi-304 CNS post hoc: #tarlatamab delayed CNS progression/death vs chemo in 2L ES-SCLC. CNS PFS HR 0.54 overall; HR 0.40 with brain mets. Also improved OS in pts with brain mets: 13.9 vs 6.8 mo; HR 0.51. Strong CNS signal here.

#ASCO26 One of the most clinically relevant SCLC updates of the meeting. In DeLLphi-304, tarlatamab not only improved OS versus chemotherapy, but also showed meaningful intracranial activity: • CNS progression/death HR 0.54 overall • HR 0.40 in patients with brain metastases

🔥🚨@OncoAlert Hot off the press. Just presented @ASCO #ASCO26 by Dr. @g_mountzios ⭐️#PostHoc Analysis Results of #Intracranial 🧠 #Efficacy of: ❇️#Tarlatamab 🆚 #Chemotherapy in #2nd line treatment for #SmallCell #LungCancer in the #DeLLphi304 Trial. ‼️‼️#Exciting &

DeLLphi-304: Tarlatamab vs Chemo for Brain Mets in Relapsed SCLC ▫️Median CNS PFS 6.5 vs 4.2 mos ▫️Intracranial CR: 14.9% vs 5.4% @g_mountzios #ASCO26

DeLLphi-304: 🫁 Tarlatamab Redefines CNS Control in Relapsed SCLC, Cutting Intracranial Progression Risk by 60% @ASCO @OncoAlert #Lcsm #ASCO26
DeLLphi-304 Key Takeaways
ESMO 2026 (3808O) — Extended follow-up of overall survival (data cutoff 18 Feb 2026)
Dr. Charles M. Rudin (Memorial Sloan Kettering Cancer Center) presented this update on October 26, 2026 in the ESMO 2026 Proffered Paper session on non-metastatic NSCLC and other thoracic malignancies (invited discussant: Kersti Oselin), with simultaneous publication in Annals of Oncology. It is a later data cut of the same randomized population (tarlatamab n=254 vs chemotherapy n=255: topotecan, lurbinectedin or amrubicin). The primary endpoint, overall survival, was met at the primary (interim) analysis (data cutoff 29 Jan 2025, below); this extended follow-up is descriptive, with no new p-values reported. Median follow-up is now 23.3 vs 22.8 months for OS, versus 11.2 vs 11.7 months at the primary analysis.
| Endpoint (DCO 18 Feb 2026) | Tarlatamab (n=254) | Chemotherapy (n=255) | Source |
|---|---|---|---|
| Median overall survival (primary endpoint) | 13.6 mo (11.9–15.8) | 8.4 mo (7.2–10.2) | 3808O abstract |
| OS hazard ratio | 0.62 (95% CI 0.51–0.76) | 3808O abstract; 3808O slides | |
| OS at 12 / 18 / 24 months | 56% / 42% / 30% | 39% / 24% / 15% | 12, 18 mo: 3808O abstract; 24 mo: 3808O slides (Annals of Oncology: 30.3% vs 14.9%) |
| Median progression-free survival | 4.2 mo (3.0–4.4) | 3.2 mo (2.9–4.2) | 3808O abstract |
| PFS hazard ratio | 0.69 (95% CI 0.57–0.84) | 3808O abstract; 3808O slides | |
| PFS at 12 / 18 months | 21% / 16% | 6% / 4% | 12 mo: 3808O abstract; 18 mo: 3808O slides |
| Objective response rate | 35% (30–42) | 20% (16–26) | 3808O slides (Annals of Oncology: 35.4% vs 20.4%) |
| Median duration of response (responders, n=90 vs 52) | 7.1 mo (4.5–12.4) | 5.5 mo (4.2–5.7) | 3808O abstract; 3808O slides |
| Responders still in response at 12 months (KM estimate) | 42% | 10% | 3808O abstract; 3808O slides |
| Sustained disease control ≥52 weeks | 24% (62 pts) | 4% (11 pts) | 3808O abstract |
| Grade ≥3 treatment-related adverse events | 28% | 63% | 3808O abstract |
| Discontinuation due to treatment-related adverse events | 3% | 7% | 3808O abstract (Annals of Oncology: 3.2% vs 6.6%) |
In exploratory subgroup analyses the OS hazard ratio was 0.65 (95% CI 0.48–0.86) in patients with platinum-resistant disease (chemotherapy-free interval <90 days) and 0.52 (95% CI 0.38–0.70) in patients with baseline brain metastases. The abstract reports no new safety signals, with treatment-related adverse events decreasing over time; the paper reports no serious treatment-related adverse events with onset at 12 months or later, and cytokine release syndrome and ICANS occurring early and predominantly low grade. (3808O abstract; Annals of Oncology; DCO 18 Feb 2026)
The primary-analysis figures below (median OS 13.6 vs 8.3 months, HR 0.60) come from the earlier data cut; the 8.4-month chemotherapy median and HR 0.62 belong to the extended follow-up. The two cuts are reported separately here. DeLLphi-304 is the second-line trial; DeLLphi-305 (first-line maintenance tarlatamab plus durvalumab) is a separate trial with its own page.
Extended follow-up: OS 13.6 vs 8.4 mo · HR 0.62 (0.51–0.76) · 24-mo OS 30% vs 15%Source: ESMO 2026 programme, abstract 3808O (Rudin et al.) ↗
Source: Rudin CM et al., Annals of Oncology 2026, doi:10.1016/j.annonc.2026.10.095 ↗
Overall Survival (Primary Endpoint — MET, primary analysis, ASCO 2025 / NEJM)
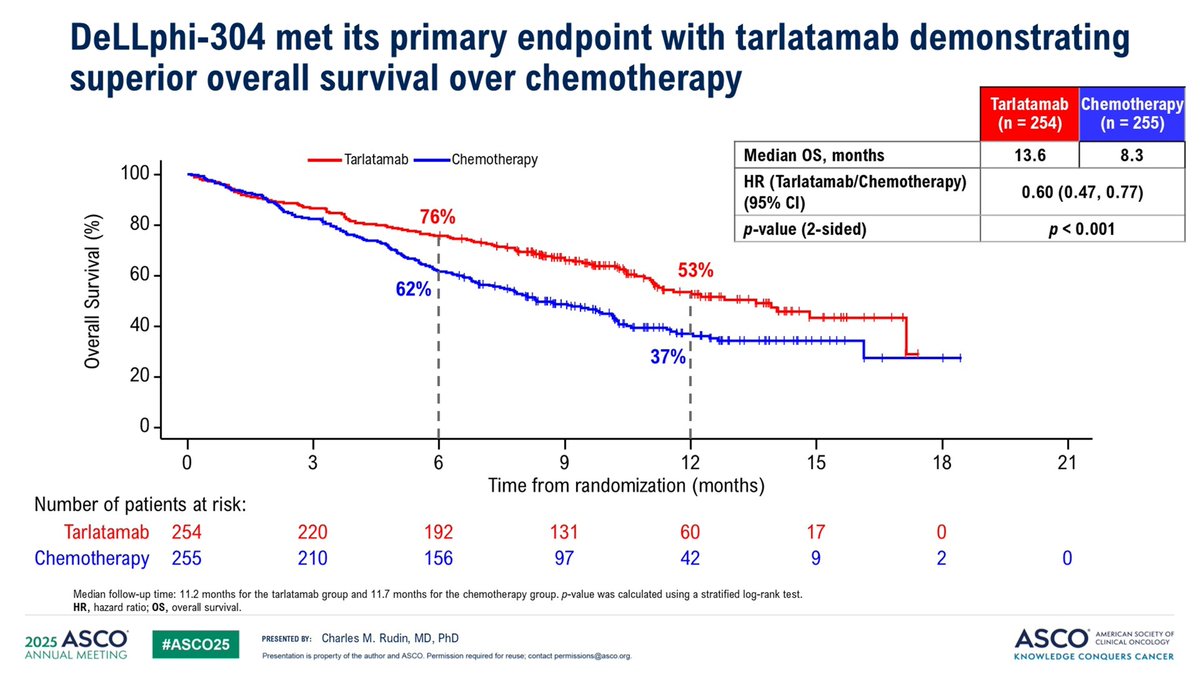
In the pivotal analysis presented at ASCO 2025 and published in NEJM, tarlatamab produced a statistically significant overall-survival benefit versus chemotherapy in 2L SCLC: median OS 13.6 vs 8.3 months (HR 0.60; 95% CI 0.47–0.77; p<0.001). In a pre-specified exploratory subgroup analysis, the OS hazard ratio was similar by chemotherapy-free interval (0.60 [95% CI 0.43–0.84] for CFI <90 days; 0.65 [0.45–0.93] for ≥90 days; FDA label).
Median OS 13.6 vs 8.3 mo · HR 0.60 (0.47–0.77) · p<0.001Sources: Mountzios et al., N Engl J Med 2025;393(4):349-361 (doi:10.1056/NEJMoa2502099) · ASCO 2025 oral presentationProgression-Free Survival & Response (primary analysis, ASCO 2025 / NEJM / FDA label)
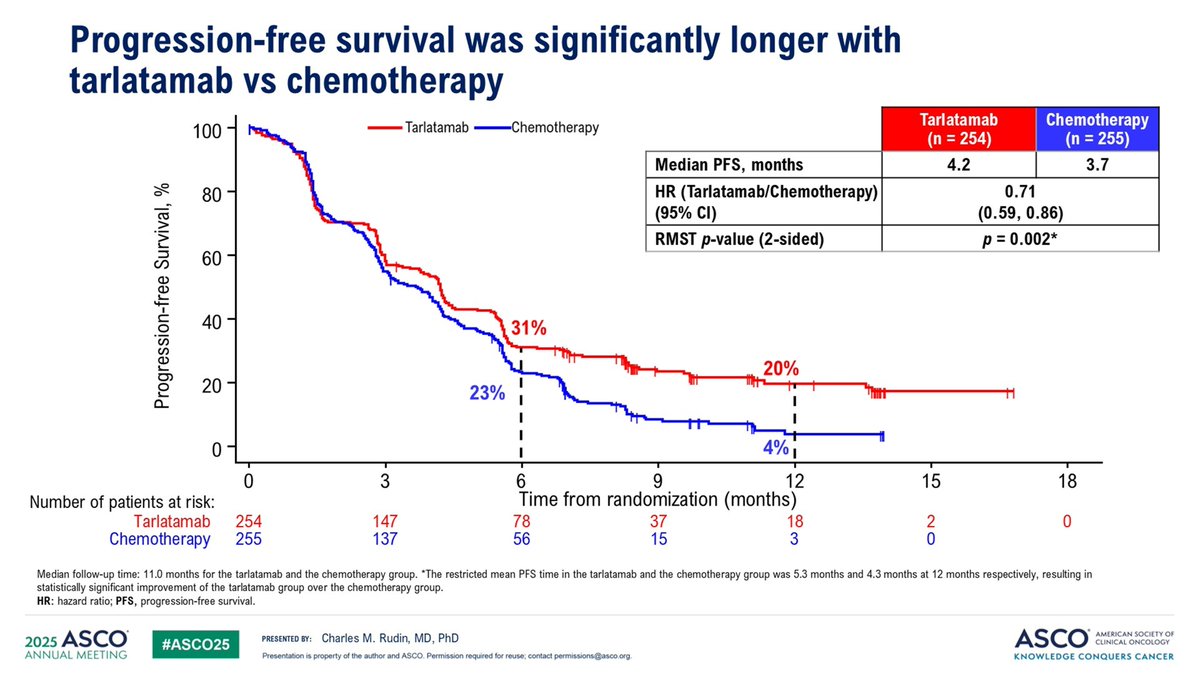
Tarlatamab also improved investigator-assessed progression-free survival, a key secondary endpoint. The FDA prescribing information reports median PFS 4.2 vs 3.2 months (HR 0.72; 95% CI 0.59–0.88; p<0.001); the NEJM publication and the ASCO 2025 primary-analysis slide reported 4.2 vs 3.7 months (HR 0.71; 95% CI 0.59–0.86; 2-sided restricted-mean PFS test p=0.002). On the ASCO 2025 primary-analysis slide (median follow-up about 11 months), the objective response rate was 35% vs 20% (investigator-assessed; not formally tested) and median duration of response 6.9 vs 5.5 months; extended-follow-up response data are in the ESMO 2026 table above. Patient-reported dyspnea also improved significantly at week 18 with tarlatamab.
PFS 4.2 vs 3.2 mo · HR 0.72 (0.59–0.88) (FDA label) · ORR 35% vs 20% (ASCO 2025 primary analysis)Sources: DeLLphi-304, N Engl J Med 2025;393(4):349-361 · ASCO 2025 primary-analysis slides (Rudin) · FDA Imdelltra prescribing informationCNS Post Hoc — Intracranial Efficacy (#ASCO26, Abstract 8006)
In this post hoc analysis, tarlatamab delayed time to CNS progression/death versus chemotherapy across the overall (ITT) population — median CNS PFS not reached vs 7.2 months (HR 0.54; 95% CI 0.39–0.75). Among patients with baseline brain metastases (39% of each arm), the intracranial benefit was more pronounced: median CNS PFS 6.5 vs 4.2 months (HR 0.40; 95% CI 0.24–0.66); intracranial complete response 15% vs 5%; CNS tumor shrinkage (≥30%) 56% vs 38%; CNS duration of disease control 8.2 vs 5.2 months; and overall survival 13.9 vs 6.8 months (HR 0.51; 95% CI 0.34–0.74) favoring tarlatamab.
Brain-mets pts: CNS PFS 6.5 vs 4.2 mo · HR 0.40 · iCR 15% vs 5% · OS 13.9 vs 6.8 mo (HR 0.51) · ITT CNS PFS NR vs 7.2 mo · HR 0.54 (0.39–0.75)Sources: Mountzios et al., DeLLphi-304 CNS post hoc, ASCO 2026 Abstract 8006 (J Clin Oncol 44, suppl) · The ASCO Post · OncLive ASCO 2026 coverageSafety & Tolerability
Tarlatamab was associated with fewer severe (Grade ≥3) adverse events than chemotherapy (54% vs 80%), largely reflecting reduced hematologic toxicity. The characteristic tarlatamab toxicities are cytokine release syndrome (CRS, 56% — predominantly Grade 1–2; Grade ≥3 only 1.2%), concentrated around the step-up dosing period, and immune effector cell–associated neurotoxicity syndrome (ICANS) — both are covered by the boxed warning and are managed with monitoring and supportive care. Serious adverse reactions occurred in 52% of patients; 6% permanently discontinued tarlatamab for an adverse reaction (FDA label).
Grade ≥3 AEs (any cause) 54% vs 80% (NEJM) · CRS 56%, Grade 3–4 1.2% (FDA label) · 6% permanently discontinued tarlatamab for an adverse reaction (FDA label)Sources: DeLLphi-304, N Engl J Med 2025;393(4):349-361 · FDA Imdelltra prescribing information (rev. 11/2025)Regulatory status & clinical implications
FDA approved (ES-SCLC with progression on or after platinum-based chemotherapy); Amgen; tarlatamab (Imdelltra). DeLLphi-304 establishes tarlatamab as a standard second-line option in relapsed SCLC, an area with historically poor outcomes. The ASCO 2026 CNS data are especially meaningful because brain metastases are common in SCLC and have been difficult to control with chemotherapy — one KOL (@uozkerim) called it one of the most clinically relevant SCLC updates of the meeting. These post hoc, hypothesis-generating findings are consistent with activity in patients with CNS involvement; DeLLphi-304 is the confirmatory Phase 3 for the approval.
Standard 2L SCLC option · Meaningful intracranial control in brain-mets ptsSources: ASCO 2026 Abstract 8006 discussion · The ASCO Post · KOL commentary (#ASCO26)Compiled and reviewed by the KOL Pulse research team, led by Brian Shields, Founder, KOL Pulse. Last updated October 26, 2026.
KOLs Discussing DeLLphi-304



DeLLphi-304 Key Slides & Visuals
ESMO 2026 slides


More slides on this page
CNS post hoc slides shared by KOLs at the #ASCO26 oral abstract session (Abstract 8006, presented by Giannis Mountzios, MD), plus the ASCO 2025 primary overall-survival readout. Click any image to expand.

























DeLLphi-304 Trial Design
DeLLphi-304 (NCT05740566) is a Phase 3, global, randomized, open-label trial of tarlatamab (Imdelltra) versus investigator's choice of standard chemotherapy (topotecan, lurbinectedin, or amrubicin) in patients with small-cell lung cancer that has relapsed after one prior platinum-based regimen. Tarlatamab is a first-in-class DLL3 × CD3 bispecific T-cell engager (BiTE). The pivotal results — a statistically significant overall-survival benefit — were presented at ASCO 2025 and simultaneously published in the New England Journal of Medicine. At #ASCO26, Dr. Giannis Mountzios presented a prespecified CNS post hoc analysis (Abstract 8006) characterizing intracranial efficacy, including in the subgroup with baseline brain metastases.
Study Design
Phase 3, global, randomized 1:1, open-label. Tarlatamab IV (1 mg step dose, then 10 mg Q2W) vs investigator's choice chemotherapy. Primary endpoint: overall survival. CNS endpoints assessed by post hoc analysis.
Population
Adults with relapsed SCLC after exactly one prior platinum-based line; 44% platinum-resistant (chemotherapy-free interval <90 days; 223/509). Patients with treated/stable brain metastases were eligible, enabling the intracranial efficacy analysis.
Intervention
Experimental: Tarlatamab (DLL3 BiTE), Q2W after step-up dosing. Control: Topotecan, lurbinectedin, or amrubicin per investigator choice.
Endpoints
Primary: Overall survival. Key secondary: PFS, ORR, safety, PROs. Post hoc (ASCO 2026): time to CNS progression/death, intracranial response, and OS in patients with brain metastases.
Key KOL Sentiments — DeLLphi-304











Earlier: WCLC 2026 reaction (Sept 2026)
WCLC 2026: Live KOL Reaction
Physician posts about this trial captured live during the IASLC 2026 World Conference on Lung Cancer (Seoul, September 12–15). Quotes are verbatim; each card links to the original post. Last updated 2026-09-13.

DeLLphi-304 FAQ
What did the DeLLphi-304 extended follow-up at ESMO 2026 show?
At ESMO 2026 (abstract 3808O; data cutoff 18 February 2026; median follow-up about 23 months), median overall survival was 13.6 vs 8.4 months with tarlatamab vs chemotherapy (HR 0.62; 95% CI 0.51-0.76), 24-month overall survival was 30% vs 15%, and grade 3 or higher treatment-related adverse events occurred in 28% vs 63%. It is a later data cut of the second-line trial, distinct from DeLLphi-305 (first-line maintenance tarlatamab plus durvalumab). See At a Glance.
What is the DeLLphi-304 trial?
DeLLphi-304 (NCT05740566) is a Phase 3 randomized trial comparing tarlatamab (Imdelltra), a DLL3-targeting bispecific T-cell engager, with standard chemotherapy in relapsed small cell lung cancer after platinum-based therapy. Overall survival was the primary endpoint. See Trial Design.
What overall survival benefit did DeLLphi-304 show?
Tarlatamab produced a statistically significant overall-survival benefit versus chemotherapy (HR 0.60), and also improved progression-free survival and objective response. Medians, confidence intervals and sources are in At a Glance.
What did the ASCO 2026 CNS analysis of DeLLphi-304 find?
The post hoc analysis (Abstract 8006) showed tarlatamab delayed intracranial progression versus chemotherapy, with a larger benefit in patients with baseline brain metastases. Figures are in At a Glance.
Is tarlatamab FDA approved for small cell lung cancer?
Yes. Tarlatamab (Imdelltra) received accelerated approval in May 2024 for extensive-stage SCLC that progressed on or after platinum-based chemotherapy; on November 19, 2025 the FDA converted it to traditional approval based on DeLLphi-304. See At a Glance.
What is the safety profile of tarlatamab in DeLLphi-304?
Tarlatamab caused fewer severe adverse events than chemotherapy. Cytokine release syndrome, mostly Grade 1-2 and concentrated around step-up dosing, and ICANS are its characteristic toxicities and require monitoring during initiation. Rates are in At a Glance.