MajesTEC-9 (NCT05572515) is a Phase 3, randomized, open-label trial testing teclistamab (Tecvayli) monotherapy against investigator's choice of pomalidomide/bortezomib/dexamethasone (PVd) or carfilzomib/dexamethasone (Kd) in patients with relapsed/refractory multiple myeloma who received 1-3 prior lines of therapy, including an anti-CD38 monoclonal antibody and lenalidomide (614 participants, 24 countries). Published in the New England Journal of Medicine (2026), the trial showed significantly improved progression-free and overall survival with teclistamab monotherapy. This earlier-line, single-agent use of teclistamab is investigational. Sponsor: Janssen Research & Development, LLC (Johnson & Johnson), per the CT.gov record (NCT05572515).
Discover KOL Sentiment on MajesTEC-9 →Design — Phase 3, randomized, open-label; teclistamab (Tecvayli) monotherapy vs investigator's choice PVd or Kd in relapsed/refractory multiple myeloma, 1-3 prior lines including anti-CD38 mAb + lenalidomide (614 participants, 24 countries; NCT05572515). Sponsor: Janssen Research & Development, LLC. (NEJM 2026)
PFS (primary) — 18-month PFS 69.8% vs 26.9% with teclistamab vs PVd/Kd (HR 0.29), per physician-reported data from the NEJM readout. Median PFS not reached vs ~8 months.
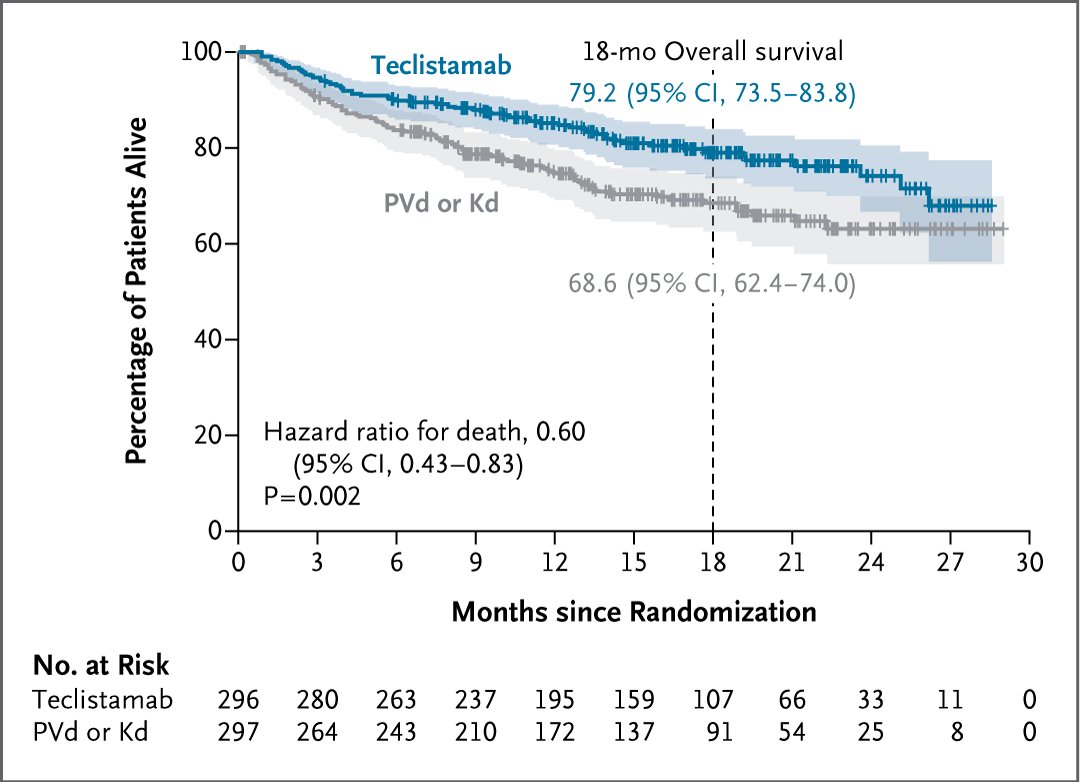
OS — 18-month OS 79% vs 69% (HR 0.60) favoring teclistamab monotherapy.
Depth of response — ≥CR 65.9% vs 16.8%; MRD-negative CR (ITT) 38.5% vs 6.7% with teclistamab vs PVd/Kd.
Safety — Grade 3/4 AEs 84.9% vs 76.3%; Grade 3/4 infection 41.6% vs 29.0% (fatal infection 5.5% vs 2.8%); CRS 66% (mostly Grade 1-2, all resolved). Physicians emphasize infection prophylaxis (IVIG) given the higher infection signal.
Regulatory / Sponsor — INVESTIGATIONAL for this earlier-line, monotherapy indication — Tecvayli is FDA approved as monotherapy after ≥4 prior lines, and with daratumumab after 1+ prior line (March 2026, MajesTEC-3). Janssen Research & Development, LLC (Johnson & Johnson). (CT.gov, FDA label)
Compiled and reviewed by the KOL Pulse research team, led by Brian Shields, Founder, KOL Pulse. Last updated September 27, 2026.


Top tweets by impressions — click to view on X
Just out: Majestic Majestec-9 results. #ASCO26 @NEJM Single agent teclistamab beats standard triplet in relapsed myeloma. https://t.co/2TeFjBuZSv @DrOlaLandgren @thanosdimop https://t.co/YzL3USaptY
Day 1 #ASCO26 highlights: 1. #CROWN (update): ALK+ NSCLC 2. #OptiTROPLung05: SacTMT/IO NSCLC 3. #WuKONG28: EGFR 20 NSCLC 4. #EV302 (update): EV-Pembro mUC 5. #MajesTEC9: Teclistamab in RRMM 6. #SUCCESSOR2: Me

Original Article: Teclistamab in Multiple Myeloma with One to Three Previous Lines of Therapy (phase 3 MajesTEC-9 trial) https://t.co/pNQbui4Dfk Editorial: Redefining Early Relapse in Multiple Myeloma — Time to Change
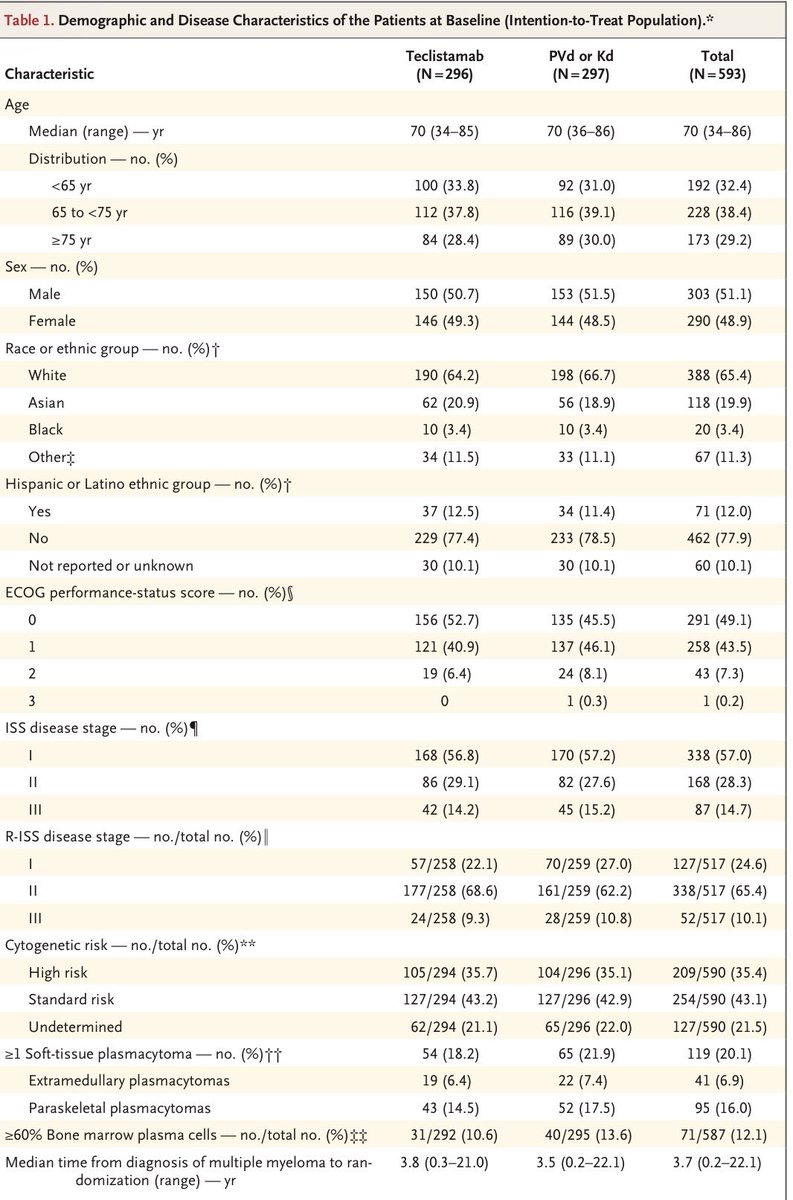
#mmsm #ASCO26 MajesTEC-9 ➡️Tec vs. PVd/Kd (1-3 prior lines of therapy) ➡️Len refractory: 80%; anti-CD38 refractory: 85% ➡️median F/U ~1.5 yrs ➡️18-mo PFS rate: 70% vs 27% ➡️improved OS with Tec vs PVd/Kd (HR: 0.60), eve
1. MajesTEC-9 [Tec vs PVd/Kd]: Single-agent Tec decimated PVd/Kd in a population that was 80% anti-CD38-refrcatory and 85% Len-refractory, with a PFS HR of 0.29 and OS HR of 0.6. While the trial should have ideally all

MAJESTEC-9 trial at #ASCO26 : the message was strikingly simple: a couple of curves summarized it all. At the end, curves speak louder than words. @TheIACH @COMyCongress https://t.co/qRLn964Rsu
MajesTec - 9 & MajecTec - 3 & Cartitude - 4 - My interpretations. IMO: the real question is no longer Tec vs CAR-T. The real question is: which patient should receive which immunotherapy, and when? MajesTEC-9
Concomitant publication in @NEJM #ASCO26 BCMA bispecific moves earlier in myeloma. MajesTEC-9 | NEJM 2026 Teclistamab monotherapy vs PVd/Kd in RRMM after 1-3 prior lines, all exposed to anti-CD38 + lenalidomide. 🧬 18

1) MajesTEC-9 (Mina, 7507) - Teclistamab vs. (VPd or Kd). Full summary below. Tec clearly beats out some inferior and less-than-standard comparators. I want to make 4 points about this study 1 - VPd and Kd are not stro

1/ 🧵 A Dominant Victory for BCMA: Teclistamab Scores Big in MajesTEC-9 from #ASCO26 Teclistamab moves earlier in RRMM! MajesTEC-9 evaluated teclistamab monotherapy vs PVd/Kd in patients with MM after 1–3 prior lines,
MajesTEC-9 tests whether single-agent teclistamab can outperform standard-of-care triplets (PVd or Kd) at first-to-third relapse in patients already exposed to anti-CD38 therapy and lenalidomide. Published in NEJM (2026) with a significant PFS and OS benefit, it is one of two Phase 3 teclistamab readouts this cycle alongside MajesTEC-3 (teclistamab + daratumumab, FDA approved March 2026).
Teclistamab monotherapy significantly improved PFS versus investigator's choice PVd or Kd. 18-month PFS was 69.8% with teclistamab vs 26.9% with PVd/Kd (HR 0.29), per physician-reported NEJM data. Median PFS was not reached in the teclistamab arm vs approximately 8 months in the control arm.
18-month OS was 79% with teclistamab vs 69% with PVd/Kd (HR 0.60), reflecting improved survival despite substantial prior anti-CD38 and lenalidomide exposure in this population (about 85% anti-CD38-refractory).
≥CR was 65.9% with teclistamab vs 16.8% with PVd/Kd. MRD-negative CR in the intent-to-treat population was 38.5% vs 6.7%, suggesting deeper responses may underlie the survival benefit.
Grade 3/4 AEs occurred in 84.9% of teclistamab-treated patients vs 76.3% with PVd/Kd. Grade 3/4 infections were more common with teclistamab (41.6% vs 29.0%), including fatal infections (5.5% vs 2.8%). CRS occurred in 66% (mostly Grade 1-2, all resolved); ICANS in 4% (mostly Grade 1-2). Physicians emphasize IVIG and infection prophylaxis as important given this signal.
⚠ Phase 3, NEJM-published — practice-informing but investigational for this indication. MajesTEC-9 supports teclistamab as an effective earlier-line option for anti-CD38/lenalidomide-exposed patients, but open questions remain per KOL commentary: teclistamab vs CAR-T at first relapse, optimal duration of therapy, and whether the PVd/Kd control arm reflects the strongest modern comparator. Regulatory review for this specific monotherapy earlier-line indication is pending.
MajesTEC-9 (NCT05572515) is a Phase 3, randomized, open-label trial evaluating teclistamab (Tecvayli) monotherapy against investigator's choice of PVd (pomalidomide, bortezomib, dexamethasone) or Kd (carfilzomib, dexamethasone) in patients with relapsed or refractory multiple myeloma who received 1-3 prior lines of therapy, including an anti-CD38 monoclonal antibody and lenalidomide. It is sponsored by Janssen Research & Development, LLC.
Published in the New England Journal of Medicine (2026), MajesTEC-9 showed teclistamab monotherapy significantly improved 18-month PFS (69.8% vs 26.9%, HR 0.29) and 18-month OS (79% vs 69%, HR 0.60) versus PVd/Kd. Deep responses were more common with teclistamab, including MRD-negative CR in the ITT population (38.5% vs 6.7%).
Not yet specifically for this indication. Tecvayli is FDA approved as monotherapy for relapsed/refractory multiple myeloma after at least 4 prior lines, and in combination with daratumumab after at least 1 prior line (approved March 2026, based on the MajesTEC-3 trial). Its use as single-agent therapy at first-to-third relapse, as studied in MajesTEC-9, is investigational.
Grade 3/4 adverse events occurred in 84.9% of teclistamab-treated patients vs 76.3% with PVd/Kd, driven mainly by higher infection rates (Grade 3/4 infection 41.6% vs 29.0%; fatal infections 5.5% vs 2.8%). CRS occurred in 66% of teclistamab patients, nearly all Grade 1-2 and resolved. Physicians on X have emphasized infection prophylaxis (IVIG) as important given this signal.
Both are Phase 3 teclistamab trials at earlier relapse, but they test different regimens in different populations. MajesTEC-3 tests teclistamab plus daratumumab in patients not necessarily refractory to anti-CD38 therapy. MajesTEC-9 tests teclistamab as a single agent in patients already exposed and largely refractory (about 85%) to an anti-CD38 antibody and lenalidomide — a more treatment-experienced population, per physician commentary on X.