Physician reactions to the LBA50 results
Full, verbatim posts from physicians on X during ESMO 2026 week (October 22–24, 2026), newest first and linked to the originals. Most cite the PFS gain; several point to hematologic toxicity, immature OS, the China-only population, and where iza-bren would sit next to other ADCs.

#PANKUBreast01 Ph III results for iza bren (bispecific EGFR/HER3 ADC) vs TPC chemo, in previously treated HR +/HER- MBC 🔹mPFS: 4.0 vs. 8.1 mo, HR 0.41 🔹 ORR: 20% vs 40% 🔹 DoR: 4.2 vs. 6.9 mo 🔹 ILD: only 1.1% & all grade 1/2 #ESMO26 #ESMOAmbassadors https://t.co/ikHLXiLHX1

🚨 PANKU-Breast01 | ESMO 2026 | LBA50 TWO TARGETS. DOUBLE THE PFS. BUT WHAT ABOUT SURVIVAL? Phase III trial of izalontamab brengitecan (iza-bren), a bispecific EGFR/HER3 ADC, in previously treated HR+/HER2− advanced breast cancer. 🔹 N = 383 | Iza-bren vs physician's choice chemotherapy 🔹 Median PFS: 8.18 vs 4.01 months 🔹 HR 0.41 — 59% lower hazard of progression or death 🔹 ORR: 40.5% vs 20.2% 🔹 ILD: 1.1%, all grade 1–2 ⚠️ OS immature. Optimal ADC sequencing remains unresolved. TAKE-HOME Dual EGFR/HER3 targeting nearly doubles median PFS, but an overall survival advantage remains unproven. 📖 Ref: Lan B et al. PANKU-Breast01. ESMO 2026; LBA50. @myESMO @OncoAlert #MVOnco #ESMO2026 #BreastCancer #ADC

#ESMO26 | PANKU-Breast01 In HR+/HER2− mBC, after CDK4/6i and 1–2 prior chemotherapy lines: Iza-bren vs chemotherapy: PFS: 8.2 vs 4.0 months (HR 0.41); ORR: 40.5% vs 20.2% https://t.co/izrdBxO77a https://t.co/iDkohswiRI

Iza-bren shows significant mPFS of 8.2 mos vs 4.0 mos , HR=0.41 #ESMO26 @OncoAlert https://t.co/Dk2JusQLRi

🇨🇳 PANKU-Breast01: the HER3-EGFR bispecific TOPO1 ADC Iza-Bren improved PFS vs chemo in HR+/HER2- MBC (OS immature). High rate of hematologic toxicity, with ~50% G3+ anemia, neutropenia and thrombocytopenia, and most patients requiring dose reductions⚠️. #ESMO26 #ESMOAmbassadors https://t.co/f1zn2X0bpe

PANKU-Breast01 #ESMO26 Iza-bren (EGFRxHER3-ADC) significantly improved PFS vs chemotherapy in pretreated HR+/HER2− advanced breast cancer (8.2 vs 4.0 months; HR 0.41). ORR doubled (40.5% vs 20.2%), with manageable safety (ILD 1.1%). OS remains immature. https://t.co/EfZyLTGV02

PANKU-Breast01 HR+ MBC, prior cdk 4/6i, 1-2 prior chemo Iza-bren vs TPC ~70% 1 prior chemo PFS 8.2 vs 4.0 mo, HR 0.41 p<0.0001 ORR 40.5% vs 20.2% DOR 6.9 mo vs 4.2 mo OS immature Most tox: heme tox, primary GCSF was not required @OncoAlert #ESMO26 https://t.co/zdUlK7U21Q

Oral abstract #BreastCancer session at #ESMO26: results from PANKUbreast01 published in @TheLancet shoring efficacy of bispecific ADC #IzaBren in pretreated patients with HR+/HER2- advanced disease @OncoAlert @myESMO https://t.co/QJy9STIjLz

PANKU-Breast01 🇨🇳: dual EGFR and HER3 ADC Iza-Bren vs TPC in HR+/HER2- pre-treated MBC: 🔹 Median PFS improvement with Iza-bren: 8.2 vs 4 months (HR 0.41) 🔹 OS immature 🔸 More grade 3 AEs with Iza-bren #ESMO26 #ESMOAmbassadors @myESMO @PTarantinoMD @E_de_Azambuja https://t.co/ORpXqVnLMk

#ESMO2026 Panku-breast01 Izabren sig. improves PFS in met HR+HER2 post CDK4i #BreastCancer 👏New targets 🎈impressive ORR too ➡️broadly comparable to DB04 - here all HER2 But 🎈haem tox Still have the what next issue 🤷🏻♀️ Online publication in @TheLancetOncol #ESMOAmbassadors #bcsm @OncoAlert @myESMO

At #ESMO26 proffered paper session 1️⃣ on #breastcancer Iza-bren ⬆️ PFS vs TPC in pretreated HR+ HER2-neg mBC Simultaneous publication in @TheLancetOncol @OncoAlert https://t.co/2dTssDG8tq

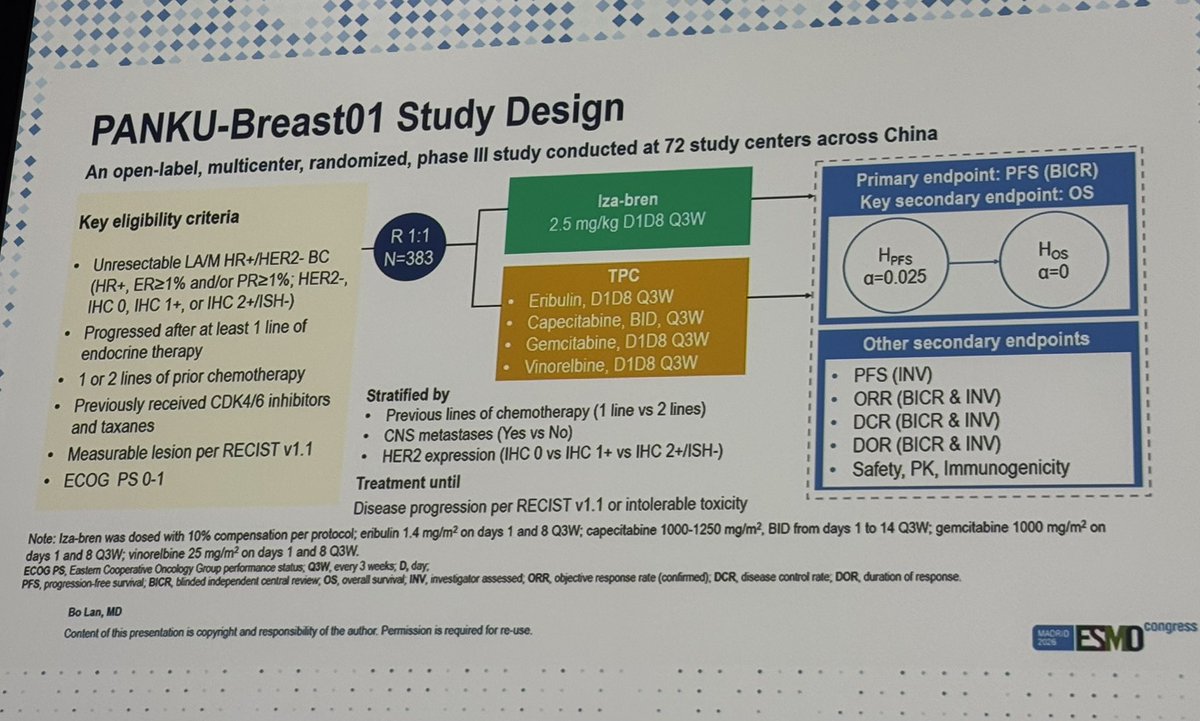
📌 Proffered paper 1: Breast cancer, early and advanced stage ✨PANKU-Breast01: Randomized Phase III Study of Izalontamab Brengitecan in Previously Treated Unresectable Locally Advanced or Metastatic HR+/HER2- Breast Cancer Presented by ✨ Bo Lan 👉🏻In this pre-specified analysis, iza-bren demonstrated a statistically significant and clinically meaningful improvement in PFS vs TPC in previously treated HR+/HER2-BC, meeting the primary endpoint. 👉🏻Iza-bren demonstrated an improved confirmed ORR and more durable response than TPC. #ESMO26 🇪🇸 @OncoAlert #OncoAlertAF

PANKU-Breast01 presented at #ESMO26 Iza-bren vs CT in HR+/HER2- after ET and 1 or 2 lines of CT ✅️ significantly improved PFS Mostly hematologic toxicity, 1% ILD events @OncoAlert https://t.co/Xwo7yVmiTM

PANKU-Breast01 | #ESMO26 Iza-bren significantly improved PFS in pretreated HR+/HER2− advanced #BreastCancer vs physician’s choice chemotherapy (8.2 vs 4.0 months; HR 0.41). @OncoAlert #bcsm https://t.co/FS1TSa1cLo

Iza-bren improves PFS compared to standard chemo in pts with HR+ HER2 neg MBC after 1-2 lines of CT for metastatic disease #ESMO26 #ESMOAmbassadors #ESMOcommunity @myESMO https://t.co/h8TrfHlQel

PANKU-Breast01 at #ESMO26: izalontamab brengitecan, an EGFR×HER3 bispecific ADC, doubled PFS vs physician's-choice chemo in pretreated HR+/HER2- MBC (8.2 vs 4.0 mo, HR 0.41). A new target pairing after CDK4/6 - promising, though a Chinese-only population. #ESMOAmbassadors @myESMO https://t.co/s4PYcCD56O
𝕏#ESMO26 | PANKU-Breast01 In HR+/HER2− mBC, the EGFR/HER3 bispecific ADC (iza-bren): PFS: 8.18 vs 4.05 months (HR 0.41). Grade ≥3 TRAEs: 40.5% vs 20.2%. OS remains immature. An impressive PFS benefit. However, in an era when ADCs such as T-DXd and SG are already in use, superiority over chemotherapy alone is not enough. Another treatment option… The added value of bispecific targeting, particularly its efficacy after other TOP1-ADCs, remains uncertain. These are the key data needed to define its place in treatment sequencing.
𝕏I’ve added the PANKU-Breast01 results to Dr. Barbara Pistilli’s excellent original slide👇 https://t.co/9DABg8HFkl https://t.co/iBIMpJWeSe
 𝕏
🚨 #ESMO26 | PANKU-Breast01 🇨🇳 Izalontamab brengitecan (iza-bren), an EGFR×HER3 bispecific ADC, significantly improved PFS 🆚 physician’s choice chemotherapy in HR+/HER2− advanced #BreastCancer after endocrine therapy, CDK4/6i and 1–2 chemotherapy lines. 🔹 mPFS: 8.2 🆚 4.0 months (HR 0.41) 🔹 Confirmed ORR: 40.5% 🆚 20.2% 🔹 OS remains immature ⚠️ Grade ≥3 TRAEs: 85% 🆚 66%, predominantly haematological. 🎯 Promising efficacy in a heavily pretreated population; toxicity and validation beyond China remain key considerations. 📖 Simultaneously published in @TheLancet : https://t.co/2ccmyPJSO4 @OncoAlert @myESMO
 𝕏
#PANKUBreast01: iza-bren, an EGFR x HER3 bispecific ADC with a TOPO1 payload, vs chemo in HR+/HER2- MBC n=383. PFS 8.2 vs 4.0 mo, HR 0.41. ORR 40.5% vs 20.2%. A real result, and it enrolled HER2 0, 1+ and 2+, so no HER2 test gates it. In clinic it lands in a space already holding T-DXd, Dato-DXd and sacituzumab. All TOPO1. Iza-bren is a new target, not a new mechanism. The number I want is how many patients had a prior ADC, and how they did. #bcsm #ESMO26 @myESMO
 𝕏
#ESMO26 | Impressive results with a next-generation bispecific ADC! Phase III PANKU-Breast01: EGFR×HER3-targeting iza-bren improved median PFS in HR+/HER2− metastatic breast cancer (8.2 vs 4.0 months; HR 0.41). However, grade ≥3 treatment-related AEs reached 85.3%. Key questions: Do ESR1, PIK3CA, or PTEN alterations influence response? What is the impact of prior ADC exposure? #ESMO26 #BreastCancer #ADC @myESMO @oncodaily @OncoAlert
 𝕏
#ESMO26 | PANKU-Breast01 Phase III: iza-bren, an EGFR×HER3 bispecific ADC, vs chemotherapy in previously treated HR+/HER2− advanced BC (N=383). ▪️ mPFS: 8.2 vs 4.0 months HR 0.41 (95% CI 0.33–0.53); P<0.0001 ▪️ ORR: 40.5% vs 20.2% ▪️ OS immature ▪️ Grade ≥3 TRAEs predominantly hematologic; ILD 1.1% (grade 1–2) Promising efficacy. Key question: where will it fit in ADC sequencing? 🔹 𝗕𝗠𝗦’𝘀 𝗼𝗻𝗴𝗼𝗶𝗻𝗴 𝗜𝗭𝗔𝗕𝗥𝗜𝗚𝗛𝗧-𝗕𝗿𝗲𝗮𝘀𝘁𝟬𝟭 𝘪𝘻𝘢-𝘣𝘳𝘦𝘯 𝘪𝘯 𝘢 𝘥𝘪𝘧𝘧𝘦𝘳𝘦𝘯𝘵 𝘱𝘰𝘱𝘶𝘭𝘢𝘵𝘪𝘰𝘯: 1𝘓 𝘢𝘥𝘷𝘢𝘯𝘤𝘦𝘥 𝘛𝘕𝘉𝘊 𝘰𝘳 𝘌𝘙-𝘭𝘰𝘸/𝘏𝘌𝘙2− 𝘉𝘊 𝘪𝘯𝘦𝘭𝘪𝘨𝘪𝘣𝘭𝘦 𝘧𝘰𝘳 𝘢𝘯𝘵𝘪–𝘗𝘋-(𝘓)1 𝘵𝘩𝘦𝘳𝘢𝘱𝘺. #Breastcancer #ADCs #PANKUBreast01

🚨 ESMO 2026 | PANKU-Breast01 (LBA50) #esmo26 Impressive phase III results for izalontamab brengitecan (iza-bren), a bispecific EGFR/HER3 ADC, in previously treated MBC HR +ve Her2 -ve Iza-bren vs physician's choice chemotherapy: 🔹 Median PFS: 8.18 vs 4.01 months 🔹 HR 0.41 (95% CI 0.33–0.53; p<0.0001) 🔹 ORR: 40.5% vs 20.2% 🔹 Median DoR: 6.93 vs 4.21 months 🔹 ILD: 1.1% (all grade 1–2) 🔹 OS: Immature A remarkable 59% reduction in the hazard of progression or death, with manageable toxicity. Another ADC enters the increasingly crowded HR+/HER2− breast cancer landscape. @OncBrothers @myESMO @OncoAlert
Physician sentiment
PANKU-Breast01 Key Slides
ESMO 2026 slides
Presented by Bo Lan, MD (LBA50, Proffered Paper Session, Oct 23, 2026), as photographed and shared by physicians. Each slide appears once, from the physician post with the widest reach. Click any image to enlarge; full transcriptions are under “View OCR Text”.





| Arm | N | Events | Median PFS, mo (95% CI) | 6 mo | 9 mo | 12 mo |
|---|---|---|---|---|---|---|
| Iza-bren | 190 | 130 | 8.2 (6.9–8.6) | 62.8% | 41.8% | 26.5% |
| TPC | 193 | 159 | 4.0 (2.9–4.3) | 24.2% | 14.4% | 9.2% |
| HR 0.41 (95% CI 0.33–0.53), stratified Cox model; P<0.0001, one-sided stratified log-rank test. Subjects at risk at 0/3/6/9/12/15/18/21/24 mo: 190/138/97/63/38/22/12/4/0 vs 193/96/34/17/10/4/2/1/0. | ||||||
Source: ESMO 2026 LBA50 slide (Bo Lan), as shared on X by Erika Hamilton, Oct 23, 2026. Landmark rates are the values printed on the curve. Iza-bren is investigational and not FDA approved.









More ESMO 2026 slides from physicians


PANKU-Breast01 Key Takeaways
ESMO 2026 results — LBA50 (October 23, 2026)
Bo Lan presented LBA50 in the Proffered Paper session (breast cancer) on Friday, October 23, 2026, 14:35–14:45, at ESMO 2026 in Madrid. The results were published the same day in The Lancet. The trial ran at 72 centers in China.
Results, from the abstract (ESMO 2026 LBA50 abstract, data cutoff 21 Jul 2026):
- Patients: 383 randomized and treated (iza-bren 190, chemotherapy 193). Median PFS follow-up 15.24 vs 13.63 months.
- PFS by BICR (primary endpoint): median 8.18 months (95% CI 6.93–8.58) vs 4.01 months (95% CI 2.92–4.30); HR 0.41 (95% CI 0.33–0.53); P<0.0001.
- Response: confirmed ORR by BICR 40.5% vs 20.2%; median duration of response 6.93 vs 4.21 months.
- Overall survival: immature at this interim analysis; the abstract reports no detrimental effect.
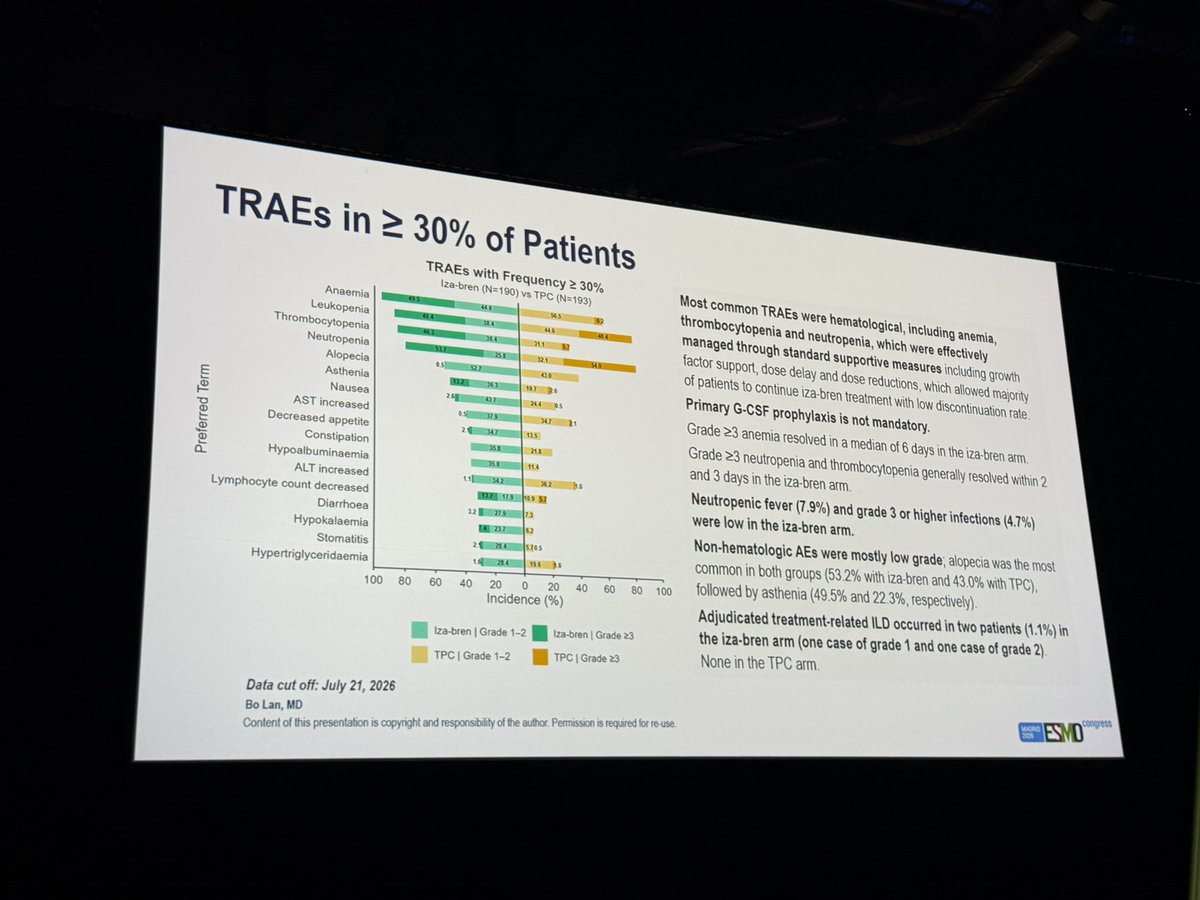
- Safety: grade ≥3 TRAEs were predominantly hematologic; 1.6% of patients discontinued iza-bren because of TRAEs; adjudicated ILD in 2 patients (1.1%) on iza-bren, grade 1 or 2. The abstract does not report the overall grade ≥3 TRAE rate.
Safety, from the presentation slides (ESMO 2026 LBA50 presentation, Bo Lan, data cutoff 21 Jul 2026; slide photos posted on X by @PTarantinoMD), iza-bren vs chemotherapy:
- Grade ≥3 TRAEs 85.3% vs 65.8%; treatment-related serious AEs 41.6% vs 11.4%
- TRAEs leading to dose reduction 64.7% vs 28.5%; to dose interruption 56.3% vs 37.8%; to discontinuation 1.6% vs 1.0%
- TRAEs leading to death: 2 patients (1.1%) vs 1 patient (0.5%)
- Grade ≥3 neutropenia 53.7%, anemia 49.5%, leukopenia 48.4%, and thrombocytopenia 46.3% with iza-bren. The slide states primary G-CSF prophylaxis is not mandatory.
The presentation slide and the BMS press release round median PFS to 8.2 vs 4.0 months. Some posts on X restate figures differently; the values above are taken from the abstract text and the presentation slides as labelled. The abstract concludes that the results support iza-bren “as a new standard of care option in this population in China.”
Sources: ESMO 2026 LBA50 abstract · The Lancet publication · SystImmune / BMS press release (Oct 23, 2026) · ClinicalTrials.gov NCT06343948
Topline result — Aug 26, 2026
Iza-bren met the primary endpoint of PFS at a pre-specified interim analysis, per Biokin’s announcement. No numbers were released with the topline; the full results followed at ESMO 2026 (above).
The drug
Iza-bren (izalontamab brengitecan, BL-B01D1) is a bispecific antibody-drug conjugate targeting both EGFR and HER3. It is developed by SystImmune (a Biokin subsidiary) and, outside China, jointly with Bristol Myers Squibb under an exclusive license. The FDA has granted Breakthrough Therapy Designation in previously treated EGFR-mutated NSCLC — not in breast cancer. SystImmune / BMS press release
Regulatory
⚠ Iza-bren is investigational and not FDA approved in any indication. PANKU-Breast01 was conducted in China; applicability of its results to regulatory filings outside China has not been announced.

