LIVE #WCLC26 — live KOL coverage of the World Conference on Lung Cancer View Full Coverage →
KOL Pulse · AI-Native Trial Intelligence

DESTINY-Lung04 Trial

DESTINY-Lung04 (NCT05048797) is the global Phase 3 trial of Enhertu (trastuzumab deruxtecan, Daiichi Sankyo/AstraZeneca) as first-line treatment versus platinum–pemetrexed plus pembrolizumab in HER2-mutant (exon 19/20) unresectable, locally advanced or metastatic non-squamous NSCLC. At the WCLC 2026 presidential session (Rotow et al, PL03.08), the readout showed median PFS 14.3 vs 8.3 months (HR 0.63, P<0.0001) and ORR 70.0% vs 44.5% — the first HER2-directed medicine to beat the global first-line standard in a Phase 3 NSCLC trial. Interim OS shows no benefit to date and ILD remains the key toxicity. First-line use is investigational.

Phase 3 · NCT05048797 1L HER2m (ex19/20) nonsquamous NSCLC T-DXd vs platinum + pemetrexed + pembrolizumab WCLC 2026: PFS 14.3 vs 8.3 mo · HR 0.63 ⚠ 1L investigational · ✅ 2L+ FDA-approved (DL02)
See the KOL Reaction

DESTINY-Lung04 Key Takeaways

Design

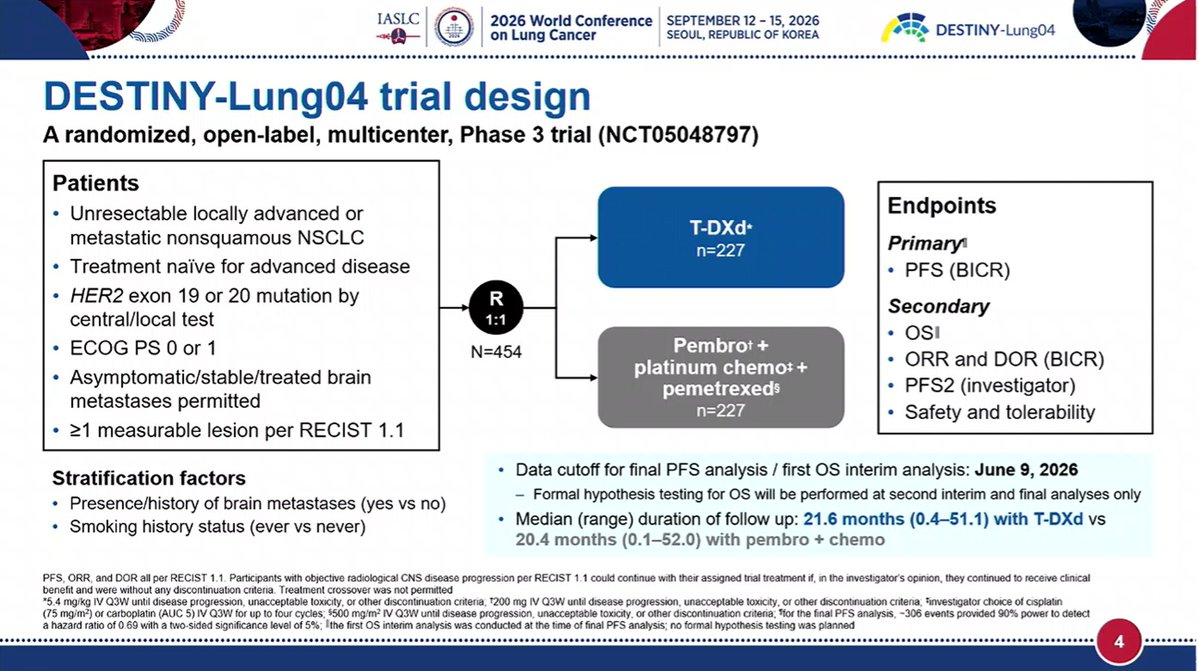
Global, randomized (1:1), open-label Phase 3: T-DXd vs platinum (cisplatin or carboplatin) + pemetrexed + pembrolizumab as first-line therapy. Setting: treatment-naive advanced disease. Actual enrollment 454 (ClinicalTrials.gov). Primary endpoint: PFS by blinded independent central review; secondary endpoints include OS, investigator PFS, ORR, DoR, PK, patient-reported tolerability, immunogenicity and safety. ClinicalTrials.gov · Daiichi Sankyo trial-initiation PR

WCLC 2026 readout — Sept 14, 2026

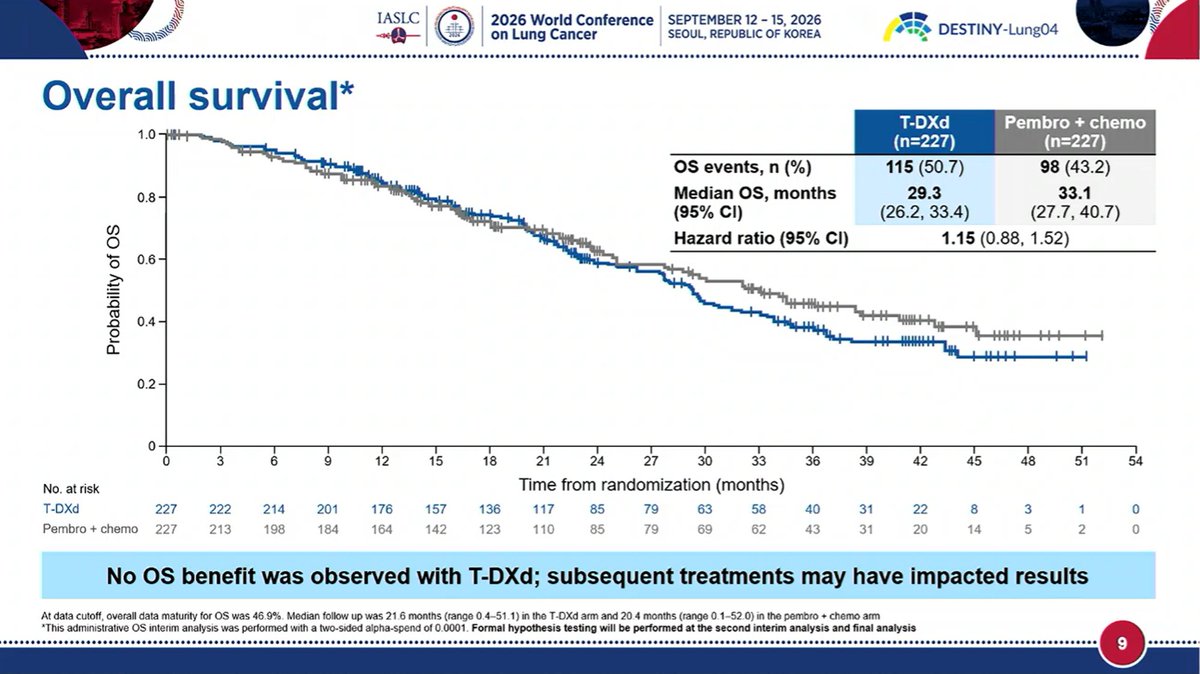
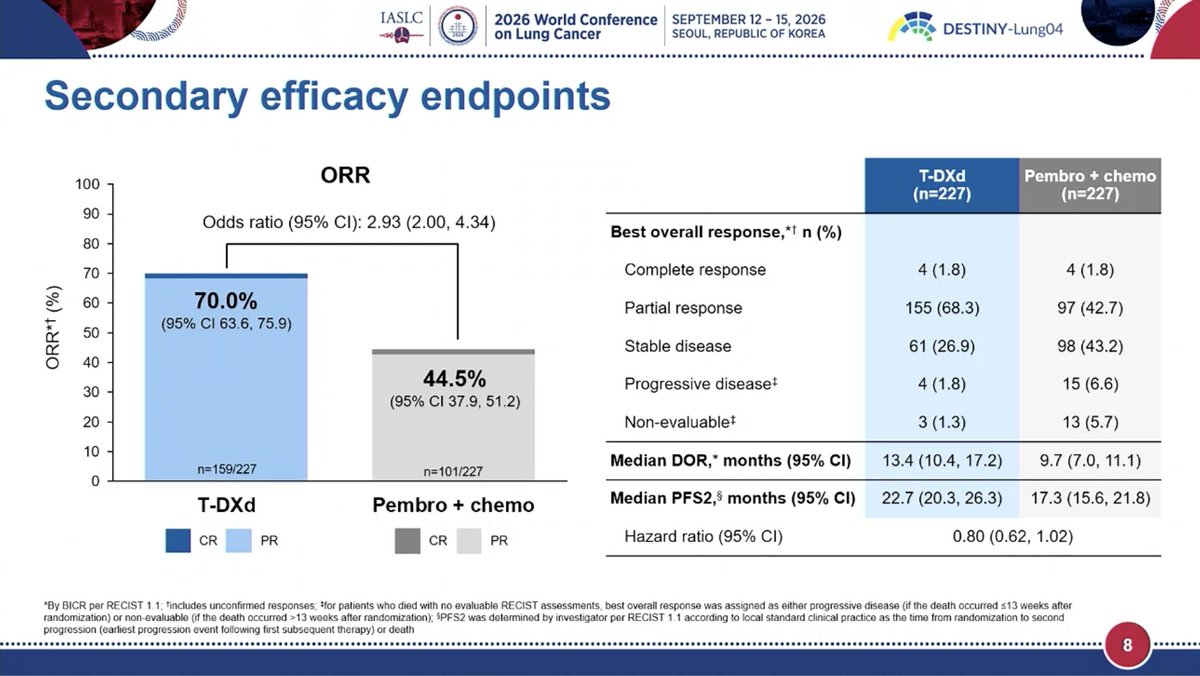
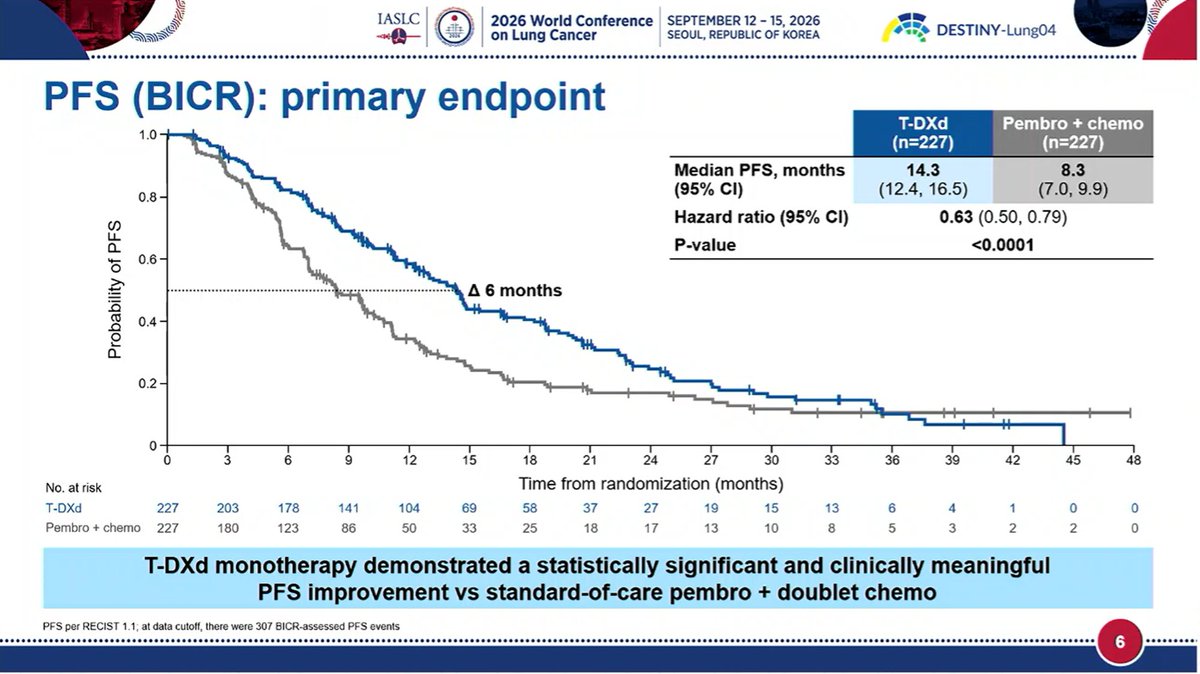
Median PFS 14.3 vs 8.3 months; HR 0.63 (95% CI 0.50–0.79; P<0.0001) for first-line T-DXd versus pembrolizumab + platinum–pemetrexed — a ~6-month improvement, maintained in patients with baseline brain metastases (~23% of enrollment; PFS HR 0.62). ORR 70.0% vs 44.5%; median DoR 13.4 vs 9.7 months; investigator-assessed PFS2 22.7 vs 17.3 months. No OS benefit at the first interim analysis (median 29.3 vs 33.1 months; HR 1.15, 95% CI 0.88–1.52; 46.9% maturity) — interpretation confounded by subsequent HER2-directed therapy in 48.0% of the control arm vs 23.3% of the T-DXd arm. Drug-related AEs led to discontinuation in 15.9% of both arms; adjudicated drug-related ILD/pneumonitis 20.8% with T-DXd (grade 5: 1.8%) — the toxicity physicians flagged most. (WCLC 2026 presidential session PL03.08, Rotow et al; DCO June 9, 2026) Slide captures: Dr. Stephen V. Liu · Dr. Hidehito Horinouchi

Biomarker

HER2 (ERBB2) exon 19 or 20 activating mutations; no other targetable oncogenic alterations permitted. Daiichi Sankyo PR

Regulatory

First-line use is investigational. ✅ Enhertu is approved (FDA accelerated approval; >80 countries/regions) for previously treated metastatic NSCLC with activating HER2 (ERBB2) mutations, based on DESTINY-Lung02 and/or DESTINY-Lung05, and separately for previously treated HER2-positive (IHC 3+) solid tumors with no satisfactory alternative options. FDA approval notifications

Free Access · KOL Pulse Intelligence

Track oncology’s top KOLs in your specialty

Create a free account, pick the tumor types you cover, and go beyond the tweet — the intelligence pharma teams use to map influence and prepare for engagement:

  • Enhanced KOL profiles
  • Pharma influence & potential advisory-board patterns
  • 2025 Open Payments financial analysis
  • Social-media sentiment & trend signals
Get free access — pick your specialty
Choose the tumor types you follow. No cost, unsubscribe anytime.

WCLC 2026: Live KOL Reaction

Physician posts about this trial captured live during the IASLC 2026 World Conference on Lung Cancer (Seoul, September 12–15). Quotes are verbatim; each card links to the original post. Last updated 2026-09-15.

Eric K. Singhi, MD
Eric K. Singhi, MD@lungoncdoc

T-DXd trying to catch up in the frontline setting with zongertinib and sevabertinib Results from #DESTINYLung04…. #WCLC26 https://t.co/wb9BkFV7dg

6.1K impressions17 likes2026-09-14
Hidehito HORINOUCHI
Hidehito HORINOUCHI@HHorinouchi

🆙#WCLC26 #LCSM Plenary Session 🔥DESTINY-Lung04: First-Line Trastuzumab Deruxtecan (T-DXd) in Patients With Metastatic HER2-Mutant NSCLC: Primary Results 🎙️ @JuliaRotow 🎯PFS HR 0.63 (95%CI 0.50-0.79) 🎯OS HR 1.15 (95%CI 0.88-0.92) 🔢PL03.08 ☑️NCT05048797 🔗 https://t.co/gAahGHJGeA @OncoAlert @Larvol @IASLC

5.2K impressions28 likes2026-09-14
Stephen V Liu, MD
Stephen V Liu, MD@StephenVLiu

Dr. @JuliaRotow at #WCLC26 with primary results from DESTINY-Lung04: first-line trastuzumab deruxtecan vs platinum + pemetrexed + pembro in advanced HER2 mutant NSCLC. Primary endpoint of PFS favors T-DXd at 14.3 vs 8.3m, HR 0.63 and RR 70% vs 44.5%, DOR 13.7 vs 9.7m, PFS2 22.7 vs 17.3m.

3.4K impressions34 likes2026-09-14
Stephen V Liu, MD
Stephen V Liu, MD@StephenVLiu

#WCLC26 In DESTINY-Lung04, no OS signal yet. Toxicities led to discontinuation in 16% of both arms. Biggest concern here is the ILD at 20.8% - while most were grade 1/2 and resolved, these are still high rates. This will impact delivery and possibly subsequent therapies... https://t.co/ZUQSd7yaFX

2.6K impressions20 likes2026-09-14
Masahiro TORASAWA, MD. PhD.
Masahiro TORASAWA, MD. PhD.@M_Torasawa

#WCLC26 | DESTINY-Lung04 🧬 Ph3: 1L T-DXd vs pembrolizumab + chemo in advanced HER2m NSCLC (n=454; ~94% HER2 exon20) 📉 PFS: 14.3 vs 8.3 mo; HR 0.63 (95% CI 0.50–0.79; p<0.0001) → ~6-month improvement 🎯 ORR: 70.0% vs 44.5% ⏳ DoR: 13.4 vs 9.7 mo 🧠 Benefit maintained in patients with brain mets: PFS HR 0.62 📊 Interim OS showed no benefit: • 29.3 vs 33.1 mo • HR 1.15 (95% CI 0.88–1.52) ⚠️ Interpretation complicated by subsequent therapy imbalance: HER2-directed therapy 48.0% vs 23.3% in the control vs T-DXd arms 🫁 Adjudicated drug-related ILD/pneumonitis: 20.8% • G≥3: 4.4% • G5: 1.8%

1.2K impressions5 likes2026-09-14
Uğur Özkerim
Uğur Özkerim@UOzkerim

DESTINY-Lung04 at #WCLC26 In 1L HER2-mutant advanced NSCLC, T-DXd significantly improved PFS vs pembrolizumab + chemotherapy: mPFS 14.3 vs 8.3 months (HR 0.63; P<0.0001) ORR: 70.0% vs 44.5% However, no OS benefit was observed at this analysis (29.3 vs 33.1 months; HR 1.15). The first Phase 3 trial showing benefit of a HER2-directed therapy vs SOC in this setting. @OncoAlert @GlopesMd @ManuelDomine @StephenVLiu @weoncologists @OpenMedKate

846 impressions8 likes2026-09-14
Laura Alder, MD
Laura Alder, MD@LauraAlderMD

Dr @JuliaRotow with terrific presentation of DESTINY-Lung04 #WCLC26. ORR 70% vs 44.5%, improved PFS. ‼️No significant OS benefit ; notably, 48% of chemo arm did receive subsequent HER2 directed treatment 🚨ILD any grade 20.8% (78.7% G 1/2) ⭐️Zongertinib my choice for 1L treatment in HER2 TKD alterations

796 impressions13 likes2026-09-14
Diego A. Díaz-García
Diego A. Díaz-García@diegoadiazg

🫁 DESTINY-Lung04: T-DXd in HER2-mutant NSCLC. @JuliaRotow First-line T-DXd significantly improved PFS vs pembro + chemo: 14.3 vs 8.3 months HR 0.63 (95% CI, 0.50-0.79; P<0.0001) ORR was 70.0% vs 44.5%, with median DoR of 13.4 vs 9.7 mo. OS did not favor T-DXd (HR 1.15), with subsequent therapy imbalances limiting interpretation. ILD/pneumonitis occurred in 20.8% with T-DXd, predominantly grade 1/2. #CánCare #oncology #thoraciconcology #lungcancer #NSCLC #HER2 #ADC #WCLC26 @IASLC

770 impressions12 likes2026-09-14
Miguel Gonzalez Velez, MD
Miguel Gonzalez Velez, MD@mgonzalezvelMD

DESTINY-Lung04. T-DXd vs pembrolizumab + chemo as 1L therapy in HER2-mutant (exon 19/20) NSCLC by @JuliaRotow #WCLC26 Take: Primary endpoint met PFS 14.3mo (T-DXd) vs 8.3mo. ORR 70% vs 44.5%; DOR 13.4 vs 9.7mo; median treatment duration 12mo vs 7mo. OS at 46.9% maturity numerically favors the control arm: 29.3mo (T-DXd) vs 33.1mo (pembro+chemo), HR 1.15 (0.88–1.52). no OS benefit, with many confounding postreatment. Great to see the comparator here is genuine current SOC not a weaker historical control, which makes the PFS win more meaningful but also makes the OS numbers harder to wave away. Again going back to the ORR/PFS/OS dilemma. #NSCLC #LCSM

737 impressions2 likes2026-09-14
Dr Riyaz Shah
Dr Riyaz Shah@DrRiyazShah

DESTINY-Lung04; front line, no protocol mandated x over; n454; 23% have brain mets; mPFS 8.3 v 14.3m HR 0.63; ORR 70%; mDOR 13.4m; no OS benefit! 48% of control arm got subsequent her2 directed therapy: 21% any grade ILD; @Bayer and @Boehringer can give a sigh of relief #WCLC26 https://t.co/LFPLj0hlsF

726 impressions11 likes2026-09-14
gilberto lopes
gilberto lopes@GlopesMd

#WCLC26 Presidential Symposium: DESTINY-Lung04 1L T-DXd vs pembrolizumab + platinum/pemetrexed in metastatic HER2-mutant NSCLC: • PFS 14.3 vs 8.3 mo • HR 0.63 (95% CI 0.50–0.79), P<0.0001 • ORR 70.0% vs 44.5% • DoR 13.4 vs 9.7 mo https://t.co/f2lIDEBgH7

638 impressions1 likes2026-09-14
MV Chandrakanth
MV Chandrakanth@ChandrakanthMv

DESTINY-Lung04 🫁 Can T-DXd move up front in HER2-mutant advanced NSCLC? T-DXd vs pembrolizumab + platinum/pemetrexed: → PFS: 14.3 vs 8.3 months → HR 0.63 → ORR: 70% vs 44.5% → DoR: 13.4 vs 9.7 months A compelling improvement in disease control. But the trade-off matters: ILD 20.8%, including 1.8% Grade 5 ILD with T-DXd. OS remains difficult to interpret at this analysis, particularly in the context of imbalanced subsequent therapies. Take-home: T-DXd emerges as an important new first-line option for advanced HER2-mutant NSCLC — with vigilant ILD recognition and monitoring essential. 📚 Reference: DESTINY-Lung04, Phase III study; WCLC 2026. #MVOnco #DESTINYLung04 #TDXd #HER2 #HER2Mutant #NSCLC #LungCancer #ThoracicOncology #WCLC2026 #Oncology

589 impressions3 likes2026-09-14
Hidehito HORINOUCHI
Hidehito HORINOUCHI@HHorinouchi

🆙#WCLC26 #LCSM Plenary Session 🔥DESTINY-Lung04: First-Line Trastuzumab Deruxtecan (T-DXd) in Patients With Metastatic HER2-Mutant NSCLC: Primary Results 🎙️ @JuliaRotow 🔢PL03.08 🎯T-DXd Showed Statistically Significant and Clinically Meaningful PFS Improvement vs SOC (Chemo+Pembrolizumab) as First-Line Therapy ☑️NCT05048797 🔗 https://t.co/gAahGHJGeA @OncoAlert @Larvol @IASLC

5.2K impressions50 likes2026-08-21
Stephen V Liu, MD
Stephen V Liu, MD@StephenVLiu

FDA grants accelerated approval to sevabertinib as first-line HER2 mutant (TKD) NSCLC. Based on SOHO-01 with RR 75% and 38% of those lasting ≥ 12m. Joins zongertinib here, with trastuzumab deruxtecan presumably joining soon based on DESTINY Lung-04. https://t.co/W90xpc8g55

2.2K impressions26 likes2026-09-09

The TKI-vs-ADC Debate: Where Does 1L T-DXd Fit?

Dr. Antonio Calles’ critical read of the readout — the most-viewed physician post on DESTINY-Lung04 of the day — drew a sequencing debate: oral HER2 TKIs first, T-DXd saved for second line? Verbatim, in conversation order. (His “truck test” meme follow-up is below.)

Dr. Antonio Calles
Dr. Antonio Calles @Tony_Calles · 2026-09-14
View on X ↗

😳 Disappointing results of T-DXd in large randomized phase III Destiny-Lung04 first line in HER2mut NSCLC vs SoC chemo-pembro. Although control arm outperformed, the lack of translation into OS benefit and the concerning safety issues of this agent warrants a lot of discussion, specially in the upcoming data from selective HER2 TKIs, with are associated with better tolerance and safety profile. #WCLC26 @iasclc #lcsm

S
Santhosh Ambika, MD @RenoHemonc · reply · 2026-09-14
View on X ↗

@Tony_Calles Keep calm and order Zong or Seva ..

G
Guilherme S. C. Correia, MD @guicorreiamd · reply · 2026-09-14
View on X ↗

@Tony_Calles @NReguart Absolutely! Hard to argue against the safety and convenience of TKIs. If data about T-DXd after HER2 TKI shows a compelling signal, it would further support saving this ADC for 2nd line.

The “Truck Test” — the OS debate, meme edition

Dr. Antonio Calles followed his critical read of the DESTINY-Lung04 survival curves by quote-tweeting himself to call for “the truck test” — and Drs. Balazs Halmos and Paolo Tarantino answered in GIFs. Embedded natively below so the GIFs play; every post is verbatim.

Dr Rishabh Jain
Dr Rishabh Jain@DrRishabhOnco

DESTINY-Lung04: impressive PFS with first-line T-DXd, but the OS curve tells a very different story. T-DXd vs pembrolizumab + platinum/pemetrexed: • mPFS: 14.3 vs 8.3 months • HR 0.63 | P<0.0001 • 37% lower risk of progression/death But OS did not favor T-DXd: • mOS: 29.3 vs 33.1 months • HR 1.15 (95% CI 0.88–1.52) • OS remains immature Clinical verdict: A clear first-line PFS win in HER2-mutant NSCLC, but the survival story remains unresolved. #WCLC26 #LungCancer @IASLC @OncoAlert

1.1K impressions4 likes2026-09-14
Tom Newsom-Davis
Tom Newsom-Davis@tnewsomdavis

DESTINY-Lung04 1L Trastuzumab Deruxtecan v PPC, HER2mut NSCLC ✅🔼mPFS 14.3 v 8.3, HR 0.63 ✅🔼ORR 70 v 44% ❌No diff OS ❗️Pneumonitis 20%, 4% Gr3+ 🤔 New 1L option, joining Zongertinib ORR + PFS similar to TKIs OS likely reflects subsequent Rx Watch 🫁! ❓sequencing #WCLC26 https://t.co/MBUSCb0CWL

898 impressions6 likes2026-09-14
Uğur Özkerim
Uğur Özkerim@UOzkerim

DESTINY-Lung04 at #WCLC26 In 1L HER2-mutant advanced NSCLC, T-DXd significantly improved PFS vs pembrolizumab + chemotherapy: mPFS 14.3 vs 8.3 months (HR 0.63; P<0.0001) ORR: 70.0% vs 44.5% However, no OS benefit was observed at this analysis (29.3 vs 33.1 months; HR 1.15). The first Phase 3 trial showing benefit of a HER2-directed therapy vs SOC in this setting.

7 impressions1 likes2026-09-14
Dr. Estela Rodriguez
Dr. Estela Rodriguez@Latinamd

#WCLC26 Presidential Symposium Day 2 🔥#DESTINY-Lung04: First-line trastuzumab deruxtecan (TDxd) vs chemo IO in #HER2-mutant metastatic NSCLC. 🎙️@JuliaRotow ▶️ Median PFS: 14.3 vs 8.3 mo ▶️ HR 0.63; P<0.0001 ▶️ ORR: 70.0% vs 44.5% ▶️ DOR: 13.7 vs 9.7 mo ⬆️ crossover ⚠️Grade ≥3 TRAEs similar 🫁Adjudicated drug-related ILD: 20.8% 👉🏽👉🏽TDxd is more active than chemoIO, competes w oral drugs in market w less chemo side effects 👉🏽👉🏽some caution about ILD but overall we have used this drug safely in 2nd line. @Exon20Group #lcsm @IASLC

349 impressions4 likes2026-09-15
Tom Newsom-Davis
Tom Newsom-Davis@tnewsomdavis

My thoughts on DESTINY-Lung04 and 1L HER2 options (from my LinkedIn, sorry so tiny!) #WCLC26 https://t.co/0t5BjaFSg9

280 impressions5 likes2026-09-15
Prof. Dr. Ahmet Dirican
Prof. Dr. Ahmet Dirican@dr_dirican

An important result from WCLC 2026 that could change clinical practice! Presented at the @IASLC #WCLC26 Presidential Symposium, the Phase III DESTINY-Lung04 trial may bring HER2-targeted therapy into the first-line setting for advanced HER2-mutant NSCLC. In patients with previously untreated, advanced non-squamous NSCLC harboring HER2 (ERBB2) exon 19/20 mutations: T-DXd (Enhertu) vs pembrolizumab + platinum/pemetrexed 🔹 Median PFS: 14.3 vs 8.3 months 🔹 HR 0.63 → 37% reduction in the risk of progression or death 🔹 ORR: 70% vs 44.5% 🔹 Median DoR: 13.4 vs 9.7 months OS data are still immature, with no survival benefit demonstrated at this time. HER2 mutation is becoming an important determinant not only for later-line therapy, but also for first-line treatment selection in NSCLC. These results once again highlight the importance of comprehensive molecular profiling/NGS at diagnosis. @IASLC @oncodaily @OncodailyLung @myESMO @OncBrothers @RManochakian @Latinamd @HosseinBorghaei #WCLC26 #PrecisionOncology #NGS

95 impressions0 likes2026-09-15
Dr Rishabh Jain
Dr Rishabh Jain@DrRishabhOnco

DESTINY-Lung04: impressive PFS with first-line T-DXd, but the OS curve tells a very different story. T-DXd vs pembrolizumab + platinum/pemetrexed: • mPFS: 14.3 vs 8.3 months • HR 0.63 | P<0.0001 • 37% lower risk of progression/death But OS did not favor T-DXd: • mOS: 29.3 vs 33.1 months • HR 1.15 (95% CI 0.88–1.52) • OS remains immature Clinical verdict: A clear first-line PFS win in HER2-mutant NSCLC, but the survival story remains unresolved. #WCLC26 #LungCancer @IASLC @OncoAlert

85 impressions0 likes2026-09-14
Dr. Estela Rodriguez
Dr. Estela Rodriguez@Latinamd

#WCLC26 Presidential Symposium Day 2 🔥#DESTINY-Lung04: First-line trastuzumab deruxtecan (TDxd) vs chemo IO in #HER2-mutant metastatic NSCLC. 🎙️@JuliaRotow ▶️ Median PFS: 14.3 vs 8.3 mo ▶️ HR 0.63; P<0.0001 ▶️ ORR: 70.0% vs 44.5% ▶️ DOR: 13.7 vs 9.7 mo ⚠️Grade ≥3 TRAEs similar 🫁Adjudicated drug-related ILD: 20.8% 👉🏽👉🏽TDxd is more active than chemoIO, competes w oral drugs in market w less chemo side effects 👉🏽👉🏽some caution about ILD but overall we have used this drug safely in 2nd line. @Exon20Group #lcsm @IASLC

21 impressions0 likes2026-09-15

Top KOLs Discussing DESTINY-Lung04

Julia Rotow MD
Julia Rotow MD
Presenter · WCLC 2026 PL03.08
Chul Kim
Chul Kim
2.2K impressions
Dr. Antonio Calles 🫁🚭
Dr. Antonio Calles
2.1K impressions
Toni Choueiri, MD
Toni Choueiri, MD
1.9K impressions
Yakup Ergün
Yakup Erg n
1.7K impressions
Jackie Aredo
Jackie Aredo
741 impressions
Hidehito HORINOUCHI
Hidehito HORINOUCHI
671 impressions
David Gandara
David Gandara
463 impressions
Giannis Mountzios
Giannis Mountzios
151 impressions
Enes Erul MD
Enes Erul MD
82 impressions

DESTINY-Lung04 Key Slides & Visuals
WCLC 2026 presidential-session slide captures (Sept 14, 2026) lead, followed by topline-day captures and the IASLC 2026 Targeted Therapies cross-agent comparison that frames the HER2-mutant NSCLC race. Full text via the OCR toggle on each card. Comparison-table values are from the published prior-line datasets cited on the slide.

Hidehito HORINOUCHI @HHorinouchi · 2026-09-14
WCLC 2026 primary results: design, PFS, OS, subsequent therapies
WCLC 2026 · Sep 14, 2026 · Presidential session PL03.08
View Post
DESTINY-Lung04 WCLC 2026 slide - trial design: randomized open-label Phase 3, N=454, T-DXd vs pembrolizumab + platinum + pemetrexedDESTINY-Lung04 WCLC 2026 slide - PFS (BICR) primary endpoint: median 14.3 vs 8.3 months, HR 0.63, P<0.0001DESTINY-Lung04 WCLC 2026 slide - overall survival first interim: median 29.3 vs 33.1 months, HR 1.15, no OS benefitDESTINY-Lung04 WCLC 2026 slide - imbalance in subsequent therapies: HER2-directed 48.0% control vs 23.3% T-DXd arm
[Slide 1] DESTINY-Lung04 trial design - A randomized, open-label, multicenter, Phase 3 trial (NCT05048797). Patients: Unresectable locally advanced or metastatic nonsquamous NSCLC; treatment naive for advanced disease; HER2 exon 19 or 20 mutation by central/local test; ECOG PS 0 or 1; asymptomatic/stable/treated brain metastases permitted; >=1 measurable lesion per RECIST 1.1. Stratification factors: presence/history of brain metastases (yes vs no); smoking history status (ever vs never). Randomized 1:1 (N=454) -> T-DXd (5.4 mg/kg IV Q3W) n=227 | Pembro + platinum chemo (investigator choice cisplatin or carboplatin) + pemetrexed, n=227. Endpoints - Primary: PFS (BICR). Secondary: OS, ORR and DOR (BICR), PFS2 (investigator), safety and tolerability. Data cutoff for final PFS analysis / first OS interim analysis: June 9, 2026; formal hypothesis testing for OS will be performed at second interim and final analyses only. Median (range) duration of follow-up: 21.6 months (0.4-51.1) with T-DXd vs 20.4 months (0.1-52.0) with pembro + chemo. Treatment crossover was not permitted. [Slide 2] PFS (BICR): primary endpoint - Kaplan-Meier curves, T-DXd (n=227) vs pembro + chemo (n=227). Median PFS 14.3 months (95% CI 12.4-16.5) vs 8.3 months (95% CI 7.0-9.9); hazard ratio 0.63 (95% CI 0.50-0.79); P-value <0.0001; delta 6 months at the median. T-DXd monotherapy demonstrated a statistically significant and clinically meaningful PFS improvement vs standard-of-care pembro + doublet chemo. PFS per RECIST 1.1; at data cutoff there were 307 BICR-assessed PFS events. [Slide 3] Overall survival (first OS interim analysis) - OS events: T-DXd 115 (50.7%) vs pembro + chemo 98 (43.2%). Median OS 29.3 months (95% CI 26.2-33.4) vs 33.1 months (95% CI 27.7-40.7); hazard ratio 1.15 (95% CI 0.88-1.52). No OS benefit was observed with T-DXd; subsequent treatments may have impacted results. At data cutoff, overall data maturity for OS was 46.9%. Median follow-up was 21.6 months (range 0.4-51.1) in the T-DXd arm and 20.4 months (0.1-52.0) in the pembro + chemo arm. This administrative OS interim analysis was performed with a two-sided alpha-spend of 0.0001; formal hypothesis testing will be performed at the second interim analysis and final analysis. [Slide 4] Imbalance in subsequent therapies - T-DXd arm (n=227): had subsequent treatment 71.5% (n=133/186). Subsequent treatments, any line, proportion of patients randomized: HER2 directed 23.3% (HER2 ADC 5.3%, HER2 TKI 18.1%); IO based 28.6%; IO + chemo 23.8%. Pembro + chemo arm (n=227): had subsequent treatment 72.4% (n=152/210). HER2 directed 48.0% (HER2 ADC 33.0%, HER2 TKI 27.8%); IO based 5.3%; IO + chemo 4.0%. More patients in the pembro + chemo arm subsequently received HER2-directed therapies: 48.0% vs 23.3%. Use of subsequent IO + chemo combination therapies in the T-DXd arm was limited (23.8%). Imbalance in subsequent HER2-directed / IO + chemo therapies may have confounded interpretation of OS.
Stephen V Liu, MD @StephenVLiu · 2026-09-14
Primary results: PFS, ORR, DoR and PFS2 (Dr. Julia Rotow presenting)
WCLC 2026 · Sep 14, 2026 · Presidential session PL03.08
View Post
Dr. Julia Rotow presenting DESTINY-Lung04 primary results at the WCLC 2026 Presidential Symposium podium in SeoulDESTINY-Lung04 WCLC 2026 slide - trial design: randomized open-label Phase 3, N=454, primary endpoint PFS by BICRDESTINY-Lung04 WCLC 2026 slide - PFS (BICR) primary endpoint: median 14.3 vs 8.3 months, HR 0.63, P<0.0001DESTINY-Lung04 WCLC 2026 slide - secondary efficacy endpoints: ORR 70.0% vs 44.5%, median DOR 13.4 vs 9.7 months, PFS2 22.7 vs 17.3 months
[Slide 1] Photo: Dr. Julia Rotow (Dana-Farber Cancer Institute) presenting the DESTINY-Lung04 primary results at the WCLC 2026 Presidential Symposium podium in Seoul. Conference-branding image; no data content. [Slide 2] DESTINY-Lung04 trial design - A randomized, open-label, multicenter, Phase 3 trial (NCT05048797). Patients: Unresectable locally advanced or metastatic nonsquamous NSCLC; treatment naive for advanced disease; HER2 exon 19 or 20 mutation by central/local test; ECOG PS 0 or 1; asymptomatic/stable/treated brain metastases permitted; >=1 measurable lesion per RECIST 1.1. Stratification factors: presence/history of brain metastases (yes vs no); smoking history status (ever vs never). Randomized 1:1 (N=454) -> T-DXd (5.4 mg/kg IV Q3W) n=227 | Pembro + platinum chemo (investigator choice cisplatin or carboplatin) + pemetrexed, n=227. Endpoints - Primary: PFS (BICR). Secondary: OS, ORR and DOR (BICR), PFS2 (investigator), safety and tolerability. Data cutoff for final PFS analysis / first OS interim analysis: June 9, 2026; formal hypothesis testing for OS will be performed at second interim and final analyses only. Median (range) duration of follow-up: 21.6 months (0.4-51.1) with T-DXd vs 20.4 months (0.1-52.0) with pembro + chemo. Treatment crossover was not permitted. [Slide 3] PFS (BICR): primary endpoint - Kaplan-Meier curves, T-DXd (n=227) vs pembro + chemo (n=227). Median PFS 14.3 months (95% CI 12.4-16.5) vs 8.3 months (95% CI 7.0-9.9); hazard ratio 0.63 (95% CI 0.50-0.79); P-value <0.0001; delta 6 months at the median. T-DXd monotherapy demonstrated a statistically significant and clinically meaningful PFS improvement vs standard-of-care pembro + doublet chemo. PFS per RECIST 1.1; at data cutoff there were 307 BICR-assessed PFS events. [Slide 4] Secondary efficacy endpoints - ORR (BICR; includes unconfirmed responses): T-DXd 70.0% (95% CI 63.6-75.9; n=159/227) vs pembro + chemo 44.5% (95% CI 37.9-51.2; n=101/227); odds ratio 2.93 (95% CI 2.00-4.34). Best overall response, n (%): complete response 4 (1.8) vs 4 (1.8); partial response 155 (68.3) vs 97 (42.7); stable disease 61 (26.9) vs 98 (43.2); progressive disease 4 (1.8) vs 15 (6.6); non-evaluable 3 (1.3) vs 13 (5.7). Median DOR, months (95% CI): 13.4 (10.4-17.2) vs 9.7 (7.0-11.1). Median PFS2 (investigator), months (95% CI): 22.7 (20.3-26.3) vs 17.3 (15.6-21.8); hazard ratio 0.80 (95% CI 0.62-1.02).
Stephen V Liu, MD @StephenVLiu · 2026-09-14
OS interim, overall safety and ILD/pneumonitis
WCLC 2026 · Sep 14, 2026 · Presidential session PL03.08
View Post
DESTINY-Lung04 WCLC 2026 slide - overall survival first interim: median 29.3 vs 33.1 months, HR 1.15, 46.9% maturityDESTINY-Lung04 WCLC 2026 slide - overall safety summary: drug-related AE discontinuation 15.9% in both armsDESTINY-Lung04 WCLC 2026 slide - most common drug-related adverse events by arm, any grade and grade 3 or higherDESTINY-Lung04 WCLC 2026 slide - adverse events of special interest: adjudicated drug-related ILD/pneumonitis 20.8% with T-DXd vs 2.3%
[Slide 1] Overall survival (first OS interim analysis) - OS events: T-DXd 115 (50.7%) vs pembro + chemo 98 (43.2%). Median OS 29.3 months (95% CI 26.2-33.4) vs 33.1 months (95% CI 27.7-40.7); hazard ratio 1.15 (95% CI 0.88-1.52). No OS benefit was observed with T-DXd; subsequent treatments may have impacted results. At data cutoff, overall data maturity for OS was 46.9%. Median follow-up was 21.6 months (range 0.4-51.1) in the T-DXd arm and 20.4 months (0.1-52.0) in the pembro + chemo arm. This administrative OS interim analysis was performed with a two-sided alpha-spend of 0.0001; formal hypothesis testing will be performed at the second interim analysis and final analysis. [Slide 2] Overall safety summary (investigator assessed) - T-DXd (n=226) vs pembro + chemo (n=220). Median (range) treatment duration: 12.3 months (0.7-44.8) vs 7.1 months (0.7-49.1). Drug-related AEs, n (%): any grade 204 (90.3) vs 197 (89.5); grade >=3: 77 (34.1) vs 74 (33.6); serious 35 (15.5) vs 22 (10.0); associated with any drug discontinuation 36 (15.9) vs 35 (15.9); associated with dose reduction 40 (17.7) vs 35 (15.9); associated with death 4 (1.8) vs 1 (0.5). Drug-related AEs associated with death were pneumonitis (n=4) in the T-DXd arm and sepsis (n=1) in the pembro + chemo arm. [Slide 3] Most common (>=15% in either arm) drug-related AEs (investigator assessed) - any grade / grade >=3, %, T-DXd (n=226) vs pembro + chemo (n=220): nausea 50.0/1.8 vs 38.2/0.9; fatigue 38.5/4.4 vs 34.1/3.2; neutropenia 35.0/11.1 vs 35.0/14.1; alopecia 32.7/0.9 vs 6.8/0; decreased appetite 29.6/0.4 vs 21.8/0.5; anemia 27.9/2.7 vs 44.1/11.4; constipation 24.8/0 vs 17.3/0; diarrhea 23.5/2.2 vs 12.7/1.4; transaminases increased 23.0/1.8 vs 29.1/3.2; leukopenia 19.5/3.5 vs 22.7/5.9; vomiting 19.0/1.3 vs 14.1/0.9; thrombocytopenia 18.1/4.4 vs 21.4/5.5; stomatitis 15.0/0 vs 7.7/0; rash 5.8/0.4 vs 15.5/0.9. [Slide 4] Adverse events of special interest - adjudicated drug-related ILD/pneumonitis, n (%), T-DXd (n=226) vs pembro + chemo (n=220): any grade 47 (20.8) vs 5 (2.3); grade 1: 7 (3.1) vs 1 (0.5); grade 2: 30 (13.3) vs 4 (1.8); grade 3: 5 (2.2) vs 0; grade 4: 1 (0.4) vs 0; grade 5: 4 (1.8) vs 0. Left ventricular dysfunction: any grade 7 (3.1) vs 1 (0.5). In the T-DXd arm: most cases of ILD were grade 1/2 (78.7%) and resolved (66.0%); 16 of the 30 grade 2 adjudicated ILD events were upgraded from grade 1 (per investigator) because of use of steroids; delayed initiation and/or suboptimal steroid dosing was observed in 90% of all grade >=3 ILD cases, including all four grade 5 cases; among patients with grade <=3 ILD who discontinued T-DXd, 64.1% received subsequent therapy, consistent with the overall T-DXd arm (71.5%). ILD remains an important risk of T-DXd and should be monitored/managed appropriately.
Masahiro TORASAWA, MD. PhD. @M_Torasawa · 2026-09-14
Design, baseline characteristics, PFS and OS
WCLC 2026 · Sep 14, 2026 · Presidential session PL03.08
View Post
DESTINY-Lung04 WCLC 2026 slide - trial design schema photographed in the presidential session hallDESTINY-Lung04 WCLC 2026 slide - demographics and baseline characteristics: ~94% HER2 exon 20, brain metastases 22.9% vs 24.2%DESTINY-Lung04 WCLC 2026 slide - PFS (BICR) primary endpoint Kaplan-Meier curves: median 14.3 vs 8.3 months, HR 0.63DESTINY-Lung04 WCLC 2026 slide - overall survival Kaplan-Meier curves: median 29.3 vs 33.1 months, HR 1.15
[Slide 1] DESTINY-Lung04 trial design - A randomized, open-label, multicenter, Phase 3 trial (NCT05048797). Patients: Unresectable locally advanced or metastatic nonsquamous NSCLC; treatment naive for advanced disease; HER2 exon 19 or 20 mutation by central/local test; ECOG PS 0 or 1; asymptomatic/stable/treated brain metastases permitted; >=1 measurable lesion per RECIST 1.1. Stratification factors: presence/history of brain metastases (yes vs no); smoking history status (ever vs never). Randomized 1:1 (N=454) -> T-DXd (5.4 mg/kg IV Q3W) n=227 | Pembro + platinum chemo (investigator choice cisplatin or carboplatin) + pemetrexed, n=227. Endpoints - Primary: PFS (BICR). Secondary: OS, ORR and DOR (BICR), PFS2 (investigator), safety and tolerability. Data cutoff for final PFS analysis / first OS interim analysis: June 9, 2026; formal hypothesis testing for OS will be performed at second interim and final analyses only. Median (range) duration of follow-up: 21.6 months (0.4-51.1) with T-DXd vs 20.4 months (0.1-52.0) with pembro + chemo. Treatment crossover was not permitted. [Slide 2] Demographics and baseline characteristics - T-DXd (n=227) vs pembro + chemo (n=227). Median age 62 years (range 26-85) vs 62 (31-85); female sex 58.6% vs 57.7%. Region: Asia 46.3% vs 52.9%; Europe 38.3% vs 30.4%; North America 11.5% vs 13.2%; rest of world 4.0% vs 3.5%. ECOG PS 0: 47.1% vs 47.6%; PS 1: 52.9% vs 52.0%. Never-smokers 62.1% in both arms. Liver metastases 19.8% vs 13.7%; brain metastases 22.9% vs 24.2% (all patients with brain metastases at baseline had received prior local therapy). HER2 mutation: exon 20 94.3% vs 93.0%; exon 19 4.4% vs 6.6%. PD-L1 status: <1% 41.9% vs 35.7%; 1-49% 15.0% vs 16.7%; >=50% 4.8% vs 3.5%; missing 38.3% vs 44.1% (prospective testing was not mandated). Disease status: de novo metastatic 75.8% vs 78.0%; recurrence/relapse 18.1% vs 18.5%; unresectable locally advanced 6.2% vs 3.5%. [Slide 3] PFS (BICR): primary endpoint - Kaplan-Meier curves, T-DXd (n=227) vs pembro + chemo (n=227). Median PFS 14.3 months (95% CI 12.4-16.5) vs 8.3 months (95% CI 7.0-9.9); hazard ratio 0.63 (95% CI 0.50-0.79); P-value <0.0001; delta 6 months at the median. T-DXd monotherapy demonstrated a statistically significant and clinically meaningful PFS improvement vs standard-of-care pembro + doublet chemo. PFS per RECIST 1.1; at data cutoff there were 307 BICR-assessed PFS events. [Slide 4] Overall survival (first OS interim analysis) - OS events: T-DXd 115 (50.7%) vs pembro + chemo 98 (43.2%). Median OS 29.3 months (95% CI 26.2-33.4) vs 33.1 months (95% CI 27.7-40.7); hazard ratio 1.15 (95% CI 0.88-1.52). No OS benefit was observed with T-DXd; subsequent treatments may have impacted results. At data cutoff, overall data maturity for OS was 46.9%. Median follow-up was 21.6 months (range 0.4-51.1) in the T-DXd arm and 20.4 months (0.1-52.0) in the pembro + chemo arm. This administrative OS interim analysis was performed with a two-sided alpha-spend of 0.0001; formal hypothesis testing will be performed at the second interim analysis and final analysis.
Toni Choueiri, MD @DrChoueiri · 2026-08-17
DESTINY-Lung04 Phase 3 design
Trial schematic - T-DXd vs platinum+pemetrexed+pembrolizumab, 1L HER2mt NSCLC
View Post
DESTINY-Lung04 conference slide — trial design schema: A Phase 3 Trial of T-DXd as 1L Treatment in Metastatic HER2mt
DESTINY-Lung04: A Phase 3 Trial of T-DXd as 1L Treatment in Metastatic HER2mt NSCLC Patient population (N~264 as designed; ClinicalTrials.gov actual enrollment 454): Unresectable, locally advanced (not amenable to curative therapy), or metastatic nonsquamous NSCLC with HER2 exon 19 or 20 mutations; Naive to systemic therapy in the locally advanced or metastatic setting; No known other targetable oncogenic mutations/alterations. Randomization 1:1 -> Arm 1: T-DXd | Arm 2: Standard of care: platinum (cisplatin or carboplatin) + pemetrexed + pembrolizumab
Giannis Mountzios @g_mountzios · 2026-08-17
Daiichi Sankyo topline press release
Press release, Aug 17, 2026
View Post
SAFFRON — Daiichi Sankyo topline press release
Enhertu(R) Demonstrated Statistically Significant and Clinically Meaningful Improvement in PFS as First-Line Treatment of Patients with HER2 Mutant Advanced NSCLC in DESTINY-Lung04 Phase 3 Trial. August 17, 2026. - Daiichi Sankyo and AstraZeneca's Enhertu is the first and only HER2-directed medicine to improve progression-free survival over global standard of care in a phase 3 trial in this setting - Data to be presented at an upcoming medical meeting and shared with global regulatory authorities
Chul Kim @chulkimMD · 2026-02-20
HER2-mutant NSCLC agent landscape (IASLC Targeted Therapies 2026)
Cross-trial comparison incl. DESTINY-Lung02 - published sources cited on slide
View Post
SAFFRON — HER2-mutant NSCLC agent landscape (IASLC Targeted Therapies 2026) (1)SAFFRON — HER2-mutant NSCLC agent landscape (IASLC Targeted Therapies 2026) (2)SAFFRON — HER2-mutant NSCLC agent landscape (IASLC Targeted Therapies 2026) (3)
IASLC 2026 Targeted Therapies of Lung Cancer Meeting (Feb 18-21, 2026, Huntington Beach, USA) - cross-trial comparison tables for HER2-mutant NSCLC (as shown; sources cited on slide: Heymach et al NEJM 2025;392:2321-33; Le et al NEJM 2025;393:1819-1832; Li et al NEJM 2022;386:241-51; Goto et al JCO 2023;41:4862-4863; Popat et al ESMO 2025 Abs LBA74). [Table 1 - previously treated:] T-DXd (DESTINY-Lung02, 5.4 mg/kg; n=102, 97% TKD): 34% CNS met+, 15% prior HER2 TKI, 74% prior ICI; 63% YVMA; ORR 50% (39-59); DCR 93% (86-97); PFS 9.9 mo (7.4-NE); CNS ORR 50% (23-77) n=14; common AEs nausea 67%, neutropenia 43%, ILD 13% (2% >=Gr3); dose reduction 17%, discontinuation 14%. Zongertinib (n=75, Cohort 1, all TKD): 37% CNS met+, 9% prior HER2 therapy, 76% prior ICI; 57% YVMA; ORR 71% (60-80); DCR 96% (89-99); PFS 12.4 mo (8.2-NE); CNS ORR 41% (25-59) n=27; AEs diarrhea 56%, rash 33%, ILD not reported; dose reduction 7%, discontinuation 3%. Sevabertinib (n=81, Cohort D, 90% TKD): 22% CNS met+, 2% prior HER2 therapy, 72% prior ICI; 60% YVMA; ORR 64% (53-75); DCR 81% (71-89); PFS 8.3 mo (6.9-12.3); CNS ORR N/A; AEs diarrhea 84-91%, rash 47-51%, ILD not reported; dose reduction 26%, discontinuation 5%. [Table 2 - by line:] Treatment-naive: T-DXd N/A; zongertinib ORR 77% (66-85) n=74, 6-mo PFS 79% (68-87); sevabertinib ORR 71% (59-81) n=73, PFS NE (9.6-NE). Previously treated: T-DXd 50% (39-59) n=102, mPFS 9.9 (7.4-NE); zongertinib 71% (60-80) n=75, 12.4 (8.2-NE); sevabertinib 64% (53-75) n=81, 8.3 (6.9-12.3). Post-HER2-directed therapy: zongertinib 48% (32-65) n=31, 6.8 (5.4-NE); sevabertinib 38% (25-52) n=55, PFS 5.5 (4.3-8.3). [Table 3 - ongoing first-line Phase 3 trials (ClinicalTrials.gov accessed 2/4/2026):] DESTINY-Lung04: T-DXd vs platinum+pemetrexed+pembrolizumab, PFS, NCT05048797. SOHO-02: sevabertinib vs same control, PFS, NCT06452277. Beamion LUNG-2: zongertinib vs same control, PFS, NCT06151574.

DESTINY-Lung04 Top Tweets

Chul Kim@chulkimMD
𝕏

HER2-mutant NSCLC landscape at #TTLC2026 by Dr. Christina Paik👇 In previously treated pts, three FDA approved drugs: T-DXd, Zongertinib, Sevabertinib. 1L phase 3 trials ongoing: DESTINY-Lung04, Beamion LUNG-2 m, SOHO-02. https://t.co/f9meok1tFL

2.2K views 0 likes0 RT 2026-02-20
Toni Choueiri, MD@DrChoueiri
𝕏

JUST IN (again, today!) and also from @AstraZeneca: DESTINY-Lung04 Phase III trial showed T-DXd (trastuzumab deruxtecan) PFS &gt; chemo+pembro in FIRST-LINE metastatic HER2-mutant lung cancer (2-4% of all NSCLC) https://t.co/C86sHsx0jN @OncoAlert @OpenMedicineHQ https://t.co/j8VOYZjWAR

1.9K views 0 likes0 RT 2026-08-17
Yakup Ergün@dr_yakupergun
𝕏

HER2-mutant NSCLC is rapidly becoming a truly targetable disease DESTINY-Lung04 trial to show that upfront HER2-directed T-DXd improves PFS over pembro +chemo The key question now is sequencing: ADC first, or the emerging HER2-selective TKIs? OS and full data will matter. https://t.co/DrR4ebk274

1.7K views 31 likes7 RT 2026-08-17
Dr. Antonio Calles 🫁🚭@Tony_Calles
𝕏

Enhertu demonstrated statistically significant and clinically meaningful improvement in progression-free survival as 1st-line treatment of patients with HER2-mutant advanced non-small cell lung cancer in DESTINY-Lung04 Phase III trial. https://t.co/AaHX1LPrla

1.3K views 0 likes0 RT 2026-08-17
Dr. Antonio Calles 🫁🚭@Tony_Calles
𝕏

“The DESTINY-Lung04 data will be presented at a forthcoming medical meeting and shared with global regulatory authorities.” “The trial will continue as planned to evaluate secondary endpoints including overall survival.” https://t.co/2pOoc4jXxd

753 views 0 likes0 RT 2026-08-17
International Lung Cancer Summit@LungSummit
𝕏

Three first-line trials, DESTINY-LUNG04, BEAMION-LUNG02 & SOHO-02, are redefining the HER2-mutant NSCLC landscape. At ILCS 2025, @stephanieplsaw asked how we’ll decide the “winner” if all three outperform Keynote-189: PFS, OS, CNS efficacy, toxicity, or timing of approval? Watch her full talk: https://t.co/qBfsppMWQK Results from BEAMION-LUNG01 (LBA74) & SOHO-01 (LBA75) will offer more insights at #ESMO25. Don’t miss it – add this and other key abstracts to your calendar 👇 https://t.co/50RRVPuS18

743 views 0 likes0 RT 2025-10-14
Jackie Aredo@JackieAredoMD
𝕏

@TumorBoardTues @riess_md @IntegrityCE @DrSanjayPopat @stephanieplsaw @StephenVLiu @LeXiuning @NarjustFlorezMD @SukiPaddaMD @JoelNealMD @Latinamd @jillfeldman4 @Exon20Group @drgandara @LeciaSequist @marinagarassino @peters_solange 21/25 #TumorBoardTuesday 👏Lots of progress for HER2 ex20ins 🫁. More to come! 1️⃣ 1L Anti-HER2 🔹 Ph 3 Beamion LUNG-2: Zongertinib (NCT06151574) 🔹 Ph 3 SOHO-02: Sevabertinib (NCT06452277) 🔹 Ph 3 DESTINY-Lung04: T-DXd (NCT05048797) ➡️ Control=plat/pemetrexed/pembro in all

741 views 0 likes0 RT 2026-03-11
Hidehito HORINOUCHI@HHorinouchi
𝕏

🔥DESTINY-Lung04: "Statistically significant and clinically meaningful improvement in PFS" 🆙 @AstraZeneca @DaiichiSankyo 👥Patients: HER2 exon19/20-mutant, unresectable/locally advanced or metastatic non-squamous NSCLC, 1st-line 3⃣Phase III ⚖️Trastuzumab deruxtecan ⚖️Platinum-pemetrexed doublet + pembrolizumab 🔢NCT05048797 #LCSM @OncoAlert @Larvol 🔗 https://t.co/jWxU9lCT3T

671 views 5 likes3 RT 2026-08-17
David Gandara@drgandara
𝕏

Re- Destiny-Lung04, Phase III of T-DXd vs Chemo in HER2-mutated NSCLC . Big news, although these results anticipated. Will it translate into improved overall survival? https://t.co/28MVd2vhae

463 views 0 likes0 RT 2026-08-17
Giannis Mountzios@g_mountzios
𝕏

🔔 Destiny-lung04 press release: First proof of evidence that HER2-directed therapies are improving outcomes vs SoC in 1L HER2-mutant NSCLC . Ongoing studies are exploring TDXd in 1L using HER2 IHC and PDL1&lt;50% as biomarkers ( Destiny Lung-06) #some #LCSM https://t.co/08I8k0yno0

151 views 0 likes0 RT 2026-08-17

About the DESTINY-Lung04 Trial

HER2 (ERBB2) mutations drive roughly 2–4% of nonsquamous NSCLC, disproportionately in younger patients and never-smokers, and until recently had no targeted first-line option: standard care has been PD-(L)1 immunotherapy with or without platinum chemotherapy. Enhertu — a HER2-directed antibody-drug conjugate — changed the treated-disease landscape via DESTINY-Lung02, which earned FDA accelerated approval in previously treated HER2-mutant NSCLC. DESTINY-Lung04 asks the next question: should it move to first line?

On August 17, 2026 — the same morning AstraZeneca announced SAFFRON’s positive readout — Daiichi Sankyo and AstraZeneca reported that T-DXd significantly improved PFS over platinum–pemetrexed plus pembrolizumab. Physicians on this page called it the first proof that HER2-directed therapy beats standard of care up front, while noting what remains open: overall survival is still maturing, and the oral HER2 TKIs zongertinib (Beamion LUNG-2) and sevabertinib (SOHO-02, confirmatory) are running Phase 3 trials against the same control — and sevabertinib (Hyrnuo) already holds FDA accelerated approval for first-line HER2 TKD-mutant NSCLC (September 9, 2026, per SOHO-01) — a sequencing debate the IASLC comparison slide on this page lays out.

Trial Methodology & Results

Study Design

Global, randomized (1:1), open-label Phase 3; actual enrollment 454 (ClinicalTrials.gov; ~264 originally planned). Randomization stratified by smoking history and presence/history of brain metastasis.

Population

Treatment-naive (advanced setting), unresectable locally advanced or metastatic non-squamous NSCLC with HER2 exon 19 or 20 mutation; no other targetable oncogenic alterations.

Interventions

Arm 1: T-DXd (trastuzumab deruxtecan) 5.4 mg/kg. Arm 2: standard of care — platinum (cisplatin or carboplatin) + pemetrexed + pembrolizumab.

Endpoints

Primary: PFS by BICR. Secondary: OS, investigator PFS, ORR, DoR (BICR and investigator), PK, patient-reported tolerability, immunogenicity, safety.

Biomarker

HER2 (ERBB2) exon 19 or 20 activating mutation.

Sponsor

AstraZeneca (ClinicalTrials.gov sponsor) with Daiichi Sankyo as collaborator; Enhertu was discovered by Daiichi Sankyo and is jointly developed and commercialized by both companies.

Efficacy — topline only

T-DXd delivered a statistically significant and clinically meaningful improvement in PFS (primary endpoint, BICR) versus platinum–pemetrexed plus pembrolizumab: median 14.3 vs 8.3 months, HR 0.63 (95% CI 0.50–0.79; P<0.0001). ORR was 70.0% vs 44.5% (odds ratio 2.93), median DoR 13.4 vs 9.7 months, and investigator-assessed PFS2 22.7 vs 17.3 months (HR 0.80, 95% CI 0.62–1.02). At the first OS interim analysis there was no OS benefit (median 29.3 vs 33.1 months; HR 1.15, 95% CI 0.88–1.52; 46.9% maturity); formal OS hypothesis testing is reserved for the second interim and final analyses. (WCLC 2026 presidential session PL03.08, Rotow et al; DCO June 9, 2026)

First HER2-directed medicine to beat global 1L standard of care in Phase 3
Daiichi Sankyo topline PR, Aug 17, 2026 · WCLC 2026 primary-results slides (via Dr. Stephen V. Liu)

Safety

Per the WCLC 2026 presentation (investigator-assessed; DCO June 9, 2026): drug-related AEs of any grade occurred in 90.3% with T-DXd (n=226) vs 89.5% with pembrolizumab + chemotherapy (n=220); grade ≥3 in 34.1% vs 33.6%; and drug-related AEs led to discontinuation in 15.9% of both arms. Adjudicated drug-related ILD/pneumonitis — the risk physicians flagged most — occurred in 20.8% of T-DXd patients vs 2.3% (grade ≥3 4.4%, including four grade 5 events); most cases were grade 1/2 (78.7%) and resolved. Median treatment duration was 12.3 vs 7.1 months. (WCLC 2026 presidential session PL03.08, Rotow et al)

Daiichi Sankyo PR, Aug 17, 2026 · WCLC 2026 safety slides (via Dr. Stephen V. Liu, OCR above)

Clinical Implications

⚠ First-line T-DXd in HER2m NSCLC is investigational pending full data and regulatory review. ✅ Enhertu remains FDA-approved (accelerated) in previously treated HER2-mutant disease. If the PFS benefit holds up with OS and tolerability, the 1L treatment paradigm for HER2-mutant NSCLC would shift from chemo-immunotherapy to targeted therapy — with sequencing against the oral HER2 TKIs (zongertinib approved Feb 2026 in later lines; Beamion LUNG-2 and SOHO-02 pending) as the next debate.

Source: FDA approval notifications

DESTINY-Lung04 in the News

DESTINY-Lung04 FAQ

What is the DESTINY-Lung04 trial?

DESTINY-Lung04 (NCT05048797) is a global, randomized (1:1), open-label Phase 3 trial testing Enhertu (trastuzumab deruxtecan, T-DXd) as FIRST-LINE treatment versus the global standard of care - platinum (cisplatin or carboplatin) plus pemetrexed plus pembrolizumab - in patients with unresectable, locally advanced or metastatic non-squamous NSCLC harboring a HER2 exon 19 or 20 mutation. It is the first head-to-head trial of a HER2-directed therapy against standard of care in this first-line setting. ClinicalTrials.gov lists actual enrollment of 454 patients.

What did the DESTINY-Lung04 results show at WCLC 2026?

Primary results were presented by Dr. Julia Rotow (Dana-Farber Cancer Institute) at the WCLC 2026 presidential session in Seoul on September 14, 2026 (data cutoff June 9, 2026). First-line T-DXd improved median PFS to 14.3 months versus 8.3 months with pembrolizumab plus platinum-pemetrexed (HR 0.63, 95% CI 0.50-0.79; P<0.0001), with ORR 70.0% versus 44.5% and median duration of response 13.4 versus 9.7 months. At the first interim analysis there was no overall survival benefit (median OS 29.3 vs 33.1 months; HR 1.15, 95% CI 0.88-1.52; 46.9% maturity), with interpretation complicated by subsequent HER2-directed therapy in 48.0% of the control arm versus 23.3% of the T-DXd arm. Drug-related adverse events led to discontinuation in 15.9% of both arms, and adjudicated drug-related ILD/pneumonitis occurred in 20.8% of T-DXd patients (grade 5: 1.8%).

Is Enhertu approved for HER2-mutant lung cancer?

Yes - for previously treated disease: Enhertu holds FDA accelerated approval for adults with unresectable or metastatic NSCLC whose tumors have activating HER2 (ERBB2) mutations after a prior systemic therapy (based on DESTINY-Lung02 and/or DESTINY-Lung05), and a separate accelerated approval for previously treated HER2-positive (IHC 3+) solid tumors with no satisfactory alternative treatment options. The FIRST-LINE use studied in DESTINY-Lung04 is investigational.

Who is eligible in DESTINY-Lung04?

Adults with treatment-naive (in the advanced setting), unresectable, locally advanced or metastatic non-squamous NSCLC with a HER2 exon 19 or 20 mutation and no other targetable oncogenic alterations.

Why does DESTINY-Lung04 matter?

HER2-mutant NSCLC often affects younger patients and historically lacked a targeted first-line option - standard first-line care has been immunotherapy with or without chemotherapy. DESTINY-Lung04 is the first Phase 3 trial to show a PFS benefit for a HER2-directed medicine over that global standard in first line, and it lands in an increasingly competitive space alongside the oral HER2 TKIs zongertinib (Beamion LUNG-2, Phase 3 against the same control) and sevabertinib, which received FDA accelerated approval for first-line HER2 TKD-mutant NSCLC on September 9, 2026 (SOHO-01), with SOHO-02 as its confirmatory Phase 3.

Key KOL Sentiments — DESTINY-Lung04

KOLComment (verbatim)Sentiment
Dr. Antonio Calles 😳 Disappointing results of T-DXd in large randomized phase III Destiny-Lung04 first line in HER2mut NSCLC vs SoC chemo-pembro. Although control arm outperformed, the lack of translation into OS benefit and the concerning safety issues of this agent warrants a lot of discussion, specially in the upcoming data from selective HER2 TKIs, with are associated with better tolerance and safety profile. #WCLC26 @iasclc #lcsm Negative
Guilherme S. C. Correia, MD @Tony_Calles @NReguart Absolutely! Hard to argue against the safety and convenience of TKIs. If data about T-DXd after HER2 TKI shows a compelling signal, it would further support saving this ADC for 2nd line. Neutral
Uğur Özkerim DESTINY-Lung04 at #WCLC26 In 1L HER2-mutant advanced NSCLC, T-DXd significantly improved PFS vs pembrolizumab + chemotherapy: mPFS 14.3 vs 8.3 months (HR 0.63; P<0.0001) ORR: 70.0% vs 44.5% However, no OS benefit was observed at this analysis (29.3 vs 33.1 months; HR 1.15). The first Phase 3 trial showing benefit of a HER2-directed therapy vs SOC in this setting. @OncoAlert @GlopesMd @ManuelDomine @StephenVLiu @weoncologists @OpenMedKate Positive
MV Chandrakanth DESTINY-Lung04 🫁 Can T-DXd move up front in HER2-mutant advanced NSCLC? T-DXd vs pembrolizumab + platinum/pemetrexed: → PFS: 14.3 vs 8.3 months → HR 0.63 → ORR: 70% vs 44.5% → DoR: 13.4 vs 9.7 months A compelling improvement in disease control. But the trade-off matters: ILD 20.8%, including 1.8% Grade 5 ILD with T-DXd. OS remains difficult to interpret at this analysis, particularly in the context of imbalanced subsequent therapies. Take-home: T-DXd emerges as an important new first-line option for advanced HER2-mutant NSCLC — with vigilant ILD recognition and monitoring essential. 📚 Reference: DESTINY-Lung04, Phase III study; WCLC 2026. #MVOnco #DESTINYLung04 #TDXd #HER2 #HER2Mutant #NSCLC #LungCancer #ThoracicOncology #WCLC2026 #Oncology Positive
Eric K. Singhi, MD T-DXd trying to catch up in the frontline setting with zongertinib and sevabertinib Results from #DESTINYLung04…. #WCLC26 https://t.co/wb9BkFV7dg Neutral
Hidehito HORINOUCHI 🆙#WCLC26 #LCSM Plenary Session 🔥DESTINY-Lung04: First-Line Trastuzumab Deruxtecan (T-DXd) in Patients With Metastatic HER2-Mutant NSCLC: Primary Results 🎙️ @JuliaRotow 🎯PFS HR 0.63 (95%CI 0.50-0.79) 🎯OS HR 1.15 (95%CI 0.88-0.92) 🔢PL03.08 ☑️NCT05048797 🔗 https://t.co/gAahGHJGeA @OncoAlert @Larvol @IASLC Neutral
Stephen V Liu, MD Dr. @JuliaRotow at #WCLC26 with primary results from DESTINY-Lung04: first-line trastuzumab deruxtecan vs platinum + pemetrexed + pembro in advanced HER2 mutant NSCLC. Primary endpoint of PFS favors T-DXd at 14.3 vs 8.3m, HR 0.63 and RR 70% vs 44.5%, DOR 13.7 vs 9.7m, PFS2 22.7 vs 17.3m. Neutral
Masahiro TORASAWA, MD. PhD. #WCLC26 | DESTINY-Lung04 🧬 Ph3: 1L T-DXd vs pembrolizumab + chemo in advanced HER2m NSCLC (n=454; ~94% HER2 exon20) 📉 PFS: 14.3 vs 8.3 mo; HR 0.63 (95% CI 0.50–0.79; p<0.0001) → ~6-month improvement 🎯 ORR: 70.0% vs 44.5% ⏳ DoR: 13.4 vs 9.7 mo 🧠 Benefit maintained in patients with brain mets: PFS HR 0.62 📊 Interim OS showed no benefit: • 29.3 vs 33.1 mo • HR 1.15 (95% CI 0.88–1.52) ⚠️ Interpretation complicated by subsequent therapy imbalance: HER2-directed therapy 48.0% vs 23.3% in the control vs T-DXd arms 🫁 Adjudicated drug-related ILD/pneumonitis: 20.8% • G≥3: 4.4% • G5: 1.8% Neutral
Diego A. Díaz-García 🫁 DESTINY-Lung04: T-DXd in HER2-mutant NSCLC. @JuliaRotow First-line T-DXd significantly improved PFS vs pembro + chemo: 14.3 vs 8.3 months HR 0.63 (95% CI, 0.50-0.79; P<0.0001) ORR was 70.0% vs 44.5%, with median DoR of 13.4 vs 9.7 mo. OS did not favor T-DXd (HR 1.15), with subsequent therapy imbalances limiting interpretation. ILD/pneumonitis occurred in 20.8% with T-DXd, predominantly grade 1/2. #CánCare #oncology #thoraciconcology #lungcancer #NSCLC #HER2 #ADC #WCLC26 @IASLC Neutral
Miguel Gonzalez Velez, MD DESTINY-Lung04. T-DXd vs pembrolizumab + chemo as 1L therapy in HER2-mutant (exon 19/20) NSCLC by @JuliaRotow #WCLC26 Take: Primary endpoint met PFS 14.3mo (T-DXd) vs 8.3mo. ORR 70% vs 44.5%; DOR 13.4 vs 9.7mo; median treatment duration 12mo vs 7mo. OS at 46.9% maturity numerically favors the control arm: 29.3mo (T-DXd) vs 33.1mo (pembro+chemo), HR 1.15 (0.88–1.52). no OS benefit, with many confounding postreatment. Great to see the comparator here is genuine current SOC not a weaker historical control, which makes the PFS win more meaningful but also makes the OS numbers harder to wave away. Again going back to the ORR/PFS/OS dilemma. #NSCLC #LCSM Neutral
gilberto lopes #WCLC26 Presidential Symposium: DESTINY-Lung04 1L T-DXd vs pembrolizumab + platinum/pemetrexed in metastatic HER2-mutant NSCLC: • PFS 14.3 vs 8.3 mo • HR 0.63 (95% CI 0.50–0.79), P<0.0001 • ORR 70.0% vs 44.5% • DoR 13.4 vs 9.7 mo https://t.co/f2lIDEBgH7 Neutral
Misty Dawn Shields Dr. Julia Rotow @JuliaRotow presents the DESTINY-Lung-04 data of trastuzumab deruxtecan vs pembro+chemo in 1L HER2 NSCLC at @IASLC #WCLC26. T-DXd improved PFS and ORR, yet OS benefit is limited with this regimen, likely confounded by access to 2L HER2-directed therapies. AEs notable with ILD 20.8% (>4% G3+). Difficult to know how T-DXd will fit in the sequencing of an evolving HER2 landscape with available TKIs zongertinib & sevabertinib. @lungoncdoc @LUNGevity @LungCancerEu @YoungLungCancer @GO2forLungCancr @StephenVLiu Neutral
Noemi Reguart DESTINY-Lung04 🔥 #WCLC26. 1L T-DXd significantly improves PFS vs pembro + platinum/pemetrexed in HER2-mutant NSCLC: 14.3 vs 8.3 mo | HR 0.63 (95% CI 0.50–0.79), P<0.0001. IA No OS benefit. Of note considerable ILD (overall 20.8%, 2% Gr 5).@JuliaRotow #HER2 #NSCLC #LCSM https://t.co/TjVOi2qyPf Neutral
Jose Fernando Moura, PhD DESTINY-Lung04 🚨 T-DXd in 1L HER2m NSCLC: ORR 70%. PFS, ✅ OS not ARROS-1 🔥 Zidesamtinib in TKI-naïve ROS1+ NSCLC: ORR 94%, CR 15%. Impressive activity. Durability, CNS control and PFS will define its place in 1L. @IASLC #WCLC26 @KolPulseAI @OncoAlert @Larvol @GlopesMd @StephenVLiu Neutral
Joshua Reuss Dr. @JuliaRotow presents Ph3 DESTINY-Lung04 T-DXd vs Pembro-chemo #WCLC26. ✅️ PFS 14.3 vs 8.3mo (HR 0.63) ✅️ ORR 7O vs 45% ☑️ No OS diff observed 1st ph3 study for HER2-targeted Rx in adv HER2m NSCLC. Efficacy by mutation type & CNS efficacy will help in agent selection. https://t.co/wRbyeY4eZd Neutral
Jennifer A. Marks, MD Dr. @JuliaRotow presents DESTINYLung04, 1L T-DXd in HER2 mt NSCLC. Study met its primary endpoint of mPFS, 14.3 vs 8.3 mo, HR 0.63; P<0.0001. No OS benefit but durability and response favored T-DXd. ILD and ♥️ AEs require awareness and close monitoring @IASLC #WCLC26 #LCSM https://t.co/615R1IXBwO Neutral
OsmanKostekMD WCLC 2026 | DESTINY-Lung04 1L T-DXd improved PFS (14.3 vs 8.3 mo; HR 0.63) and ORR (70% vs 44.5%) in HER2-mut NSCLC. OS superiority not shown (HR 1.15), with interpretation complicated by imbalanced subsequent HER2-directed therapy (48% vs ~23%). ILD remains key. #WCLC26 #HER2 https://t.co/WhQRNxRnhm Neutral
Kenn Samala #TrastuzumabDeruxtecan #DestinyLung04 #WCLC26 ✅️ PFS: 14.3 mos vs 8.3 mos HR 0.63 ✅️ PFS benefit seen across subgroups ✅️ ORR: 70% ✅️ No Significant OS benefit (effected likely by subsequent treatments) https://t.co/PfWRQ9yUyE Neutral
Stephen V Liu, MD #WCLC26 In DESTINY-Lung04, no OS signal yet. Toxicities led to discontinuation in 16% of both arms. Biggest concern here is the ILD at 20.8% - while most were grade 1/2 and resolved, these are still high rates. This will impact delivery and possibly subsequent therapies... https://t.co/ZUQSd7yaFX Negative
Laura Alder, MD Dr @JuliaRotow with terrific presentation of DESTINY-Lung04 #WCLC26. ORR 70% vs 44.5%, improved PFS. ‼️No significant OS benefit ; notably, 48% of chemo arm did receive subsequent HER2 directed treatment 🚨ILD any grade 20.8% (78.7% G 1/2) ⭐️Zongertinib my choice for 1L treatment in HER2 TKD alterations Negative
Dr Riyaz Shah DESTINY-Lung04; front line, no protocol mandated x over; n454; 23% have brain mets; mPFS 8.3 v 14.3m HR 0.63; ORR 70%; mDOR 13.4m; no OS benefit! 48% of control arm got subsequent her2 directed therapy: 21% any grade ILD; @Bayer and @Boehringer can give a sigh of relief #WCLC26 https://t.co/LFPLj0hlsF Negative
Urs Weber MD Congratulations @JuliaRotow on an excellent presentation of DESTINY-Lung04 at @IASLC #WCLC26! T-Dxd is clearly an active drug in HER2-mutant NSCLC, but the lack of OS benefit raises the question of whether its role is truly in 1L, especially now that we have effective TKIs. https://t.co/iPi6JuJCF4 Negative
Yakup Ergün HER2-mutant NSCLC is rapidly becoming a truly targetable disease DESTINY-Lung04 trial to show that upfront HER2-directed T-DXd improves PFS over pembro +chemo The key question now is sequencing: ADC first, or the emerging HER2-selective TKIs? OS and full data will matter. https://t.co/DrR4ebk274 Positive
Giannis Mountzios 🔔 Destiny-lung04 press release: First proof of evidence that HER2-directed therapies are improving outcomes vs SoC in 1L HER2-mutant NSCLC . Ongoing studies are exploring TDXd in 1L using HER2 IHC and PDL1&lt;50% as biomarkers ( Destiny Lung-06) #some #LCSM https://t.co/08I8k0yno0 Positive
Chul Kim HER2-mutant NSCLC landscape at #TTLC2026 by Dr. Christina Paik👇 In previously treated pts, three FDA approved drugs: T-DXd, Zongertinib, Sevabertinib. 1L phase 3 trials ongoing: DESTINY-Lung04, Beamion LUNG-2 m, SOHO-02. https://t.co/f9meok1tFL Neutral
Toni Choueiri, MD JUST IN (again, today!) and also from @AstraZeneca: DESTINY-Lung04 Phase III trial showed T-DXd (trastuzumab deruxtecan) PFS &gt; chemo+pembro in FIRST-LINE metastatic HER2-mutant lung cancer (2-4% of all NSCLC) https://t.co/C86sHsx0jN @OncoAlert @OpenMedicineHQ https://t.co/j8VOYZjWAR Neutral
Dr. Antonio Calles 🫁🚭 Enhertu demonstrated statistically significant and clinically meaningful improvement in progression-free survival as 1st-line treatment of patients with HER2-mutant advanced non-small cell lung cancer in DESTINY-Lung04 Phase III trial. https://t.co/AaHX1LPrla Neutral
Dr. Antonio Calles 🫁🚭 “The DESTINY-Lung04 data will be presented at a forthcoming medical meeting and shared with global regulatory authorities.” “The trial will continue as planned to evaluate secondary endpoints including overall survival.” https://t.co/2pOoc4jXxd Neutral
Jackie Aredo @TumorBoardTues @riess_md @IntegrityCE @DrSanjayPopat @stephanieplsaw @StephenVLiu @LeXiuning @NarjustFlorezMD @SukiPaddaMD @JoelNealMD @Latinamd @jillfeldman4 @Exon20Group @drgandara @LeciaSequist @marinagarassino @peters_solange 21/25 #TumorBoardTuesday 👏Lots of progress for HER2 ex20ins 🫁. More to come! 1️⃣ 1L Anti-HER2 🔹 Ph 3 Beamion LUNG-2: Zongertinib (NCT06151574) 🔹 Ph 3 SOHO-02: Sevabertinib (NCT06452277) 🔹 Ph 3 DESTINY-Lung04: T-DXd (NCT05048797) ➡️ Control=plat/pemetrexed/pembro in all Neutral
Hidehito HORINOUCHI 🔥DESTINY-Lung04: "Statistically significant and clinically meaningful improvement in PFS" 🆙 @AstraZeneca @DaiichiSankyo 👥Patients: HER2 exon19/20-mutant, unresectable/locally advanced or metastatic non-squamous NSCLC, 1st-line 3⃣Phase III ⚖️Trastuzumab deruxtecan ⚖️Platinum-pemetrexed doublet + pembrolizumab 🔢NCT05048797 #LCSM @OncoAlert @Larvol 🔗 https://t.co/jWxU9lCT3T Neutral
David Gandara Re- Destiny-Lung04, Phase III of T-DXd vs Chemo in HER2-mutated NSCLC . Big news, although these results anticipated. Will it translate into improved overall survival? https://t.co/28MVd2vhae Neutral
Enes Erul MD A remarkable day for precision oncology in NSCLC ✅ SAFFRON: osimertinib + savolitinib improved both PFS and OS in MET-driven resistance after osimertinib. ✅ DESTINY-Lung04: T-DXd improved PFS over chemo-immunotherapy in 1L HER2-mutant NSCLC. @isliquidbiopsy @RobertoBoreaMD https://t.co/athnwugaoj Neutral
120s · every quote verbatim