LIVE #WCLC26 — live KOL coverage of the World Conference on Lung Cancer View Full Coverage →
KOL Pulse - Trial Profile

IMpower030 Trial

IMpower030 (NCT03456063) is Roche/Genentech's phase III trial of perioperative atezolizumab plus neoadjuvant chemotherapy versus chemotherapy alone in resectable stage II–IIIB NSCLC (N=453). In the final analysis presented at WCLC 2026 (OA04.03), event-free survival trends favored atezolizumab but did not meet the prespecified statistical threshold, despite a pathological complete response rate of 29.6% versus 8.5% in the primary analysis population — a statistically negative result carrying a real pathological signal, which physicians debated all afternoon.

Phase III · NCT03456063 Sponsor: Roche / Genentech EFS primary endpoint NOT met pCR 29.6% vs 8.5% WCLC 2026 · OA04.03 · N=453

IMpower030 at a Glance

Design

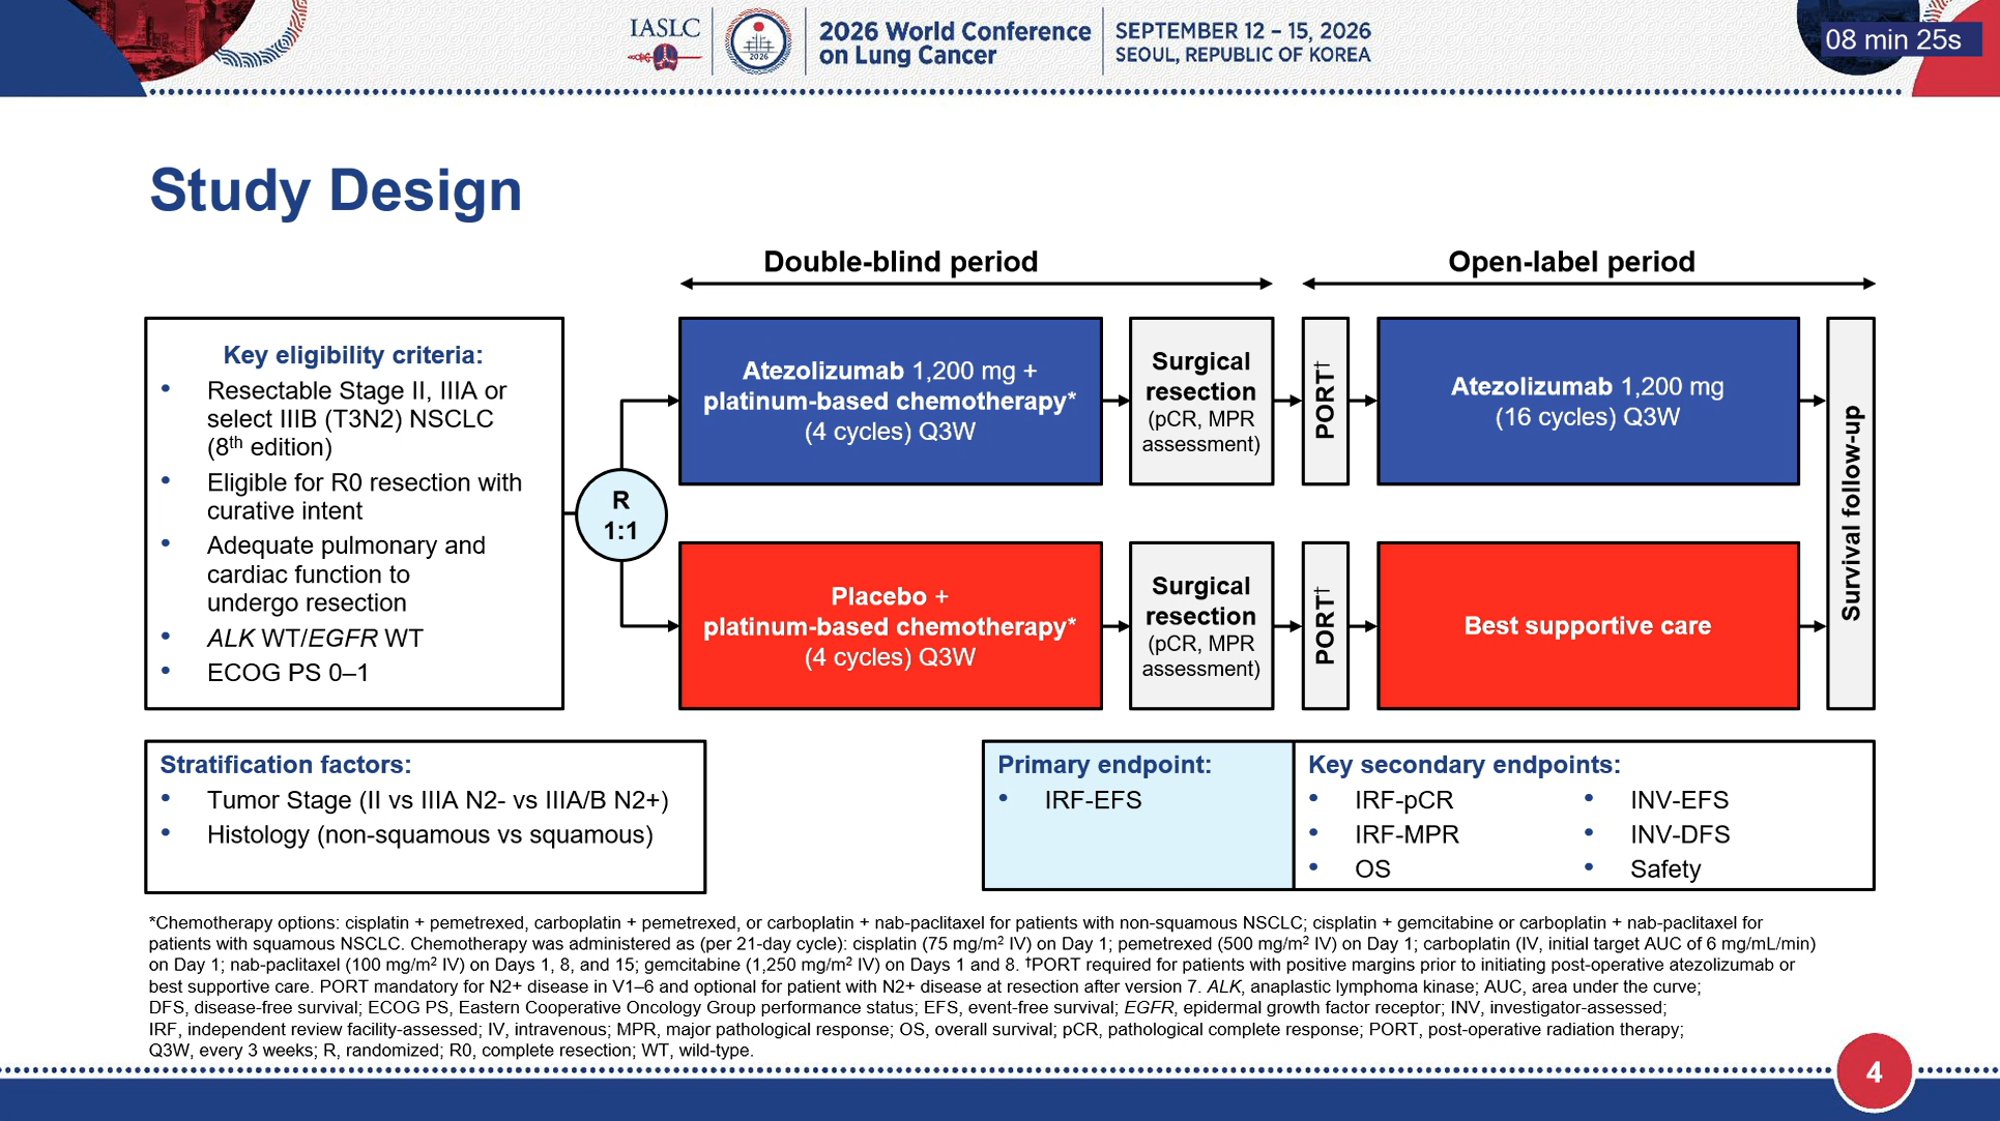
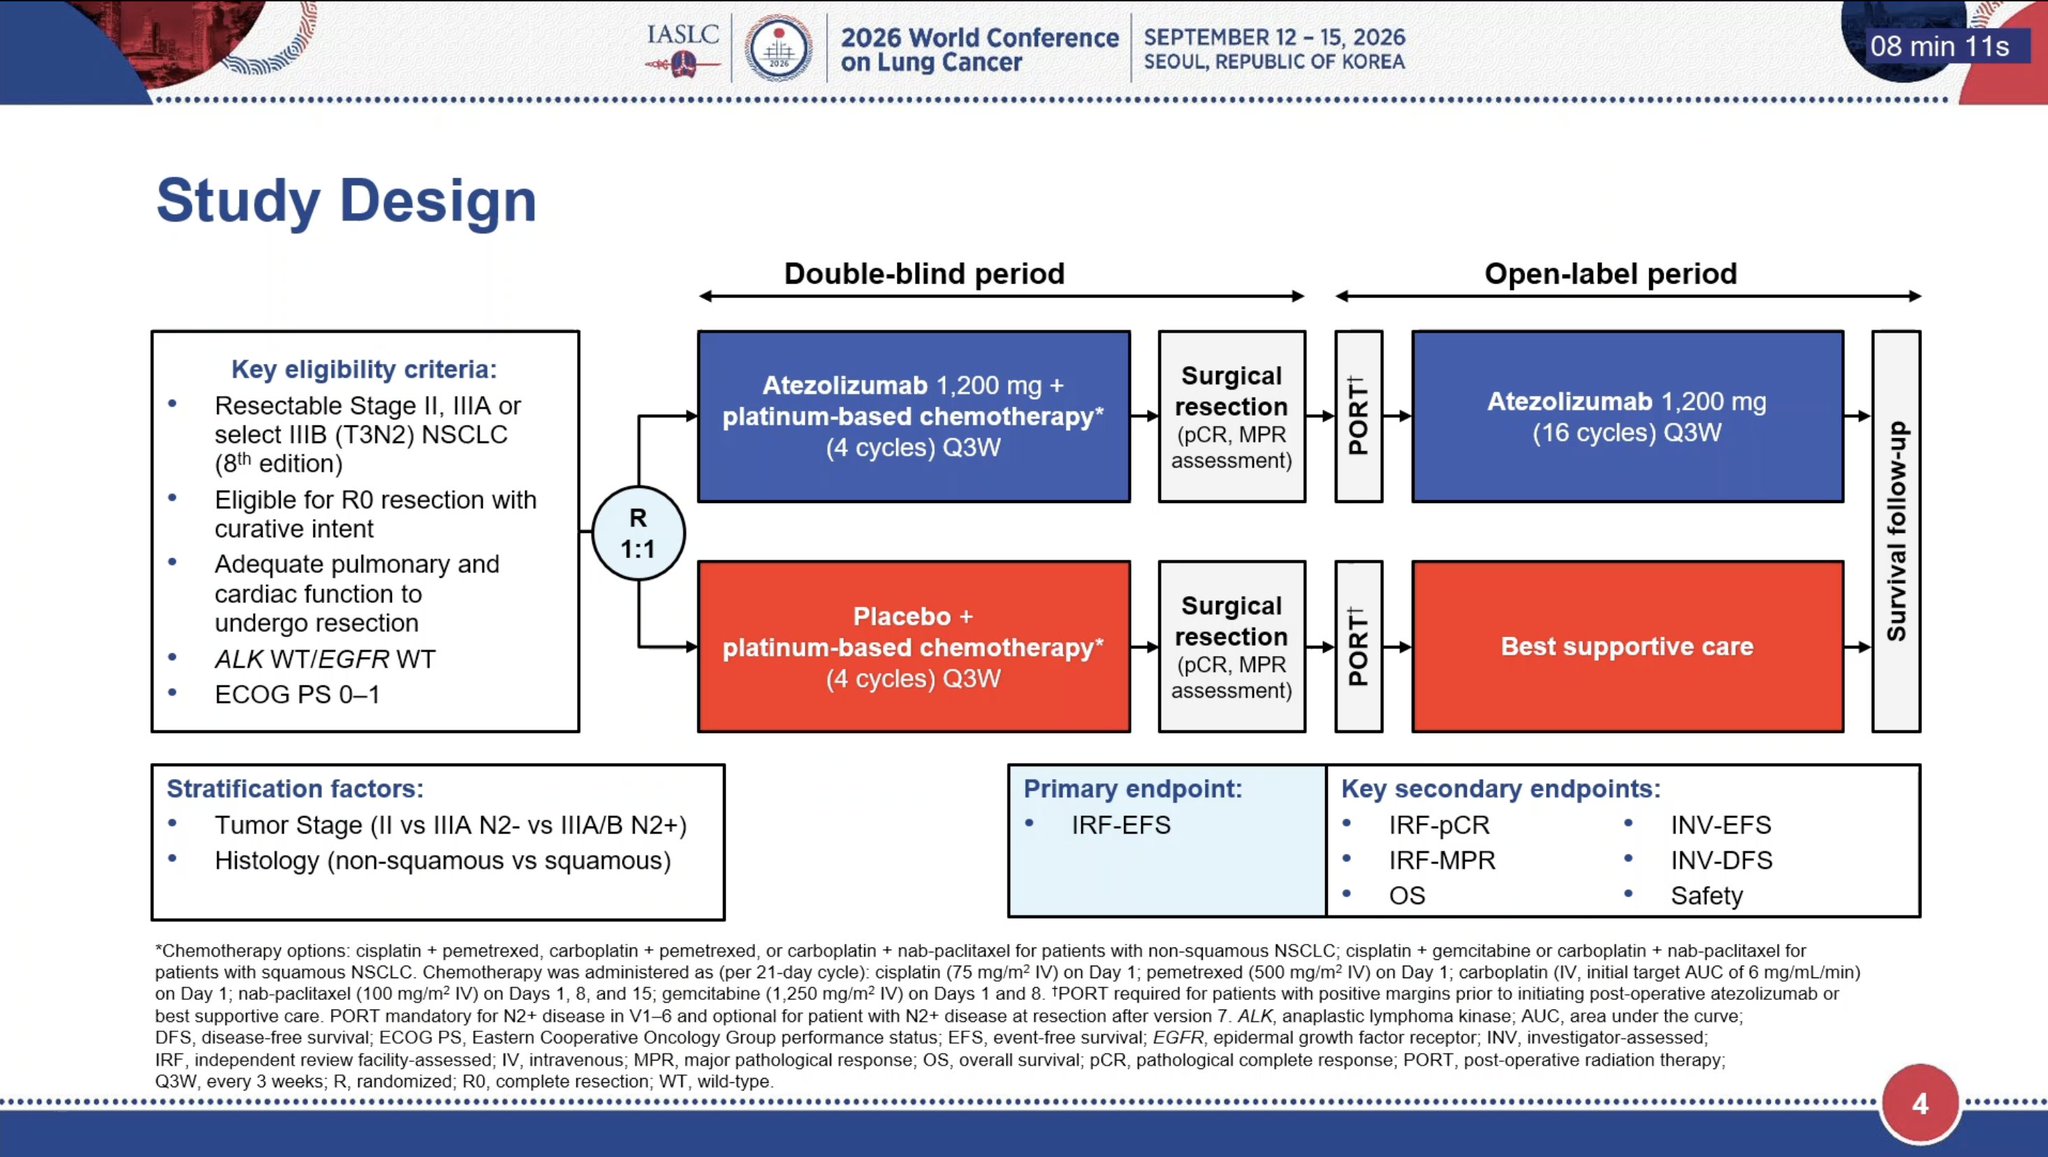
Phase III, randomized: perioperative atezolizumab + platinum-based neoadjuvant chemotherapy versus neoadjuvant chemotherapy alone in resectable stage II–IIIB NSCLC; N=453; EFS primary endpoint. (WCLC 2026 OA04.03 via verbatim KOL captures)

Primary result

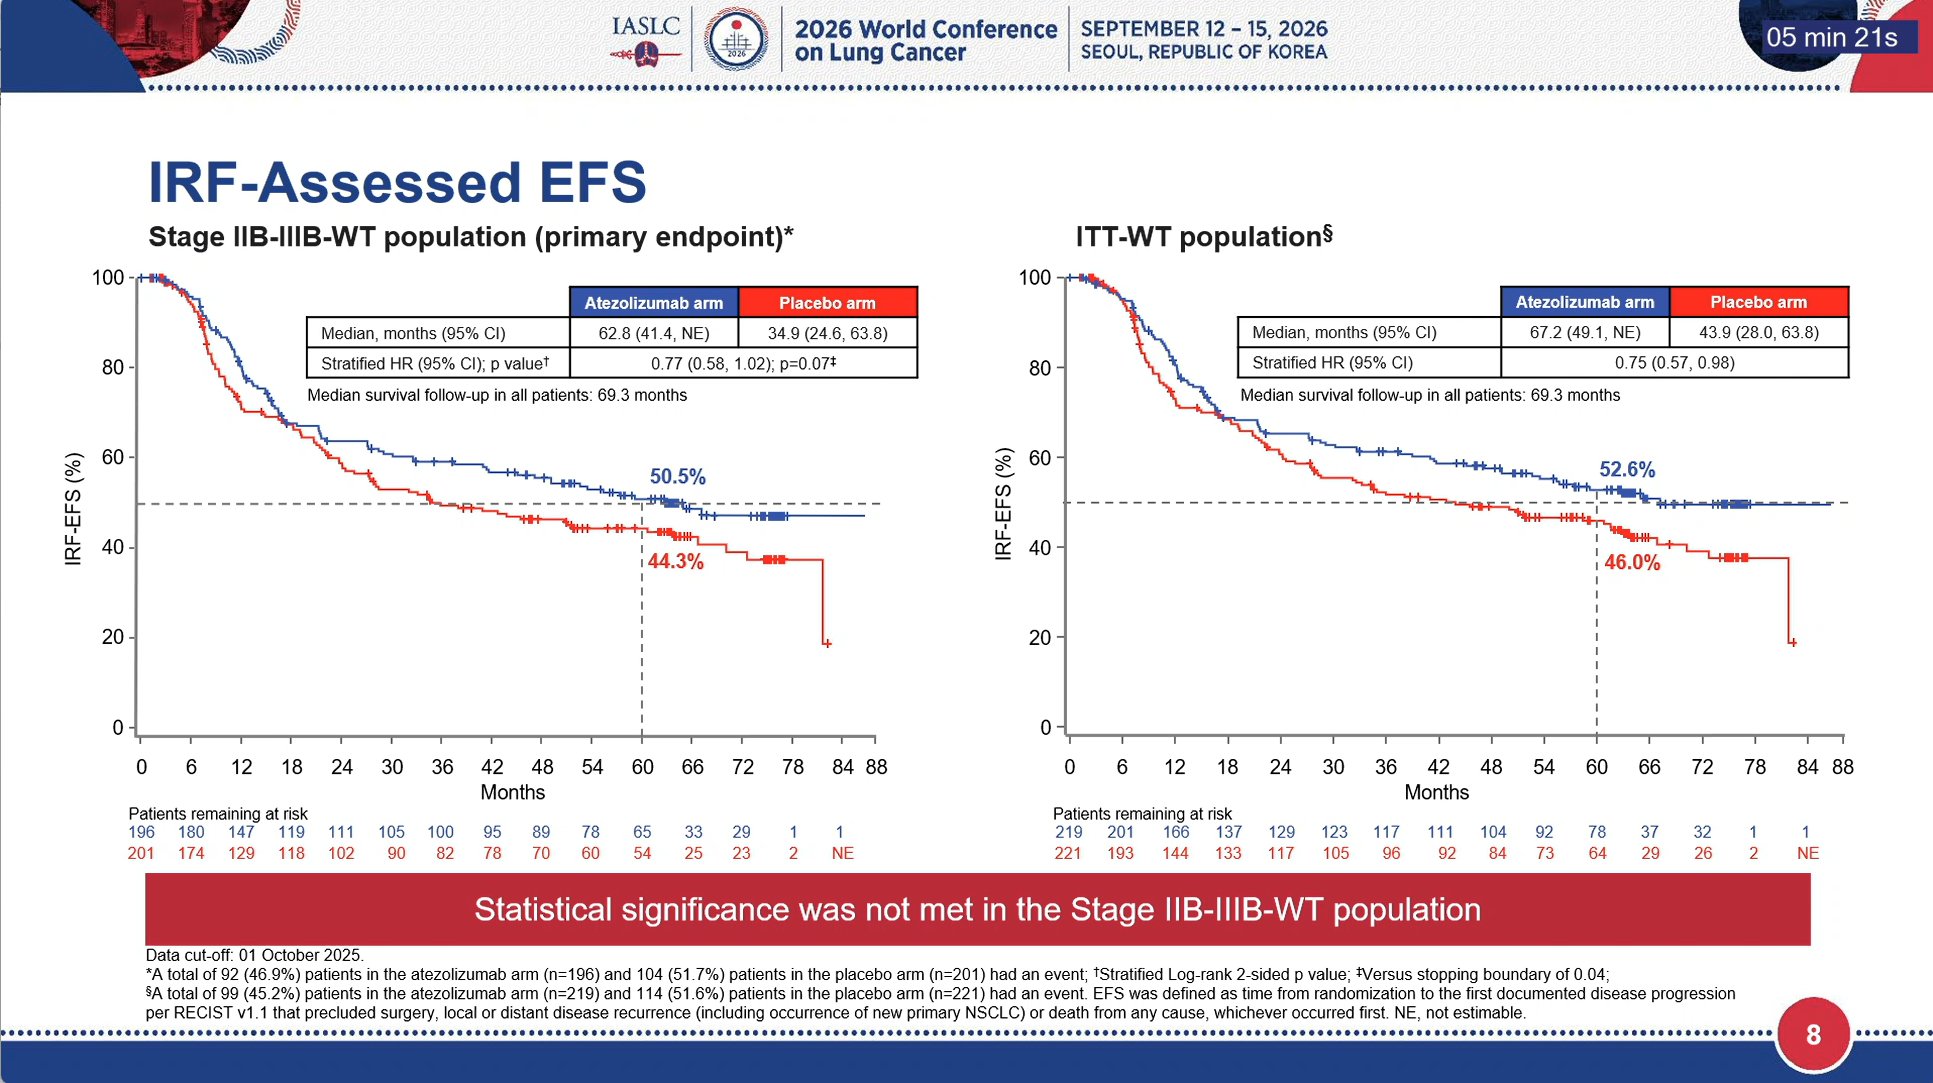
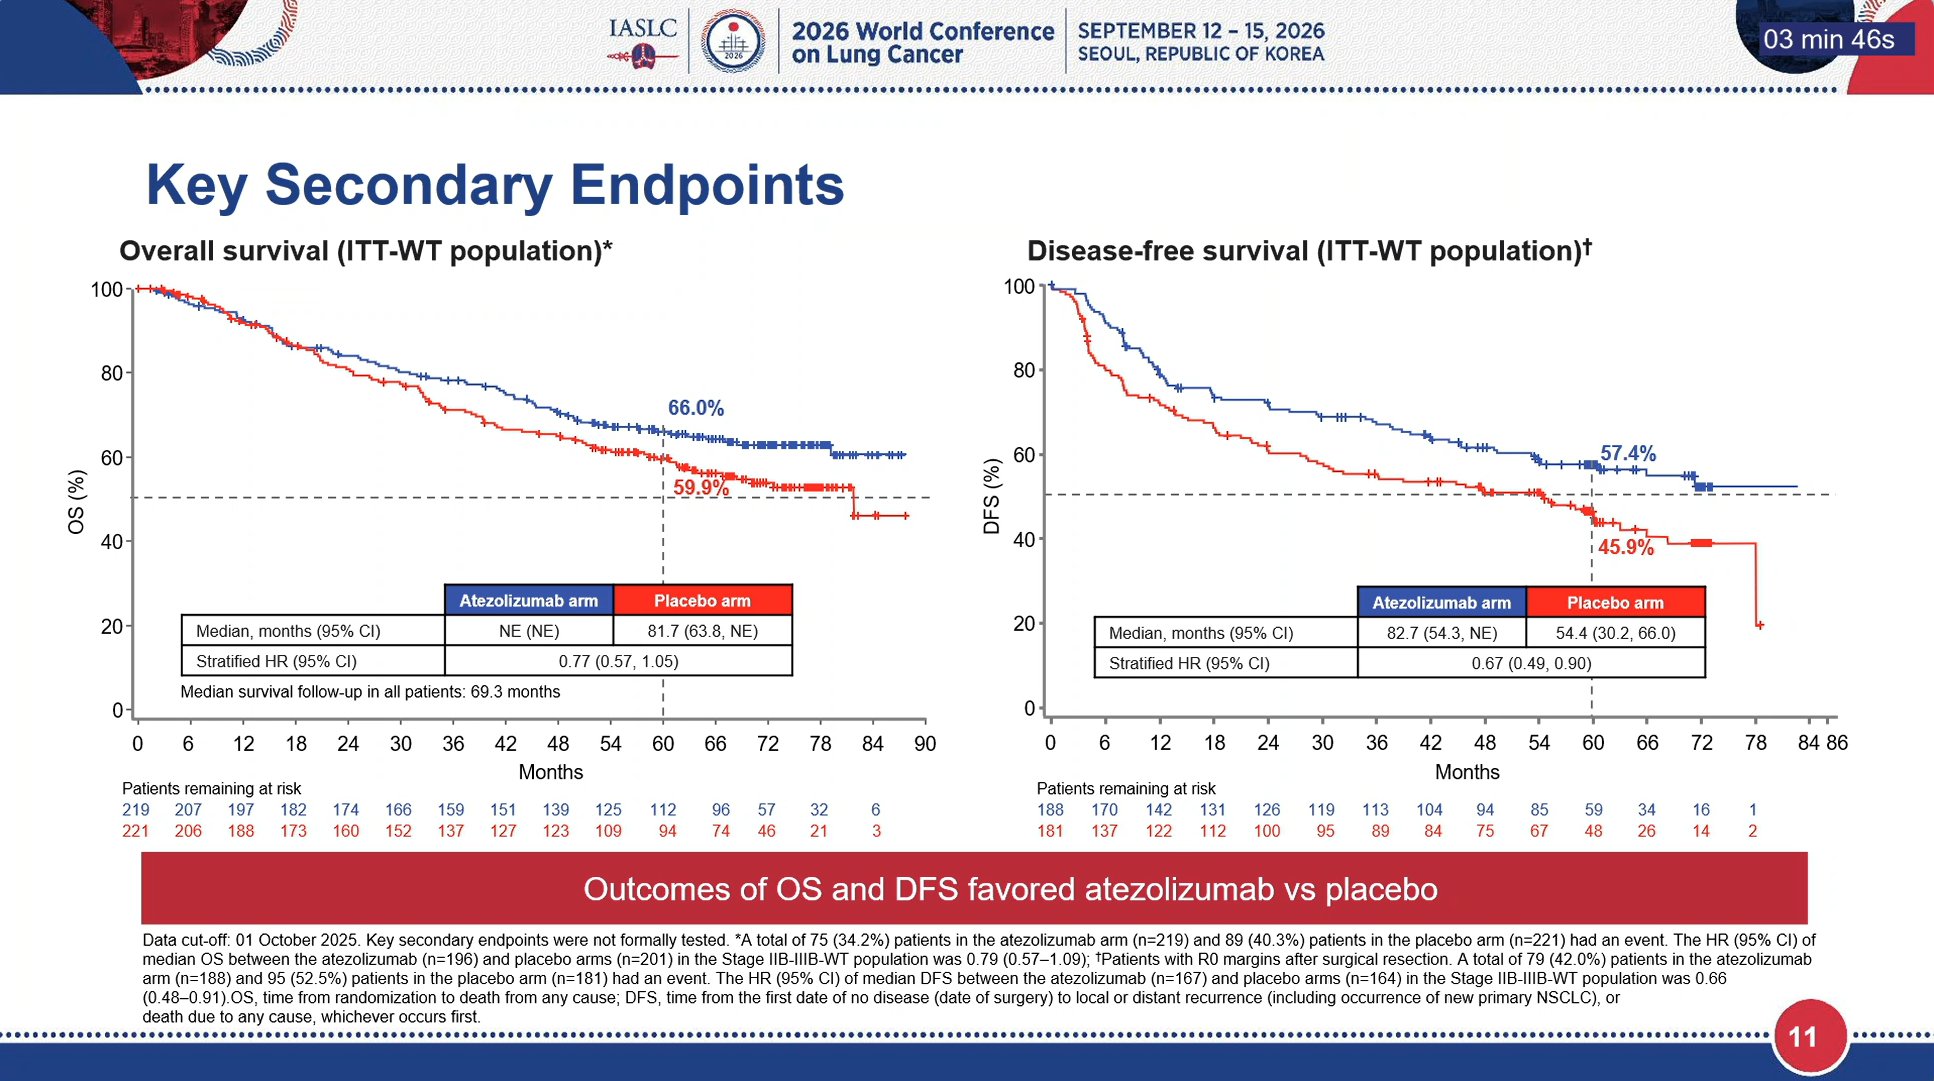
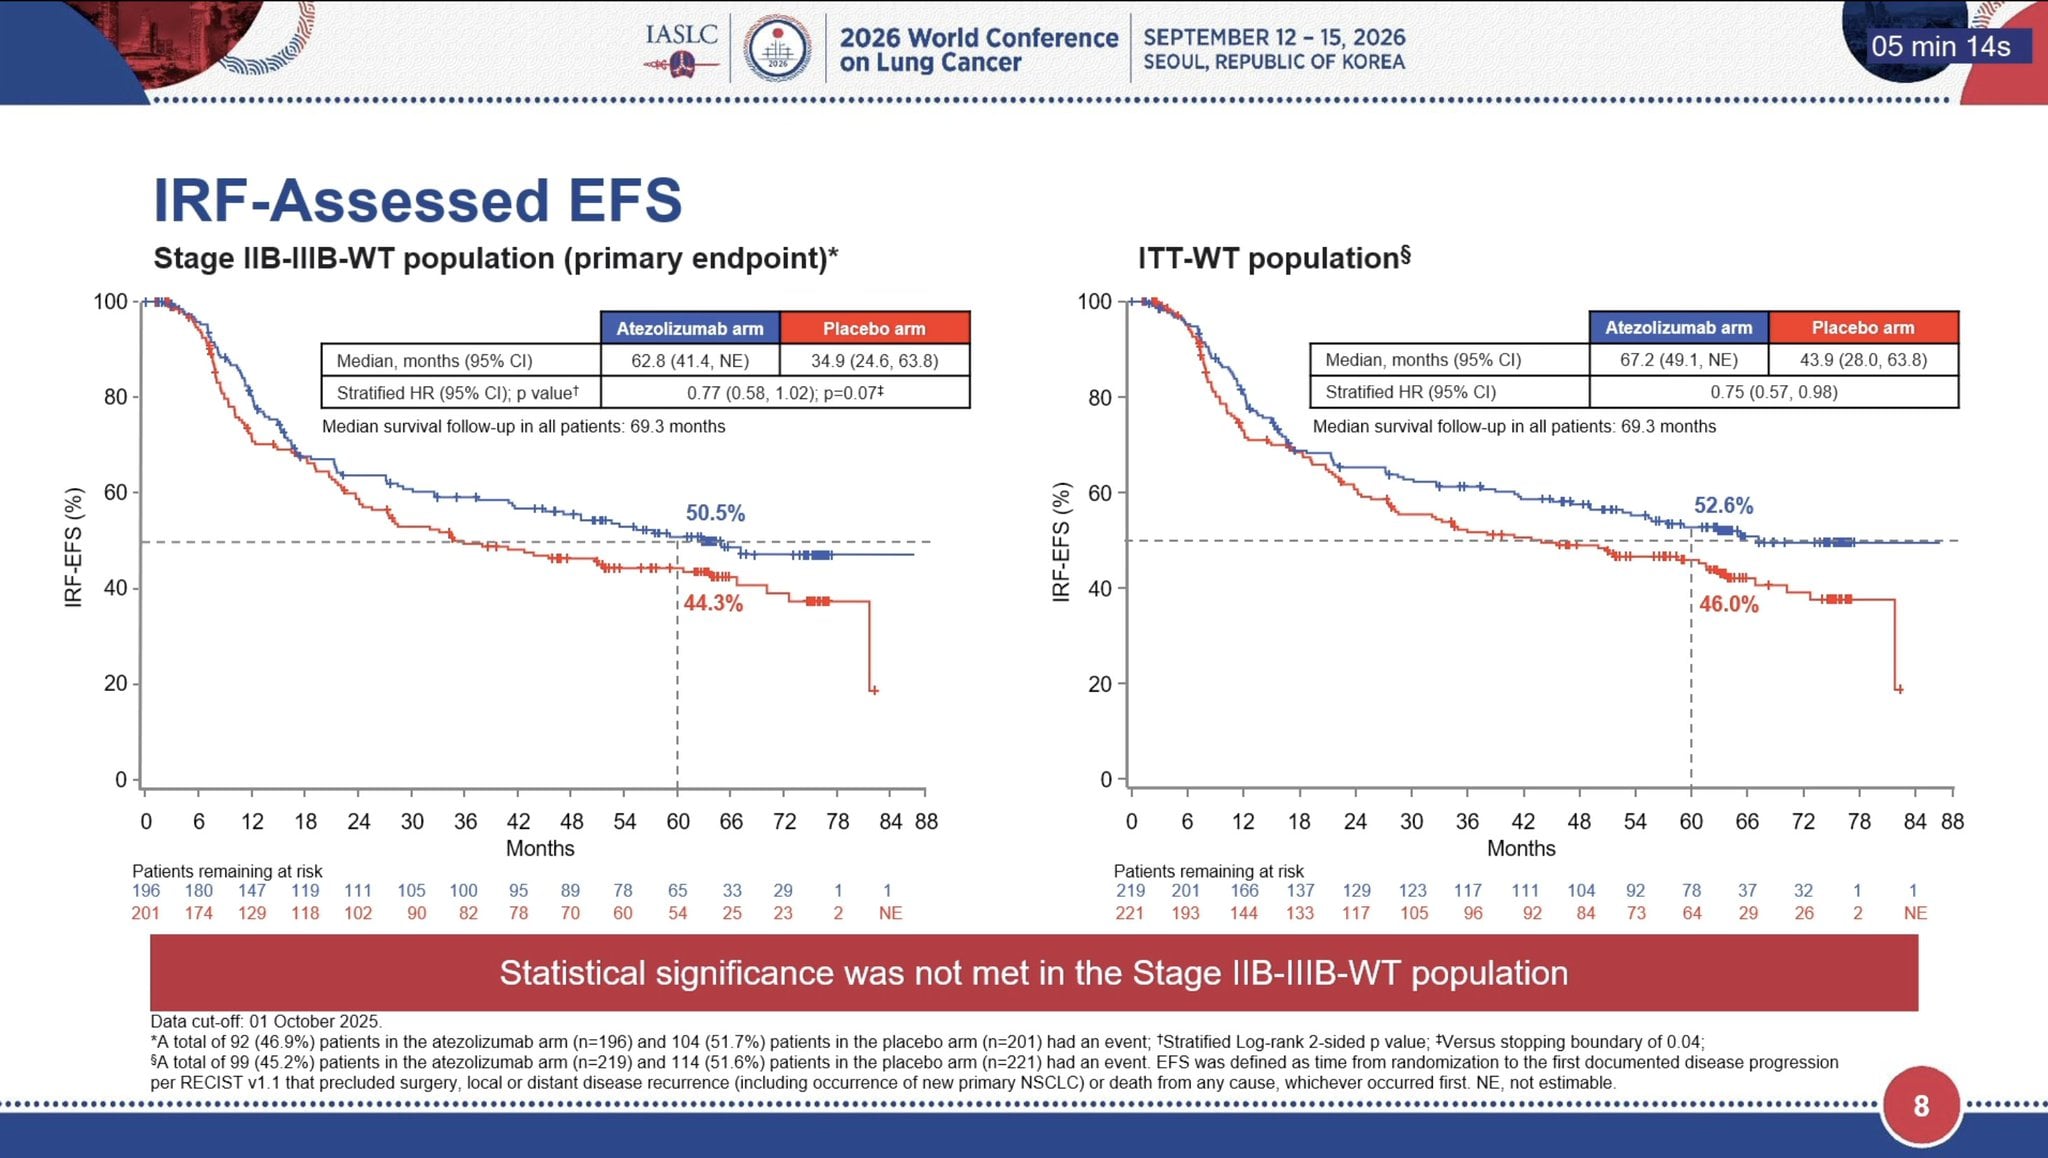
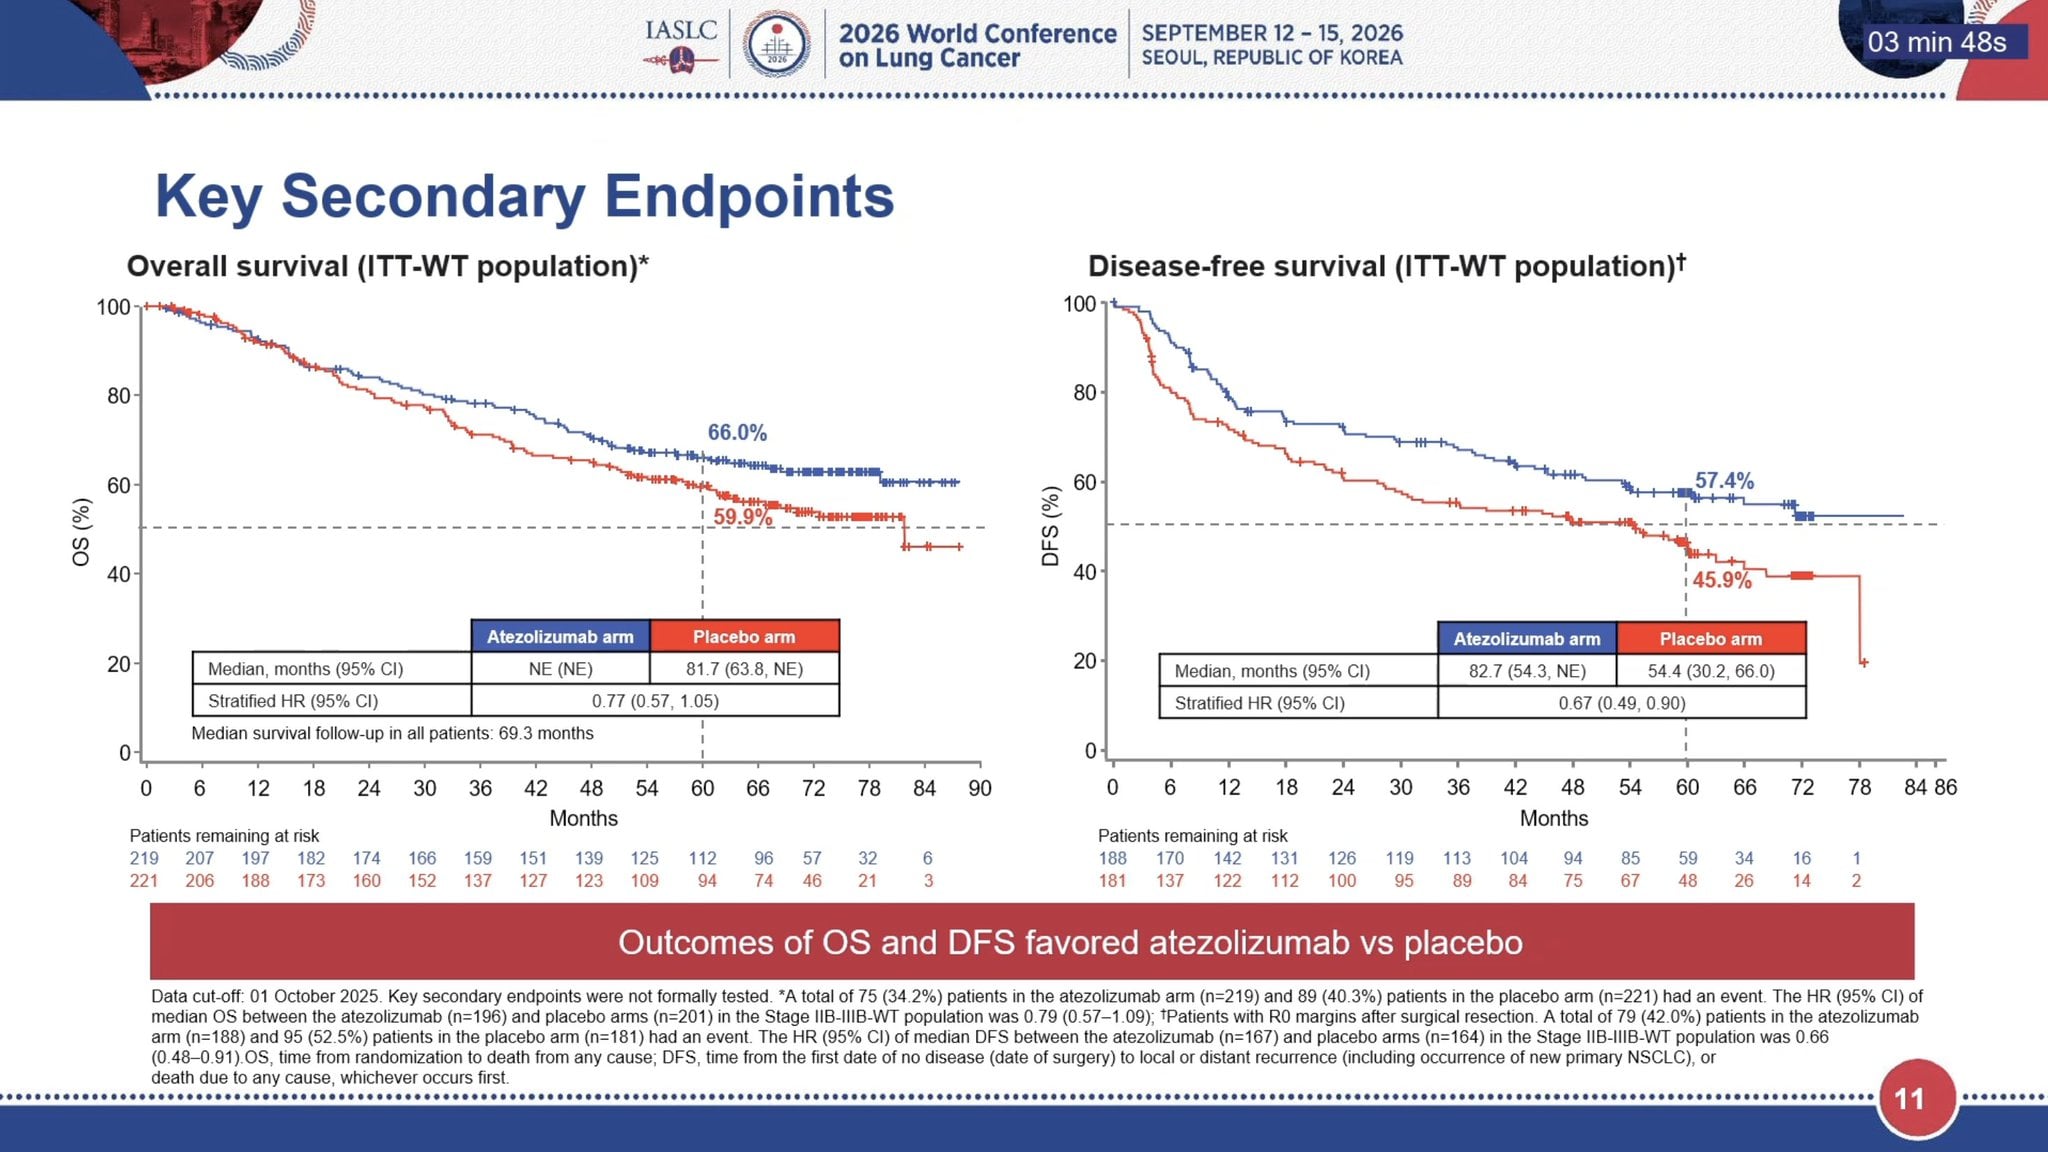
EFS did not meet the prespecified statistical threshold: median EFS 62.8 months (95% CI 41.4–NE) vs 34.9 months (24.6–63.8), HR 0.77 (95% CI 0.58–1.02), p=0.07 against a stopping boundary of 0.04; OS trends likewise non-significant. High surgical-completion rates in both arms, with the control arm noted to over-perform. (Presented primary-endpoint slide, OA04.03, DCO 01-Oct-2025; verbatim KOL posts: Liu, Newsom-Davis)

Pathological response

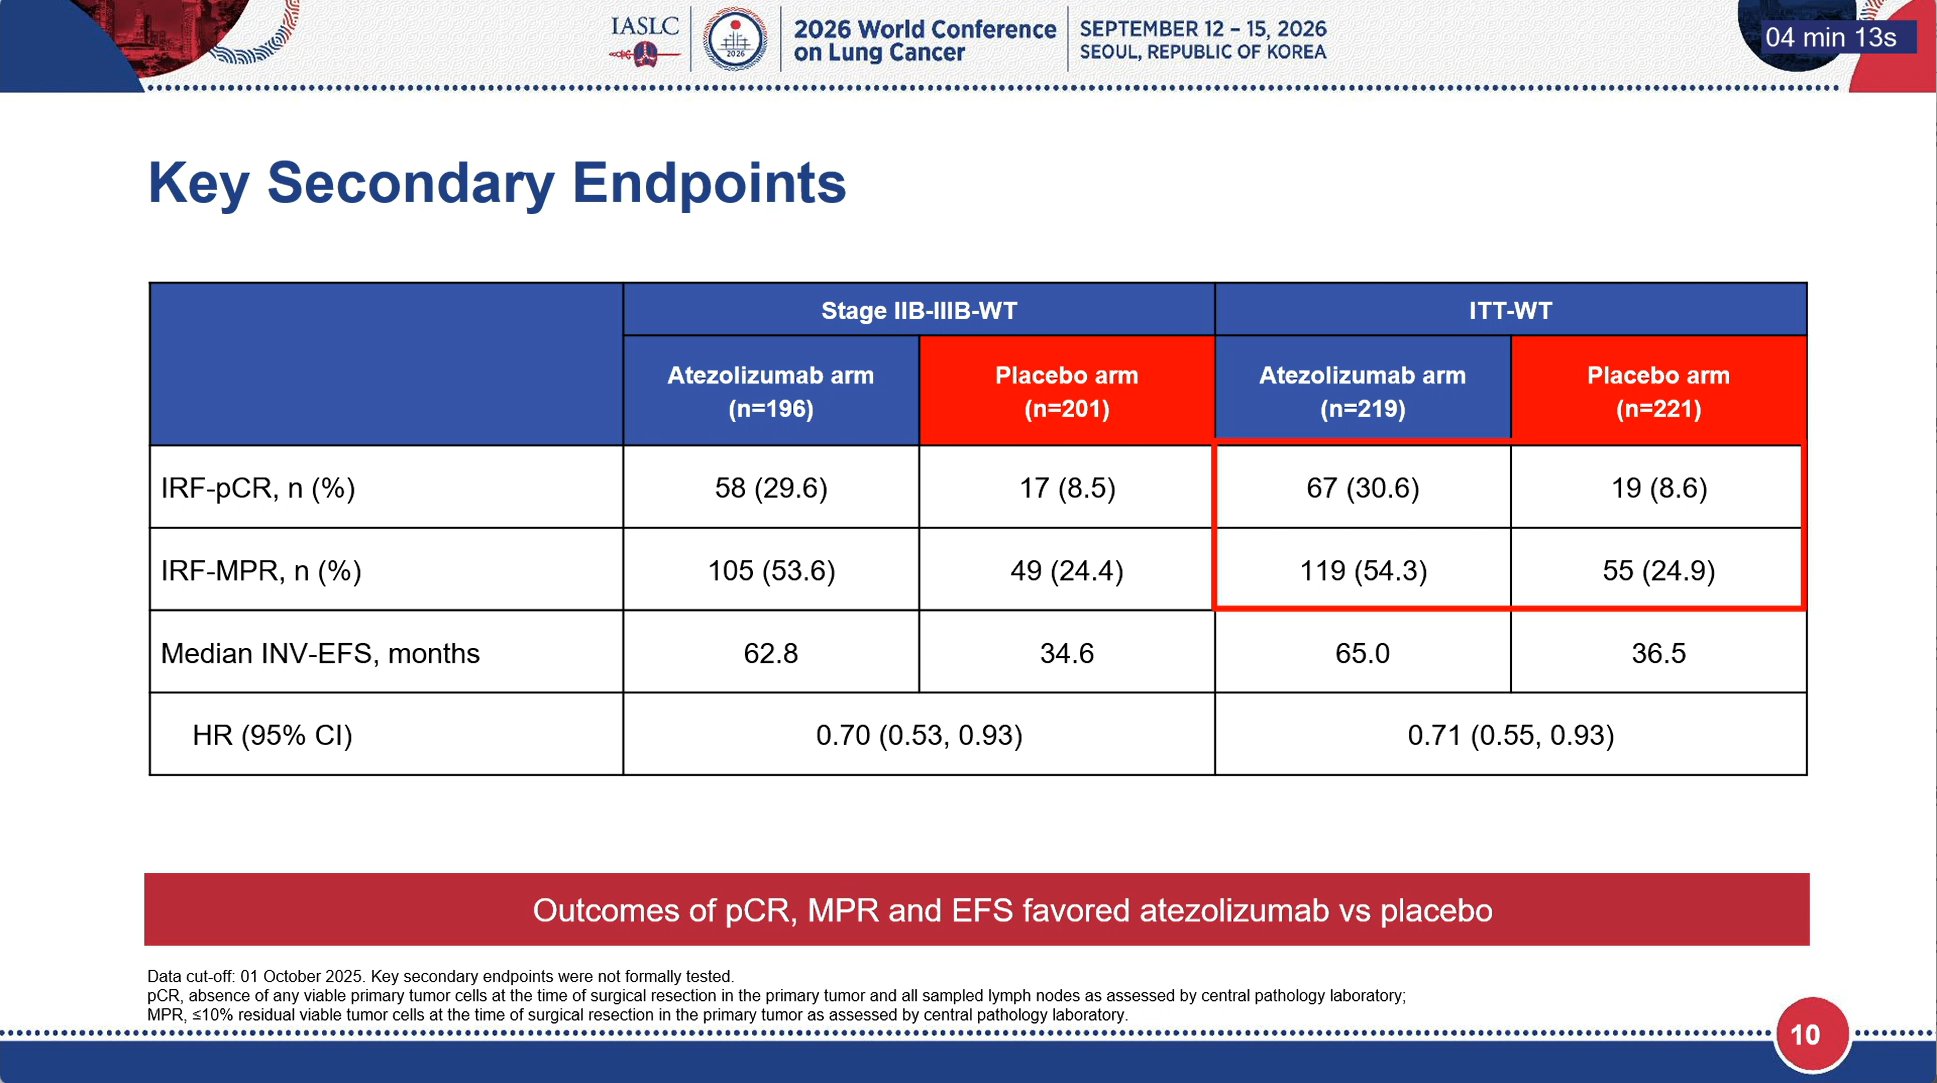
pCR 29.6% versus 8.5% in the stage IIB–IIIB wild-type analysis population (n=196/201), and 30.6% versus 8.6% in the ITT wild-type population (n=219/221) — two populations, not one rounded number. The disconnect between deep pathological response and the missed EFS threshold drove the meeting's discussion. (Presented slides; verbatim KOL captures: Newsom-Davis, Özdoğan)

Regulatory status

⚠️ The perioperative IMpower030 regimen is not approved. Atezolizumab (Tecentriq) holds an adjuvant approval in PD-L1≥1% stage II–IIIA NSCLC after resection and chemo (IMpower010); that indication is unaffected. (FDA labeling context)

KOL pulse

Stephen V. Liu: “Unfortunately, EFS did not meet significance.” Mustafa Özdoğan: “Two negative Phase 3 atezolizumab trials—but two very different messages.” (paired with SWOG/NRG S1914 in The Lancet)

KOLs Discussing IMpower030

Ben Solomon, MD
Ben Solomon, MD
@bensolomon1
Presenter · WCLC 2026 OA04.03
Hidehito HORINOUCHI
Hidehito HORINOUCHI
@HHorinouchi
4,989 impressions
Mustafa Özdoğan, MD
Mustafa Özdoğan, MD
@ozdogan_md
3,546 impressions
Stephen V Liu, MD
Stephen V Liu, MD
@StephenVLiu
3,015 impressions
Diego A. Díaz-García
@diegoadiazg
999 impressions
Dr Riyaz Shah
Dr Riyaz Shah
@DrRiyazShah
807 impressions
Tom Newsom-Davis
Tom Newsom-Davis
@tnewsomdavis
688 impressions

Key Slides & Data

Slides shared by global KOLs, mirrored to our CDN; slide text panels are verbatim Textract OCR.

Hidehito HORINOUCHI
IMpower030 — shared slides
WCLC 2026 · 2026-09-13
View on X
[Slide 1] IASLC 2026 World Conference SEPTEMBER 12 - - 15, 2026 08 min 25s on Lung Cancer SEOUL, REPUBLIC OF KOREA Study Design Double-blind period Open-label period Key eligibility criteria: Atezolizumab 1,200 mg + Surgical Resectable Stage II, IIIA or platinum-based chemotherapy* resection (pCR, MPR PORT Atezolizumab 1,200 mg select IIIB (T3N2) NSCLC (16 cycles) Q3W (8th edition) (4 cycles) Q3W assessment) Eligible for R0 resection with curative intent R 1:1 Adequate pulmonary and cardiac function to Survival follow-up Placebo + Surgical undergo resection resection ALK WT/EGFR WT platinum-based chemotherapy* (pCR, MPR PORT Best supportive care (4 cycles) Q3W ECOG PS 0-1 assessment) Stratification factors: Primary endpoint: Key secondary endpoints: Tumor Stage (II VS IIIA N2- VS IIIA/B N2+) IRF-EFS IRF-pCR INV-EFS Histology (non-squamous vs squamous) IRF-MPR INV-DFS OS Safety *Chemotherapy options: cisplatin + pemetrexed, carboplatin + pemetrexed, or carboplatin + nab-paclitaxel for patients with non-squamous NSCLC; cisplatin + gemcitabine or carboplatin + nab-paclitaxel for patients with squamous NSCLC. Chemotherapy was administered as (per 21-day cycle): cisplatin (75 mg/m² IV) on Day 1; pemetrexed (500 mg/m2 IV) on Day 1; carboplatin (IV, initial target AUC of 6 mg/mL/min) on Day 1; nab-paclitaxel (100 mg/m2 IV) on Days 1, 8, and 15; gemcitabine (1,250 mg/m² IV) on Days 1 and 8. PORT required for patients with positive margins prior to initiating post-operative atezolizumab or best supportive care. PORT mandatory for N2+ disease in V1-6 and optional for patient with N2+ disease at resection after version 7. ALK, anaplastic lymphoma kinase; AUC, area under the curve; DFS, disease-free survival; ECOG PS, Eastern Cooperative Oncology Group performance status; EFS, event-free survival; EGFR, epidermal growth factor receptor; INV, investigator-assessed; IRF, independent review facility-assessed; IV, intravenous; MPR, major pathological response; OS, overall survival; pCR, pathological complete response; PORT, post-operative radiation therapy; Q3W, every 3 weeks; R, randomized; R0, complete resection; WT, wild-type. 4 --- [Slide 2] IASLC 2026 World Conference SEPTEMBER 12 - 15, 2026 05 min 21s 2026 on Lung Cancer SEOUL, REPUBLIC OF KOREA IRF-Assessed EFS Stage IIB-IIIB-WT population (primary endpoint)* ITT-WT population$ 100 100 Atezolizumab arm Placebo arm Atezolizumab arm Placebo arm Median, months (95% CI) 62.8 (41.4, NE) 34.9 (24.6, 63.8) Median, months (95% CI) 67.2 (49.1, NE) 43.9 (28.0, 63.8) 80 Stratified HR (95% CI); p value+ 0.77 (0.58, 1.02); p=0.07 80 Stratified HR (95% CI) 0.75 (0.57, 0.98) Median survival follow-up in all patients: 69.3 months Median survival follow-up in all patients: 69.3 months 60 60 52.6% IRF-EFS (%) 50.5% IRF-EFS (%) 40 40 44.3% 46.0% 20 20 0 0 0 6 12 18 24 30 36 42 48 54 60 66 72 78 84 88 0 6 12 18 24 30 36 42 48 54 60 66 72 78 84 88 Months Months Patients remaining at risk Patients remaining at risk 196 180 147 119 111 105 100 95 89 78 65 33 29 1 1 219 201 166 137 129 123 117 111 104 92 78 37 32 1 1 201 174 129 118 102 90 82 78 70 60 54 25 23 2 NE 221 193 144 133 117 105 96 92 84 73 64 29 26 2 NE Statistical significance was not met in the Stage IIB-IIIB-WT population Data cut-off: 01 October 2025. *A total of 92 (46.9%) patients in the atezolizumab arm (n=196) and 104 (51.7%) patients in the placebo arm (n=201) had an event; +Stratified Log-rank 2-sided p value; Versus stopping boundary of 0.04; $A total of 99 (45.2%) patients in the atezolizumab arm (n=219) and 114 (51.6%) patients in the placebo arm (n=221) had an event. EFS was defined as time from randomization to the first documented disease progression per RECIST v1.1 that precluded surgery, local or distant disease recurrence (including occurrence of new primary NSCLC) or death from any cause, whichever occurred first. NE, not estimable. 8 --- [Slide 3] IASLC 2026 World Conference SEPTEMBER 12 - 15, 2026 04 min 13s on Lung Cancer SEOUL, REPUBLIC OF KOREA Key Secondary Endpoints Stage IIB-IIIB-WT ITT-WT Atezolizumab arm Placebo arm Atezolizumab arm Placebo arm (n=196) (n=201) (n=219) (n=221) IRF-pCR, n (%) 58 (29.6) 17 (8.5) 67 (30.6) 19 (8.6) IRF-MPR, n (%) 105 (53.6) 49 (24.4) 119 (54.3) 55 (24.9) Median INV-EFS, months 62.8 34.6 65.0 36.5 HR (95% CI) 0.70 (0.53, 0.93) 0.71 (0.55, 0.93) Outcomes of pCR, MPR and EFS favored atezolizumab VS placebo Data cut-off: 01 October 2025. Key secondary endpoints were not formally tested. pCR, absence of any viable primary tumor cells at the time of surgical resection in the primary tumor and all sampled lymph nodes as assessed by central pathology laboratory; MPR, <10% residual viable tumor cells at the time of surgical resection in the primary tumor as assessed by central pathology laboratory. 10 --- [Slide 4] IASLC 2026 World Conference SEPTEMBER 12 - 15, 2026 03 min 46s on Lung Cancer SEOUL, REPUBLIC OF KOREA Key Secondary Endpoints Overall survival (ITT-WT population)* Disease-free survival (ITT-WT population)+ 100 100 80 80 66.0% 60 60 57.4% OS (%) 59.9% DFS (%) 40 40 45.9% Atezolizumab arm Placebo arm Atezolizumab arm Placebo arm 20 Median, months (95% CI) NE (NE) 81.7 (63.8, NE) 20 Median, months (95% CI) 82.7 (54.3, NE) 54.4 (30.2, 66.0) Stratified HR (95% CI) 0.77 (0.57, 1.05) Stratified HR (95% CI) 0.67 (0.49, 0.90) Median survival follow-up in all patients: 69.3 months 0 0 0 6 12 18 24 30 36 42 48 54 60 66 72 78 84 90 0 6 12 18 24 30 36 42 48 54 60 66 72 78 84 86 Months Months Patients remaining at risk Patients remaining at risk 219 207 197 182 174 166 159 151 139 125 112 96 57 32 6 188 170 142 131 126 119 113 104 94 85 59 34 16 1 221 206 188 173 160 152 137 127 123 109 94 74 46 21 3 181 137 122 112 100 95 89 84 75 67 48 26 14 2 Outcomes of OS and DFS favored atezolizumab VS placebo Data cut-off: 01 October 2025. Key secondary endpoints were not formally tested. *A total of 75 (34.2%) patients in the atezolizumab arm (n=219) and 89 (40.3%) patients in the placebo arm (n=221) had an event. The HR (95% CI) of median os between the atezolizumab (n=196) and placebo arms (n=201) in the Stage IIB-IIIB-WT population was 0.79 (0.57-1.09); Patients with R0 margins after surgical resection. A total of 79 (42.0%) patients in the atezolizumab arm (n=188) and 95 (52.5%) patients in the placebo arm (n=181) had an event. The HR (95% CI) of median DFS between the atezolizumab (n=167) and placebo arms (n=164) in the Stage IIB-IIIB-WT population was 0.66 (0.48-0.91).OS, time from randomization to death from any cause; DFS, time from the first date of no disease (date of surgery) to local or distant recurrence (including occurrence of new primary NSCLC), or death due to any cause, whichever occurs first. 11
Stephen V Liu, MD
Stephen V Liu, MD@StephenVLiu
IMpower030 — shared slides
WCLC 2026 · 2026-09-13
View on X
[Slide 1] IASLC 2026 World Conference at 2276 on Lung Cancer - KALC SEPTEMBER 12 - 15, 2026 I SEOUL, REPUBLIC OF KOREA SCIENCE WITHOUT BOUNDARIES: UNITING THE WORLD AGAINST THORACIC CANCER --- [Slide 2] IASLC 2026 World Conference SEPTEMBER 12 - 15, 2026 08 min 11s 2026 on Lung Cancer SEOUL, REPUBLIC OF KOREA Study Design Double-blind period Open-label period Key eligibility criteria: Atezolizumab 1,200 mg + Surgical Resectable Stage II, IIIA or platinum-based chemotherapy* resection (pCR, MPR PORT Atezolizumab 1,200 mg select IIIB (T3N2) NSCLC (8th edition) (4 cycles) Q3W (16 cycles) Q3W assessment) Eligible for R0 resection with curative intent R 1:1 Adequate pulmonary and cardiac function to Survival follow-up Placebo + Surgical undergo resection resection ALK WT/EGFR WT platinum-based chemotherapy* (pCR, MPR PORT Best supportive care ECOG PS 0-1 (4 cycles) Q3W assessment) Stratification factors: Primary endpoint: Key secondary endpoints: Tumor Stage (II VS IIIA N2- VS IIIA/B N2+) IRF-EFS IRF-pCR INV-EFS Histology (non-squamous vs squamous) IRF-MPR INV-DFS OS Safety *Chemotherapy options: cisplatin + pemetrexed, carboplatin + pemetrexed, or carboplatin + nab-paclitaxel for patients with non-squamous NSCLC; cisplatin + gemcitabine or carboplatin + nab-paclitaxel for patients with squamous NSCLC. Chemotherapy was administered as (per 21-day cycle): cisplatin (75 mg/m² IV) on Day 1; pemetrexed (500 mg/m² IV) on Day 1; carboplatin (IV, initial target AUC of 6 mg/mL/min) on Day 1; nab-paclitaxel (100 mg/m² IV) on Days 1, 8, and 15; gemcitabine (1,250 mg/m² IV) on Days 1 and 8. PORT required for patients with positive margins prior to initiating post-operative atezolizumab or best supportive care. PORT mandatory for N2+ disease in V1-6 and optional for patient with N2+ disease at resection after version 7. ALK, anaplastic lymphoma kinase; AUC, area under the curve; DFS, disease-free survival; ECOG PS, Eastern Cooperative Oncology Group performance status; EFS, event-free survival; EGFR, epidermal growth factor receptor; INV, investigator-assessed; IRF, independent review facility-assessed; IV, intravenous; MPR, major pathological response; OS, overall survival; pCR, pathological complete response; PORT, post-operative radiation therapy; Q3W, every 3 weeks; R, randomized; R0, complete resection; WT, wild-type. 4 --- [Slide 3] IASLC 2026 World Conference SEPTEMBER 12 - 15, 2026 05 min 14s 2026 on Lung Cancer SEOUL, REPUBLIC OF KOREA IRF-Assessed EFS Stage IIB-IIIB-WT population (primary endpoint)* ITT-WT population$ 100 100 Atezolizumab arm Placebo arm Atezolizumab arm Placebo arm Median, months (95% CI) 62.8 (41.4, NE) 34.9 (24.6, 63.8) Median, months (95% CI) 67.2 (49.1, NE) 43.9 (28.0, 63.8) 80 Stratified HR (95% CI); p value+ 0.77 (0.58, 1.02); p=0.07 80 Stratified HR (95% CI) 0.75 (0.57, 0.98) Median survival follow-up in all patients: 69.3 months Median survival follow-up in all patients: 69.3 months 60 60 52.6% IRF-EFS (%) 50.5% IRF-EFS (%) 40 40 44.3% 46.0% 20 20 0 0 0 6 12 18 24 30 36 42 48 54 60 66 72 78 84 88 0 6 12 18 24 30 36 42 48 54 60 66 72 78 84 88 Months Months Patients remaining at risk Patients remaining at risk 196 180 147 119 111 105 100 95 89 78 65 33 29 1 1 219 201 166 137 129 123 117 111 104 92 78 37 32 1 1 201 174 129 118 102 90 82 78 70 60 54 25 23 2 NE 221 193 144 133 117 105 96 92 84 73 64 29 26 2 NE Statistical significance was not met in the Stage IIB-IIIB-WT population Data cut-off: 01 October 2025. *A total of 92 (46.9%) patients in the atezolizumab arm (n=196) and 104 (51.7%) patients in the placebo arm (n=201) had an event; TStratified Log-rank 2-sided p value; Versus stopping boundary of 0.04; $A total of 99 (45.2%) patients in the atezolizumab arm (n=219) and 114 (51.6%) patients in the placebo arm (n=221) had an event. EFS was defined as time from randomization to the first documented disease progression per RECIST v1.1 that precluded surgery, local or distant disease recurrence (including occurrence of new primary NSCLC) or death from any cause, whichever occurred first. NE, not estimable. 8 --- [Slide 4] IASLC 2026 World Conference SEPTEMBER 12 - 15, 2026 03 min 48s on Lung Cancer SEOUL, REPUBLIC OF KOREA Key Secondary Endpoints Overall survival (ITT-WT population)* Disease-free survival (ITT-WT population)+ 100 100 80 80 66.0% 60 60 57.4% OS (%) 59.9% DFS (%) 40 40 45.9% Atezolizumab arm Placebo arm Atezolizumab arm Placebo arm 20 Median, months (95% CI) NE (NE) 81.7 (63.8, NE) 20 Median, months (95% CI) 82.7 (54.3, NE) 54.4 (30.2, 66.0) Stratified HR (95% CI) 0.77 (0.57, 1.05) Stratified HR (95% CI) 0.67 (0.49, 0.90) Median survival follow-up in all patients: 69.3 months 0 0 0 6 12 18 24 30 36 42 48 54 60 66 72 78 84 90 0 6 12 18 24 30 36 42 48 54 60 66 72 78 84 86 Months Months Patients remaining at risk Patients remaining at risk 219 207 197 182 174 166 159 151 139 125 112 96 57 32 6 188 170 142 131 126 119 113 104 94 85 59 34 16 1 221 206 188 173 160 152 137 127 123 109 94 74 46 21 3 181 137 122 112 100 95 89 84 75 67 48 26 14 2 Outcomes of OS and DFS favored atezolizumab vs placebo Data cut-off: 01 October 2025. Key secondary endpoints were not formally tested. *A total of 75 (34.2%) patients in the atezolizumab arm (n=219) and 89 (40.3%) patients in the placebo arm (n=221) had an event. The HR (95% CI) of median OS between the atezolizumab (n=196) and placebo arms (n=201) in the Stage IIB-IIIB-WT population was 0.79 (0.57-1.09); Patients with R0 margins after surgical resection. A total of 79 (42.0%) patients in the atezolizumab arm (n=188) and 95 (52.5%) patients in the placebo arm (n=181) had an event. The HR (95% CI) of median DFS between the atezolizumab (n=167) and placebo arms (n=164) in the Stage IIB-IIIB-WT population was 0.66 (0.48-0.91).OS, time from randomization to death from any cause; DFS, time from the first date of no disease (date of surgery) to local or distant recurrence (including occurrence of new primary NSCLC), or death due to any cause, whichever occurs first. 11

What Physicians Said

Hidehito HORINOUCHI
Hidehito HORINOUCHI@HHorinouchi

🆙#WCLC26 #LCSM OA04.03 🔥Final Analysis of the Phase 3 IMpower030 Study: Perioperative Atezolizumab + Chemotherapy in Resectable Stage II-IIIB NSCLC 🎙️@bensolomon1 🎯EFS HR 0.77 (95%CI 0.58-1.02) 🎯OS HR 0.77 (95%CI 0.57-1.07) 🎯pCR Atezo 30.6% vs. Placebo 8.6% 🔢OA04.03 ☑️NCT03456063 🔗 https://t.co/rN1vqVmvgD @OncoAlert @Larvol @IASLC

👀 4,9892026-09-13
Mustafa Özdoğan, MD
Mustafa Özdoğan, MD@ozdogan_md

Two negative Phase 3 atezolizumab trials—but two very different messages. IMpower030 missed its statistical threshold despite a strong efficacy signal. S1914 showed no survival gain and greater toxicity. In early-stage NSCLC, context matters. #WCLC26 #LungCancer #NSCLC #Immunotherapy

👀 3,5462026-09-12
Stephen V Liu, MD
Stephen V Liu, MD@StephenVLiu

Dr. @bensolomon1 presents IMpower 030: perioperative atezolizumab + chemo in resectable NSCLC at #WCLC26. Unfortunately, EFS did not meet significance. Trends present for EFS and OS but not significant. High rates of surgery in both arms ~90% and placebo arm performed better than expected. Disappointing negative results.

👀 3,0152026-09-13
Diego A. Díaz-García
Diego A. Díaz-García@diegoadiazg

🫁 IMpower030: perioperative atezolizumab did not meet its primary endpoint in resectable NSCLC. @bensolomon1 Despite numerical improvements with atezolizumab + chemotherapy: • EFS: 62.8 vs 34.9 months • pCR: 29.6% vs 8.5% • MPR: 53.6% vs 24.4% The study did not demonstrate a statistically significant EFS benefit, although other efficacy endpoints numerically favored the experimental arm. #CánCare #NSCLC #ThoracicOncology #Immunotherapy #Atezolizumab #WCLC @IASLC

👀 9992026-09-13
Dr Riyaz Shah
Dr Riyaz Shah@DrRiyazShah

IMpower030: final analysis; hierarchical stats testing (grrrrr); #WCLC26 https://t.co/y2AfHQblIW

👀 8072026-09-13
Tom Newsom-Davis
Tom Newsom-Davis@tnewsomdavis

IMpower030: periop Atezolizumab 👉 Standard neo-adj chemoIO + adj immuno design ❌ Did not meet EFS 1’ end-point ✅ pCR 30% 🔺Control arm over-performed ✅Reflected by 🔼 resection rates 🤔 Missing 1’ end-point likely reflects tighter pt selection #WCLC26 https://t.co/LcrO3brX8m

👀 6882026-09-13

About the IMpower030 Trial

IMpower030 was one of the last first-generation perioperative chemo-immunotherapy phase IIIs to read out, arriving after KEYNOTE-671, CheckMate-77T and AEGEAN had already reshaped the resectable landscape. Its final analysis at WCLC 2026 landed as the statistical miss with a real pathological signal: pCR more than tripled, EFS and OS trends favored atezolizumab, but the prespecified threshold was not met — partly, physicians noted, because the control arm over-performed against historical expectations.

The discussion paired it with SWOG/NRG S1914 (SBRT ± atezolizumab, published the same week in The Lancet, also negative) as “same label, different clinical meaning”: a reminder that context, staging mix and comparator behavior — not a class effect — decide these trials. The perioperative field's standard remains with the approved pembrolizumab-, nivolumab- and durvalumab-based regimens.

Trial Methodology & Results

Study Design

Phase III randomized: perioperative atezolizumab + neoadjuvant platinum chemo vs neoadjuvant chemo alone; resectable stage II–IIIB NSCLC; N=453; EFS primary. (WCLC 2026 OA04.03 via verbatim captures)

Population

Resectable stage II–IIIB NSCLC. (WCLC 2026 OA04.03)

Outcome

EFS threshold not met (trends for EFS and OS, not significant); pCR 29.6% vs 8.5%; high resection rates in both arms. (Verbatim KOL captures)

Context

Read out after KEYNOTE-671 / CheckMate-77T / AEGEAN set the perioperative standard; discussed alongside SWOG/NRG S1914 (Lancet, negative) at the meeting.

Event-free survival — threshold not met

The final analysis missed the primary endpoint: median EFS 62.8 months (95% CI 41.4–NE) with perioperative atezolizumab versus 34.9 months (24.6–63.8) with chemotherapy alone, HR 0.77 (95% CI 0.58–1.02), p=0.07 against a stopping boundary of 0.04 — a favorable trend that did not reach the prespecified threshold; OS trends were likewise non-significant. Physicians attributed part of the miss to an over-performing control arm, reflected in high surgery rates in both arms. Note the enrolled N of 453 differs from the analysis populations (stage IIB–IIIB WT n=397; ITT-WT n=440). (WCLC 2026 OA04.03 presented primary-endpoint slide, DCO 01-Oct-2025; verbatim KOL captures: Liu, Newsom-Davis)

EFS HR 0.77 (0.58–1.02), p=0.07 vs boundary 0.04 · medians 62.8 vs 34.9 mo
Source: WCLC 2026 OA04.03 (verbatim KOL captures) ↗

Pathological response — the real signal

pCR was 29.6% versus 8.5% in the stage IIB–IIIB wild-type population (n=196/201), and 30.6% versus 8.6% in the ITT wild-type population (n=219/221) — deep responses that did not convert into a statistically significant EFS win, the disconnect that framed the meeting's “negative on the endpoint, active on the tumor” debate. (Presented slides; verbatim KOL captures: Newsom-Davis, Özdoğan)

pCR 29.6% vs 8.5%
Source: WCLC 2026 OA04.03 (verbatim KOL captures) ↗

WCLC 2026: Live KOL Reaction

Physician posts about this trial captured live during the IASLC 2026 World Conference on Lung Cancer (Seoul, September 12–15). Quotes are verbatim; each card links to the original post. Last updated 2026-09-15.

IMpower030 FAQ

What is the IMpower030 trial?

IMpower030 (NCT03456063) is a Roche/Genentech phase III randomized trial of perioperative atezolizumab (Tecentriq) added to neoadjuvant platinum-based chemotherapy, versus neoadjuvant chemotherapy alone, in 453 patients with resectable stage II–IIIB NSCLC, with event-free survival as the primary endpoint.

What did the final analysis show?

Presented at WCLC 2026 (OA04.03): EFS trends favored the atezolizumab arm but did not meet the prespecified statistical threshold, and OS trends were also non-significant — despite a pathological complete response rate of 29.6% versus 8.5%. Surgery rates were high in both arms, with the control arm noted to over-perform.

Does this change atezolizumab's approvals?

No. The perioperative IMpower030 regimen was never approved and is not advancing on this data. Atezolizumab's existing adjuvant approval in PD-L1-positive stage II–IIIA NSCLC after resection and chemotherapy (based on IMpower010) is unaffected.

Why do physicians call it 'statistically negative, clinically suggestive'?

Because the biological activity was evident — pCR more than tripled and event-free survival trended in favor — but the trial missed its statistical threshold, partly due to strong control-arm performance. It reads as a timing-and-context miss in a field whose standard was already set by other perioperative regimens.

What is SWOG/NRG S1914 and why was it discussed together?

S1914, published in The Lancet the same week, tested SBRT with or without atezolizumab in high-risk early NSCLC and was also negative (2-year OS 82% in both arms) with more toxicity. KOLs paired the two as 'same label, different clinical meaning' — two negative atezolizumab trials whose lessons are about setting and selection, not a class effect.

Key KOL Sentiments

KOLComment (verbatim)SentimentDate
Hidehito HORINOUCHI
@HHorinouchi
🆙#WCLC26 #LCSM OA04.03 🔥Final Analysis of the Phase 3 IMpower030 Study: Perioperative Atezolizumab + Chemotherapy in Resectable Stage II-IIIB NSCLC 🎙️@bensolomon1 🎯EFS HR 0.77 (95%CI 0.58-1.02) 🎯OS HR 0.77 (95%CI 0.57-1.07) 🎯pCR Atezo 30.6% vs. Placebo 8.6% 🔢OA04.03 ☑️NCT03456063 🔗 https://t.co/rN1vqVmvgD @OncoAlert @Larvol @IASLCNeutral2026-09-13
Dr Riyaz Shah
@DrRiyazShah
IMpower030: final analysis; hierarchical stats testing (grrrrr); #WCLC26 https://t.co/y2AfHQblIWNeutral2026-09-13
Mustafa Özdoğan, MD
@ozdogan_md
Two negative Phase 3 atezolizumab trials—but two very different messages. IMpower030 missed its statistical threshold despite a strong efficacy signal. S1914 showed no survival gain and greater toxicity. In early-stage NSCLC, context matters. #WCLC26 #LungCancer #NSCLC #ImmunotherapyNegative2026-09-12
Stephen V Liu, MD
@StephenVLiu
Dr. @bensolomon1 presents IMpower 030: perioperative atezolizumab + chemo in resectable NSCLC at #WCLC26. Unfortunately, EFS did not meet significance. Trends present for EFS and OS but not significant. High rates of surgery in both arms ~90% and placebo arm performed better than expected. Disappointing negative results.Negative2026-09-13
Diego A. Díaz-García
@diegoadiazg
🫁 IMpower030: perioperative atezolizumab did not meet its primary endpoint in resectable NSCLC. @bensolomon1 Despite numerical improvements with atezolizumab + chemotherapy: • EFS: 62.8 vs 34.9 months • pCR: 29.6% vs 8.5% • MPR: 53.6% vs 24.4% The study did not demonstrate a statistically significant EFS benefit, although other efficacy endpoints numerically favored the experimental arm. #CánCare #NSCLC #ThoracicOncology #Immunotherapy #Atezolizumab #WCLC @IASLCNegative2026-09-13
Tom Newsom-Davis
@tnewsomdavis
IMpower030: periop Atezolizumab 👉 Standard neo-adj chemoIO + adj immuno design ❌ Did not meet EFS 1’ end-point ✅ pCR 30% 🔺Control arm over-performed ✅Reflected by 🔼 resection rates 🤔 Missing 1’ end-point likely reflects tighter pt selection #WCLC26 https://t.co/LcrO3brX8mNegative2026-09-13
Free Access · KOL Pulse Intelligence

Track oncology’s top KOLs in your specialty

Create a free account, pick the tumor types you cover, and go beyond the tweet — the intelligence pharma teams use to map influence and prepare for engagement:

  • Enhanced KOL profiles
  • Pharma influence & potential advisory-board patterns
  • 2025 Open Payments financial analysis
  • Social-media sentiment & trend signals
Get free access — pick your specialty
Choose the tumor types you follow. No cost, unsubscribe anytime.

Compiled and reviewed by the KOL Pulse research team, led by Brian Shields, Founder, KOL Pulse. Last updated September 13, 2026. Every statistic carries its source label in place; every quote is verbatim from the physician's own post.