● LIVE #ESMO26 live from Madrid, Oct 23–27 — today’s highlights, trending trials and physician reactions Follow ESMO 2026 live →
KOL Pulse · AI-Native Trial Intelligence

INTerpath-001 Trial

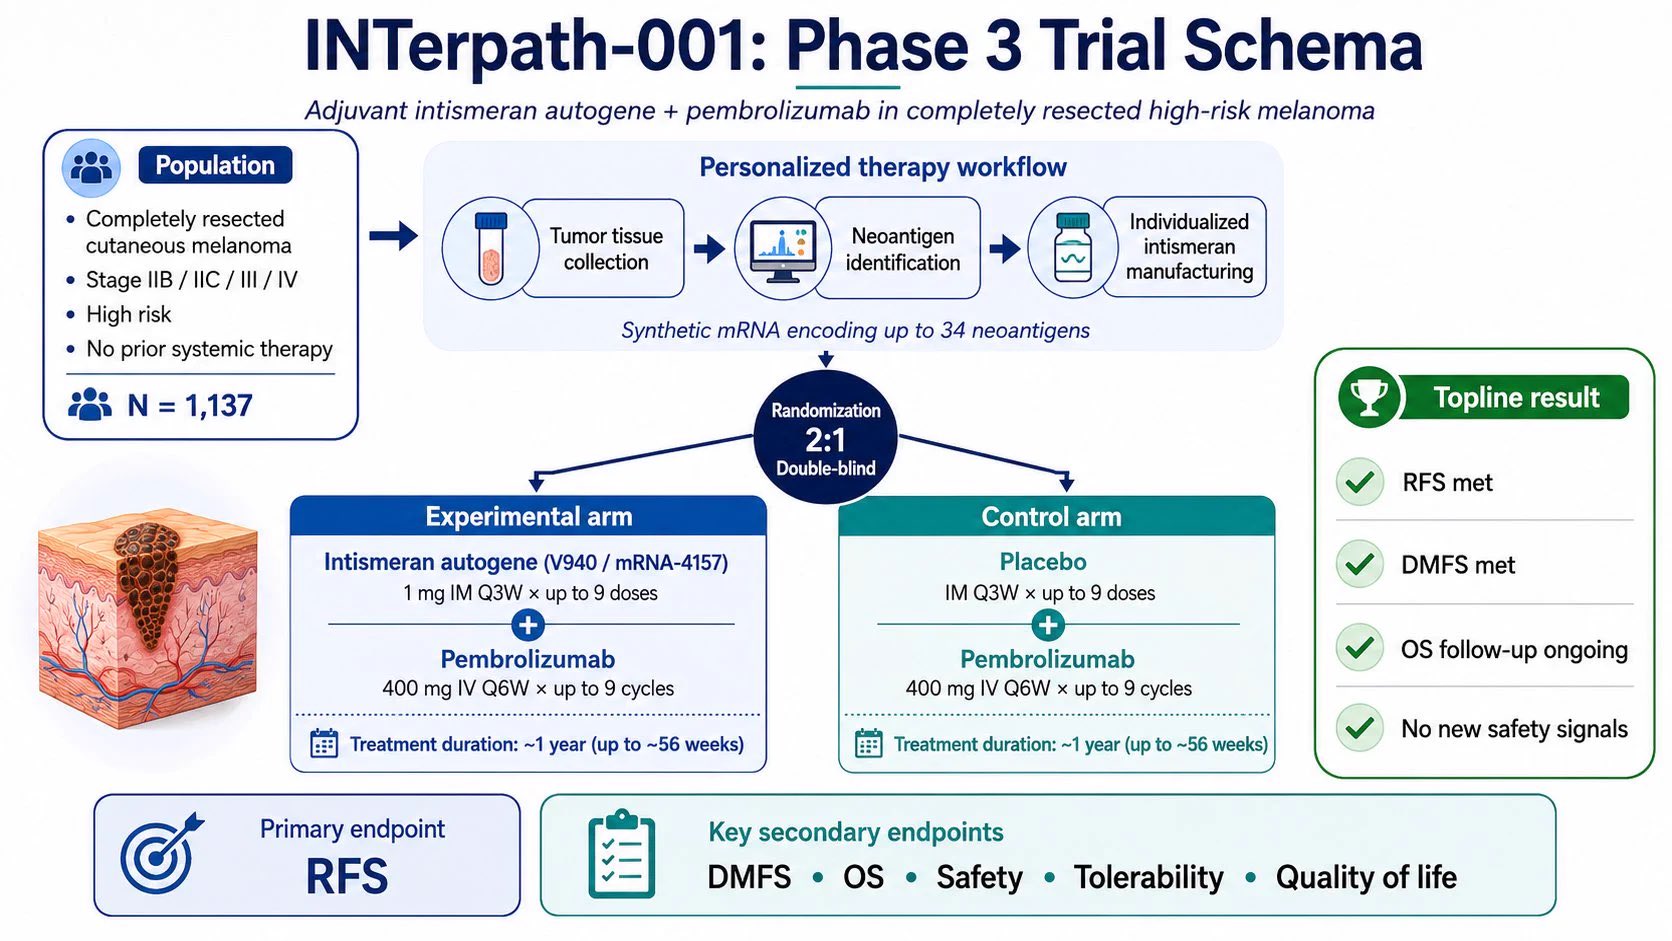
INTerpath-001 (NCT05933577) is the Phase 3, double-blind trial of adjuvant intismeran autogene (V940/mRNA-4157, Merck & Moderna) plus pembrolizumab (Keytruda) versus pembrolizumab alone in completely resected stage IIB–IV melanoma. On August 19, 2026 it met BOTH endpoints — recurrence-free survival and distant metastasis-free survival — the first positive Phase 3 ever for an individualized neoantigen therapy. Presented at ESMO 2026 (LBA1, October 24; DCO 30-Jun-2026, median follow-up 24.6 mo): RFS HR 0.58 (95% CI 0.45–0.75), 24-month RFS 82.2% vs 70.0%; DMFS HR 0.62 (0.45–0.85). Overall survival is immature and did not meet its prespecified significance boundary (HR 0.77, 95% CI 0.45–1.31; P=0.33). Investigational.

Phase 3 · NCT05933577 · n=1,137 Resected stage IIB–IV melanoma RFS met · DMFS met · OS immature First positive Ph3 for an individualized neoantigen therapy ⚠ Investigational Presented: ESMO 2026 Presidential Symposium · LBA1 · Oct 24, 2026
See the KOL Coverage

Physician reactions and the comparator debate

After the abstract release, several physicians compared INTerpath-001 with SWOG S1801, where neoadjuvant plus adjuvant pembrolizumab was tested against adjuvant pembrolizumab alone. Others pointed out that the two trials enrolled different populations and used different endpoints. The posts below are full and verbatim, newest first, and linked to the originals; they run from ESMO 2026 week (October 17–24, 2026) back to the August 2026 topline announcement.

Prof.Dr.Erdinç Nayır
Prof.Dr.Erdinç Nayır@dronkoloji
𝕏

🔴 Avrupa Onkoloji Kongresi (ESMO 2026)’nde açıklandı! Malign melanomda immünoterapiye, kişiye özel hazırlanmış mRNA kanser aşısının eklenmesi kanserin tekrarlaması veya ölüm riskini %42 azaldı Uzak metastaz riskini de %38 azaldı. Faz 3 INTerpath-001 çalışması. #cancer #oncology #ESMO2026

1.3K views 24 likes3 RT 2026-10-24
Hidehito HORINOUCHI
Hidehito HORINOUCHI@HHorinouchi
𝕏

🆙#ESMO26 Presidential Symposium I 🔥INTerpath-001: Phase 3 Study of the mRNA-Based Individualized Neoantigen Therapy (INT) Intismeran Autogene (Intismeran) Plus Pembrolizumab (Pembro) vs Pembro Alone for Adjuvant Treatment of Resected Stage IIB-IV Melanoma (MEL) 🎙️ @ProfGLongMIA 🔢LBA1 🎯Met Primary Endpoint: Significantly Improved RFS 🎯24-Mo 82.2% vs 70.0%, HR 0.58 🎯DMFS HR 0.62 🎯Grade≥3 AEs 23.6% vs 20.3% ☑️NCT05933577 🔗 https://t.co/Lb6tzuMm0z @OncoAlert @Larvol @myESMO

379 views 7 likes5 RT 2026-10-24
Tejas Patil
Tejas Patil@TejasPatilMD
𝕏

🌟AND finally, #ESMO26 wouldn't be complete without some of the HEAVY hitters. I expect these data to change practice! 1⃣Tarlatamab plus durvalumab (durva) vs durva as 1L maintenance (1LM) therapy following durva, platinum, and etoposide (1L durva + EP) in extensive-stage small cell lung cancer (ES-SCLC): Primary analysis of the phase 3 DeLLphi-305 trial. I fully expect this trial to establish DLL3 TCE as the dominant first line strategy in SCLC and will likely be practice changing. 2⃣Krascendo 1: Efficacy and safety of divarasib (diva) vs sotorasib (soto) or adagrasib (ada) in previously treated locally advanced or metastatic KRAS G12C-mutated NSCLC. Given the evolution of KRAS G12Ci in this space, what is notable here is the direct prospective comparison to current KRAS G12Ci (adagrasib / sotorasib). Looking forward to ascertain magnitude of potential benefit and safety differences. 3⃣INTerpath-001: Phase 3 study of the mRNA-based individualized neoantigen therapy (INT) intismeran autogene (intismeran) plus pembrolizumab (pembro) vs pembro alone for adjuvant treatment of resected stage IIB-IV melanoma (MEL) Technically not a lung cancer study, but I believe this trial to be game-changing from a proof-of-concept approach. In my mind, this study establishes personalized mRNA-based approaches as a viable approach and worthy of research and clinical investment. @lcsmchat @OncoAlert @OncLive @Onco_Nexus @LungCancerEu @Lung_Cancers @LungCancerRx @MedwatchHQ @KRASKickers @SclcSMASHERS @YoungLungCancer

271 views 3 likes2 RT 2026-10-24
Mustafa Özdoğan, MD
Mustafa Özdoğan, MD@ozdogan_md
𝕏

Twelve more patients in a hundred stay recurrence-free at 2 years — on top of pembrolizumab alone. INTerpath-001 (LBA1, #ESMO26): resected stage IIB–IV melanoma; intismeran autogene + pembrolizumab vs pembrolizumab (n=1,137). Early release after embargo breach — confirm at PS I (Long). @ProfGLongMIA

246 views 3 likes4 RT 2026-10-24
Evelyn Wong
Evelyn Wong@EvelynWongYT
𝕏

Enjoyed @MarcoGerlinger's take on INTerpath & the discontinued BNT-122 CRC study at #ESMO26. What can each teach us? A reminder: we’re testing a strategy: that includes tumour biology, combination therapy and patient selection and not just a vaccine. #ESMOAmbassadors https://t.co/NfRxtIrsui

86 views 2 likes0 RT 2026-10-24
Mustafa Özdoğan, MD
Mustafa Özdoğan, MD@ozdogan_md
𝕏

Congratulations on bringing INTerpath-001 to PS I — a positive Phase 3 on an active control is a high bar. What I most want from Long’s slides: stage IIB vs III/IV subgroup RFS, timing of toxicity relative to immunization doses, and manufacturing turnaround / treatment-start delay in the personalized arm. Circulating: RFS HR 0.58, +12.2 pp at 24 mo; G≥3 23.6 vs 20.3. OS still the endpoint that decides clinic adoption.

51 views 1 likes1 RT 2026-10-24
Yakup Ergün
Yakup Ergün@dr_yakupergun
𝕏

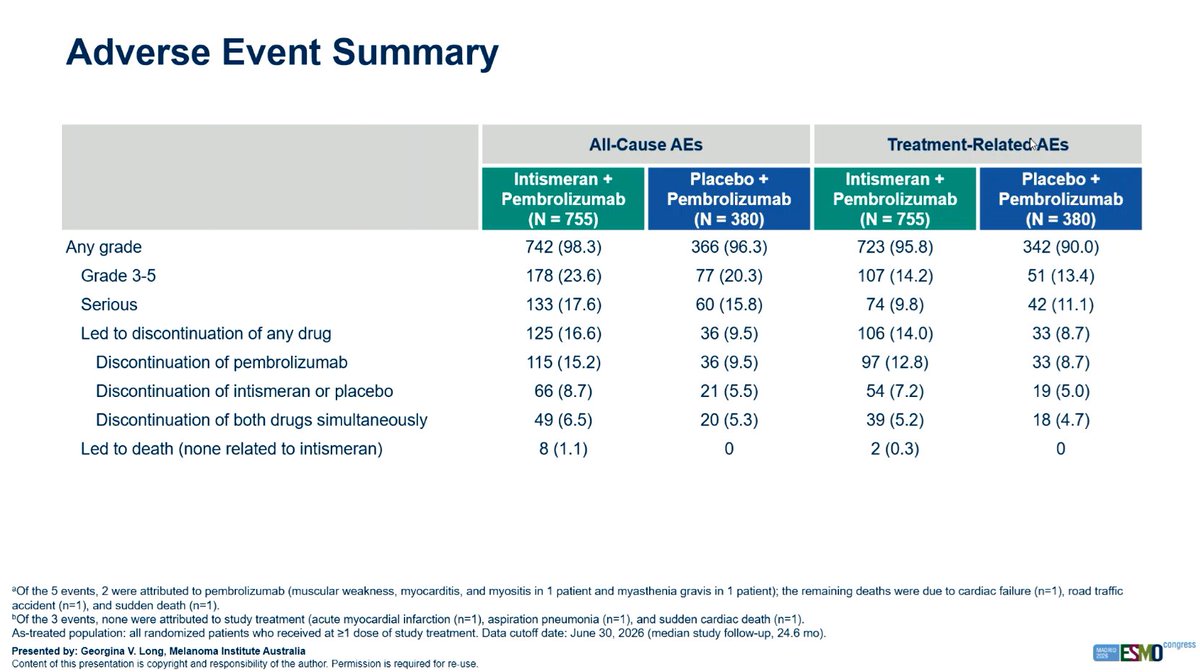
#ESMO26 INTerpath-001 8 Grade 5 AEs in the experimental arm, 0 in the control arm. Of course, it could all be pure coincidence! After all, 6 of the 8 events were not considered TRAE Perhaps it was just the excitement of being randomized to the experimental arm? I'm genuinely curious about the independent causality assessment.

5.4K views 20 likes2 RT 2026-10-24
Yakup Ergün
Yakup Ergün@dr_yakupergun
𝕏

#ESMO26 | INTerpath-001: My Personal Perspective Ahead of the Presidential Session This innovation deserves recognition: a groundbreaking result for personalized cancer vaccines. However, in patients with macroscopic stage III melanoma who are eligible for neoadjuvant IO, this trial does not establish the added value over contemporary perioperative strategies. Neoadjuvant treatment can produce substantial responses while allowing some patients to avoid adjuvant therapy. The trial design I would prioritize is: Neoadjuvant IO → surgery → standard adjuvant therapy ± a personalized vaccine in patients without a major pathological response. Here, “failure to achieve a major pathological response” is a more appropriate selection criterion than “any residual disease.” Patients with minimal residual viable tumor who still achieve a major pathological response should not automatically receive additional treatment. This approach would direct treatment intensification toward patients at higher risk of recurrence. The key biological uncertainty, however, is that IO-resistant residual disease is not necessarily vaccine-sensitive. Whether vaccination can overcome that resistance needs to be demonstrated. This criticism should remain specific to that population: INTerpath-001 retains distinct clinical value for patients with stage IIB/IIC disease and those who underwent surgery without neoadjuvant therapy.

3.9K views 24 likes6 RT 2026-10-24
Toni Choueiri, MD
Toni Choueiri, MD@DrChoueiri
𝕏

Superb presentation by Georgina Long! INTerpath-001: adding personalized mRNA vaccine intismeran to pembrolizumab reduced recurrence/death risk by 42% in resected stage IIB-IV melanoma (HR 0.58). A major step for cancer vaccines! #ESMO26 @OncoAlert @myESMO #ESMO26 https://t.co/9miRzK7fhb

1.4K views 27 likes14 RT 2026-10-24
Balazs Halmos
Balazs Halmos@BalazsHalmosMD
𝕏

I admit i am very much into intismeran…and it seems many others too as it is standing room only here… Fabulous presentation/data on the Interpath-001 trial demonstrating clear benefit of this space age bespoke neoantigen vaccine along w pembro for pts w resected high risk melanoma as to 40% or so improvement in RFS/distant met free survival Indeed a landmark trial for precision medicine and hopefully not too Long before we see confirmation in nsclc/other trials! Interpath- indeed makes us foresee a wonderful path and light ahead for our field! #ESMO26

1.4K views 21 likes5 RT 2026-10-24
Yago Garitaonaindía
Yago Garitaonaindía@YGaritaonaindia
𝕏

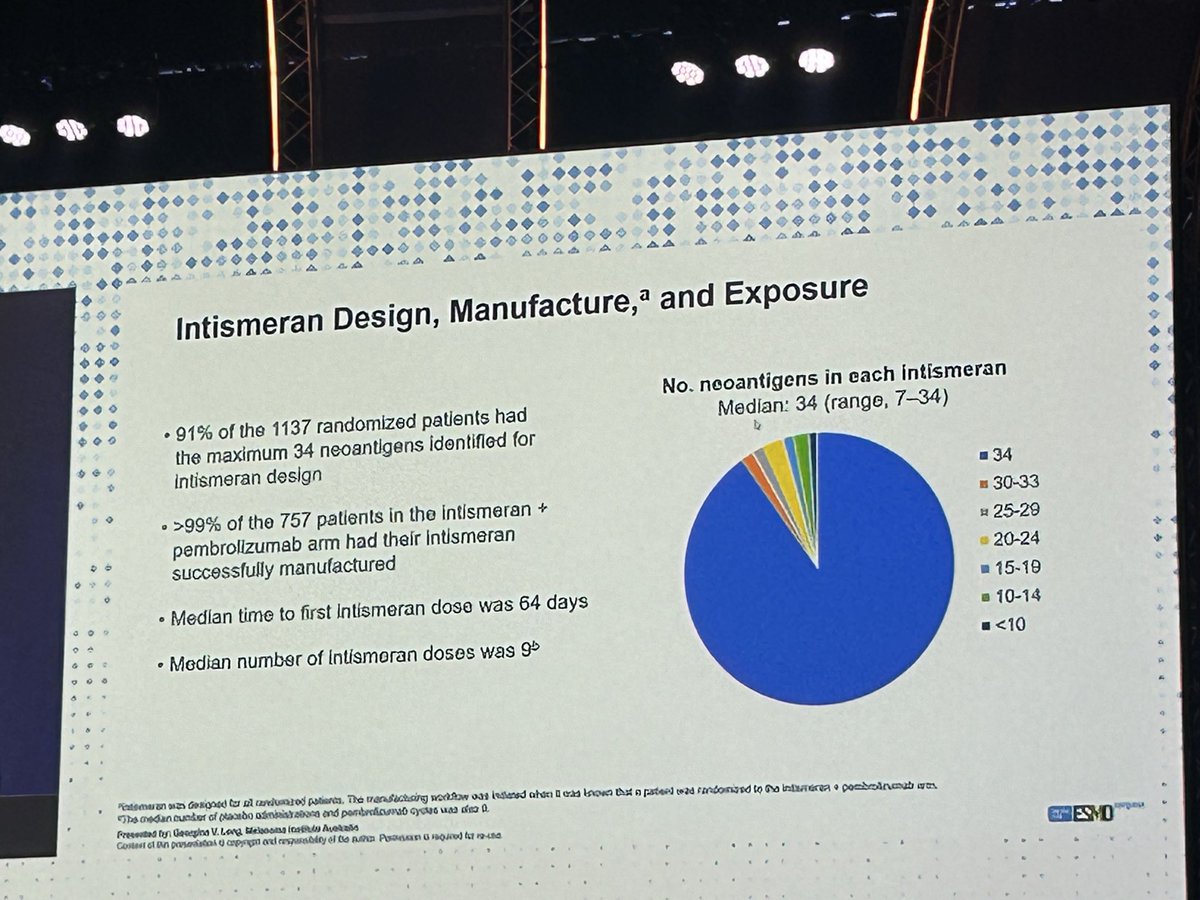
🔥 #ESMO26 INTerpath-001, full data (now yes) On top of RFS HR 0.58 and DMFS HR 0.62: • Manufacturing success >99% • >90% of patients got the maximum 34 neoantigens 🔍 Practice-changing? For a population, yes. Two things still to prove: • Can an mRNA strategy rescue patients primary refractory to neoadjuvant ipi-nivo (no pathologic response)? • Will it move OS in stage II-IIIB too? Resuls in @NEJM soon @myESMO @OncoAlert @Larvol @_SEOM #Melanoma #Immunotherapy

1.2K views 12 likes4 RT 2026-10-24
Mario Balsa
Mario Balsa@MarioBalsaMD
𝕏

👑 Presidential #ESMO26! INTerpath-001: personalized mRNA vaccination reaches phase III in melanoma. Resected stage IIB–IV melanoma, N=1,137: intismeran + pembrolizumab vs pembrolizumab. 💥 At 24 months: • RFS: 82.2% vs 70.0% → HR 0.58 • DMFS: 88.5% vs 80.2% → HR 0.62 • Absolute gains: +12.2% RFS / +8.3% DMFS • Benefit emerges mainly after 6 months • Grade ≥3 AEs: 23.6% vs 20.3% • OS still immature A clinically meaningful new mechanism, but the real question now is positioning 🤔 For macroscopic stage III: adjuvant personalized vaccine after surgery, or neoadjuvant ipi/nivo before it? Biomarkers may ultimately decide. Congrats to @ProfGLongMIA and all the team! 👏🏼 @OncoAlert @OncoReporte @myESMO @_SEOM @GrupoMelanoma

939 views 15 likes10 RT 2026-10-24
Alfredo Addeo MD
Alfredo Addeo MD@Alfdoc2
𝕏

🔥 Personalized cancer vaccines delivering impressive results at #ESMO26! @ProfGLongMIA presents the phase III INTerpath-001 trial in resected high-risk melanoma. Individualized neoantigen mRNA vaccine intismeran autogene + pembrolizumab vs pembrolizumab alone. Key results: 🔹 DMFS: HR 0.62 (95% CI 0.45–0.85), p=0.002 🔹 24-month DMFS: 88.5% vs 80.2% 🔹 RFS: HR 0.58 (95% CI 0.45–0.75) A major milestone for personalized cancer vaccines! A promising step towards truly individualized immunotherapy. #ESMOAmbassador #ESMO26 #Melanoma #CancerVaccines #Immunotherapy

892 views 11 likes7 RT 2026-10-24
Yüksel Ürün
Yüksel Ürün@DrYukselUrun
𝕏

A long-awaited breakthrough in cancer vaccines. One patient. One tumor. One personalized mRNA vaccine. INTErpath-001 brings this vision closer to clinical reality. Are we ready to deliver it? @myESMO @OncoAlert @OpenMedicineHQ #ESMO26 @ProfGLongMIA @FAndreMD @curijoey @YJanjigianMD

870 views 13 likes6 RT 2026-10-24
Hidehito HORINOUCHI
Hidehito HORINOUCHI@HHorinouchi
𝕏

🆙#ESMO26 Presidential Symposium I 🔥INTerpath-001: Phase 3 Study of the mRNA-Based Individualized Neoantigen Therapy (INT) Intismeran Autogene (Intismeran) Plus Pembrolizumab (Pembro) vs Pembro Alone for Adjuvant Treatment of Resected Stage IIB-IV Melanoma (MEL) 🎙️ @ProfGLongMIA 🔢LBA1 🎯Met Primary Endpoint: Significantly Improved RFS 🎯24-Mo 82.2% vs 70.0%, HR 0.58 🎯DMFS HR 0.62 🎯Grade≥3 AEs 23.6% vs 20.3% ☑️NCT05933577 🔗 https://t.co/Lb6tzuMm0z @OncoAlert @Larvol @myESMO

708 views 7 likes4 RT 2026-10-24
Yakup Ergün
Yakup Ergün@dr_yakupergun
𝕏

#ESMO26 | INTerpath-001👇 https://t.co/9zQwLrfkBe https://t.co/jA8OFWtQqd

698 views 3 likes2 RT 2026-10-24
Yüksel Ürün
Yüksel Ürün@DrYukselUrun
𝕏

A milestone for personalized cancer vaccines. INTErpath-001: 42% lower recurrence/death risk; 24-month RFS 82.2% vs 70%. Can we extend this benefit to other cancers? @myESMO @OncoAlert @OpenMedicineHQ #ESMO26 https://t.co/567xy0e42L

499 views 13 likes5 RT 2026-10-24
Sara Coca Membribes
Sara Coca Membribes@scocmem
𝕏

#ESMO26 Starting the Presidential Session with INTerpath-001 Intismeran + pembro shows ⬇️risk of recurrence and of distant mets including high-risk stages. A major step forward for personalised cancer vaccines, looking forward to see the data in other tumour types @OncoAlert https://t.co/SBGq9djNGK

497 views 12 likes6 RT 2026-10-24
Martín Angel
Martín Angel@Martin_AngelMD
𝕏

Presidential symposium 1️⃣!! Interpath-001: adjuvant INT (intismeram) plus pembro impact in RFS & DMFS for stage II-IV resectable melanoma #ESMO26 @ProfGLongMIA @myESMO #personalizedmedicine https://t.co/G5Pf70eb1x

456 views 6 likes7 RT 2026-10-24
Shilpa Gupta
Shilpa Gupta@shilpaonc
𝕏

Practice-changing at #ESMO26 Presidential @ProfGLongMIA INTerpath-001: personalized mRNA neoantigen Tx (intismeran) + pembro vs pembro alone in resected stage IIB–IV melanoma (n=1,137) RFS HR 0.58, 2-yr RFS 82% vs 70%
DMFS HR 0.62, 2-yr DMFS 89% vs 80% It's the 1st phase 3 win for an individualized cancer vaccine against an active IO control. OS is pending, but the adjuvant melanoma bar just moved. Kudos to the entire team! Moving moment as @ProfGLongMIA paid tribute to Dr. Jeff Weber, who designed this trial and enrolled patients until his passing. Jeff was a dear friend and my colleague at @MoffittNews and today's results are his legacy 💙 Bladder next: INTerpath-005 in MIUC, look forward to seeing the data in future!

451 views 1 likes0 RT 2026-10-24
Tian Zhang, MD, MHS, FASCO (@tiansterzhangmd.bsky)
Tian Zhang, MD, MHS, FASCO (@tiansterzhangmd.bsky)@TiansterZhang
𝕏

with 1st neoantigen vaccine intismeran w pembro vs placebo w pembro, increased recurrent free & metastasis free survival in resected melanoma. Congrats to the teams!! @oncoalert @myESMO #ESMO26 https://t.co/2orLB7ug7y

437 views 10 likes9 RT 2026-10-24
Renee Maria Saliby
Renee Maria Saliby@ReneeSaliby
𝕏

INTerpath-001 - the result of decades of scientific advances and research led to this moment! And brilliant delivery by @ProfGLongMIA Personalized mRNA vaccines + Pembro as adjuvant trt improve RFS for pts with resects IIB-IV Melanoma!! Important points: Tox: a significant number of adverse events occurred BEFORE the vaccine was started Access: the vaccines was given globally #ESMO26 @OncoAlert

434 views 16 likes9 RT 2026-10-24
David H Aggen, MD PhD
David H Aggen, MD PhD@Dr_Aggen
𝕏

There is clear additive activity with a personalized mRNA vaccine with intismeran autogene with pembrolizumab in melanoma where dual PD1 failed before. Presented by @ProfGLongMIA - I hope the same will come in the future for RCC #ESMO26 #Oncoalert https://t.co/Owe1QY5Uuh

426 views 7 likes6 RT 2026-10-24
Shilpa Gupta
Shilpa Gupta@shilpaonc
𝕏

#ESMO26 @myESMO Presidential session presentation by session @ProfGLongMIA INTerpath-001: intismeran + pembro vs pembro in resected stage IIB–IV melanoma (n=1,137) RFS HR 0.58, 2-yr RFS 82% vs 70%
DMFS HR 0.62, 2-yr DMFS 89% vs 80% 1st phase 3 win for an individualized cancer vaccine against an active IO control. OS is pending, but the adjuvant melanoma bar just moved! Moving moment as @ProfGLongMIA paid tribute to Dr. Jeff Weber, who designed this trial and enrolled patients until his passing. Jeff was a dear friend and my colleague at @MoffittNews and today's results are his legacy 💙 Bladder next: INTerpath-005 in MIUC, look forward to seeing the data in future!

424 views 7 likes7 RT 2026-10-24
Daniel Heng
Daniel Heng@DrDanielHeng
𝕏

#INTerpath001 amazing adjuvant melanoma trial of a personalized vaccine plus pembrolizumab. 17% of patients didn’t have sufficient tumor sample to create the neoantigen vaccine. DFS highly positive and OS immature. @oncoalert #ESMO26 excited to see other tumor data coming soon! https://t.co/VyUKabIWE2

381 views 10 likes8 RT 2026-10-24
Gaia Griguolo
Gaia Griguolo@GaiaGriguolo
𝕏

First positive trial with individualized neoantigen therapy! Adding intismeran (personalized mRNA vaccine) to pembro improves RFS and DMFS in stage IIB/IIC, III, or IV resected melanoma Opening the door to this approach across different solid tumors! @OncoAlert #Esmo26 https://t.co/lcNNegQ5S0

326 views 5 likes6 RT 2026-10-24
Shankar Siva
Shankar Siva@_ShankarSiva
𝕏

#ESMO26 Interpath-01; 🚨addition of individual tumour directed mRNA vaccine intismeran n=1137 patient phIII trial in resected #melanoma to pembro anti-PD1. ⬇️ risk of distant mets or death by 38%. Similar G3-5 TRAEs similar ~14%. OS not mature. 💥A new era in personalised mRNA therapy?

311 views 3 likes1 RT 2026-10-24
Fernanda G. Herrera
Fernanda G. Herrera@fg_herrera
𝕏

Welcome INTERpath-001 first mRNA vaccine for melanoma treatment with no potentiation of Pembro AE https://t.co/ZKEYemE2k2

310 views 5 likes1 RT 2026-10-24
Ana I. Velázquez Mañana, MD, MSc, FASCO
Ana I. Velázquez Mañana, MD, MSc, FASCO@AnaVManana
𝕏

INTerpath-001 adjuvant Intismeran Autogene + Pembro vs Pembro for resected stage IIB-IV #Melanoma Impressive RFS and distant metastasis free survival improvement with a truly personalized and neoantigen-driven approach @ProfGLongMIA #ESMO26 @myESMO https://t.co/NQ1xb6krW8

307 views 4 likes7 RT 2026-10-24
Alfredo Addeo MD
Alfredo Addeo MD@Alfdoc2
𝕏

Balanced discussion by prof Svane of the phase III INTerpath-001 trial at #ESMO26. Personalized cancer vaccines represent a major step forward, but: 🔹 Will the RFS benefit translate into improved OS? 🔹 Where should adjuvant vaccination fit alongside neoadjuvant ipilimumab/nivolumab? 🔹 Who benefits most? Predictive biomarkers remain urgently needed. 🔹 Manufacturing complexity, treatment delays, costs and access are major challenges. 👏 Compelling data and a milestone for personalized oncology, but clinical positioning and real-world feasibility will be crucial! #ESMOAmbassador #ESMO26 #Melanoma #CancerVaccin

302 views 6 likes1 RT 2026-10-24
Abeid Athman (Omar).
Abeid Athman (Omar).@bin_abeid
𝕏

In INTerpath-001, the combination of adjuvant Intismeran plus pembro is superior to pembro alone in resected melanoma mproves RFS in ITT 70% vs 82.2% HR 0.58 #ESMO2026 @darioT_ @myESMO @DrChoueiri @FAndreMD @OncoAlert https://t.co/lKvGZajEEZ

288 views 6 likes5 RT 2026-10-24
Alan Tan
Alan Tan@alantanmd
𝕏

Georgina Long presented INTerpath-001 at #ESMO26: intismeran + pembrolizumab vs placebo + pembrolizumab as adjuvant therapy for resected melanoma. It met the primary RFS endpoint (42% reduction in risk of recurrence or death) and the key secondary DMFS endpoint (38% reduction). OS is still immature, and follow-up is ongoing.

261 views 4 likes1 RT 2026-10-24
Dr. Antonio Calles 🫁🚭
Dr. Antonio Calles 🫁🚭@Tony_Calles
𝕏

🧬 Personalized mRNA vaccines work‼️ 📈 INTERPATH-001 met its primary endpoint in resected melanoma patients, paving the way to other tumor types and combinations, including lung 🫁 #cancer 🚀 🌓 One small step for a vaccine, one giant leap for personalized medicine. #ESMO26 @myesmo

214 views 4 likes3 RT 2026-10-24
Clara Steiner
Clara Steiner@Clara__Steiner
𝕏

When urologists are paying attention to Melanoma trials: exciting times for personalized cancer vaccines with the data from INTERPATH-001 excellently presented by @ProfGLongMIA at #ESMO2026! Curious for what’s to come in GU! https://t.co/DvwMBcBTMB

211 views 4 likes1 RT 2026-10-24
Oriol Mirallas MD
Oriol Mirallas MD@DrMirallas
𝕏

🔥 Presidential Symposium I #ESMO26 INTerpath-001: double-blind phase 3 study of intismeran (mRNA vaccine) + pembro as adjuvant therapy for resected stage IIB–IV #melanoma ✔️ RFS 82.2 vs 70% HR 0.58 ✔️ DMFS 88.5 vs 80.2% HR 0.62 ☣️ No increased risk of toxicity in the combination ✅🧫 mRNA Vaccine in adjuvant melanoma treatment together with anti-PD1 @OncoAlert @myESMO @ASCO @_SEOM @UTMDAnderson @brunolarvol 👇🏽👇🏽

202 views 1 likes0 RT 2026-10-24
José Márcio Barros de Figueiredo MD, MSc
José Márcio Barros de Figueiredo MD, MSc@josemarciofigu1
𝕏

#ESMO26 | LBA1 – INTerpath-001 ✅ First positive Phase 3 of individualized mRNA neoantigen therapy in adjuvant melanoma Intismeran autogene + pembrolizumab vs pembrolizumab alone (Resected stage IIB–IV | N=1,137 | median FU 24.6 mo) ✅ RFS: HR 0.58 (0.45–0.75) | p<0.001 → 24-mo RFS 82.2% vs 70.0% ✅ DMFS: HR 0.62 (0.45–0.85) | p=0.002 → 24-mo DMFS 88.5% vs 80.2% ✅ Benefit across most subgroups ✅ Manageable safety (no potentiation of pembro AEs) ✅ OS still immature New benchmark for adjuvant melanoma. Presented by Georgina V. Long #ESMO26 #Melanoma #mRNA #INTerpath001 @myESMO @OncoAlert

202 views 3 likes1 RT 2026-10-24
Prof. Dr. Ahmet Dirican
Prof. Dr. Ahmet Dirican@dr_dirican
𝕏

ESMO 2026 | Personalized mRNA Cancer Vaccines Deliver Phase III Success! INTerpath-001: Intismeran + pembrolizumab in resected high-risk melanoma. • RFS: HR 0.58 (42% risk reduction) • 24-month RFS: 82.2% vs 70.0% (+12.2%) • DMFS: HR 0.62 (38% risk reduction) 3 Key Takeaways: 1. Personalized neoantigen vaccines have demonstrated clinically meaningful Phase III efficacy. 2. No major increase in severe treatment-related toxicity, but overall survival data remain immature. 3. Predictive biomarkers, ctDNA/MRD, and optimal sequencing versus neoadjuvant immunotherapy are the next critical questions. A major milestone for personalized oncology. #ESMO26 @myesmo @oncodaily @OncoAlert #CancerVaccines #Melanoma

165 views 1 likes2 RT 2026-10-24
Peter Grell MD
Peter Grell MD@GrellMd
𝕏

Phase 3 results from the INTerpath-001 trial confirm that the individualized mRNA vaccine plus pembrolizumab significantly improves outcomes in adjuvant treatment of malignant melanoma. The era of mRNA vaccines in oncology has officially begun!👏 #ESMO26! https://t.co/BO9n6VKQpp

109 views 1 likes0 RT 2026-10-24
Kevin Tay
Kevin Tay@KVTay316
𝕏

Surgeon's view: they want different things from the operation. Neoadjuvant pembro treats the disease before it comes out. The vaccine is built from the tumour after it's out. INTerpath-001 enrolled patients with no prior systemic therapy, so it doesn't answer the "both" question.

77 views 0 likes0 RT 2026-10-24
Michiel Strijbos
Michiel Strijbos@StrijbosMichiel
𝕏

One Patient. One Tumor. One mRNA Vaccine. 🧬💉
INTErpath-001: Cancer’s custom nightmare just arrived. Ready? 🚀

69 views 2 likes1 RT 2026-10-24
Kevin Tay
Kevin Tay@KVTay316
𝕏

Merck and Moderna's personalised mRNA melanoma vaccine (intismeran) plus pembrolizumab cut recurrence or death by 42% vs pembrolizumab alone in INTerpath-001: 1,137 patients, completely resected stage IIB–IV. 2-year recurrence-free 82.2% vs 70.0%. Overall survival not mature yet. The detail surgeons should notice: each vaccine is built from that patient's own resected tumour, coding up to 34 neoantigens. So the operation is no longer just the end of the cancer pathway. It's the first step in making the drug. How we handle the specimen, whether there's enough tissue, how fast it reaches sequencing: all of that now sits inside the treatment.

56 views 0 likes0 RT 2026-10-24
Nicholas Hornstein
Nicholas Hornstein@GIMedOnc
𝕏

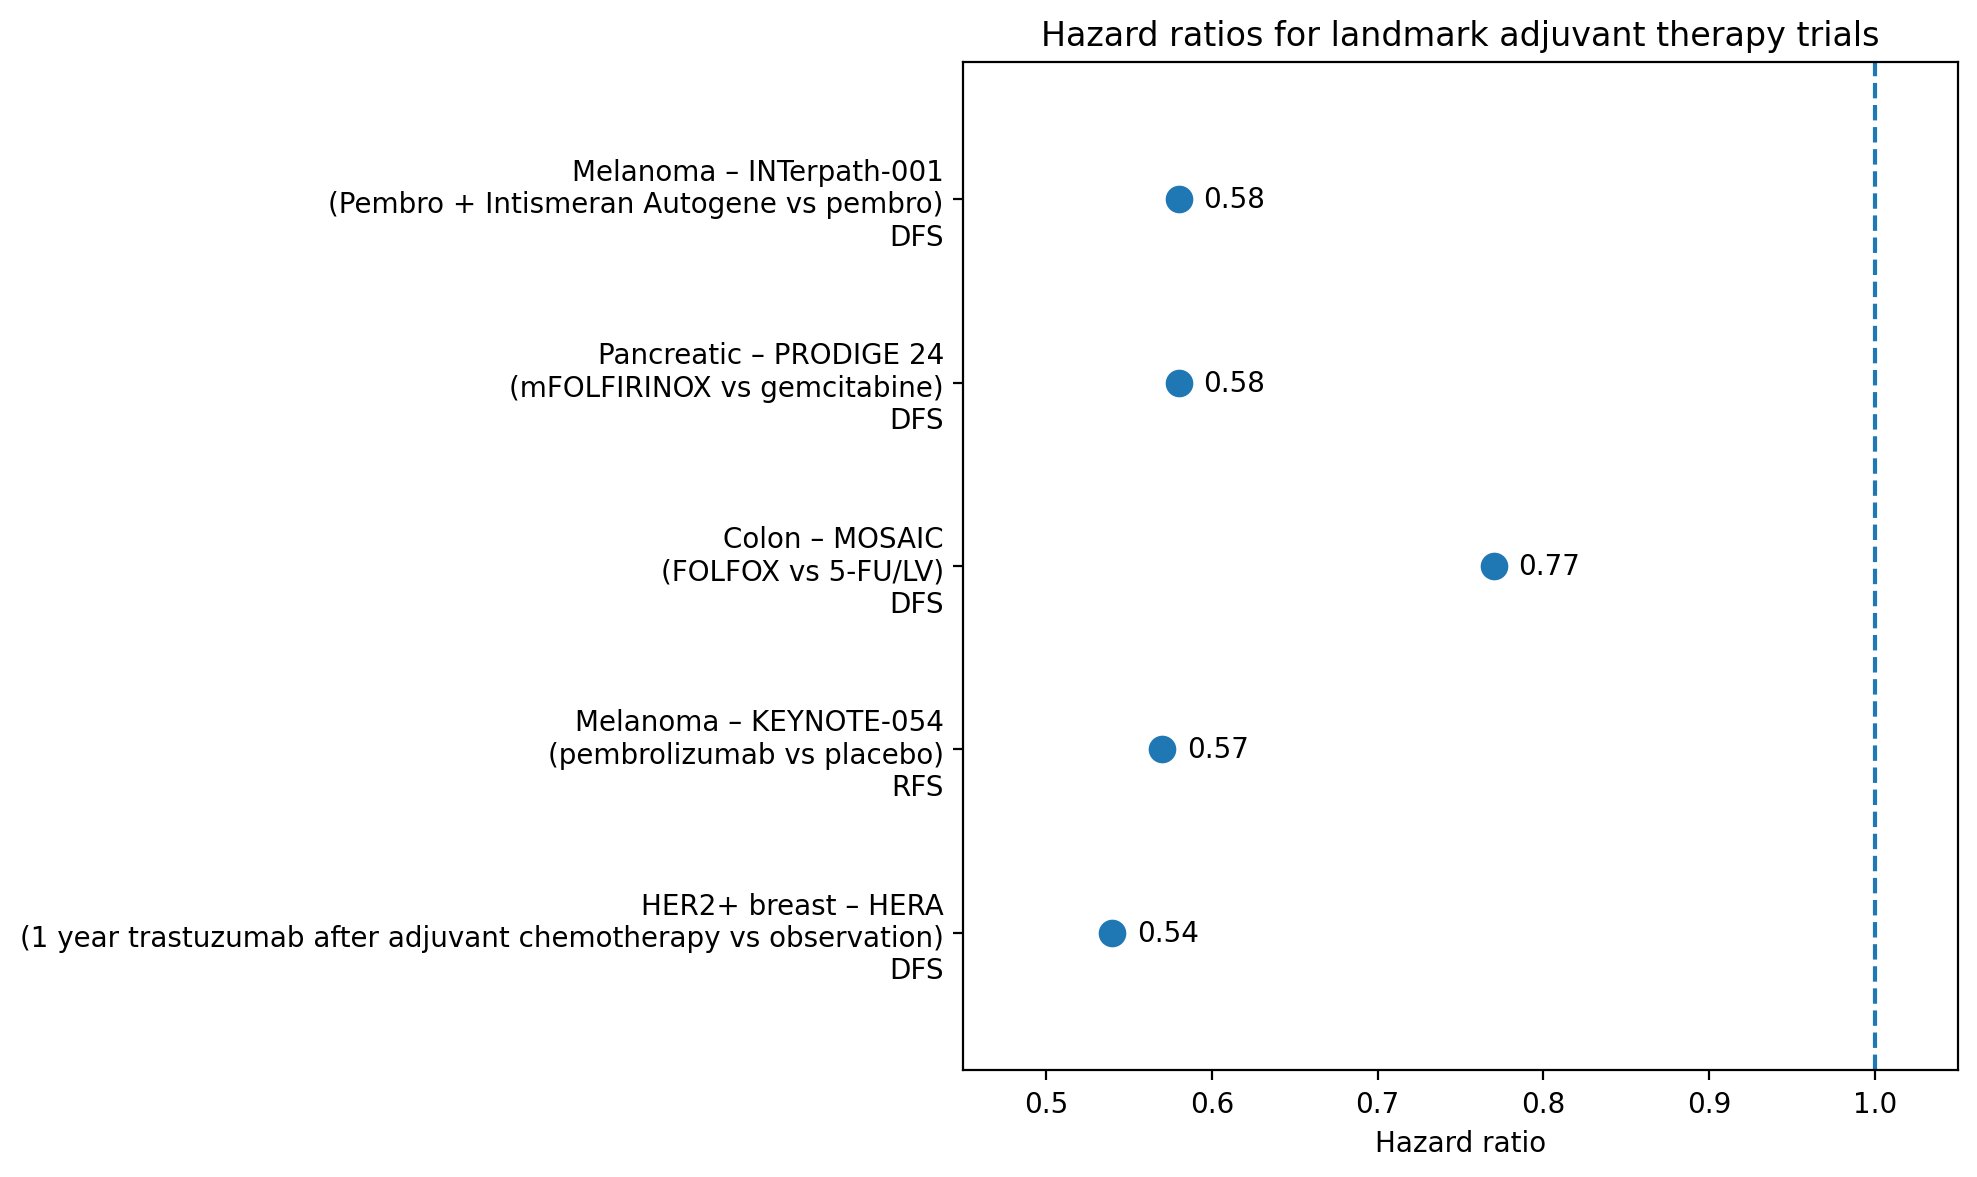
Topline ESMO data from INTerpath-001 (#Moderna's personalized cancer vaccine) reportedly leaked elsewhere: RFS HR 0.58 (Honestly shame on people for breaking embargo’s). There is a huge divide here between physicians and non-physicians on the outcome. To me, this was huge and clearly worked. This hazard ratio puts it in the company of the most paradigm-changing adjuvant trials in oncology history. Yes, the same outcome can be generated from giving pembro in the neoadjuvant space [SWOG S1801 neoadjuvant + adjuvant pembro vs adjuvant pembro alone: EFS HR 0.58.] That isn't the point. A peptide vaccine strategy yielded the same outcome as having a tumor in vivo. This demonstrates the tech worked, now it can be applied more broadly or potentially even supercharge the neoadjuvant space with less immunogenic tumors. Time to do better and apply to more things (like colon cancer pls). #ESMO26
@OncoAlert @TheGutOncLab

1.4K views 26 likes7 RT 2026-10-23
Mario Balsa
Mario Balsa@MarioBalsaMD
𝕏

🚨 #ESMO26 | Phase III INTerpath-001 🚨 After an early embargo breach, @myESMO brought the abstract release forward!!!!!! And yes, it’s clearly positive: 📉 RFS HR 0.58 📉 DMFS HR 0.62 But here’s the uncomfortable part: SWOG S1801 also reported an HR 0.58…simply by moving 3 doses of pembrolizumab BEFORE surgery… ☝🏼Not the same population. Not the same endpoint. Not a cross-trial comparison. Still, in 2026, should a personalized mRNA vaccine really be benchmarked against adjuvant pembro alone? Before calling this a new standard, I want to see the vaccine face the NEOADJUVANT era. Same HR. Different path. And that may be the real INTerpath question 👀 @OncoAlert @OncoReporte @myESMO @_SEOM @GrupoMelanoma What do you think? @SuyogCancer @OncBrothers @A_May_MD @Dr_R_Kurzrock

991 views 15 likes9 RT 2026-10-23
Yago Garitaonaindía
Yago Garitaonaindía@YGaritaonaindia
𝕏

Some thoughts on the INTerpath-001 backlash, and the simplistic "neoadjuvant already does better, so why bother" take. I think it misses a few important things. ➡️ First, the neoadjuvant data (S1801, NADINA) come from patients with macroscopic, clinically detectable nodal disease. INTerpath-001 also includes node-negative IIB/IIC and patients whose nodal disease only showed up on sentinel node biopsy. In the big SLN trials, about two thirds of SLN+ patients had deposits ≤1 mm. None of these patients are neoadjuvant candidates. We see the same confusion in #NSCLC all the time, when people compare stage IIIA from adjuvant trials (pathological staging) with stage IIIA from neoadjuvant trials (clinical staging). Same stage on paper, not the same patients. ➡️ Second, INTerpath-001 was designed before NADINA read out, when adjuvant anti-PD-1 was still the default for resected stage III. Judging it against today's practice is a bit of hindsight. ➡️ Third, I suspect the most logical place for a neoantigen vaccine is after neoadjuvant ICI in patients who don't reach pCR. INTerpath-009 is already testing exactly this in NSCLC, so we'll get some hints there. ➡️ And all of this comes with only an absolute ~3% increase in grade ≥3 toxicity, which also belongs in the balance. For macroscopic stage III, the critique lands. I want to see the full data and the stage breakdown at LBA1. But I'd be careful firing at this result before we've even seen it properly. @OncoAlert @Larvol @KolPulseAI @_SEOM @myESMO #Melanoma #ESMO26

431 views 8 likes5 RT 2026-10-23
MV Chandrakanth
MV Chandrakanth@ChandrakanthMv
𝕏

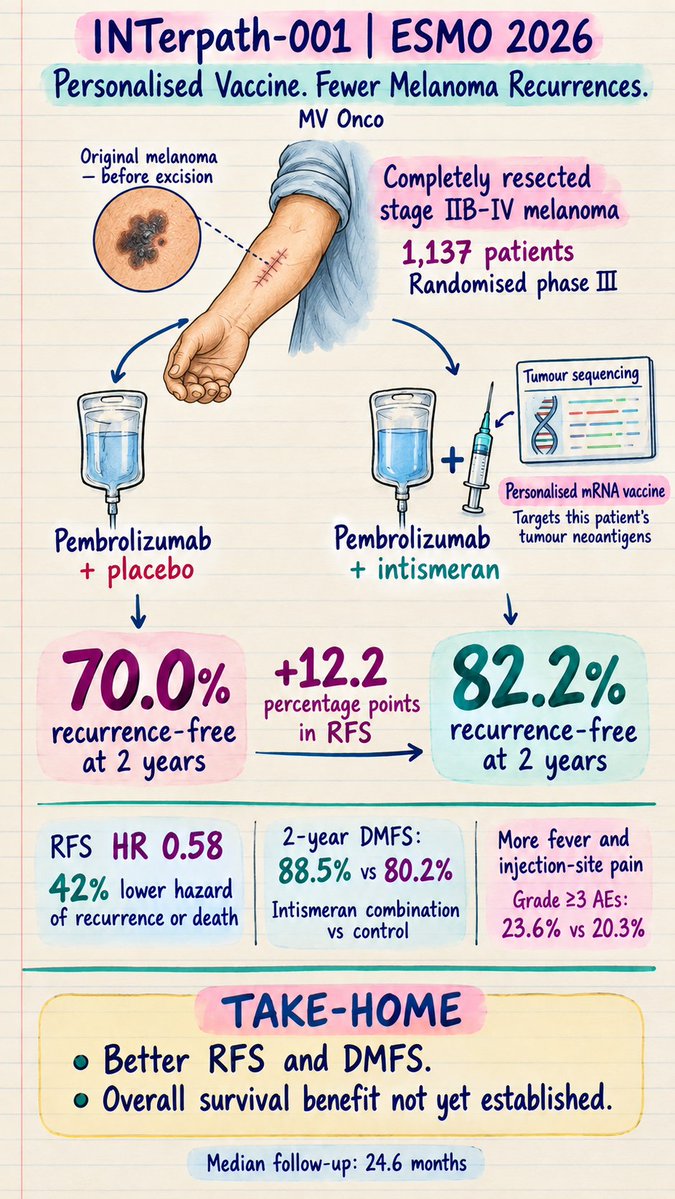
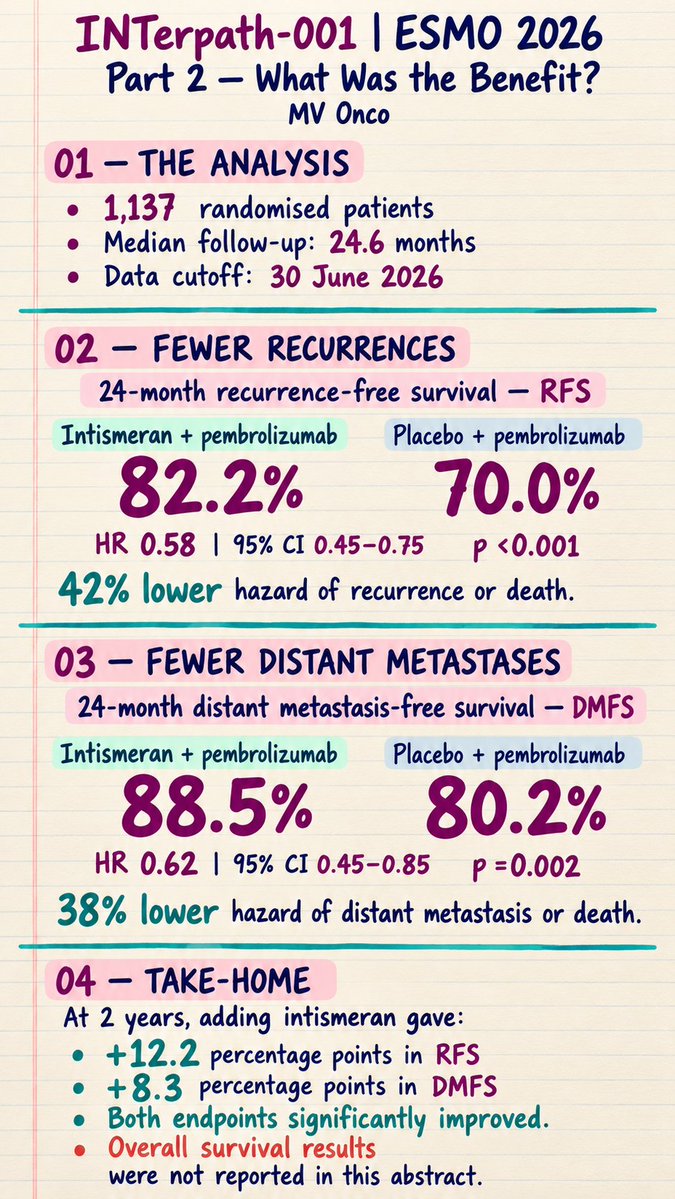
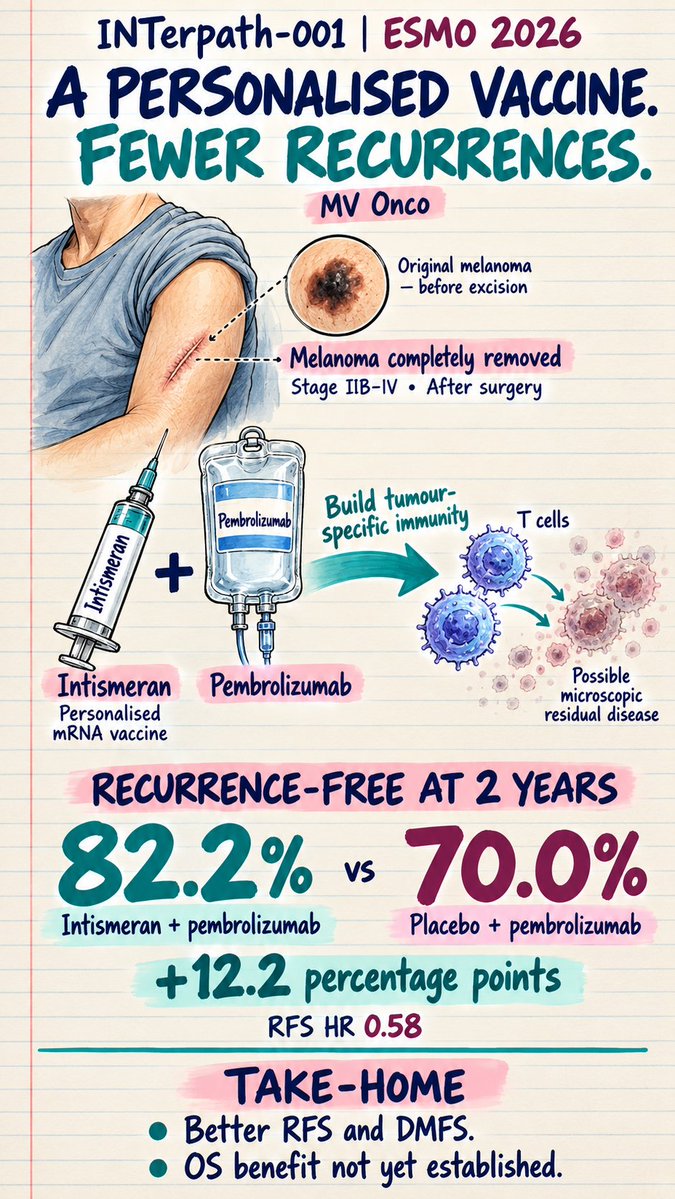
ADJUVANT MELANOMA | ESMO 2026 INTerpath-001: How Much Benefit Are We Actually Adding? Adding a personalised mRNA vaccine to pembrolizumab improved 2-year RFS from 70.0% to 82.2%. Absolute gain: +12.2 percentage points | HR 0.58 Unlike earlier adjuvant trials against placebo or ipilimumab, this benefit was demonstrated on top of pembrolizumab. ⚠️ Cross-trial comparisons are not valid: populations, comparators and follow-up differ. OS benefit remains unproven. The key question: Will this RFS advantage translate into improved long-term survival? #MVOnco #ESMO2026 #INTerpath001 #Melanoma #CancerVaccine #Immunotherapy

306 views 2 likes2 RT 2026-10-23
ALFONSO DUEÑAS GONZALEZ
ALFONSO DUEÑAS GONZALEZ@duenas_gon28
𝕏

Cautionary note – personalized mRNA neoantigen vaccine (intismeran / mRNA-4157) in resected melanoma. The reported reduction in recurrence is real, yet several core uncertainties remain unresolved. The control was an inactive placebo, not a scrambled or irrelevant mRNA matched for mass and antigen number. Non-specific innate effects of the mRNA-LNP platform therefore cannot be separated from antigen-specific activity. No published in vitro data have tested whether the encoded neoantigen peptides or mRNA constructs exert any direct stimulatory or pro-proliferative effect on melanoma cells independent of the immune system. This possibility has not been experimentally excluded. Overall survival benefit is still immature, and the contribution of the vaccine outside the adjuvant Keytruda combination is unproven. Manufacturing time, cost, and scalability constraints are substantial; generalizability beyond highly selected resected melanoma remains limited. These open questions do not erase the clinical signal. They do limit how confidently the mechanism and the true incremental value of the personalized neoantigens can be asserted.

243 views 0 likes0 RT 2026-10-23
Mario Balsa
Mario Balsa@MarioBalsaMD
𝕏

🚨 Scientific embargoes exist for a reason: fair access to data, scientific integrity and, ultimately, patients. Seeing a major #ESMO26 study disclosed ahead of schedule is disappointing. I think ESMO takes its embargo policy seriously, and I would expect a breach of this magnitude to have consequences. Science should set the timeline, not the stock market 😡 With INTerpath-001, someone clearly took a shortcut on the path to the data. @OncoAlert @OncoReporte @myESMO @_SEOM @GrupoMelanoma

5.9K views 27 likes6 RT 2026-10-23
Balazs Halmos
Balazs Halmos@BalazsHalmosMD
𝕏

I note of skepticism that the the adjuvant individualized neoantigen therapy data is not meaningful progress In case of NSCLC- we shall learn as there are 3 separate studies ongoing (one just completing accrual!) But scientifically… Neoadj IO works better compared to adj IO as activated T cells need to see the “in situ vaccine” of the native tumor for long-standing benefit. Postop in micromet setting simply stated there is just no cancer cells to work with- as an analogy, for T cells to build muscles they need machines in the gym… otherwise, no lifting- no muscle… Now the beauty of INT is that it does provide an excellent gym with the best tailored neoantigen weight machines for the immune system to work with! So w results of Interpath-001 i’d say- T cells and all of us, lets go to the gym and Cheers on a first set of great results!

1.7K views 13 likes3 RT 2026-10-23
BASEM BAHRANI باسم البحراني
BASEM BAHRANI باسم البحراني@basemstat
𝕏

💉لقاح mRNA شخصي يقلل خطر عودة سرطان الجلد أو الوفاة بنسبة 42% 📉 أعلنت شركتا Moderna⁠ و Merck⁠ نتائج تجربة INTerpath-001 من المرحلة الثالثة 📉 اختبرت التجربة لقاح Intismeran autogene المصمم خصيصاً وفق الطفرات الجينية لورم كل مريض بشكل شخصي بالإضافة إلى العلاج المناعي Pembrolizumab بعد الاستئصال الجراحي لسرطان الجلد الميلانيني عالي الخطورة 📉 شملت التجربة أكثر من 1,100 مريض 📉 النتيجة 🔹انخفاض الخطر النسبي Relative Hazard Reduction لعودة السرطان أو الوفاة 42% 🔹انخفاض الخطر النسبي للانتشار البعيد أو الوفاة 38% 🔹البقاء دون عودة السرطان مع العلاج المركب 82.2% و تمثل نسبة المرضى الذين بقوا دون عودة السرطان أو الوفاة خلال عامين Recurrence-Free Survival 🔹البقاء دون عودة السرطان مع Pembrolizumab وحده 70% 📉 الأهمية السريرية: يمثل هذا أول دليل من المرحلة الثالثة على فائدة سريرية للقاح سرطاني شخصي قائم على تقنية mRNA عند إضافته إلى العلاج المناعي ❗️النتائج مشجعة انخفاض الخطر النسبي بنسبة 42% لا يعني انخفاض الوفيات وحدها بهذه النسبة بيانات البقاء الكلي غير مكتملة و لم يحصل اللقاح بعد على الموافقات التنظيمية https://t.co/Znw4S3Pl7Z https://t.co/wGMx1VeKui https://t.co/FXD240UPQd

1.1K views 5 likes2 RT 2026-10-23
Tian Zhang, MD, MHS, FASCO (@tiansterzhangmd.bsky)
Tian Zhang, MD, MHS, FASCO (@tiansterzhangmd.bsky)@TiansterZhang
𝕏

with med onc pearls for neoantigen mRNA vaccines. The future is happening now — esp w readout of INTERPATH-001 trial this #ESMO26 @myESMO @oncoalert https://t.co/EhNz2A40yG

732 views 13 likes9 RT 2026-10-23
Ahmad Tarhini
Ahmad Tarhini@ATarhiniMDPhD
𝕏

#Madrid #ESMO26 | Main findings from INTerpath-001 released: #Intismeran + #pembrolizumab reduced risk of recurrence or death by 42% (HR, 0.58), risk of distant metastasis or death by 38% (HR, 0.62); 24-monRFS rates 82.2% vs 70.0% | Proud to be part of this effort @MoffittNews

280 views 4 likes1 RT 2026-10-23
Aiken Dao
Aiken Dao@AikenDao
𝕏

Encouraging developments in personalised cancer immunotherapy. Phase 3 results from the INTerpath-001 trial suggest that an investigational mRNA-based treatment, intismeran autogene, combined with pembrolizumab, reduced the relative risk of melanoma recurrence or death by 42% compared with pembrolizumab alone. At two years, 82.2% of patients receiving the combination remained free from recurrence, compared with 70% in the control group. The treatment is individually designed using mutations identified in each patient's tumour. Overall survival outcomes remain under evaluation, but these findings represent promising progress towards more personalised approaches to cancer treatment. #Melanoma #CancerResearch #mRNA #Immunotherapy #PrecisionMedicine https://t.co/7gPUjc3Bjh

83 views 0 likes0 RT 2026-10-23
Yago Garitaonaindía
Yago Garitaonaindía@YGaritaonaindia
𝕏

When INTerpath-001 opened, neoadjuvant pembro had only one randomized phase 2 behind it. The phase 3 evidence came later with NADINA. Adjuvant pembro was a justified control arm. Evidence often moves faster than trials, that's everyday oncology. But I insist, it only applies to macroscopic disease, not to IIB-IIC or cN0 stage III.

75 views 1 likes0 RT 2026-10-23
ツチノコ在宅ケモ屋
ツチノコ在宅ケモ屋@tsurutacl
𝕏

ツチノコ的ESMOレビュー① いきなり情報解禁前にデータが漏れるという大波乱の幕開けです。 モデルナの株価が25%下落の 大・暴・落!! 個別化mRNAがんワクチン 「intismeran autogene」 の第Ⅲ相試験、INTerpath-001ですね。 すでにデータが世に出てしまったため、ESMOが正式に情報解禁を前倒ししました。 これ、何をやっているかというと、、 患者さんのがんの遺伝子情報を調べて、その人のがんに特有の目印を狙うmRNAワクチンを作る。 それを使って、免疫に 「この目印のあるがん細胞を攻撃してくれ」 と教える治療です。 患者さんごとに作る、オーダーメイドのがんワクチンですね。 今回の対象は完全切除後のStage IIB〜IVの悪性黒色腫の患者さん1,137人。 ①個別化mRNAがんワクチン+キイトルーダ(Pembrolizumab) ②キイトルーダ単独 を比較しています。 結果は、、 【2年無再発生存率】 82.2% vs 70.0% HR 0.58、p<0.001 再発または死亡のリスクが42%低下。 【2年遠隔転移無生存率】 88.5% vs 80.2% HR 0.62、p=0.002 遠隔転移または死亡のリスクが38%低下。 Grade 3〜5の治療関連有害事象は 14.2% vs 13.4%でした。 全生存期間はまだ追跡が必要ですが、キイトルーダに上乗せして再発を減らしたというのは、臨床的には重要な結果だと思います。 ところが、、 モデルナの株価は、データ公開後に25%超下落したと報じられています。 「え、効いてるのに何で?」 ってなりますよね。 そもそもモデルナ株は、今回の治療への期待などから年初来500%超も上昇していました。 なので、良い結果が出ること自体は、すでに株価に織り込まれていたという話です。 加えて、先行する第Ⅱ相試験から期待されていたほどには 遠隔転移を抑える効果が大きくなかった、という受け止めもあったようです。 ただし、対象や追跡期間の違う試験をそのまま比較して「効果が落ちた」とは言えません。 個人的には、患者さんごとに作るmRNAがんワクチンが、第Ⅲ相で再発抑制効果を示したこと自体が大きいと思います。 ただ、これで色々ながんに効くと決まったわけではありません。 まずはメラノーマでの結果として評価して、OSと他のがん種の試験の結果を今後は見ていきたいですね。 ツチノコ的には数十年もすればゲノム含めがん治療は完全に個別化される可能性があると思っているので 標準治療の教育体系から変えていかなくてはならないのでは? という印象です。 公式資料: https://t.co/NWcEXu7k0B⁠ #ESMO26 米モデルナの株価が一時26%安 治験データ漏洩、期待に届かず:日本経済新聞 https://t.co/ZM4mZ3zM9N

7.1K views 55 likes6 RT 2026-10-22
NonsparseOncologist
NonsparseOncologist@5_utr
𝕏

‼️ Interesting commentary on INTerpath-001 No need for vaccine if pembro given neoadjuvant? Wow, await further details / data here, but what a dud! Precision/Personalized dud https://t.co/i1SNiVUjfz

1.6K views 15 likes4 RT 2026-10-22
Eric Topol
Eric Topol@EricTopol
𝕏

How to improve outcomes in patients with metastatic melanoma post-surgical resection, and specifically, vs controls: —Reduce 2-year mortality from 82 to 70% —Reduce recurrence by 42% Treat with a personalized mRNA neoantigen vaccine @statnews @adamfeuerstein

8,214 views 55 likes11 RT 2026-10-22
Yago Garitaonaindía
Yago Garitaonaindía@YGaritaonaindia
𝕏

🚨 #ESMO26 INTerpath-001 leaked before the embargo, so @myESMO released it early ➡️ Intismeran (mRNA-4157) + pembro vs placebo + pembro, adjuvant stage IIB-IV #melanoma • 24-mo RFS 82.2% vs 70.0% | HR 0.58 • 24-mo DMFS 88.5% vs 80.2% | HR 0.62 • G≥3 AEs 23.6% vs 20.3% 👇👇

1,130 views 4 likes1 RT 2026-10-22
Mark Yarchoan
Mark Yarchoan@MarkYarchoan
𝕏

Topline ESMO data from INTerpath-001 (#Moderna’s personalized cancer vaccine) reportedly leaked elsewhere: DFS HR 0.58 This hazard ratio puts it in the company of the most paradigm-changing adjuvant trials in oncology history:

828 views 2 likes2 RT 2026-10-22
Omid Hamid, MD
Omid Hamid, MD@OmidHamidMD
𝕏

@moderna_tx will ultimately find its strength in solid tumors including melanoma that have poor response to neoadjuvant as adjuvant combo including #nsclc - don't forget that there are many stage 3 patients that aren't offered neoadjuvant. Also a broader group of III melanoma based on sentinel node - benefit for a broader group. The head to head comparison is false.

578 views 2 likes1 RT 2026-10-22
Amol Akhade
Amol Akhade@SuyogCancer
𝕏

🚨 ESMO 2026 | INTErpath-001 (LBA1) - as data is released by Esmo 🔹 24-month RFS: 82.2% vs 70.0% HR 0.58 (95% CI 0.45–0.75); P<0.001 🔹 24-month DMFS: 88.5% vs 80.2% HR 0.62 (95% CI 0.45–0.85); P=0.002 🔹 Grade ≥3 adverse events: 23.6% vs 20.3% The trial randomized 1,137 patients with resected stage IIB–IV melanoma. Both arms received pembrolizumab; the experimental arm added an individualized mRNA neoantigen therapy. The key question now: will better recurrence control translate into an overall survival benefit? Looking forward to full dataset on day 2 . #ESMO26 @myESMO

452 views 4 likes1 RT 2026-10-22
Estela Rodriguez
Estela Rodriguez@Latinamd
𝕏

🤷🏽‍♀️Proof that the market is irrational. This now officially released Merck/Moderna cancer vaccine (mRNA-457) results from a Phase 3 study of 1,100 pts w high-risk melanoma to be presented at #ESMO26 look impressive to me- cuts melanoma death or recurrence risk by 42% and cancer metastases by 38% but shares fall ?

404 views 7 likes1 RT 2026-10-22
Yakup Ergün
Yakup Ergün@dr_yakupergun
𝕏

An embargo breach at a congress as prestigious as ESMO is unacceptable. If I remember correctly, something similar happened in 2023. It is deeply troubling to feel that sharing scientific data is driven more by stock market movements than by patients and science…!!!

172 views 1 likes1 RT 2026-10-22
Pablo Jiménez
Pablo Jiménez@PaulJiL
𝕏

@OncoAlert @brunolarvol @adamfeuerstein An alleged third-party leak of the top plenary presentation of the #interpath-001 at #ESMO2026 . Source still unknown. #Intismeran autogene + pembro reportedly reduced recurrence or death (EFS) risk by 42% (HR 0.58) for resected IIB-IV #melanoma Possible #PracticeChanging pending safety and full text publication

141 views 0 likes0 RT 2026-10-22
Estela Rodriguez
Estela Rodriguez@Latinamd
𝕏

Looking forward to the presentation and discussion. #LBA1 Phase 3 INTerpath-001 trial results at #ESMO26 👉🏽The Kaplan-Meir curves don’t always tell the whole story. Side effects, cost, access matter but 👉🏽Its is very exciting that a personalized mRNA technology can be used to control cancer recurrence.

101 views 1 likes0 RT 2026-10-22
Mustafa Özdoğan, MD
Mustafa Özdoğan, MD@ozdogan_md
𝕏

Personalised mRNA therapy reaches Phase 3 in melanoma: INTerpath-001 met RFS and DMFS with intismeran autogene + pembrolizumab. The key question now is magnitude-HRs, absolute benefit and detailed toxicity are still awaited. Presented by @ProfGLongMIA at @myESMO. Developed by @moderna_tx + @Merck. #ESMO26 #Melanoma

315 views 5 likes4 RT 2026-10-20
Yakup Ergün
Yakup Ergün@dr_yakupergun
𝕏

I’d applaud these trials, but I’d remain seated 😅😅 INTerpath-001 is an innovative treatment approach. However, there is no comparison with neoadjuvant nivo + ipi, a strong option particularly in macroscopic stage III melanoma. DeLLphi-305 showed a survival benefit with maintenance tarlatamab + durvalumab. But the comparator is durvalumab monotherapy. We also have positive results from IMforte with maintenance atezo + lurbinectedin. So this is another potential maintenance option; its place among the existing options remains to be defined. In HARMONi-GI1, even if not one but three trucks could fit between the Kaplan–Meier curves, global validation will still be expected because the trial was conducted exclusively in China 🫣 For me, VOLGA’s most interesting feature is the omission of adjuvant EV. As for the survival benefit of perioperative EV + immunotherapy, we already have strong data.

999 views 9 likes1 RT 2026-10-19
Enrique Grande@drenriquegrande
𝕏

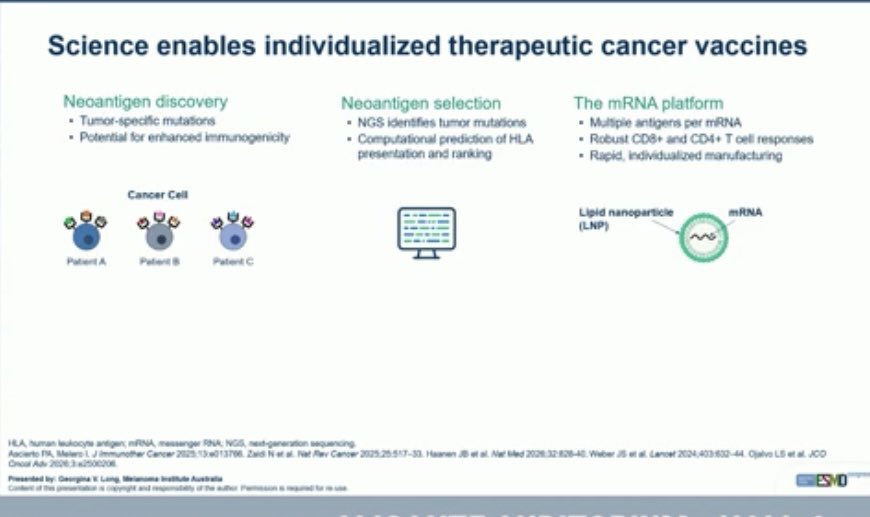
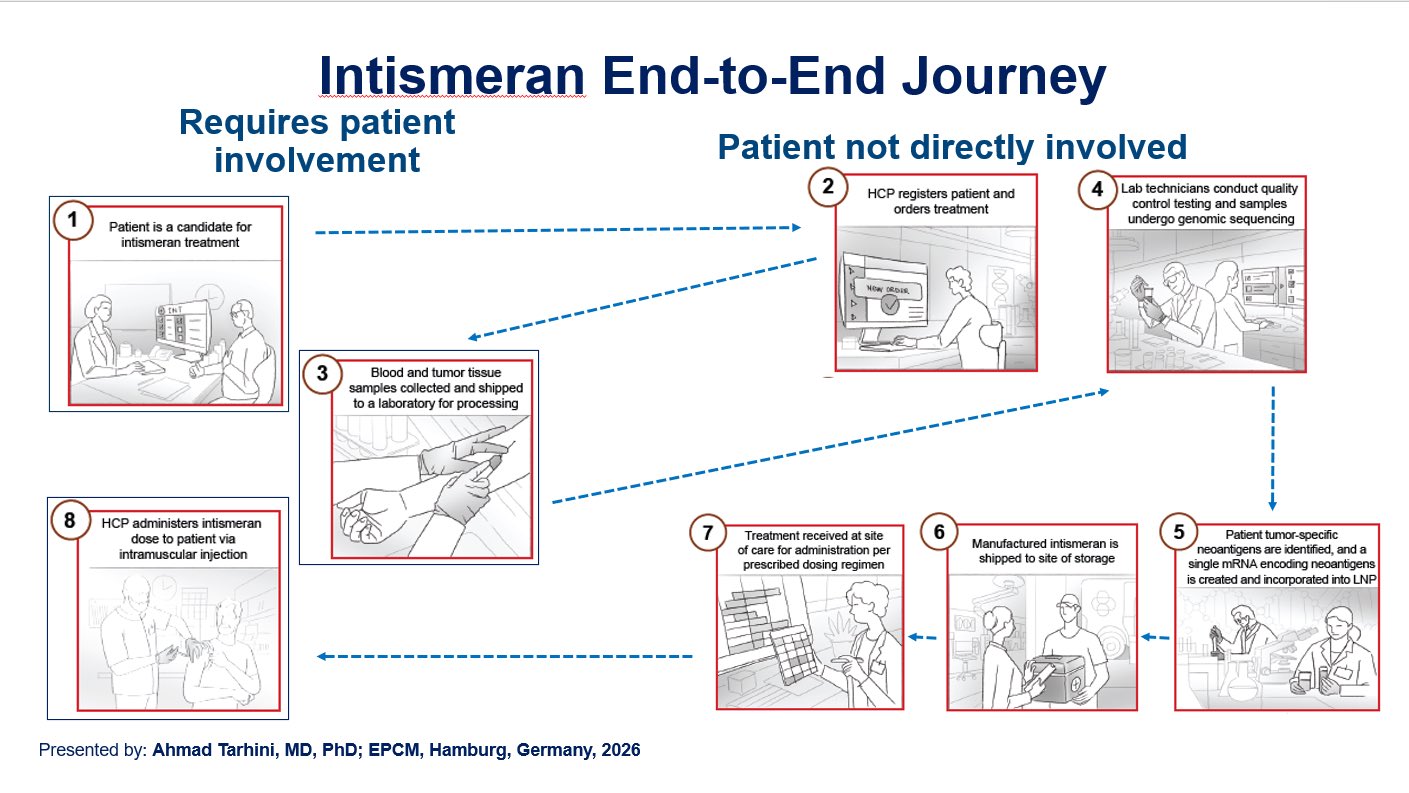
🧬 HOW DOES A PERSONALIZED mRNA CANCER VACCINE ACTUALLY WORK? As an oncologist, and also as a university professor, I strongly believe that understanding how a new treatment works is often the best way to understand why it may eventually change our clinical practice. So, what exactly is a personalized mRNA cancer vaccine? The concept is both sophisticated and surprisingly intuitive. 1️⃣ Start with the patient's own tumor 🧬 Every cancer is genetically different. By sequencing tumor DNA and RNA, and comparing this information with normal tissue , we can identify tumor-specific mutations. Some of these mutations generate abnormal proteins that are not present in healthy cells. These are called neoantigens. And importantly, they can become molecular "flags" allowing the immune system to distinguish cancer cells from normal cells. 2️⃣ Select the best targets 🎯 Not every mutation will generate an effective immune response. Bioinformatic algorithms therefore analyze the patient's tumor and predict which neoantigens are most likely to be recognized by their immune system. In the case of intismeran autogene, up to 34 patient-specific neoantigens can be selected. 3️⃣ Build an individualized mRNA therapy 💉 Here comes the fascinating part. A synthetic mRNA sequence encoding those selected neoantigens is manufactured specifically for that individual patient. Think about what this means. We are no longer simply choosing the best available drug for a patient. We are manufacturing a treatment based on the molecular identity of that patient's own cancer. 4️⃣ Teach the immune system what to recognize 🛡️ After administration, the mRNA enters cells and provides the instructions to produce the selected neoantigens. These neoantigens are processed and presented to the immune system, activating tumor-specific CD4+ and CD8+ T cells. The objective is to generate an immune response capable of recognizing cells carrying those same neoantigens. 5️⃣ Let T cells search for the cancer 🔎 Those activated T cells can then recognize tumor cells displaying the corresponding antigens and potentially destroy them. This is why combining personalized vaccination with PD-1 blockade such as pembrolizumab makes so much biological sense: 🎯 The vaccine may teach the immune system WHAT to attack. 🔓 Checkpoint inhibition may help the immune system KEEP attacking it. And this is where, in my view, the concept becomes much bigger than one drug or one tumor type. For many years, we have defined precision oncology as: “the right treatment for the right patient.” Personalized mRNA vaccines introduce an even more ambitious paradigm: “a treatment designed and manufactured specifically from the molecular characteristics of one patient's cancer.” @OncoAlert @_SEOM @moderna_tx @GEPAC_ Figure adapted from: doi:10.3390/cancers17091408.

77.2K views 718 likes257 RT 2026-08-20
G Curigliano MD PhD@curijoey
𝕏

Don’t miss the data at #ESMO2026 https://t.co/vFiJ0ruccU [QUOTED] JUST IN and via @Merck + @moderna_tx: A landmark moment for cancer immunotherapy. 🎯 Phase 3 INTerpath-001 is positive: the individualized mRNA neoantigen therapy intismeran (V940/mRNA-4157) + pembrolizumab significantly improved both RFS/DMFS vs pembrolizumab alone after resection of high-risk melanoma. For years, the idea of designing a treatment around the unique mutations of each patient’s tumor seemed aspirational. Now we have the first positive Phase 3 trial (N=1137) of an individualized neoantigen therapy—and of an mRNA-based cancer therapy. Personalized cancer vaccines are moving from promise to reality. Now we need to see the magnitude of benefit, durability, and ultimately OS. But today is an important day for the field—and hopefully for our patients. 👏 Congrats to #CathyWu @DanaFarber for her trailblazing research that is materializing in tangible outcomes! At @DanaFarber_GU we are closely working with Cathy + @DFCI_NeoVax team on several GU protocols, after our @Nature work with @BraunMDPhD et al (https://t.co/BdbKJqMKOw) https://t.co/Akd0XQt3ml

18.1K views 58 likes10 RT 2026-08-20
Enrique Grande@drenriquegrande
𝕏

💉 Personalized mRNA cancer vaccines like intismeran autogene (V940/mRNA-4157) can work in genitourinary cancers? Three ongoing studies are particularly interesting. 🔵 KIDNEY CANCER — INTerpath-004 This randomized, double-blind Phase II study is evaluating adjuvant: V940 + pembrolizumab vs placebo + pembrolizumab following nephrectomy in patients with RCC at increased risk of recurrence. The primary endpoint is disease-free survival, with distant metastasis-free survival and overall survival among the secondary endpoints. If individualized neoantigen vaccination works in RCC, it could therefore tell us something very important about the biology of this platform: its potential may extend beyond simply selecting tumors with very high mutational burden. 🟠 MUSCLE-INVASIVE BLADDER CANCER — INTerpath-005 Here the development strategy is even more ambitious. INTerpath-005 is a Phase I/II program exploring V940 in two different settings. One cohort evaluates a perioperative strategy combining: V940 + pembrolizumab + enfortumab vedotin in cisplatin-ineligible patients undergoing radical cystectomy. Another randomized cohort evaluates adjuvant: V940 + pembrolizumab vs placebo + pembrolizumab in patients with high-risk resected muscle-invasive urothelial carcinoma. Could we combine three completely different therapeutic principles? 💥 EV → rapidly kills Nectin-4-expressing tumor cells 🔓 Pembrolizumab → releases PD-1-mediated immune inhibition 🎯 V940 → potentially generates an individualized T-cell response against that patient's unique tumor neoantigens ADC + checkpoint inhibition + personalized vaccination. Three mechanisms. One objective: eradicate micrometastatic residual disease before it can become clinically visible. And there is another bladder cancer study that should not be overlooked. 🟡 NON-MUSCLE-INVASIVE BLADDER CANCER — INTerpath-011 This ongoing randomized Phase II study is evaluating: V940 + BCG vs BCG alone in treatment-naïve high-risk NMIBC. I find this particularly intriguing. BCG has successfully exploited the immune system against bladder cancer for decades. Combining this established local immunotherapy with a systemic, individualized neoantigen-directed immune strategy represents a completely different way of thinking about treatment intensification in early bladder cancer. Of course, none of these studies is guaranteed to reproduce what we have seen in melanoma. For someone who has spent much of his career developing new treatments for kidney and bladder cancer, I find the possibility particularly exciting. Precision oncology has traditionally meant finding the right drug for the right patient. Personalized mRNA vaccines introduce an even more ambitious concept: creating a different drug for each individual patient's cancer. @OncoAlert @_SEOM @GuardConsortium @urotoday @GUOncologyNow @LACOG_group @GEPAC_

2.2K views 33 likes9 RT 2026-08-20
Eric Topol@EricTopol
𝕏

The mRNA vaccine success vs melanoma in a Phase definitive 3 randomized trial today is on top of signs of success for personalized mRNA neoantigen vaccines vs pancreatic cancer, triple negative breast cancer, and non-small cell lung cancer https://t.co/cv4iXW11mw

12.4K views 0 likes0 RT 2026-08-19
Paolo Tarantino@PTarantinoMD
𝕏

Positive phase 3 data for adjuvant pembro +/- personalized mRNA-based neoantigen vaccine for melanoma just announced by Merck and Moderna. Welcome to the future! https://t.co/rlKAvv7sbo https://t.co/BxYKh4NKKw

3.3K views 65 likes23 RT 2026-08-19
Balazs Halmos@BalazsHalmosMD
𝕏

Newly minted twins- Intismeran and pembro are feeling pretty good today https://t.co/62jEnUt1mk https://t.co/5F8aw2rFqf [QUOTED] Are you into Intismeran- the new “individualized neoantigen therapy” (graciously avoiding the term “vaccine”) from Merck/Moderna? If you haven’t- you should! Maybe biggest news in onc for some time along w daraxonrasib- positive results in pivotal melanoma trial as to RFS improvement of this Space age technology which still makes my head spin- whole genome seq- neoantigen selection- personalized “INT” delivered to your patient in just a few weeks… and it works! Many studies ongoing in lung/bladder etc- eager to learn results (and continue to offer to our pts at Monte @BrendonStilesMD !) Now Back to the Future and let’s keep enrolling!

2.9K views 25 likes2 RT 2026-08-19
Toni Choueiri, MD@DrChoueiri
𝕏

JUST IN and via @Merck + @moderna_tx: A landmark moment for cancer immunotherapy. 🎯 Phase 3 INTerpath-001 is positive: the individualized mRNA neoantigen therapy intismeran (V940/mRNA-4157) + pembrolizumab significantly improved both RFS/DMFS vs pembrolizumab alone after resection of high-risk melanoma. For years, the idea of designing a treatment around the unique mutations of each patient’s tumor seemed aspirational. Now we have the first positive Phase 3 trial (N=1137) of an individualized neoantigen therapy—and of an mRNA-based cancer therapy. Personalized cancer vaccines are moving from promise to reality. Now we need to see the magnitude of benefit, durability, and ultimately OS. But today is an important day for the field—and hopefully for our patients. 👏 Congrats to #CathyWu @DanaFarber for her trailblazing research that is materializing in tangible outcomes! At @DanaFarber_GU we are closely working with Cathy + @DFCI_NeoVax team on several GU protocols, after our @Nature work with @BraunMDPhD et al (https://t.co/BdbKJqMKOw) https://t.co/Akd0XQt3ml

2.5K views 45 likes16 RT 2026-08-19
Hidehito HORINOUCHI@HHorinouchi
𝕏

🔥INTerpath-002: Adj Pembrolizumab + V940 (mRNA-4157) vs. Pembro 🆙 @Merck @moderna_tx 🎯Primary completion: 2030-06-25 👥Patients: Completely resected (R0) Stage II, IIIA or IIIB (N2) NSCLC, post-surgery and adjuvant chemotherapy 3⃣Phase III ⚖️Intismeran autogene (mRNA-4157) + pembrolizumab ⚖️Pembrolizumab alone (+ placebo) 🔢NCT06077760 #LCSM @OncoAlert @Larvol

2.5K views 17 likes5 RT 2026-08-19
Sara Coca Membribes@scocmem
𝕏

A milestone for individualised neoantigen therapy and encouraging for the broader V940 (mRNA-4157) programme! Will the melanoma signal translate to GU cancers? - INTerpath-004: V940 + pembro vs pembro in adjuvant RCC - INTerpath-005: V940 + pembro vs pembro in MIUC @OncoAlert https://t.co/Q16XNfFHJX https://t.co/leaRqALAaQ

1.9K views 14 likes10 RT 2026-08-19
Hidehito HORINOUCHI@HHorinouchi
𝕏

mRNA-4157-P201/KEYNOTE-942: Pembrolizumab +/- mRNA-4157 (V940, personalized cancer vaccine) as adjuvant therapy in resectable melanoma, a randomized phase 2, open-label study by Dr. Jeffrey Weber. What happens in melanoma will happen in lung cancer. #AACR23 #LCSM https://t.co/Rebrpl0Ltb

44.5K views 41 likes16 RT 2023-04-17

Note: per the ESMO 2026 LBA1 abstract, 82.2% vs 70.0% are 24-month recurrence-free survival rates (intismeran + pembrolizumab vs placebo + pembrolizumab), not mortality rates.

INTerpath-001 Key Takeaways

Results — ESMO 2026 LBA1 (presented Oct 24, 2026)

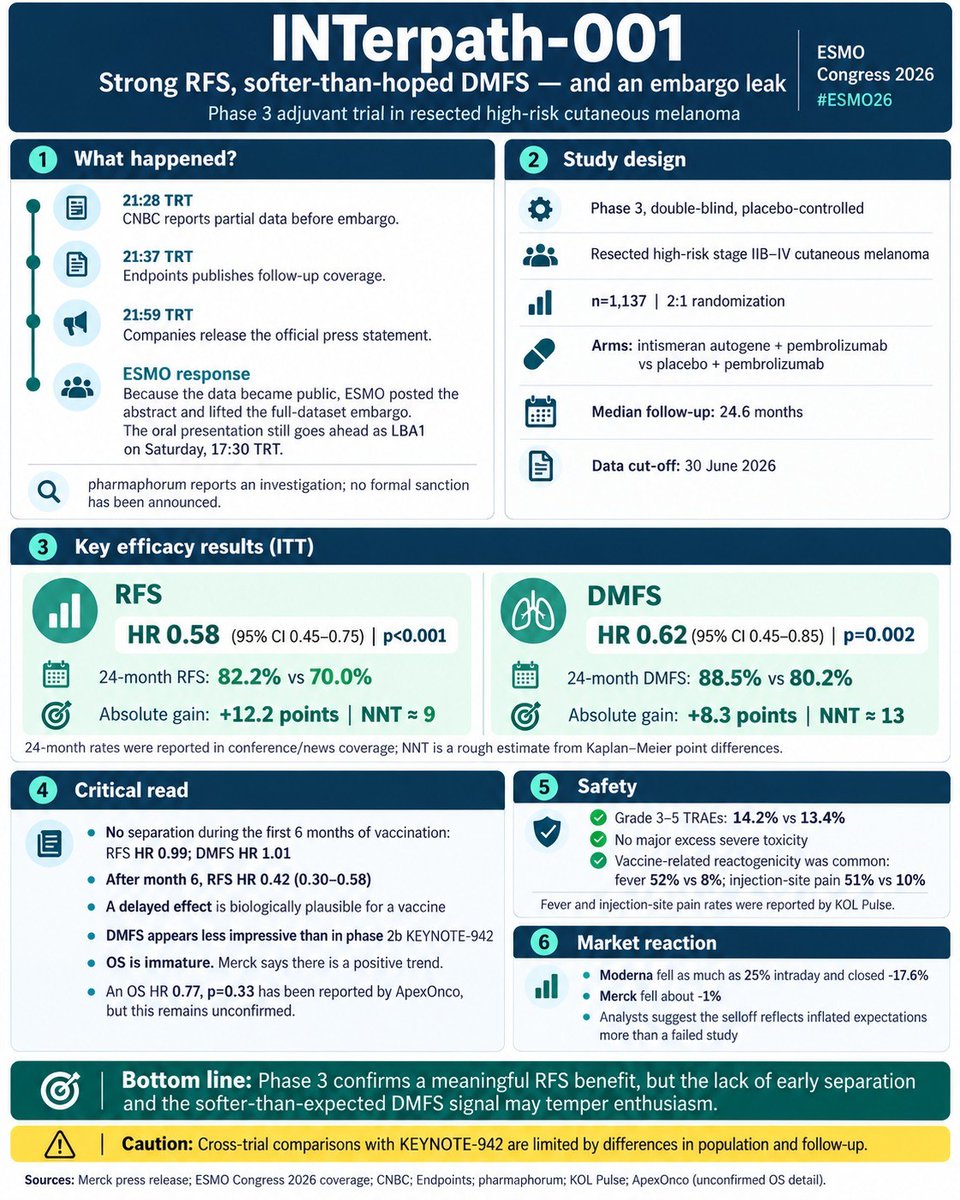
ITT, N=1,137 (757 vs 380); DCO 30-Jun-2026, median follow-up 24.6 mo. RFS (primary): 136 (18.0%) vs 111 (29.2%) events; HR 0.58 (95% CI 0.45–0.75), two-sided P<0.001 (multiplicity-adjusted significance level 0.024692); 24-month RFS 82.2% (79.3–84.8) vs 70.0% (65.0–74.5). DMFS (key secondary): 89 (11.8%) vs 71 (18.7%) events; HR 0.62 (0.45–0.85), two-sided P=0.002 (significance level 0.01608); 24-month DMFS 88.5% (86.0–90.6) vs 80.2% (75.6–84.0). Overall survival (secondary): immature and did not meet the prespecified significance boundary — HR 0.77 (0.45–1.31), two-sided P=0.33; follow-up is ongoing. RFS sensitivity analyses: piecewise HR 0.99 (0.66–1.49) for months 0–6 and 0.42 (0.30–0.58) after month 6 (ITT); mITT (patients who received intismeran or placebo as assigned, 726 vs 365) HR 0.51 (0.39–0.67), 24-month RFS 84.2% vs 70.4%. Topline (Aug 19, 2026): met the primary endpoint (RFS) and the key secondary endpoint (DMFS) — per the PR, the “first and only combination regimen” to do so in this adjuvant melanoma population; effect sizes were not announced at topline.
RFS HR 0.58 · DMFS HR 0.62 · OS immature (HR 0.77, P=0.33)
Source: ESMO 2026 LBA1 RFS/DMFS slides (Long) · LBA1 piecewise + summary slides (OS footnote) · LBA1 mITT slide · Merck/Moderna topline PR

Presented: ESMO 2026 Presidential Symposium (LBA1, Oct 24, 2026)

Moderna announced three intismeran autogene abstracts at ESMO Congress 2026 (October 23–27, Madrid). The INTerpath-001 Phase 3 full results were presented in the Presidential Symposium as LBA1 on October 24, 2026 by Professor Georgina V. Long (invited discussant: Inge Marie Svane). ESMO had released the abstract on October 22 after the embargo was breached; its figures are in the collapsed October 22 abstract-release panel near the bottom of this page, and the presented slides are in the Slides section. Moderna PR, Sept 21, 2026

Safety

As-treated population 755 vs 380 (DCO 30-Jun-2026, median follow-up 24.6 mo). All-cause grade 3–5 AEs 23.6% vs 20.3%; treatment-related grade 3–5 AEs 14.2% vs 13.4%; all-cause serious AEs 17.6% vs 15.8% (treatment-related 9.8% vs 11.1%). All-cause AEs led to discontinuation of any drug in 16.6% vs 9.5% (treatment-related 14.0% vs 8.7%); all-cause discontinuation of both drugs simultaneously 6.5% vs 5.3%. All-cause AEs led to death in 8 (1.1%) vs 0 patients, none related to intismeran; treatment-related AEs leading to death 2 (0.3%) vs 0. The presenter concluded that safety was generally consistent with previous experience, with no potentiation of pembrolizumab-associated AEs. Source: ESMO 2026 LBA1 adverse event summary slide (Long) · LBA1 summary slide

The KEYNOTE-942 antecedent — where today’s circulating numbers come from

The randomized Phase 2b KEYNOTE-942 (n=157, resected stage III/IV) first showed the benefit, consistent across every analysis (per Dr. Carlino’s ASCO 2026 slide, transcribed on this page): primary (Nov 14, 2022 cut) RFS HR 0.561 (95% CI 0.309–1.017, P=0.0266); 3-year (Nov 3, 2023) HR 0.510 (0.288–0.906); 5-year (Dec 15, 2025) HR 0.510 (0.294–0.887) — plus 5-year DMFS HR 0.411 (0.200–0.843, per the topline PR). ⚠ Hazard ratios circulating on announcement day are these Phase 2b figures — INTerpath-001’s own figures come from its LBA1 abstract (RFS HR 0.58, 95% CI 0.45–0.75) (ESMO 2026 LBA1 abstract, DCO 30-Jun-2026, median f/u 24.6 mo). Merck: KEYNOTE-942 5-year data

Regulatory status & clinical implications

⚠ Investigational — not approved by FDA or any other regulator. Merck and Moderna plan to engage regulators on filing submissions for intismeran + pembrolizumab based on these results. If the presented magnitude holds up, adjuvant melanoma would gain its first individualized therapy on top of PD-1 blockade — and the INT modality gains randomized Phase 3 validation with read-through to the sibling INTerpath programs (NSCLC, bladder, 1L melanoma). Physicians on this page flag the open questions: magnitude of benefit, durability, OS, manufacturing turnaround and cost. Merck topline PR

Free Access · KOL Pulse Intelligence

Track oncology’s top KOLs in your specialty

Create a free account, pick the tumor types you cover, and go beyond the tweet — the intelligence pharma teams use to map influence and prepare for engagement:

  • ✓Enhanced KOL profiles
  • ✓Pharma influence & potential advisory-board patterns
  • ✓2025 Open Payments financial analysis
  • ✓Social-media sentiment & trend signals
Get free access — pick your specialty
Choose the tumor types you follow. No cost, unsubscribe anytime.

Top KOLs Discussing INTerpath-001

Professor Georgina Long AO
Georgina Long, AO
Principal Investigator
Enrique Grande
Enrique Grande
80.0K impressions
Hidehito HORINOUCHI
Hidehito HORINOUCHI
47.5K impressions
G Curigliano MD PhD
G Curigliano MD PhD
18.1K impressions
Eric Topol
Eric Topol
12.4K impressions
Balazs Halmos
Balazs Halmos
4.3K impressions
Paolo Tarantino
Paolo Tarantino
3.3K impressions
Toni Choueiri, MD
Toni Choueiri, MD
2.5K impressions
Sara Coca Membribes
Sara Coca Membribes
1.9K impressions
Tom Powles
Tom Powles
1.5K impressions
Henry C Fung| MM, lymphoma, leukemia & CART
1.4K impressions
Dr. Estela Rodriguez
1.4K impressions
Anirban Maitra
Anirban Maitra
1.2K impressions
Markus Eckstein
Markus Eckstein
722 impressions
Daisuke Kotani, MD, Ph.D 小谷 大輔
696 impressions
Elvina Almuradova
Elvina Almuradova
528 impressions
Ahmad Tarhini
Ahmad Tarhini
379 impressions
Mario Balsa
Mario Balsa
1.2K impressions
Patrick Forde
Patrick Forde
228 impressions
Niklas Klümper
Niklas Klümper
227 impressions
Yüksel Ürün
Yüksel Ürün
218 impressions
Vivek Subbiah, MD
Vivek Subbiah, MD
214 impressions
Allan Pereira, MD, PhD
206 impressions
Yannick Buccella MD
Yannick Buccella MD
170 impressions
Eric D Whitman, MD
Eric D Whitman, MD
117 impressions
Syed A. Ahmad
Syed A. Ahmad
113 impressions
Gavitt Woodard
Gavitt Woodard
66 impressions
Arturo LoAIza-Bonilla, MD MSEd
40 impressions
Yago Garitaonaindía
Yago Garitaonaindía
482 impressions
Tarek Haykal, MD, MHS
30 impressions
MJosé Juan
MJosé Juan
20 impressions
Jose Fernando Moura, PhD
10 impressions

INTerpath-001 Key Slides & Visuals

Presented at ESMO 2026 (October 24, 2026)

LBA1, Presidential Symposium I, presented by Georgina V. Long (Melanoma Institute Australia); invited discussant Inge Marie Svane. Data cutoff June 30, 2026 (median study follow-up 24.6 months). Slides as photographed and shared by physicians on X; survival-curve values are in tables built only from numbers printed on the slides. Intismeran autogene is investigational. Click any image to enlarge.

Hidehito HORINOUCHI
Hidehito HORINOUCHI @HHorinouchi · #ESMO26 · Oct 24, 2026
INTerpath-001 · ESMO 2026 · Oct 24, 2026
Study design · RFS (primary) · DMFS (key secondary) · AEs ≥10%
View post on X ↗
Recurrence-free survival, ITT primary analysis
RFS, ITT (DCO 30-Jun-2026, median f/u 24.6 mo)NEvents, n (%)Median (95% CI)24-month RFS (95% CI)
Intismeran + pembrolizumab757136 (18.0%)Not printed82.2% (79.3–84.8)
Placebo + pembrolizumab380111 (29.2%)Not printed70.0% (65.0–74.5)
HR 0.58 (95% CI 0.45–0.75); P < 0.001, two-sided (multiplicity-adjusted significance level, two-sided 0.024692).
Distant metastasis-free survival, ITT primary analysis
DMFS, ITT (DCO 30-Jun-2026, median f/u 24.6 mo)NEvents, n (%)Median (95% CI)24-month DMFS (95% CI)
Intismeran + pembrolizumab75789 (11.8%)Not printed88.5% (86.0–90.6)
Placebo + pembrolizumab38071 (18.7%)Not printed80.2% (75.6–84.0)
HR 0.62 (95% CI 0.45–0.85); P = 0.002, two-sided (multiplicity-adjusted significance level, two-sided 0.01608).
[Slide 1] INTerpath-001: Randomized, Double-Blind, Phase 3 Trial Key Eligibility Criteria • Age ≥18 years • Resected cutaneous melanoma • AJCC 8th ed. Stage IIB/IIC (clinical IIB/IIC permitted), III, or IV • FFPE tumor sample suitable for NGS and intismeran generation • No prior systemic therapy • ECOG PS 0 or 1 R 2:1 Intismeran 1 mg IM Q3W for 9 doses + Pembrolizumab 400 mg IV Q6W for 9 cycles Placeboa IM Q3W for 9 doses + Pembrolizumab 400 mg IV Q6W for 9 cycles Stratification factors • Risk-based stage (IIB/IIC/IIIA/IIIB vs IIIC/IIID/IV) • Age (<65 years vs ≥65 years) Pembrolizumab • Started at randomization, ≤13 weeks after resection Intismeran • Started upon availability to site • Earliest: Cycle 1, day 22 • Latest: Cycle 4, day 1 Primary end point: RFS per investigator Secondary end points: DMFS per investigator, OS, patient-reported outcomes, safety aNormal saline or dextrose. Placebo was started at random to maintain the blind. ClinicalTrials.gov identifier: NCT05933577. Presented by: Georgina V. Long, Melanoma Institute Australia --- [Slide 2] RFS Primary Analysis: ITT HR 0.58 (95% CI 0.45–0.75) P < 0.001 (two sided)a 82.2% (95% CI 79.3–84.8) 70.0% (95% CI 65.0–74.5) | N | Events, n (%) Intismeran + pembrolizumab | 757 | 136 (18.0%) Placebo + pembrolizumab | 380 | 111 (29.2%) aMultiplicity-adjusted significance level: two-sided 0.024692. ITT: all randomized patients according to the arm to which they were assigned. RFS: time from randomization to the first occurrence of any recurrence or death from any cause. Data cutoff date: June 30, 2026 (median study follow-up, 24.6 mo). Presented by: Georgina V. Long, Melanoma Institute Australia (Survival-curve slide: number-at-risk rows and axis ticks omitted; printed values are in the table above.) --- [Slide 3] DMFS Primary Analysis: ITT HR 0.62 (95% CI 0.45–0.85) P = 0.002 (two sided)a 88.5% (95% CI 86.0–90.6) 80.2% (95% CI 75.6–84.0) | N | Events, n (%) Intismeran + pembrolizumab | 757 | 89 (11.8%) Placebo + pembrolizumab | 380 | 71 (18.7%) aMultiplicity-adjusted significance level: two-sided 0.01608. ITT: all randomized patients according to the arm to which they were assigned. DMFS: time from randomization to first occurrence of distant metastasis or death from any cause. Data cutoff date: June 30, 2026 (median study follow-up, 24.6 mo). Presented by: Georgina V. Long, Melanoma Institute Australia (Survival-curve slide: number-at-risk rows and axis ticks omitted; printed values are in the table above.) --- [Slide 4] All-Cause AEs, Incidence ≥10% AE | Intismeran + Pembrolizumab (N = 755) % | Placebo + Pembrolizumab (N = 380) % Pyrexia | 52.2 | 8.2 Injection site pain | 51.0 | 9.5 Fatigue | 38.5 | 29.7 Influenza-like illness | 25.4 | 9.2 Diarrhea | 23.7 | 23.7 Pruritus | 23.4 | 23.4 Headache | 23.3 | 13.2 Arthralgia | 22.6 | 23.2 Injection site reaction | 21.6 | 1.6 Nausea | 21.2 | 15.3 Myalgia | 20.3 | 10.5 Asthenia | 19.9 | 18.2 Injection site erythema | 19.9 | 0.8 Chills | 16.2 | 3.4 Hypothyroidism | 15.8 | 15.5 Rash | 15.1 | 17.6 Cough | 10.9 | 10.3 Dry mouth | 9.7 | 11.3 ~10% greater incidence vs pembrolizumab alone due to intismeran injection Low grade and transient Managed per standard practice Legend: Grade 1–2 | Grade 3–5 As-treated population: all randomized patients who received at ≥1 dose of study treatment. Data cutoff date: June 30, 2026 (median study follow-up, 24.6 mo). Presented by: Georgina V. Long, Melanoma Institute Australia
Prof Tom John
Prof Tom John @TommyJohn00 · #ESMO26 · Oct 24, 2026
INTerpath-001 · ESMO 2026 · Oct 24, 2026
Mechanism of action · Baseline characteristics
View post on X ↗
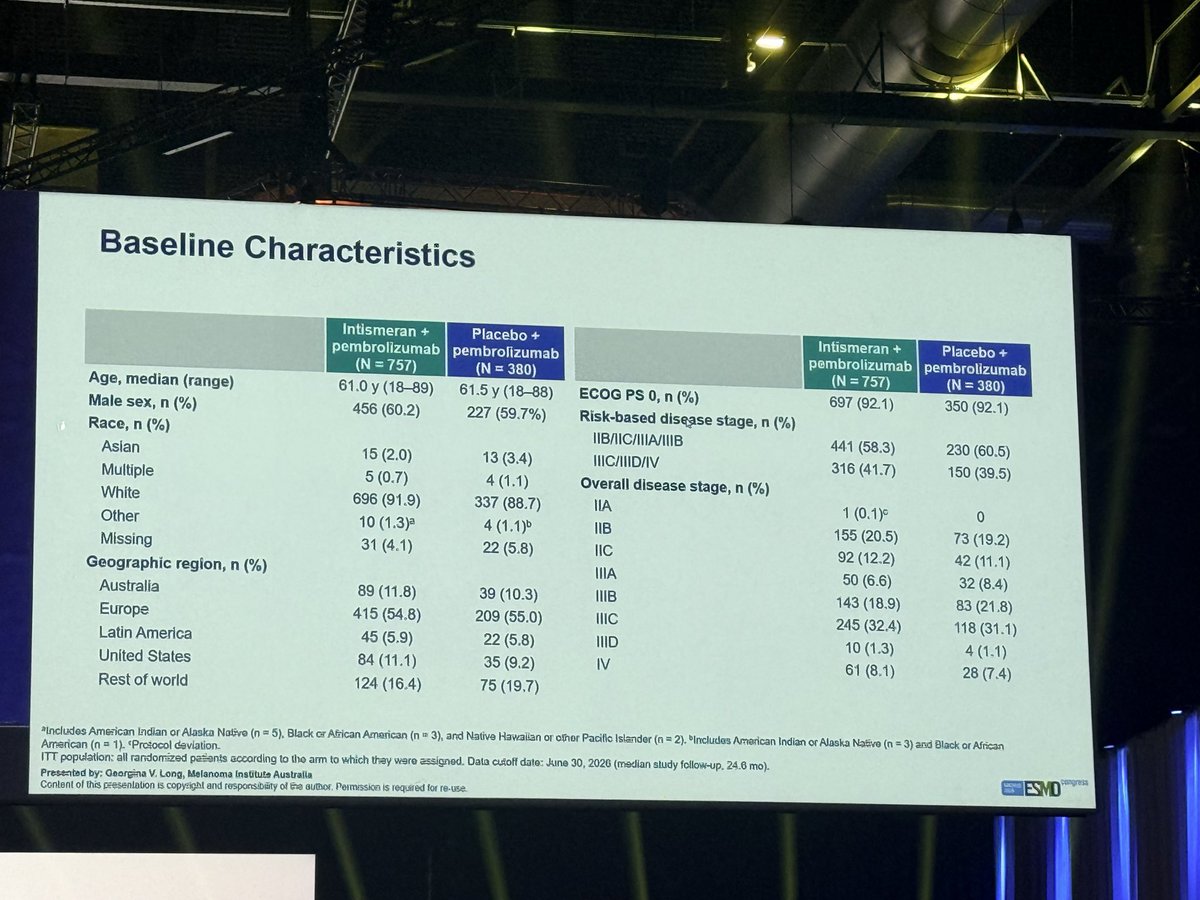
[Slide 1] Intismeran mechanism of action • Intismeran is designed to strengthen existing and create new T cell responses1-3 1 Administer INT 2 mRNA uptake into cells 3 mRNA translated into protein and processed 4 Neoantigen presentation 5 T cell activation and clonal expansion 6 Migration to tumor microenvironment 7 Tumor cell killing APC (eg, dendritic cell); Endosome; Endoplasmic reticulum; Polypeptide; Proteasome; Tumor-specific neoantigens; Endo-lysosomes; MHC I; MHC II; CD8 T cell (cytotoxic activity); CD4 T cell (memory); T cells; CD4+ T cell; CD8+ T cell; Cytokine release; Dying tumor cell aHypothetical mechanism of action. 1Weber JS et al. Lancet 2024;403:632–44. 2Ojalvo LS et al. JCO Oncol Adv 2026;3:e2500206. 3Gainor JF, et al. Cancer Discov. 2024;14(11):2209-2223 Presented by: Georgina V. Long, Melanoma Institute Australia --- [Slide 2] Baseline Characteristics | Intismeran + pembrolizumab (N = 757) | Placebo + pembrolizumab (N = 380) Age, median (range) | 61.0 y (18–89) | 61.5 y (18–88) Male sex, n (%) | 456 (60.2) | 227 (59.7%) Race, n (%) Asian | 15 (2.0) | 13 (3.4) Multiple | 5 (0.7) | 4 (1.1) White | 696 (91.9) | 337 (88.7) Other | 10 (1.3)a | 4 (1.1)b Missing | 31 (4.1) | 22 (5.8) Geographic region, n (%) Australia | 89 (11.8) | 39 (10.3) Europe | 415 (54.8) | 209 (55.0) Latin America | 45 (5.9) | 22 (5.8) United States | 84 (11.1) | 35 (9.2) Rest of world | 124 (16.4) | 75 (19.7) ECOG PS 0, n (%) | 697 (92.1) | 350 (92.1) Risk-based disease stage, n (%) IIB/IIC/IIIA/IIIB | 441 (58.3) | 230 (60.5) IIIC/IIID/IV | 316 (41.7) | 150 (39.5) Overall disease stage, n (%) IIA | 1 (0.1)c | 0 IIB | 155 (20.5) | 73 (19.2) IIC | 92 (12.2) | 42 (11.1) IIIA | 50 (6.6) | 32 (8.4) IIIB | 143 (18.9) | 83 (21.8) IIIC | 245 (32.4) | 118 (31.1) IIID | 10 (1.3) | 4 (1.1) IV | 61 (8.1) | 28 (7.4) aIncludes American Indian or Alaska Native (n = 5), Black or African American (n = 3), and Native Hawaiian or other Pacific Islander (n = 2). bIncludes American Indian or Alaska Native (n = 3) and Black or African American (n = 1). cProtocol deviation. ITT population: all randomized patients according to the arm to which they were assigned. Data cutoff date: June 30, 2026 (median study follow-up, 24.6 mo). Presented by: Georgina V. Long, Melanoma Institute Australia
Dr. Antonio Calles
Dr. Antonio Calles @Tony_Calles · #ESMO26 · Oct 24, 2026
INTerpath-001 · ESMO 2026 · Oct 24, 2026
Treatment disposition and exposure
View post on X ↗
[Slide 1] Treatment Disposition and Exposure 1749 patients screened 302 (17.3%) had inadequate tumor sample 125 (7.1%) not disease free 91 (5.2%) did not provide informed consent 94 (5.4%) excluded for other reasons 1137 randomized (2:1 ratio) 757 to intismeran + pembrolizumab | 380 to placebo + pembrolizumab 756 received ≥1 dose of treatment | 379 received ≥1 dose of treatment 756 received ≥1 dose of pembrolizumab | 379 received ≥1 dose of pembrolizumab 726 (96.0%) received ≥1 dose of intismeran | 365 (96.3%) received ≥1 dose of placebo 1 (0.1%) received ≥1 dose of placebo(a) | 228 (30.2%) discontinued treatment | 117 (30.9%) discontinued treatment 114 (15.1%) adverse event | 37 (9.8%) adverse event 82 (10.8%) recurrence/relapse | 68 (17.9%) recurrence/relapse 32 (4.2%) other | 12 (3.2%) other 528 (69.8%) completed treatment | 262 (69.1%) completed treatment (a)The patient for whom intismeran could not be manufactured received placebo to maintain the blind. Presented by: Georgina V. Long, Melanoma Institute Australia
Yago Garitaonaindía
Yago Garitaonaindía @YGaritaonaindia · #ESMO26 · Oct 24, 2026
INTerpath-001 · ESMO 2026 · Oct 24, 2026
Intismeran design, manufacture and exposure
View post on X ↗
[Slide 1] Intismeran Design, Manufacture,a and Exposure • 91% of the 1137 randomized patients had the maximum 34 neoantigens identified for intismeran design • >99% of the 757 patients in the intismeran + pembrolizumab arm had their intismeran successfully manufactured • Median time to first intismeran dose was 64 days • Median number of intismeran doses was 9b No. neoantigens in each intismeran Median: 34 (range, 7–34) Pie chart legend: 34 | 30-33 | 25-29 | 20-24 | 15-19 | 10-14 | <10 [footnotes a/b largely illegible: aIntismeran was designed for all randomized patients. The manufacturing workflow was initiated when it was known that a patient was randomized to the intismeran + pembrolizumab arm. bThe median number of placebo administrations and pembrolizumab cycles was also [?]] Presented by: Georgina V. Long, Melanoma Institute Australia
Yakup Ergün
Yakup Ergün @dr_yakupergun · #ESMO26 · Oct 24, 2026
INTerpath-001 · ESMO 2026 · Oct 24, 2026
Prespecified subgroups (RFS and DMFS)
View post on X ↗
[Slide 1] Efficacy in Prespecified Subgroups RFS and DMFS benefits observed in most subgroups Recurrence-Free Survival Subgroup | Intismeran + Pembro Events/Patients | Placebo + Pembro Events/Patients | Hazard Ratio (95% CI) All patients | 136/757 | 111/380 | 0.58 (0.45–0.75) Age <65 yr | 79/458 | 61/230 | 0.65 (0.47–0.91) Age ≥65 yr | 57/299 | 50/150 | 0.53 (0.36–0.77) Sex Female | 57/301 | 40/153 | 0.71 (0.47–1.06) Sex Male | 79/456 | 71/227 | 0.54 (0.39–0.74) Australia | 16/89 | 12/39 | 0.54 (0.26–1.15) Europe | 70/415 | 54/209 | 0.64 (0.45–0.92) Latin America | 15/45 | 9/22 | 0.85 (0.37–1.95) United States | 12/84 | 10/35 | 0.50 (0.22–1.16) Rest of world | 23/124 | 26/75 | 0.50 (0.29–0.89) ECOG PS 0 | 120/697 | 97/350 | 0.61 (0.47–0.80) ECOG PS 1 | 16/60 | 14/30 | 0.48 (0.24–0.99) Risk-based disease stage IIB/IIC/IIIA/IIIB | 59/440 | 50/230 | 0.60 (0.41–0.88) Risk-based disease stage IIIC/IIID/IV | 77/316 | 61/150 | 0.57 (0.41–0.79) Axis: 0.2 | 0.5 | 1.0 | 0.5 ; Intismeran + Pembro Better / Placebo + Pembro Better Distant Metastasis-Free Survival Subgroup | Intismeran + Pembro Events/Patients | Placebo + Pembro Events/Patients | Hazard Ratio (95% CI) All patients | 89/757 | 71/380 | 0.62 (0.45–0.85) Age <65 yr | 47/458 | 37/230 | 0.65 (0.42–0.99) Age ≥65 yr | 42/299 | 34/150 | 0.61 (0.39–0.95) Sex Female | 31/301 | 27/153 | 0.58 (0.34–0.97) Sex Male | 58/456 | 44/227 | 0.66 (0.44–0.97) Australia | 12/89 | 11/39 | 0.42 (0.19–0.96) Europe | 42/415 | 34/209 | 0.63 (0.40–0.99) Latin America | 11/45 | 9/22 | 0.62 (0.26–1.49) United States | 8/84 | 2/35 | 1.77 (0.38–8.35) Rest of world | 16/124 | 15/75 | 0.63 (0.31–1.28) ECOG PS 0 | 77/697 | 60/350 | 0.65 (0.46–0.91) ECOG PS 1 | 12/60 | 11/30 | 0.47 (0.21–1.06) Risk-based disease stage IIB/IIC/IIIA/IIIB | 41/440 | 33/230 | 0.65 (0.41–1.02) Risk-based disease stage IIIC/IIID/IV | 48/316 | 38/150 | 0.59 (0.39–0.91) Axis: 0.2 | 0.5 | 1.0 | 2.0 | 3.0 | 9.0 ; Intismeran + Pembro Better / Placebo + Pembro Better ITT: all randomized patients according to the arm to which they were assigned. Data cutoff date: June 30, 2026 (median study follow-up, 24.6 mo). Presented by: Georgina V. Long, Melanoma Institute Australia
Alan Tan
Alan Tan @alantanmd · #ESMO26 · Oct 24, 2026
INTerpath-001 · ESMO 2026 · Oct 24, 2026
RFS sensitivity analysis (mITT)
View post on X ↗
Recurrence-free survival — sensitivity analysis, mITT population
RFS, mITT (DCO 30-Jun-2026, median f/u 24.6 mo)NEvents, n (%)Median (95% CI)24-month RFS (95% CI)
Intismeran + pembrolizumab726116 (16.0%)Not printed84.2% (81.3–86.7)
Placebo + pembrolizumab365106 (29.0%)Not printed70.4% (65.3–74.9)
HR 0.51 (95% CI 0.39–0.67); no p-value printed (sensitivity analysis).
[Slide 1] RFS Sensitivity Analysis: mITT HR 0.51 (95% CI 0.39–0.67) 84.2% (95% CI 81.3–86.7) 70.4% (95% CI 65.3–74.9) | N | Events,a n (%) Intismeran + pembrolizumab | 726 | 116a (16.0%) Placebo + pembrolizumab | 365 | 106b (29.0%) [a3]1 patients in the intismeran + pembrolizumab arm were excluded from the mITT population due to AEs (n=13), recurrence (n=10), or other reason (n=8). RFS events occurred in 20 (64.5%) of the 31 patients who did not [re]ceive intismeran as planned. b15 patients in the placebo + pembrolizumab arm were excluded from the mITT population due to AEs (n=5), recurrence (n=4), or other reason (n=6). RFS events occurred in and 5 (33.3%) of [the 15] patients who did not receive placebo as planned. mITT: all randomized patients who received intismeran or placebo as assigned. RFS: time from randomization to the first occurrence of any recurrence or death from any [ca]use. Data cutoff date: June 30, 2026 (median study follow-up, 24.6 mo). [Pre]sented by: Georgina V. Long, Melanoma Institute Australia (Survival-curve slide: number-at-risk rows and axis ticks omitted; printed values are in the table above.)
Petros Grivas
Petros Grivas @PGrivasMDPhD · #ESMO26 · Oct 24, 2026
INTerpath-001 · ESMO 2026 · Oct 24, 2026
RFS piecewise hazard ratios · Summary and conclusions
View post on X ↗
RFS sensitivity analysis: piecewise hazard ratios, ITT population
RFS piecewise, ITT (DCO 30-Jun-2026, median f/u 24.6 mo)NEvents 0–6 mo (rate)Events >6 mo (rate)
Intismeran + pembrolizumab75768 (0.016)68 (0.006)
Placebo + pembrolizumab38035 (0.016)76 (0.015)
0–6 months: HR 0.99 (95% CI 0.66–1.49); >6 months: HR 0.42 (95% CI 0.30–0.58). No p-values or medians printed (sensitivity analysis). Rate = no. of events divided by person-time in each interval.
[Slide 1] RFS Sensitivity Analysis: Piecewise Hazard Ratios, ITT 0-6 months: HR 0.99 (95% CI 0.66–1.49) >6 months: HR 0.42 (95% CI 0.30–0.58) | 0-6 months | >6 months | Events (ratea) Intismeran + pembrolizumab | 68 (0.016) | 68 (0.006) Placebo + pembrolizumab | 35 (0.016) | 76 (0.015) aRate calculated as no. of events divided by person-time in each interval. ITT: all randomized patients according to the arm to which they were assigned. RFS: time from randomization to the first occurrence of any recurrence or death from any cause. Data cutoff date: June 30, 2026 (median study follow-up, 24.6 mo). Presented by: Georgina V. Long, Melanoma Institute Australia (Survival-curve slide: number-at-risk rows and axis ticks omitted; printed values are in the table above.) --- [Slide 2] Summary and Conclusions • INTerpath-001 met both the primary RFS and key secondary DMFS endpoints – Intismeran + pembrolizumab reduced the risk of recurrence or death by 42% and the risk of distant metastasis or death by 38% compared with placebo + pembrolizumab – In a sensitivity analysis, intismeran + pembrolizumab reduced the risk of recurrence or death by 58% after month 6 – Benefit was observed in most prespecified subgroups, including risk-based disease stages – OS was immature and did not meet prespecified significance boundarya; follow-up is ongoing • Safety was generally consistent with previous experience, with no potentiation of pembrolizumab-associated AEs with the combination • Intismeran was reliably delivered at a global scale • Ongoing phase 2 and 3 trials are evaluating intismeran for bladder cancer, melanoma, NSCLC, and RCC in the neoadjuvant, adjuvant, or metastatic settings • INTerpath-001 sets a new benchmark for adjuvant therapy in melanoma and establishes intismeran as a landmark advance in personalized cancer medicine aThe hazard ratio for OS was 0.77 (95% CI, 0.45–1.31); two-sided P = 0.33. Presented by: Georgina V. Long, Melanoma Institute Australia
Yakup Ergün
Yakup Ergün @dr_yakupergun · #ESMO26 · Oct 24, 2026
INTerpath-001 · ESMO 2026 · Oct 24, 2026
Adverse event summary
View post on X ↗
[Slide 1] Adverse Event Summary | All-Cause AEs: Intismeran + Pembrolizumab (N = 755) | All-Cause AEs: Placebo + Pembrolizumab (N = 380) | Treatment-Related AEs: Intismeran + Pembrolizumab (N = 755) | Treatment-Related AEs: Placebo + Pembrolizumab (N = 380) Any grade | 742 (98.3) | 366 (96.3) | 723 (95.8) | 342 (90.0) Grade 3-5 | 178 (23.6) | 77 (20.3) | 107 (14.2) | 51 (13.4) Serious | 133 (17.6) | 60 (15.8) | 74 (9.8) | 42 (11.1) Led to discontinuation of any drug | 125 (16.6) | 36 (9.5) | 106 (14.0) | 33 (8.7) Discontinuation of pembrolizumab | 115 (15.2) | 36 (9.5) | 97 (12.8) | 33 (8.7) Discontinuation of intismeran or placebo | 66 (8.7) | 21 (5.5) | 54 (7.2) | 19 (5.0) Discontinuation of both drugs simultaneously | 49 (6.5) | 20 (5.3) | 39 (5.2) | 18 (4.7) Led to death (none related to intismeran) | 8 (1.1) | 0 | 2 (0.3) | 0 aOf the 5 events, 2 were attributed to pembrolizumab (muscular weakness, myocarditis, and myositis in 1 patient and myasthenia gravis in 1 patient); the remaining deaths were due to cardiac failure (n=1), road traffic accident (n=1), and sudden death (n=1). bOf the 3 events, none were attributed to study treatment (acute myocardial infarction (n=1), aspiration pneumonia (n=1), and sudden cardiac death (n=1). As-treated population: all randomized patients who received at ≥1 dose of study treatment. Data cutoff date: June 30, 2026 (median study follow-up, 24.6 mo). Presented by: Georgina V. Long, Melanoma Institute Australia
Alfredo Addeo MD
Alfredo Addeo MD @Alfdoc2 · #ESMO26 · Oct 24, 2026
INTerpath-001 · ESMO 2026 · Oct 24, 2026
Invited discussant (Inge Marie Svane): take-home messages
View post on X ↗
[Slide 1] Take-home messages The INTerpath-001 results are compelling and mark a crucial moment for personalized cancer vaccines OPEN QUESTIONS • Will improved RFS translate into improved OS with longer FU and when will data be available ? • To which extend is the clinical efficacy of Intismeran driven by neoantigen-dependent immune effects ? • How should adjuvant pembro/intismeran be positioned compared to neoadjuvant ipi/nivo for macroscopic St III/IV ? – For patients without major pathological response ? • Further insight into predictive biomarkers and MOA are urgently needed HURDLES • Intismeran production process is complex and time-consuming which translate into an expensive drug • Intismeran is not available for a significant number of patients with tissue samples unsuitable for sequencing • Health technology assessments have yet to evaluate Intismeran real-world cost-effectiveness and feasibility Inge Marie Svane
KOL-Made Infographics#ESMO26
Summary graphics designed by physicians on October 24, 2026, not conference slides. Click to enlarge.

ESMO 2026 slides

The LBA1 recurrence-free survival curve and the abstract, released early after the embargo break, as shared by physicians. Slides from the full LBA1 presentation (Georgina V. Long, Presidential Symposium, Oct 24) are shown above. Click any image to enlarge.

ツチノコ在宅ケモ屋
ツチノコ在宅ケモ屋 @tsurutacl · #ESMO26 · Oct 22, 2026
LBA1: recurrence-free survival, ITT population (Georgina V. Long)
View post on X ↗
Recurrence-free survival, ITT population
RFS, ITT (DCO 30-Jun-2026, median f/u 24.6 mo)NEvents, n (%)24-month RFS (95% CI)
Intismeran + pembrolizumab757136 (18.0%)82.2% (79.3–84.8)
Placebo + pembrolizumab380111 (29.2%)70.0% (65.0–74.5)
HR 0.58 (95% CI 0.45–0.75); P<0.001, two-sided (multiplicity-adjusted significance level, two-sided 0.024692). Median RFS not printed on the slide. No. at risk at 0/6/12/18/24/30/35 months: 757/683/646/618/136/10/0 vs 380/341/302/282/72/3/0.
[Image 1] Survival-curve slide: the printed values are in the numbers table above.
Mario Balsa
Mario Balsa @MarioBalsaMD · #ESMO26 · Oct 23, 2026
LBA1 abstract (released early): results and table
View post on X ↗
[Image 1] Results 1137 pts were randomized: 757 to intismeran + pembro, 380 to placebo + pembro; 726 (95.9%) received ≥1 dose of intismeran and 365 (96.1%) received ≥1 dose of placebo as planned. Median follow-up as of 30Jun2026 was 24.6 mo. Intismeran + pembro significantly improved RFS and DMFS compared with placebo + pembro (Table). Benefit was similar in stage IIB–IIIB and IIIC–IV MEL and other subgroups. For intismeran + pembro vs placebo + pembro, AEs were grade ≥3 in 23.6% vs 20.3%; 6.5% vs 5.3% discontinued both drugs simultaneously due to an AE. Most common AEs were pyrexia (52.2% vs 8.2%), injection site pain (51.0% vs 9.5%), and fatigue (38.5% vs 29.7%). Table: LBA1 | Intismeran + pembro (N = 757) | Placebo + pembro (N = 380) Recurrence-free survival (RFS) 24-mo rate, % (95% CI) | 82.2 (79.3–84.8) | 70.0 (65.0–74.5) HR (95% CI) | 0.58 (0.45–0.75) | — Two-sided P | <0.001 | — Distant metastasis-free survival (DMFS) 24-mo rate, % (95% CI) | 88.5 (86.0–90.6) | 80.2 (75.6–84.0) HR (95% CI) | 0.62 (0.45–0.85) | — Two-sided P | 0.002 | —
KOL-made infographics#ESMO26
Summary graphics designed by physicians, not conference slides. Click to enlarge.
Enlarged slide image

More ESMO 2026 slides from physicians

More slides from ESMO 2026 (Madrid) as photographed and shared on X by physicians, newest first. Each post is shown verbatim; click any slide to enlarge, and open the OCR text under each post. All ESMO 2026 INTerpath-001 slides in the KOL Pulse slide library →

Elvina Almuradova (@Dr_ElvinaA)
Elvina Almuradova @Dr_ElvinaA
INTerpath-001 · ESMO 2026 slides
Oct 24, 2026 · ESMO 2026
View on X ↗
INTerpath-001: In macroscopic stage III melanoma, added value beyond neoadjuvant IO remains unclear. Next: target patients without MPR—but can vaccines overcome IO resistance? Value in stage IIB/IIC remains distinct. #ESMO26 @Larvol @OncoAlert @myESMO https://t.co/E4nKMmpxfy
Katy Beckermann (@katy_beckermann)
Katy Beckermann @katy_beckermann
INTerpath-001 · ESMO 2026 slides
Oct 24, 2026 · ESMO 2026
View on X ↗
Intismeran, an individualized mRNA neoantigen vaccine, plus pembrolizumab beat pembrolizumab alone in resected stage IIB-IV melanoma. Same adjuvant pembro backbone we use in RCC. 📈 RFS HR 0.58, 24-mo RFS 82.2% vs 70.0%, n=1,137 ⚠️ OS HR 0.77, p=0.33. Grade 3-5 AEs 23.6% vs 20.3% 📝 Discussant's hurdles: 17% screen-failed on tissue, 6 to 8 weeks to manufacture, no biomarker to pick patients Look forward to seeing the many trials assessing across other tumor types in future. #Melanoma #Immunotherapy #ClinicalTrials #ESMO26
[Slide 1] [Vision transcription of the slide image; Kaplan-Meier curve captured as a table, raw curve values not transcribed] RFS Primary Analysis: ITT [Survival data captured as a table] Arm | N | Events, n (%) | 24-month RFS (95% CI) Intismeran + pembrolizumab | 757 | 136 (18.0%) | 82.2% (79.3-84.8) Placebo + pembrolizumab | 380 | 111 (29.2%) | 70.0% (65.0-74.5) HR 0.58 (95% CI 0.45-0.75); P < 0.001 (two sided)a No. at risk (months 0 / 6 / 12 / 18 / 24 / 30 / 35): intismeran + pembrolizumab 757 / 683 / 646 / 618 / 136 / 10 / 0; placebo + pembrolizumab 380 / 341 / 302 / 282 / 72 / 3 / 0 aMultiplicity-adjusted significance level: two-sided 0.024692. ITT: all randomized patients according to the arm to which they were assigned. RFS: time from randomization to the first occurrence of any recurrence or death from any cause. Data cutoff date: June 30, 2026 (median study follow-up, 24.6 mo). Presented by: Georgina V. Long, Melanoma Institute Australia
Prof. Dr. Ahmet Dirican (@dr_dirican)
INTerpath-001 · ESMO 2026 slides
Oct 24, 2026 · ESMO 2026
View on X ↗
ESMO 2026 | Personalized mRNA Cancer Vaccines Deliver Phase III Success! INTerpath-001: Intismeran + pembrolizumab in resected high-risk melanoma. • RFS: HR 0.58 (42% risk reduction) • 24-month RFS: 82.2% vs 70.0% (+12.2%) • DMFS: HR 0.62 (38% risk reduction) 3 Key Takeaways: 1. Personalized neoantigen vaccines have demonstrated clinically meaningful Phase III efficacy. 2. No major increase in severe treatment-related toxicity, but overall survival data remain immature. 3. Predictive biomarkers, ctDNA/MRD, and optimal sequencing versus neoadjuvant immunotherapy are the next critical questions. A major milestone for personalized oncology. #ESMO26 @myesmo @oncodaily @OncoAlert #CancerVaccines #Melanoma
[Slide 1] [Left slide] Summary and Conclusions • INTerpath-001 met both the primary RFS and key secondary DMFS endpoints – Intismeran + pembrolizumab reduced the risk of recurrence or death by 42% and the risk of distant metastasis or death by 38% compared with placebo + pembrolizumab – In a sensitivity analysis, intismeran + pembrolizumab reduced the risk of recurrence or death by 58% after month 6 – Benefit was observed in most prespecified subgroups, including risk-based disease stages – OS was immature and did not meet prespecified significance boundarya; follow-up is ongoing • Safety was generally consistent with previous experience, with no potentiation of pembrolizumab-associated AEs with the combination • Intismeran was reliably delivered at a global scale • Ongoing phase 2 and 3 trials are evaluating intismeran for bladder cancer, melanoma, NSCLC, and RCC in the neoadjuvant, adjuvant, or metastatic settings • INTerpath-001 sets a new benchmark for adjuvant therapy in melanoma and establishes intismeran as a landmark advance in personalized cancer medicine aThe hazard ratio for OS was 0.77 (95% CI, 0.45–1.31); two-sided P = 0.33. Presented by: Georgina V. Long, Melanoma Institute Australia [Right slide] Take-home messages The INTerpath-001 results are compelling and mark a crucial moment for personalized cancer vaccines OPEN QUESTIONS • Will improved RFS translate into improved OS with longer follow-up and when will data be available ? • To which extent is the clinical efficacy of intismeran driven by neoantigen-dependent immune effects ? • How should adjuvant pembrolizumab/intismeran be positioned compared to neoadjuvant ipi/nivo for macroscopic stage III/IV ? – For patients without major pathological response ? • Further insight into predictive biomarkers and mechanisms of action are urgently needed. HURDLES • Intismeran production process is complex and time-consuming which translate into an expensive drug • Intismeran is not available for a significant number of patients with tissue samples unsuitable for sequencing • Health technology assessments have yet to evaluate Intismeran real-world cost-effectiveness and feasibility PERSPECTIVES • Potential for broader use across other cancer types and disease stages • Potential for new treatment combinations Inge Marie Svane
Mario Balsa (@MarioBalsaMD)
Mario Balsa @MarioBalsaMD
INTerpath-001 · ESMO 2026 slides
Oct 24, 2026 · ESMO 2026
View on X ↗
👑 Presidential #ESMO26! INTerpath-001: personalized mRNA vaccination reaches phase III in melanoma. Resected stage IIB–IV melanoma, N=1,137: intismeran + pembrolizumab vs pembrolizumab. 💥 At 24 months: • RFS: 82.2% vs 70.0% → HR 0.58 • DMFS: 88.5% vs 80.2% → HR 0.62 • Absolute gains: +12.2% RFS / +8.3% DMFS • Benefit emerges mainly after 6 months • Grade ≥3 AEs: 23.6% vs 20.3% • OS still immature A clinically meaningful new mechanism, but the real question now is positioning 🤔 For macroscopic stage III: adjuvant personalized vaccine after surgery, or neoadjuvant ipi/nivo before it? Biomarkers may ultimately decide. Congrats to @ProfGLongMIA and all the team! 👏🏼 @OncoAlert @OncoReporte @myESMO @_SEOM @GrupoMelanoma
[Slide 2] DMFS Primary Analysis: ITT 88.5% (95% CI 86.0–90.6) 80.2% (95% CI 75.6–84.0) HR 0.62 (95% CI 0.45–0.85) P = 0.002 (two sided)a | N | Events, n (%) Intismeran + pembrolizumab | 757 | 89 (11.8%) Placebo + pembrolizumab | 380 | 71 (18.7%) Months No. at risk 757 | 708 | 682 | 658 | 149 | 11 | 0 380 | 357 | 342 | 323 | 83 | 3 | 0 aMultiplicity-adjusted significance level: two-sided 0.01608. ITT: all randomized patients according to the arm to which they were assigned. DMFS: time from randomization to first occurrence of distant metastasis or death from any cause. Data cutoff date: June 30, 2026 (median study follow-up, 24.6 mo). Presented by: Georgina V. Long, Melanoma Institute Australia Survival table Endpoint: DMFS (ITT, primary analysis) Intismeran + pembrolizumab | 757 Placebo + pembrolizumab | 380 HR: 0.62 HR CI: 0.45–0.85 P: 0.002 (two sided) Landmark rates: 24 months: Intismeran + pembrolizumab 88.5% (CI 86.0–90.6) | Placebo + pembrolizumab 80.2% (CI 75.6–84.0)
Shilpa Gupta (@shilpaonc)
Shilpa Gupta @shilpaonc
INTerpath-001 · ESMO 2026 slides
Oct 24, 2026 · ESMO 2026
View on X ↗
#ESMO26 @myESMO Presidential session presentation by session @ProfGLongMIA INTerpath-001: intismeran + pembro vs pembro in resected stage IIB–IV melanoma (n=1,137) RFS HR 0.58, 2-yr RFS 82% vs 70%
DMFS HR 0.62, 2-yr DMFS 89% vs 80% 1st phase 3 win for an individualized cancer vaccine against an active IO control. OS is pending, but the adjuvant melanoma bar just moved! Moving moment as @ProfGLongMIA paid tribute to Dr. Jeff Weber, who designed this trial and enrolled patients until his passing. Jeff was a dear friend and my colleague at @MoffittNews and today's results are his legacy 💙 Bladder next: INTerpath-005 in MIUC, look forward to seeing the data in future!
Alfredo Addeo MD (@Alfdoc2)
Alfredo Addeo MD @Alfdoc2
INTerpath-001 · ESMO 2026 slides
Oct 24, 2026 · ESMO 2026
View on X ↗
Balanced discussion by prof Svane of the phase III INTerpath-001 trial at #ESMO26. Personalized cancer vaccines represent a major step forward, but: 🔹 Will the RFS benefit translate into improved OS? 🔹 Where should adjuvant vaccination fit alongside neoadjuvant ipilimumab/nivolumab? 🔹 Who benefits most? Predictive biomarkers remain urgently needed. 🔹 Manufacturing complexity, treatment delays, costs and access are major challenges. 👏 Compelling data and a milestone for personalized oncology, but clinical positioning and real-world feasibility will be crucial! #ESMOAmbassador #ESMO26 #Melanoma #CancerVaccin
[Slide 2] Neoadjuvant therapy for macroscopic resectable disease EFS, RFS according to pathological response, and Real-world OS NADINA - EFS neo-adjuvant ipi/nivo versus adj nivo macroscopic stage III [KM curve] Neoadjuvant 83.7 | Adjuvant 57.2 (labels at 12 months) Events/N: Neoadjuvant: 28/212; Adjuvant: 72/211 HR= 0.32 ( 99.9% CI: 0.15 - 0.66 ), p <0.0001 Months since Randomization NADINA - RFS neo-adjuvant ipi/nivo versus adj nivo macroscopic stage III [KM curve] Major pathological response 95.1 | Partial pathological response 76.1 | Pathological nonresponse 57.0 (labels at 12 months) Months since Randomization ESMO Guidelines: Neoadjuvant ipi/nivo is recommended for macroscopic resectable st III and IV melanoma Neoajduvant ipi/nivo is associated with 30% severe toxicity as compared to 15% for adjuvant anti-PD1 NADINA have not yet presented mature OS data Inge Marie Svane Blank et al NEJM 2024, Long et al Nature Med 2026 Survival table Endpoint: EFS (NADINA, neoadjuvant ipi/nivo vs adjuvant nivo, macroscopic stage III) Neoadjuvant ipi/nivo | 212 Adjuvant nivo | 211 HR: 0.32 HR CI: 99.9% CI 0.15-0.66 P: <0.0001 Landmark rates: 12 months: Neoadjuvant ipi/nivo 83.7 | Adjuvant nivo 57.2 | RFS - major pathological response 95.1 | RFS - partial pathological response 76.1 | RFS - pathological nonresponse 57.0
Balazs Halmos (@BalazsHalmosMD)
Balazs Halmos @BalazsHalmosMD
INTerpath-001 · ESMO 2026 slides
Oct 24, 2026 · ESMO 2026
View on X ↗
I admit i am very much into intismeran…and it seems many others too as it is standing room only here… Fabulous presentation/data on the Interpath-001 trial demonstrating clear benefit of this space age bespoke neoantigen vaccine along w pembro for pts w resected high risk melanoma as to 40% or so improvement in RFS/distant met free survival Indeed a landmark trial for precision medicine and hopefully not too Long before we see confirmation in nsclc/other trials! Interpath- indeed makes us foresee a wonderful path and light ahead for our field! #ESMO26
Daniel Heng (@DrDanielHeng)
Daniel Heng @DrDanielHeng
INTerpath-001 · ESMO 2026 slides
Oct 24, 2026 · ESMO 2026
View on X ↗
#INTerpath001 amazing adjuvant melanoma trial of a personalized vaccine plus pembrolizumab. 17% of patients didn’t have sufficient tumor sample to create the neoantigen vaccine. DFS highly positive and OS immature. @oncoalert #ESMO26 excited to see other tumor data coming soon! https://t.co/VyUKabIWE2
Renee Maria Saliby (@ReneeSaliby)
Renee Maria Saliby @ReneeSaliby
INTerpath-001 · ESMO 2026 slides
Oct 24, 2026 · ESMO 2026
View on X ↗
INTerpath-001 - the result of decades of scientific advances and research led to this moment! Personalized mRNA vaccines + Pembro as adjuvant trt improve RFS for pts with resects IIB-IV Melanoma!! Important points: Tox: a significant number of adverse events occurred BEFORE the vaccine was started Access: the vaccines was given globally #ESMO26 @OncoAlert
[Slide 1] Science enables individualized therapeutic cancer vaccines Neoantigen discovery • Tumor-specific mutations • Potential for enhanced immunogenicity Cancer Cell — Patient A | Patient B | Patient C Neoantigen selection • NGS identifies tumor mutations • Computational prediction of HLA presentation and ranking The mRNA platform • Multiple antigens per mRNA • Robust CD8+ and CD4+ T cell responses • Rapid, individualized manufacturing Lipid nanoparticle (LNP) | mRNA HLA, human leukocyte antigen; mRNA, messenger RNA; NGS, next-generation sequencing. Ascierto PA, Melero I. J Immunother Cancer 2025;13:e013766. Zaidi N et al. Nat Rev Cancer 2025;25:517–33. Haanen JB et al. Nat Med 2026;32:828-40. Weber JS et al. Lancet 2024;403:632–44. Ojalvo LS et al. JCO Oncol Adv 2026;3:e2500206. Presented by: Georgina V. Long, Melanoma Institute Australia
Yago Garitaonaindía (@YGaritaonaindia)
Yago Garitaonaindía @YGaritaonaindia
INTerpath-001 · ESMO 2026 slides
Oct 24, 2026 · ESMO 2026
View on X ↗
🔥 #ESMO26 INTerpath-001, full data (now yes) On top of RFS HR 0.58 and DMFS HR 0.62: • Manufacturing success >99% • >90% of patients got the maximum 34 neoantigens 🔍 Practice-changing? For a population, yes. Two things still to prove: • Can an mRNA strategy rescue patients primary refractory to neoadjuvant ipi-nivo (no pathologic response)? • Will it move OS in stage II-IIIB too? Resuls in @NEJM soon @myESMO @OncoAlert @Larvol @_SEOM #Melanoma #Immunotherapy
[Slide 1] Intismeran mechanism of action • Intismeran is designed to strengthen existing and create new T cell responses1-3 • Pembrolizumab blocks PD-1 to enhance T-cell activity, complementing intismeran's MOA 1 Administer INT 2 mRNA uptake into cells 3 mRNA translated into protein and processed 4 Neoantigen presentation 5 T cell activation and clonal expansion 6 Migration to tumor microenvironment 7 Tumor cell killing 8 Epitopes releaseda Diagram labels: APC (eg, dendritic cell); [illegible small diagram labels]; T cells; Dying tumor cell; Cytokine release [footnotes and references illegible] Presented by: Georgina V. Long, Melanoma Institute Australia [blurred]
deniztural (@drdeniztural)
deniztural @drdeniztural
INTerpath-001 · ESMO 2026 slides
Oct 24, 2026 · ESMO 2026
View on X ↗
The First Positive Phase III Trial of a Personalized mRNA Cancer Therapy Adding individualized mRNA therapy to adjuvant pembrolizumab reduced the risk of recurrence or death by 42% in patients with resected stage IIB–IV melanoma. #ESMO2026 https://t.co/aSdzLwcxiG
RFS Sensitivity Analysis: Piecewise Hazard Ratios, ITT 0-6 months: HR 0.99 (95% CI 0.66–1.49) >6 months: HR 0.42 (95% CI 0.30–0.58) | 0-6 months Events (ratea) | >6 months Events (ratea) Intismeran + pembrolizumab | 68 (0.016) | 68 (0.006) Placebo + pembrolizumab | 35 (0.016) | 76 (0.015) Months: 0 | 6 | 12 | 18 | 24 | 30 | 35 No. at risk 757 | 683 | 646 | 618 | 136 | 10 | 0 380 | 341 | 302 | 282 | 72 | 3 | 0 aRate calculated as no. of events divided by person-time in each interval. ITT: all randomized patients according to the arm to which they were assigned. RFS: time from randomization to the first occurrence of any recurrence or death from any cause. Data cutoff date: June 30, 2026 (median study follow-up, 24.6 mo). Presented by: Georgina V. Long, Melanoma Institute Australia Survival table Endpoint: RFS sensitivity analysis — piecewise hazard ratios (ITT) Intismeran + pembrolizumab | 757 Placebo + pembrolizumab | 380 HR: 0-6 months: 0.99; >6 months: 0.42 HR CI: 0-6 months: 0.66–1.49; >6 months: 0.30–0.58
Alfredo Addeo MD (@Alfdoc2)
Alfredo Addeo MD @Alfdoc2
INTerpath-001 · ESMO 2026 slides
Oct 24, 2026 · ESMO 2026
View on X ↗
🔥 Personalized cancer vaccines delivering impressive results at #ESMO26! @ProfGLongMIA presents the phase III INTerpath-001 trial in resected high-risk melanoma. Individualized neoantigen mRNA vaccine intismeran autogene + pembrolizumab vs pembrolizumab alone. Key results: 🔹 DMFS: HR 0.62 (95% CI 0.45–0.85), p=0.002 🔹 24-month DMFS: 88.5% vs 80.2% 🔹 RFS: HR 0.58 (95% CI 0.45–0.75) A major milestone for personalized cancer vaccines! A promising step towards truly individualized immunotherapy. #ESMOAmbassador #ESMO26 #Melanoma #CancerVaccines #Immunotherapy
[Slide 1] Science enables individualized therapeutic cancer vaccines Neoantigen discovery • Tumor-specific mutations • Potential for enhanced immunogenicity Cancer Cell: Patient A | Patient B | Patient C Neoantigen selection • NGS identifies tumor mutations • Computational prediction of HLA presentation and ranking The mRNA platform • Multiple antigens per mRNA • Robust CD8+ and CD4+ T cell responses • Rapid, individualized manufacturing Lipid nanoparticle (LNP) | mRNA HLA, human leukocyte antigen; mRNA, messenger RNA; NGS, next-generation sequencing. Ascierto PA, Melero I. J Immunother Cancer 2025;13:e013766. Zaidi N et al. Nat Rev Cancer 2025;25:517–33. Haanen JB et al. Nat Med 2026;32:828-40. Weber JS et al. Lancet 2024;403:632–44. Ojalvo LS et al. JCO Oncol Adv 2026;3:e2500206. Presented by: Georgina V. Long, Melanoma Institute Australia [Slide 2] Standardized intismeran workflow 1 Tissue and blood samples 2 Neoantigen identification 3 mRNA design 4 Manufacture 5 Administer ~6-8 weeks Presented by: Georgina V. Long, Melanoma Institute Australia [Slide 3] INTerpath-001: Randomized, Double-Blind, Phase 3 Trial Key Eligibility Criteria • Age ≥18 years • Resected cutaneous melanoma • AJCC 8th ed. Stage IIB/IIC (clinical IIB/IIC permitted), III, or IV • FFPE tumor sample suitable for NGS and intismeran generation • No prior systemic therapy • ECOG PS 0 or 1 R 2:1 Intismeran 1 mg IM Q3W for 9 doses + Pembrolizumab 400 mg IV Q6W for 9 cycles Placeboa IM Q3W for 9 doses + Pembrolizumab 400 mg IV Q6W for 9 cycles Stratification factors • Risk-based stage (IIB/IIC/IIIA/IIIB vs IIIC/IIID/IV) • Age (<65 years vs ≥65 years) aNormal saline or dextrose. Placebo was started at random to maintain the blind. ClinicalTrials.gov identifier: NCT05933577. Presented by: Georgina V. Long, Melanoma Institute Australia
Toni Choueiri, MD (@DrChoueiri)
Toni Choueiri, MD @DrChoueiri
INTerpath-001 · ESMO 2026 slides
Oct 24, 2026 · ESMO 2026
View on X ↗
Superb presentation by Georgina Long! INTerpath-001: adding personalized mRNA vaccine intismeran to pembrolizumab reduced recurrence/death risk by 42% in resected stage IIB-IV melanoma (HR 0.58). A major step for cancer vaccines! #ESMO26 @OncoAlert @myESMO #ESMO26 https://t.co/9miRzK7fhb
INTerpath-001: Phase 3 Study of the mRNA-Based Individualized Neoantigen Therapy (INT) Intismeran Autogene plus Pembrolizumab vs Pembrolizumab Alone for Adjuvant Treatment of Resected Stage IIB-IV Melanoma Georgina V. Long; Muhammad A. Khattak; Helen J. Gogas; Dirk Schadendorf; Ana Arance; Matteo S. Carlino; Piotr Rutkowski; Gareth Rivalland; Antoni Ribas; Janice M. Mehnert; Patrick A. Ott; Reinhard Dummer; Paola Queirolo; Christoffer Gebhardt; Laureen S. Ojalvo; Jinchun Zhang; Dmitri O. Grebennik; Mizuho Fukunaga-Kalabis; Paolo A. Ascierto; Michele Del Vecchio on behalf of the INTerpath-001 Investigators MADRID 2026 ESMO congress
Elad Sharon (@EladSharonMD)
Elad Sharon @EladSharonMD
INTerpath-001 · ESMO 2026 slides
Oct 24, 2026 · ESMO 2026
View on X ↗
Watching the intismeran presentation by @ProfGLongMIA here @myESMO here in Madrid #ESMO26 https://t.co/MDuBbMTtsJ
[Slide 1] Science enables individualized therapeutic cancer vaccines Neoantigen discovery - Tumor-specific mutations - Potential for enhanced immunogenicity Cancer Cell | Patient A | Patient B | Patient C Neoantigen selection - NGS identifies tumor mutations - Computational prediction of HLA presentation and ranking The mRNA platform - Multiple antigens per mRNA - Robust CD8+ and CD4+ T cell responses - Rapid, individualized manufacturing Lipid nanoparticle (LNP) | mRNA Presented by: Georgina V. Long, Melanoma Institute Australia [footnote abbreviations and references illegible]
Yakup Ergün (@dr_yakupergun)
Yakup Ergün @dr_yakupergun
INTerpath-001 · ESMO 2026 slides
Oct 24, 2026 · ESMO 2026
View on X ↗
#ESMO26 | INTerpath-001: My Personal Perspective Ahead of the Presidential Session This innovation deserves recognition: a groundbreaking result for personalized cancer vaccines. However, in patients with macroscopic stage III melanoma who are eligible for neoadjuvant IO, this trial does not establish the added value over contemporary perioperative strategies. Neoadjuvant treatment can produce substantial responses while allowing some patients to avoid adjuvant therapy. The trial design I would prioritize is: Neoadjuvant IO → surgery → standard adjuvant therapy ± a personalized vaccine in patients without a major pathological response. Here, “failure to achieve a major pathological response” is a more appropriate selection criterion than “any residual disease.” Patients with minimal residual viable tumor who still achieve a major pathological response should not automatically receive additional treatment. This approach would direct treatment intensification toward patients at higher risk of recurrence. The key biological uncertainty, however, is that IO-resistant residual disease is not necessarily vaccine-sensitive. Whether vaccination can overcome that resistance needs to be demonstrated. This criticism should remain specific to that population: INTerpath-001 retains distinct clinical value for patients with stage IIB/IIC disease and those who underwent surgery without neoadjuvant therapy.
LBA1 - INTerpath-001: Phase 3 study of the mRNA-based individualized neoantigen therapy (INT) intismeran autogene (intismeran) plus pembrolizumab (pembro) vs pembro alone for adjuvant treatment of resected stage IIB-IV melanoma (MEL) Speakers Georgina V. Long (Sydney, Australia) Lecture Time 16:30 - 16:42 Abstract Background Many patients (pts) with resected high-risk MEL experience recurrence despite adjuvant therapy. Enhancing immune activation may improve efficacy. Intismeran is an mRNA-based INT designed to expand pre-existing and generate de novo neoantigen-specific antitumor T-cell responses by targeting pt-specific tumor-derived antigens. INTerpath-001 (NCT05933577) is a double-blind phase 3 study of intismeran + pembro as adjuvant therapy for resected stage IIB–IV MEL. Methods Eligible adults with surgically resected stage IIB/IIC (pathologic or clinical) or III/IV cutaneous MEL and a tumor sample suitable for next-generation sequencing were randomized 2:1 to pembro 400 mg (9 cycles, IV Q6W) + intismeran 1 mg or placebo (9 doses, IM Q3W). Pembro started at randomization, intismeran or placebo upon availability. Primary endpoint: RFS. Secondary endpoints: DMFS, OS, and safety. Results 1137 pts were randomized: 757 to intismeran + pembro, 380 to placebo + pembro; 726 (95.9%) received ≥1 dose of intismeran and 365 (96.1%) received ≥1 dose of placebo as planned. Median follow-up as of 30Jun2026 was 24.6 mo. Intismeran + pembro significantly improved RFS and DMFS compared with placebo + pembro (Table). Benefit was similar in stage IIB–IIIB and IIIC–IV MEL and other subgroups. For intismeran + pembro vs placebo + pembro, AEs were grade ≥3 in 23.6% vs 20.3%; 6.5% vs 5.3% discontinued both drugs simultaneously due to an AE. Most common AEs were pyrexia (52.2% vs 8.2%), injection site pain (51.0% vs 9.5%), and fatigue (38.5% vs 29.7%). Table: LBA1 | Intismeran + pembro (N = 757) | Placebo + pembro (N = 380) Recurrence-free survival (RFS) 24-mo rate, % (95% CI) | 82.2 (79.3–84.8) | 70.0 (65.0–74.5) HR (95% CI) | 0.58 (0.45–0.75) | — Two-sided P | <0.001 | — Distant metastasis-free survival (DMFS) 24-mo rate, % (95% CI) | 88.5 (86.0–90.6) | 80.2 (75.6–84.0) HR (95% CI) | 0.62 (0.45–0.85) | — Two-sided P | 0.002 | — Conclusions Intismeran + pembro significantly improved RFS and DMFS compared with placebo + pembro and was generally well tolerated when given as adjuvant therapy for stage IIB–IV MEL. These findings set a new benchmark for adjuvant MEL and are a pivotal advance in personalized medicine and cancer treatment.
Evelyn Wong (@EvelynWongYT)
Evelyn Wong @EvelynWongYT
INTerpath-001 · ESMO 2026 slides
Oct 24, 2026 · ESMO 2026
View on X ↗
Enjoyed @MarcoGerlinger's take on INTerpath & the discontinued BNT-122 CRC study at #ESMO26. What can each teach us? A reminder: we’re testing a strategy: that includes tumour biology, combination therapy and patient selection and not just a vaccine. #ESMOAmbassadors https://t.co/NfRxtIrsui
[Slide 1] Trial design and patient selection INTerpath-001: - Melanoma – high mutation load, highly immunogenic - Pembrolizumab – potent backbone, with vaccine directing T cell response - High risk population – resected stage IIB – IV melanoma CRC: BNT-122: - MSS/MMRp CRC – modest mutation load, low immunogenicity & often immune-excluded - Vaccine monotherapy – in a tumour type where immunotherapy has so far not succeeded - Very high risk population: - ctDNA positive - Roche Avenio ctDNA test limit of detection ~0.1% vs. Signatera 0.01%1 - Potential under-detection of low-level MRD 1) Chen et al. Mol Diagn Ther 2021 [Slide 2] Taking the brakes off immune cells and tackling immunosuppression in CRC - MMRp CRC: modest immunogenicity, often immune excluded - In the metastatic setting: negligible response rates and PFS benefit from PD1/PDL1 +/- CTLA4 ICIs1 - Still: omission of trial arm with vaccine + ICI appears like a key mistake now - Several next-generation ICIs look more promising in CRC: - Botensilimab/Balstilimab (PD1 + Fc-enhanced CTLA4): 17% RR in 101 MSS CRC (0% in patients with liver metastases)2 - INCA33890 (PD1/TGFBR bispecific AB): 15.2% RR in 105 MSS CRC (12% in patients with liver metastases)3 - We need combination trials with ICIs that overcome immunosuppression in CRC. 1) Chen et al. Jama Onc 2020 2) Bullock et al. Nat Med 2024 3) Moyers GI ASCO 2026
KOL-Made Infographics
Physician-authored summary graphics from ESMO 2026 · click to enlarge
@ramonphysician · Oct 25, 2026 · ESMO 2026
@Dr_Ivanoncologo · Oct 24, 2026 · ESMO 2026
KOL-Made Infographics
Physician-authored summary graphics from ESMO 2026 · click to enlarge
@drtarsh · Oct 25, 2026 · ESMO 2026

More slides on this page

Earlier slides

Earlier materials: the topline press release as shared by physicians, and Dr. Ahmad Tarhini’s EPCM Hamburg 2026 walkthrough of how an individualized neoantigen therapy is actually made. Full transcriptions via the OCR toggle.

MJosé Juan @mjuanfi81 · 2026-08-19
Merck/Moderna topline press release - full first page
RFS + DMFS met - shared by Dr. M. Jose Juan (verbatim capture, OCR below)
View Post
Ahmad Tarhini @ATarhiniMDPhD · 2026-08-19
Intismeran end-to-end workflow - EPCM Hamburg 2026
Presented by Dr. Ahmad Tarhini - the 8-step individualized manufacturing journey
View Post
Daisuke Kotani, MD, Ph.D 小谷 大輔 @DaisukeKotani · 2026-08-19
KEYNOTE-942: RFS benefit across primary, 3-year and 5-year analyses (ASCO 2026)
Presented by Dr. Matteo S. Carlino - the Phase 2b antecedent, shared by Dr. Daisuke Kotani
View Post
[Slide - ASCO 2026 Annual Meeting, presented by Matteo S. Carlino, MD, PhD] KEYNOTE-942: 'Consistent and durable RFS benefit across primary, 3-year, and 5-year analyses' - intismeran plus pembrolizumab (n=107) vs pembrolizumab (n=50). Primary Analysis (Nov 14, 2022 data cut): events 22.4% (24/107) vs 40.0% (20/50); HR 0.561 (95% CI 0.309-1.017), P=0.0266 (formal hypothesis testing of RFS, overall one-sided alpha=0.10, performed at primary analysis). 3-Year Analysis (Nov 3, 2023): events 23.4% (25/107) vs 44.0% (22/50); HR 0.510 (0.288-0.906). 5-Year Analysis (Dec 15, 2025): events 26.2% (28/107) vs 46.0% (23/50); HR 0.510 (0.294-0.887). Refs: 1. Weber JS et al, Lancet 2024;403(10427):632-644. 2. Carlino MS et al, JCO Oncol Adv 2026;3(1):e2500008.
KOL-Made Infographics
Graphics made and shared by physicians on October 22, 2026. Click to enlarge on X.
INTerpath-001 Phase 3 trial schema infographic: completely resected stage IIB-IV melanoma, N=1,137, randomized 2:1 to intismeran autogene plus pembrolizumab or placebo plus pembrolizumab; primary endpoint RFS; shared by Pablo Jimenez
@PaulJiL · trial schema ↗
Mark Yarchoan chart of hazard ratios for landmark adjuvant trials: INTerpath-001 0.58, PRODIGE 24 0.58, MOSAIC 0.77, KEYNOTE-054 0.57, HERA 0.54
@MarkYarchoan · adjuvant HR chart* ↗

INTerpath-001 Trial Design

Intismeran autogene is an mRNA-based individualized neoantigen therapy: each patient’s resected tumor is sequenced, up to 34 tumor-specific neoantigens are selected, and a single mRNA encoding them is manufactured for that patient, then given with pembrolizumab. INTerpath-001 tested this combination against pembrolizumab alone as adjuvant therapy in completely resected stage IIB–IV cutaneous melanoma.

Sibling INTerpath trials are ongoing in NSCLC, bladder cancer and first-line advanced melanoma. Principal investigator Professor Georgina Long (Melanoma Institute Australia) said the combination “has the potential to establish a new treatment paradigm in the adjuvant melanoma setting.” Results are in At a Glance.

Study Design

Randomized (2:1), double-blind, placebo- and active-comparator-controlled global Phase 3. 1,137 patients enrolled following complete surgical resection.

Population

Completely resected, high-risk stage IIB–IV cutaneous melanoma; no prior systemic therapy.

Interventions

Intismeran autogene 1 mg IM q3w (up to 9 doses) + pembrolizumab 400 mg q6w (up to 9 cycles, ~1 year) vs placebo + pembrolizumab.

Endpoints

Primary: recurrence-free survival (RFS). Key secondary: distant metastasis-free survival (DMFS). Other secondary: OS, safety, quality of life (EORTC QLQ-C30).

Manufacturing

Each dose is patient-individualized: tumor + blood sequencing → neoantigen selection → single-mRNA manufacture → IM administration (see Dr. Tarhini’s workflow slide above).

Sponsors

Merck Sharp & Dohme (sponsor) with ModernaTX (collaborator); intismeran jointly developed by Merck and Moderna.

Design sources: Merck topline PR · ClinicalTrials.gov

INTerpath-001 in the News

Earlier: October 22, 2026 LBA1 abstract release and press-release analyses

October 22, 2026: INTerpath-001 LBA1 abstract released

ESMO released the LBA1 abstract on October 22, 2026 after its figures appeared early on a medical news site. ESMO said the embargo “has been breached” and lifted it on the full dataset. ESMO on X, Oct 22, 2026

From the abstract (ESMO 2026 LBA1 abstract, DCO 30-Jun-2026, median f/u 24.6 mo) — intismeran autogene + pembrolizumab (n=757) vs placebo + pembrolizumab (n=380), randomized 2:1, N=1,137:

  • RFS (primary): 24-month RFS 82.2% (95% CI 79.3–84.8) vs 70.0% (65.0–74.5); HR 0.58 (95% CI 0.45–0.75); two-sided P<0.001 (ESMO 2026 LBA1 abstract, DCO 30-Jun-2026, median f/u 24.6 mo)
  • DMFS (secondary): 24-month DMFS 88.5% (95% CI 86.0–90.6) vs 80.2% (75.6–84.0); HR 0.62 (95% CI 0.45–0.85); two-sided P=0.002 (ESMO 2026 LBA1 abstract, DCO 30-Jun-2026, median f/u 24.6 mo)
  • Safety: grade ≥3 AEs 23.6% vs 20.3%; 6.5% vs 5.3% discontinued both drugs simultaneously due to an AE; most common AEs pyrexia (52.2% vs 8.2%), injection-site pain (51.0% vs 9.5%) and fatigue (38.5% vs 29.7%) (ESMO 2026 LBA1 abstract, DCO 30-Jun-2026, median f/u 24.6 mo)
  • Subgroups: per the abstract, benefit was similar in stage IIB–IIIB and IIIC–IV melanoma and other subgroups
  • Overall survival: not reported in the abstract

Merck and Moderna press release, October 22, 2026, 2:59 PM ET, added analyses not in the abstract:

  • First six months: RFS HR 0.99 (95% CI 0.66–1.49); DMFS HR 1.01 (95% CI 0.58–1.79) (Merck/Moderna press release, Oct 22, 2026)
  • After six months (pre-specified sensitivity analysis): RFS HR 0.42 (95% CI 0.30–0.58); DMFS HR 0.50 (95% CI 0.34–0.73) (Merck/Moderna press release, Oct 22, 2026)
  • Patients who received at least one dose as planned (pre-specified sensitivity analysis): RFS HR 0.51 (95% CI 0.39–0.67); DMFS HR 0.55 (95% CI 0.40–0.77) (Merck/Moderna press release, Oct 22, 2026)
  • Overall survival: “data are not yet mature, but a favorable trend in OS with intismeran plus KEYTRUDA has been observed” (Merck/Moderna press release, Oct 22, 2026)
  • Treatment-related AEs: grade 3–5 in 14.2% vs 13.4% (Merck/Moderna press release, Oct 22, 2026). The abstract’s 23.6% vs 20.3% counts grade ≥3 AEs of any cause.
  • Accepted for publication in The New England Journal of Medicine; the companies are “engaging with regulatory authorities” (Merck/Moderna press release, Oct 22, 2026). Press release

The leak, the market reaction and the neoadjuvant debate: KOL Pulse blog

Full data were presented at the ESMO 2026 Presidential Symposium (LBA1, October 24, 2026) by Professor Georgina V. Long (invited discussant: Inge Marie Svane), including overall survival (immature; HR 0.77, 95% CI 0.45–1.31; P=0.33) — see At a Glance below. Intismeran autogene remains investigational. ESMO 2026 LBA1 abstract

INTerpath-001 FAQ

What is the INTerpath-001 trial?

INTerpath-001 (NCT05933577, V940-001) is a randomized (2:1), double-blind global Phase 3 trial of adjuvant intismeran autogene (V940 / mRNA-4157, Merck and Moderna) plus pembrolizumab (Keytruda) versus pembrolizumab alone in 1,137 patients with completely resected, high-risk stage IIB-IV cutaneous melanoma. Dosing and endpoints: Trial Design.

What did INTerpath-001 show?

The trial met its primary endpoint, recurrence-free survival (HR 0.58), and its key secondary endpoint, distant metastasis-free survival, in the full results presented at the ESMO 2026 Presidential Symposium (LBA1, October 24, 2026). Overall survival was immature and did not meet its prespecified significance boundary. Figures, safety and data cut-off: At a Glance.

What is intismeran autogene?

An mRNA-based individualized neoantigen therapy (INT): each patient's resected tumor is sequenced, up to 34 patient-specific neoantigens are encoded on a single mRNA, and the therapy is manufactured individually to train that patient's immune system to recognize and attack their cancer. It was formerly known as mRNA-4157 or V940.

How do these results relate to KEYNOTE-942?

KEYNOTE-942 was the randomized Phase 2b antecedent (n=157, resected stage III/IV melanoma) and showed a consistent RFS benefit at every analysis. Hazard ratios that circulated on announcement day were KEYNOTE-942 Phase 2b figures, not INTerpath-001 results. Both sets of figures are in At a Glance.

Is intismeran autogene approved?

No. Intismeran autogene plus pembrolizumab is investigational and not approved by the FDA or any other regulator. Merck and Moderna stated they will engage with regulators on filing submissions based on INTerpath-001. See At a Glance.

Key KOL Sentiments — INTerpath-001

KOLComment (verbatim)Sentiment
G Curigliano MD PhD Don’t miss the data at #ESMO2026 https://t.co/vFiJ0ruccU [QUOTED] JUST IN and via @Merck + @moderna_tx: A landmark moment for cancer immunotherapy. 🎯 Phase 3 INTerpath-001 is positive: the individualized mRNA neoantigen therapy intismeran (V940/mRNA-4157) + pembrolizumab significantly improved both RFS/DMFS vs pembrolizumab alone after resection of high-risk melanoma. For years, the idea of designing a treatment around the unique mutations of each patient’s tumor seemed aspirational. Now we have the first positive Phase 3 trial (N=1137) of an individualized neoantigen therapy—and of an mRNA-based cancer therapy. Personalized cancer vaccines are moving from promise to reality. Now we need to see the magnitude of benefit, durability, and ultimately OS. But today is an important day for the field—and hopefully for our patients. 👏 Congrats to #CathyWu @DanaFarber for her trailblazing research that is materializing in tangible outcomes! At @DanaFarber_GU we are closely working with Cathy + @DFCI_NeoVax team on several GU protocols, after our @Nature work with @BraunMDPhD et al (https://t.co/BdbKJqMKOw) https://t.co/Akd0XQt3ml Positive
Eric Topol The mRNA vaccine success vs melanoma in a Phase definitive 3 randomized trial today is on top of signs of success for personalized mRNA neoantigen vaccines vs pancreatic cancer, triple negative breast cancer, and non-small cell lung cancer https://t.co/cv4iXW11mw Positive
Paolo Tarantino Positive phase 3 data for adjuvant pembro +/- personalized mRNA-based neoantigen vaccine for melanoma just announced by Merck and Moderna. Welcome to the future! https://t.co/rlKAvv7sbo https://t.co/BxYKh4NKKw Positive
Balazs Halmos Newly minted twins- Intismeran and pembro are feeling pretty good today https://t.co/62jEnUt1mk https://t.co/5F8aw2rFqf [QUOTED] Are you into Intismeran- the new “individualized neoantigen therapy” (graciously avoiding the term “vaccine”) from Merck/Moderna? If you haven’t- you should! Maybe biggest news in onc for some time along w daraxonrasib- positive results in pivotal melanoma trial as to RFS improvement of this Space age technology which still makes my head spin- whole genome seq- neoantigen selection- personalized “INT” delivered to your patient in just a few weeks… and it works! Many studies ongoing in lung/bladder etc- eager to learn results (and continue to offer to our pts at Monte @BrendonStilesMD !) Now Back to the Future and let’s keep enrolling! Positive
Toni Choueiri, MD JUST IN and via @Merck + @moderna_tx: A landmark moment for cancer immunotherapy. 🎯 Phase 3 INTerpath-001 is positive: the individualized mRNA neoantigen therapy intismeran (V940/mRNA-4157) + pembrolizumab significantly improved both RFS/DMFS vs pembrolizumab alone after resection of high-risk melanoma. For years, the idea of designing a treatment around the unique mutations of each patient’s tumor seemed aspirational. Now we have the first positive Phase 3 trial (N=1137) of an individualized neoantigen therapy—and of an mRNA-based cancer therapy. Personalized cancer vaccines are moving from promise to reality. Now we need to see the magnitude of benefit, durability, and ultimately OS. But today is an important day for the field—and hopefully for our patients. 👏 Congrats to #CathyWu @DanaFarber for her trailblazing research that is materializing in tangible outcomes! At @DanaFarber_GU we are closely working with Cathy + @DFCI_NeoVax team on several GU protocols, after our @Nature work with @BraunMDPhD et al (https://t.co/BdbKJqMKOw) https://t.co/Akd0XQt3ml Positive
Balazs Halmos Are you into Intismeran- the new “individualized neoantigen therapy” (graciously avoiding the term “vaccine”) from Merck/Moderna? If you haven’t- you should! Maybe biggest news in onc for some time along w daraxonrasib- positive results in pivotal melanoma trial as to RFS improvement of this Space age technology which still makes my head spin- whole genome seq- neoantigen selection- personalized “INT” delivered to your patient in just a few weeks… and it works! Many studies ongoing in lung/bladder etc- eager to learn results (and continue to offer to our pts at Monte @BrendonStilesMD !) Now Back to the Future and let’s keep enrolling! Positive
Dr. Estela Rodriguez Melanoma research lead the way in the approval of checkpoint inhibitors. Excited to see this @Merck @moderna_tx press release about the positive pivotal Phase 3 INTerpath-001 trial in resected stage IIB–IV melanoma, RFS were significantly improved vs pembrolizumab alone. ~1,100 patients. 👉🏽This is precision immuno-oncology at the individual neoantigen patient level. Now the big question: can we reproduce this across lung, bladder, and other solid tumors? Positive
Ahmad Tarhini Exciting announcement today from Phase3 INTerpath001 of #Intismeran & #Pemrolizumab as #AdjuvantTherapy in #Melanoma | RFS & DMFS | Individualized #neoantigen therapy designed based on the unique mutational ‘fingerprint' of a patient's own tumor | @MoffittNews https://t.co/SM4f384Wa8 Positive
Patrick Forde Next step lung cancer? Adjuvant personalized vaccine improves outcomes in resected melanoma. Trials either fully accrued or ongoing in lung! #lcsm https://t.co/zqOeKTH2Nl Positive
Yüksel Ürün Personalized cancer vaccines crossed a major line. Phase 3 INTerpath-001 is positive in resected melanoma. We also participated in the adjuvant RCC trial and are looking forward to seeing its results. @OncoAlert @ONCOassist @OpenMedicineHQ @AnkaraUni @Ankaratip1945 https://t.co/poRpkCiF4V Positive
Vivek Subbiah, MD ⭐️🚨 Moderna and Merck say mRNA cancer vaccine succeeded in late-stage melanoma trial. ⭐️So-called “neoantigen” vaccines have long been seen as having potential as cancer treatments, but this is the first randomized Phase 3 clinical trial aimed at definitively proving their benefit. In this case the personalized vaccine, intismeran, was combined with Merck’s Keytruda in adjuvant melanoma, meaning patients’ disease had been surgically removed @OncoAlert https://t.co/5em9OgrOdQ via @statnews Positive
Yannick Buccella MD A personalized mRNA cancer vaccine passed Phase 3, genuinely great news for melanoma patients! What happens here? They sequence your tumor, find up to 34 mutations unique to it, and build a custom vaccine that trains your immune system to hunt those exact cells. In a phase 2 trial earlier this year the vaccine with immunotherapy has shown ~49% lower risk of recurrence or death vs immunotherapy alone, which is the current standard of care. We are waiting now for the details of the phase 3. After that that concept is now expanding to lung, kidney, bladder cancer and hopefully to many more to come. Huge win for science! Positive
Eric D Whitman, MD Very exciting news, happy to have been an investigator on this trial. Excited to learn full results! https://t.co/0fhiswRi1k Positive
Gavitt Woodard Great to see positive results in melanoma and hope it also works in NSCLC. Yale @SmilowCancer is a site for @Merck @moderna_tx INT trial as adjuvant therapy in stage I NSCLC and recently randomized our first pt. Excited to see trials and have more to offer stage I NSCLC pts! https://t.co/MYI1CDb7ya Positive
Yago Garitaonaindía 🔥🔥 First positive Phase 3 for an individualized neoantigen therapy: INTerpath-001 (press releas, @Merck) Intismeran (mRNA-4157) + pembro in resected stage IIB-IV melanoma (n=1,137) ➡️ RFS met | DMFS met | OS immature ✋🏼Topline only. But this opens a new chapter in IO. https://t.co/CS5Nsmx9l5 Positive
Tarek Haykal, MD, MHS BREAKING: Intismeran with Keytruda is the first and only combination to demonstrate statistically significant and clinically meaningful improvements in RFS and DMFS compared to KEYTRUDA alone for patients in the adjuvant melanoma setting. So happy for our patients and our field! https://t.co/IkVQJVCb0O Positive
Enrique Grande 🧬 HOW DOES A PERSONALIZED mRNA CANCER VACCINE ACTUALLY WORK? As an oncologist, and also as a university professor, I strongly believe that understanding how a new treatment works is often the best way to understand why it may eventually change our clinical practice. So, what exactly is a personalized mRNA cancer vaccine? The concept is both sophisticated and surprisingly intuitive. 1️⃣ Start with the patient's own tumor 🧬 Every cancer is genetically different. By sequencing tumor DNA and RNA, and comparing this information with normal tissue , we can identify tumor-specific mutations. Some of these mutations generate abnormal proteins that are not present in healthy cells. These are called neoantigens. And importantly, they can become molecular "flags" allowing the immune system to distinguish cancer cells from normal cells. 2️⃣ Select the best targets 🎯 Not every mutation will generate an effective immune response. Bioinformatic algorithms therefore analyze the patient's tumor and predict which neoantigens are most likely to be recognized by their immune system. In the case of intismeran autogene, up to 34 patient-specific neoantigens can be selected. 3️⃣ Build an individualized mRNA therapy 💉 Here comes the fascinating part. A synthetic mRNA sequence encoding those selected neoantigens is manufactured specifically for that individual patient. Think about what this means. We are no longer simply choosing the best available drug for a patient. We are manufacturing a treatment based on the molecular identity of that patient's own cancer. 4️⃣ Teach the immune system what to recognize 🛡️ After administration, the mRNA enters cells and provides the instructions to produce the selected neoantigens. These neoantigens are processed and presented to the immune system, activating tumor-specific CD4+ and CD8+ T cells. The objective is to generate an immune response capable of recognizing cells carrying those same neoantigens. 5️⃣ Let T cells search for the cancer 🔎 Those activated T cells can then recognize tumor cells displaying the corresponding antigens and potentially destroy them. This is why combining personalized vaccination with PD-1 blockade such as pembrolizumab makes so much biological sense: 🎯 The vaccine may teach the immune system WHAT to attack. 🔓 Checkpoint inhibition may help the immune system KEEP attacking it. And this is where, in my view, the concept becomes much bigger than one drug or one tumor type. For many years, we have defined precision oncology as: “the right treatment for the right patient.” Personalized mRNA vaccines introduce an even more ambitious paradigm: “a treatment designed and manufactured specifically from the molecular characteristics of one patient's cancer.” @OncoAlert @_SEOM @moderna_tx @GEPAC_ Figure adapted from: doi:10.3390/cancers17091408. Neutral
Hidehito HORINOUCHI mRNA-4157-P201/KEYNOTE-942: Pembrolizumab +/- mRNA-4157 (V940, personalized cancer vaccine) as adjuvant therapy in resectable melanoma, a randomized phase 2, open-label study by Dr. Jeffrey Weber. What happens in melanoma will happen in lung cancer. #AACR23 #LCSM https://t.co/Rebrpl0Ltb Neutral
Hidehito HORINOUCHI 🔥INTerpath-002: Adj Pembrolizumab + V940 (mRNA-4157) vs. Pembro 🆙 @Merck @moderna_tx 🎯Primary completion: 2030-06-25 👥Patients: Completely resected (R0) Stage II, IIIA or IIIB (N2) NSCLC, post-surgery and adjuvant chemotherapy 3⃣Phase III ⚖️Intismeran autogene (mRNA-4157) + pembrolizumab ⚖️Pembrolizumab alone (+ placebo) 🔢NCT06077760 #LCSM @OncoAlert @Larvol Neutral
Enrique Grande 💉 Personalized mRNA cancer vaccines like intismeran autogene (V940/mRNA-4157) can work in genitourinary cancers? Three ongoing studies are particularly interesting. 🔵 KIDNEY CANCER — INTerpath-004 This randomized, double-blind Phase II study is evaluating adjuvant: V940 + pembrolizumab vs placebo + pembrolizumab following nephrectomy in patients with RCC at increased risk of recurrence. The primary endpoint is disease-free survival, with distant metastasis-free survival and overall survival among the secondary endpoints. If individualized neoantigen vaccination works in RCC, it could therefore tell us something very important about the biology of this platform: its potential may extend beyond simply selecting tumors with very high mutational burden. 🟠 MUSCLE-INVASIVE BLADDER CANCER — INTerpath-005 Here the development strategy is even more ambitious. INTerpath-005 is a Phase I/II program exploring V940 in two different settings. One cohort evaluates a perioperative strategy combining: V940 + pembrolizumab + enfortumab vedotin in cisplatin-ineligible patients undergoing radical cystectomy. Another randomized cohort evaluates adjuvant: V940 + pembrolizumab vs placebo + pembrolizumab in patients with high-risk resected muscle-invasive urothelial carcinoma. Could we combine three completely different therapeutic principles? 💥 EV → rapidly kills Nectin-4-expressing tumor cells 🔓 Pembrolizumab → releases PD-1-mediated immune inhibition 🎯 V940 → potentially generates an individualized T-cell response against that patient's unique tumor neoantigens ADC + checkpoint inhibition + personalized vaccination. Three mechanisms. One objective: eradicate micrometastatic residual disease before it can become clinically visible. And there is another bladder cancer study that should not be overlooked. 🟡 NON-MUSCLE-INVASIVE BLADDER CANCER — INTerpath-011 This ongoing randomized Phase II study is evaluating: V940 + BCG vs BCG alone in treatment-naïve high-risk NMIBC. I find this particularly intriguing. BCG has successfully exploited the immune system against bladder cancer for decades. Combining this established local immunotherapy with a systemic, individualized neoantigen-directed immune strategy represents a completely different way of thinking about treatment intensification in early bladder cancer. Of course, none of these studies is guaranteed to reproduce what we have seen in melanoma. For someone who has spent much of his career developing new treatments for kidney and bladder cancer, I find the possibility particularly exciting. Precision oncology has traditionally meant finding the right drug for the right patient. Personalized mRNA vaccines introduce an even more ambitious concept: creating a different drug for each individual patient's cancer. @OncoAlert @_SEOM @GuardConsortium @urotoday @GUOncologyNow @LACOG_group @GEPAC_ Neutral
Sara Coca Membribes A milestone for individualised neoantigen therapy and encouraging for the broader V940 (mRNA-4157) programme! Will the melanoma signal translate to GU cancers? - INTerpath-004: V940 + pembro vs pembro in adjuvant RCC - INTerpath-005: V940 + pembro vs pembro in MIUC @OncoAlert https://t.co/Q16XNfFHJX https://t.co/leaRqALAaQ Neutral
Tom Powles Personalized mRNA-based neoantigen vaccines + pembo are being tested in a number of randomised adjuvant cancer trials (included bladder and renal). The 1st positive trial (RIII in melanoma) was announced today. PCVs are logistically complex with limited monotherapy activity in advanced disease, but early IO combinations in MRD may overcome tumor microenvironment resistance. Patient selection or even vaccine generation could occur with ctDNA. @OncoAlert https://t.co/FUC1sDu3pn Neutral
Henry C Fung| MM, lymphoma, leukemia & CART Amazing !!! This maybe the future of Cell Therapy for solid tumors. Personalized. AI-designed. Multiplex. Neoantigen TCR-T may be one of the most compelling paths to bring the power of CAR-T to solid tumors. 🧬 Sequence the tumor 🤖 AI identifies the best neoantigens 🎯 Select multiple targets to limit immune escape 🧫 Engineer the optimal TCRs 🦠 Build a personalized T-cell product Perhaps the future is not simply CAR-T vs TCR-T. It is a personalized synthetic immune system, designed from the patient’s own tumor. That could change everything. #Medtwitter #CART [QUOTED] JUST IN and via @Merck + @moderna_tx: A landmark moment for cancer immunotherapy. 🎯 Phase 3 INTerpath-001 is positive: the individualized mRNA neoantigen therapy intismeran (V940/mRNA-4157) + pembrolizumab significantly improved both RFS/DMFS vs pembrolizumab alone after resection of high-risk melanoma. For years, the idea of designing a treatment around the unique mutations of each patient’s tumor seemed aspirational. Now we have the first positive Phase 3 trial (N=1137) of an individualized neoantigen therapy—and of an mRNA-based cancer therapy. Personalized cancer vaccines are moving from promise to reality. Now we need to see the magnitude of benefit, durability, and ultimately OS. But today is an important day for the field—and hopefully for our patients. 👏 Congrats to #CathyWu @DanaFarber for her trailblazing research that is materializing in tangible outcomes! At @DanaFarber_GU we are closely working with Cathy + @DFCI_NeoVax team on several GU protocols, after our @Nature work with @BraunMDPhD et al (https://t.co/BdbKJqMKOw) https://t.co/Akd0XQt3ml Neutral
Anirban Maitra Huge news in personalized cancer vaccine space this morning.* * awaiting full release of data. Moderna and Merck say mRNA cancer vaccine succeeded in late-stage melanoma trial https://t.co/3Il37x9Rr9 @Perlmutter_CC @JaniceM10 Neutral
Enrique Grande Today may represent a turning point for personalized cancer immunotherapy. The positive Phase III results from INTerpath-001, evaluating the individualized neoantigen therapy intismeran autogene (V940/mRNA-4157) in combination with pembrolizumab in patients with resected high-risk melanoma, go far beyond melanoma itself. For me, the most exciting aspect of these results is the clinical validation of the platform. For years, personalized mRNA cancer vaccines have represented an extraordinarily attractive scientific concept: identify the unique neoantigens generated by an individual patient's tumor, design a personalized mRNA therapy against them, and use the immune system to recognize and eliminate residual cancer cells. Now, for the first time, this approach has succeeded in a Phase III trial, with significant and clinically meaningful improvements in both recurrence-free survival and distant metastasis-free survival. This matters because melanoma may only be the beginning. The question now becomes whether this strategy can be successfully translated across tumor types. We will hopefully learn much more soon from the ongoing pivotal program in non-small cell lung cancer. And, from my own field, I am particularly excited about what this technology could mean for bladder and kidney cancers. Both are diseases in which immunotherapy has already fundamentally changed outcomes, but where we still need better ways to identify, amplify and sustain effective antitumor immune responses. The possibility of adding a truly individualized, tumor-specific immune strategy opens a fascinating new avenue for drug development. Of course, important questions remain: magnitude and durability of benefit, patient selection, manufacturing timelines, scalability, biomarkers, cost, and most importantly, whether the melanoma results can be reproduced in other malignancies. But this is precisely what makes drug development so exciting. Sometimes a positive trial changes a treatment algorithm. Other times, it may validate an entirely new therapeutic platform. The coming results across tumor types will tell us which of those stories we are witnessing today. Congratulations to all the investigators, patients, families and teams at Moderna and Merck who have contributed to reaching this milestone. https://t.co/z8ZhAxJPM6 Neutral
Markus Eckstein 🚨 Landmark Phase 3 result for personalized cancer vaccines: INTerpath-001 met both RFS and DMFS endpoints: intismeran autogene (mRNA-4157/V940) + KEYTRUDA showed statistically significant and clinically meaningful improvements vs KEYTRUDA alone in resected high-risk melanoma. First positive Phase 3 readout for an individualized neoantigen therapy and an mRNA-based cancer therapy. https://t.co/2BPXkel85o Neutral
Elvina Almuradova The first positive Phase 3 trial of an individualized mRNA-based cancer therapy. Phase 3 INTerpath-001: individualized mRNA therapy + pembrolizumab significantly improved RFS and DMFS vs pembrolizumab alone in resected stage IIB–IV melanoma. @Larvol @OncoAlert https://t.co/ojCj4neKOc Neutral
Daisuke Kotani, MD, Ph.D 小谷 大輔 @OncoAlert Moderna neoantigen therapy (intismeran autogene) + pembro: Adj Ph3 in resected Stage IIB-IV melanoma met its primary endpoint of RFS Slides: 5-year follow-up results from Ph2 presented at #ASCO26. @OncoAlert @ASCO https://t.co/K8zSl0Hlse Neutral
Hidehito HORINOUCHI 🔥INTerpath-001: "Statistically significant and clinically meaningful improvements in RFS and DMFS" 🆙 @Merck @moderna_tx 👥Patients: Completely resected stage IIB-IV cutaneous melanoma, no prior systemic therapy 3⃣Phase III ⚖️Intismeran autogene (mRNA-4157) + pembrolizumab ⚖️Pembrolizumab alone (+ placebo) 🔢NCT05933577 @OncoAlert @Larvol 🔗 https://t.co/gwh3BHxVNI Neutral
Mario Balsa 🚨 Big week in oncology!!!! And @OncoAlert has it all in one place! 🔗 https://t.co/UUWeOePJ1B From daraxonrasib finally putting RAS inhibition on the map in pancreatic cancer to INTerpath-001 pushing personalized neoantigen therapy forward in melanoma 😉 One newsletter. The studies everyone will be talking about 🔥 Neutral
Niklas Klümper 🚨 Personalized cancer vaccines reach Phase III. Very exciting topline results from INTerpath-001: Intismeran autogene + pembrolizumab met both 🎯 primary endpoint: RFS 🎯 key secondary endpoint: DMFS vs pembrolizumab alone after complete resection of stage IIB–IV melanoma. Why this matters beyond melanoma: 🧬 Intismeran is an individualized mRNA neoantigen therapy, generated from the unique mutational profile of each patient’s tumor This is the first positive Phase III readout for an individualized neoantigen therapy / mRNA-based cancer therapy. The Phase II signal was already impressive and durable: at 5 years, adding intismeran reduced the risk of recurrence/death by 49% (HR 0.51) and distant metastasis/death by 59% (HR 0.41). Now we need to see the full Phase III data: effect size, absolute benefit, safety, subgroups—and ultimately OS. Particularly exciting from a precision-oncology perspective: tumor sequencing → patient-specific neoantigens → individualized therapy → improved clinical outcome! And highly relevant beyond melanoma, with the platform already being investigated across other tumors, including bladder cancer and RCC. A potentially important milestone for truly individualized cancer immunotherapy. @OncoAlert @weoncologists @DrChoueiri @oncodaily @OncBrothers Neutral
Allan Pereira, MD, PhD Landmark moment for cancer immunotherapy! 🩺🧬✨ Merck and Moderna just announced that their personalized mRNA neoantigen therapy (intismeran autogene) + Keytruda met both primary and key secondary endpoints in its Phase III melanoma trial (INTerpath-001)! 🚨🔬📊 sources: - https://t.co/7pUYOL4ky1 - https://t.co/KQOYf6G7EQ - @KobeissiLetter - @moderna_tx Neutral
Daisuke Kotani, MD, Ph.D 小谷 大輔 モデルナのmRNA個別化ネオアンチゲン療法(Intismeran Autogene)+Pembro併用療法 Stage IIB-IV悪性黒色腫を対象に、術後補助療法Ph3において、主要評価項目(RFS)を達成。 スライドは #ASCO26 で発表されたPh2の5年フォローアップ結果。 https://t.co/uaHFp1lExp @OncoAlert https://t.co/5eFABf6AbX Neutral
Syed A. Ahmad Moderna, Merck cancer vaccine shows initial late-stage melanoma data https://t.co/h2IWzFGleW Neutral
Markus Eckstein Phase 3 data for adjuvant pembro +/- personalized mRNA-based neoantigen vaccine for melanoma is positive. Press release just announced. Curious to see the data probably at ESMO? Wonder if neoantigen vaccines will also show effects in palliative/metastatic setting. https://t.co/OAgHIaxAGu Neutral
Arturo LoAIza-Bonilla, MD MSEd Intismeran is manufactured from each patient’s tumor and encodes up to 34 patient-specific neoantigens; @Merck and @moderna_tx now have nine Phase II/III studies across melanoma, NSCLC, bladder cancer and RCC. The most important next datapoint is the full INTerpath-001 dataset: absolute RFS/DMFS curves, hazard ratios, subgroup effects, manufacturing turnaround, quality of life and eventually OS. Excited for @myESMO Neutral
MJosé Juan 🚨Phase III INTerpath-001 is ✅ In resected stage IIB–IV melanoma intismeran autogene(V940)+pembro significantly improved RFS/DMFS vs pembro,confirming KEYNOTE-942 signal ⚠️ Magnitude of benefit not yet disclosed. OS FU continues Will RCC follow?Awaiting INTerpath-004 @OncoAlert https://t.co/WEHhepkhEn Neutral
Jose Fernando Moura, PhD News news Coming soon in others solid tumors @OncoAlert https://t.co/zxY97lW1XO Neutral
Moderna/Merck just ran a 1,137-patient Phase 3 trial where every single dose was unique to that patient's tumor. It worked. The pipeline: surgical resection → whole exome + RNA sequencing → ML neoantigen ranking → mRNA encoding up to 34 patient-specific targets → manufactured and shipped in 8 weeks. One drug, different sequence for every patient. The ML step is worth to note: the algorithm ingests WES + RNA-seq to identify somatic mutations, then predicts which of those will actually be immunogenic, ie, displayed on tumor cell surface and trigger a T-cell response. It's designed to keep learning from accumulated clinical and immunogenicity data across patients, not just per-patient. INTerpath-001 (Stage IIB-IV resected melanoma, 2:1 randomized): combination with pembrolizumab beat Keytruda alone on both primary (RFS) and key secondary (DMFS) at interim. Phase 2b at ASCO 2026 showed 49% reduction in recurrence/death, 59% in distant metastasis/death at 5 years. Phase 3 confirmed both. What this validates: — tumor-specific neoantigen prediction by ML works in a blinded trial at scale — 8-week personalized mRNA manufacturing is operationally real — effect is additive on PD-1 blockade, not redundant This is first positive Ph3 for individualized neoantigen therapy. First positive Ph3 for any mRNA cancer therapeutic. What a great time to live in!! This is the best time for AI & biotech! Neutral
Cancer vaccines have a history of broken promises. Intismeran could be the start of a new era! I discussed with @natashaloder at @TheEconomist why the data are “promising for the field of melanoma and cancer as a whole.” @Merck @moderna_tx https://t.co/2UBt902e1P https://t.co/sUaZGb4wee Neutral
Follow what KOLs are saying about the most exciting data in Cancer Research 👉 INTerpath-001 Trial: Intismeran + Pembrolizumab in Resected Melanoma https://t.co/dCXf4EOIzr Neutral
Lots of push back at Moderna and Merck’s early press release of the phase 3 trial (INTerpath-001) that builds directly on the durable Phase 2b trial signal which showed a 50% lower recurrence risk of high risk Melanoma at 5 years . The phase 2b data was reported in June 2026 Phase 2b 5-year update, link below. mRNA neo-antigen vaccines are the future of cancer therapy IMO. Neutral
Yago Garitaonaindía 🚨 #ESMO26 INTerpath-001 leaked before the embargo, so @myESMO released it early ➡️ Intismeran (mRNA-4157) + pembro vs placebo + pembro, adjuvant stage IIB-IV #melanoma • 24-mo RFS 82.2% vs 70.0% | HR 0.58 • 24-mo DMFS 88.5% vs 80.2% | HR 0.62 • G≥3 AEs 23.6% vs 20.3% 👇👇 Neutral
Yakup Ergün An embargo breach at a congress as prestigious as ESMO is unacceptable. If I remember correctly, something similar happened in 2023. It is deeply troubling to feel that sharing scientific data is driven more by stock market movements than by patients and science…!!! Neutral
Eric Topol How to improve outcomes in patients with metastatic melanoma post-surgical resection, and specifically, vs controls: —Reduce 2-year mortality from 82 to 70% —Reduce recurrence by 42% Treat with a personalized mRNA neoantigen vaccine @statnews @adamfeuerstein Positive
Mark Yarchoan Topline ESMO data from INTerpath-001 (#Moderna’s personalized cancer vaccine) reportedly leaked elsewhere: DFS HR 0.58 This hazard ratio puts it in the company of the most paradigm-changing adjuvant trials in oncology history: Positive
Omid Hamid, MD @moderna_tx will ultimately find its strength in solid tumors including melanoma that have poor response to neoadjuvant as adjuvant combo including #nsclc - don't forget that there are many stage 3 patients that aren't offered neoadjuvant. Also a broader group of III melanoma based on sentinel node - benefit for a broader group. The head to head comparison is false. Positive
Amol Akhade 🚨 ESMO 2026 | INTErpath-001 (LBA1) - as data is released by Esmo 🔹 24-month RFS: 82.2% vs 70.0% HR 0.58 (95% CI 0.45–0.75); P<0.001 🔹 24-month DMFS: 88.5% vs 80.2% HR 0.62 (95% CI 0.45–0.85); P=0.002 🔹 Grade ≥3 adverse events: 23.6% vs 20.3% The trial randomized 1,137 patients with resected stage IIB–IV melanoma. Both arms received pembrolizumab; the experimental arm added an individualized mRNA neoantigen therapy. The key question now: will better recurrence control translate into an overall survival benefit? Looking forward to full dataset on day 2 . #ESMO26 @myESMO Neutral
Estela Rodriguez 🤷🏽‍♀️Proof that the market is irrational. This now officially released Merck/Moderna cancer vaccine (mRNA-457) results from a Phase 3 study of 1,100 pts w high-risk melanoma to be presented at #ESMO26 look impressive to me- cuts melanoma death or recurrence risk by 42% and cancer metastases by 38% but shares fall ? Positive
Pablo Jiménez @OncoAlert @brunolarvol @adamfeuerstein An alleged third-party leak of the top plenary presentation of the #interpath-001 at #ESMO2026 . Source still unknown. #Intismeran autogene + pembro reportedly reduced recurrence or death (EFS) risk by 42% (HR 0.58) for resected IIB-IV #melanoma Possible #PracticeChanging pending safety and full text publication Neutral
Estela Rodriguez Looking forward to the presentation and discussion. #LBA1 Phase 3 INTerpath-001 trial results at #ESMO26 👉🏽The Kaplan-Meir curves don’t always tell the whole story. Side effects, cost, access matter but 👉🏽Its is very exciting that a personalized mRNA technology can be used to control cancer recurrence. Positive
NonsparseOncologist ‼️ Interesting commentary on INTerpath-001 No need for vaccine if pembro given neoadjuvant? Wow, await further details / data here, but what a dud! Precision/Personalized dud https://t.co/i1SNiVUjfz Negative
ALFONSO DUEÑAS GONZALEZ Cautionary note – personalized mRNA neoantigen vaccine (intismeran / mRNA-4157) in resected melanoma. The reported reduction in recurrence is real, yet several core uncertainties remain unresolved. The control was an inactive placebo, not a scrambled or irrelevant mRNA matched for mass and antigen number. Non-specific innate effects of the mRNA-LNP platform therefore cannot be separated from antigen-specific activity. No published in vitro data have tested whether the encoded neoantigen peptides or mRNA constructs exert any direct stimulatory or pro-proliferative effect on melanoma cells independent of the immune system. This possibility has not been experimentally excluded. Overall survival benefit is still immature, and the contribution of the vaccine outside the adjuvant Keytruda combination is unproven. Manufacturing time, cost, and scalability constraints are substantial; generalizability beyond highly selected resected melanoma remains limited. These open questions do not erase the clinical signal. They do limit how confidently the mechanism and the true incremental value of the personalized neoantigens can be asserted. Neutral
Mario Balsa 🚨 #ESMO26 | Phase III INTerpath-001 🚨 After an early embargo breach, @myESMO brought the abstract release forward!!!!!! And yes, it’s clearly positive: 📉 RFS HR 0.58 📉 DMFS HR 0.62 But here’s the uncomfortable part: SWOG S1801 also reported an HR 0.58…simply by moving 3 doses of pembrolizumab BEFORE surgery… ☝🏼Not the same population. Not the same endpoint. Not a cross-trial comparison. Still, in 2026, should a personalized mRNA vaccine really be benchmarked against adjuvant pembro alone? Before calling this a new standard, I want to see the vaccine face the NEOADJUVANT era. Same HR. Different path. And that may be the real INTerpath question 👀 @OncoAlert @OncoReporte @myESMO @_SEOM @GrupoMelanoma What do you think? @SuyogCancer @OncBrothers @A_May_MD @Dr_R_Kurzrock Neutral
Yago Garitaonaindía Some thoughts on the INTerpath-001 backlash, and the simplistic "neoadjuvant already does better, so why bother" take. I think it misses a few important things. ➡️ First, the neoadjuvant data (S1801, NADINA) come from patients with macroscopic, clinically detectable nodal disease. INTerpath-001 also includes node-negative IIB/IIC and patients whose nodal disease only showed up on sentinel node biopsy. In the big SLN trials, about two thirds of SLN+ patients had deposits ≤1 mm. None of these patients are neoadjuvant candidates. We see the same confusion in #NSCLC all the time, when people compare stage IIIA from adjuvant trials (pathological staging) with stage IIIA from neoadjuvant trials (clinical staging). Same stage on paper, not the same patients. ➡️ Second, INTerpath-001 was designed before NADINA read out, when adjuvant anti-PD-1 was still the default for resected stage III. Judging it against today's practice is a bit of hindsight. ➡️ Third, I suspect the most logical place for a neoantigen vaccine is after neoadjuvant ICI in patients who don't reach pCR. INTerpath-009 is already testing exactly this in NSCLC, so we'll get some hints there. ➡️ And all of this comes with only an absolute ~3% increase in grade ≥3 toxicity, which also belongs in the balance. For macroscopic stage III, the critique lands. I want to see the full data and the stage breakdown at LBA1. But I'd be careful firing at this result before we've even seen it properly. @OncoAlert @Larvol @KolPulseAI @_SEOM @myESMO #Melanoma #ESMO26 Positive
Nicholas Hornstein Topline ESMO data from INTerpath-001 (#Moderna's personalized cancer vaccine) reportedly leaked elsewhere: RFS HR 0.58 (Honestly shame on people for breaking embargo’s). There is a huge divide here between physicians and non-physicians on the outcome. To me, this was huge and clearly worked. This hazard ratio puts it in the company of the most paradigm-changing adjuvant trials in oncology history. Yes, the same outcome can be generated from giving pembro in the neoadjuvant space [SWOG S1801 neoadjuvant + adjuvant pembro vs adjuvant pembro alone: EFS HR 0.58.] That isn't the point. A peptide vaccine strategy yielded the same outcome as having a tumor in vivo. This demonstrates the tech worked, now it can be applied more broadly or potentially even supercharge the neoadjuvant space with less immunogenic tumors. Time to do better and apply to more things (like colon cancer pls). #ESMO26
@OncoAlert @TheGutOncLab Positive
MV Chandrakanth ADJUVANT MELANOMA | ESMO 2026 INTerpath-001: How Much Benefit Are We Actually Adding? Adding a personalised mRNA vaccine to pembrolizumab improved 2-year RFS from 70.0% to 82.2%. Absolute gain: +12.2 percentage points | HR 0.58 Unlike earlier adjuvant trials against placebo or ipilimumab, this benefit was demonstrated on top of pembrolizumab. ⚠️ Cross-trial comparisons are not valid: populations, comparators and follow-up differ. OS benefit remains unproven. The key question: Will this RFS advantage translate into improved long-term survival? #MVOnco #ESMO2026 #INTerpath001 #Melanoma #CancerVaccine #Immunotherapy Neutral
ツチノコ在宅ケモ屋 ツチノコ的ESMOレビュー① いきなり情報解禁前にデータが漏れるという大波乱の幕開けです。 モデルナの株価が25%下落の 大・暴・落!! 個別化mRNAがんワクチン 「intismeran autogene」 の第Ⅲ相試験、INTerpath-001ですね。 すでにデータが世に出てしまったため、ESMOが正式に情報解禁を前倒ししました。 これ、何をやっているかというと、、 患者さんのがんの遺伝子情報を調べて、その人のがんに特有の目印を狙うmRNAワクチンを作る。 それを使って、免疫に 「この目印のあるがん細胞を攻撃してくれ」 と教える治療です。 患者さんごとに作る、オーダーメイドのがんワクチンですね。 今回の対象は完全切除後のStage IIB〜IVの悪性黒色腫の患者さん1,137人。 ①個別化mRNAがんワクチン+キイトルーダ(Pembrolizumab) ②キイトルーダ単独 を比較しています。 結果は、、 【2年無再発生存率】 82.2% vs 70.0% HR 0.58、p<0.001 再発または死亡のリスクが42%低下。 【2年遠隔転移無生存率】 88.5% vs 80.2% HR 0.62、p=0.002 遠隔転移または死亡のリスクが38%低下。 Grade 3〜5の治療関連有害事象は 14.2% vs 13.4%でした。 全生存期間はまだ追跡が必要ですが、キイトルーダに上乗せして再発を減らしたというのは、臨床的には重要な結果だと思います。 ところが、、 モデルナの株価は、データ公開後に25%超下落したと報じられています。 「え、効いてるのに何で?」 ってなりますよね。 そもそもモデルナ株は、今回の治療への期待などから年初来500%超も上昇していました。 なので、良い結果が出ること自体は、すでに株価に織り込まれていたという話です。 加えて、先行する第Ⅱ相試験から期待されていたほどには 遠隔転移を抑える効果が大きくなかった、という受け止めもあったようです。 ただし、対象や追跡期間の違う試験をそのまま比較して「効果が落ちた」とは言えません。 個人的には、患者さんごとに作るmRNAがんワクチンが、第Ⅲ相で再発抑制効果を示したこと自体が大きいと思います。 ただ、これで色々ながんに効くと決まったわけではありません。 まずはメラノーマでの結果として評価して、OSと他のがん種の試験の結果を今後は見ていきたいですね。 ツチノコ的には数十年もすればゲノム含めがん治療は完全に個別化される可能性があると思っているので 標準治療の教育体系から変えていかなくてはならないのでは? という印象です。 公式資料: https://t.co/NWcEXu7k0B⁠ #ESMO26 米モデルナの株価が一時26%安 治験データ漏洩、期待に届かず:日本経済新聞 https://t.co/ZM4mZ3zM9N Positive
Mario Balsa 🚨 Scientific embargoes exist for a reason: fair access to data, scientific integrity and, ultimately, patients. Seeing a major #ESMO26 study disclosed ahead of schedule is disappointing. I think ESMO takes its embargo policy seriously, and I would expect a breach of this magnitude to have consequences. Science should set the timeline, not the stock market 😡 With INTerpath-001, someone clearly took a shortcut on the path to the data. @OncoAlert @OncoReporte @myESMO @_SEOM @GrupoMelanoma Neutral
Balazs Halmos I note of skepticism that the the adjuvant individualized neoantigen therapy data is not meaningful progress In case of NSCLC- we shall learn as there are 3 separate studies ongoing (one just completing accrual!) But scientifically… Neoadj IO works better compared to adj IO as activated T cells need to see the “in situ vaccine” of the native tumor for long-standing benefit. Postop in micromet setting simply stated there is just no cancer cells to work with- as an analogy, for T cells to build muscles they need machines in the gym… otherwise, no lifting- no muscle… Now the beauty of INT is that it does provide an excellent gym with the best tailored neoantigen weight machines for the immune system to work with! So w results of Interpath-001 i’d say- T cells and all of us, lets go to the gym and Cheers on a first set of great results! Positive
Prof.Dr.Erdinç Nayır 🔴 Avrupa Onkoloji Kongresi (ESMO 2026)’nde açıklandı! Malign melanomda immünoterapiye, kişiye özel hazırlanmış mRNA kanser aşısının eklenmesi kanserin tekrarlaması veya ölüm riskini %42 azaldı Uzak metastaz riskini de %38 azaldı. Faz 3 INTerpath-001 çalışması. #cancer #oncology #ESMO2026 Neutral
BASEM BAHRANI باسم البحراني 💉لقاح mRNA شخصي يقلل خطر عودة سرطان الجلد أو الوفاة بنسبة 42% 📉 أعلنت شركتا Moderna⁠ و Merck⁠ نتائج تجربة INTerpath-001 من المرحلة الثالثة 📉 اختبرت التجربة لقاح Intismeran autogene المصمم خصيصاً وفق الطفرات الجينية لورم كل مريض بشكل شخصي بالإضافة إلى العلاج المناعي Pembrolizumab بعد الاستئصال الجراحي لسرطان الجلد الميلانيني عالي الخطورة 📉 شملت التجربة أكثر من 1,100 مريض 📉 النتيجة 🔹انخفاض الخطر النسبي Relative Hazard Reduction لعودة السرطان أو الوفاة 42% 🔹انخفاض الخطر النسبي للانتشار البعيد أو الوفاة 38% 🔹البقاء دون عودة السرطان مع العلاج المركب 82.2% و تمثل نسبة المرضى الذين بقوا دون عودة السرطان أو الوفاة خلال عامين Recurrence-Free Survival 🔹البقاء دون عودة السرطان مع Pembrolizumab وحده 70% 📉 الأهمية السريرية: يمثل هذا أول دليل من المرحلة الثالثة على فائدة سريرية للقاح سرطاني شخصي قائم على تقنية mRNA عند إضافته إلى العلاج المناعي ❗️النتائج مشجعة انخفاض الخطر النسبي بنسبة 42% لا يعني انخفاض الوفيات وحدها بهذه النسبة بيانات البقاء الكلي غير مكتملة و لم يحصل اللقاح بعد على الموافقات التنظيمية https://t.co/Znw4S3Pl7Z https://t.co/wGMx1VeKui https://t.co/FXD240UPQd Neutral
Yakup Ergün I’d applaud these trials, but I’d remain seated 😅😅 INTerpath-001 is an innovative treatment approach. However, there is no comparison with neoadjuvant nivo + ipi, a strong option particularly in macroscopic stage III melanoma. DeLLphi-305 showed a survival benefit with maintenance tarlatamab + durvalumab. But the comparator is durvalumab monotherapy. We also have positive results from IMforte with maintenance atezo + lurbinectedin. So this is another potential maintenance option; its place among the existing options remains to be defined. In HARMONi-GI1, even if not one but three trucks could fit between the Kaplan–Meier curves, global validation will still be expected because the trial was conducted exclusively in China 🫣 For me, VOLGA’s most interesting feature is the omission of adjuvant EV. As for the survival benefit of perioperative EV + immunotherapy, we already have strong data. Neutral
Tian Zhang, MD, MHS, FASCO (@tiansterzhangmd.bsky) with med onc pearls for neoantigen mRNA vaccines. The future is happening now — esp w readout of INTERPATH-001 trial this #ESMO26 @myESMO @oncoalert https://t.co/EhNz2A40yG Neutral
Hidehito HORINOUCHI 🆙#ESMO26 Presidential Symposium I 🔥INTerpath-001: Phase 3 Study of the mRNA-Based Individualized Neoantigen Therapy (INT) Intismeran Autogene (Intismeran) Plus Pembrolizumab (Pembro) vs Pembro Alone for Adjuvant Treatment of Resected Stage IIB-IV Melanoma (MEL) 🎙️ @ProfGLongMIA 🔢LBA1 🎯Met Primary Endpoint: Significantly Improved RFS 🎯24-Mo 82.2% vs 70.0%, HR 0.58 🎯DMFS HR 0.62 🎯Grade≥3 AEs 23.6% vs 20.3% ☑️NCT05933577 🔗 https://t.co/Lb6tzuMm0z @OncoAlert @Larvol @myESMO Positive
Mustafa Özdoğan, MD Personalised mRNA therapy reaches Phase 3 in melanoma: INTerpath-001 met RFS and DMFS with intismeran autogene + pembrolizumab. The key question now is magnitude-HRs, absolute benefit and detailed toxicity are still awaited. Presented by @ProfGLongMIA at @myESMO. Developed by @moderna_tx + @Merck. #ESMO26 #Melanoma Neutral
Ahmad Tarhini #Madrid #ESMO26 | Main findings from INTerpath-001 released: #Intismeran + #pembrolizumab reduced risk of recurrence or death by 42% (HR, 0.58), risk of distant metastasis or death by 38% (HR, 0.62); 24-monRFS rates 82.2% vs 70.0% | Proud to be part of this effort @MoffittNews Neutral
Tejas Patil 🌟AND finally, #ESMO26 wouldn't be complete without some of the HEAVY hitters. I expect these data to change practice! 1⃣Tarlatamab plus durvalumab (durva) vs durva as 1L maintenance (1LM) therapy following durva, platinum, and etoposide (1L durva + EP) in extensive-stage small cell lung cancer (ES-SCLC): Primary analysis of the phase 3 DeLLphi-305 trial. I fully expect this trial to establish DLL3 TCE as the dominant first line strategy in SCLC and will likely be practice changing. 2⃣Krascendo 1: Efficacy and safety of divarasib (diva) vs sotorasib (soto) or adagrasib (ada) in previously treated locally advanced or metastatic KRAS G12C-mutated NSCLC. Given the evolution of KRAS G12Ci in this space, what is notable here is the direct prospective comparison to current KRAS G12Ci (adagrasib / sotorasib). Looking forward to ascertain magnitude of potential benefit and safety differences. 3⃣INTerpath-001: Phase 3 study of the mRNA-based individualized neoantigen therapy (INT) intismeran autogene (intismeran) plus pembrolizumab (pembro) vs pembro alone for adjuvant treatment of resected stage IIB-IV melanoma (MEL) Technically not a lung cancer study, but I believe this trial to be game-changing from a proof-of-concept approach. In my mind, this study establishes personalized mRNA-based approaches as a viable approach and worthy of research and clinical investment. @lcsmchat @OncoAlert @OncLive @Onco_Nexus @LungCancerEu @Lung_Cancers @LungCancerRx @MedwatchHQ @KRASKickers @SclcSMASHERS @YoungLungCancer Positive
Mustafa Özdoğan, MD Twelve more patients in a hundred stay recurrence-free at 2 years — on top of pembrolizumab alone. INTerpath-001 (LBA1, #ESMO26): resected stage IIB–IV melanoma; intismeran autogene + pembrolizumab vs pembrolizumab (n=1,137). Early release after embargo breach — confirm at PS I (Long). @ProfGLongMIA Neutral
Evelyn Wong Enjoyed @MarcoGerlinger's take on INTerpath & the discontinued BNT-122 CRC study at #ESMO26. What can each teach us? A reminder: we’re testing a strategy: that includes tumour biology, combination therapy and patient selection and not just a vaccine. #ESMOAmbassadors https://t.co/NfRxtIrsui Neutral
Aiken Dao Encouraging developments in personalised cancer immunotherapy. Phase 3 results from the INTerpath-001 trial suggest that an investigational mRNA-based treatment, intismeran autogene, combined with pembrolizumab, reduced the relative risk of melanoma recurrence or death by 42% compared with pembrolizumab alone. At two years, 82.2% of patients receiving the combination remained free from recurrence, compared with 70% in the control group. The treatment is individually designed using mutations identified in each patient's tumour. Overall survival outcomes remain under evaluation, but these findings represent promising progress towards more personalised approaches to cancer treatment. #Melanoma #CancerResearch #mRNA #Immunotherapy #PrecisionMedicine https://t.co/7gPUjc3Bjh Positive
Yago Garitaonaindía When INTerpath-001 opened, neoadjuvant pembro had only one randomized phase 2 behind it. The phase 3 evidence came later with NADINA. Adjuvant pembro was a justified control arm. Evidence often moves faster than trials, that's everyday oncology. But I insist, it only applies to macroscopic disease, not to IIB-IIC or cN0 stage III. Neutral
Mustafa Özdoğan, MD Congratulations on bringing INTerpath-001 to PS I — a positive Phase 3 on an active control is a high bar. What I most want from Long’s slides: stage IIB vs III/IV subgroup RFS, timing of toxicity relative to immunization doses, and manufacturing turnaround / treatment-start delay in the personalized arm. Circulating: RFS HR 0.58, +12.2 pp at 24 mo; G≥3 23.6 vs 20.3. OS still the endpoint that decides clinic adoption. Positive
Yakup Ergün #ESMO26 INTerpath-001 8 Grade 5 AEs in the experimental arm, 0 in the control arm. Of course, it could all be pure coincidence! After all, 6 of the 8 events were not considered TRAE Perhaps it was just the excitement of being randomized to the experimental arm? I'm genuinely curious about the independent causality assessment. Neutral
Yakup Ergün #ESMO26 | INTerpath-001: My Personal Perspective Ahead of the Presidential Session This innovation deserves recognition: a groundbreaking result for personalized cancer vaccines. However, in patients with macroscopic stage III melanoma who are eligible for neoadjuvant IO, this trial does not establish the added value over contemporary perioperative strategies. Neoadjuvant treatment can produce substantial responses while allowing some patients to avoid adjuvant therapy. The trial design I would prioritize is: Neoadjuvant IO → surgery → standard adjuvant therapy ± a personalized vaccine in patients without a major pathological response. Here, “failure to achieve a major pathological response” is a more appropriate selection criterion than “any residual disease.” Patients with minimal residual viable tumor who still achieve a major pathological response should not automatically receive additional treatment. This approach would direct treatment intensification toward patients at higher risk of recurrence. The key biological uncertainty, however, is that IO-resistant residual disease is not necessarily vaccine-sensitive. Whether vaccination can overcome that resistance needs to be demonstrated. This criticism should remain specific to that population: INTerpath-001 retains distinct clinical value for patients with stage IIB/IIC disease and those who underwent surgery without neoadjuvant therapy. Neutral
Toni Choueiri, MD Superb presentation by Georgina Long! INTerpath-001: adding personalized mRNA vaccine intismeran to pembrolizumab reduced recurrence/death risk by 42% in resected stage IIB-IV melanoma (HR 0.58). A major step for cancer vaccines! #ESMO26 @OncoAlert @myESMO #ESMO26 https://t.co/9miRzK7fhb Positive
Balazs Halmos I admit i am very much into intismeran…and it seems many others too as it is standing room only here… Fabulous presentation/data on the Interpath-001 trial demonstrating clear benefit of this space age bespoke neoantigen vaccine along w pembro for pts w resected high risk melanoma as to 40% or so improvement in RFS/distant met free survival Indeed a landmark trial for precision medicine and hopefully not too Long before we see confirmation in nsclc/other trials! Interpath- indeed makes us foresee a wonderful path and light ahead for our field! #ESMO26 Neutral
Yago Garitaonaindía 🔥 #ESMO26 INTerpath-001, full data (now yes) On top of RFS HR 0.58 and DMFS HR 0.62: • Manufacturing success >99% • >90% of patients got the maximum 34 neoantigens 🔍 Practice-changing? For a population, yes. Two things still to prove: • Can an mRNA strategy rescue patients primary refractory to neoadjuvant ipi-nivo (no pathologic response)? • Will it move OS in stage II-IIIB too? Resuls in @NEJM soon @myESMO @OncoAlert @Larvol @_SEOM #Melanoma #Immunotherapy Positive
Mario Balsa 👑 Presidential #ESMO26! INTerpath-001: personalized mRNA vaccination reaches phase III in melanoma. Resected stage IIB–IV melanoma, N=1,137: intismeran + pembrolizumab vs pembrolizumab. 💥 At 24 months: • RFS: 82.2% vs 70.0% → HR 0.58 • DMFS: 88.5% vs 80.2% → HR 0.62 • Absolute gains: +12.2% RFS / +8.3% DMFS • Benefit emerges mainly after 6 months • Grade ≥3 AEs: 23.6% vs 20.3% • OS still immature A clinically meaningful new mechanism, but the real question now is positioning 🤔 For macroscopic stage III: adjuvant personalized vaccine after surgery, or neoadjuvant ipi/nivo before it? Biomarkers may ultimately decide. Congrats to @ProfGLongMIA and all the team! 👏🏼 @OncoAlert @OncoReporte @myESMO @_SEOM @GrupoMelanoma Positive
Alfredo Addeo MD 🔥 Personalized cancer vaccines delivering impressive results at #ESMO26! @ProfGLongMIA presents the phase III INTerpath-001 trial in resected high-risk melanoma. Individualized neoantigen mRNA vaccine intismeran autogene + pembrolizumab vs pembrolizumab alone. Key results: 🔹 DMFS: HR 0.62 (95% CI 0.45–0.85), p=0.002 🔹 24-month DMFS: 88.5% vs 80.2% 🔹 RFS: HR 0.58 (95% CI 0.45–0.75) A major milestone for personalized cancer vaccines! A promising step towards truly individualized immunotherapy. #ESMOAmbassador #ESMO26 #Melanoma #CancerVaccines #Immunotherapy Positive
Yüksel Ürün A long-awaited breakthrough in cancer vaccines. One patient. One tumor. One personalized mRNA vaccine. INTErpath-001 brings this vision closer to clinical reality. Are we ready to deliver it? @myESMO @OncoAlert @OpenMedicineHQ #ESMO26 @ProfGLongMIA @FAndreMD @curijoey @YJanjigianMD Positive
Hidehito HORINOUCHI 🆙#ESMO26 Presidential Symposium I 🔥INTerpath-001: Phase 3 Study of the mRNA-Based Individualized Neoantigen Therapy (INT) Intismeran Autogene (Intismeran) Plus Pembrolizumab (Pembro) vs Pembro Alone for Adjuvant Treatment of Resected Stage IIB-IV Melanoma (MEL) 🎙️ @ProfGLongMIA 🔢LBA1 🎯Met Primary Endpoint: Significantly Improved RFS 🎯24-Mo 82.2% vs 70.0%, HR 0.58 🎯DMFS HR 0.62 🎯Grade≥3 AEs 23.6% vs 20.3% ☑️NCT05933577 🔗 https://t.co/Lb6tzuMm0z @OncoAlert @Larvol @myESMO Positive
Yakup Ergün #ESMO26 | INTerpath-001👇 https://t.co/9zQwLrfkBe https://t.co/jA8OFWtQqd Neutral
Yüksel Ürün A milestone for personalized cancer vaccines. INTErpath-001: 42% lower recurrence/death risk; 24-month RFS 82.2% vs 70%. Can we extend this benefit to other cancers? @myESMO @OncoAlert @OpenMedicineHQ #ESMO26 https://t.co/567xy0e42L Neutral
Sara Coca Membribes #ESMO26 Starting the Presidential Session with INTerpath-001 Intismeran + pembro shows ⬇️risk of recurrence and of distant mets including high-risk stages. A major step forward for personalised cancer vaccines, looking forward to see the data in other tumour types @OncoAlert https://t.co/SBGq9djNGK Positive
Martín Angel Presidential symposium 1️⃣!! Interpath-001: adjuvant INT (intismeram) plus pembro impact in RFS & DMFS for stage II-IV resectable melanoma #ESMO26 @ProfGLongMIA @myESMO #personalizedmedicine https://t.co/G5Pf70eb1x Neutral
Shilpa Gupta Practice-changing at #ESMO26 Presidential @ProfGLongMIA INTerpath-001: personalized mRNA neoantigen Tx (intismeran) + pembro vs pembro alone in resected stage IIB–IV melanoma (n=1,137) RFS HR 0.58, 2-yr RFS 82% vs 70%
DMFS HR 0.62, 2-yr DMFS 89% vs 80% It's the 1st phase 3 win for an individualized cancer vaccine against an active IO control. OS is pending, but the adjuvant melanoma bar just moved. Kudos to the entire team! Moving moment as @ProfGLongMIA paid tribute to Dr. Jeff Weber, who designed this trial and enrolled patients until his passing. Jeff was a dear friend and my colleague at @MoffittNews and today's results are his legacy 💙 Bladder next: INTerpath-005 in MIUC, look forward to seeing the data in future! Positive
Tian Zhang, MD, MHS, FASCO (@tiansterzhangmd.bsky) with 1st neoantigen vaccine intismeran w pembro vs placebo w pembro, increased recurrent free & metastasis free survival in resected melanoma. Congrats to the teams!! @oncoalert @myESMO #ESMO26 https://t.co/2orLB7ug7y Neutral
Renee Maria Saliby INTerpath-001 - the result of decades of scientific advances and research led to this moment! And brilliant delivery by @ProfGLongMIA Personalized mRNA vaccines + Pembro as adjuvant trt improve RFS for pts with resects IIB-IV Melanoma!! Important points: Tox: a significant number of adverse events occurred BEFORE the vaccine was started Access: the vaccines was given globally #ESMO26 @OncoAlert Positive
David H Aggen, MD PhD There is clear additive activity with a personalized mRNA vaccine with intismeran autogene with pembrolizumab in melanoma where dual PD1 failed before. Presented by @ProfGLongMIA - I hope the same will come in the future for RCC #ESMO26 #Oncoalert https://t.co/Owe1QY5Uuh Positive
Shilpa Gupta #ESMO26 @myESMO Presidential session presentation by session @ProfGLongMIA INTerpath-001: intismeran + pembro vs pembro in resected stage IIB–IV melanoma (n=1,137) RFS HR 0.58, 2-yr RFS 82% vs 70%
DMFS HR 0.62, 2-yr DMFS 89% vs 80% 1st phase 3 win for an individualized cancer vaccine against an active IO control. OS is pending, but the adjuvant melanoma bar just moved! Moving moment as @ProfGLongMIA paid tribute to Dr. Jeff Weber, who designed this trial and enrolled patients until his passing. Jeff was a dear friend and my colleague at @MoffittNews and today's results are his legacy 💙 Bladder next: INTerpath-005 in MIUC, look forward to seeing the data in future! Positive
Daniel Heng #INTerpath001 amazing adjuvant melanoma trial of a personalized vaccine plus pembrolizumab. 17% of patients didn’t have sufficient tumor sample to create the neoantigen vaccine. DFS highly positive and OS immature. @oncoalert #ESMO26 excited to see other tumor data coming soon! https://t.co/VyUKabIWE2 Positive
Gaia Griguolo First positive trial with individualized neoantigen therapy! Adding intismeran (personalized mRNA vaccine) to pembro improves RFS and DMFS in stage IIB/IIC, III, or IV resected melanoma Opening the door to this approach across different solid tumors! @OncoAlert #Esmo26 https://t.co/lcNNegQ5S0 Neutral
Shankar Siva #ESMO26 Interpath-01; 🚨addition of individual tumour directed mRNA vaccine intismeran n=1137 patient phIII trial in resected #melanoma to pembro anti-PD1. ⬇️ risk of distant mets or death by 38%. Similar G3-5 TRAEs similar ~14%. OS not mature. 💥A new era in personalised mRNA therapy? Neutral
Fernanda G. Herrera Welcome INTERpath-001 first mRNA vaccine for melanoma treatment with no potentiation of Pembro AE https://t.co/ZKEYemE2k2 Neutral
Ana I. Velázquez Mañana, MD, MSc, FASCO INTerpath-001 adjuvant Intismeran Autogene + Pembro vs Pembro for resected stage IIB-IV #Melanoma Impressive RFS and distant metastasis free survival improvement with a truly personalized and neoantigen-driven approach @ProfGLongMIA #ESMO26 @myESMO https://t.co/NQ1xb6krW8 Positive
Alfredo Addeo MD Balanced discussion by prof Svane of the phase III INTerpath-001 trial at #ESMO26. Personalized cancer vaccines represent a major step forward, but: 🔹 Will the RFS benefit translate into improved OS? 🔹 Where should adjuvant vaccination fit alongside neoadjuvant ipilimumab/nivolumab? 🔹 Who benefits most? Predictive biomarkers remain urgently needed. 🔹 Manufacturing complexity, treatment delays, costs and access are major challenges. 👏 Compelling data and a milestone for personalized oncology, but clinical positioning and real-world feasibility will be crucial! #ESMOAmbassador #ESMO26 #Melanoma #CancerVaccin Positive
Abeid Athman (Omar). In INTerpath-001, the combination of adjuvant Intismeran plus pembro is superior to pembro alone in resected melanoma mproves RFS in ITT 70% vs 82.2% HR 0.58 #ESMO2026 @darioT_ @myESMO @DrChoueiri @FAndreMD @OncoAlert https://t.co/lKvGZajEEZ Neutral
Alan Tan Georgina Long presented INTerpath-001 at #ESMO26: intismeran + pembrolizumab vs placebo + pembrolizumab as adjuvant therapy for resected melanoma. It met the primary RFS endpoint (42% reduction in risk of recurrence or death) and the key secondary DMFS endpoint (38% reduction). OS is still immature, and follow-up is ongoing. Neutral
Dr. Antonio Calles 🫁🚭 🧬 Personalized mRNA vaccines work‼️ 📈 INTERPATH-001 met its primary endpoint in resected melanoma patients, paving the way to other tumor types and combinations, including lung 🫁 #cancer 🚀 🌓 One small step for a vaccine, one giant leap for personalized medicine. #ESMO26 @myesmo Neutral
Clara Steiner When urologists are paying attention to Melanoma trials: exciting times for personalized cancer vaccines with the data from INTERPATH-001 excellently presented by @ProfGLongMIA at #ESMO2026! Curious for what’s to come in GU! https://t.co/DvwMBcBTMB Positive
Oriol Mirallas MD 🔥 Presidential Symposium I #ESMO26 INTerpath-001: double-blind phase 3 study of intismeran (mRNA vaccine) + pembro as adjuvant therapy for resected stage IIB–IV #melanoma ✔️ RFS 82.2 vs 70% HR 0.58 ✔️ DMFS 88.5 vs 80.2% HR 0.62 ☣️ No increased risk of toxicity in the combination ✅🧫 mRNA Vaccine in adjuvant melanoma treatment together with anti-PD1 @OncoAlert @myESMO @ASCO @_SEOM @UTMDAnderson @brunolarvol 👇🏽👇🏽 Positive
José Márcio Barros de Figueiredo MD, MSc #ESMO26 | LBA1 – INTerpath-001 ✅ First positive Phase 3 of individualized mRNA neoantigen therapy in adjuvant melanoma Intismeran autogene + pembrolizumab vs pembrolizumab alone (Resected stage IIB–IV | N=1,137 | median FU 24.6 mo) ✅ RFS: HR 0.58 (0.45–0.75) | p<0.001 → 24-mo RFS 82.2% vs 70.0% ✅ DMFS: HR 0.62 (0.45–0.85) | p=0.002 → 24-mo DMFS 88.5% vs 80.2% ✅ Benefit across most subgroups ✅ Manageable safety (no potentiation of pembro AEs) ✅ OS still immature New benchmark for adjuvant melanoma. Presented by Georgina V. Long #ESMO26 #Melanoma #mRNA #INTerpath001 @myESMO @OncoAlert Neutral
Prof. Dr. Ahmet Dirican ESMO 2026 | Personalized mRNA Cancer Vaccines Deliver Phase III Success! INTerpath-001: Intismeran + pembrolizumab in resected high-risk melanoma. • RFS: HR 0.58 (42% risk reduction) • 24-month RFS: 82.2% vs 70.0% (+12.2%) • DMFS: HR 0.62 (38% risk reduction) 3 Key Takeaways: 1. Personalized neoantigen vaccines have demonstrated clinically meaningful Phase III efficacy. 2. No major increase in severe treatment-related toxicity, but overall survival data remain immature. 3. Predictive biomarkers, ctDNA/MRD, and optimal sequencing versus neoadjuvant immunotherapy are the next critical questions. A major milestone for personalized oncology. #ESMO26 @myesmo @oncodaily @OncoAlert #CancerVaccines #Melanoma Positive
Peter Grell MD Phase 3 results from the INTerpath-001 trial confirm that the individualized mRNA vaccine plus pembrolizumab significantly improves outcomes in adjuvant treatment of malignant melanoma. The era of mRNA vaccines in oncology has officially begun!👏 #ESMO26! https://t.co/BO9n6VKQpp Positive
Kevin Tay Surgeon's view: they want different things from the operation. Neoadjuvant pembro treats the disease before it comes out. The vaccine is built from the tumour after it's out. INTerpath-001 enrolled patients with no prior systemic therapy, so it doesn't answer the "both" question. Neutral
Michiel Strijbos One Patient. One Tumor. One mRNA Vaccine. 🧬💉
INTErpath-001: Cancer’s custom nightmare just arrived. Ready? 🚀 Neutral
Kevin Tay Merck and Moderna's personalised mRNA melanoma vaccine (intismeran) plus pembrolizumab cut recurrence or death by 42% vs pembrolizumab alone in INTerpath-001: 1,137 patients, completely resected stage IIB–IV. 2-year recurrence-free 82.2% vs 70.0%. Overall survival not mature yet. The detail surgeons should notice: each vaccine is built from that patient's own resected tumour, coding up to 34 neoantigens. So the operation is no longer just the end of the cancer pathway. It's the first step in making the drug. How we handle the specimen, whether there's enough tissue, how fast it reaches sequencing: all of that now sits inside the treatment. Neutral