Unresectable Stage III EGFR NSCLC - AstraZeneca
Discover KOL Sentiment on LAURA →Design - Phase 3 osimertinib vs placebo as consolidation after definitive chemoradiotherapy, unresectable stage III EGFR-mutated NSCLC (NCT03521154).
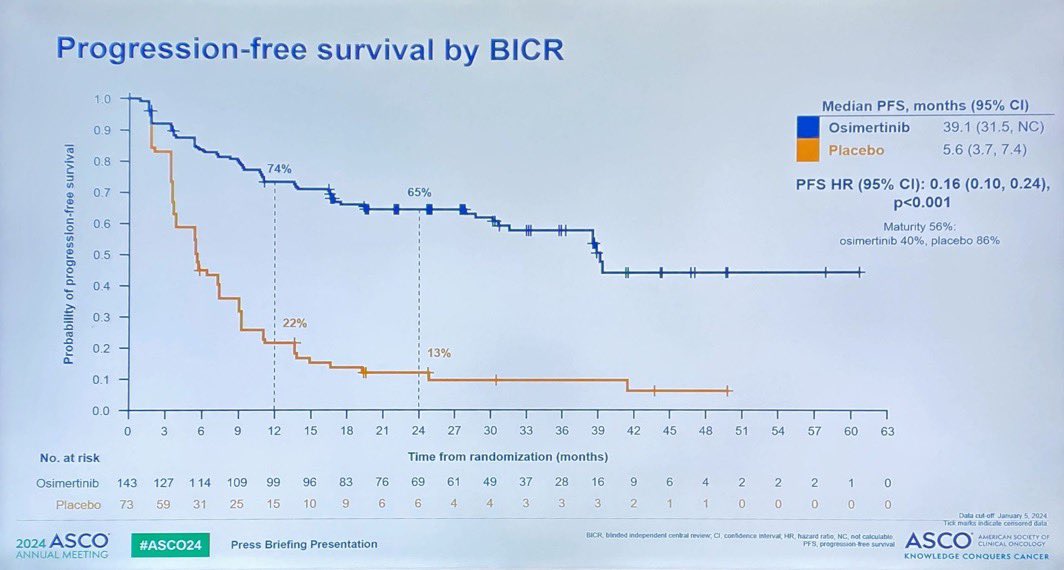
PFS (primary) - Median 39.1 vs 5.6 mo, HR 0.16 - an 84% reduction in risk of progression or death.
OS - Immature; interim trend favors osimertinib (median 58.8 vs 54.1 mo, HR 0.67) with high placebo-to-osimertinib crossover (78-80%).
Safety - Grade 3+ AEs 35% vs 12%; ILD/pneumonitis (incl. radiation pneumonitis) 56% vs 38%, mostly Grade 1-2, one fatal case (0.7%).
Regulatory - FDA approved September 2024.
Sponsor / drug - AstraZeneca; osimertinib (Tagrisso).
Compiled and reviewed by the KOL Pulse research team, led by Brian Shields, Founder, KOL Pulse. Last updated July 21, 2026.








Top 10 by impressions - click to view on X
#LungSeries: w/ @BalazsHalmosMD we 🗣️ the SoC for mNSCLC w/🎯mutation in 1L (Osi, Ami, Alectinib, Lorlatinib, et al) Full discussion: - - - Also on the “Oncology...

LAURA passes the "truck test" to a rousing ovation at #ASCO24 plenary session, with osimertinib given to patients with locally advanced unresectable stage III EGFRmut NSCLC...
Laura curves . Incredible. HR of 0.16 . 39. 1 months vs 5.6 months. With almost 80 % Cross over. Definitely practice changing . @DrRiyazShah @OncBrothers @OncoAlert...
Impressive increase in PFS with consolidation osimertinib after CRT for pts w unresectable stage III lung cancer. Crossover on progression 82% higher than in most other studies. OS far from mature....

LIFETIME osimertinib after a treatment with curative intent? In pts with EGFRmut stage III NSCLC, chemo-radiotherapy can CURE pts. Were pts in LAURA properly staged by petscan/brain RMI? Why not...
Overheard at Best of #ASCO24 Albuquerque: “Wait. Are you that doctor that dances while giving updates on lung cancer?” Why yes, that’s me 😂
IT DOESN’T MATTER IF YOU CALL IT ADJUVANT OR CONSOLIDATION, USE YOUR BEST SYSTEMIC TREATMENT AFTER DEFINITIVE TREATMENT FOR EGFR M+ LUNG CANCER (AND PROBABLY ALK AND RET+)!

🔥🚨Hot off the press. Press Release by @AstraZeneca. #LAURA Phase III trial of #Osimertinib vs placebo after chemoradiotherapy for pts with unresectable...
With news of the positive results from LAURA (consolidation osimertinib for stage III #EGFR NSCLC post chemoradiation), how would you approach a similar setting today: unresectable...

80% is false. Crossover to OSI was only given to 50/66
75% of patients
I guess the other 25% of patients didn't deserve the best care?
Paper also doesn't say if OSI was the next initial therapy or given later @Timothee_MD #asco24 #asco2024.

LAURA is a landmark Phase III, double-blind, placebo-controlled trial that established consolidation osimertinib (Tagrisso) as the new standard of care for patients with unresectable stage III EGFR-mutant NSCLC who have not progressed during or after definitive chemoradiation therapy. The trial randomized 216 patients across 17 countries in a 2:1 ratio to receive osimertinib 80 mg daily or placebo until disease progression. LAURA is the first phase 3 study to assess a targeted agent following chemoradiotherapy in unresectable stage III NSCLC, filling a critical treatment gap where durvalumab (PACIFIC) showed inconclusive efficacy in the small EGFR-mutant subset.
On September 25, 2024, the FDA approved osimertinib (Tagrisso) for unresectable stage III EGFR-mutant NSCLC after chemoradiation — the first targeted therapy in this setting. EMA (CHMP) followed in November 2024. Details in the FDA Approval section.
Consolidation osimertinib reduced new brain lesions (8% vs 29%) and improved CNS progression-free survival (HR 0.17), with fewer distant metastases than placebo (Annals of Oncology 2024). A presented analysis also examined outcomes by baseline PET staging — a central point in the KOL staging debate below.
Annals of Oncology 2024 (CNS efficacy analysis) →Updated OS showed a favorable trend — HR 0.67 (95% CI 0.40–1.14) — but remained immature at ~31% maturity and not statistically significant, with around 80% of placebo-arm patients who progressed receiving a third-generation EGFR TKI, mostly osimertinib (Ramalingam, ELCC 2025). The interim OS at the NEJM primary was HR 0.81 at ~20% maturity.
Ramalingam et al., J Thorac Oncol 2025 (ELCC LBA4) →A dedicated safety publication reported radiation pneumonitis in 48% vs 38% (predominantly grade 1–2, no grade 4–5; 87% of affected osimertinib patients continued or restarted treatment) and ILD in 8% vs 1%. Exposure-adjusted grade ≥3 AE rates were broadly comparable between arms; no new safety signals (Lung Cancer 2026).
Kato et al., Lung Cancer 2026 (safety analysis) →From Dr. Giannis Mountzios's post on Dr. Ramalingam's ELCC 2026 presentation: in the subgroup of patients who had a baseline PET scan, the PFS hazard ratio was similar to the full trial population (“0.24 vs 0.17”) — speaking directly to the staging questions raised after the plenary — with significant crossover to osimertinib among post-progression treatments.
Dr. Mountzios on X, March 2026 →Phase III, international, double-blind, 2:1 randomized, placebo-controlled trial in patients with unresectable stage III EGFR-mutant (exon 19 deletion or L858R) NSCLC who completed definitive platinum-based concurrent or sequential chemoradiation therapy without disease progression. EGFR mutations identified by central or local certified testing. Randomization stratified by CRT type (concurrent vs sequential), tumor staging (IIIA vs IIIB/IIIC), and China cohort.
Adults (18+ years, 20+ in Japan) with locally advanced, unresectable stage III NSCLC harboring EGFR exon 19 deletions or L858R mutations, WHO performance status 0-1, who completed at least 2 cycles or 5 weekly doses of platinum-based chemotherapy with radiation (54-66 Gy) within 6 weeks prior to randomization. Excluded patients with history of ILD, symptomatic pneumonitis following CRT, or prior EGFR TKI therapy.
Osimertinib 80 mg orally once daily versus placebo, continued until disease progression by BICR (RECIST 1.1), unacceptable toxicity, or other discontinuation criteria. Open-label osimertinib crossover offered to placebo patients upon progression.
Primary endpoint: progression-free survival (PFS) assessed by blinded independent central review (BICR) per RECIST 1.1. Key secondary endpoints: overall survival (OS) and CNS progression-free survival by BICR. Additional secondary endpoints: objective response rate (ORR), duration of response (DoR), time to first subsequent treatment (TFST), second PFS (PFS2), time to second subsequent treatment (TSST), safety, and tolerability.
Osimertinib demonstrated a profound PFS benefit versus placebo. Median PFS was 39.1 months (95% CI: 31.5-NE) with osimertinib versus 5.6 months (95% CI: 3.7-7.4) with placebo, with a hazard ratio of 0.16 (95% CI: 0.10-0.24; p<0.001), representing an 84% reduction in risk of disease progression or death. PFS rates at 12 and 24 months were 74% and 65% with osimertinib versus 22% and 13% with placebo. Investigator-assessed PFS was consistent (HR 0.19; 95% CI: 0.12-0.29). Benefit was observed across all prespecified subgroups.
Interim OS data at 20% maturity showed a non-significant trend favoring osimertinib: 36-month OS rates of 84% vs 74% (HR 0.81; 95% CI: 0.42-1.56; p=0.53). Updated OS analysis at 31% maturity (ELCC 2025) showed median OS of 58.8 months vs 54.1 months (HR 0.67; 95% CI: 0.40-1.14; p=0.140), with 48-month OS rates of 70% vs 52%. Notably, 78-80% of placebo patients crossed over to receive osimertinib upon progression, confounding OS interpretation. Final OS analysis planned at 60% maturity.
Grade 3+ adverse events occurred in 35% of osimertinib patients vs 12% with placebo. ILD/pneumonitis (including radiation pneumonitis) occurred in 56% of osimertinib patients vs 38% placebo; majority were Grade 1-2, with Grade 3 in 3.5% and one fatal case (0.7%). Radiation pneumonitis specifically occurred in 48.3% vs 38.4%. ILD or ILD-like reactions reported in 7.7% vs 1.4%. Permanent discontinuation due to AEs was 8.4%; dose interruptions in 42.0%; dose reductions in 4.9%. Most common AEs: radiation pneumonitis (48.3%), diarrhea (35.7%), rash (35.7%), paronychia (23.1%).
LAURA established osimertinib as the new standard of care (NCCN Category 1) for unresectable stage III EGFR-mutant NSCLC after CRT, replacing durvalumab consolidation for this molecular subgroup. Key clinical debates include: (1) the unusually low 5.6-month placebo PFS suggesting possible occult metastatic disease due to inadequate baseline staging; (2) immature OS data with high crossover rates (78-80%) complicating survival interpretation; (3) overtreatment concerns since 20-30% of stage III patients may be cured by CRT alone, raising questions about exposing all patients to indefinite osimertinib with its associated physical (35% Grade 3+ AEs) and financial toxicity (ICER $322,308/QALY in US); (4) alternative close-surveillance strategy advocated by some oncologists to spare cured patients from unnecessary treatment while catching recurrence early.
LAURA is a Phase 3 randomized trial (NCT03521154) of osimertinib (Tagrisso) versus placebo given as consolidation therapy after definitive chemoradiotherapy in patients with unresectable stage III EGFR-mutated (exon 19 deletion or L858R) non-small cell lung cancer. Progression-free survival was the primary endpoint.
Osimertinib produced a profound PFS benefit: median PFS was 39.1 months versus 5.6 months with placebo (HR 0.16; 95% CI 0.10-0.24; p<0.001), an 84% reduction in the risk of disease progression or death. The 12- and 24-month PFS rates were 74% and 65% with osimertinib versus much lower rates with placebo.
Overall survival data remain immature. An interim analysis showed a non-significant trend favoring osimertinib (median 58.8 vs 54.1 months, HR 0.67; p=0.140), but interpretation is complicated because 78-80% of placebo patients crossed over to receive osimertinib after progression. Longer follow-up is ongoing.
Yes. In September 2024 the FDA approved osimertinib (Tagrisso) for adults with locally advanced, unresectable stage III NSCLC whose disease has not progressed during or after platinum-based chemoradiation and whose tumors carry EGFR exon 19 deletions or exon 21 L858R mutations, based on LAURA.
Grade 3 or higher adverse events occurred in 35% of osimertinib patients versus 12% with placebo. Interstitial lung disease/pneumonitis (including radiation pneumonitis) was reported in 56% of osimertinib patients versus 38% with placebo; most cases were Grade 1-2, with Grade 3 in 3.5% and one fatal case (0.7%). Pneumonitis monitoring after chemoradiation is important.

































