LIVE #WCLC26 — live KOL coverage of the World Conference on Lung Cancer View Full Coverage →
KOL Pulse - Trial Profile

EVOKE-03 / KEYNOTE-D46 Trial

EVOKE-03 / KEYNOTE-D46 (one trial, two names; NCT05609968) was the Merck-sponsored phase III of Gilead's sacituzumab govitecan (Trodelvy) plus pembrolizumab versus pembrolizumab alone, first line in PD-L1 TPS ≥50% metastatic NSCLC (~620 patients). The trial was discontinued in June 2026 on the data monitoring committee's recommendation; the final data presented at WCLC 2026 showed PFS 11.8 vs 7.7 months (HR 0.81, not statistically significant), no OS benefit (HR 1.07), and substantially more toxicity.

Phase III · NCT05609968 · one trial, two names Sponsor: Merck · partner Gilead (Trodelvy) Trial DISCONTINUED June 8, 2026 (eDMC recommendation) 1L PD-L1 TPS ≥50% mNSCLC · ~620 patients WCLC 2026 final data

EVOKE-03 / KEYNOTE-D46 at a Glance

Design

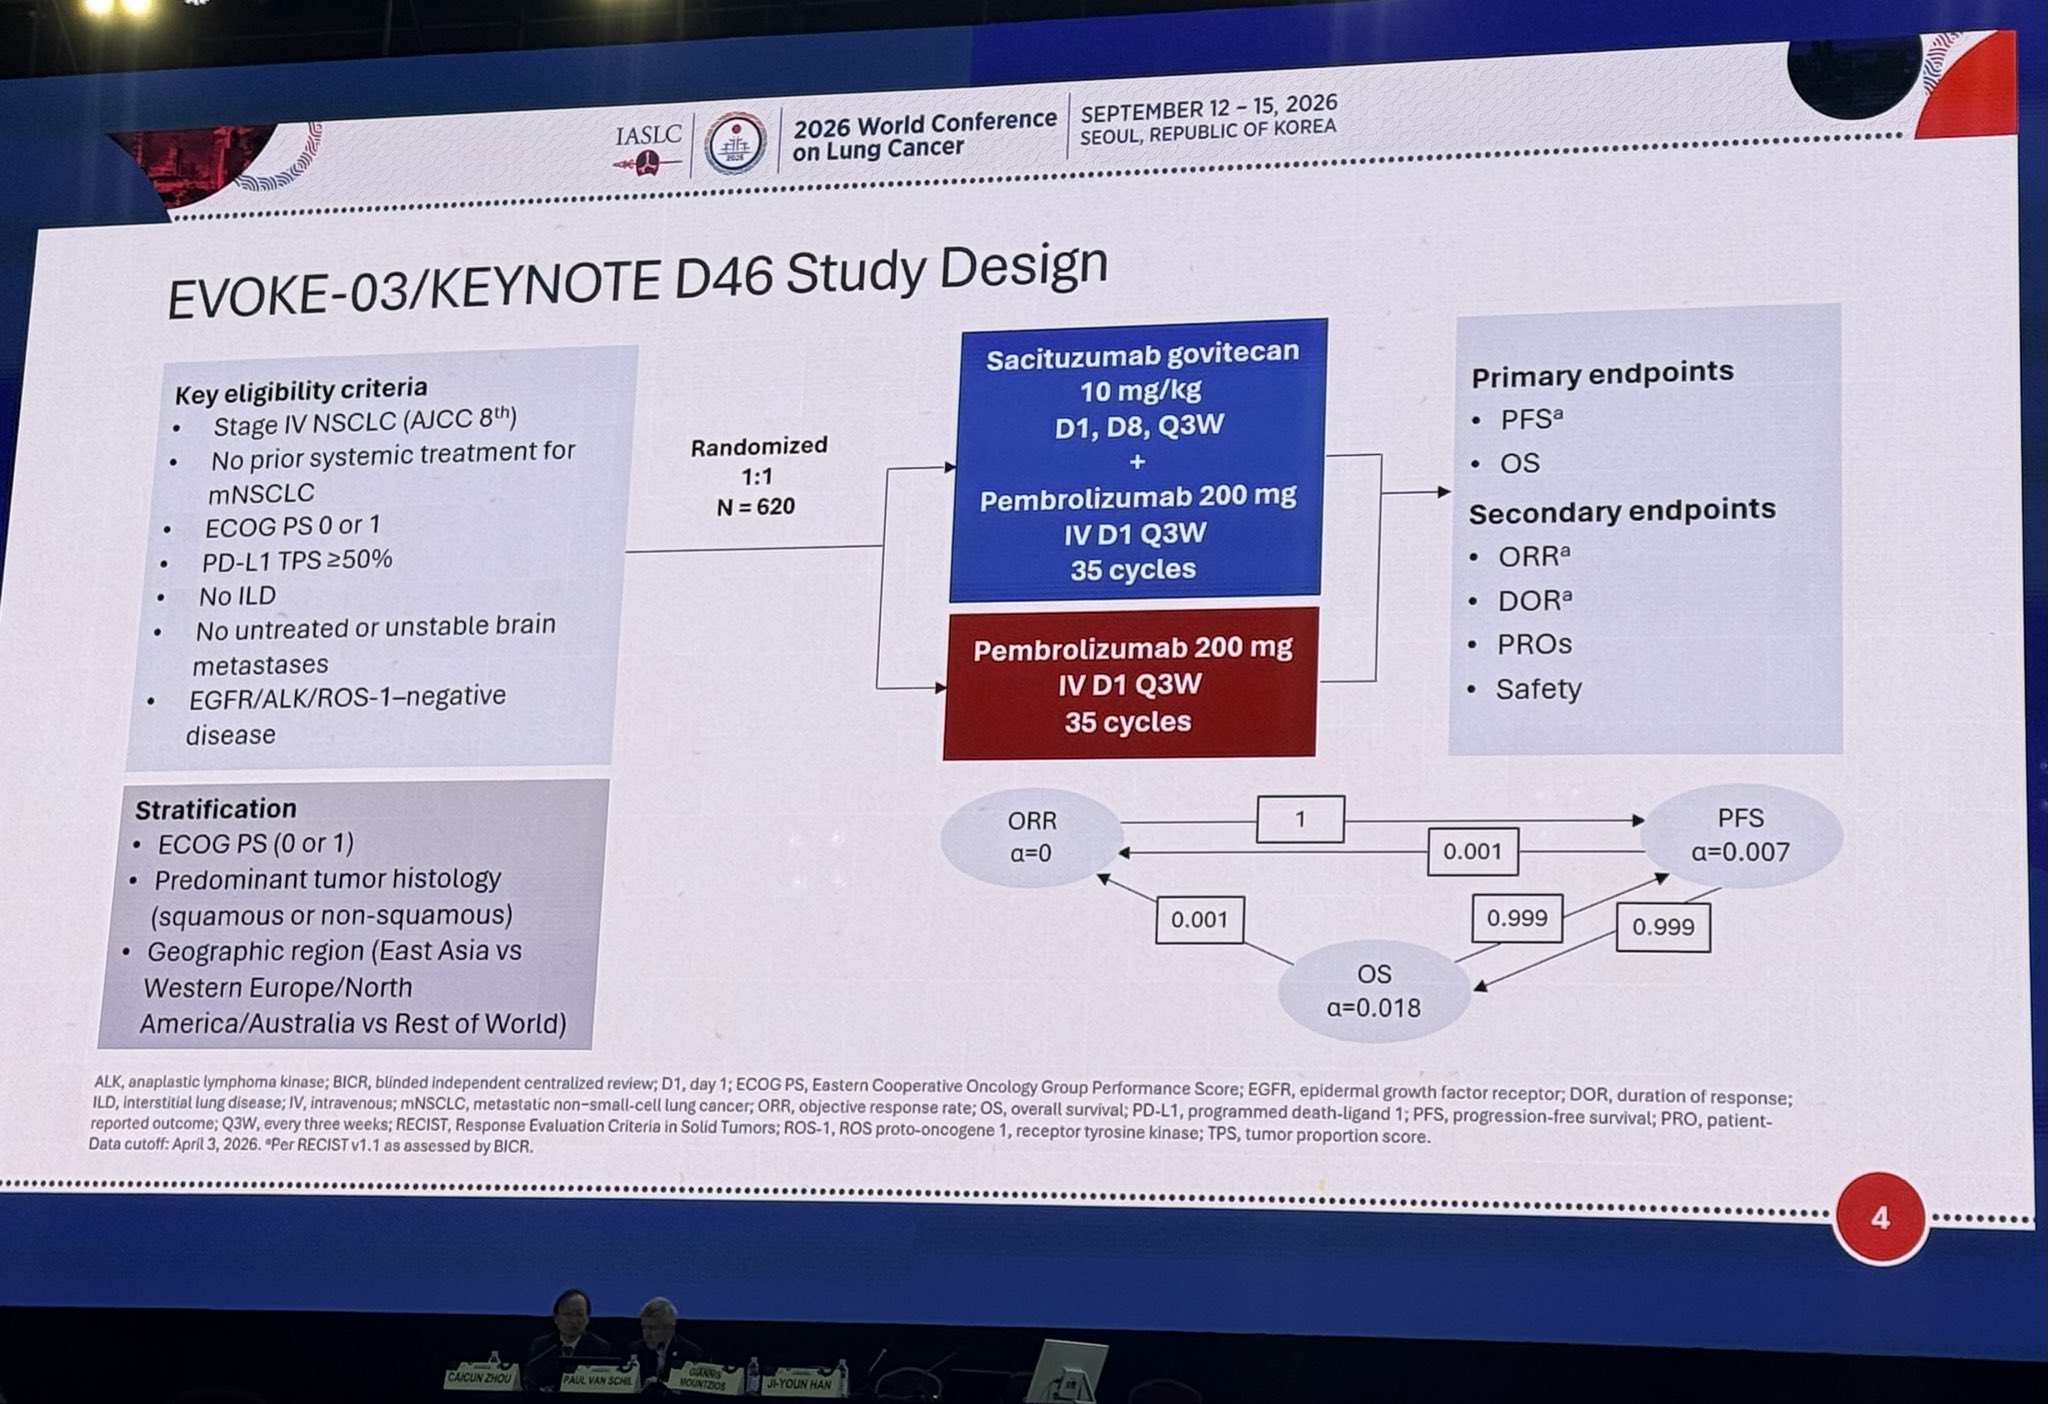
Global, open-label, randomized phase III: sacituzumab govitecan 10 mg/kg (days 1, 8 q3w) plus pembrolizumab vs pembrolizumab monotherapy, first line in metastatic NSCLC with PD-L1 TPS ≥50% and no EGFR/ALK/ROS1 alterations; ~620 patients; dual primary endpoints of BICR PFS and OS. EVOKE-03 (Gilead's name) and KEYNOTE-D46 (Merck's) are the same study. (Merck/Gilead press release; Targeted Oncology)

Efficacy

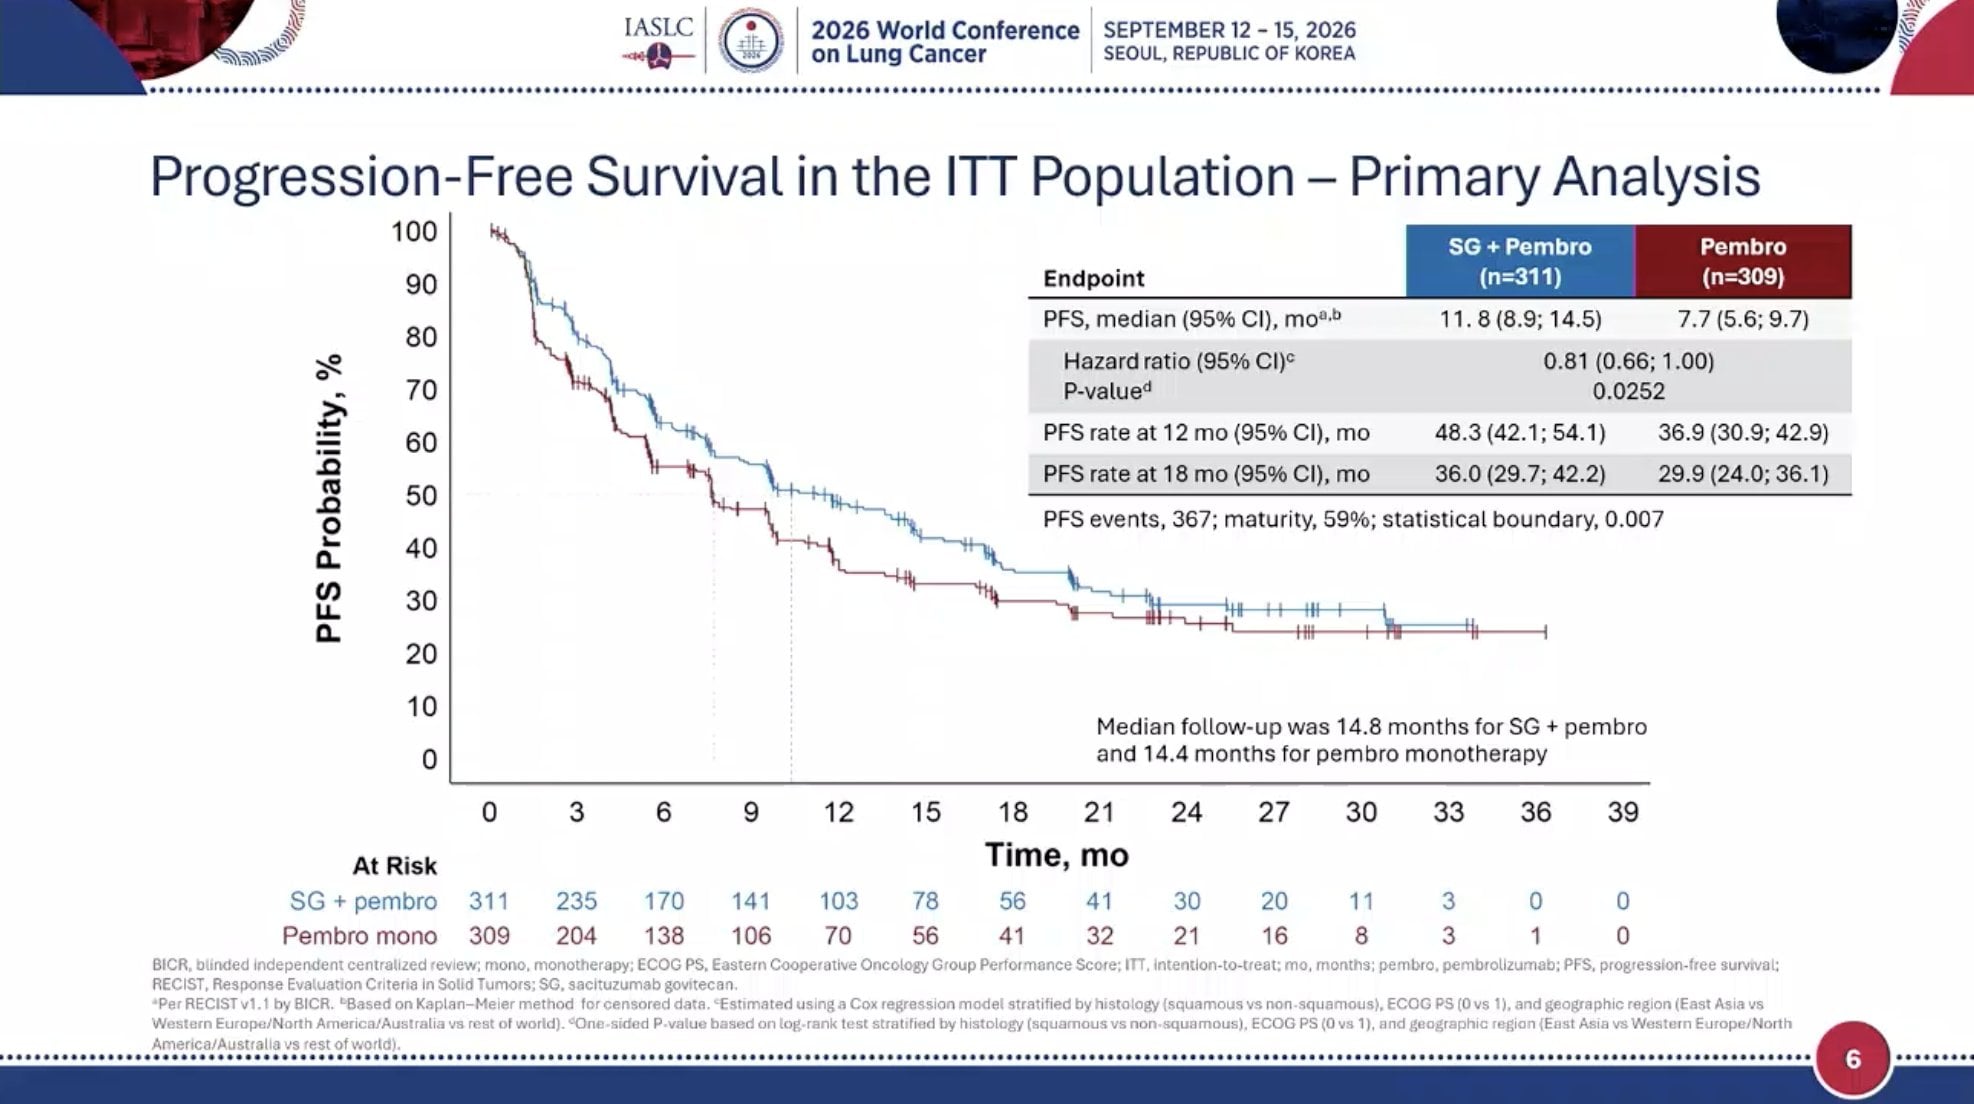
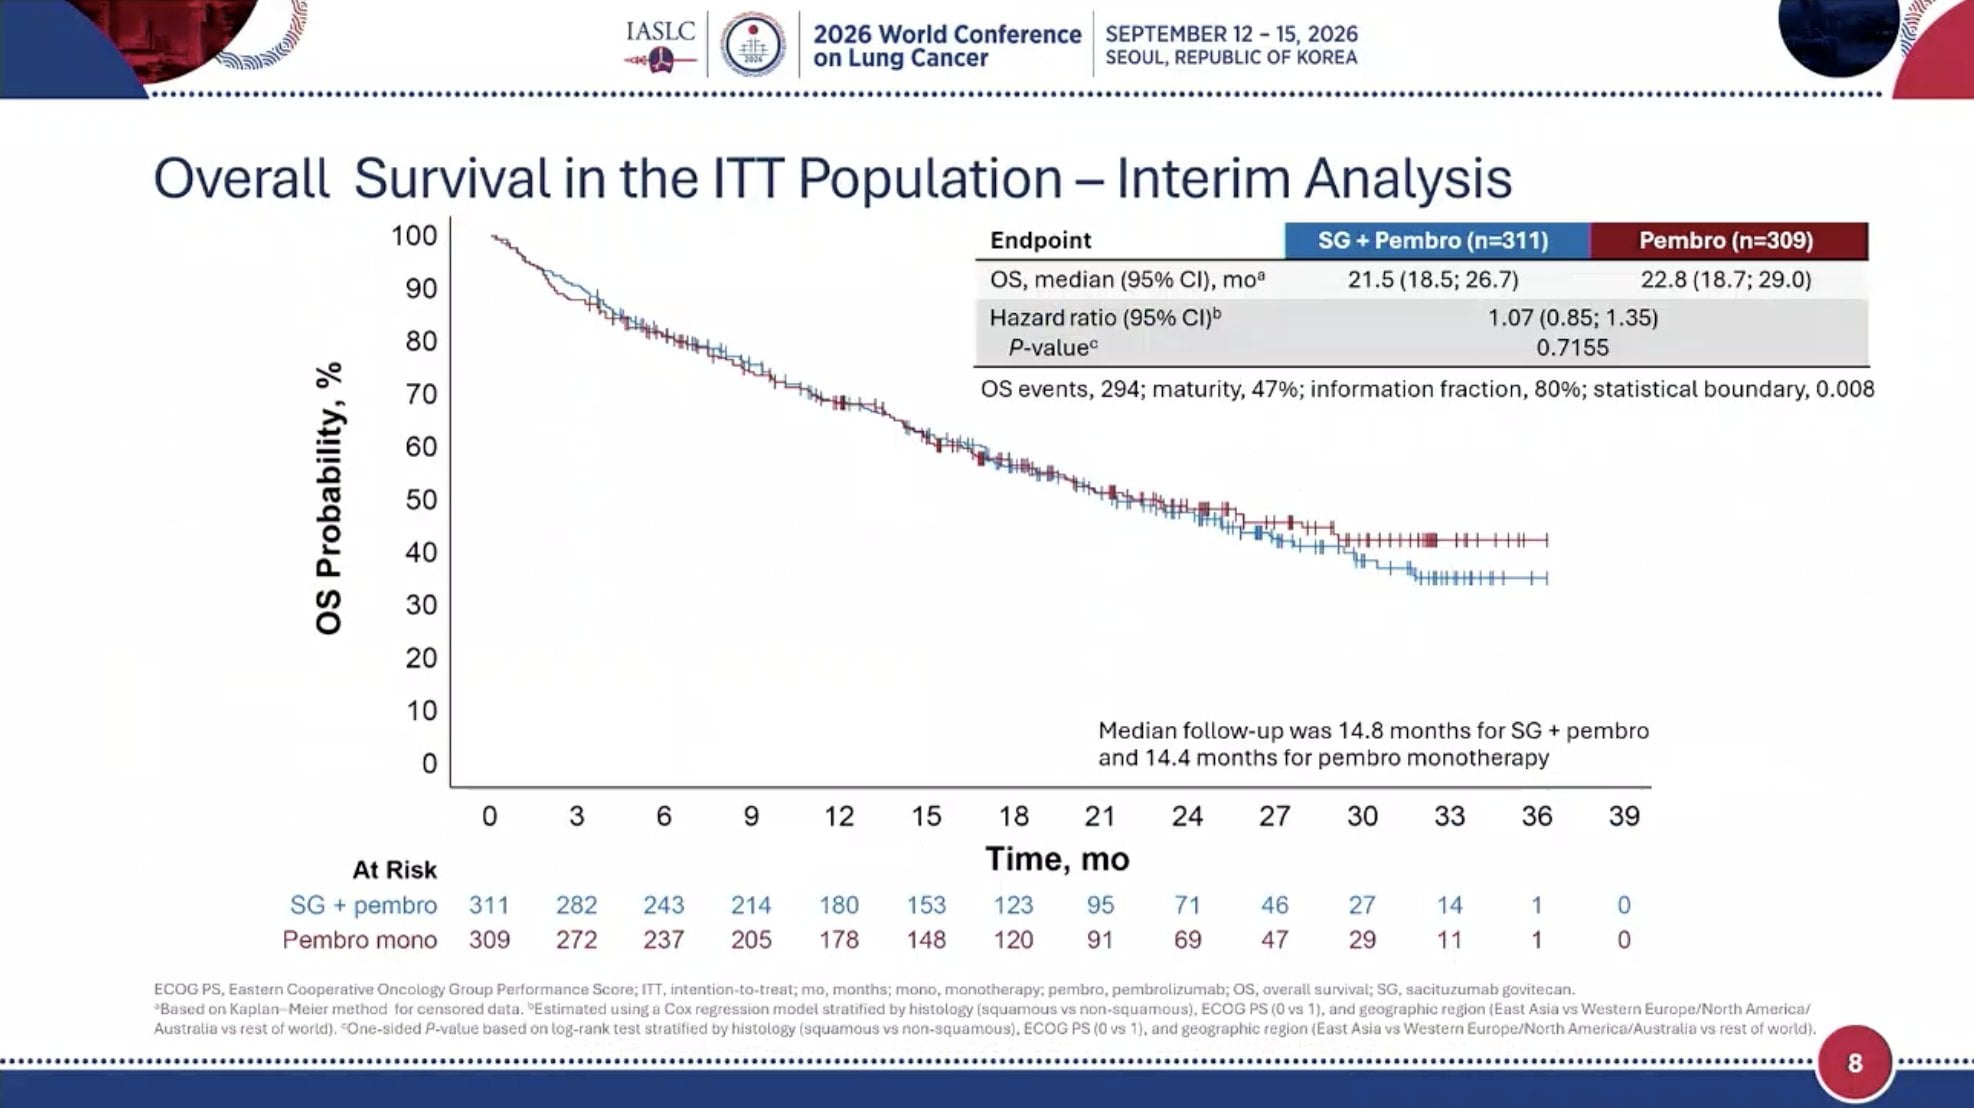
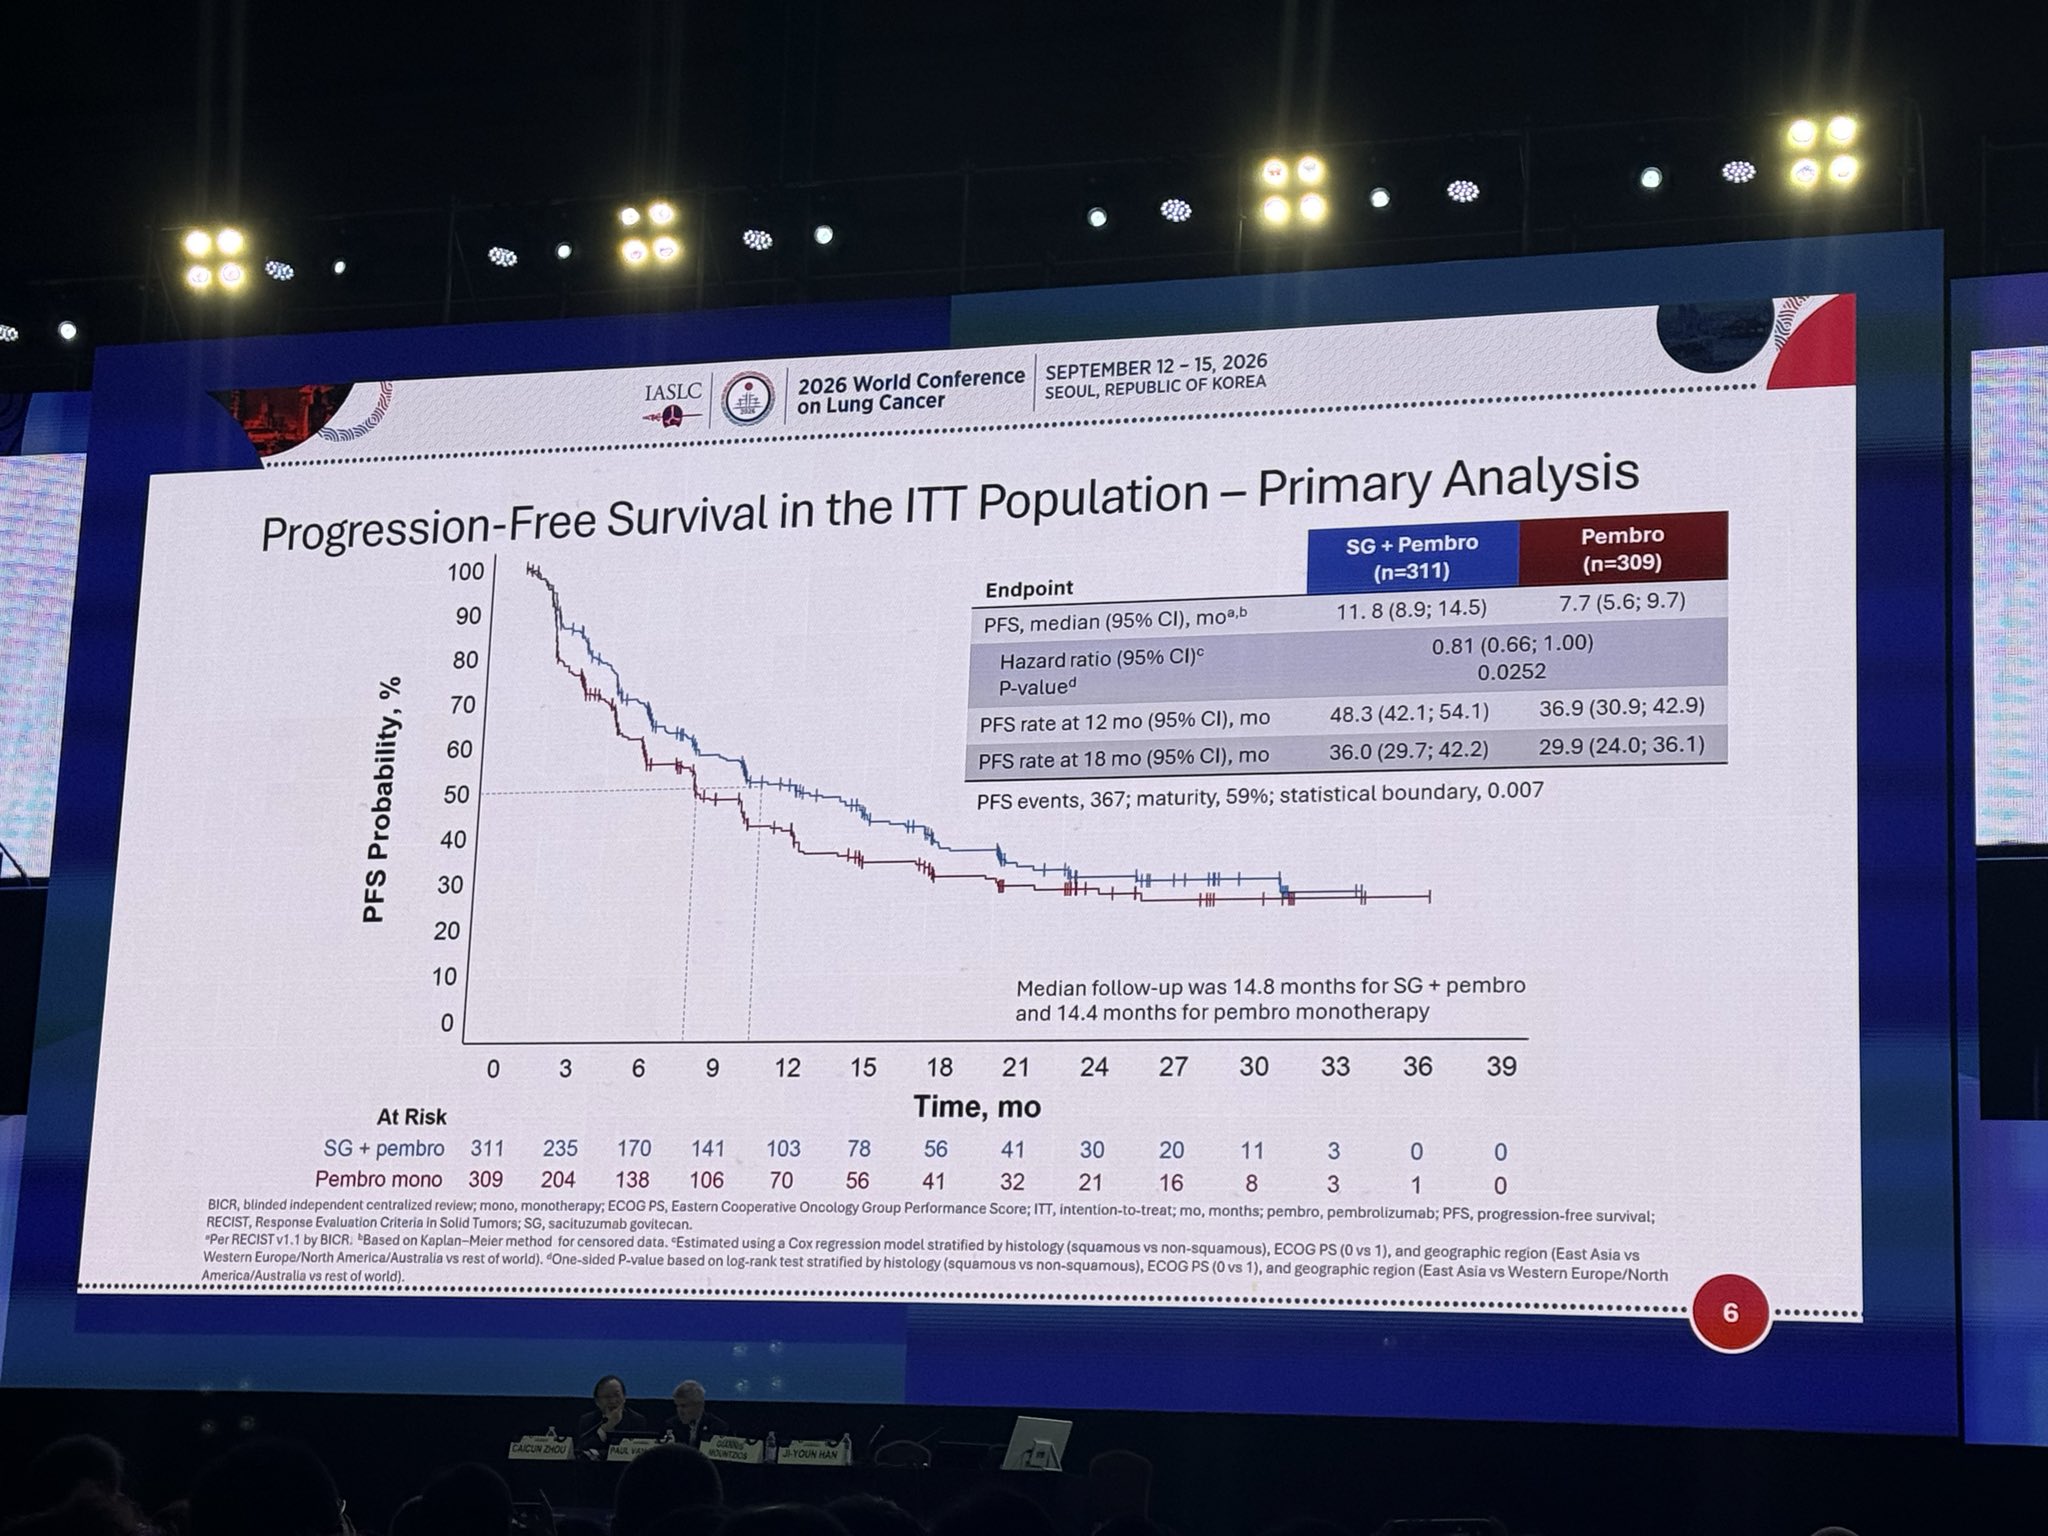
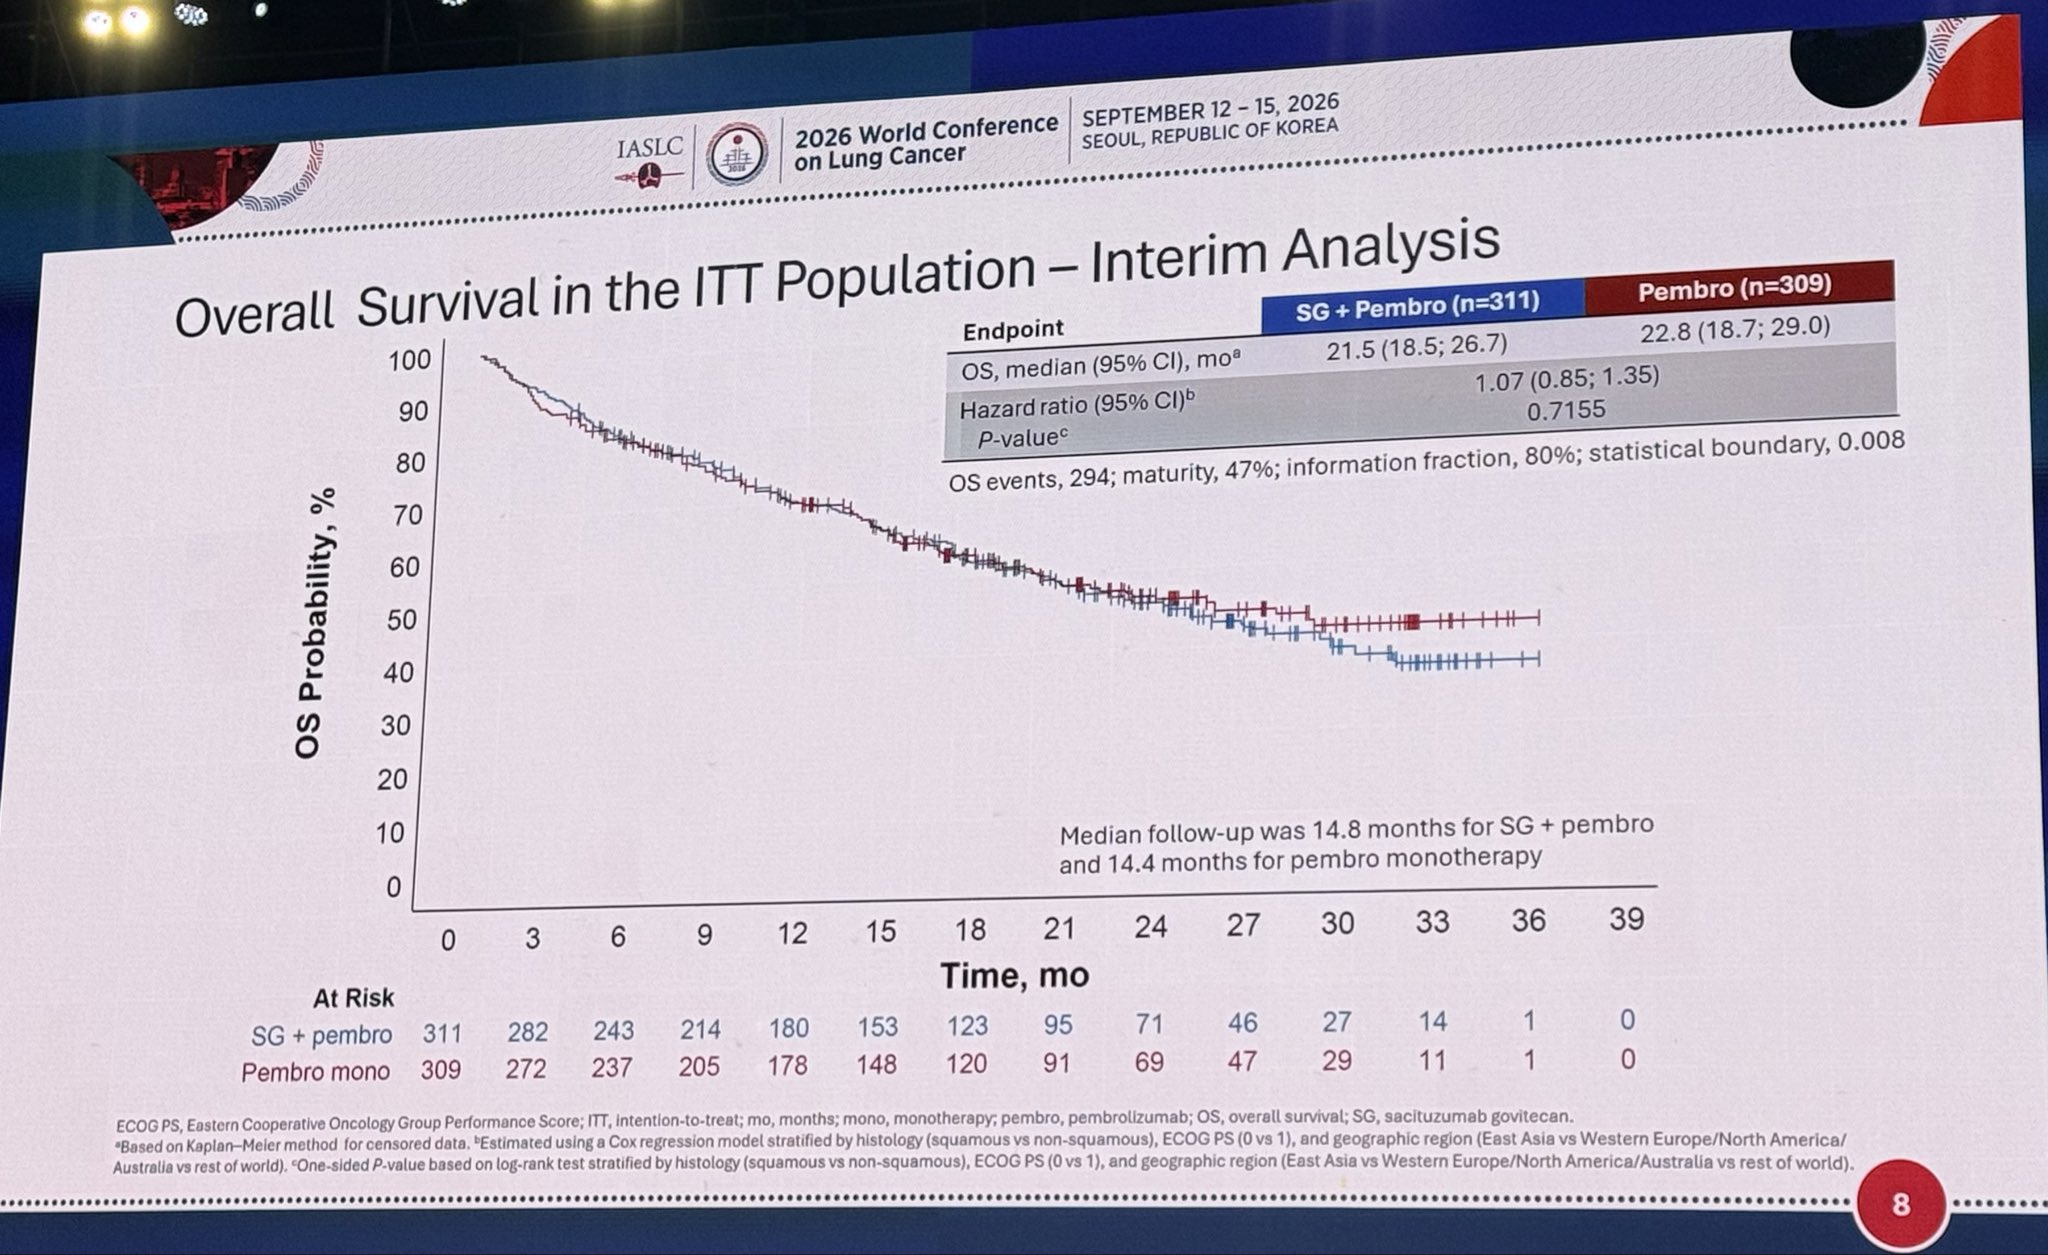
Final PFS analysis: 11.8 vs 7.7 months, HR 0.81 (95% CI 0.66–1.00 — the upper bound exactly 1.00) — a numerical difference that did not meet the threshold for statistical significance; interim OS analysis HR 1.07 (95% CI 0.85–1.35), median OS 21.5 vs 22.8 months numerically FAVORING pembrolizumab alone, with futility indicated. (WCLC 2026 presented slides via verbatim physician captures, incl. Liu on this page)

Safety

Grade ≥3 treatment-related AEs 55.7% vs 16.5% — substantially more toxicity for the combination against no significant efficacy gain. (WCLC 2026 presentation via verbatim KOL capture)

Status

Discontinued June 8, 2026 on the external data monitoring committee's recommendation after the prespecified final PFS and interim OS analyses. Trodelvy remains approved in its existing indications; this first-line NSCLC combination is not moving forward. (Merck/Gilead press release)

KOL pulse

Amol Akhade: “Evoke 03 . Important negative study.” Tom John: “A negative study with another ADC+Pembro as first line treatment. More tox with ADC.”

KOLs Discussing EVOKE-03 / KEYNOTE-D46

Giannis Mountzios
Giannis Mountzios
@g_mountzios
EVOKE-03 presenter (PL02.06)
Dr Riyaz Shah
Dr Riyaz Shah
@DrRiyazShah
397 impressions
MV Chandrakanth
MV Chandrakanth
@ChandrakanthMv
376 impressions
Uğur Özkerim
Uğur Özkerim
@UOzkerim
580 impressions
Diego A. Díaz-García
@diegoadiazg
361 impressions
Roberto Ferrara
Roberto Ferrara
@RobertoFerrara_
422 impressions
Tom Newsom-Davis
Tom Newsom-Davis
@tnewsomdavis
377 impressions
Miguel Gonzalez Velez, MD
@mgonzalezvelMD
145 impressions
Stephen V Liu, MD
Stephen V Liu, MD
@StephenVLiu
28,494 impressions
Prof Tom John
Prof Tom John
@TommyJohn00
11,332 impressions
Hidehito HORINOUCHI
Hidehito HORINOUCHI
@HHorinouchi
4,554 impressions
Dr Amol Akhade
Dr Amol Akhade
@SuyogCancer
1,750 impressions
Dr. Antonio Calles 🫁🚭
@Tony_Calles
1,116 impressions
Misty Dawn Shields
Misty Dawn Shields
@drshieldsmd
797 impressions

Key Slides & Data

Slides shared by global KOLs, mirrored to our CDN; slide text panels are verbatim Textract OCR.

Stephen V Liu, MD
Stephen V Liu, MD@StephenVLiu
EVOKE-03 / KEYNOTE-D46 — shared slides
WCLC 2026 · 2026-09-13
View on X
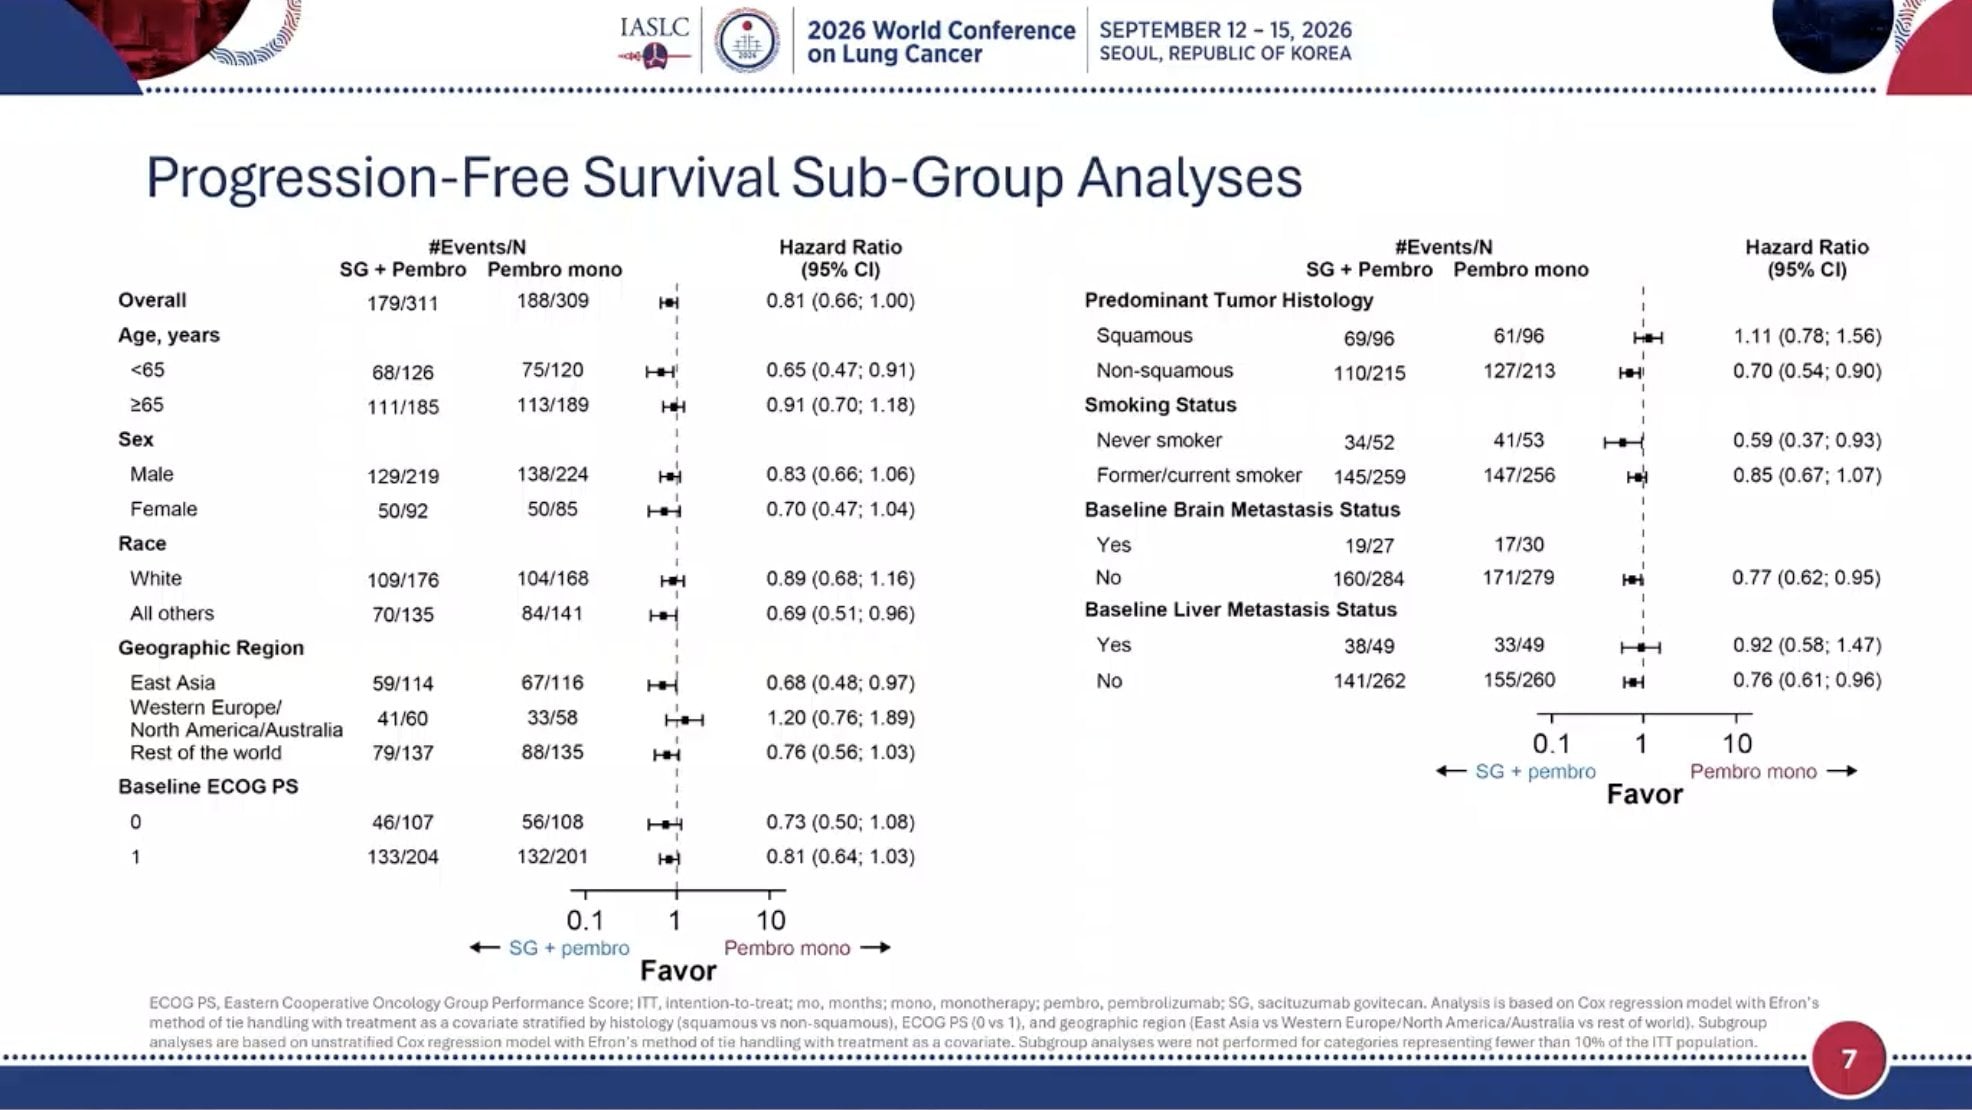
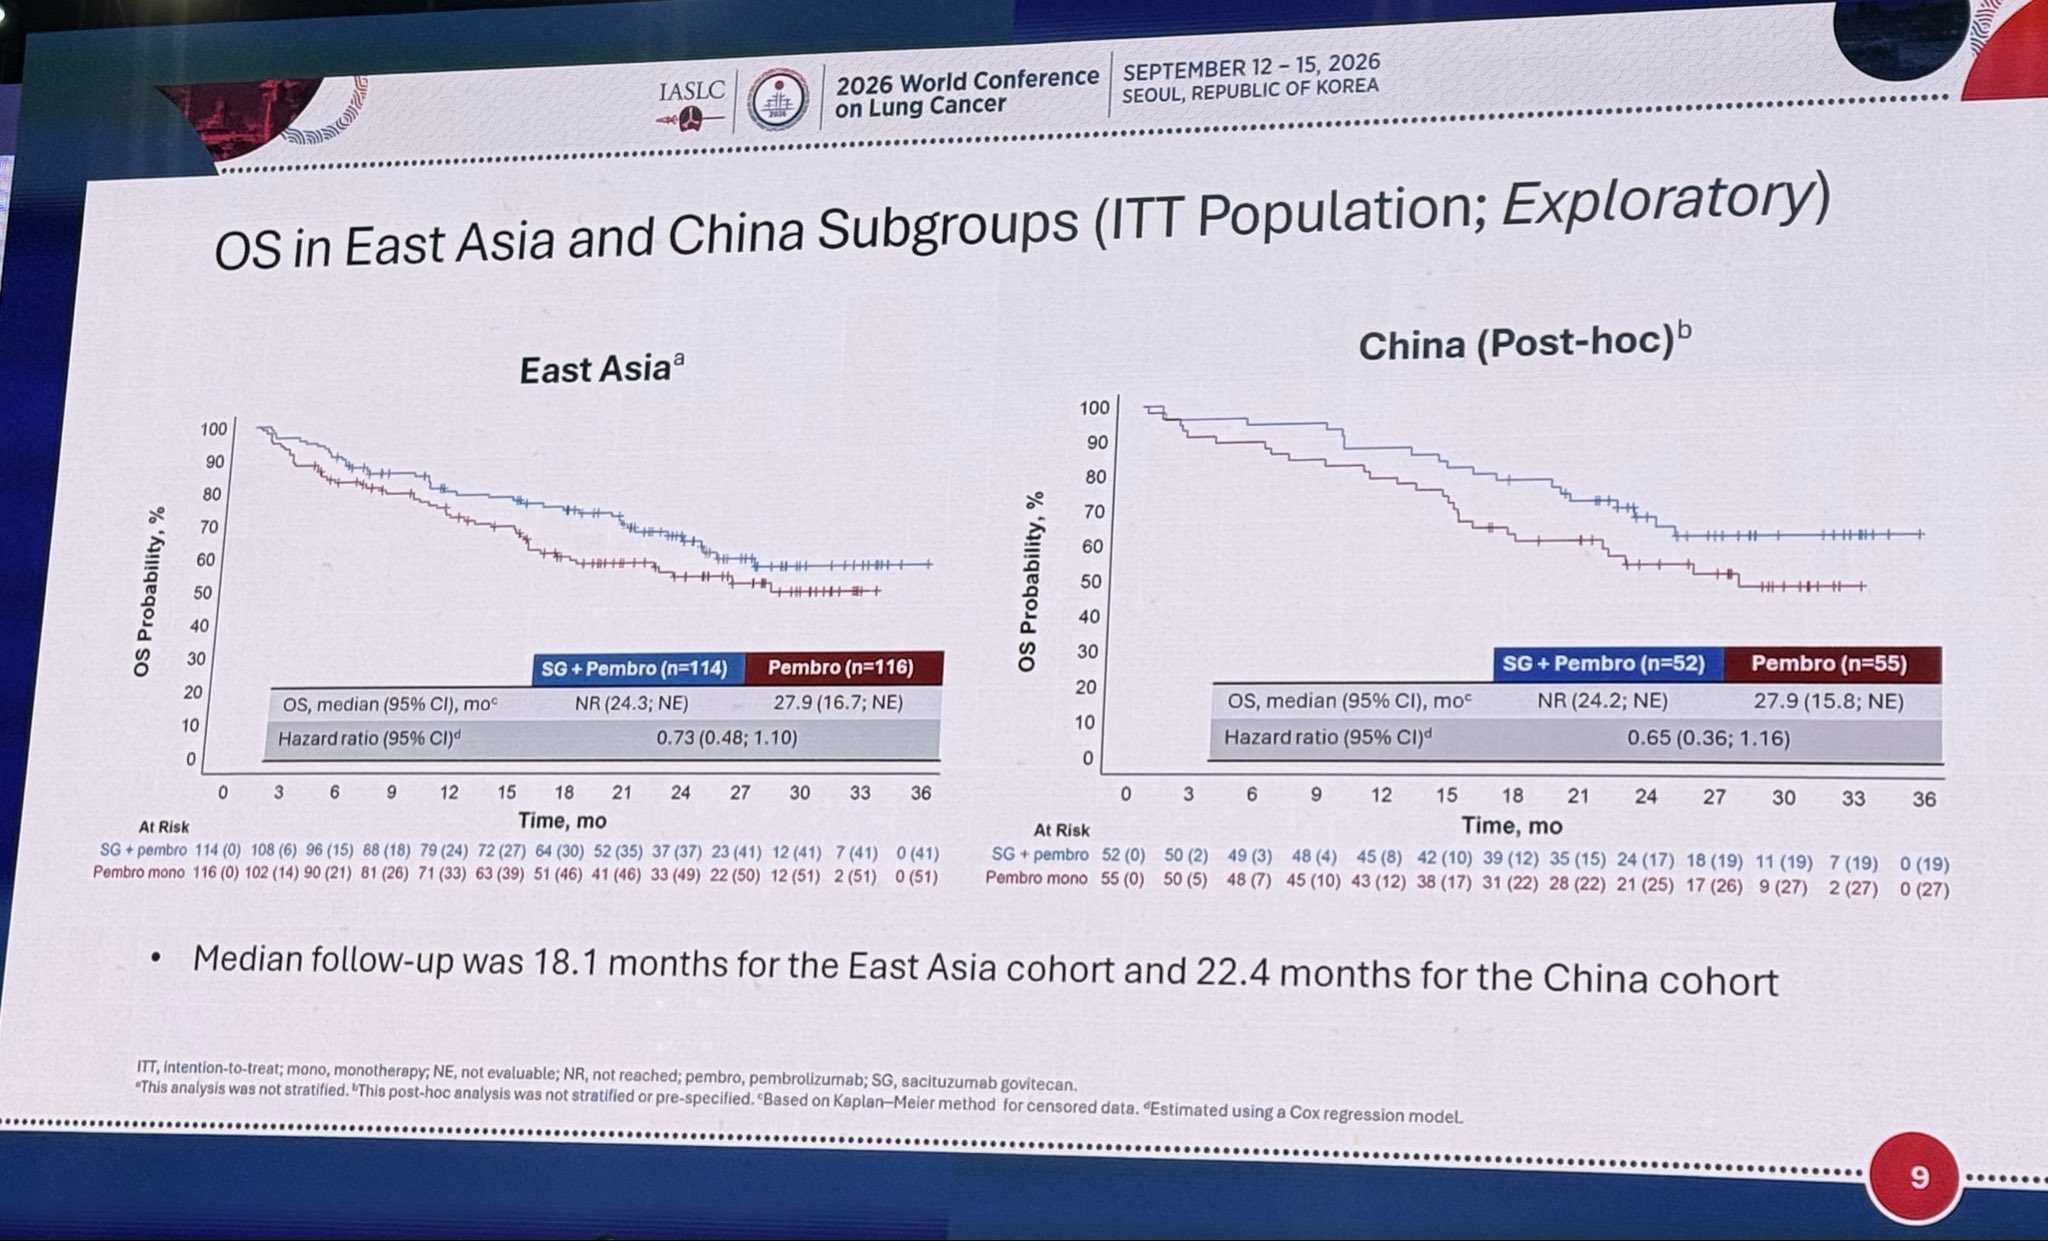
[Slide 1] IASLC 2026 World Conference SEPTEMBER 12 - 15, 2026 on Lung Cancer SEOUL, REPUBLIC OF KOREA Progression-Free Survival in the ITT Population - Primary Analysis 100 SG + Pembro Pembro 90 Endpoint (n=311) (n=309) PFS, median (95% CI), moᵃ.ᵇ 11. 8 (8.9; 14.5) 7.7 (5.6; 9.7) 80 Hazard ratio (95% CI)c 0.81 (0.66; 1.00) 70 P-valued 0.0252 PFS Probability, % 60 PFS rate at 12 mo (95% CI), mo 48.3 (42.1; 54.1) 36.9 (30.9; 42.9) PFS rate at 18 mo (95% CI), mo 36.0 (29.7; 42.2) 29.9 (24.0; 36.1) 50 PFS events, 367; maturity, 59%; statistical boundary, 0.007 40 30 20 10 Median follow-up was 14.8 months for SG + pembro 0 and 14.4 months for pembro monotherapy 0 3 6 9 12 15 18 21 24 27 30 33 36 39 At Risk Time, mo SG + pembro 311 235 170 141 103 78 56 41 30 20 11 3 0 0 Pembro mono 309 204 138 106 70 56 41 32 21 16 8 3 1 0 BICR, blinded independent centralized review; mono, monotherapy; ECOG PS, Eastern Cooperative Oncology Group Performance Score: ITT. intention-to-treat; mo, months; pembro, pembrolizumab; PFS, progression-free survival; RECIST, Response Evaluation Criteria in Solid Tumors; SG, sacituzumab govitecan. "Per RECIST v1.1 by BICR. Based on Kaplan-Meier method for censored data. Estimated using a Cox regression model stratified by histology (squamous VS non-squamous), ECOG PS (0 VS 1), and geographic region (East Asia VS Western Europe/North America/Australia vs rest of world). "One-sided P-value based on log-rank test stratified by histology (squamous VS non-squamous), ECOG PS (0 VS 1), and geographic region (East Asia VS Western Europe/North America/Australla VS rest of world). 6 --- [Slide 2] IASLC 2026 World Conference SEPTEMBER 12 - 15, 2026 on Lung Cancer SEOUL, REPUBLIC OF KOREA Progression-Free Survival Sub-Group Analyses #Events/N Hazard Ratio #Events/N Hazard Ratio SG + Pembro Pembro mono (95% CI) SG + Pembro Pembro mono (95% CI) Overall 179/311 188/309 0.81 (0.66; 1.00) Predominant Tumor Histology Age, years Squamous 69/96 61/96 1.11 (0.78; 1.56) <65 68/126 75/120 0.65 (0.47; 0.91) Non-squamous 110/215 127/213 0.70 (0.54; 0.90) ≥65 111/185 113/189 0.91 (0.70; 1.18) Smoking Status Sex Never smoker 34/52 41/53 0.59 (0.37; 0.93) Male 129/219 138/224 0.83 (0.66; 1.06) Former/current smoker 145/259 147/256 0.85 (0.67; 1.07) Female 50/92 50/85 0.70 (0.47; 1.04) Baseline Brain Metastasis Status Race Yes 19/27 17/30 White 109/176 104/168 0.89 (0.68; 1.16) No 160/284 171/279 0.77 (0.62; 0.95) All others 70/135 84/141 0.69 (0.51; 0.96) Baseline Liver Metastasis Status Geographic Region Yes 38/49 33/49 0.92 (0.58; 1.47) East Asia 59/114 67/116 0.68 (0.48; 0.97) No 141/262 155/260 0.76 (0.61; 0.96) Western Europe/ 41/60 33/58 North America/Australia 1.20 (0.76; 1.89) Rest of the world 79/137 88/135 0.76 (0.56; 1.03) 0.1 1 10 SG + pembro Pembro mono Baseline ECOG PS Favor 0 46/107 56/108 0.73 (0.50; 1.08) 1 133/204 132/201 0.81 (0.64; 1.03) 0.1 1 10 SG + pembro Pembro mono Favor ECOG PS, Eastern Cooperative Oncology Group Performance Score; ITT, intention-to-treat; mo, months; mono, monotherapy; pembro, pembrolizumab; SG, sacituzumab govitecan. Analysis is based on Cox regression model with Efron's method of tie handling with treatment as a covariate stratified by histology (squamous VS non-squamous), ECOG PS (0 VS 1), and geographic region (East Asia VS Western Europe/North America/Australia vs rest of world). Subgroup analyses are based on unstratified Cox regression model with Efron's method of tie handling with treatment as a covariate. Subgroup analyses were not performed for categories representing fewer than 10% of the ITT population. 7 --- [Slide 3] IASLC 2026 World Conference SEPTEMBER 12 - 15, 2026 on Lung Cancer SEOUL, REPUBLIC OF KOREA Overall Survival in the ITT Population - Interim Analysis 100 Endpoint SG + Pembro (n=311) Pembro (n=309) 90 OS, median (95% CI), moᵃ 21.5 (18.5; 26.7) 22.8 (18.7; 29.0) Hazard ratio (95% CI)ᵇ 1.07 (0.85; 1.35) 80 P-valueᶜ 0.7155 70 OS events, 294; maturity, 47%; information fraction, 80%; statistical boundary, 0.008 OS Probability, % 60 50 40 30 20 10 Median follow-up was 14.8 months for SG + pembro 0 and 14.4 months for pembro monotherapy 0 3 6 9 12 15 18 21 24 27 30 33 36 39 At Risk Time, mo SG + pembro 311 282 243 214 180 153 123 95 71 46 27 14 1 0 Pembro mono 309 272 237 205 178 148 120 91 69 47 29 11 1 0 ECOG PS, Eastern Cooperative Oncology Group Performance Score; ITT, intention-to-treat; mo, months; mono, monotherapy; pembro, pembrolizumab; OS, overall survival; SG, sacituzumab govitecan. Based on Kaplan-Meier method for censored data. Estimated using a Cox regression model stratified by histology (squamous VS non-squamous), ECOG PS (0 VS 1), and geographic region (East Asia VS Western Europe/North America/ Australia VS rest of world). One-sided P-value based on log-rank test stratified by histology (squamous VS non-squamous). ECOG PS (0 VS 1). and geographic region (East Asia VS Western Europe/North America/Australia vs rest of world). 8
Prof Tom John
Prof Tom John@TommyJohn00
EVOKE-03 / KEYNOTE-D46 — shared slides
WCLC 2026 · 2026-09-13
View on X
[Slide 1] and IASLC 2026 World Conference SEPTEMBER 12 - 15, 2026 E on Lung Cancer SEOUL, REPUBLIC OF KOREA EVOKE-03/KEYNOTE D46 Study Design Key eligibility criteria Sacituzumab govitecan Stage IV NSCLC (AJCC 8th) 10 mg/kg Primary endpoints No prior systemic treatment for Randomized D1, D8, Q3W PFSᵃ mNSCLC 1:1 + OS ECOG PS 0 or 1 N = 620 Pembrolizumab 200 mg PD-L1 TPS ≥50% IV D1 Q3W Secondary endpoints No ILD 35 cycles ORRᵃ No untreated or unstable brain DORᵃ metastases Pembrolizumab 200 mg PROs EGFR/ALK/ROS-1-negative IV D1 Q3W Safety disease 35 cycles Stratification ORR 1 PFS ECOG PS (0 or 1) a=0 0.001 a=0.007 Predominant tumor histology (squamous or non-squamous) 0.001 0.999 0.999 Geographic region (East Asia VS OS Western Europe/North a=0.018 America/Australia VS Rest of World) ALK, anaplastic lymphoma kinase; BICR, blinded independent centralized review; D1, day 1; ECOG PS, Eastern Cooperative Oncology Group Performance Score; EGFR, epidermal growth factor receptor; DOR, duration of response; ILD, interstitial lung disease; IV, intravenous; mNSCLC, metastatic non-small-cell lung cancer; ORR, objective response rate; OS, overall survival; PD-L1, programmed death-ligand 1; PFS, progression-free survival; PRO, patient- reported outcome; Q3W, every three weeks; RECIST, Response Evaluation Criteria in Solid Tumors; ROS-1, ROS proto-oncogene 1, receptor tyrosine kinase; TPS, tumor proportion score. Data cutoff: April 3, 2026. *Per RECIST v1.1 as assessed by BICR. 4 --- [Slide 2] IASLC 2026 World Conference SEPTEMBER 12 - 15, 2026 on Lung Cancer SEOUL, REPUBLIC OF KOREA Progression-Free Survival in the ITT Population - Primary Analysis 100 SG + Pembro Pembro 90 Endpoint (n=311) (n=309) 80 PFS, median (95% CI), moa,b 11. 8 (8.9; 14.5) 7.7 (5.6; 9.7) Hazard ratio (95% CI)c 0.81 (0.66; 1.00) 70 P-valued 0.0252 PFS Probability, % 60 PFS rate at 12 mo (95% CI), mo 48.3 (42.1; 54.1) 36.9 (30.9; 42.9) PFS rate at 18 mo (95% CI), mo 36.0 (29.7; 42.2) 50 29.9 (24.0; 36.1) PFS events, 367; maturity, 59%; statistical boundary, 0.007 40 30 20 10 Median follow-up was 14.8 months for SG + pembro 0 and 14.4 months for pembro monotherapy 0 3 6 9 12 15 18 21 24 27 30 33 36 39 At Risk Time, mo SG + pembro 311 235 170 141 103 78 56 41 30 20 11 3 0 0 Pembro mono 309 204 138 106 70 56 41 32 21 16 8 3 1 0 BICR, blinded independent centralized review; mono, monotherapy; ECOG PS, Eastern Cooperative Oncology Group Performance Score; ITT, intention-to-treat; mo, months; pembro, pembrolizumab; PFS, progression-free survival; RECIST, Response Evaluation Criteria in Solid Tumors; SG, sacituzumab govitecan. "Per RECIST v1.1 by BICR. Based on Kaplan-Meier method for censored data. Estimated using a Cox regression model stratified by histology (squamous VS non-squamous), ECOG PS (0 VS 1), and geographic region (East Asia VS Western Europe/North America/Australia VS rest of world). "One-sided P-value based on log-rank test stratified by histology (squamous vs non-squamous), ECOG PS (0 VS 1), and geographic region (East Asia VS Western Europe/North America/Australia vs rest of world). 6 --- [Slide 3] and IASLC 2026 World Conference SEPTEMBER 12 - 15, 2026 on Lung Cancer SEOUL, REPUBLIC OF KOREA OS in East Asia and China Subgroups (ITT Population; Exploratory) East Asiaᵃ China (Post-hoc)b 100 100 90 90 80 80 70 70 OS Probability, % 60 os Probability, % 60 50 50 40 40 30 30 SG + Pembro (n=114) Pembro (n=116) SG + Pembro (n=52) Pembro (n=55) 20 20 OS, median (95% CI), moᶜ NR (24.3; NE) 27.9 (16.7; NE) OS, median (95% CI), moc NR (24.2; NE) 27.9 (15.8; NE) 10 10 Hazard ratio (95% CI) 0.73 (0.48; 1.10) Hazard ratio (95% CI)ᵈ 0.65 (0.36; 1.16) 0 0 0 3 6 9 12 15 18 21 24 27 30 33 36 0 3 6 9 12 15 18 21 24 27 30 33 36 At Risk Time, mo At Risk Time, mo SG + pembro 114 (0) 108 (6) 96 (15) 88 (18) 79 (24) 72 (27) 64 (30) 52 (35) 37 (37) 23 (41) 12 (41) 7 (41) 0 (41) SG + pembro 52 (0) 50 (2) 49 (3) 48 (4) 45 (8) 42 (10) 39 (12) 35 (15) 24 (17) 18 (19) 11 (19) 7 (19) 0 (19) Pembro mono 116 (0) 102 (14) 90 (21) 81 (26) 71 (33) 63 (39) 51 (46) 41 (46) 33 (49) 22 (50) 12 (51) 2 (51) 0 (51) Pembro mono 55 (0) 50 (5) 48 (7) 45 (10) 43 (12) 38 (17) 31 (22) 28 (22) 21 (25) 17 (26) 9 (27) 2 (27) 0 (27) Median follow-up was 18.1 months for the East Asia cohort and 22.4 months for the China cohort ITT, intention-to-treat; mono, monotherapy; NE, not evaluable; NR, not reached; pembro, pembrolizumab; SG, sacituzumab govitecan. "This analysis was not stratified. "This post-hoc analysis was not stratified or pre-specified. "Based on Kaplan-Meier method for censored data. "Estimated using a Cox regression model. o --- [Slide 4] 2020 and IASLC 2026 World Conference SEPTEMBER 12 - - 15, 2026 on Lung Cancer SEOUL, REPUBLIC OF KOREA Overall Survival in the ITT Population - Interim Analysis 100 Endpoint SG + Pembro (n=311) Pembro (n=309) OS, median (95% CI), moᵃ 21.5 (18.5; 26.7) 22.8 (18.7; 29.0) 90 Hazard ratio (95% CI)ᵇ 1.07 (0.85; 1.35) 80 P-valueᶜ 0.7155 OS events, 294; maturity, 47%; information fraction, 80%; statistical boundary, 0.008 70 os Probability, % 60 50 40 30 20 10 Median follow-up was 14.8 months for SG + pembro 0 and 14.4 months for pembro monotherapy 0 3 6 9 12 15 18 21 24 27 30 33 36 39 At Risk Time, mo SG + pembro 311 282 243 214 180 153 123 95 71 46 27 14 1 0 Pembro mono 309 272 237 205 178 148 120 91 69 47 29 11 1 0 ECOG PS, Eastern Cooperative Oncology Group Performance Score; ITT, intention-to-treat; mo, months; mono, monotherapy; pembro, pembrolizumab; OS, overall survival; SG, sacituzumab govitecan. "Based on Kaplan-Meier method for censored data. Estimated using a Cox regression model stratified by histology (squamous vs non-squamous), ECOG PS (0 VS 1), and geographic region (East Asia VS Western Europe/North America/ Australia VS rest of world). "One-sided P-value based on log-rank test stratified by histology (squamous VS non-squamous), ECOG PS (0 VS 1), and geographic region (East Asia vs Western Europe/North America/Australia vs rest of world). 8

What Physicians Said

Giannis Mountzios
Giannis Mountzios@g_mountzios

🌟 Truly honored that our work has been selected for presentation at the Presidential Symposium 1 of the World Lung Cancer Conference #WCLC26 in Seoul: ⏰ Sunday, 13 September 08:00-10:30 KST 🗒️ Presidential Symposium 1 📌 Plenary, Hall D2, 3F Primary analysis of the global, randomized phase III EVOKE-03/KEYNOTE D46 clinical trial on the combination of Sacituzumab Govitecan plus pembro vs pembro monotherapy in patients with advanced #NSCLC and high #PDL1 expression. Thank you @IASLC for selecting a negative (by press release) phase III trial for the Presidential Symposium, those data are important to be shared and communicated in detail, because they provide food for thought and can be hypothesis generating for future trials. Looking forward to the discussion that will follow, especially in he context of the Optitrop Lung 05 results. @IASLC @myESMO @lcsmchat @OncoAlert @OncBrothers @OncLive @PeerView @oncodaily @VJOncology @MedscapeOnc @LungCancerEu @YoungLungCancer @lcrf_org @LUNGevity @HeSMO_X @fairlifelcc @HenryDunantGR #IASLC #ThoracicMalignancy #WCLC26 https://t.co/pvnFKqNzXc

👀 4,3792026-08-20
Stephen V Liu, MD
Stephen V Liu, MD@StephenVLiu

Dr. @g_mountzios at #WCLC26 presents results of EVOKE-03 / KEYNOTE D46: phase III study of sacituzumab govitecan (Trop2 ADC) with pembro vs pembro alone in NSCLC with PD-L1 ≥50%. Median f/u 14.7m. https://t.co/U1jhvkkDXB

👀 4,9232026-09-13
Dr Riyaz Shah
Dr Riyaz Shah@DrRiyazShah

EVOKE-03/KEYNOTE D46; Sac-govitecan trop2ADC; P3RCT; high PDL1 (>50%) randomised to Pembro vs SG+ Pembro; n620; 4 month longer mPFS but HR not stat significant ; OS flat ; Interesting as suggests chemoIO might not beat IO alone in high PDL1 within a prospective RCT #WCLC26 https://t.co/v6BUMaBEWK

👀 3972026-09-13
MV Chandrakanth
MV Chandrakanth@ChandrakanthMv

EVOKE-03: More responses — but no survival gain? Phase III | 620 patients with untreated metastatic NSCLC, PD-L1 ≥50% SG + pembrolizumab vs pembrolizumab alone ORR: 56.6% vs 43.7% → more tumors responded PFS: 11.8 vs 7.7 months | HR 0.81 → numerical improvement, not statistically significant per prespecified boundary OS: 21.5 vs 22.8 months | HR 1.07 → no survival benefit Grade ≥3 TRAEs: 55.7% vs 16.5% → substantially more toxicity Non-squamous and East Asian subgroups showed interesting signals — hypothesis-generating, not practice-changing Take-home: More responses ≠ longer survival. Pembrolizumab remains a standard option in PD-L1-high, driver-negative NSCLC. Reference: Mountzios G et al. EVOKE-03/KEYNOTE-D46, PL02.06 | WCLC 2026 #MVOnco #WCLC2026 #EVOKE03 #NSCLC #LungCancer #Immunotherapy #TROP2

👀 3762026-09-13
Uğur Özkerim
Uğur Özkerim@UOzkerim

EVOKE-03/KEYNOTE-D46 at #WCLC26 In 1L metastatic NSCLC with PD-L1 TPS ≥50%, adding sacituzumab govitecan to pembrolizumab did not meet the primary PFS endpoint despite numerically longer PFS (11.8 vs 7.7 mo; HR 0.81). No OS benefit was observed at the interim analysis (HR 1.07). @OncoAlert @ManuelDomine @weoncologists @OpenMedKate @g_mountzios

👀 5802026-09-13
Diego A. Díaz-García
Diego A. Díaz-García@diegoadiazg

🫁 EVOKE-03: adding a Trop-2 ADC to pembrolizumab did not improve outcomes in PD-L1-high NSCLC. PFS: 11.8 vs 7.7 months, HR 0.81 OS: 21.5 vs 22.8 months ORR: 56.6% vs 43.7% Grade ≥3 TRAEs: 55.7% vs 16.5%. A negative phase III study despite higher response rates with the combination. #CánCare #NSCLC #LungCancer #ThoracicOncology #ADC #Immunotherapy #WCLC26 @IASLC

👀 3612026-09-13
Stephen V Liu, MD
Stephen V Liu, MD@StephenVLiu

As would be expected, much greater toxicity with sacituzumab govitecan + pembro arm vs pembro alone. With no PFS/OS signal and worse toxicity, this strategy fails in an unselected population. Other ADC trials in different PD-L1 subsets and exploring biomarkers pending. #WCLC26 https://t.co/jpwoUE29EB

👀 1,7542026-09-13
Roberto Ferrara
Roberto Ferrara@RobertoFerrara_

Evoke 03 Sacituzumab Gov+ Pembro no benefit in OS. In 2026 it's time to integrate other biomarkers different than high PD-L1 expression in clinical trials to test escalation strategies. PFS data in PD-L1 >90% curve will overlap? #WCLC2026 https://t.co/JecL0Y8IUy

👀 4222026-09-13
Tom Newsom-Davis
Tom Newsom-Davis@tnewsomdavis

EVOKE-03 Ph3, Saci-Gov+Pembro v Pembro 1L NSCLC PD-L1 >50% SG+Pembro: ❌🔼mPFS 11 v 7m, HR 0.81 (not sig) ❌No OS benefit ❓benefit in Asian & non-sq popn ❌🔼 Gr3+ TRAE 73 v 45% 🤔 Early Ph2 activity lost in Ph3 Post-hoc Asia data = limited value End of SG in NSCLC IMO #WCLC26 https://t.co/MW60DL1p0m

👀 3772026-09-13
Miguel Gonzalez Velez, MD
Miguel Gonzalez Velez, MD@mgonzalezvelMD

EVOKE-03/KND46 negative readout for a Sac-GT. Take: Dual primary endpoint, neither met. PFS numerically favored SG + pembro but wasn't statistically significant. Interim OS: 21.5 vs 22.8 mo, HR 1.07. ORR (55.6% vs 43.7%) and DCR (83.3% vs 73.1%) both favored the combo, but no PFS/OS. I think SG is a first-generation ADC with inferior efficacy and higher toxicity. Response rate gains without OS or durable PFS benefit in settings where pembrolizumab is good and safe as discussed by @Dr_R_Kurzrock @oncology_bg Interesting split by geography in Asia… #NSCLC #LCSM #WCLC26

👀 1452026-09-13
Stephen V Liu, MD
Stephen V Liu, MD@StephenVLiu

EVOKE-03 did not meet the primary endpoint. PFS 11.8 vs 7.7m, HR 0.81 but did not meet threshold for statistical significance. Consistent across subgroups. No difference in OS: 21.5 vs 22.8m, HR 1.07. #WCLC26 https://t.co/j3v6jr8N7H

👀 28,4942026-09-13
Prof Tom John
Prof Tom John@TommyJohn00

@g_mountzios presenting EVOKE-03. A negative study with another ADC+Pembro as first line treatment. More tox with ADC. The most interesting slide for me is the result based on region. Asian patients do better. Will this be the same for other studies too? #WCLC26 #LCSM https://t.co/wNtaXlRTBB

👀 11,3322026-09-13
Hidehito HORINOUCHI
Hidehito HORINOUCHI@HHorinouchi

🆙#WCLC26 #LCSM Plenary Session 🔥EVOKE-03/KEYNOTE D46: Primary Results from Phase 3: Sacituzumab Govitecan + Pembrolizumab in PD-L1 TPS ≥50% Metastatic NSCLC 🎙️ @g_mountzios 🎯PFS HR 0.81 (95% CI 0.66-1.00) 🎯OS HR 1.07 (95% 0.85-1.35) 🔢PL02.06 ☑️NCT05609968 🔗 https://t.co/JvkpEBLlSo @OncoAlert @Larvol @IASLC

👀 4,5542026-09-13
Dr Amol Akhade
Dr Amol Akhade@SuyogCancer

Evoke 03 . Important negative study. SG plus Pembrolizumab in 1st line NSCLC with PDL1 above 50 % @IASLC @StephenVLiu @DrRiyazShah @RManochakian @FordePatrick @PatelOncology https://t.co/PDuPiGhxX3

👀 1,7502026-09-13
Dr. Antonio Calles 🫁🚭
Dr. Antonio Calles 🫁🚭@Tony_Calles

EVOKE-03: SG + Pembro did not improve clinical outcomes over Pembro alone but with an increased rate of known side effects in patients with NSCLC and high PD-L1 expression (>50%) #WCLC26 #LCSM @IASLC https://t.co/zDPQEJIo1p

👀 1,1162026-09-13
Misty Dawn Shields
Misty Dawn Shields@drshieldsmd

Dr. Giannis Mountzios @g_mountzios presented at @IASLC #WCLC26 the EVOKE-03 Phase 3 study investigating sacituzumab govitecan (SG) + pembrolizumab vs pembrolizumab alone in PD-L1 >50% NSCLC. Unfortunately, while there was an improvement in PFS, ORR, and DCR, no significant improvement in OS was observed. Unclear what the rates of oncogenic drivers and co-alterations here were amongst the patients included in this study. Difficult to improve outcomes with adjunct therapies in PD-L1 high NSCLC. More research is needed for additional therapeutic targets in this patient population to improve outcomes and prevent recurrence/resistance. @LUNGevity @LauraAlderMD @lungoncdoc @BrunaPellini @RManochakian @StephenVLiu @FordePatrick @FSkoulidis

👀 7972026-09-13

About the EVOKE-03 / KEYNOTE-D46 Trial

EVOKE-03 / KEYNOTE-D46 asked whether adding a TROP2-directed ADC to pembrolizumab could beat pembrolizumab alone in the population where checkpoint monotherapy is already most active — PD-L1 TPS ≥50% first-line metastatic NSCLC. The answer was no: a numerical PFS edge that missed significance, an OS hazard ratio above 1 at the interim with futility indicated, and nearly 3.4× the severe treatment-related toxicity.

Physicians at WCLC 2026 read it as a class lesson rather than a molecule failure alone: several noted the mounting difficulty of improving on pembrolizumab monotherapy in PD-L1-high disease with ADC add-ons, with subgroup signals (non-squamous, East Asian patients) called hypothesis-generating at most.

Trial Methodology & Results

Study Design

Global, open-label, randomized 1:1 phase III; sacituzumab govitecan + pembrolizumab vs pembrolizumab; dual primary endpoints BICR PFS (RECIST v1.1) and OS. (Targeted Oncology; Merck/Gilead PR)

Population

Previously untreated metastatic NSCLC, PD-L1 TPS ≥50%, no sensitizing EGFR/ALK/ROS1 alterations; ~620 patients worldwide. (Merck/Gilead PR)

Outcome

Final PFS not significant (11.8 vs 7.7 mo, HR 0.81); interim OS HR 1.07 with futility; Grade ≥3 TRAEs 55.7% vs 16.5%. (WCLC 2026 presentation via verbatim KOL posts)

Status

Discontinued June 8, 2026 per eDMC recommendation; final data presented at WCLC 2026. (Merck/Gilead PR)

Final efficacy — endpoints not met

PFS was 11.8 versus 7.7 months, HR 0.81 with a 95% CI of 0.66–1.00 — the upper bound landing exactly on 1.00 — numerically longer with the combination but below the threshold for statistical significance under the trial's dual-primary design. The interim OS analysis showed HR 1.07 (95% CI 0.85–1.35) with median OS 21.5 versus 22.8 months — numerically favoring pembrolizumab alone — and futility for eventual OS superiority. (WCLC 2026 presented slides, via the verbatim physician captures on this page incl. Liu)

PFS HR 0.81 (NS) · OS HR 1.07
Source: WCLC 2026 presentation (verbatim KOL captures) ↗

Toxicity — the deciding margin

Grade ≥3 treatment-related adverse events occurred in 55.7% with the combination versus 16.5% with pembrolizumab alone — the toxicity cost that, against non-significant efficacy, ended the program in this setting. (WCLC 2026 presented slides via verbatim physician capture on the KOL Pulse conference page)

Gr≥3 TRAE 55.7% vs 16.5%
Source: Merck/Gilead June 8, 2026 update · WCLC 2026 data ↗

WCLC 2026: Live KOL Reaction

Physician posts about this trial captured live during the IASLC 2026 World Conference on Lung Cancer (Seoul, September 12–15). Quotes are verbatim; each card links to the original post. Last updated 2026-09-15.

Hidehito HORINOUCHI
Hidehito HORINOUCHI@HHorinouchi

🆙#WCLC26 #LCSM Plenary Session 🔥EVOKE-03/KEYNOTE D46: Primary Results from Phase 3: Sacituzumab Govitecan + Pembrolizumab in PD-L1 TPS ≥50% Metastatic NSCLC 🎙️ @g_mountzios 🔢PL02.06 ☑️NCT05609968 🔗 https://t.co/icbDk1Zjnh @OncoAlert @Larvol @IASLC https://t.co/pMAIqOHdqF https://t.co/4ShK6WS6fB

7.3K impressions6 likes2026-08-20
Masahiro TORASAWA, MD. PhD.
Masahiro TORASAWA, MD. PhD.@M_Torasawa

1/2 🚨 Several #WCLC26 Presidential Symposium trials already have topline press releases 👀 🙌 ARTEMIS-008 | Risvutatug Rezetecan • Phase 3 in relapsed SCLC • Met the primary endpoint of OS vs. topotecan • Statistically significant and clinically meaningful OS benefit! 🔗 https://t.co/WavE0BuSbb 🤦‍♂️ EVOKE-03 / KEYNOTE-D46 | Sacituzumab Govitecan + pembrolizumab • 1L PD-L1 TPS ≥50% metastatic NSCLC • PFS improvement did not reach statistical significance • Study was discontinued after an eDMC review 🔗 https://t.co/t0DcvrKJmz

4.5K impressions13 likes2026-08-20
Dr Amol Akhade
Dr Amol Akhade@SuyogCancer

We learn from every trial Be it positive or not . Excellent discussion on Evoke 03. @IASLC @GlopesMd @StephenVLiu @RManochakian @OncBrothers #wclc2026 https://t.co/dUnY6Qdtet

1.5K impressions8 likes2026-09-13
gilberto lopes
gilberto lopes@GlopesMd

5/6 EVOKE-03 / KEYNOTE-D46 Sacituzumab govitecan + pembrolizumab vs pembrolizumab alone in untreated metastatic NSCLC with PD-L1 ≥50%. The early data looked promising. But phase III tells a different story: ❌ PFS numerically favored the combination but did not reach statistical significance, and the study was discontinued. At WCLC I want to understand why — and what the OS, subgroup and safety data teach us.

969 impressions7 likes2026-08-21
MV Chandrakanth
MV Chandrakanth@ChandrakanthMv

EVOKE-03: More response ≠ longer survival SG + pembrolizumab vs pembrolizumab in PD-L1 ≥50% metastatic NSCLC. More responses: ORR 56.6% vs 43.7%. PFS numerically longer: 11.8 vs 7.7 months | HR 0.81. But no OS benefit: 21.5 vs 22.8 months | HR 1.07. Much more Grade ≥3 toxicity: 55.7% vs 16.5%. Take-home: More tumors shrank, but patients did not live longer. Mountzios G et al. EVOKE-03/KEYNOTE-D46 | WCLC 2026 #MVOnco #WCLC2026 #EVOKE03 #NSCLC #LungCancer

326 impressions0 likes2026-09-13
Paul H, PharmD, RPH
Paul H, PharmD, RPH@phsiao4

The fact that Gilead Sciences’ #sacituzumabgovitecan (#SG)failed as a first-line treatment for non-small cell lung cancer was not new. Yet newly revealed global phase 3 data could reignite the question around translating Chinese data to the West. Evoke-03 trial https://t.co/Dg3KNyHfqc

279 impressions0 likes2026-09-13
OncOtaku
OncOtaku@OncOtaku

📝EVOKE-03   ✓PD-L1高発現では👑PBR単剤にADC追加効果なし ↔️EV-302(mUC)👏 👀両試験でのNeutropenia発現率の違い(=宿主免疫への負の影響)がICIの効果に直結? 🤔類似試験(TroFuse-007, TROPION-Lung08)の行く末は? 🤔PD-L1低発現/陰性ではどうか? #WCLC26 https://t.co/dKyvWferwj

137 impressions0 likes2026-09-13
Casey Davis
Casey Davis@CaseyHealthC

@Latinamd @IASLC @GlopesMd Honestly I'm skeptical on EVOKE-03 after how the earlier sacituzumab + pembro data read out. PD-L1 >=50% enrichment may not be enough. My money's on the B7-H3 ADCs instead.

110 impressions1 likes2026-09-12
Giannis Mountzios
Giannis Mountzios@g_mountzios

🌟 Truly honored that our work has been selected for presentation at the Presidential Symposium 1 of the World Lung Cancer Conference #WCLC26 in Seoul: ⏰ Sunday, 13 September 08:00-10:30 KST 🗒️ Presidential Symposium 1 📌 Plenary, Hall D2, 3F Primary analysis of the global, randomized phase III EVOKE-03/KEYNOTE D46 clinical trial on the combination of Sacituzumab Govitecan plus pembro vs pembro monotherapy in patients with advanced #NSCLC and high #PDL1 expression. Thank you @IASLC for selecting a negative (by press release) phase III trial for the Presidential Symposium, those data are important to be shared and communicated in detail, because they provide food for thought and can be hypothesis generating for future trials. Looking forward to the discussion that will follow, especially in he context of the Optitrop Lung 05 results. #ThoracicMalignancy #WCLC26 #IASLC #ThoracicMalignancy #WCLC26 https://t.co/pvnFKqNzXc

24 impressions0 likes2026-08-20
Hidehito HORINOUCHI
Hidehito HORINOUCHI@HHorinouchi

🆙#WCLC26 #LCSM Plenary Session 🔥EVOKE-03/KEYNOTE D46: Primary Results from Phase 3: Sacituzumab Govitecan + Pembrolizumab in PD-L1 TPS ≥50% Metastatic NSCLC 🎙️ @g_mountzios 🔢PL02.06 ☑️NCT05609968 🔗 https://t.co/icbDk1Zjnh @OncoAlert @Larvol @IASLC https://t.co/4ShK6WS6fB

176 impressions1 likes2026-08-20
Giannis Mountzios
Giannis Mountzios@g_mountzios

🌟 Truly honored that our work has been selected for presentation at the Presidential Symposium 1 of the World Lung Cancer Conference #WCLC26 in Seoul on Sunday, September 13: Primary analysis of the global, randomized phase III EVOKE-03/KEYNOTE D46 clinical trial on the combination of Sacituzumab Govitecan plus pembro vs pembro monotherapy in patients with advanced #NSCLC and high #PDL1 expression. Thank you @IASLC for selecting a negative (by press release) phase III trial for the Presidential Symposium, those data are important to be shared and communicated in detail, because they provide food for thought and can be hypothesis generating for future trials. Looking forward to the discussion that will follow, especially in he context of the Optitrop Lung 05 results. #ThoracicMalignancy #WCLC26 ⏰ Sunday, 13 September 08:00-10:30 KST 🗒️ Presidential Symposium 1 📌 Plenary, Hall D2, 3F #IASLC #ThoracicMalignancy #WCLC26 https://t.co/pvnFKqNzXc

18 impressions0 likes2026-08-20
Giannis Mountzios
Giannis Mountzios@g_mountzios

🌟 Truly honored that our work has been selected for presentation at the Presidential Symposium 1 of the World Lung Cancer Conference #WCLC26 in Seoul: Primary analysis of the global, randomized phase III EVOKE-03/KEYNOTE D46 clinical trial on the combination of Sacituzumab Govitecan plus pembro vs pembro monotherapy in patients with advanced #NSCLC and high #PDL1 expression. ⏰ Sunday, 13 September 08:00-10:30 KST 🗒️ Presidential Symposium 1 📌 Plenary, Hall D2, 3F Thank you @IASLC for selecting a negative (by press release) phase III trial for the Presidential Symposium, those data are important to be shared and communicated in detail, because they provide food for thought and can be hypothesis generating for future trials. Looking forward to the discussion that will follow, especially in he context of the Optitrop Lung 05 results. #ThoracicMalignancy #WCLC26 #IASLC #ThoracicMalignancy #WCLC26 https://t.co/pvnFKqNzXc

16 impressions0 likes2026-08-20

EVOKE-03 / KEYNOTE-D46 FAQ

Are EVOKE-03 and KEYNOTE-D46 the same trial?

Yes — one phase III study with two names: EVOKE-03 in Gilead's nomenclature and KEYNOTE-D46 in Merck's (NCT05609968). Merck sponsored and operationalized the trial; Gilead's Trodelvy (sacituzumab govitecan) was the investigational addition. Some conference trackers list the two names as separate trials; they are not.

What did the trial test?

Whether adding sacituzumab govitecan, a TROP2-directed antibody-drug conjugate, to pembrolizumab improves outcomes versus pembrolizumab alone as first-line treatment for metastatic NSCLC with PD-L1 TPS ≥50% and no EGFR/ALK/ROS1 alterations, in about 620 patients with dual primary endpoints of PFS and OS.

What were the results?

Negative on both primaries: final PFS 11.8 versus 7.7 months (HR 0.81, 95% CI 0.66–1.00) missed statistical significance, the interim OS analysis showed HR 1.07 (95% CI 0.85–1.35) with median OS 21.5 versus 22.8 months and futility, and Grade ≥3 treatment-related adverse events were 55.7% versus 16.5%. The trial was discontinued in June 2026 on the data monitoring committee's recommendation, and the full data were presented at WCLC 2026.

Does this affect Trodelvy's approvals?

No. Sacituzumab govitecan remains approved in its existing indications (including metastatic triple-negative and HR+/HER2- breast cancer); it was never approved for first-line NSCLC, and this combination is not advancing in that setting.

What do KOLs take from it?

That beating pembrolizumab monotherapy in PD-L1-high first-line NSCLC remains extraordinarily hard: the toxicity of adding an ADC payload was not paid back in efficacy, echoing other negative ADC-plus-IO first-line attempts discussed at the meeting. Subgroup signals were described as hypothesis-generating only.

Key KOL Sentiments

KOLComment (verbatim)SentimentDate
Giannis Mountzios
@g_mountzios
🌟 Truly honored that our work has been selected for presentation at the Presidential Symposium 1 of the World Lung Cancer Conference #WCLC26 in Seoul: ⏰ Sunday, 13 September 08:00-10:30 KST 🗒️ Presidential Symposium 1 📌 Plenary, Hall D2, 3F Primary analysis of the global, randomized phase III EVOKE-03/KEYNOTE D46 clinical trial on the combination of Sacituzumab Govitecan plus pembro vs pembro monotherapy in patients with advanced #NSCLC and high #PDL1 expression. Thank you @IASLC for selecting a negative (by press release) phase III trial for the Presidential Symposium, those data are important to be shared and communicated in detail, because they provide food for thought and can be hypothesis generating for future trials. Looking forward to the discussion that will follow, especially in he context of the Optitrop Lung 05 results. @IASLC @myESMO @lcsmchat @OncoAlert @OncBrothers @OncLive @PeerView @oncodaily @VJOncology @MedscapeOnc @LungCancerEu @YoungLungCancer @lcrf_org @LUNGevity @HeSMO_X @fairlifelcc @HenryDunantGR #IASLC #ThoracicMalignancy #WCLC26 https://t.co/pvnFKqNzXcPositive2026-08-20
Stephen V Liu, MD
@StephenVLiu
Dr. @g_mountzios at #WCLC26 presents results of EVOKE-03 / KEYNOTE D46: phase III study of sacituzumab govitecan (Trop2 ADC) with pembro vs pembro alone in NSCLC with PD-L1 ≥50%. Median f/u 14.7m. https://t.co/U1jhvkkDXBNeutral2026-09-13
Dr Riyaz Shah
@DrRiyazShah
EVOKE-03/KEYNOTE D46; Sac-govitecan trop2ADC; P3RCT; high PDL1 (>50%) randomised to Pembro vs SG+ Pembro; n620; 4 month longer mPFS but HR not stat significant ; OS flat ; Interesting as suggests chemoIO might not beat IO alone in high PDL1 within a prospective RCT #WCLC26 https://t.co/v6BUMaBEWKNeutral2026-09-13
MV Chandrakanth
@ChandrakanthMv
EVOKE-03: More responses — but no survival gain? Phase III | 620 patients with untreated metastatic NSCLC, PD-L1 ≥50% SG + pembrolizumab vs pembrolizumab alone ORR: 56.6% vs 43.7% → more tumors responded PFS: 11.8 vs 7.7 months | HR 0.81 → numerical improvement, not statistically significant per prespecified boundary OS: 21.5 vs 22.8 months | HR 1.07 → no survival benefit Grade ≥3 TRAEs: 55.7% vs 16.5% → substantially more toxicity Non-squamous and East Asian subgroups showed interesting signals — hypothesis-generating, not practice-changing Take-home: More responses ≠ longer survival. Pembrolizumab remains a standard option in PD-L1-high, driver-negative NSCLC. Reference: Mountzios G et al. EVOKE-03/KEYNOTE-D46, PL02.06 | WCLC 2026 #MVOnco #WCLC2026 #EVOKE03 #NSCLC #LungCancer #Immunotherapy #TROP2Neutral2026-09-13
Uğur Özkerim
@UOzkerim
EVOKE-03/KEYNOTE-D46 at #WCLC26 In 1L metastatic NSCLC with PD-L1 TPS ≥50%, adding sacituzumab govitecan to pembrolizumab did not meet the primary PFS endpoint despite numerically longer PFS (11.8 vs 7.7 mo; HR 0.81). No OS benefit was observed at the interim analysis (HR 1.07). @OncoAlert @ManuelDomine @weoncologists @OpenMedKate @g_mountziosNeutral2026-09-13
Diego A. Díaz-García
@diegoadiazg
🫁 EVOKE-03: adding a Trop-2 ADC to pembrolizumab did not improve outcomes in PD-L1-high NSCLC. PFS: 11.8 vs 7.7 months, HR 0.81 OS: 21.5 vs 22.8 months ORR: 56.6% vs 43.7% Grade ≥3 TRAEs: 55.7% vs 16.5%. A negative phase III study despite higher response rates with the combination. #CánCare #NSCLC #LungCancer #ThoracicOncology #ADC #Immunotherapy #WCLC26 @IASLCNeutral2026-09-13
Stephen V Liu, MD
@StephenVLiu
As would be expected, much greater toxicity with sacituzumab govitecan + pembro arm vs pembro alone. With no PFS/OS signal and worse toxicity, this strategy fails in an unselected population. Other ADC trials in different PD-L1 subsets and exploring biomarkers pending. #WCLC26 https://t.co/jpwoUE29EBNegative2026-09-13
Roberto Ferrara
@RobertoFerrara_
Evoke 03 Sacituzumab Gov+ Pembro no benefit in OS. In 2026 it's time to integrate other biomarkers different than high PD-L1 expression in clinical trials to test escalation strategies. PFS data in PD-L1 >90% curve will overlap? #WCLC2026 https://t.co/JecL0Y8IUyNegative2026-09-13
Tom Newsom-Davis
@tnewsomdavis
EVOKE-03 Ph3, Saci-Gov+Pembro v Pembro 1L NSCLC PD-L1 >50% SG+Pembro: ❌🔼mPFS 11 v 7m, HR 0.81 (not sig) ❌No OS benefit ❓benefit in Asian & non-sq popn ❌🔼 Gr3+ TRAE 73 v 45% 🤔 Early Ph2 activity lost in Ph3 Post-hoc Asia data = limited value End of SG in NSCLC IMO #WCLC26 https://t.co/MW60DL1p0mNegative2026-09-13
Miguel Gonzalez Velez, MD
@mgonzalezvelMD
EVOKE-03/KND46 negative readout for a Sac-GT. Take: Dual primary endpoint, neither met. PFS numerically favored SG + pembro but wasn't statistically significant. Interim OS: 21.5 vs 22.8 mo, HR 1.07. ORR (55.6% vs 43.7%) and DCR (83.3% vs 73.1%) both favored the combo, but no PFS/OS. I think SG is a first-generation ADC with inferior efficacy and higher toxicity. Response rate gains without OS or durable PFS benefit in settings where pembrolizumab is good and safe as discussed by @Dr_R_Kurzrock @oncology_bg Interesting split by geography in Asia… #NSCLC #LCSM #WCLC26Negative2026-09-13
Hidehito HORINOUCHI
@HHorinouchi
🆙#WCLC26 #LCSM Plenary Session 🔥EVOKE-03/KEYNOTE D46: Primary Results from Phase 3: Sacituzumab Govitecan + Pembrolizumab in PD-L1 TPS ≥50% Metastatic NSCLC 🎙️ @g_mountzios 🎯PFS HR 0.81 (95% CI 0.66-1.00) 🎯OS HR 1.07 (95% 0.85-1.35) 🔢PL02.06 ☑️NCT05609968 🔗 https://t.co/JvkpEBLlSo @OncoAlert @Larvol @IASLCNeutral2026-09-13
Dr. Antonio Calles 🫁🚭
@Tony_Calles
EVOKE-03: SG + Pembro did not improve clinical outcomes over Pembro alone but with an increased rate of known side effects in patients with NSCLC and high PD-L1 expression (>50%) #WCLC26 #LCSM @IASLC https://t.co/zDPQEJIo1pNeutral2026-09-13
Misty Dawn Shields
@drshieldsmd
Dr. Giannis Mountzios @g_mountzios presented at @IASLC #WCLC26 the EVOKE-03 Phase 3 study investigating sacituzumab govitecan (SG) + pembrolizumab vs pembrolizumab alone in PD-L1 >50% NSCLC. Unfortunately, while there was an improvement in PFS, ORR, and DCR, no significant improvement in OS was observed. Unclear what the rates of oncogenic drivers and co-alterations here were amongst the patients included in this study. Difficult to improve outcomes with adjunct therapies in PD-L1 high NSCLC. More research is needed for additional therapeutic targets in this patient population to improve outcomes and prevent recurrence/resistance. @LUNGevity @LauraAlderMD @lungoncdoc @BrunaPellini @RManochakian @StephenVLiu @FordePatrick @FSkoulidisNeutral2026-09-13
Stephen V Liu, MD
@StephenVLiu
EVOKE-03 did not meet the primary endpoint. PFS 11.8 vs 7.7m, HR 0.81 but did not meet threshold for statistical significance. Consistent across subgroups. No difference in OS: 21.5 vs 22.8m, HR 1.07. #WCLC26 https://t.co/j3v6jr8N7HNegative2026-09-13
Prof Tom John
@TommyJohn00
@g_mountzios presenting EVOKE-03. A negative study with another ADC+Pembro as first line treatment. More tox with ADC. The most interesting slide for me is the result based on region. Asian patients do better. Will this be the same for other studies too? #WCLC26 #LCSM https://t.co/wNtaXlRTBBNegative2026-09-13
Dr Amol Akhade
@SuyogCancer
Evoke 03 . Important negative study. SG plus Pembrolizumab in 1st line NSCLC with PDL1 above 50 % @IASLC @StephenVLiu @DrRiyazShah @RManochakian @FordePatrick @PatelOncology https://t.co/PDuPiGhxX3Negative2026-09-13
Free Access · KOL Pulse Intelligence

Track oncology’s top KOLs in your specialty

Create a free account, pick the tumor types you cover, and go beyond the tweet — the intelligence pharma teams use to map influence and prepare for engagement:

  • Enhanced KOL profiles
  • Pharma influence & potential advisory-board patterns
  • 2025 Open Payments financial analysis
  • Social-media sentiment & trend signals
Get free access — pick your specialty
Choose the tumor types you follow. No cost, unsubscribe anytime.

Compiled and reviewed by the KOL Pulse research team, led by Brian Shields, Founder, KOL Pulse. Last updated September 13, 2026. Every statistic carries its source label in place; every quote is verbatim from the physician's own post.