PREVIEW ASH 2026 — New Orleans, Dec 12–15: the abstracts hematologists are watching, top voices and trial buzz See the ASH 2026 preview →
KOL Pulse

AI in Oncology — KOL Digest

KOL DigestThursday, November 19, 2026 All editions →

OpenEvidence partners with the Oncology Brothers and The Uromigos, UpToDate rolls out Expert AI, and a Lancet study finds chatbot ads steer drug picks

The Oncology Brothers (Drs. Rahul and Rohit Gosain) announced the OpenEvidence partnership on X this week. Asked how it works, they replied that OpenEvidence “will supplement published data with our panelists quotes from the podcast.” The screenshots show the format: a “Verbatim Expert Perspective” card credited “Originally shared on Oncology Brothers.” On Nov 13, Katy Beckermann posted a slide showing the same format for The Uromigos. 

  1. OpenEvidence teams up with the Oncology Brothers and The Uromigos
  2. OpenEvidence vs. UpToDate: the race for the clinical reference
  3. Can you trust the model? Ads, benchmarks and validation
  4. AI in oncology education and fellowship training
  5. In the clinic: tools physicians are building and using
Topic 1

OpenEvidence teams up with the Oncology Brothers and The Uromigos

Oncology Brothers — profile photo, @OncBrothers on X
Oncology Brothers@OncBrothers on X
Community oncology podcast — Drs. Rahul Gosain (Wilmot Cancer Institute) and Rohit Gosain (Roswell Park)
Yes… it’s true!

We are excited to share that we have partnered with @OpenEvidence so expert quotes & practices can be shared in the right context… especially where data is limited.

It’s not AI vs us, but how we incorporate these tools together to deliver better care in community settings!

#OncTwitter #HemeTwitter @TravisZack2 @VivHo @OncoAlert @OncUpdates @WilmotCancer @RoswellPark
Oncology Brothers and OpenEvidence partnership graphic: the ONC Brothers logo on black beside the OpenEvidence logo on white
View post on X ↗

“Tell us more! How does it work?”

Oncology Brothers — profile photo, @OncBrothers on XOncology Brothers@OncBrothers
@MKnoll_MD @OpenEvidence @RManochakian @BijoyTelivala @lungoncdoc @GlopesMd @RahulBanerjeeMD @rmistry91 @Dr_AmerZeidan @NiuSanford @PGrivasMDPhD @montypal Based on the prompt, @OpenEvidence will supplement published data with our panelists quotes from the podcast to the user of what is actually being done in real life clinical practice 👇👇@jmikhaelmd @rmistry91 🙏🏽🙏🏽

x.com/rmistry91/stat… ↗
OpenEvidence mobile screen showing a 'Verbatim Expert Perspective' card: Dr. Joseph Mikhael (International Myeloma Foundation) on choosing therapy before CAR-T collection, credited 'Originally shared on Oncology Brothers'
View post on X ↗
Ronak H. Mistry, DO — profile photo, @rmistry91 on X
Ronak H. Mistry, DO@rmistry91 on X
Hematologist — Penn Medicine; co-host, The Fellow on Call
Very excited for our friends @OncBrothers for this amazing partnership with @OpenEvidence!

So much of hematology and oncology is the art of medicine.

Grateful to Rahul, Rohit and OpenEvidence to be able to share some of my takes through this exciting opportunity x.com/oncbrothers/st… ↗
OpenEvidence mobile screen showing a 'Verbatim Expert Perspective' card: Dr. Ronak Mistry, DO (Penn Medicine) on platelet transfusion thresholds in febrile patients, credited 'Originally shared on Oncology Brothers'
View post on X ↗

The Uromigos side of the partnership

Katy Beckermann — profile photo, @katy_beckermann on XKaty Beckermann@katy_beckermann
Guidelines tell us what to do with new data. They're much less help with the patient in clinic who never would have made it into the trial.

@OpenEvidence and the Uromigos are bringing expert opinion in to help with those gaps. It doesn't replace the guidelines 🤝. Look forward to see this roll out

#urovoices #uromigos
Photo of a presentation slide titled OpenEvidence X The Uromigos, showing a 'Verbatim Expert Perspective' card with Dr. Neha Vapiwala (Penn radiation oncology) on pathologic response in the PROTEUS prostate cancer trial, credited 'Originally shared on The Uromigos'
View post on X ↗
OpenEvidence — profile photo, @OpenEvidence on XOpenEvidence@OpenEvidence
@katy_beckermann Thanks, Katy. Glad to be building with @Uromigos.
View post on X ↗

A thoracic oncologist, quoted inside OpenEvidence

Dr. Nagla Abdel Karim — profile photo, @NaglaAKarimMD on XDr. Nagla Abdel Karim@NaglaAKarimMD
Thank you @OpenEvidence for quoting my perspective on the choice of systemic therapy in Thoracic Large Cell Neuroendocrine Tumors @OncoAlert @oncodaily @myESMO @ASCO @ASCOPost @IASLC
OpenEvidence mobile screen showing a 'Verbatim Expert Perspective' card: Dr. Nagla Abdel Karim on why she avoids pemetrexed in large cell neuroendocrine lung cancer
View post on X ↗
OpenEvidence — profile photo, @OpenEvidence on XOpenEvidence@OpenEvidence
@NaglaAKarimMD @OncoAlert @oncodaily @myESMO @ASCO @ASCOPost @IASLC Thank you, Dr. Abdel Karim. There's no randomized trial on pemetrexed in LCNEC, so a thoracic oncologist saying plainly why she avoids it is what the next doctor with that patient needs to read. Glad your expertise is shared on the OpenEvidence platform.
View post on X ↗
Travis Zack MD — profile photo, @TravisZack2 on XTravis Zack MD@TravisZack2
Thank you so much for your insight! I have loved learning from experts oncologists like yourself during this project x.com/NaglaAKarimMD/… ↗
View post on X ↗
Travis Zack, MD — profile photo, @TravisZack2 on X
Travis Zack, MDOpenEvidence CMO@TravisZack2 on X
Chief Medical Officer, OpenEvidence
I have learned so much building this project. So many amazing insights on how the best in the business practice within the gaps in published evidence and it's great that we will be bringing this to every oncologist at the point the question comes up in clinic x.com/OncBrothers/st… ↗
View post on X ↗
Topic 2

OpenEvidence vs. UpToDate: the race for the clinical reference

UpToDate rolls out Expert AI

Vincent Rajkumar — profile photo, @VincentRK on XVincent Rajkumar@VincentRK
I’m at the @UpToDate Editors meeting today. I’ve been an author/section editor for 20 years. The breaking news is UpToDate Expert AI.

Check out UpToDate Expert AI at your institutions. You should have access if you have access to UpToDate.

UpToDate Expert AI is unique. It is AI plus the world’s top experts analysis and interpretation rolled into one. It offers AI’s magic and proficiency with the human expert element added.

In my experience AI is incredibly helpful but very few of us rely solely on AI to make clinical decisions for a serious illness. Patients still want input from the human expert. Thats what makes UpToDate Expert AI unique. It has both. That helps the treating physician make the best management choice for their patient.
UpToDate Expert AI by Wolters Kluwer title slide at the UpToDate editors meeting
View post on X ↗
Evgeniy Padaliak — profile photo, @genepadaliak on XEvgeniy Padaliak@genepadaliak
It’s pretty nice being on the AI side of this.

@UpToDate's editors and contributors have spent decades reviewing and synthesizing the evidence so we don't need to ask an LLM to decide if a questionable paper should shape the answer.

So most of our time goes into tuning how it translates that knowledge for a specific patient:

- Cautious, but not so cautious that it delays a decision.
- Confident, but without overstating things.
- Helpful, but without making broad extrapolations.

Finding the balance is hard and I believe the recely launched V2 (US and Canada only) is very good at that. If you’ve tried it, would love to hear what you think.
View post on X ↗
Akiff Premjee, MD — profile photo, @akiffpremjee on X
Akiff Premjee, MD@akiffpremjee on X
Internal medicine physician — leads product at Patients App
seeing @UpToDate pivot from trying to compete directly with @OpenEvidence and getting clinicians to use their new app to just going the route to power other CDS tools feels like the right move

their data has always been the valuable part and licensing that out rather than trying to get users directly is the right play here

im still not fully convinced that @OpenAI will be the OS that clinicians go for but let’s see. i feel like even if its got all the bells and whistles there is something that is hard for docs to move past where the same app can be a consumer app or a professional app with different logins

this is why locking @OpenEvidence behind an NPI (which they don’t even seem to verify) feels so much more legit

not saying this is right but just feel like this is the psychology of the medicine brain
View post on X ↗
Healthcare AI Guy — profile photo, @HealthcareAIGuy on X
Healthcare AI GuyMedia@HealthcareAIGuy on X
Healthcare AI news account and weekly newsletter
NEW: OpenEvidence just launched two free AI tools for clinicians.

**Access Intelligence:**
> 2,500+ patient assistance programs
> Copay savings & enrollment
> Prior auths and appeals

**OpenEvidence Learn:**
> 50,000+ board-style questions
> AI-powered clinical case simulations
> Flashcards & CME

More AI for practicing and learning. Cool.
OpenEvidence Access Intelligence screen answering a Medicare cost question about lurasidone, listing patient assistance programs
OpenEvidence Learn 'Preceptor' screen with a list of clinical case simulations filtered by training level and specialty
View post on X ↗
Omar Saleem, MD — profile photo, @omarsaleemmd on X
Omar Saleem, MD@omarsaleemmd on X
Physician
Can attest to this already happening. My use of Epic is almost all as a database and not for much else.

accelerated when the hospital I work at deeply integrated @OpenEvidence and now I use DotFlows more than dot phrases in Epic.

Also notice next gen residents doing the same. x.com/nealkhosla/sta… ↗
View post on X ↗
Travis Zack, MD — profile photo, @TravisZack2 on X
Travis Zack, MDOpenEvidence CMO@TravisZack2 on X
Chief Medical Officer, OpenEvidence
We know Patients are using AI tools to get information about their health. At OpenEvidence, we have long talked about building a tool for patients with the same evidence engine clinician is using. Excited to study such a tool with Apple during this collab x.com/statnews/statu… ↗
View post on X ↗
Topic 3

Can you trust the model? Ads, benchmarks and validation

Berci Meskó, MD, PhD — profile photo, @Berci on X
Berci Meskó, MD, PhDMedical futurist@Berci on X
The Medical Futurist — author and keynote speaker
Shocking results from a recent study!

As large language model (LLM) platforms started introducing advertising in 2026 (even alongside growing clinical use), it seems it affects treatment selection by LLMs towards the promoted drug. 

In experiments about treatment options, it simply tended to select drugs it advertised on the platform.

"Guideline concordance remained high, meaning that shifts among guideline-concordant treatments could evade evaluations of treatment correctness. The influence of advertising was often undisclosed. Whether these output shifts could affect prescribing or patient decisions requires direct study."

This is a crucial finding that not only LLM developers, but also clinical policy-makers should pay attention to. It's like a built-in bias in the system. Let's avoid that consciously and proactively.

The Lancet study: thelancet.com/journals/landi… ↗
View post on X ↗
Aakash Desai, MD, MPH — profile photo, @ADesaiMD on X
Aakash Desai, MD, MPH@ADesaiMD on X
Thoracic and phase 1 oncologist — UAB O'Neal Comprehensive Cancer Center
TrialDesignBench (arXiv): 5 LLMs pick ph1/2 onc dose-finding designs, 617 trials
➡️ None matched expert reference
➡️ Avg balanced acc 0.307 from protocol fields
➡️ 0.547 with decision-tree walk
Who checks the LLM's pick?
doi.org/10.48550/arXiv… ↗

@OncoAlert @oncodaily @AIoncology
Aakash Desai's summary card of the TrialDesignBench preprint benchmarking five LLMs on phase 1 oncology trial design
View post on X ↗
Lung cancer imaging AI (@NEJM_AI): meta-research, 36 studies
➡️ External test set: 39%
➡️ Subgroup analyses: 28%
➡️ Uncertainty: 64%, mostly CIs, not per-patient
How do we make external validation the default?
pubmed.ncbi.nlm.nih.gov/43037489/ ↗

@LungCancerRx @OncoAlert @oncodaily
View post on X ↗

“AI is trained to parrot”? A reply

Razelle Kurzrock, MD — profile photo, @Dr_R_Kurzrock on XRazelle Kurzrock, MD@Dr_R_Kurzrock
Ha ha. We have heard criticism for long time. Every discovery—>breakthrough was criticized. AI is unique in that (i) criticism is verbose (ii) currently AI is trained on traditional; humans can be moved forward even if difficult— AI is trained to parrot/insist on conventional x.com/hemeoncbuddy/s… ↗
View post on X ↗
Veli Bakalov, MD — profile photo, @HemeOncBuddy on XVeli Bakalov, MD@HemeOncBuddy
First and foremost, I have huge respect for you and all your work! 😅

However, I think calling modern AI a “parrot” significantly understates what these models actually do. Perhaps statements like this also highlight how much more education we need about what modern AI actually is and maybe we need more webinars and @ASCO sessions for healthcare professionals on how these systems actually work.

Yes, AI is trained on existing human knowledge, but so are we. Training on existing knowledge does not mean simply retrieving or repeating it (unlike USMLE or our board exams). Modern LLMs can reason across an ocean of information in seconds, generate novel hypotheses, identify relationships, write new code, and propose solutions that were NEVER present in their training data.

AI enabled a breakthrough in the decades-old protein folding problem, resulting in 2024 Nobel Prize. That's pretty impressive parrot. 😅🦜

if reviews provided by AI today are too long or gibberish, we need to standardize them, make sure we use high standard AI engines, make sure reviewers are aware that they can violate privacy if they use AI, we need to come up with new guidelines for AI generated peer reviews etc.
View post on X ↗
Topic 4

AI in oncology education and fellowship training

Yakup Ergün, MD — profile photo, @dr_yakupergun on X
Yakup Ergün, MD@dr_yakupergun on X
Medical oncologist — Mardin Artuklu University
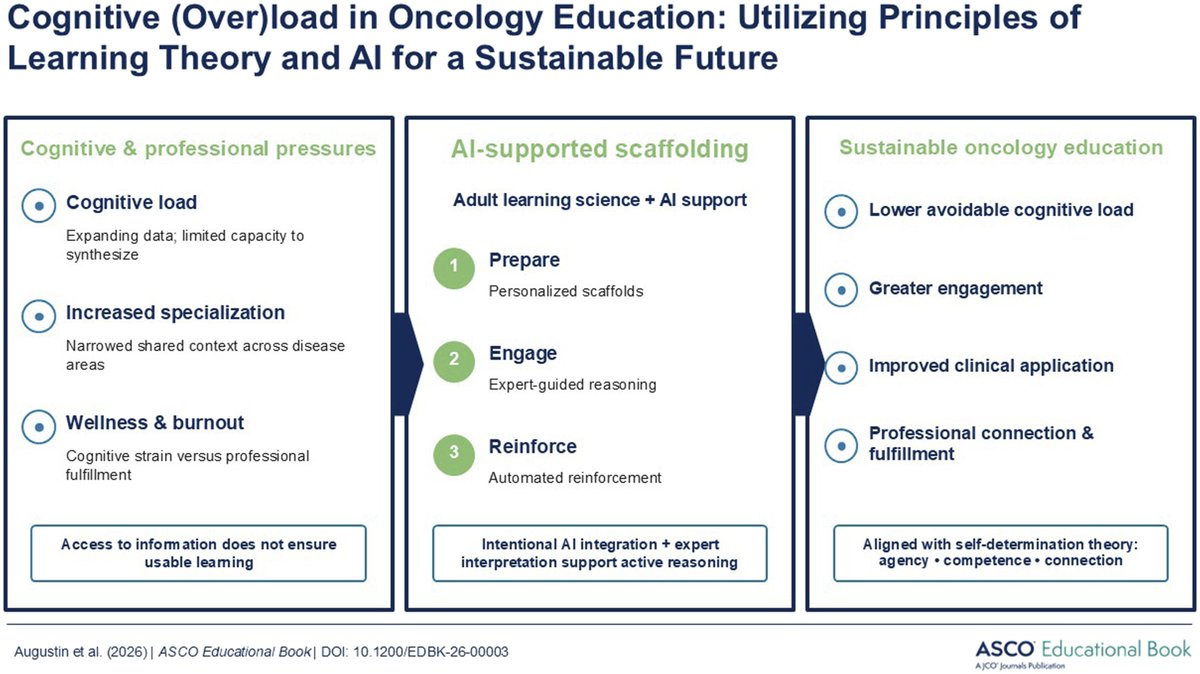
The challenge in oncology education is no longer access to information, but translating an ever-growing volume of knowledge into clinical decisions.

A new article in @ASCO Educational Book proposes AI-supported, case-based active learning instead of traditional lectures.

The goal is not to deliver more information, but to improve clinical reasoning.

ascopubs.org/doi/10.1200/ED… ↗
Figure from the ASCO Educational Book article 'Cognitive (Over)load in Oncology Education' showing pressures, AI-supported scaffolding and outcomes
View post on X ↗
Marc Braunstein, MD, PhD — profile photo, @docbraunstein on X
Marc Braunstein, MD, PhD@docbraunstein on X
Hematologist/oncologist — fellowship program director, NYU Langone Long Island
Talking about practical use of AI for fellowship administrational tasks at the @ASCO Oncology Training Program Leadership Retreat.
Agenda for the 2026 ASCO Oncology Training Program Leadership Retreat, Day 2, Nov 13
Marc Braunstein outside ASCO headquarters in Alexandria, Virginia
View post on X ↗
Topic 5

In the clinic: tools physicians are building and using

Isabel Preeshagul — profile photo, @ipreeshagul on X
Isabel Preeshagul@ipreeshagul on X
Thoracic medical oncologist — Memorial Sloan Kettering
Outstanding session @gotoPER on the future of oncology practice and how to partner with patients on how best to use AI in the clinic. #CFS
- how to handle misinformation
- using ai to interpret results
- ambient listening
Loved seeing Ms. James pt and advocate on the panel💖
Panel on stage at the 44th Chemotherapy Foundation Symposium (PER) discussing AI in oncology practice
View post on X ↗
Alan Tan, MD — profile photo, @alantanmd on X
Alan Tan, MD@alantanmd on X
GU oncologist — Vanderbilt; VP, MRD Research and Clinical Strategy, Tempus AI
Excited to launch mrdwatch.com ↗ 🧬

A free, neutral hub for MRD/ctDNA across cancers: the latest data, must-know evidence, MRD-guided trials (incl. accruing), meeting abstracts & videos.

For clinicians, patients and advocates. Tell me what to add!

#MRD #ctDNA
MRD Watch website videos page with myeloma MRD talks
MRD Watch 'How it works' panel explaining that a clear scan can still miss residual cancer cells
View post on X ↗
Chris Hourigan, MD — profile photo, @DrChrisHourigan on X
Chris Hourigan, MD@DrChrisHourigan on X
Physician-scientist — Director, Virginia Tech FBRI Cancer Research Center
I had Claude @AnthropicAI pull the @ASH_hematology #ASH26 abstracts in AML MRD. Not checked by humans or endorsed by me (although it is smart enough to pander to the bias of this subscriber regarding oral abstracts 1,6,9,16). DM me for the version with clickable links #AML #MRD
AI-generated ranking of 31 ASH 2026 AML MRD abstracts on a 1-10 reviewer-style score, shared by Chris Hourigan as not human-checked
View post on X ↗
InvestingDoc — profile photo, @InvestingDoc on X
InvestingDoc@InvestingDoc on X
Physician and medical practice founder
Excited to start using this to really improve operations at my practice. This could be amazing. I plan on making a video about it in a few weeks and will post on my youtube channel about how I use it for my practice or if I can use it for my medical practice.

cloud.google.com/blog/products/… ↗
View post on X ↗
Compiled and reviewed by the KOL Pulse research team, led by Brian Shields, Founder, KOL Pulse. Quotes are verbatim from their authors’ public posts on X. Last updated November 19, 2026.