PREVIEW ASH 2026 — New Orleans, Dec 12–15: the abstracts hematologists are watching, top voices and trial buzz See the ASH 2026 preview →
Pre-Conference Preview  ·  Starts Dec 12

ASH 2026 Conference Intelligence

Real-time KOL buzz, top themes, and trial signals from the 68th ASH Annual Meeting — New Orleans · December 12–15, 2026. Physicians are already previewing the abstracts: bispecific and trispecific T-cell engagers, next-generation CAR-T, chemo-free mantle cell lymphoma, and menin inhibitors in AML.

Dec 12 (Day 1) 30 days to go Dec 15 (Day 4)
144
Tweets Captured
56
Unique KOLs
142.1K
Total Impressions
30
Days to ASH26
Last updated: November 12, 2026 13:31 UTC

Most Anticipated #ASH26 Abstracts

Plasma cell disorders, myeloma and AL amyloidosis: the full 11-post preview thread from Samer Al Hadidi, MD,MS,FACP (@HadidiSamer), UT Southwestern, posted 2026-11-11. Each post is shown verbatim and in full, in his own numbering. Abstract data are pre-meeting and may change at presentation.

@HadidiSamer
Samer Al Hadidi, MD,MS,FACP@HadidiSamer · 11-post thread · 2026-11-11
Swipe →
1/11
@HadidiSamer
Samer Al Hadidi, MD,MS,FACP @HadidiSamer
My top @ASH_hematology #ASH26 abstracts for plasma cell disorders including myeloma and AL amyloidosis #mmsm @utswcancer 1️⃣MonumenTAL-6: Tec+Tal and Tal+Pom vs EPd/PVd ➡️Phase III, RRMM after 1–4 prior lines, all exposed to anti-CD38 and lenalidomide (80% anti-CD38-refractory) ➡️n=838; median FU: 13.4 mo ➡️Tec+Tal improved PFS HR 0.11; 12-mo PFS 89% vs 30%) and OS (HR 0.38; 12-mo OS 91% vs 80%). Tal+Pom also better than control arm (PFS HR 0.27, OS HR 0.55). 🛑Grade 3/4 infections were 312% with Tec+Tal vs 25% with control (92% of patients needed IVIG), ICANS 6%, taste changes 76% and weight loss 41% (Only 6% stopped treatment for AEs) Time limited therapy with dual targeting in pts after anti-CD38/len failure
👁 900 ❤ 14 🔁 7
2/11
@HadidiSamer
Samer Al Hadidi, MD,MS,FACP @HadidiSamer
My top @ASH_hematology #ASH26 abstracts for plasma cell disorders including myeloma and AL amyloidosis #mmsm @utswcancer 2️⃣MagnetisMM-5: elranatamab vs DPd ➡️phase III, RRMM after 1–4 prior lines (72% len-refractory, only 6% had prior anti-CD38) ➡️n=497; median FU ~ 32 mo ➡️elranatamab improved PFS (HR 0.56; median not reached vs 27 mo, 36-mo PFS 64% vs 41%). OS is still immature. 🛑Grade ≥3 infections were similar (44% vs 41%) indicating high risk of infection in all RRMM but really high in control arm. 🛑Elra+Dara arm: 36-mo PFS 75%, but grade ≥3 infections of 54%. In patients who is anti-CD38 naive, tec-dara data looks better with improved OS already reported.
👁 234 ❤ 0 🔁 0
3/11
@HadidiSamer
Samer Al Hadidi, MD,MS,FACP @HadidiSamer
My top @ASH_hematology #ASH26 abstracts for plasma cell disorders including myeloma and AL amyloidosis #mmsm @utswcancer 3️⃣iMMagine-1: Anito-cel ➡️registrational phase II, RRMM 4th line or later ➡️ n=117; median FU 18 mo ➡️ORR 96%, CR/sCR 75%, MRD negative at 10⁻⁵ 95%. 24-mo PFS 58% and 24-mo OS 84% 🛑CRS 86%, almost all grade 1–2 (one grade 5). ICANS 8% (one grade 3). Grade ≥3 infections only 9% ➡️No parkinsonism, cranial nerve palsy, GBS, IEC-enterocolitis or secondary T-cell malignancy Short follow up and relapses already occurring in ~ half of patients indicating likely lower efficacy than Cilta Cel though with no safety signal with short follow up The ASH 2026 iMMagine-1 abstract uses a January 5, 2026 cutoff, only about 3 months after the ASH 2025 cutoff
👁 199 ❤ 0 🔁 0
4/11
@HadidiSamer
Samer Al Hadidi, MD,MS,FACP @HadidiSamer
My top @ASH_hematology #ASH26 abstracts for plasma cell disorders including myeloma and AL amyloidosis #mmsm @utswcancer 4️⃣EXCALIBER-RRMM: Iberdomide-Dd vs DVd ➡️ Phase III RRMM after 1–2 prior lines, not anti-CD38- or bortezomib refractory ➡️median follow-up 15.7 mo, MRD-negative CR was 41% vs 21% (OR 2.75). MRD-negative CR lasting ≥12 months was 18.8% vs 6.6%. PFS press release: 42 months with Iberdomide-Dd vs 20 months with DVd (HR 0.49) 🛑Grade 3/4 neutropenia very high (84% vs 11%), Grade 3/4 infections were 39% vs 22%. Good to see improvement of PFS, however BCMA therapies should be used prior given OS benefit
👁 94 ❤ 0 🔁 0
5/11
@HadidiSamer
Samer Al Hadidi, MD,MS,FACP @HadidiSamer
My top @ASH_hematology #ASH26 abstracts for plasma cell disorders including myeloma and AL amyloidosis #mmsm @utswcancer 5️⃣IEC-Enterocolitis after cilta-cel (US Myeloma Immunotherapy Consortium) ➡️Commercial cilta-cel, n=1,793 across 23 sites. ➡️Incidence: 3.0% (55 cases), rising each year from 1.8% (2022) to 3.9% (2025) as recognition improves. Median onset was day 96. 🛑No predictors. It was associated with higher odds of other toxicities( parkinsonism and cranial nerve palsy) Important data given the safety signal. 56% of affected patients died, 29 of 31 without myeloma progression, and 12-mo non-relapse mortality was 51%
👁 96 ❤ 2 🔁 0
6/11
@HadidiSamer
Samer Al Hadidi, MD,MS,FACP @HadidiSamer
My top @ASH_hematology #ASH26 abstracts for plasma cell disorders including myeloma and AL amyloidosis #mmsm @utswcancer 6️⃣ NEXICART-2: NXC-201 BCMA CAR-T in AL amyloidosis ➡️ Phase I/II, R/R AL amyloidosis, 62% cardiac involvement; ➡️ n=45, median FU: 9 mo ➡️Free light chains normalized in 96% at a median of 7 days, CR was 100% (16/16) in patients followed >12 months, and 96% of the rest are MRD-negative. Organ responses were 100% cardiac (9/9) and 100% renal (11/11). NT-proBNP fell by a median 57% and proteinuria by 91%. There was no neurotoxicity of any kind and no treatment-related infections 🛑 Grade 3/4 neutropenia was 82%.
👁 90 ❤ 0 🔁 0
7/11
@HadidiSamer
Samer Al Hadidi, MD,MS,FACP @HadidiSamer
My top @ASH_hematology #ASH26 abstracts for plasma cell disorders including myeloma and AL amyloidosis #mmsm @utswcancer 7️⃣BMS-986453: Dual BCMA×GPRC5D CAR-T ➡️ phase I, RRMM after ≥3 prior lines (median 4), 60% prior BCMA therapy, 17% prior BCMA and GPRC5D; ➡️n=58; median FU ~ 1 yr ➡️Efficacy at 75–150M dose: ORR 94% (CR 71%), and 89% even after prior BCMA therapy. In naïve patients: ORR 100%, CR 88%, MRD-negative at 10⁻⁶ 100%, 12-mo PFS 93% (62% overall). 🛑CRS 78% (one grade 5, at 300M), ICANS 3%, infections 52% (21% grade ≥3). GPRC5D on-target/off-tumor effects in 50% (nails 36%, oral 34%, skin 19%) Nice to see data on dual targeting CAR-T
👁 92 ❤ 0 🔁 0
8/11
@HadidiSamer
Samer Al Hadidi, MD,MS,FACP @HadidiSamer
My top @ASH_hematology #ASH26 abstracts for plasma cell disorders including myeloma and AL amyloidosis #mmsm @utswcancer 8️⃣TALisman: prophylaxis for talquetamab oral toxicity ➡️phase II, randomized, RRMM starting talquetamab; arms were no prophylaxis or dexamethasone mouthwash, pregabalin or clonazepam ➡️n=70 🛑Prophylaxis appears to make things worse. Severe dysgeusia on the objective taste test (WETT) was 56% with no prophylaxis vs 86–100% with any of the three. 🛑Dexamethasone mouthwash added the most harm (oral mucositis 33% vs 7–13%, dysphagia 40%, thrush) and delayed recovery: 33% improved by month 3 vs 57–59% in the other arms. Important since we need to change practice offering such supportive therapies, patients taste usually improves by ~ 3 mo
👁 89 ❤ 0 🔁 0
9/11
@HadidiSamer
Samer Al Hadidi, MD,MS,FACP @HadidiSamer
My top @ASH_hematology #ASH26 abstracts for plasma cell disorders including myeloma and AL amyloidosis #mmsm @utswcancer 9️⃣ CaMMouflage: CB-011, allogeneic CRISPR-edited BCMA CAR-T ➡️Phase I, RRMM after ≥3 prior lines (median 4), n=48. ➡️At the recommended dose (higher-dose cyclophosphamide lymphodepletion plus 450M cells) in BCMA-naïve patients (n=12): ORR 92%, ≥CR 83%, MRD-negative 91%. 🛑No GvHD. Infections 49% (17% grade ≥3), prolonged grade ≥3 cytopenias 35%, CRS 34% and IEC-HS 9%. There was one grade 4 GBS and four grade 5 events It is proof that an off the shelf CAR-T can work, though with infection and cytopenia burden
👁 89 ❤ 0 🔁 0
10/11
@HadidiSamer
Samer Al Hadidi, MD,MS,FACP @HadidiSamer
My top @ASH_hematology #ASH26 abstracts for plasma cell disorders including myeloma and AL amyloidosis #mmsm @utswcancer 1️⃣0️⃣Frontline teclistamab in Mayo stage IIIB AL amyloidosis ➡️Phase II, newly diagnosed Mayo stage IIIB AL amyloidosis,teclistamab was given alone for 6 cycles (60 mg fixed dose after step-up). All had cardiac involvement and 41.7% renal involvement. Median NT-proBNP was 18,020 ng/L and median dFLC 344 mg/L. ➡️n=24, median FU: 4.0 mo ➡️ Fast responses: median 13 days to first response and 36 days to best response. At 1 month, ≥VGPR was 77.3% (CR 59.1%). Best cardiac response was 54.5% (27.3% ≥VGPR). 🛑CRS was 42%, all grade 1–2 except one grade 3, and there was no ICANS. 🛑High mortality: ~ 1/3 (8/24). Six died of progressive heart failure and 2 of infection. 5 died within 3 months, first prospective frontline bispecific study in stage IIIB AL. Clearing the light chain within about 2 weeks is the right goal in a disease where the heart deteriorates before slower regimens can work but concerning to see still high % of early cardiac deaths indicating that hematologic speed alone is not enough
👁 134 ❤ 0 🔁 0
11/11
@HadidiSamer
Samer Al Hadidi, MD,MS,FACP @HadidiSamer
My top @ASH_hematology #ASH26 abstracts for plasma cell disorders including myeloma and AL amyloidosis #mmsm @utswcancer Few other studies, very small, like mRNA-2808 (in vivo trispecific BCMA/GPRC5D/FcRH5 T-cell engagers) is novel, but n=12 with 4 responses after a median of 10 prior lines. Dysgeusia was 58%, hand-foot syndrome 42% and CRS 42% (all grade 1) and other small studies will talk about in the meeting Looking for great meeting End 🧵
👁 110 ❤ 0 🔁 0
Open the full thread on X ↗

More physician preview lists

Other hematologists sharing the abstracts they plan to watch, ranked by reach. Text is verbatim from each post.

@TalhaBadarMD
Talha Badar @TalhaBadarMD
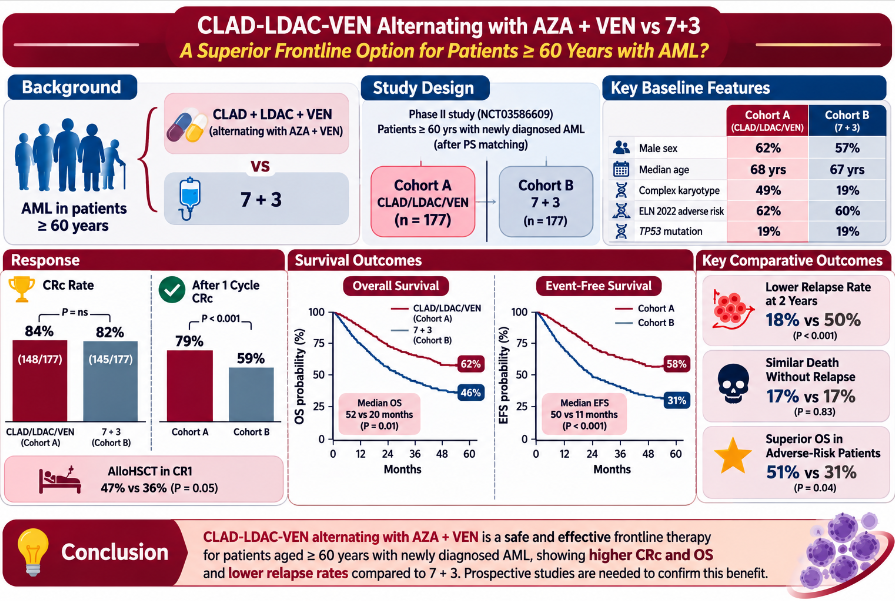
🩸 #ASH26 | #AML Abstracts to Watch (Oral) My current list of 11 AML abstracts to watch at #ASH2026 👇 #leusm A mix of potentially practice-changing frontline trials, menin inhibitors, MRD, and novel approaches in both younger and older patients. 1️⃣ Ivosidenib + intensive chemotherapy in newly diagnosed IDH1-mutated AML HOVON150/AMLSG29-18, phase 3 Superior event-free survival 📄 Abstract 0001, Press Program 📅 Sun Dec 13 | 7:00 AM CT ⚠️ Oral/plenary slot not yet confirmed 🔗 https://t.co/HAiAem9IzK 2️⃣ Gilteritinib vs midostaurin in newly diagnosed FLT3-mutated AML Subgroup analysis from HOVON156/AMLSG28-18/pasha 📄 Abstract 56 | Session 615 📅 Sat Dec 12 | 9:30 AM 📍 Great Hall BC 🔗 https://t.co/vnNwomzMZ7 3️⃣ Bleximenib in R/R AML with KMT2A rearrangements or NPM1 mutations Topline results from phase 2 CAMELOT-1 📄 Abstract 661 | Session 616 📅 Sun Dec 13 | 4:30 PM 📍 Hall B 🔗 https://t.co/Das1necevM 4️⃣ Cladribine + LDAC + venetoclax vs intensive chemotherapy (7+3) Patients ≥60 years with newly diagnosed AML 📄 Abstract 57 | Session 615 📅 Sat Dec 12 | 9:30 AM 📍 Great Hall BC 🔗 https://t.co/vuvS9OfmdF 5️⃣ Can we stop HMA + venetoclax? Discontinuation of hypomethylating agent + venetoclax in newly diagnosed AML with undetectable MRD 📄 Abstract 1009 | Session 617 📅 Mon Dec 14 | 4:30 PM 📍 Great Hall AD 🔗 https://t.co/MiP4Z7F5BL 6️⃣ Sonrotoclax + azacitidine across ELN 2024 genetic risk groups Treatment-naive AML unfit for intensive chemotherapy 📄 Abstract 60 | Session 615 📅 Sat Dec 12 | 9:30 AM 📍 Great Hall BC 🔗 https://t.co/gU3WGMcyAm 7️⃣ Venetoclax + 3-day multi-frequency decitabine vs AZA + VEN Older adults with newly diagnosed AML, updated randomized results 📄 Abstract 1012 | Session 617 📅 Mon Dec 14 | 4:30 PM 📍 Great Hall AD 🔗 https://t.co/L7cHhkZ4IF 8️⃣ Whole-genome-informed AML MRD testing Prospective multicenter validation, MEASURE 📄 Abstract 390 | Session 619 📅 Sat Dec 12 | 4:00 PM 📍 Great Hall AD 🔗 https://t.co/XPb38cdFAW 9️⃣ VEN + AZA vs daunorubicin + cytarabine induction Young adults with ELN adverse-risk AML, phase 2b 📄 Abstract 1010 | Session 617 📅 Mon Dec 14 | 4:30 PM 📍 Great Hall AD 🔗 https://t.co/T8URfhrzzg 🔟 Ziftomenib + gilteritinib in R/R NPM1- and FLT3-co-mutated AML First results from phase 1 KOMET-008 📄 Abstract 66 | Session 617 📅 Sat Dec 12 | 9:30 AM 📍 Great Hall AD 🔗 https://t.co/nTnyI2myj8 11/12 1️⃣1️⃣ FLAI-G frontline in younger FLT3-mutated AML Fludarabine + high-dose cytarabine + idarubicin + gilteritinib First interim analysis, phase 2 GIMEMA AML2924 📄 Abstract 903 | Session 617 📅 Mon Dec 14 | 2:45 PM 📍 Great Hall BC 🔗 https://t.co/OwFJZBjAnr Lots to watch at #ASH26 in AML. Particularly interested in the randomized frontline data, evolving role of menin inhibition, MRD-guided treatment decisions, and whether lower-intensity approaches can continue challenging conventional intensive chemotherapy. Which AML abstracts are on your must-see list? #AML #Leukemia #ASH26
👁 5.9K ❤ 79 🔁 23
@HenrychihangFu1
Henry C Fung| MM, lymphoma, leukemia & CART @HenrychihangFu1
🧬 CAR-T abstracts I won’t miss at #ASH26! My 10 picks across myeloma and lymphoma—from longer follow-up and earlier-line treatment to dual targeting, allogeneic platforms, and CAR-T cells generated in vivo. The questions I’ll be watching: 🔹 Durability: How long do remissions last—and how much time can patients spend free of treatment? 🔹 Earlier treatment: Which patients benefit most from moving CAR-T forward? 🔹 Dual targeting: Can BCMA × GPRC5D or CD19/CD20 targeting reduce relapse? 🔹 Safety: Can we prevent delayed neurotoxicity while preserving disease control? 🔹 Access: Can allogeneic and in vivo approaches make CAR-T available to more patients? Response rates attract attention. Durability, safety, patient selection, and study design determine clinical value. Small cohorts, subgroup analyses, and historical comparisons deserve careful interpretation. These are my current picks; late-breaking abstracts may add more! 🎺 Jazz, crawfish, Hurricanes—and plenty of CAR-T discussion. See you in New Orleans! #ASH26 #CART #MultipleMyeloma #Lymphoma #HemeTwitter
👁 4.4K ❤ 55 🔁 16
@HenrychihangFu1
Henry C Fung| MM, lymphoma, leukemia & CART @HenrychihangFu1
More to watch at #ASH26! 📅 My schedule is attached. Thank you for flagging two important omissions from my preview: 🔹 MonumenTAL-6: Phase III Tec–Tal and Tal–Pom—PFS and OS benefits versus EPd/PVd. Major results, with safety and longer follow-up essential to interpretation. 🔹 AQUILA: Final survival analysis in the enrolled high-risk SMM population—7-year OS 87.8% vs 78.7% with daratumumab versus monitoring. Important findings to examine alongside risk definitions and treatment after progression. Two additional highlights: 🔹 PERSEUS: Long-term MRD outcomes and MRD-guided daratumumab maintenance discontinuation. 🔹 MajesTEC-5, Arm G: Early results with ramantamig, a BCMA × GPRC5D × CD3 trispecific, plus daratumumab/lenalidomide in transplant-eligible, newly diagnosed MM, followed by ramantamig/daratumumab maintenance without planned ASCT. This is a separate cohort from the original teclistamab-based cohorts incorporating ASCT. An increasingly crowded—and exciting—myeloma agenda in New Orleans! 🎷🦞🍹 📅 SEE THE SCHEDULE BELOW ⬇️ Our selected abstracts, dates, times, and locations—all times CST (New Orleans local time). Dr. Fun + G #MultipleMyeloma #mmsm #HemeTwitter
👁 1.7K ❤ 15 🔁 7
@hematointensa
Hematología Intensa @hematointensa
🩸 #ASH26 | #BMT Abstracts to Watch My current list of key allogeneic hematopoietic cell transplantation abstracts to watch at #ASH2026 👇 A mix of potentially practice-changing GVHD prevention strategies, donor selection, conditioning, MRD, and emerging transplant platforms. https://t.co/xBEZ58mNjp
👁 1.4K ❤ 16 🔁 4
@SabrinaRanero
Sabrina Ranero Ferrari @SabrinaRanero
Exciting news in MCL! Zanubrutinib + rituximab in 1L transplant-ineligible MCL shows promising results in MANGROVE (interim PFS HR 0.57 vs BR). Looking forward to seeing the full data at #ASH26! https://t.co/IgRtaIcuWI
👁 682 ❤ 11 🔁 2

Top Themes Ahead of ASH 2026

Most-discussed topics across 144 curated tweets from 56 hematologists, researchers and hematology organizations. Tap any card to see the tweets.

🛡️
25
Safety: CRS, ICANS, Infections & IEC
18.8K impressions
tap to see tweets
💊
24
Chemo-Free Frontline (BTKi / Venetoclax)
35.3K impressions
tap to see tweets
🎯
17
Bispecific & Trispecific T-Cell Engagers
14.7K impressions
tap to see tweets
⏳
17
Precursor States: MGUS, Smoldering & CHIP
17.6K impressions
tap to see tweets
🔴
16
CAR-T: In Vivo, Allogeneic & Dual-Target
14.9K impressions
tap to see tweets
📊
14
MRD & Response Depth
15.6K impressions
tap to see tweets
🧬
13
Targeted Therapy in Myeloid Disease
20.4K impressions
tap to see tweets
🏥
13
Transplant & GVHD
15.9K impressions
tap to see tweets
🫀
11
AL Amyloidosis
2.1K impressions
tap to see tweets
🎓
11
Trainees, Awards & Mentorship
11.5K impressions
tap to see tweets
🩹
9
Classical Hematology: ITP, SCD & Thrombosis
7.7K impressions
tap to see tweets
🤖
3
AI, Data & Digital Tools
651 impressions
tap to see tweets
Free Access · KOL Pulse Intelligence

Track oncology’s top KOLs in your specialty

Create a free account, pick the tumor types you cover, and go beyond the tweet — the intelligence pharma teams use to map influence and prepare for engagement:

  • ✓Enhanced KOL profiles
  • ✓Pharma influence & potential advisory-board patterns
  • ✓2025 Open Payments financial analysis
  • ✓Social-media sentiment & trend signals
Get free access — pick your specialty
Choose the tumor types you follow. No cost, unsubscribe anytime.

Top Voices by Impressions

Ranked by total impressions across all ASH 2026 posts captured. Switch tabs to view physicians, institutions, and media separately.

#1 @smbenlazar
Benlazar S M A @smbenlazar
66.2K 40 tweets
#2 @haydersaeed_md
Hayder Saeed, MD @haydersaeed_md
7.9K 11 tweets
#3 @mtmdphd
6.7K 19 tweets

#4 @henrychihangfu1
6.1K 2 tweets

#5 @talhabadarmd
Talha Badar @talhabadarmd
5.9K 1 tweet
#6 @rahul2u
Rahul Thakur, MD @rahul2u
4.5K 1 tweet
#7 @tobyeyre82
Toby A. Eyre @tobyeyre82
3.8K 2 tweets
#8 @kansagramd
Ankit kansagra @kansagramd
3.4K 2 tweets
#9 @abdallah81md
2.5K 2 tweets
#10 @hadidisamer
2.1K 11 tweets
#11 @surbhisidanamd
Surbhi Sidana, MD @surbhisidanamd
2.1K 1 tweet
#12 @mshadman
1.8K 1 tweet
#1 @culymphoma
1.8K 3 tweets
#2 @bloodcancertalk
Blood Cancer Talks @bloodcancertalk
1.6K 1 tweet
#3 @ash_hematology
ASH @ash_hematology
1.3K 1 tweet
#4 @myeloma_msmart
mSMART Myeloma @myeloma_msmart
1.1K 1 tweet
#5 @tischcancer
211 1 tweet
#6 @oncolytics
Oncolytics Biotech @oncolytics
205 1 tweet
#7 @nurix_tx
Nurix Therapeutics @nurix_tx
164 1 tweet
#8 @dizal_global
Dizal Pharmaceutical @dizal_global
67 1 tweet
#1 @biopharmadive
BioPharma Dive @biopharmadive
743 1 tweet
#2 @medscapeonc
Medscape Oncology @medscapeonc
461 2 tweets
#3 @conferencehype
Conference Hype @conferencehype
83 1 tweet

Top Tweets & Trial Discussion

Highest-impact physician posts by disease area. Expand the Clinical Trials block to drill into trial-specific discussion — physician voices only, with media coverage shown (and labeled) only when no physician has posted yet.

🟣Myeloma & Plasma Cell Disorders46 tweets captured
@smbenlazar
Benlazar S M A @smbenlazar
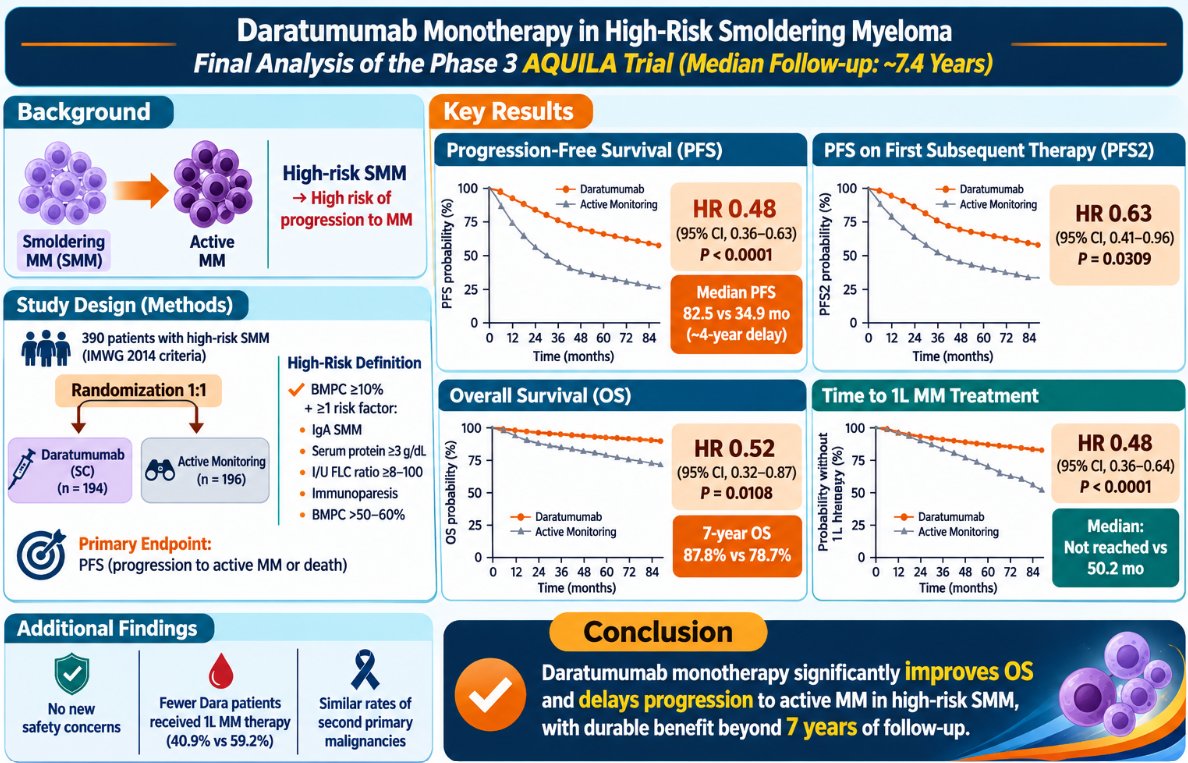
#ASH26 #MMSM Daratumumab monotherapy improves overall survival in patients with high-risk smoldering multiple myeloma: Final analyses of survival outcomes from the phase 3 AQUILA study https://t.co/MCKrBFVS0B https://t.co/vFMmUTmplR
👁 7.5K ❤ 35 🔁 9
@HenrychihangFu1
Henry C Fung| MM, lymphoma, leukemia & CART @HenrychihangFu1
🧬 CAR-T abstracts I won’t miss at #ASH26! My 10 picks across myeloma and lymphoma—from longer follow-up and earlier-line treatment to dual targeting, allogeneic platforms, and CAR-T cells generated in vivo. The questions I’ll be watching: 🔹 Durability: How long do remissions last—and how much time can patients spend free of treatment? 🔹 Earlier treatment: Which patients benefit most from moving CAR-T forward? 🔹 Dual targeting: Can BCMA × GPRC5D or CD19/CD20 targeting reduce relapse? 🔹 Safety: Can we prevent delayed neurotoxicity while preserving disease control? 🔹 Access: Can allogeneic and in vivo approaches make CAR-T available to more patients? Response rates attract attention. Durability, safety, patient selection, and study design determine clinical value. Small cohorts, subgroup analyses, and historical comparisons deserve careful interpretation. These are my current picks; late-breaking abstracts may add more! 🎺 Jazz, crawfish, Hurricanes—and plenty of CAR-T discussion. See you in New Orleans! #ASH26 #CART #MultipleMyeloma #Lymphoma #HemeTwitter
👁 4.4K ❤ 55 🔁 16
@Abdallah81MD
Al-Ola A Abdallah MD (USMIRC) @Abdallah81MD
🚨 The final AQUILA analysis #ASH2026 showed that early daratumumab improved both progression-free survival and overall survival in high-risk smoldering myeloma. At 7 years, overall survival was 87.8% with daratumumab versus 78.7% with active monitoring (HR 0.52). Here in Kansas this has been the SOC! #mmsm #myeloma #MedEd #USMIRC @USMIRCNEWS @Larvol @USMIRCNEWS @US_HMC @oncodaily @OpenMedKate
👁 2.4K ❤ 23 🔁 8
@SurbhiSidanaMD
Surbhi Sidana, MD @SurbhiSidanaMD
So proud of our group! #ASH26 #ASHKudos #mmsm #leuksm #cartsm #lymsm https://t.co/dfrRqSiERp
👁 2.1K ❤ 40 🔁 1
@kansagraMD
Ankit kansagra @kansagraMD
One shot a month, one step-up dose, dex only in the first 2 cycles. And no transplant planned. That's Arm G of MajesTEC-5 (GMMG-HD10/DSMM-XX), the first data for a trispecific in NDMM, oral at #ASH26 (abstract 110). Ramantamig hits BCMA and GPRC5D through CD3, given with dara-len for 6 cycles, then ram-dara maintenance in place of ASCT. Quick thoughts - 21 TE-NDMM pts, median age 61. ORR 100%, ≥CR 81%, and all 20 MRD-evaluable pts were MRD-neg (10^-5, NGF) after just 3 cycles - CRS in 17/18 who didn't get prophylactic toci, all grade 1-2. None in the 3 who did. No ICANS, no ataxia - The GPRC5D tax is still there but mild: taste changes 16/21, oral AEs 16/21, none above gr 2. 10 pts lost 5-20% of body weight - Only 3 gr 3 infections, nothing gr 4+. But 15/21 had an IgG <400 and 18/21 got IgG replacement - Stem cell collection after C3 worked, median 5.6 x10^6/kg in 19 pts Dual antigen targeting upfront is the most direct shot we have at antigen escape, and a Q4W schedule with almost no steroid is something community sites could actualy run. 21 pts, 7.1 mo median f/u, only 3 high-risk by IMS-IMWG. MRD-neg at 10^-5 is near the ceiling for every quad-plus-immunotherapy arm now, so it can't seperate regimens anymore. What matters is durability without ASCT, and only the maintenance readout tells us that. There's a practical cost too. IVIG in nearly every pt, for who knows how long, is chair time and money we tend to wave off in early phase data. Nice work by Marc Raab, Leo Rasche, Hermann Einsele and the GMMG/DSMM team. Exciting days ahead for all. #mmsm #MultipleMyeloma #ASH26
👁 1.8K ❤ 24 🔁 6
@mbeksac56
Meral Beksac @mbeksac56
#ASH26 abstracts are out today @FrancescoMaura4 🙏for approaching to more precise targeted immunoRx 934 TREATMENT-NAÏVE GPRC5D NEGATIVITY PREDICTS PRIMARY REFRACTORINESS TO ANTI- GPRC5D T-CELL REDIRECTING THERAPIES An approach need to implement ASAP @MM_Hub @RascheLeo @NBahlis https://t.co/0JXPNfPxAN
👁 1.8K ❤ 27 🔁 5
Clinical Trials17 trials with discussion
AQUILA Daratumumab monotherapy vs active monitoring · High-risk smoldering MM (Phase 3, final survival analysis) Full trial profile →
11.6K imp  ·  3 tweets ▼
@smbenlazar
Benlazar S M A @smbenlazar
#ASH26 #MMSM Daratumumab monotherapy improves overall survival in patients with high-risk smoldering multiple myeloma: Final analyses of survival outcomes from the phase 3 AQUILA study https://t.co/MCKrBFVS0B https://t.co/vFMmUTmplR
👁 7.5K ❤ 35 🔁 9
@Abdallah81MD
Al-Ola A Abdallah MD (USMIRC) @Abdallah81MD
🚨 The final AQUILA analysis #ASH2026 showed that early daratumumab improved both progression-free survival and overall survival in high-risk smoldering myeloma. At 7 years, overall survival was 87.8% with daratumumab versus 78.7% with active monitoring (HR 0.52). Here in Kansas this has been the SOC! #mmsm #myeloma #MedEd #USMIRC @USMIRCNEWS @Larvol @USMIRCNEWS @US_HMC @oncodaily @OpenMedKate
👁 2.4K ❤ 23 🔁 8
@HenrychihangFu1
Henry C Fung| MM, lymphoma, leukemia & CART @HenrychihangFu1
More to watch at #ASH26! 📅 My schedule is attached. Thank you for flagging two important omissions from my preview: 🔹 MonumenTAL-6: Phase III Tec–Tal and Tal–Pom—PFS and OS benefits versus EPd/PVd. Major results, with safety and longer follow-up essential to interpretation. 🔹 AQUILA: Final survival analysis in the enrolled high-risk SMM population—7-year OS 87.8% vs 78.7% with daratumumab versus monitoring. Important findings to examine alongside risk definitions and treatment after progression. Two additional highlights: 🔹 PERSEUS: Long-term MRD outcomes and MRD-guided daratumumab maintenance discontinuation. 🔹 MajesTEC-5, Arm G: Early results with ramantamig, a BCMA × GPRC5D × CD3 trispecific, plus daratumumab/lenalidomide in transplant-eligible, newly diagnosed MM, followed by ramantamig/daratumumab maintenance without planned ASCT. This is a separate cohort from the original teclistamab-based cohorts incorporating ASCT. An increasingly crowded—and exciting—myeloma agenda in New Orleans! 🎷🦞🍹 📅 SEE THE SCHEDULE BELOW ⬇️ Our selected abstracts, dates, times, and locations—all times CST (New Orleans local time). Dr. Fun + G #MultipleMyeloma #mmsm #HemeTwitter
👁 1.7K ❤ 15 🔁 7
MajesTEC-5 (Arm G) Ramantamig (BCMA×GPRC5D×CD3 trispecific) + dara-len · Transplant-eligible NDMM, no planned ASCT
3.5K imp  ·  2 tweets ▼
@kansagraMD
Ankit kansagra @kansagraMD
One shot a month, one step-up dose, dex only in the first 2 cycles. And no transplant planned. That's Arm G of MajesTEC-5 (GMMG-HD10/DSMM-XX), the first data for a trispecific in NDMM, oral at #ASH26 (abstract 110). Ramantamig hits BCMA and GPRC5D through CD3, given with dara-len for 6 cycles, then ram-dara maintenance in place of ASCT. Quick thoughts - 21 TE-NDMM pts, median age 61. ORR 100%, ≥CR 81%, and all 20 MRD-evaluable pts were MRD-neg (10^-5, NGF) after just 3 cycles - CRS in 17/18 who didn't get prophylactic toci, all grade 1-2. None in the 3 who did. No ICANS, no ataxia - The GPRC5D tax is still there but mild: taste changes 16/21, oral AEs 16/21, none above gr 2. 10 pts lost 5-20% of body weight - Only 3 gr 3 infections, nothing gr 4+. But 15/21 had an IgG <400 and 18/21 got IgG replacement - Stem cell collection after C3 worked, median 5.6 x10^6/kg in 19 pts Dual antigen targeting upfront is the most direct shot we have at antigen escape, and a Q4W schedule with almost no steroid is something community sites could actualy run. 21 pts, 7.1 mo median f/u, only 3 high-risk by IMS-IMWG. MRD-neg at 10^-5 is near the ceiling for every quad-plus-immunotherapy arm now, so it can't seperate regimens anymore. What matters is durability without ASCT, and only the maintenance readout tells us that. There's a practical cost too. IVIG in nearly every pt, for who knows how long, is chair time and money we tend to wave off in early phase data. Nice work by Marc Raab, Leo Rasche, Hermann Einsele and the GMMG/DSMM team. Exciting days ahead for all. #mmsm #MultipleMyeloma #ASH26
👁 1.8K ❤ 24 🔁 6
@HenrychihangFu1
Henry C Fung| MM, lymphoma, leukemia & CART @HenrychihangFu1
More to watch at #ASH26! 📅 My schedule is attached. Thank you for flagging two important omissions from my preview: 🔹 MonumenTAL-6: Phase III Tec–Tal and Tal–Pom—PFS and OS benefits versus EPd/PVd. Major results, with safety and longer follow-up essential to interpretation. 🔹 AQUILA: Final survival analysis in the enrolled high-risk SMM population—7-year OS 87.8% vs 78.7% with daratumumab versus monitoring. Important findings to examine alongside risk definitions and treatment after progression. Two additional highlights: 🔹 PERSEUS: Long-term MRD outcomes and MRD-guided daratumumab maintenance discontinuation. 🔹 MajesTEC-5, Arm G: Early results with ramantamig, a BCMA × GPRC5D × CD3 trispecific, plus daratumumab/lenalidomide in transplant-eligible, newly diagnosed MM, followed by ramantamig/daratumumab maintenance without planned ASCT. This is a separate cohort from the original teclistamab-based cohorts incorporating ASCT. An increasingly crowded—and exciting—myeloma agenda in New Orleans! 🎷🦞🍹 📅 SEE THE SCHEDULE BELOW ⬇️ Our selected abstracts, dates, times, and locations—all times CST (New Orleans local time). Dr. Fun + G #MultipleMyeloma #mmsm #HemeTwitter
👁 1.7K ❤ 15 🔁 7
MonumenTAL-6 Talquetamab + teclistamab, and talquetamab + pomalidomide, vs EPd/PVd · R/R MM after 1–4 prior lines (Phase 3) Full trial profile →
2.6K imp  ·  2 tweets ▼
@HenrychihangFu1
Henry C Fung| MM, lymphoma, leukemia & CART @HenrychihangFu1
More to watch at #ASH26! 📅 My schedule is attached. Thank you for flagging two important omissions from my preview: 🔹 MonumenTAL-6: Phase III Tec–Tal and Tal–Pom—PFS and OS benefits versus EPd/PVd. Major results, with safety and longer follow-up essential to interpretation. 🔹 AQUILA: Final survival analysis in the enrolled high-risk SMM population—7-year OS 87.8% vs 78.7% with daratumumab versus monitoring. Important findings to examine alongside risk definitions and treatment after progression. Two additional highlights: 🔹 PERSEUS: Long-term MRD outcomes and MRD-guided daratumumab maintenance discontinuation. 🔹 MajesTEC-5, Arm G: Early results with ramantamig, a BCMA × GPRC5D × CD3 trispecific, plus daratumumab/lenalidomide in transplant-eligible, newly diagnosed MM, followed by ramantamig/daratumumab maintenance without planned ASCT. This is a separate cohort from the original teclistamab-based cohorts incorporating ASCT. An increasingly crowded—and exciting—myeloma agenda in New Orleans! 🎷🦞🍹 📅 SEE THE SCHEDULE BELOW ⬇️ Our selected abstracts, dates, times, and locations—all times CST (New Orleans local time). Dr. Fun + G #MultipleMyeloma #mmsm #HemeTwitter
👁 1.7K ❤ 15 🔁 7
@HadidiSamer
Samer Al Hadidi, MD,MS,FACP @HadidiSamer
My top @ASH_hematology #ASH26 abstracts for plasma cell disorders including myeloma and AL amyloidosis #mmsm @utswcancer 1️⃣MonumenTAL-6: Tec+Tal and Tal+Pom vs EPd/PVd ➡️Phase III, RRMM after 1–4 prior lines, all exposed to anti-CD38 and lenalidomide (80% anti-CD38-refractory) ➡️n=838; median FU: 13.4 mo ➡️Tec+Tal improved PFS HR 0.11; 12-mo PFS 89% vs 30%) and OS (HR 0.38; 12-mo OS 91% vs 80%). Tal+Pom also better than control arm (PFS HR 0.27, OS HR 0.55). 🛑Grade 3/4 infections were 312% with Tec+Tal vs 25% with control (92% of patients needed IVIG), ICANS 6%, taste changes 76% and weight loss 41% (Only 6% stopped treatment for AEs) Time limited therapy with dual targeting in pts after anti-CD38/len failure
👁 900 ❤ 14 🔁 7
🔵Lymphoma & CLL35 tweets captured
@smbenlazar
Benlazar S M A @smbenlazar
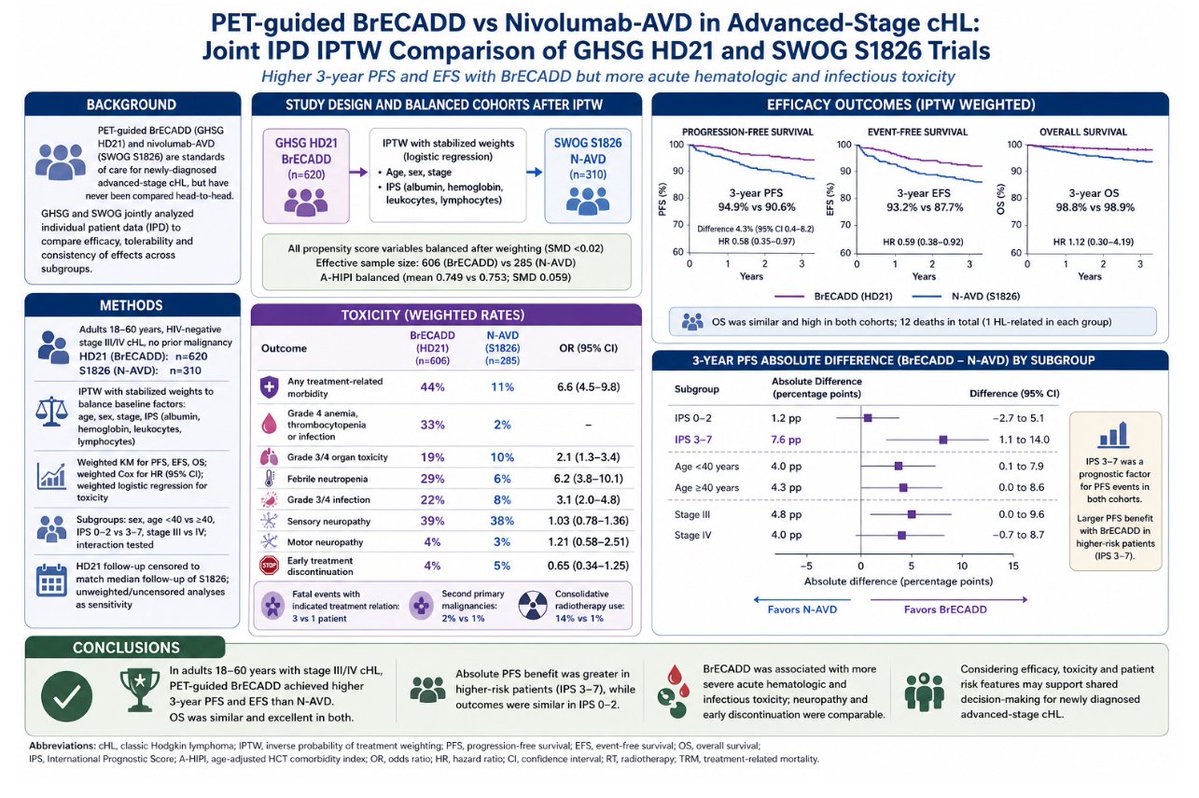
#ASH26 #HL #lymsm Individual patient data comparison of BrECADD and nivolumab-AVD in advanced-stage classic Hodgkin lymphoma: A joint GHSG/SWOG analysis of HD21 and S1826 https://t.co/6IMEMYi1a5 https://t.co/OYYDwnjJ4X
👁 5.6K ❤ 33 🔁 11
@HayderSaeed_MD
Hayder Saeed, MD @HayderSaeed_MD
CAR T made inside the patient, no lymphodepletion. First-in-human in vivo CD19 CAR T (SNC116, investigational), R/R B-NHL, n=6: ORR 5/6, CR 4/6, no grade ≥3 CRS/ICANS. Tiny, early. If it holds, CAR T logistics change. #ASH26 #CARTcells #lymsm https://t.co/kUs5hOL4Z5
👁 2.5K ❤ 20 🔁 4
@tobyeyre82
Toby A. Eyre @tobyeyre82
Looking forward to presenting the full results in the 1L BTKi MCL session on the monday evening! Do come along at #ASH2026 #MCL https://t.co/wxHN66oMOB
👁 2.3K ❤ 38 🔁 7
@mshadman
Mazyar Shadman, MD MPH @mshadman
TTNT is a very relevant endpoint in #CLL but it is surprising to see that PFS data is not even reported in some #ASH26 abstracts!
👁 1.8K ❤ 8 🔁 2
@nilalbiol
Nil Albiol @nilalbiol
🏆 Honored that our study on ARI-0001 (varnimcabtagene autoleucel) in high-risk #CLL and #RichterTransformation has been selected for an oral presentation at #ASH26 in📍New Orleans, and recognized with an ASH Abstract Achievement. @ValentinOrtizMD @JulioDelgadoHem
👁 1.5K ❤ 44 🔁 10
@majorajay
Ajay Major, MD, MBA @majorajay
Love working with this diverse group of #lymsm clinician-scientists at @CUAnschutz @CUHematology! We are looking forward to seeing you all at @ASH_hematology #ASH26. cc @mana1981 @BradHaverkos @StevenBairMD @cduarte8490 https://t.co/DJf6l3IpgX
👁 987 ❤ 7 🔁 2
Clinical Trials15 trials with discussion
SNC116 In vivo CD19 CAR-T, no lymphodepletion · R/R B-NHL (first-in-human)
4.1K imp  ·  2 tweets ▼
@HayderSaeed_MD
Hayder Saeed, MD @HayderSaeed_MD
CAR T made inside the patient, no lymphodepletion. First-in-human in vivo CD19 CAR T (SNC116, investigational), R/R B-NHL, n=6: ORR 5/6, CR 4/6, no grade ≥3 CRS/ICANS. Tiny, early. If it holds, CAR T logistics change. #ASH26 #CARTcells #lymsm https://t.co/kUs5hOL4Z5
👁 2.5K ❤ 20 🔁 4
@kansagraMD
Ankit kansagra @kansagraMD
6 pts. No lymphodepletion. No manufacturing. 4 CRs. That's SNC116, an in vivo CD19 CAR T from the National Cancer Center in Beijing and Simnova, an oral at #ASH26. @HayderSaeed_MD flagged it today and it's worth the read for anyone running a cell therapy program, not just the lymphoma folks. One IV infusion of a lentiviral vector that finds the pt's own T cells. Vector nearly gone from blood by 24 hrs, CAR T cells peaking around day 14-17, still detectable out to 90 days with stem cell-like and central memory phenotypes. ORR 5/6, CR 4/6, including a CR at the lowest dose. Two pts deepened their response between month 1 and month 3. Grade 1 CRS in 2, around day 10, each settled with a single dose of toci. No ICANS, no DLTs. Myeloma already has in vivo BCMA data with ESO-T01, so this isn't a one-off. Different construct, different target, same concept holding up. the real bottleneck in CAR-T isn't the cells, it's everythng around them. Apheresis slots, vein-to-vein time, bridging, flu-cy, the pt who progresses while waiting for product. Take out manufacturing and lymphodepletion and a lot of that goes away. That's an operational win before it's a scientific one. What we all want to know 1. Durability. n=6, median f/u 5.2 mo. No progression yet is encouraging, not proof 2. Dose vs exposure. Peak CAR T levels varied roughly 100-fold across pts. Without a product we release in a lab, how do we predict who expands and who doesn't? 3. Long term vector safety. An integrating lentivirus given straight into the body needs a real plan for off-target transduction and years of monitering 4. CRS timing. Onset around day 10, not day 1-2. Outpatient monitoring plans would need to be built around that Early, tiny, single-country, sponsor co-authored. But if this holds, the conversation about who can get CAR-T, and where, changes completely. #CART #CellTherapy #ASH26
👁 1.6K ❤ 10 🔁 5
🩸Acute & Chronic Leukemia23 tweets captured
@TalhaBadarMD
Talha Badar @TalhaBadarMD
🩸 #ASH26 | #AML Abstracts to Watch (Oral) My current list of 11 AML abstracts to watch at #ASH2026 👇 #leusm A mix of potentially practice-changing frontline trials, menin inhibitors, MRD, and novel approaches in both younger and older patients. 1️⃣ Ivosidenib + intensive chemotherapy in newly diagnosed IDH1-mutated AML HOVON150/AMLSG29-18, phase 3 Superior event-free survival 📄 Abstract 0001, Press Program 📅 Sun Dec 13 | 7:00 AM CT ⚠️ Oral/plenary slot not yet confirmed 🔗 https://t.co/HAiAem9IzK 2️⃣ Gilteritinib vs midostaurin in newly diagnosed FLT3-mutated AML Subgroup analysis from HOVON156/AMLSG28-18/pasha 📄 Abstract 56 | Session 615 📅 Sat Dec 12 | 9:30 AM 📍 Great Hall BC 🔗 https://t.co/vnNwomzMZ7 3️⃣ Bleximenib in R/R AML with KMT2A rearrangements or NPM1 mutations Topline results from phase 2 CAMELOT-1 📄 Abstract 661 | Session 616 📅 Sun Dec 13 | 4:30 PM 📍 Hall B 🔗 https://t.co/Das1necevM 4️⃣ Cladribine + LDAC + venetoclax vs intensive chemotherapy (7+3) Patients ≥60 years with newly diagnosed AML 📄 Abstract 57 | Session 615 📅 Sat Dec 12 | 9:30 AM 📍 Great Hall BC 🔗 https://t.co/vuvS9OfmdF 5️⃣ Can we stop HMA + venetoclax? Discontinuation of hypomethylating agent + venetoclax in newly diagnosed AML with undetectable MRD 📄 Abstract 1009 | Session 617 📅 Mon Dec 14 | 4:30 PM 📍 Great Hall AD 🔗 https://t.co/MiP4Z7F5BL 6️⃣ Sonrotoclax + azacitidine across ELN 2024 genetic risk groups Treatment-naive AML unfit for intensive chemotherapy 📄 Abstract 60 | Session 615 📅 Sat Dec 12 | 9:30 AM 📍 Great Hall BC 🔗 https://t.co/gU3WGMcyAm 7️⃣ Venetoclax + 3-day multi-frequency decitabine vs AZA + VEN Older adults with newly diagnosed AML, updated randomized results 📄 Abstract 1012 | Session 617 📅 Mon Dec 14 | 4:30 PM 📍 Great Hall AD 🔗 https://t.co/L7cHhkZ4IF 8️⃣ Whole-genome-informed AML MRD testing Prospective multicenter validation, MEASURE 📄 Abstract 390 | Session 619 📅 Sat Dec 12 | 4:00 PM 📍 Great Hall AD 🔗 https://t.co/XPb38cdFAW 9️⃣ VEN + AZA vs daunorubicin + cytarabine induction Young adults with ELN adverse-risk AML, phase 2b 📄 Abstract 1010 | Session 617 📅 Mon Dec 14 | 4:30 PM 📍 Great Hall AD 🔗 https://t.co/T8URfhrzzg 🔟 Ziftomenib + gilteritinib in R/R NPM1- and FLT3-co-mutated AML First results from phase 1 KOMET-008 📄 Abstract 66 | Session 617 📅 Sat Dec 12 | 9:30 AM 📍 Great Hall AD 🔗 https://t.co/nTnyI2myj8 11/12 1️⃣1️⃣ FLAI-G frontline in younger FLT3-mutated AML Fludarabine + high-dose cytarabine + idarubicin + gilteritinib First interim analysis, phase 2 GIMEMA AML2924 📄 Abstract 903 | Session 617 📅 Mon Dec 14 | 2:45 PM 📍 Great Hall BC 🔗 https://t.co/OwFJZBjAnr Lots to watch at #ASH26 in AML. Particularly interested in the randomized frontline data, evolving role of menin inhibition, MRD-guided treatment decisions, and whether lower-intensity approaches can continue challenging conventional intensive chemotherapy. Which AML abstracts are on your must-see list? #AML #Leukemia #ASH26
👁 5.9K ❤ 79 🔁 23
@smbenlazar
Benlazar S M A @smbenlazar
#ASH26 #AML #leusm Cladribine with low dose cytarabine plus venetoclax compared with intensive chemotherapy with 7+3 for patients aged ≥ 60 years with newly diagnosed AML https://t.co/WoRyTU1Dln https://t.co/QIMGeeP0yu
👁 5.0K ❤ 74 🔁 25
@GomezDLeonMD
Andres Gomez @GomezDLeonMD
In ALL there is plenty of room to study chemo plus novel agents while everyone else is busy with immunotherapy, particularly in LMICs. TACL+ Ven at #ASH26 poster 5079 #Leusm https://t.co/Ohp1Vi9Wkp https://t.co/at0wR3cqnq
👁 1.2K ❤ 21 🔁 2
@mtmdphd
Mike Thompson, MD, PhD, FASCO @mtmdphd
TP53-mutated acute myeloid leukemia is associated with increased pretreatment infection and infection-related treatment omission [Mon, Dec 14, 2026] Xiaojing Lin Sr et al. #ASH26 Abs 5130 https://t.co/q41i5ktfIa #IDonc #AMLsm #leusm
👁 591 ❤ 4 🔁 1
@SantiagoFS_
SFS @SantiagoFS_
Our #ASH2026 abstract is now online How does limited access to molecular testing affect AML risk stratification and outcomes? We explored this question using 10 years of real-world data from Colombia. 🇨🇴 Abstract #4579 https://t.co/tgXAl2juYJ
👁 207 ❤ 3 🔁 2
@MedscapeOnc
Medscape Oncology @MedscapeOnc
🧬 Choosing the right TKI in CML starts with the right data. Explore first-line selection, navigate resistance & translate mutational analysis into therapeutic decisions with coordinated team-based care. 🎯 Sharpen your CML strategy—register today! https://t.co/MD7mXZjcsr #ASH26 https://t.co/DCpecPDgHz
👁 260 ❤ 2 🔁 0
Clinical Trials5 trials with discussion
HOVON156 / AMLSG28-18 Gilteritinib vs midostaurin · Newly diagnosed FLT3-mutated AML (subgroup analysis)
7.7K imp  ·  2 tweets ▼
@TalhaBadarMD
Talha Badar @TalhaBadarMD
🩸 #ASH26 | #AML Abstracts to Watch (Oral) My current list of 11 AML abstracts to watch at #ASH2026 👇 #leusm A mix of potentially practice-changing frontline trials, menin inhibitors, MRD, and novel approaches in both younger and older patients. 1️⃣ Ivosidenib + intensive chemotherapy in newly diagnosed IDH1-mutated AML HOVON150/AMLSG29-18, phase 3 Superior event-free survival 📄 Abstract 0001, Press Program 📅 Sun Dec 13 | 7:00 AM CT ⚠️ Oral/plenary slot not yet confirmed 🔗 https://t.co/HAiAem9IzK 2️⃣ Gilteritinib vs midostaurin in newly diagnosed FLT3-mutated AML Subgroup analysis from HOVON156/AMLSG28-18/pasha 📄 Abstract 56 | Session 615 📅 Sat Dec 12 | 9:30 AM 📍 Great Hall BC 🔗 https://t.co/vnNwomzMZ7 3️⃣ Bleximenib in R/R AML with KMT2A rearrangements or NPM1 mutations Topline results from phase 2 CAMELOT-1 📄 Abstract 661 | Session 616 📅 Sun Dec 13 | 4:30 PM 📍 Hall B 🔗 https://t.co/Das1necevM 4️⃣ Cladribine + LDAC + venetoclax vs intensive chemotherapy (7+3) Patients ≥60 years with newly diagnosed AML 📄 Abstract 57 | Session 615 📅 Sat Dec 12 | 9:30 AM 📍 Great Hall BC 🔗 https://t.co/vuvS9OfmdF 5️⃣ Can we stop HMA + venetoclax? Discontinuation of hypomethylating agent + venetoclax in newly diagnosed AML with undetectable MRD 📄 Abstract 1009 | Session 617 📅 Mon Dec 14 | 4:30 PM 📍 Great Hall AD 🔗 https://t.co/MiP4Z7F5BL 6️⃣ Sonrotoclax + azacitidine across ELN 2024 genetic risk groups Treatment-naive AML unfit for intensive chemotherapy 📄 Abstract 60 | Session 615 📅 Sat Dec 12 | 9:30 AM 📍 Great Hall BC 🔗 https://t.co/gU3WGMcyAm 7️⃣ Venetoclax + 3-day multi-frequency decitabine vs AZA + VEN Older adults with newly diagnosed AML, updated randomized results 📄 Abstract 1012 | Session 617 📅 Mon Dec 14 | 4:30 PM 📍 Great Hall AD 🔗 https://t.co/L7cHhkZ4IF 8️⃣ Whole-genome-informed AML MRD testing Prospective multicenter validation, MEASURE 📄 Abstract 390 | Session 619 📅 Sat Dec 12 | 4:00 PM 📍 Great Hall AD 🔗 https://t.co/XPb38cdFAW 9️⃣ VEN + AZA vs daunorubicin + cytarabine induction Young adults with ELN adverse-risk AML, phase 2b 📄 Abstract 1010 | Session 617 📅 Mon Dec 14 | 4:30 PM 📍 Great Hall AD 🔗 https://t.co/T8URfhrzzg 🔟 Ziftomenib + gilteritinib in R/R NPM1- and FLT3-co-mutated AML First results from phase 1 KOMET-008 📄 Abstract 66 | Session 617 📅 Sat Dec 12 | 9:30 AM 📍 Great Hall AD 🔗 https://t.co/nTnyI2myj8 11/12 1️⃣1️⃣ FLAI-G frontline in younger FLT3-mutated AML Fludarabine + high-dose cytarabine + idarubicin + gilteritinib First interim analysis, phase 2 GIMEMA AML2924 📄 Abstract 903 | Session 617 📅 Mon Dec 14 | 2:45 PM 📍 Great Hall BC 🔗 https://t.co/OwFJZBjAnr Lots to watch at #ASH26 in AML. Particularly interested in the randomized frontline data, evolving role of menin inhibition, MRD-guided treatment decisions, and whether lower-intensity approaches can continue challenging conventional intensive chemotherapy. Which AML abstracts are on your must-see list? #AML #Leukemia #ASH26
👁 5.9K ❤ 79 🔁 23
@smbenlazar
Benlazar S M A @smbenlazar
#ASH26 #AML #leusm Subgroup analysis of gilteritinib versus midostaurin in newly diagnosed FLT3-mutated acute myeloid leukemia (FLT3mut+ AML): An explorative analysis from the HOVON156/AMLSG28-18/pasha trial https://t.co/xHV3FAHKVF https://t.co/fky5dIUlHo
👁 1.9K ❤ 25 🔁 5
HOVON150 / AMLSG29-18 Ivosidenib + intensive chemotherapy · Newly diagnosed IDH1-mutated AML (Phase 3)
5.9K imp  ·  1 tweet ▼
@TalhaBadarMD
Talha Badar @TalhaBadarMD
🩸 #ASH26 | #AML Abstracts to Watch (Oral) My current list of 11 AML abstracts to watch at #ASH2026 👇 #leusm A mix of potentially practice-changing frontline trials, menin inhibitors, MRD, and novel approaches in both younger and older patients. 1️⃣ Ivosidenib + intensive chemotherapy in newly diagnosed IDH1-mutated AML HOVON150/AMLSG29-18, phase 3 Superior event-free survival 📄 Abstract 0001, Press Program 📅 Sun Dec 13 | 7:00 AM CT ⚠️ Oral/plenary slot not yet confirmed 🔗 https://t.co/HAiAem9IzK 2️⃣ Gilteritinib vs midostaurin in newly diagnosed FLT3-mutated AML Subgroup analysis from HOVON156/AMLSG28-18/pasha 📄 Abstract 56 | Session 615 📅 Sat Dec 12 | 9:30 AM 📍 Great Hall BC 🔗 https://t.co/vnNwomzMZ7 3️⃣ Bleximenib in R/R AML with KMT2A rearrangements or NPM1 mutations Topline results from phase 2 CAMELOT-1 📄 Abstract 661 | Session 616 📅 Sun Dec 13 | 4:30 PM 📍 Hall B 🔗 https://t.co/Das1necevM 4️⃣ Cladribine + LDAC + venetoclax vs intensive chemotherapy (7+3) Patients ≥60 years with newly diagnosed AML 📄 Abstract 57 | Session 615 📅 Sat Dec 12 | 9:30 AM 📍 Great Hall BC 🔗 https://t.co/vuvS9OfmdF 5️⃣ Can we stop HMA + venetoclax? Discontinuation of hypomethylating agent + venetoclax in newly diagnosed AML with undetectable MRD 📄 Abstract 1009 | Session 617 📅 Mon Dec 14 | 4:30 PM 📍 Great Hall AD 🔗 https://t.co/MiP4Z7F5BL 6️⃣ Sonrotoclax + azacitidine across ELN 2024 genetic risk groups Treatment-naive AML unfit for intensive chemotherapy 📄 Abstract 60 | Session 615 📅 Sat Dec 12 | 9:30 AM 📍 Great Hall BC 🔗 https://t.co/gU3WGMcyAm 7️⃣ Venetoclax + 3-day multi-frequency decitabine vs AZA + VEN Older adults with newly diagnosed AML, updated randomized results 📄 Abstract 1012 | Session 617 📅 Mon Dec 14 | 4:30 PM 📍 Great Hall AD 🔗 https://t.co/L7cHhkZ4IF 8️⃣ Whole-genome-informed AML MRD testing Prospective multicenter validation, MEASURE 📄 Abstract 390 | Session 619 📅 Sat Dec 12 | 4:00 PM 📍 Great Hall AD 🔗 https://t.co/XPb38cdFAW 9️⃣ VEN + AZA vs daunorubicin + cytarabine induction Young adults with ELN adverse-risk AML, phase 2b 📄 Abstract 1010 | Session 617 📅 Mon Dec 14 | 4:30 PM 📍 Great Hall AD 🔗 https://t.co/T8URfhrzzg 🔟 Ziftomenib + gilteritinib in R/R NPM1- and FLT3-co-mutated AML First results from phase 1 KOMET-008 📄 Abstract 66 | Session 617 📅 Sat Dec 12 | 9:30 AM 📍 Great Hall AD 🔗 https://t.co/nTnyI2myj8 11/12 1️⃣1️⃣ FLAI-G frontline in younger FLT3-mutated AML Fludarabine + high-dose cytarabine + idarubicin + gilteritinib First interim analysis, phase 2 GIMEMA AML2924 📄 Abstract 903 | Session 617 📅 Mon Dec 14 | 2:45 PM 📍 Great Hall BC 🔗 https://t.co/OwFJZBjAnr Lots to watch at #ASH26 in AML. Particularly interested in the randomized frontline data, evolving role of menin inhibition, MRD-guided treatment decisions, and whether lower-intensity approaches can continue challenging conventional intensive chemotherapy. Which AML abstracts are on your must-see list? #AML #Leukemia #ASH26
👁 5.9K ❤ 79 🔁 23
CAMELOT-1 Bleximenib (menin inhibitor) · R/R AML with KMT2A rearrangement or NPM1 mutation (Phase 2)
5.9K imp  ·  1 tweet ▼
@TalhaBadarMD
Talha Badar @TalhaBadarMD
🩸 #ASH26 | #AML Abstracts to Watch (Oral) My current list of 11 AML abstracts to watch at #ASH2026 👇 #leusm A mix of potentially practice-changing frontline trials, menin inhibitors, MRD, and novel approaches in both younger and older patients. 1️⃣ Ivosidenib + intensive chemotherapy in newly diagnosed IDH1-mutated AML HOVON150/AMLSG29-18, phase 3 Superior event-free survival 📄 Abstract 0001, Press Program 📅 Sun Dec 13 | 7:00 AM CT ⚠️ Oral/plenary slot not yet confirmed 🔗 https://t.co/HAiAem9IzK 2️⃣ Gilteritinib vs midostaurin in newly diagnosed FLT3-mutated AML Subgroup analysis from HOVON156/AMLSG28-18/pasha 📄 Abstract 56 | Session 615 📅 Sat Dec 12 | 9:30 AM 📍 Great Hall BC 🔗 https://t.co/vnNwomzMZ7 3️⃣ Bleximenib in R/R AML with KMT2A rearrangements or NPM1 mutations Topline results from phase 2 CAMELOT-1 📄 Abstract 661 | Session 616 📅 Sun Dec 13 | 4:30 PM 📍 Hall B 🔗 https://t.co/Das1necevM 4️⃣ Cladribine + LDAC + venetoclax vs intensive chemotherapy (7+3) Patients ≥60 years with newly diagnosed AML 📄 Abstract 57 | Session 615 📅 Sat Dec 12 | 9:30 AM 📍 Great Hall BC 🔗 https://t.co/vuvS9OfmdF 5️⃣ Can we stop HMA + venetoclax? Discontinuation of hypomethylating agent + venetoclax in newly diagnosed AML with undetectable MRD 📄 Abstract 1009 | Session 617 📅 Mon Dec 14 | 4:30 PM 📍 Great Hall AD 🔗 https://t.co/MiP4Z7F5BL 6️⃣ Sonrotoclax + azacitidine across ELN 2024 genetic risk groups Treatment-naive AML unfit for intensive chemotherapy 📄 Abstract 60 | Session 615 📅 Sat Dec 12 | 9:30 AM 📍 Great Hall BC 🔗 https://t.co/gU3WGMcyAm 7️⃣ Venetoclax + 3-day multi-frequency decitabine vs AZA + VEN Older adults with newly diagnosed AML, updated randomized results 📄 Abstract 1012 | Session 617 📅 Mon Dec 14 | 4:30 PM 📍 Great Hall AD 🔗 https://t.co/L7cHhkZ4IF 8️⃣ Whole-genome-informed AML MRD testing Prospective multicenter validation, MEASURE 📄 Abstract 390 | Session 619 📅 Sat Dec 12 | 4:00 PM 📍 Great Hall AD 🔗 https://t.co/XPb38cdFAW 9️⃣ VEN + AZA vs daunorubicin + cytarabine induction Young adults with ELN adverse-risk AML, phase 2b 📄 Abstract 1010 | Session 617 📅 Mon Dec 14 | 4:30 PM 📍 Great Hall AD 🔗 https://t.co/T8URfhrzzg 🔟 Ziftomenib + gilteritinib in R/R NPM1- and FLT3-co-mutated AML First results from phase 1 KOMET-008 📄 Abstract 66 | Session 617 📅 Sat Dec 12 | 9:30 AM 📍 Great Hall AD 🔗 https://t.co/nTnyI2myj8 11/12 1️⃣1️⃣ FLAI-G frontline in younger FLT3-mutated AML Fludarabine + high-dose cytarabine + idarubicin + gilteritinib First interim analysis, phase 2 GIMEMA AML2924 📄 Abstract 903 | Session 617 📅 Mon Dec 14 | 2:45 PM 📍 Great Hall BC 🔗 https://t.co/OwFJZBjAnr Lots to watch at #ASH26 in AML. Particularly interested in the randomized frontline data, evolving role of menin inhibition, MRD-guided treatment decisions, and whether lower-intensity approaches can continue challenging conventional intensive chemotherapy. Which AML abstracts are on your must-see list? #AML #Leukemia #ASH26
👁 5.9K ❤ 79 🔁 23
🫀Classical (Benign) Hematology9 tweets captured
⬜Other / Multi-Disease22 tweets captured
@AnasOdeh07
Anas Odeh @AnasOdeh07
Grateful that 8 of our abstracts were accepted for #ASH26! I’ll present 2 posters on Dec 13 (6-8 PM), including one honored with an ASH Abstract Achievement Award. I’ll also be at ASH-a-Palooza. Looking forward to connecting in New Orleans! #ASHTrainee https://t.co/nvTHL6gOU8
👁 1.3K ❤ 18 🔁 1
@AshKishtagari
Ashwin Kishtagari, MD @AshKishtagari
Going to #ASH26, and the news I'm happiest about isn't mine. Three IM residents I mentor, Akshay Aluri, Michael Zargari and Pranay Shettywarangale, each won an ASH Abstract Achievement Award! So proud! 🧵1/4 @VUMCDiscoveries @jordanberlin5 https://t.co/D8So58ZLhn
👁 1.2K ❤ 36 🔁 5
@Farah_Yassine_
Farah Yassine @Farah_Yassine_
Another @ASH_hematology Abstract Achievement Award and another reason to look forward to #ASH26!!! 🎉 https://t.co/hDAtDCXloR
👁 1.0K ❤ 23 🔁 1
@thisisJamesD
James Davis, PharmD, BCOP @thisisJamesD
#nerdalert 🤓! Catch my oral abstract at #ASH26. I'll be presenting our consortium's research investigating tec/dara step-up dosing. Presentation is Monday Dec 14th . https://t.co/RTN8mkA6Dd We attempt to answer the following questions...🧵 https://t.co/6yNBHDzAX2
👁 824 ❤ 25 🔁 4
@BonellPatinoE
Bonell Patiño E @BonellPatinoE
Excited to share three projects from the Wiita Lab that we'll be presenting as posters at #ASH26! Looking forward to sharing our work, connecting with colleagues, and discussing exciting advances in immunotherapy. Hope to see you in New Orleans! https://t.co/14uB4UESc3
👁 712 ❤ 15 🔁 0
@mike_dickinson1
Michael Dickinson @mike_dickinson1
#ASH26 abstracts are out. Always good to go through the new stuff. But OMG could they make the web interface any more clunky? Somehow it gets worse year on year...
👁 696 ❤ 9 🔁 0

Slides & Infographics by Trial

Slides, abstract screenshots and infographics shared by the hematology community, organized by clinical trial and newest first within each — swipe or use the arrows to browse. Tap "View OCR Text" for a full-text transcription of any slide. Click a card to open the original post.

AQUILA

3 slides Full trial profile →

EXCALIBER-RRMM

2 slides Full trial profile →

General Conference Content

71 slides
KOL Pulse  ·  ASH 2026 Pre-Conference Intelligence
Data reflects curated, approved content only. Impressions update as engagement enrichment runs.
Tweets are verbatim from X/Twitter. KOL Pulse does not editorialize tweet content.