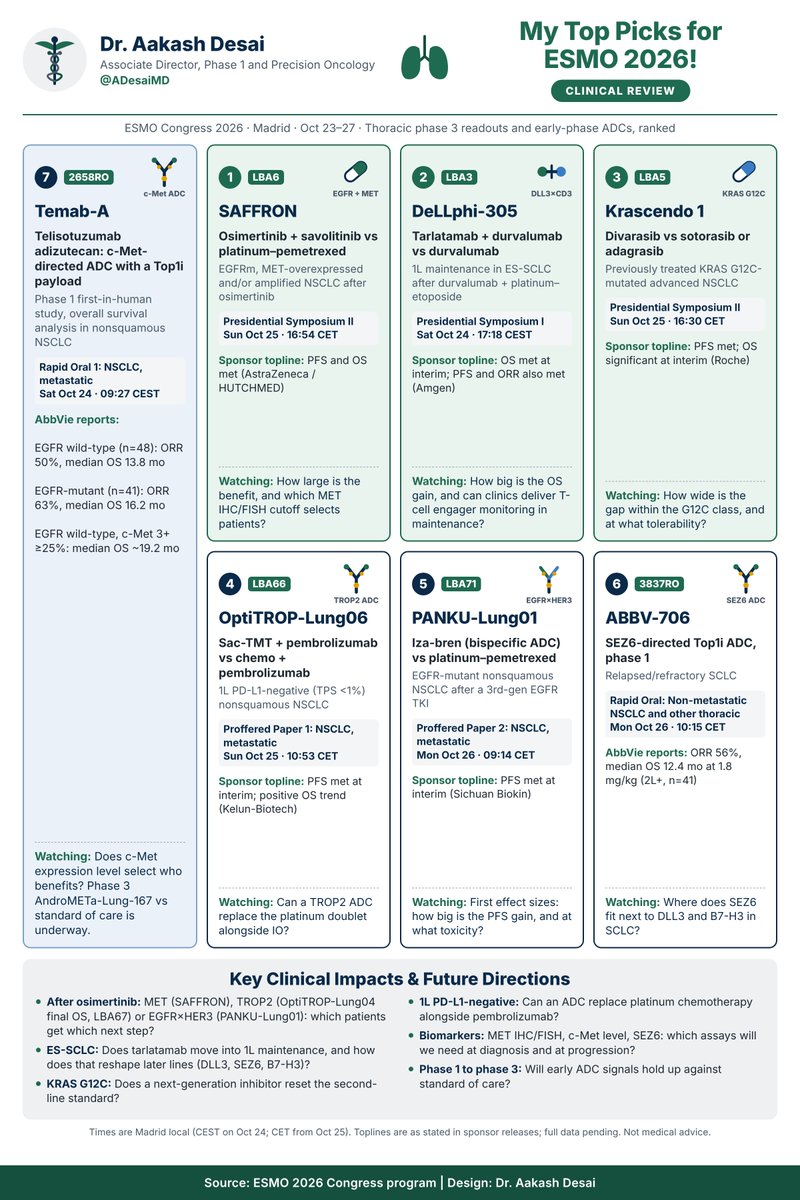
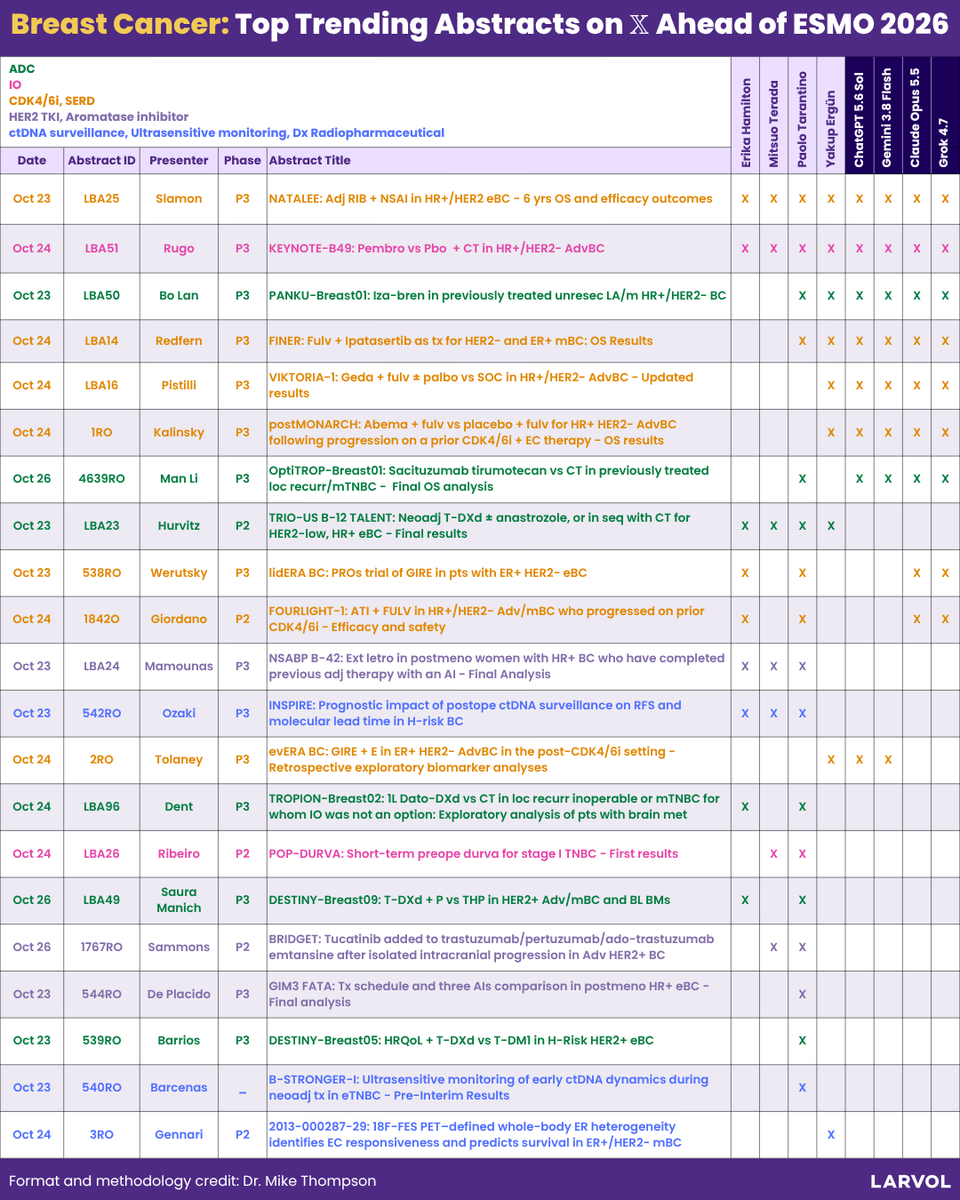
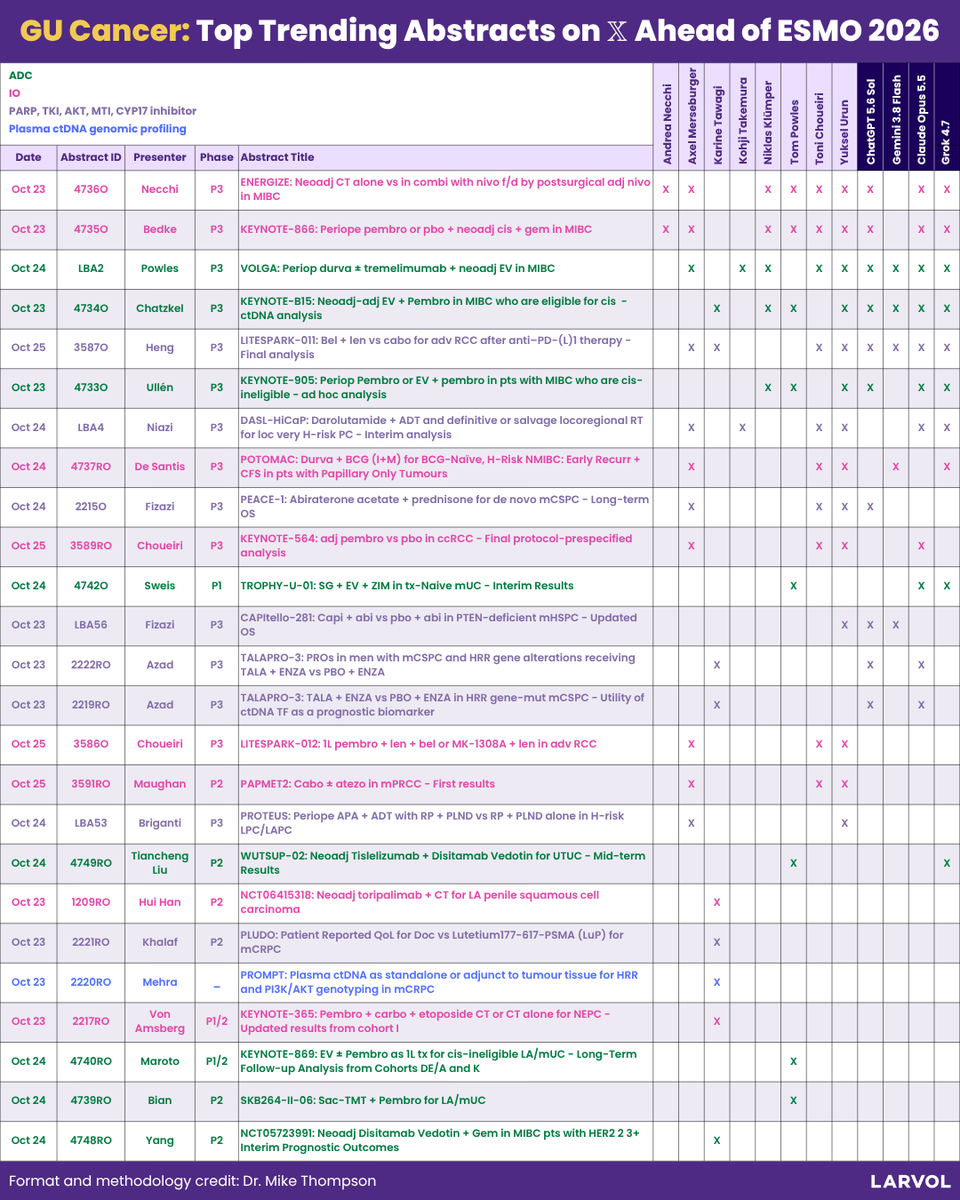
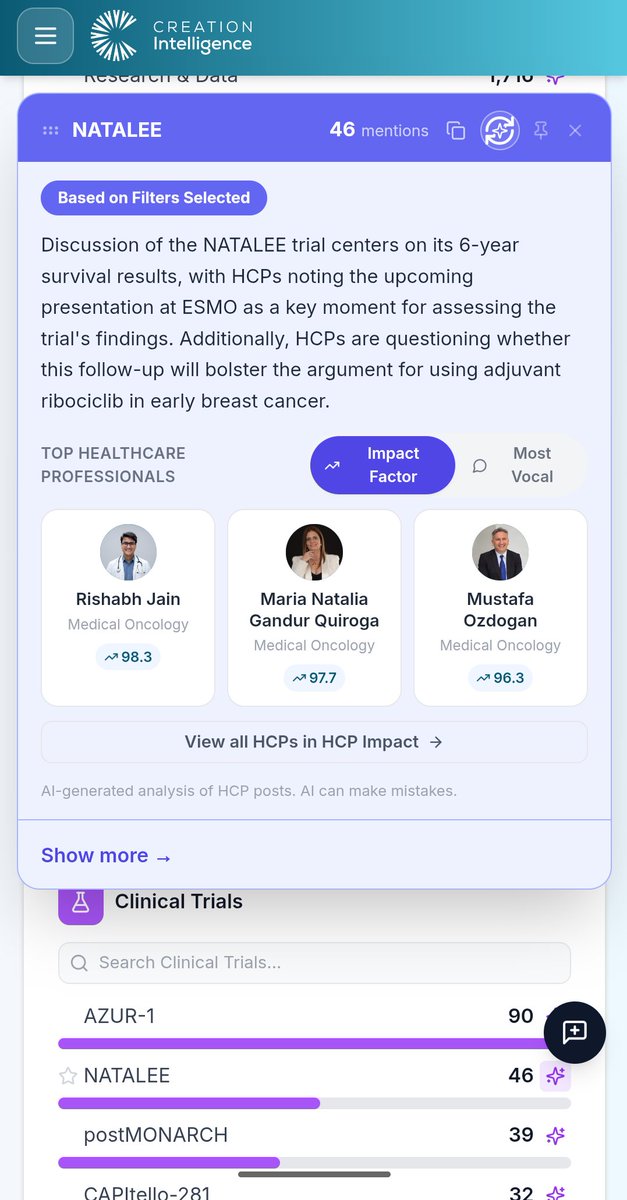
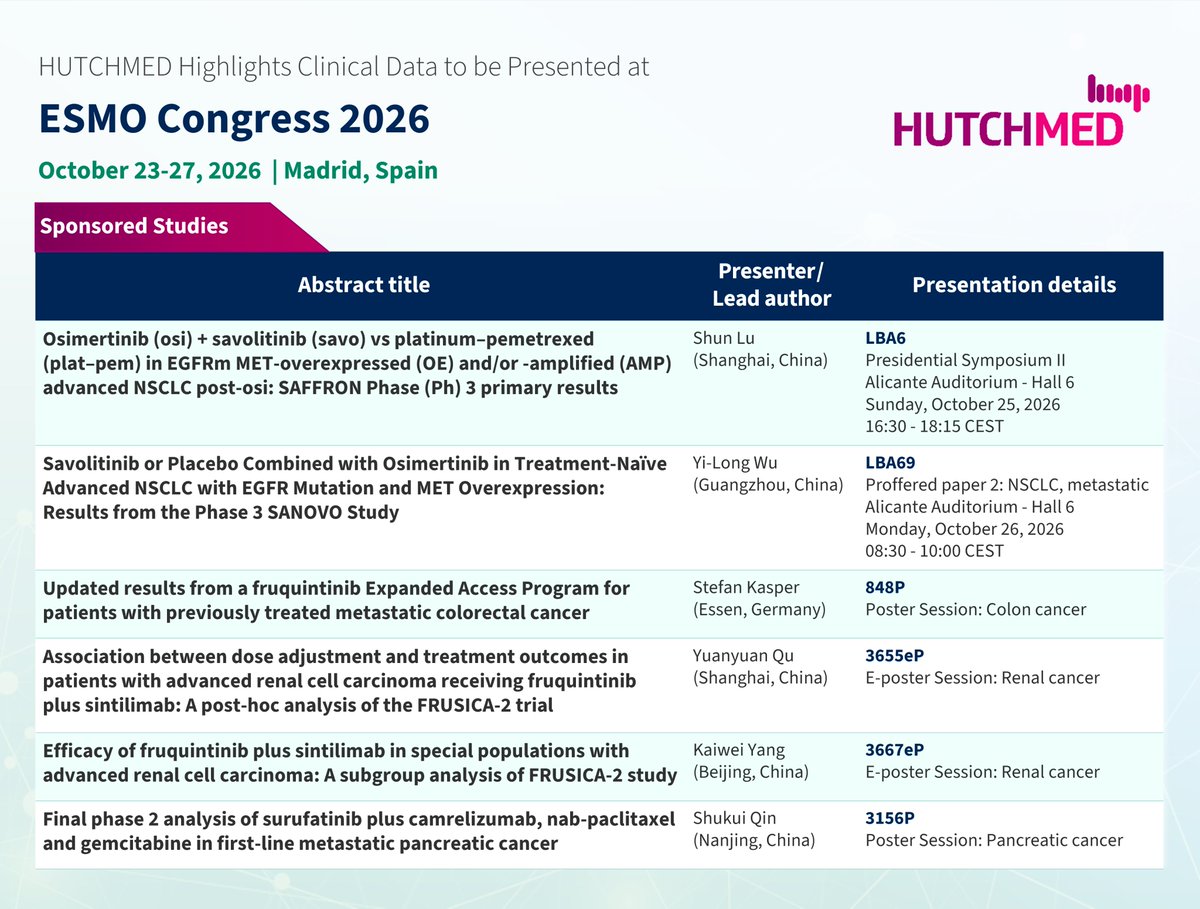
Every infographic and slide photo shared around ESMO 2026 (Madrid, October 23–27) by the oncology community: 672 image posts from 261 accounts, organized by tumor type and top-10 lists, filterable by trial and by KOL, physician posts first, each with a verbatim OCR transcription so the slide text is searchable and quotable. Updated October 23, 2026. ← Back to the full ESMO 2026 coverage
[Slide 1]
#ESMO2026
OCT 23 – 27, 2026
MADRID, SPAIN
15 TRIALS THAT COULD CHANGE PRACTICE
@DrRishabhOnco
NEW FRONTIERS IN IMMUNOTHERAPY & TARGETED THERAPY
1 INTerpath-001
Personalized mRNA vaccine + Pembrolizumab in high-risk melanoma
Can personalized mRNA vaccination reduce melanoma recurrence?
2 SAFFRON
EGFR-mutant, MET amplified/overexpressed NSCLC after osimertinib: osimertinib + savolitinib vs platinum-pemetrexed
Can MET inhibition overcome resistance to osimertinib?
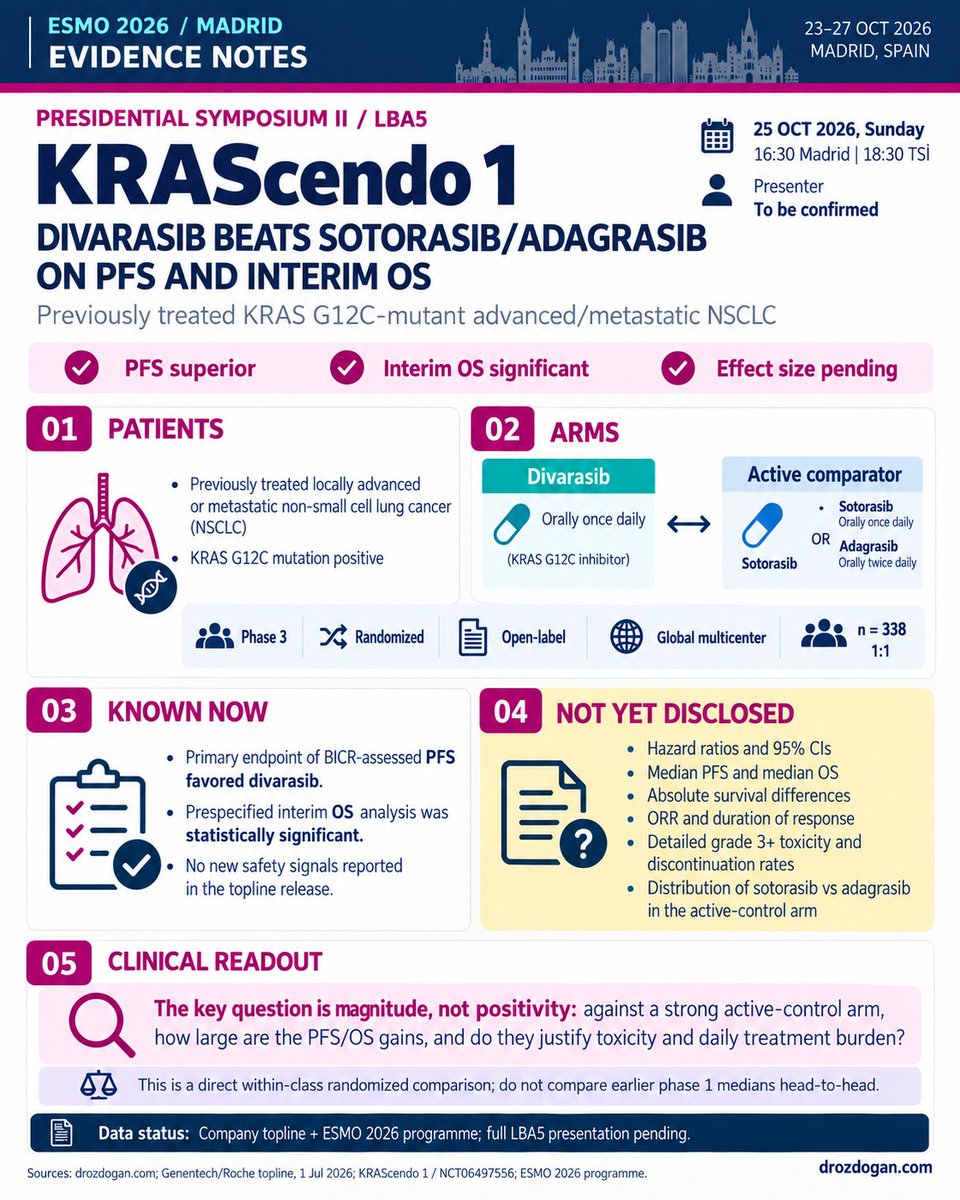
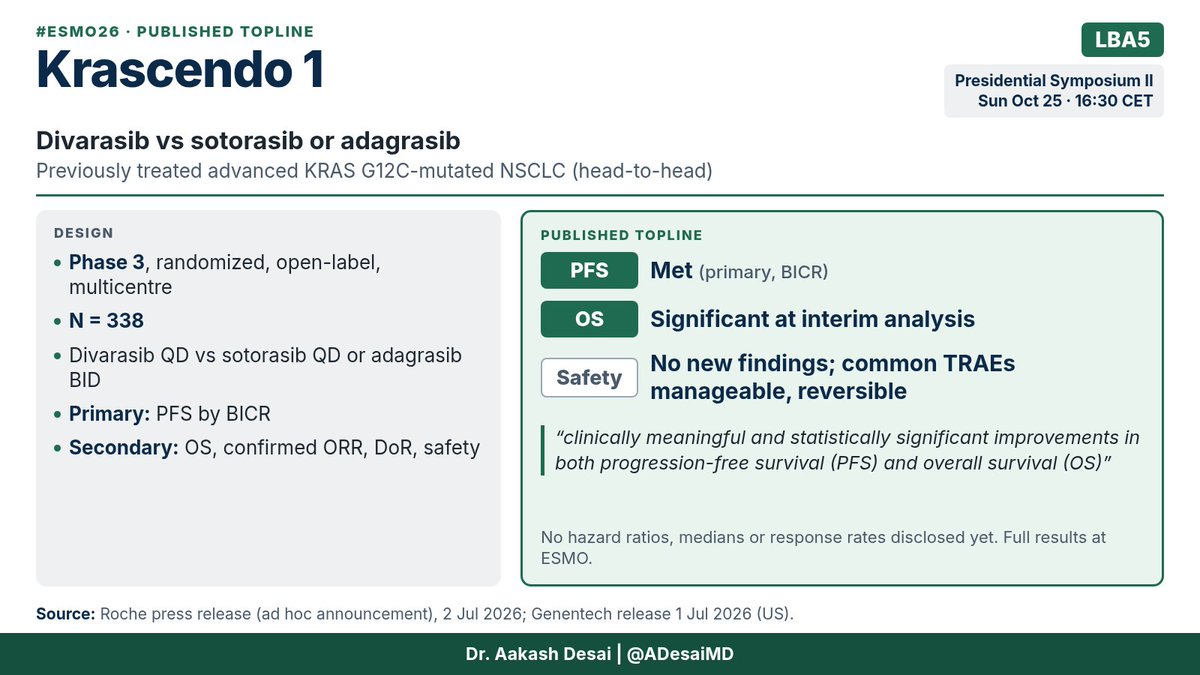
3 Krascendo 1
Divarasib vs sotorasib or adagrasib in previously treated KRAS G12C advanced NSCLC
Does a next-generation KRAS G12C inhibitor improve outcomes?
4 DeLLphi-305
Tarlatamab + durvalumab vs durvalumab maintenance after first-line durvalumab + platinum-etoposide in ES-SCLC
Can a DLL3 bispecific improve survival in extensive-stage SCLC?
5 HARMONi-GI1
Ivonescimab + chemotherapy vs durvalumab + chemotherapy in first-line advanced biliary cancer
Can adding a PD-1/VEGF bispecific improve outcomes in advanced biliary cancer?
PERIOPERATIVE, EARLY-STAGE & ADJUVANT SETTINGS
6 VOLGA
Perioperative durvalumab ± tremelimumab with neoadjuvant enfortumab vedotin in cisplatin-ineligible MIBC
Can perioperative immunotherapy improve outcomes in cisplatin-ineligible MIBC?
7 DASL-HicaP
Darolutamide + ADT + definitive or salvage RT in very high-risk localized prostate cancer
Does intensifying ADT with darolutamide improve long-term survival?
8 NATALEE
Six-year follow-up of adjuvant ribociclib in HR+/HER2– early breast cancer
Do long-term data confirm the benefit of adjuvant CDK4/6 inhibition?
9 TRIO-US B-12 TALENT
Neoadjuvant T-DXd–based therapy in HR+/HER2-low breast cancer
Can T-DXd improve pathologic response in HER2-low early breast cancer?
10 ENERGIZE
Perioperative chemotherapy plus immunotherapy strategies in muscle-invasive bladder cancer
Can perioperative immunotherapy improve outcomes in MIBC?
ADCs, NOVEL AGENTS & DISEASE-SPECIFIC ADVANCES
11 CLARITY-Gastric 01
Sonesitatug vedotin (CLDN18.2 ADC) vs investigator choice in previously treated CLDN18.2+ gastroesophageal adenocarcinoma
Can a CLDN18.2-targeted ADC improve survival in gastric/GEJ cancer?
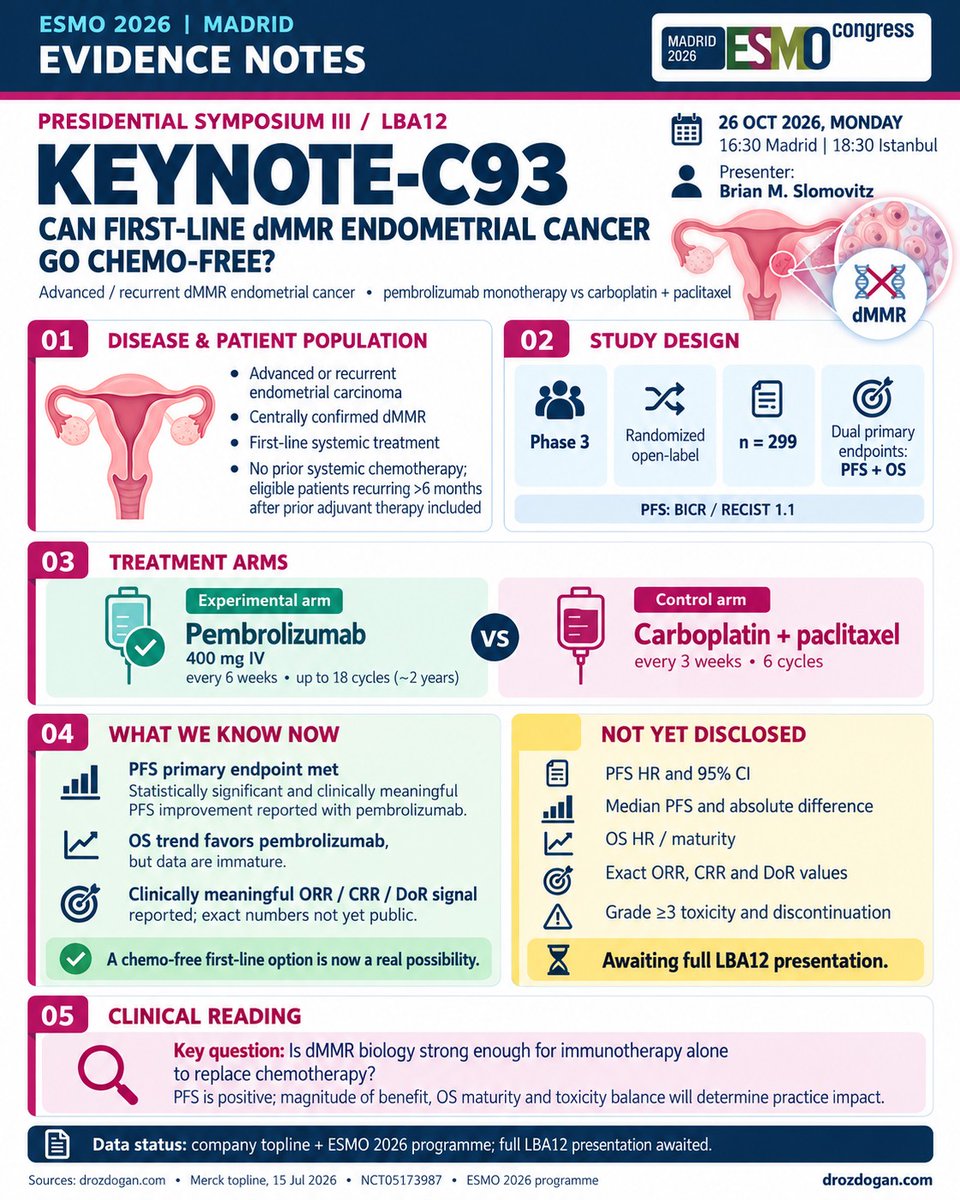
12 KEYNOTE-C93
Pembrolizumab vs chemotherapy in first-line advanced/recurrent dMMR endometrial cancer
Can chemotherapy be avoided in dMMR endometrial cancer?
13 KEYNOTE-B49
Pembrolizumab + chemotherapy in HR+/HER2– advanced breast cancer
Does adding immunotherapy improve outcomes in HR+ metastatic breast cancer?
14 LITESPARK-011
Belzutifan + lenvatinib vs cabozantinib in previously treated advanced clear-cell RCC
Can a HIF-2α-based combination outperform cabozantinib in advanced RCC?
15 SigVie-002
Integrin β6-directed ADC sigvotatug vedotin vs docetaxel in previously treated NSCLC
Can an integrin β6 ADC improve outcomes in previously treated NSCLC?
[Figure: AI-style illustrated cards with organ icons (lungs, bladder, prostate, breast, stomach, uterus, kidney, liver), Madrid skyline at top right.]
ESMO 2026
Top 10 (ish) Breast Cancer Abstracts
@PTarantinoMD
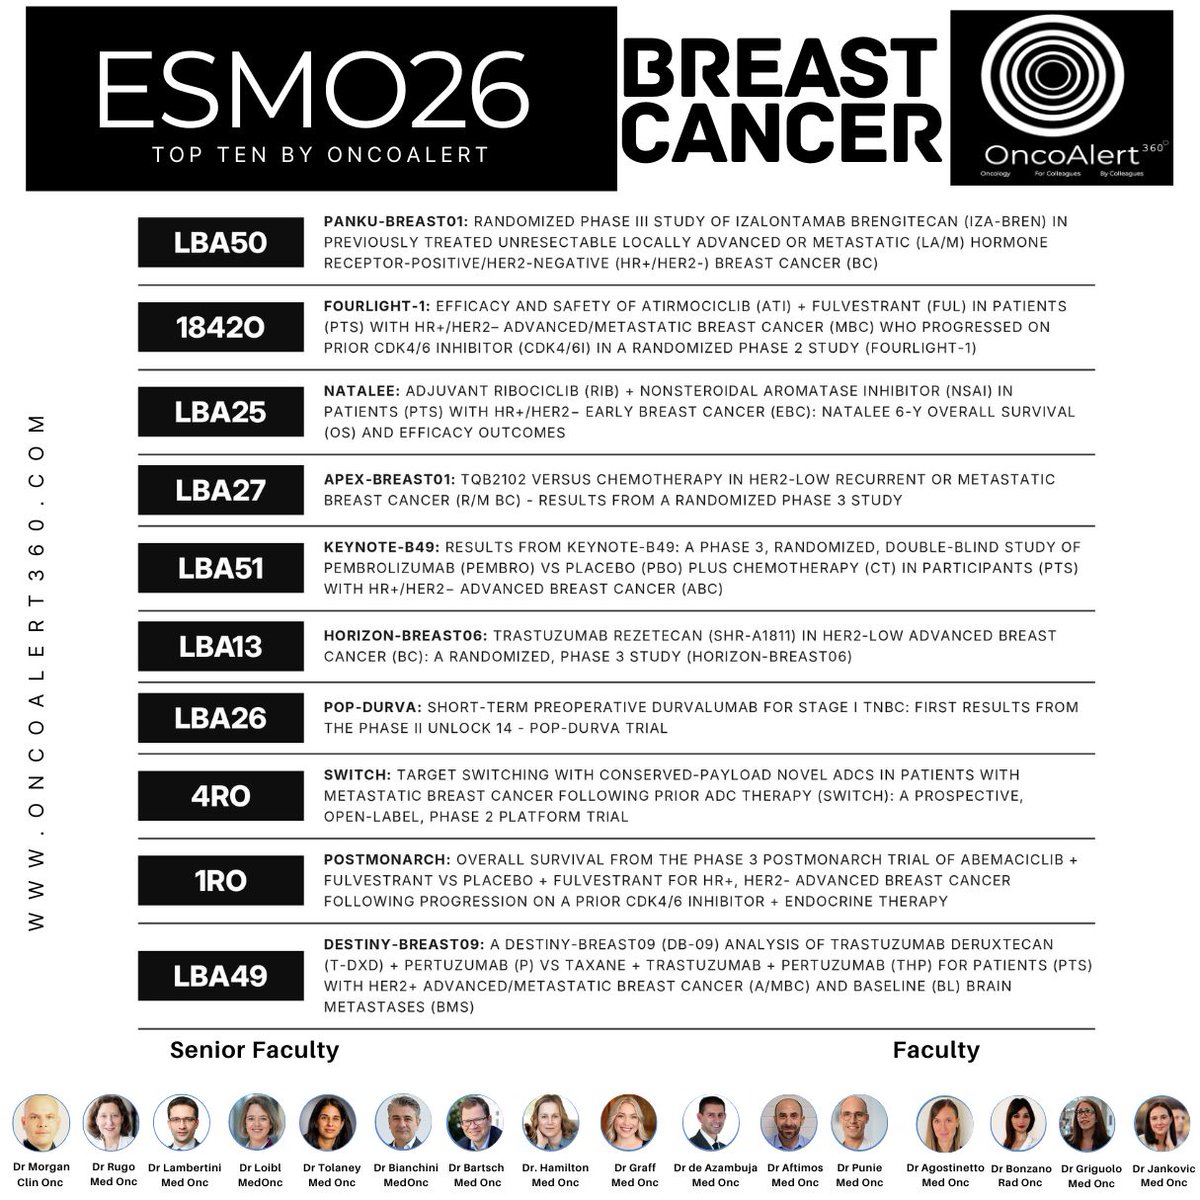
1. FOURLIGHT-1 (A. Giordano et al.) -> Announced to be positive, this randomized phase 2 trial evaluated the benefit of selective CDK4 inhibition with atirmociclib (+fulvestrant) in 2L HR+ MBC. Highly awaited.
2. BRIDGET (S. Sammons et al.) -> Could the addition of tucatinib to HP (or T-DM1) lead to favorable outcomes among pts with isolated PD from HER2+ MBC? Important data on an understudied setting.
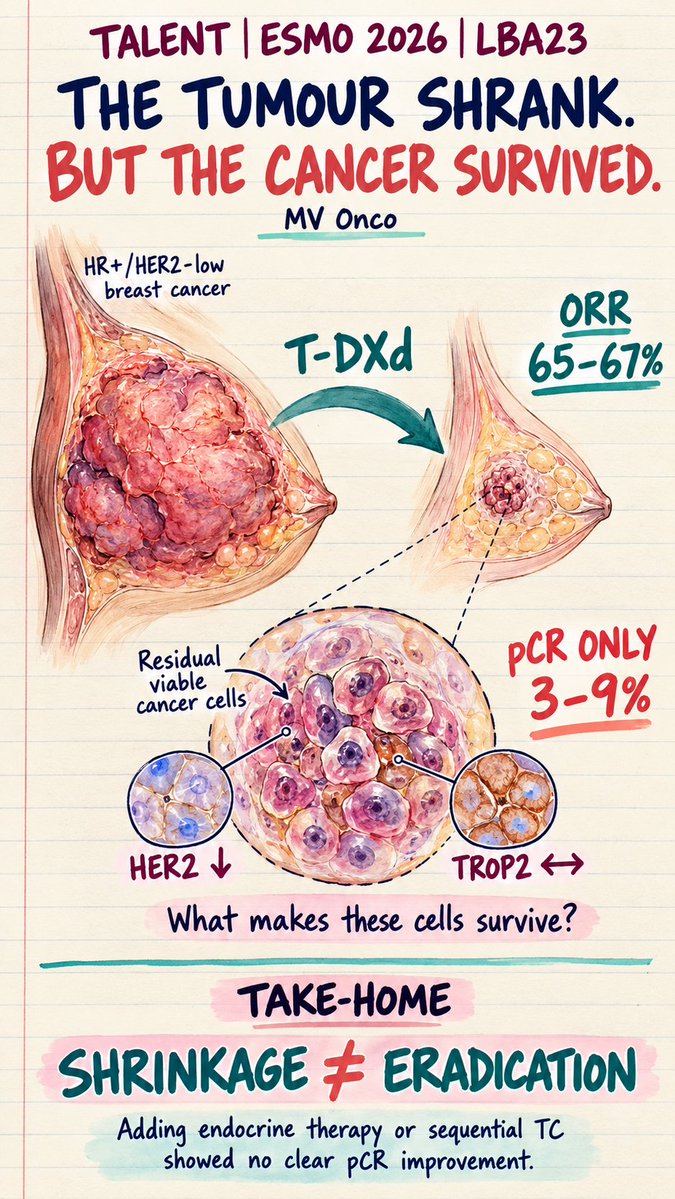
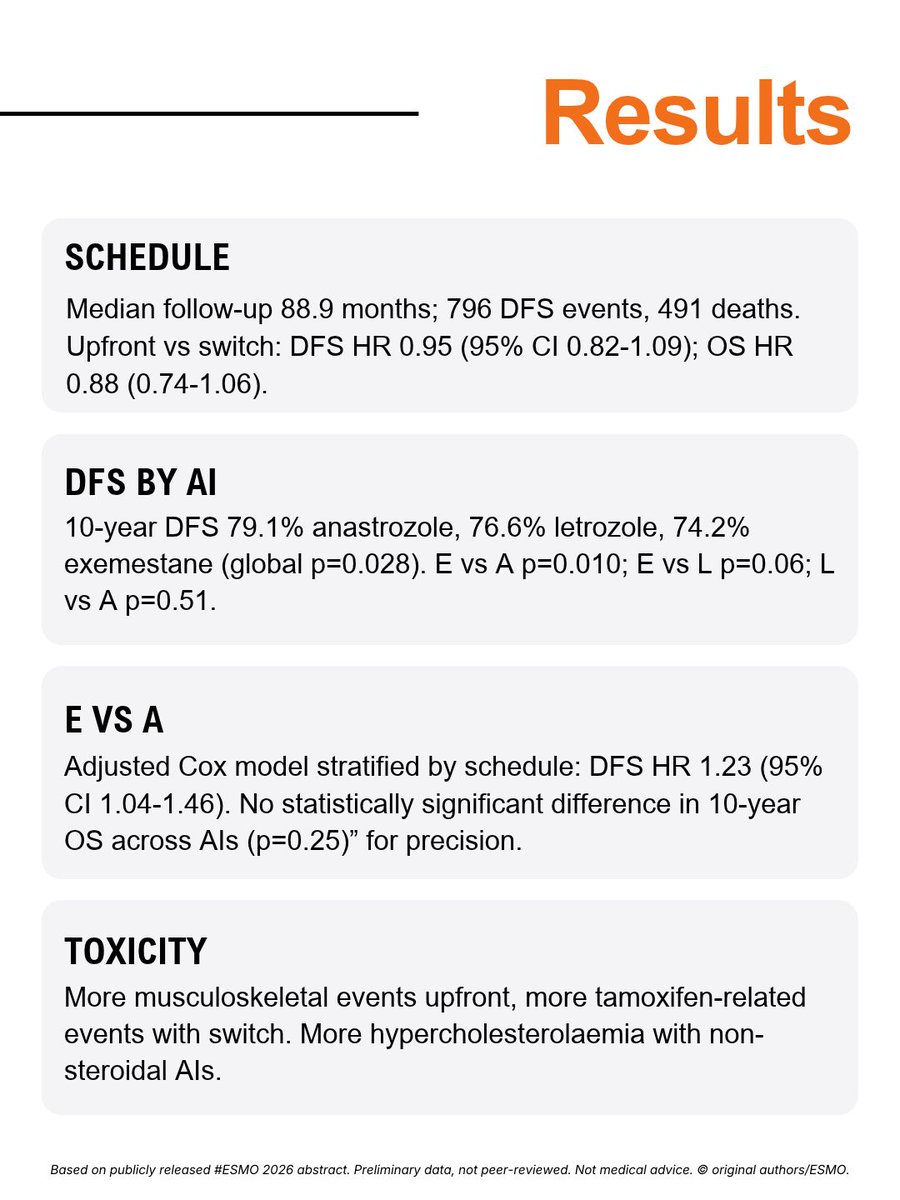
3. TALENT (S. Hurvitz et al.) -> Preliminary results from TALENT were quite disappointing, with neoadjuvant T-DXd/AI showing low pCR rate in HR+/HER2- breast cancer. At ESMO, we will see updated results, including the first data with T-DXd used in sequence with chemo in this setting.
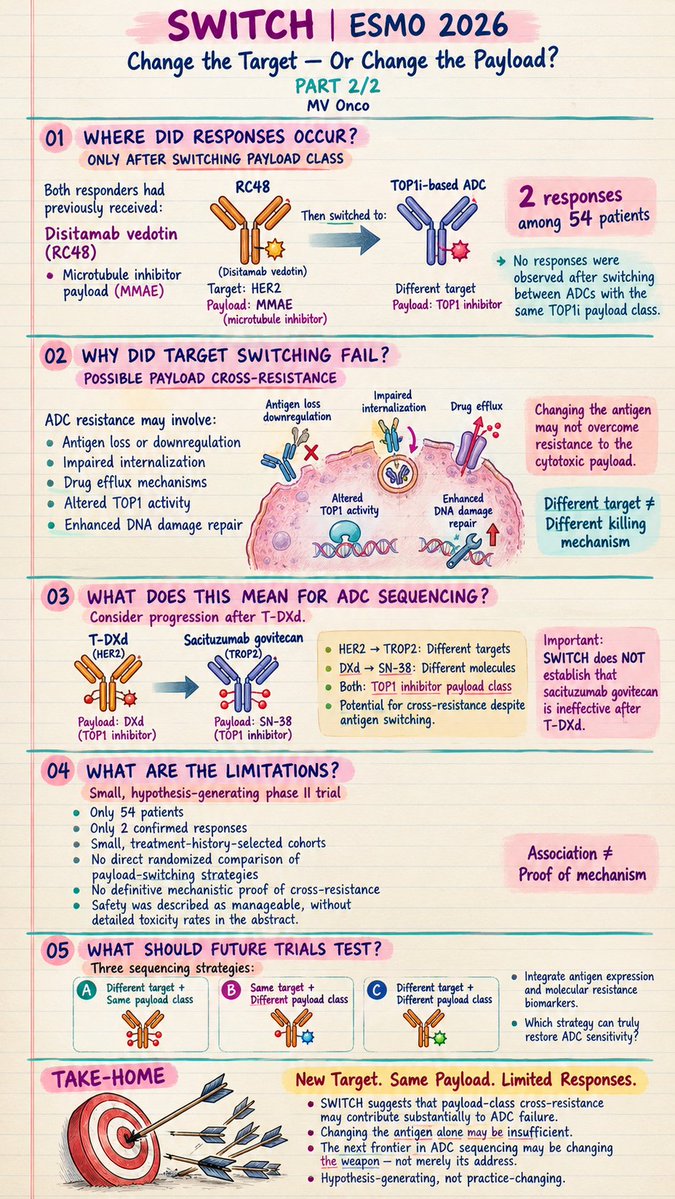
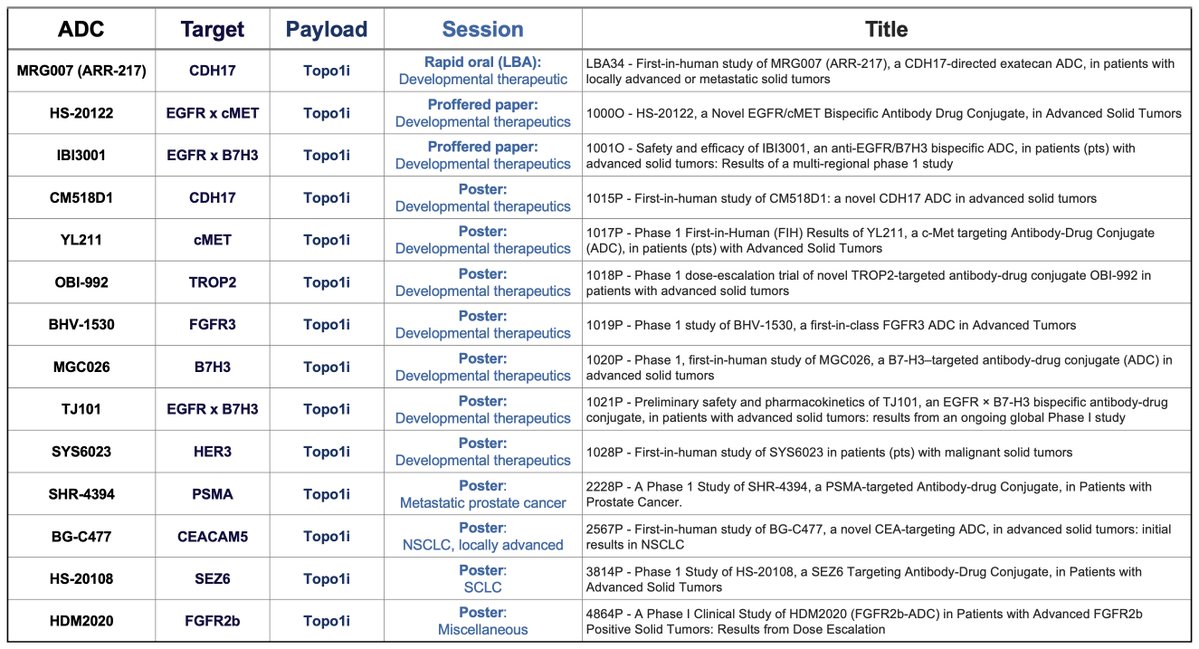
4. SWITCH (L. Fan et al.) -> Could keeping the payload (TOPO1i) but switching the target enable for continued efficacy with ADCs? SATEEN suggested limited benefit for this strategy in HER2+ disease. The SWITCH phase 2 trial tests this strategy with 4 novel TOPO1 ADCs in HR+/HER2- disease.
5. KEYNOTE-B49 (H. Rugo et al.) -> Immunotherapy has struggled to find its place in HR+ disease. This phase 3 trial tested whether using pembro early (added to 1L chemo) and in a selected population (PD-L1+) could prove beneficial for patients with HR+ MBC.
6. POP-DURVA (J. Ribeiro et al.) -> Standard treatment for stage I TNBC remains undefined. POP-DURVA tests 2 infusions of neoadjuvant durva in stage I TNBC with sTIL of >= 5%, with primary endpoint pCR
7. NSABP B42 (E. Mamounas et al.) -> The prior 10-year analysis of NSABP B42 demonstrated a significant DFS (but not OS) advantage with 10 vs 5 years of adjuvant AI in postmenopausal patients. This final analysis will clarify the long-term impact of extended AI therapy, which is increasingly utilized in practice.
8. MRD studies -> Interesting studies evaluating the prognostic role of MRD in HER2+ MBC with exceptional response (Nozawa et al.), neoadjuvant TNBC (Barcenas et al') and in the surveillance setting (Ozaki et al.)
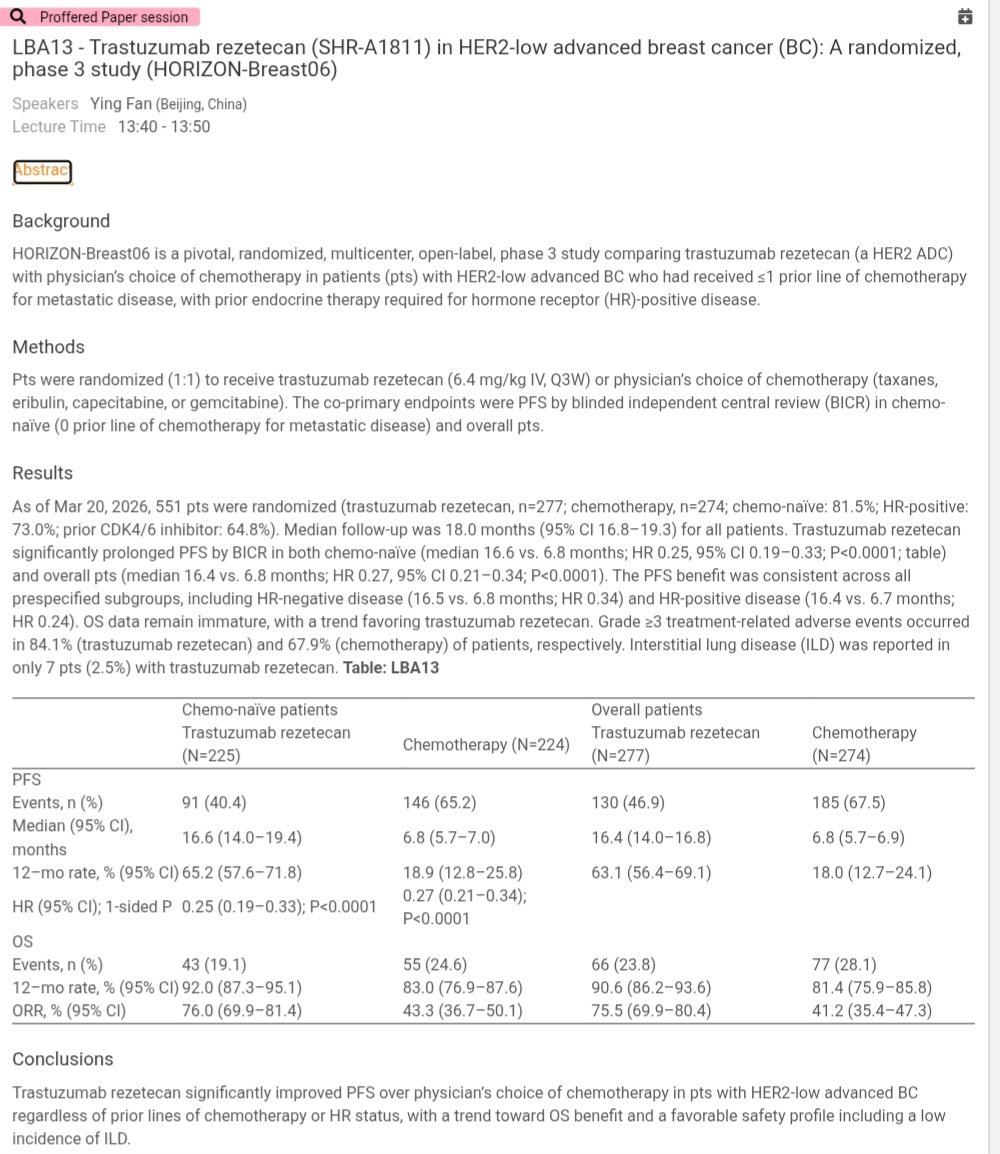
9. Exotic TOPO 1 ADC phase 3 trials -> At ESMO, we will see primary results of multiple phase 3 trials of TOP1 ADCs vs chemo conducted in China, including HORIZON-Breast06 (SHR-A1811 for HER2-low MBC), APEX-Breast01 (TQB2102 for HER2-low MBC) and PANKU-Breast01 (Iza-Bren for HR+/HER2- MBC)
10. Updates from NATALEE (6y), FINER (OS), TROPION-Breast02 (brain mets), DESTINY-Breast09 (brain mets), GIM3 FATA (AI comparison), lidERA (PROs), DESTINY-Breast05 (PROs), OptiTROP-Breast01 (OS)
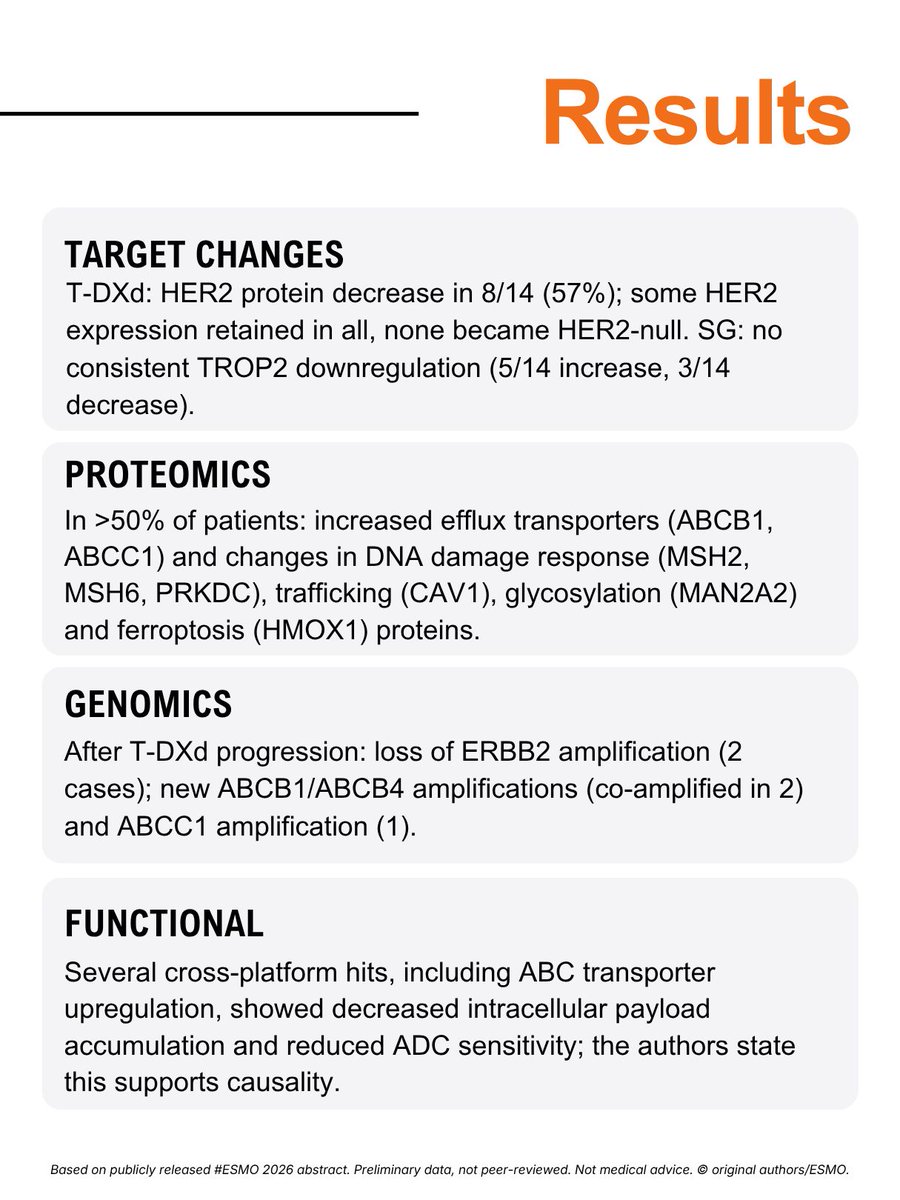
Bonus: CHARISMA (P. Tarantino et al.) -> How does breast cancer escape ADC treatment? We conducted multiomic profiling of biopsies collected pre/post-ADCs, with identification of novel mechanisms of resistance.
ESMO 2026: 10 GU Clinical Trials I'm Watching
Presidential + selected oral / proffered presentations
Clinical trials only - translational work excluded.
PRESIDENTIAL (2 PRESENTATIONS)
1. VOLGA - Perioperative durvalumab with or without tremelimumab plus neoadjuvant enfortumab vedotin in muscle-invasive bladder cancer | Bladder | Presenter: Thomas B. Powles
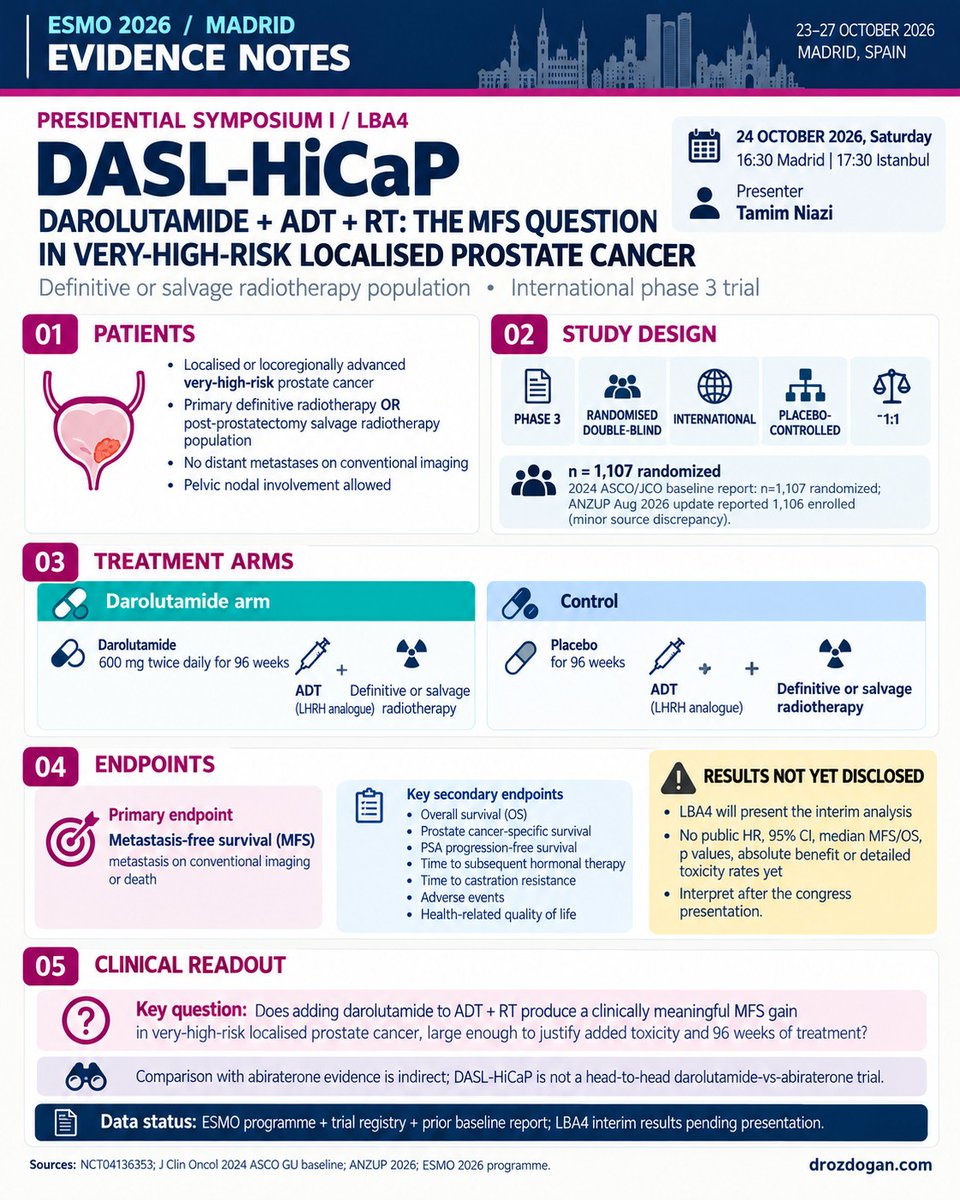
2. DASL-HiCaP (ANZUP1801) - Darolutamide with ADT and definitive or salvage locoregional radiation therapy for localized, very high-risk prostate cancer | Prostate | Presenter: Tamim Niazi
SELECTED ORAL / PROFFERED (8 PRESENTATIONS)
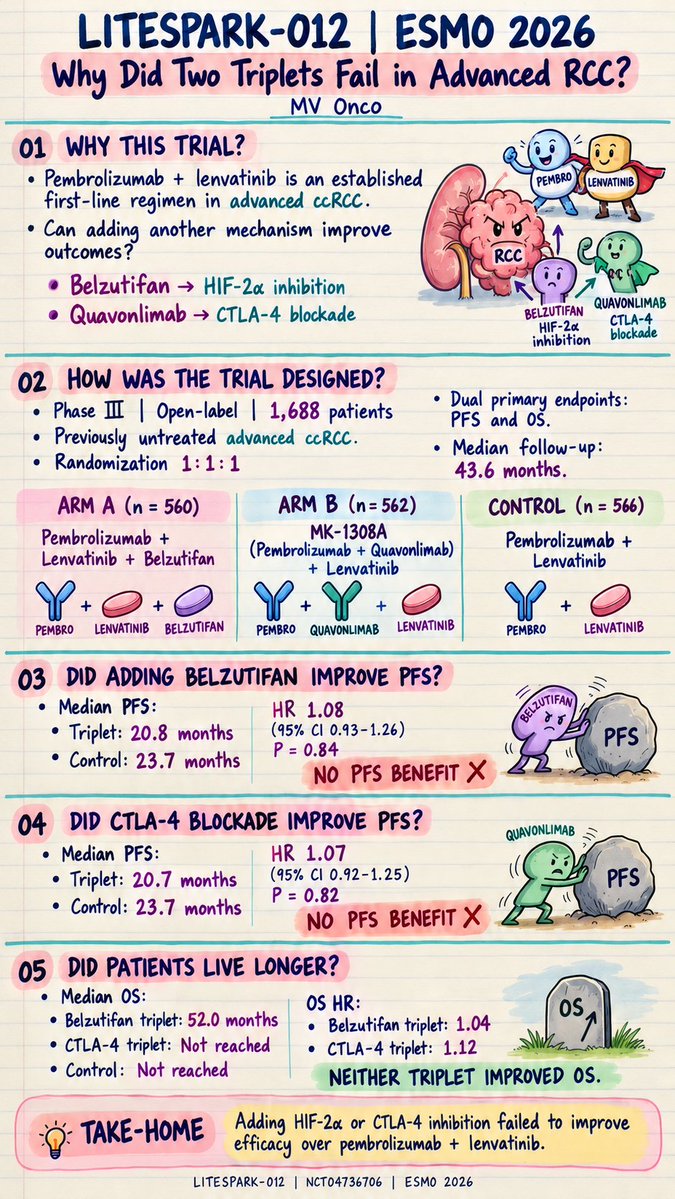
3. LITESPARK-012 - First-line pembrolizumab + lenvatinib + belzutifan or MK-1308A + lenvatinib in advanced RCC | Kidney | Presenter: Toni K. Choueiri
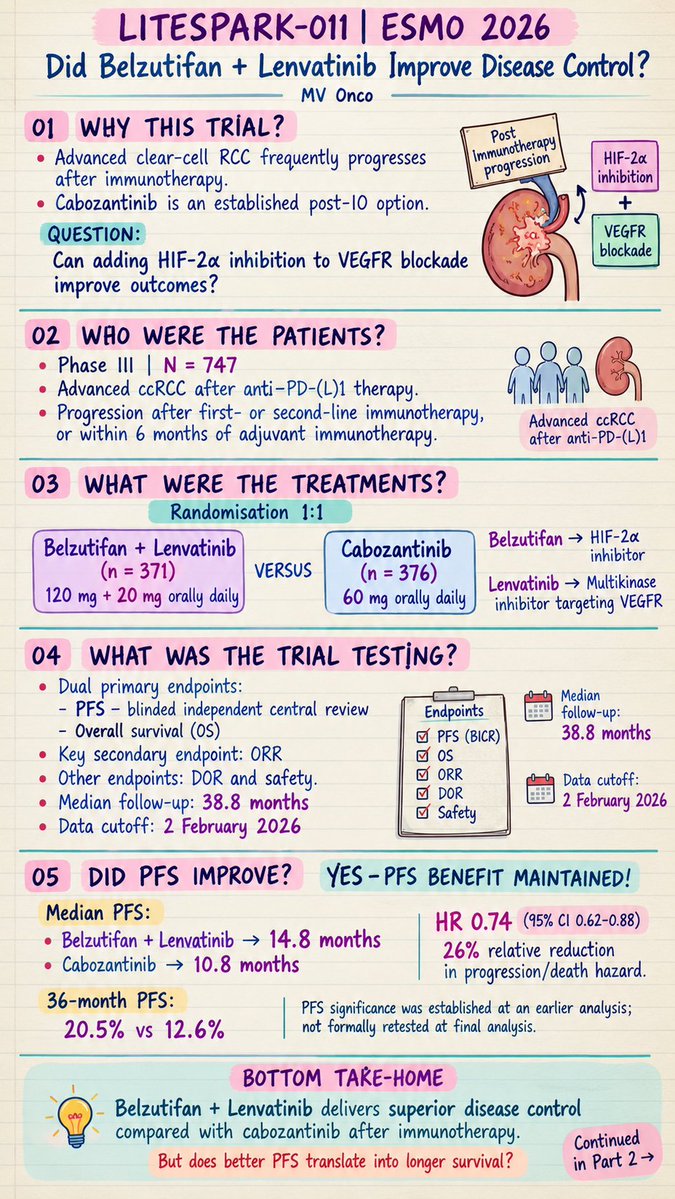
4. LITESPARK-011 - Final analysis: belzutifan + lenvatinib versus cabozantinib after anti-PD-(L)1 therapy in advanced RCC | Kidney | Presenter: Daniel Y. Heng
5. KEYNOTE-564 - Final protocol-prespecified analysis of adjuvant pembrolizumab versus placebo in clear-cell RCC | Kidney | Presenter: Toni K. Choueiri
6. SWOG S2200 - Cabozantinib with or without atezolizumab in metastatic papillary RCC | Kidney | Presenter: Benjamin L. Maughan
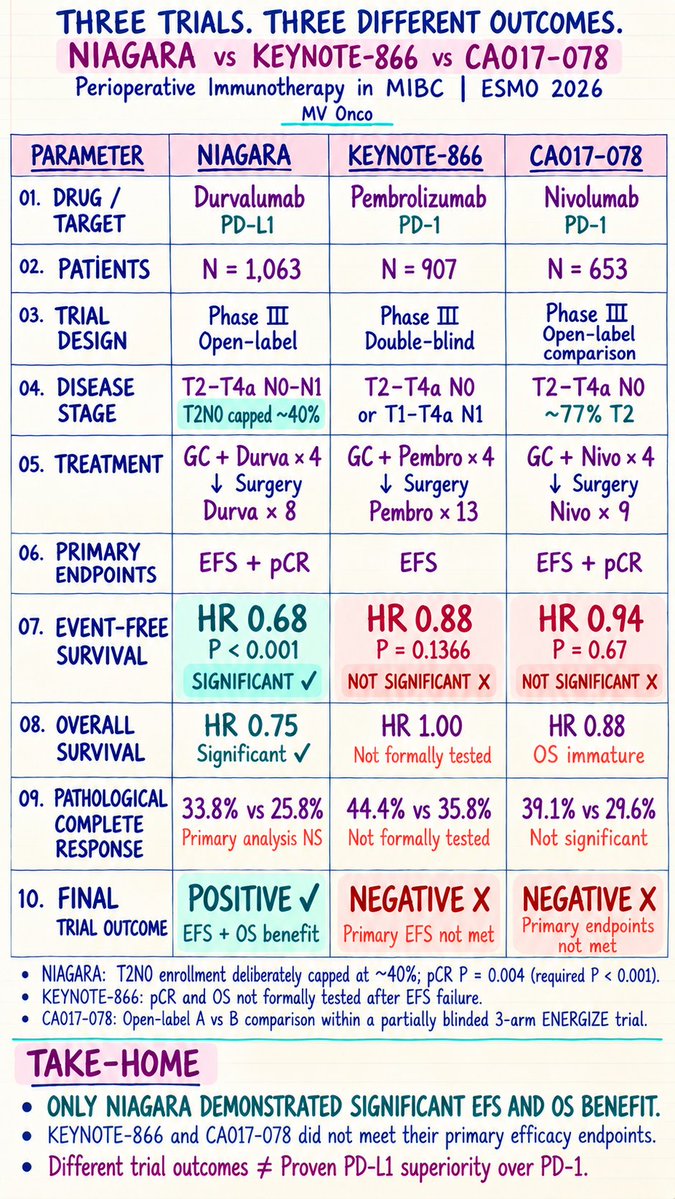
7. KEYNOTE-866 - Perioperative pembrolizumab or placebo plus neoadjuvant cisplatin/gemcitabine in muscle-invasive bladder cancer | Bladder | Presenter: Jens Bedke
8. Phase 3 perioperative nivolumab study - Neoadjuvant chemotherapy alone versus chemotherapy + nivolumab followed by adjuvant nivolumab in muscle-invasive bladder cancer | Bladder | Presenter: Andrea Necchi
9. PEACE-1 - Long-term overall survival with abiraterone acetate + prednisone in de novo metastatic castration-sensitive prostate cancer | Prostate | Presenter: Karim Fizazi
10. POTOMAC - Durvalumab in combination with BCG induction and maintenance for BCG-naive, high-risk non-muscle-invasive bladder cancer | Bladder | Presenter: Maria De Santis
Curated from ESMO 2026 presidential, oral and proffered GU sessions.
ESMO 2026, Madrid, 23-27 October 2026
@DrChoueiri
[Slide 1]
Rapid Oral session
4RO - Target switching with conserved-payload novel ADCs in patients with metastatic breast cancer following prior ADC therapy (SWITCH): A prospective, open-label, phase 2 platform trial
Speakers Lei Fan (Shanghai, China)
Lecture Time 10:20 - 10:25
Abstract
Background
Resistance to antibody-drug conjugates (ADCs) is an inevitable challenge in metastatic breast cancer (MBC), but the optimal post-progression sequencing strategy remains unclear. The SWITCH trial evaluated the efficacy and safety of a "target/payload switching" strategy using novel ADCs in patients with ADC-refractory MBC.
Methods
SWITCH is a prospective, open-label, phase 2 platform trial. Patients with human epidermal growth factor receptor 2-negative (HER2-negative) MBC who progressed on at least one prior ADC were enrolled. Based on prior treatment history, participants were randomly assigned to four novel ADC cohorts: SHR-A1811 (Cohort A), SHR-A1921 (Cohort B), SHR-A2009 (Cohort C), or SHR-A2102 (Cohort D), all carrying a topoisomerase I inhibitor (TOP1i) payload. The primary endpoint was investigator-assessed objective response rate (ORR).
Results
Between Oct 21, 2024, and Dec 30, 2025, 58 HER2-negative patients were screened, 54 of whom were randomly assigned (Cohort A: n=10; B: n=12; C: n=12; D: n=20). The population was heavily pretreated, with the majority (94.4%) having prior exposure to TOP1i-based ADCs. Confirmed ORRs were limited across all cohorts: 0% in Cohort A, 8.3% in Cohort B, 0% in Cohort C, and 5% in Cohort D. Responses were observed only in patients switching from the microtubule inhibitor-based ADC disitamab vedotin (RC48) to a TOP1 inhibitor-based ADC, whereas no responses occurred after switching between ADCs with the same payload class despite antigen switching. Treatment-related adverse events were consistent with known profiles of each ADC and manageable.
Conclusions
Rechallenging ADC-refractory MBC with novel agents targeting alternative antigens yielded limited responses, which suggested that payload cross-resistance was a primary driver of resistance. Diversified payload mechanisms in subsequent ADC sequencing were important to restore therapeutic sensitivity.
ESMO CONGRESS 2026 - MADRID - 23-27 OCTOBER
BREAST CANCER
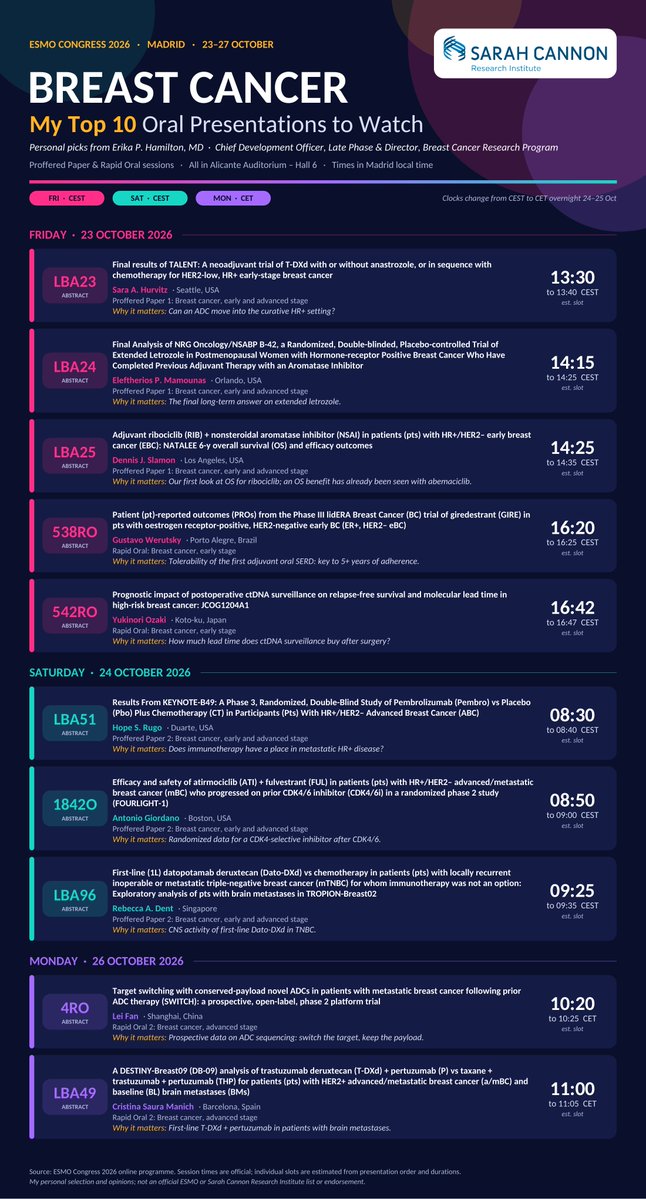
My Top 10 Oral Presentations to Watch
Personal picks from Erika P. Hamilton, MD - Chief Development Officer, Late Phase & Director, Breast Cancer Research Program
Proffered Paper & Rapid Oral sessions - All in Alicante Auditorium - Hall 6 - Times in Madrid local time
Sarah Cannon Research Institute
Clocks change from CEST to CET overnight 24-25 Oct
FRIDAY - 23 OCTOBER 2026
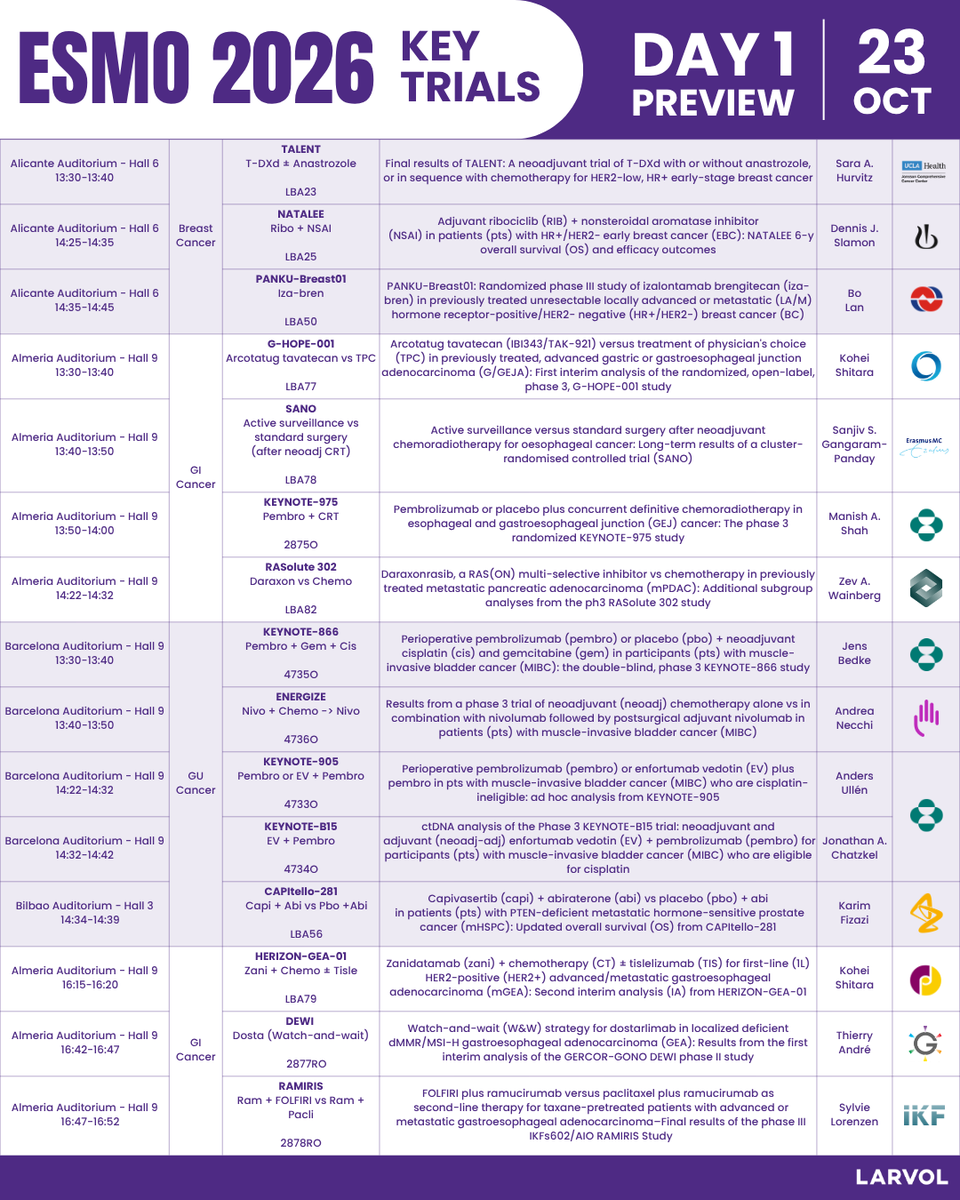
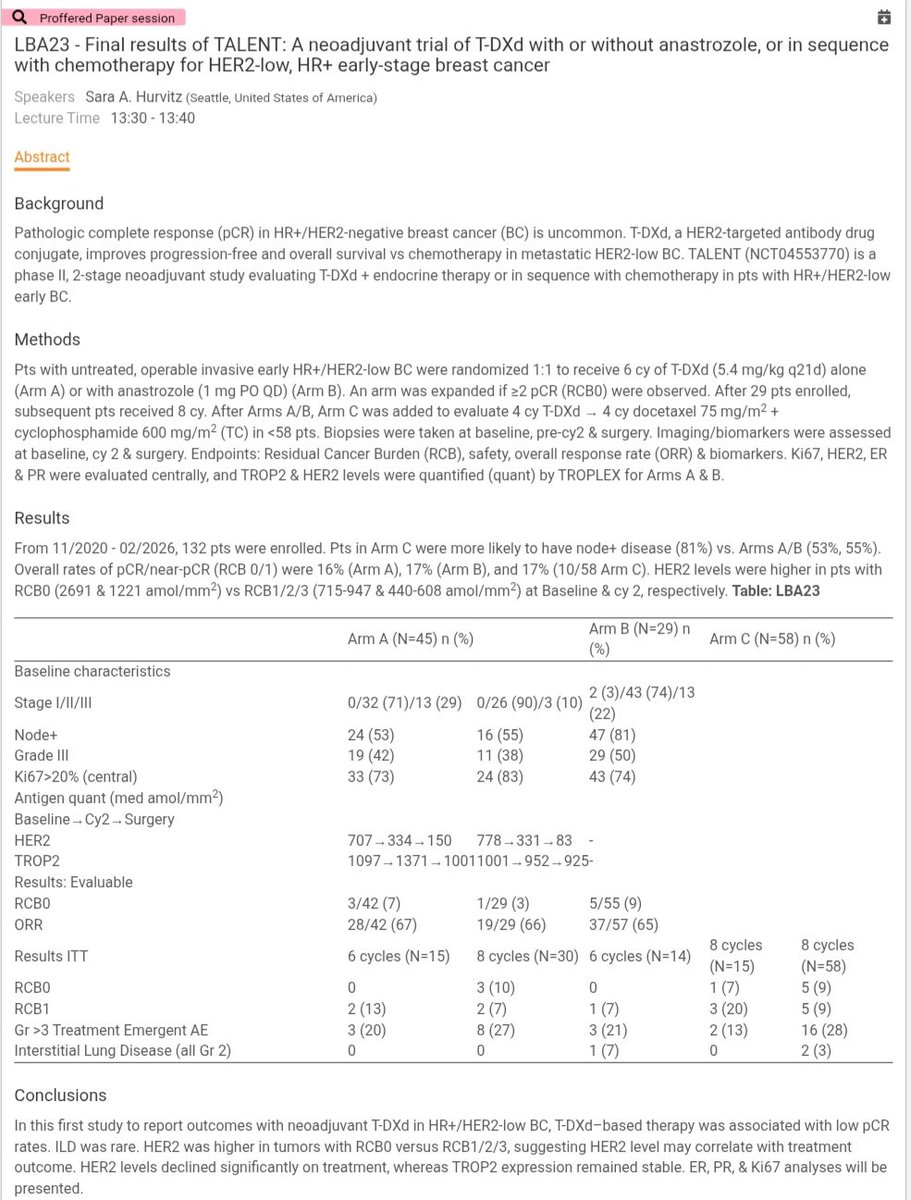
LBA23 (Abstract) - Final results of TALENT: A neoadjuvant trial of T-DXd with or without anastrozole, or in sequence with chemotherapy for HER2-low, HR+ early-stage breast cancer. Sara A. Hurvitz - Seattle, USA. Proffered Paper 1: Breast cancer, early and advanced stage. Why it matters: Can an ADC move into the curative HR+ setting? 13:30 to 13:40 CEST est. slot
LBA24 (Abstract) - Final Analysis of NRG Oncology/NSABP B-42, a Randomized, Double-blinded, Placebo-controlled Trial of Extended Letrozole in Postmenopausal Women with Hormone-receptor Positive Breast Cancer Who Have Completed Previous Adjuvant Therapy with an Aromatase Inhibitor. Eleftherios P. Mamounas - Orlando, USA. Proffered Paper 1: Breast cancer, early and advanced stage. Why it matters: The final long-term answer on extended letrozole. 14:15 to 14:25 CEST est. slot
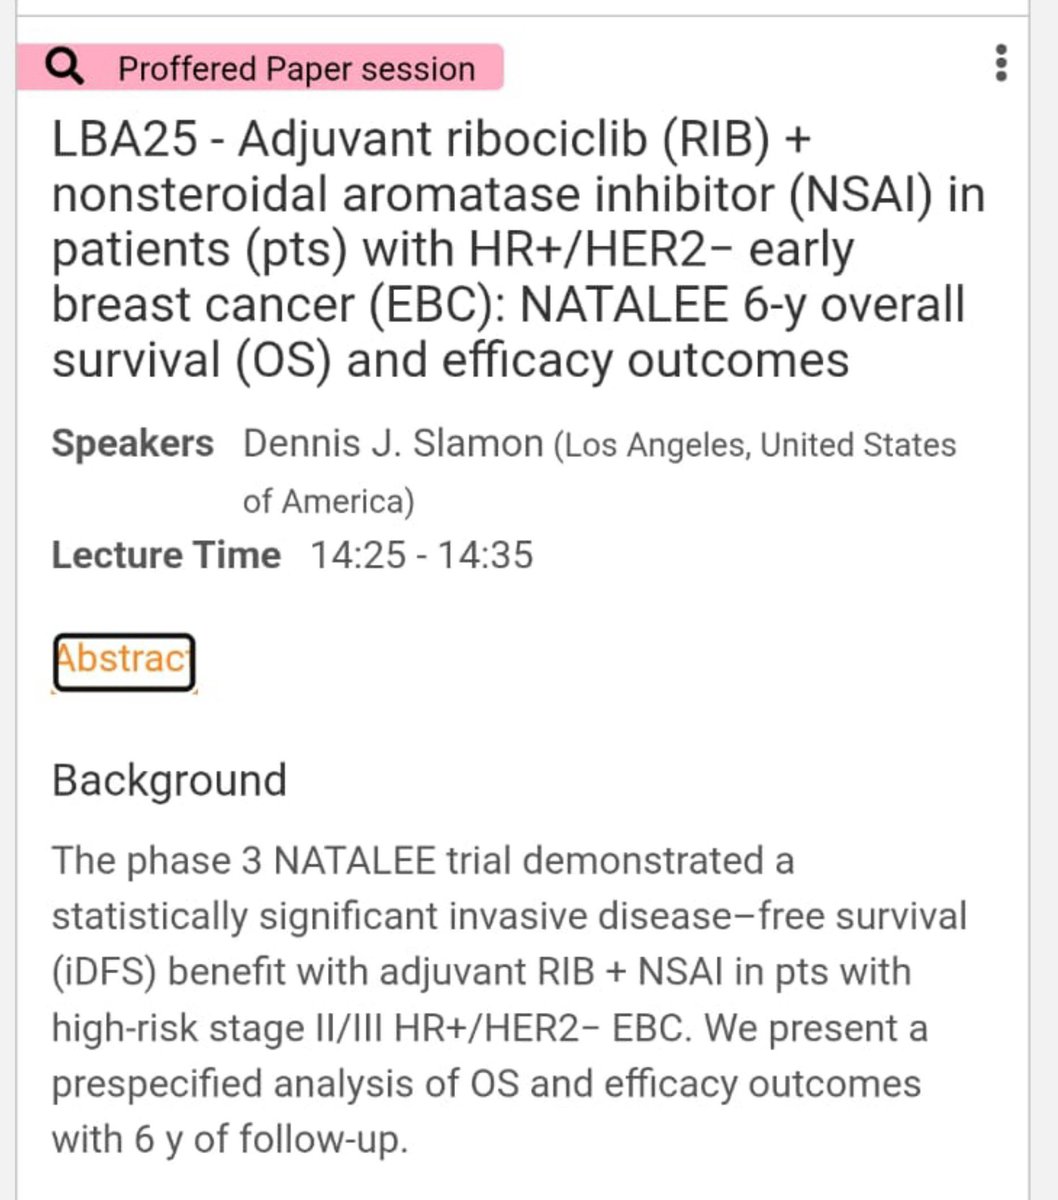
LBA25 (Abstract) - Adjuvant ribociclib (RIB) + nonsteroidal aromatase inhibitor (NSAI) in patients (pts) with HR+/HER2- early breast cancer (EBC): NATALEE 6-y overall survival (OS) and efficacy outcomes. Dennis J. Slamon - Los Angeles, USA. Proffered Paper 1: Breast cancer, early and advanced stage. Why it matters: Our first look at OS for ribociclib; an OS benefit has already been seen with abemaciclib. 14:25 to 14:35 CEST est. slot
538RO (Abstract) - Patient (pt)-reported outcomes (PROs) from the Phase III lidERA Breast Cancer (BC) trial of giredestrant (GIRE) in pts with oestrogen receptor-positive, HER2-negative early BC (ER+, HER2- eBC). Gustavo Werutsky - Porto Alegre, Brazil. Rapid Oral: Breast cancer, early stage. Why it matters: Tolerability of the first adjuvant oral SERD: key to 5+ years of adherence. 16:20 to 16:25 CEST est. slot
542RO (Abstract) - Prognostic impact of postoperative ctDNA surveillance on relapse-free survival and molecular lead time in high-risk breast cancer: JCOG1204A1. Yukinori Ozaki - Koto-ku, Japan. Rapid Oral: Breast cancer, early stage. Why it matters: How much lead time does ctDNA surveillance buy after surgery? 16:42 to 16:47 CEST est. slot
SATURDAY - 24 OCTOBER 2026
LBA51 (Abstract) - Results From KEYNOTE-B49: A Phase 3, Randomized, Double-Blind Study of Pembrolizumab (Pembro) vs Placebo (Pbo) Plus Chemotherapy (CT) in Participants (Pts) With HR+/HER2- Advanced Breast Cancer (ABC). Hope S. Rugo - Duarte, USA. Proffered Paper 2: Breast cancer, early and advanced stage. Why it matters: Does immunotherapy have a place in metastatic HR+ disease? 08:30 to 08:40 CEST est. slot
1842O (Abstract) - Efficacy and safety of atirmociclib (ATI) + fulvestrant (FUL) in patients (pts) with HR+/HER2- advanced/metastatic breast cancer (mBC) who progressed on prior CDK4/6 inhibitor (CDK4/6i) in a randomized phase 2 study (FOURLIGHT-1). Antonio Giordano - Boston, USA. Proffered Paper 2: Breast cancer, early and advanced stage. Why it matters: Randomized data for a CDK4-selective inhibitor after CDK4/6. 08:50 to 09:00 CEST est. slot
LBA96 (Abstract) - First-line (1L) datopotamab deruxtecan (Dato-DXd) vs chemotherapy in patients (pts) with locally recurrent inoperable or metastatic triple-negative breast cancer (mTNBC) for whom immunotherapy was not an option: Exploratory analysis of pts with brain metastases in TROPION-Breast02. Rebecca A. Dent - Singapore. Proffered Paper 2: Breast cancer, early and advanced stage. Why it matters: CNS activity of first-line Dato-DXd in TNBC. 09:25 to 09:35 CEST est. slot
MONDAY - 26 OCTOBER 2026
4RO (Abstract) - Target switching with conserved-payload novel ADCs in patients with metastatic breast cancer following prior ADC therapy (SWITCH): a prospective, open-label, phase 2 platform trial. Lei Fan - Shanghai, China. Rapid Oral 2: Breast cancer, advanced stage. Why it matters: Prospective data on ADC sequencing: switch the target, keep the payload. 10:20 to 10:25 CET est. slot
LBA49 (Abstract) - A DESTINY-Breast09 (DB-09) analysis of trastuzumab deruxtecan (T-DXd) + pertuzumab (P) vs taxane + trastuzumab + pertuzumab (THP) for patients (pts) with HER2+ advanced/metastatic breast cancer (a/mBC) and baseline (BL) brain metastases (BMs). Cristina Saura Manich - Barcelona, Spain. Rapid Oral 2: Breast cancer, advanced stage. Why it matters: First-line T-DXd + pertuzumab in patients with brain metastases. 11:00 to 11:05 CET est. slot
Source: ESMO Congress 2026 online programme. Session times are official; individual slots are estimated from presentation order and durations.
My personal selection and opinions; not an official ESMO or Sarah Cannon Research Institute list or endorsement.
[Slide 1]
Proffered Paper session
4735O - Perioperative pembrolizumab (pembro) or placebo (pbo) + neoadjuvant cisplatin (cis) and gemcitabine (gem) in participants (pts) with muscle-invasive bladder cancer (MIBC): the double-blind, phase 3 KEYNOTE-866 study
Speakers Jens Bedke (Stuttgart, Germany)
Lecture Time 13:30 - 13:40
Proffered Paper session
4736O - Results from a phase 3 trial of neoadjuvant (neoadj) chemotherapy alone vs in combination with nivolumab followed by postsurgical adjuvant nivolumab in patients (pts) with muscle-invasive bladder cancer (MIBC)
Speakers Andrea Necchi (Milan, Italy)
Lecture Time 13:40 - 13:50
Proffered Paper session
4742O - Sacituzumab Govitecan (SG) Combined With Enfortumab Vedotin (EV) and Zimberelimab (ZIM) in Treatment-Naive Metastatic Urothelial Cancer (mUC): Interim Results From Phase 1b TROPHY-U-01 Cohort 7
Speakers Randy Sweis (Chicago, United States of America)
Lecture Time 13:50 - 14:00
Proffered Paper session
Invited Discussant 4735O, 4736O and 4742O
Speakers Robert Jones (Bearsden, United Kingdom)
Lecture Time 14:00 - 14:12
[Slide 2]
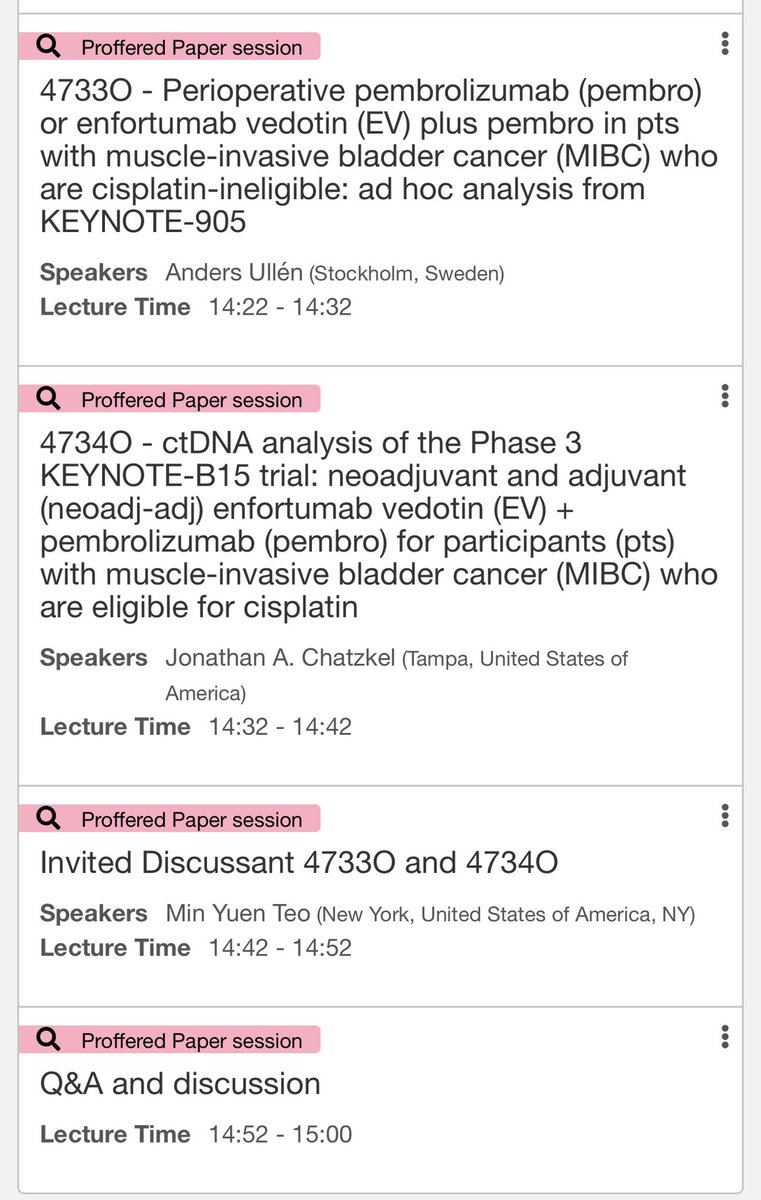
Proffered Paper session
4733O - Perioperative pembrolizumab (pembro) or enfortumab vedotin (EV) plus pembro in pts with muscle-invasive bladder cancer (MIBC) who are cisplatin-ineligible: ad hoc analysis from KEYNOTE-905
Speakers Anders Ullén (Stockholm, Sweden)
Lecture Time 14:22 - 14:32
Proffered Paper session
4734O - ctDNA analysis of the Phase 3 KEYNOTE-B15 trial: neoadjuvant and adjuvant (neoadj-adj) enfortumab vedotin (EV) + pembrolizumab (pembro) for participants (pts) with muscle-invasive bladder cancer (MIBC) who are eligible for cisplatin
Speakers Jonathan A. Chatzkel (Tampa, United States of America)
Lecture Time 14:32 - 14:42
Proffered Paper session
Invited Discussant 4733O and 4734O
Speakers Min Yuen Teo (New York, United States of America, NY)
Lecture Time 14:42 - 14:52
Proffered Paper session
Q&A and discussion
Lecture Time 14:52 - 15:00
[Slide 3]
Rapid Oral session
4739RO - Sacituzumab Tirumotecan (Sac-TMT) + Pembrolizumab (Pembro) for Locally Advanced or Metastatic Urothelial Carcinoma (la/mUC): Results From a Phase 2 Study (2870-002/SKB264-II-06)
Speakers Xiaojie Bian (Shanghai, China)
Lecture Time 10:45 - 10:50
Rapid Oral session
4740RO - Enfortumab Vedotin (EV) With or Without Pembrolizumab (P) as First-Line (1L) Treatment for Cisplatin (cis)-Ineligible Locally Advanced Or Metastatic Urothelial Carcinoma (la/mUC): Long-Term Follow-up Analysis from EV-103 Cohorts DE/A and K
Speakers Jose Pablo Maroto Rey (Barcelona, Spain)
Lecture Time 10:50 - 10:55
Rapid Oral session
4749RO - Neoadjuvant Tislelizumab plus Disitamab Vedotin for UTUC: Mid-term Results of the Phase II WUTSUP-02 Trial
Speakers Tiancheng Liu (Chengdu, China)
Lecture Time 10:55 - 11:00
Rapid Oral session
Invited Discussant 4739RO, 4740RO and 4749RO
Speakers Britt B. Suelmann (Utrecht, Netherlands)
Lecture Time 11:00 - 11:15
[Slide 1]
Rapid Oral session
4640RO - Bulumtatug fuvedotin (BFv, 9MW2821), a nectin-4-directed antibody-drug conjugate (ADC), in patients with locally advanced or metastatic triple negative breast cancer (la/mTNBC) previously treated with topoisomerase I inhibitor (TopI)-based ADCs: Results from a phase 2 study
Speakers Yanchun Meng (Shanghai, China)
Lecture Time 10:30 - 10:35
Abstract
Background
BFv is an ADC delivering monomethyl auristatin E (MMAE) to Nectin-4-expressing cells, a target highly expressed in TNBC. For patients with prior exposure to TopI-based ADCs, switching to a Nectin-4-targeted ADC with a distinct payload (MMAE) represents a rational therapeutic strategy. We report efficacy and safety data from the cohort of la/mTNBC patients previously treated with TopI-based ADCs in the phase 2 study of BFv (NCT06492005).
Methods
Cohort A enrolled la/mTNBC patients with prior TopI-based ADC therapy. BFv was given intravenously at 1.25 mg/kg on days 1 and 8 every 21 days. Primary endpoint was objective response rate (ORR). Secondary endpoints included duration of response (DOR), disease control rate (DCR), progression-free survival (PFS), overall survival (OS), and safety.
Results
As of April 10, 2026, 62 patients were enrolled, of whom 60 were evaluable for response. Median age was 50.5 years (range 32-73). Liver metastases were present in 33% of patients, and 42% had received ≥3 prior lines of therapy. All patients (100%) had received prior TopI-based ADCs: 48% received TROP-2-targeted ADCs, and 33% received HER2-targeted ADCs. All patients had prior taxane-based chemotherapy; 35% also received immune checkpoint inhibitors. The ORR was 30.0% (95% CI 18.85%-43.21%) and DCR was 80.0% (95% CI 67.67%-89.22%). Median PFS was 3.7 months (95% CI 2.96-4.34), and median DOR was 8.7 months (95% CI 2.79-NR). OS data were not mature. Common TRAEs (≥20%) included increased AST/ALT, neutropenia, leukopenia, hypertriglyceridemia, rash, hypercholesterolemia, hyperglycemia, anemia, thrombocytopenia, asthenia, and increased GGT. Grade ≥3 TRAEs (≥5%) included neutropenia, leukopenia, and increased AST.
Conclusions
BFv demonstrated promising antitumor activity with a manageable safety profile in heavily pretreated patients with la/mTNBC who had all received prior TopI-based ADCs. The first pivotal trial for this indication worldwide is underway.
[Slide 1]
ESMO 2026
TOP 15 BREAST CANCER TRIALS TO WATCH
Pre-congress watchlist | Grouped by breast cancer subtype
23 - 27 OCTOBER 2026 | MADRID, SPAIN
[Photo of Madrid Metropolis building]
HR+ / HER2- BREAST CANCER
Endocrine therapy, targeted combinations and immunotherapy
1 FOURLIGHT-1 - Atirmociclib + fulvestrant in 2L HR+/HER2- MBC [CDK4 icon]
2 PANKU-Breast01 - EGFRxHER3 bispecific ADC in HR+/HER2- MBC
3 KEYNOTE-B49 - Pembrolizumab + chemotherapy in PD-L1+ HR+/HER2- MBC
4 NATALEE - 6-year outcomes of adjuvant ribociclib in HR+/HER2- early breast cancer [KM curve icon, "6 YEARS" calendar icon]
5 FINER / MA.40 - Overall survival with ipatasertib + fulvestrant after CDK4/6i [AKT icon]
6 NSABP B-42 - Long-term outcomes of extended adjuvant aromatase inhibition
7 TALENT - Neoadjuvant T-DXd-based sequencing in HR+/HER2-low early breast cancer
8 SWITCH - ADC sequencing after prior ADC exposure in HR+/HER2- MBC
HER2-POSITIVE / HER2-LOW BREAST CANCER
Next-generation ADCs and targeted approaches
9 BRIDGET - Tucatinib-based treatment for isolated progression in HER2+ MBC [HER2 icon]
10 DESTINY-Breast09 - CNS outcomes update with first-line T-DXd + pertuzumab in HER2+ MBC [brain icon]
11 HORIZON-Breast06 - Trastuzumab rezetecan in HER2-low MBC
12 APEX-Breast01 - Novel TOP1 ADC in HER2-low MBC
TRIPLE-NEGATIVE BREAST CANCER
Immunotherapy and next-generation ADCs
13 TROPION-Breast02 - CNS outcomes update with datopotamab deruxtecan in TNBC [brain icon]
14 POP-DURVA - Neoadjuvant durvalumab in stage I TNBC
15 OptiTROP-Breast01 - Final overall survival with sacituzumab tirumotecan in TNBC
OTHER IMPORTANT ABSTRACTS TO WATCH
VIKTORIA-1 - After CDK4/6i | postMONARCH - After CDK4/6i | lidERA - Patient-reported outcomes | DESTINY-Breast05 - Patient-reported outcomes | GIM3 FATA - AI comparison | MRD studies - Prognostic role across settings | CHARISMA - Mechanisms of ADC resistance
[ESMO logo] GOOD SCIENCE BETTER MEDICINE BEST PRACTICE
@DrRishabhOnco DM - Medical Oncology (AIIMS, New Delhi) [X logo]
[Slide 1]
Top 10 Anticipated Practice Changing/Informing Abstracts for ESMO 2026
from Community Oncology's (@OncBrothers) perspective
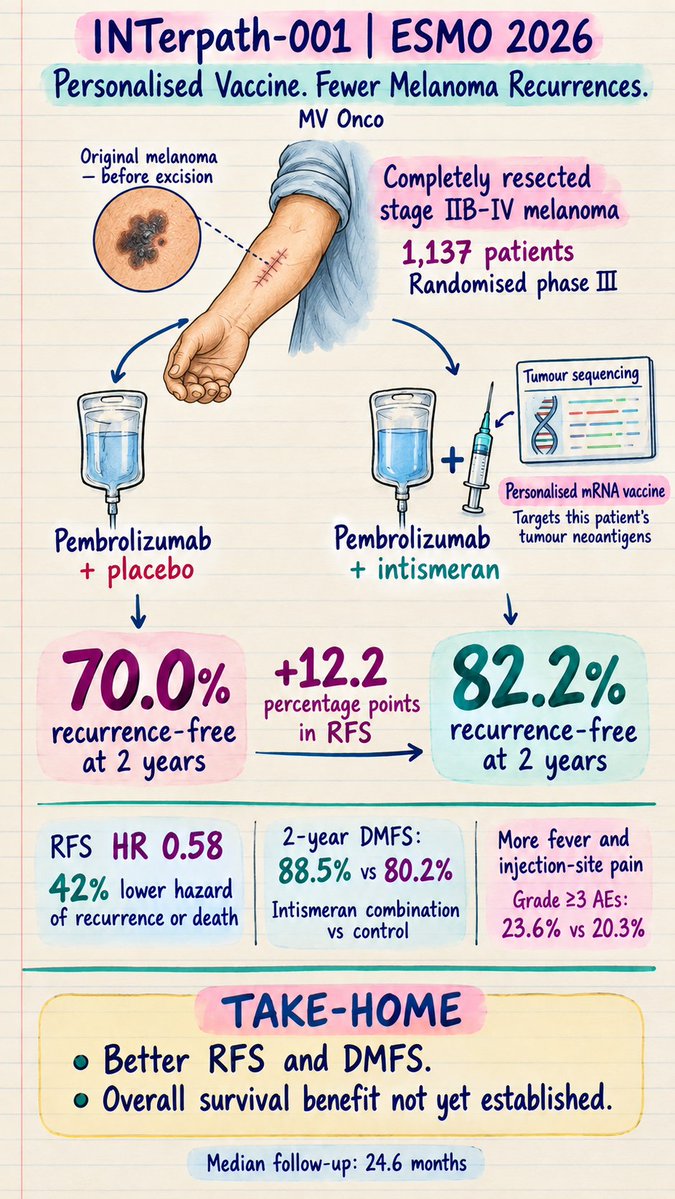
1 #INTerpath001: Ph III, Intismeran autogene (individualized mRNA neoantigen therapy) + Pembro vs. Pembro in adjuvant resected stage IIB–IV Melanoma.
2 #VOLGA: Ph III, NeoAdj Durva + EV +/- Treme → Surgery → Durva +/- Treme in cisplatin ineligible muscle invasive Bladder Cancer.
3 #ANZUP1801: Ph III, Darolutamide + ADT + XRT vs. ADT + XRT for very high risk localized Prostate Cancer.
4 #LITESPARK011: Ph III (Update), Belzutifan + Lenvatinib (FDA approved on Sept 24, 2026) vs. Cabozantinib in 2L (after IO) in advanced/metastatic Renal Cell Carcinoma.
5 #DeLLphi305: Ph III, Durvalumab + Tarlatamab vs. Durvalumab as maintenance (after chemo + IO as induction) in extensive stage Small Cell Lung Cancer.
6 #SAFFRON: Ph III, Osimertinib + Savolitinib vs. Chemo (platinum + Pemetrexed) in MET overexpressed or amplified after Osi in mEGFR Non-Small Cell Lung Cancer.
7 #CLARITYGastric01: Ph III, Sonesitatug Vedotin (sone-ve, CLDN18.2 targeting ADC) vs. physician's choice chemotherapy in 2L+ CLDN18.2+ advanced/metastatic GE Junction or Gastric Adenocarcinoma.
8 Updates in Breast Cancer:
• #TALENT: Ph II, NeoAdj T-DXd +/- ET for early stage HER2-low, HR+
• #NATALEE: Ph III, Adj Ribo + ET in resected HR+, 6yr update
• #postMONARCH: Ph III, Abema + Fulvestrant after 1L CDK4/6i + ET in metastatic HR+, OS update
• #VIKTORIA1: Ph III, Gedatolisib + Fulv +/- Palbo after 1L CDK4/6i + ET
9 #MOIO: Ph III, non-inferiority trial, Standard Immunotherapy dosing vs. Reduced frequency (once every 3 months) after 6 months of standard dosing and achieving Partial or Complete response in Metastatic Cancer (multiple primary cancers included).
10 #TroFuse005: Ph III, Sacituzumab Tirumotecan (Sac-TMT, Trop-2 targeting ADC) vs. physician's choice chemotherapy in 2L+ (after chemo + IO) in recurrent/metastatic Endometrial Cancer.
www.oncbrothers.com @Oncbrothers (YouTube) @Oncbrothers (Instagram) @Oncbrothers (X)
[Slide 1]
[Photo: speaker at a lectern (badge reads 'URO-ONKO FORUM 2026' — partly legible) presenting a slide; four panellists seated]
Cisplatin eligible
[blue, top — trial name not printed]: GC x 4 | Radical Cystectomy and PLND | Observation ; GC + Durva x 4 | Radical Cystectomy and PLND | Durva x 8 [red check mark]
KN-866 NCT03924856: GC x 4 | Radical Cystectomy and PLND | Observation ; GC + Pembro x 4 | Radical Cystectomy and PLND | Pembro x 13
ENERGIZE NCT03661320: GC x 4 | Radical Cystectomy and PLND | Observation ; GC + Nivo x 4 | Radical Cystectomy and PLND | Nivo x [number clipped]
[red box around KN-866 and ENERGIZE rows]
[orange, bottom — trial name not printed]: EV + Pembro x 4 | Radical Cystectomy and PLND | EV x 5 + Pembro x 13 ; GC x 4 | Radical Cystectomy and PLND | Observation [red check mark]
Cisplatin ineligible
KN-905/EV-303 NCT03924895 [red check mark]: EV + Pembro x 3 | Radical Cystectomy and PLND | EV x 6 + Pembro x 14 ; No preop therapy | Radical Cystectomy and PLND | Observation
Volga NCT04960709 [red box]: Durva + EV x 3 | Radical Cystectomy and PLND | Durva x 9 ; Durva/Treme + EV x 3 | Radical Cystectomy and PLND | Treme x 1 + Durva x 9 ; No preop therapy | Radical Cystectomy and PLND | Per physician choice
Modified from Rosenberg [J.] Presented at ESMO 2025
[... c]ombination with pembro is not registered by EMA f[or the] treatment of cis[platin-eligible] MIBC patients. [bottom line partly obscured by panellists]
[Slide 1]
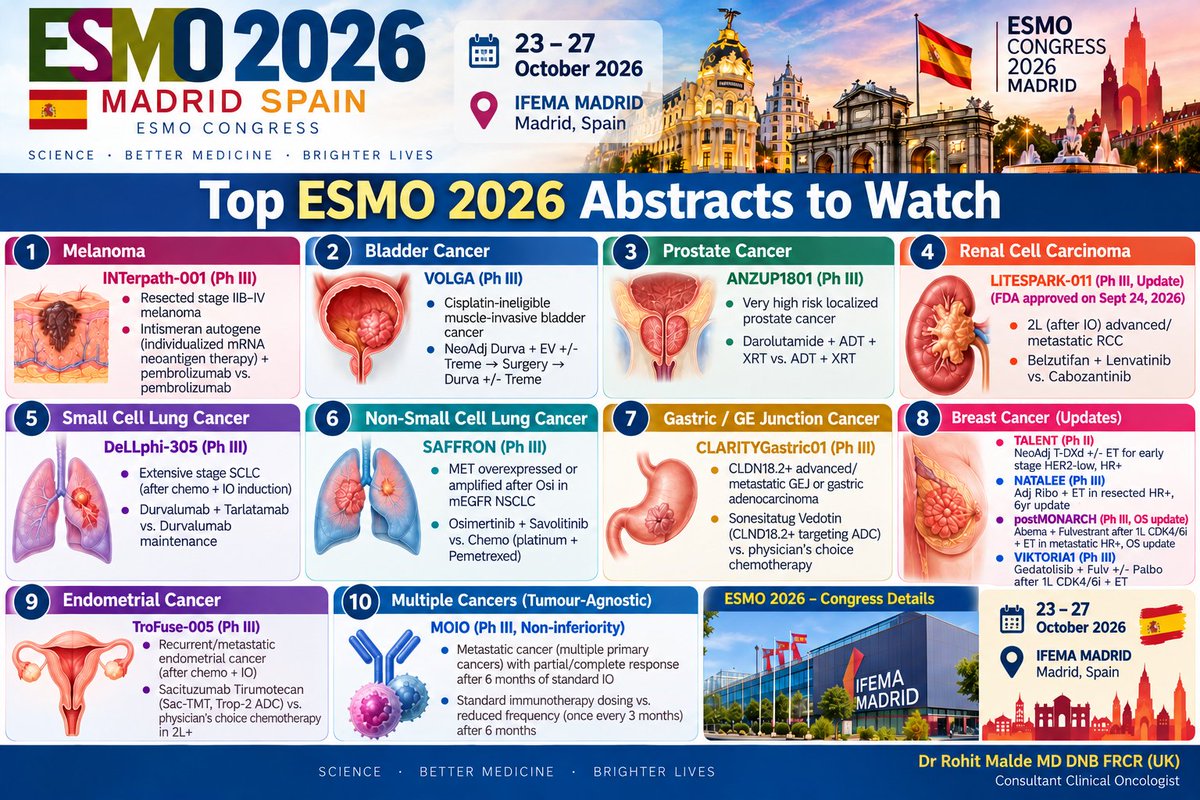
ESMO 2026 MADRID SPAIN ESMO CONGRESS
SCIENCE · BETTER MEDICINE · BRIGHTER LIVES
23 – 27 October 2026
IFEMA MADRID Madrid, Spain
ESMO CONGRESS 2026 MADRID
Top ESMO 2026 Abstracts to Watch
1 Melanoma
INTerpath-001 (Ph III)
• Resected stage IIB–IV melanoma
• Intismeran autogene (individualized mRNA neoantigen therapy) + pembrolizumab vs. pembrolizumab
2 Bladder Cancer
VOLGA (Ph III)
• Cisplatin-ineligible muscle-invasive bladder cancer
• NeoAdj Durva + EV +/- Treme → Surgery → Durva +/- Treme
3 Prostate Cancer
ANZUP1801 (Ph III)
• Very high risk localized prostate cancer
• Darolutamide + ADT + XRT vs. ADT + XRT
4 Renal Cell Carcinoma
LITESPARK-011 (Ph III, Update) (FDA approved on Sept 24, 2026)
• 2L (after IO) advanced/metastatic RCC
• Belzutifan + Lenvatinib vs. Cabozantinib
5 Small Cell Lung Cancer
DeLLphi-305 (Ph III)
• Extensive stage SCLC (after chemo + IO induction)
• Durvalumab + Tarlatamab vs. Durvalumab maintenance
6 Non-Small Cell Lung Cancer
SAFFRON (Ph III)
• MET overexpressed or amplified after Osi in mEGFR NSCLC
• Osimertinib + Savolitinib vs. Chemo (platinum + Pemetrexed)
7 Gastric / GE Junction Cancer
CLARITYGastric01 (Ph III)
• CLDN18.2+ advanced/metastatic GEJ or gastric adenocarcinoma
• Sonesitatug Vedotin (CLND18.2+ targeting ADC) vs. physician's choice chemotherapy
8 Breast Cancer (Updates)
• TALENT (Ph II) NeoAdj T-DXd +/- ET for early stage HER2-low, HR+
• NATALEE (Ph III) Adj Ribo + ET in resected HR+, 6yr update
• postMONARCH (Ph III, OS update) Abema + Fulvestrant after 1L CDK4/6i + ET in metastatic HR+, OS update
• VIKTORIA1 (Ph III) Gedatolisib + Fulv +/- Palbo after 1L CDK4/6i + ET
9 Endometrial Cancer
TroFuse-005 (Ph III)
• Recurrent/metastatic endometrial cancer (after chemo + IO)
• Sacituzumab Tirumotecan (Sac-TMT, Trop-2 ADC) vs. physician's choice chemotherapy in 2L+
10 Multiple Cancers (Tumour-Agnostic)
MOIO (Ph III, Non-inferiority)
• Metastatic cancer (multiple primary cancers) with partial/complete response after 6 months of standard IO
• Standard immunotherapy dosing vs. reduced frequency (once every 3 months) after 6 months
ESMO 2026 – Congress Details [photo: IFEMA MADRID building]
23 – 27 October 2026
IFEMA MADRID Madrid, Spain
SCIENCE · BETTER MEDICINE · BRIGHTER LIVES
Dr Rohit Malde MD DNB FRCR (UK)
Consultant Clinical Oncologist
[Slide 2]
ESMO 2026 MADRID SPAIN ESMO CONGRESS · SCIENCE · BETTER MEDICINE · BRIGHTER LIVES · 23 – 27 October 2026 · IFEMA MADRID Madrid, Spain · ESMO CONGRESS 2026 MADRID
Top ESMO 2026 Abstracts to Watch – Detailed Overview (Top 3)
1 INTerpath-001 (Phase III) — LBA1 24 Oct 2026
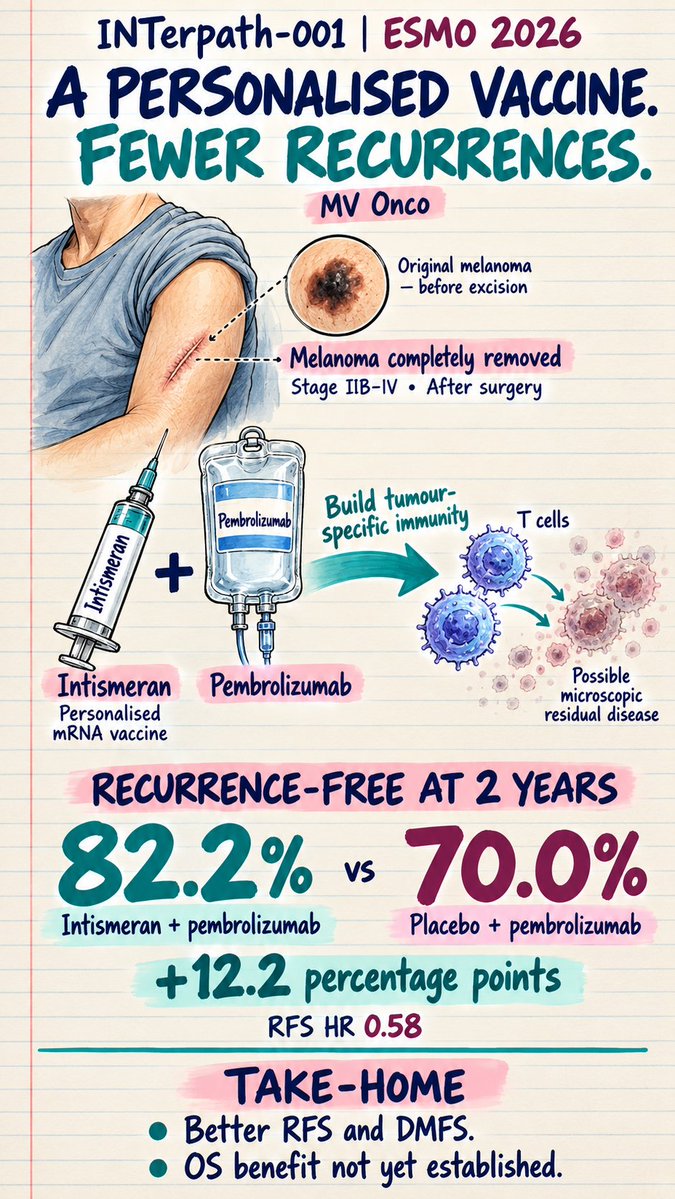
Intismeran autogene (individualized mRNA neoantigen therapy) + Pembrolizumab vs. Pembrolizumab in resected stage IIB–IV Melanoma
CANCER SITE & DISEASE SETTING: Cutaneous Melanoma • Resected stage IIB, IIC, III or IV • Adjuvant setting after complete surgical resection
WHY IMPORTANT?: High risk of recurrence despite anti-PD-1 • Personalized mRNA vaccine aims to boost tumour-specific immune response • Potential new standard in adjuvant melanoma
TRIAL DESIGN: Phase III 1,137 patients | Randomized 2:1 | Primary endpoint Recurrence-free survival (RFS) | Key secondary Distant metastasis-free survival (DMFS)
TREATMENT ARMS: Experimental Arm: Intismeran autogene (V940/mRNA-4157) 1 mg IM every 3 weeks (up to 9 doses) + Pembrolizumab 400 mg IV every 6 weeks (up to 9 cycles) | Control Arm: Placebo (vaccine) + Pembrolizumab 400 mg IV every 6 weeks (up to 9 cycles)
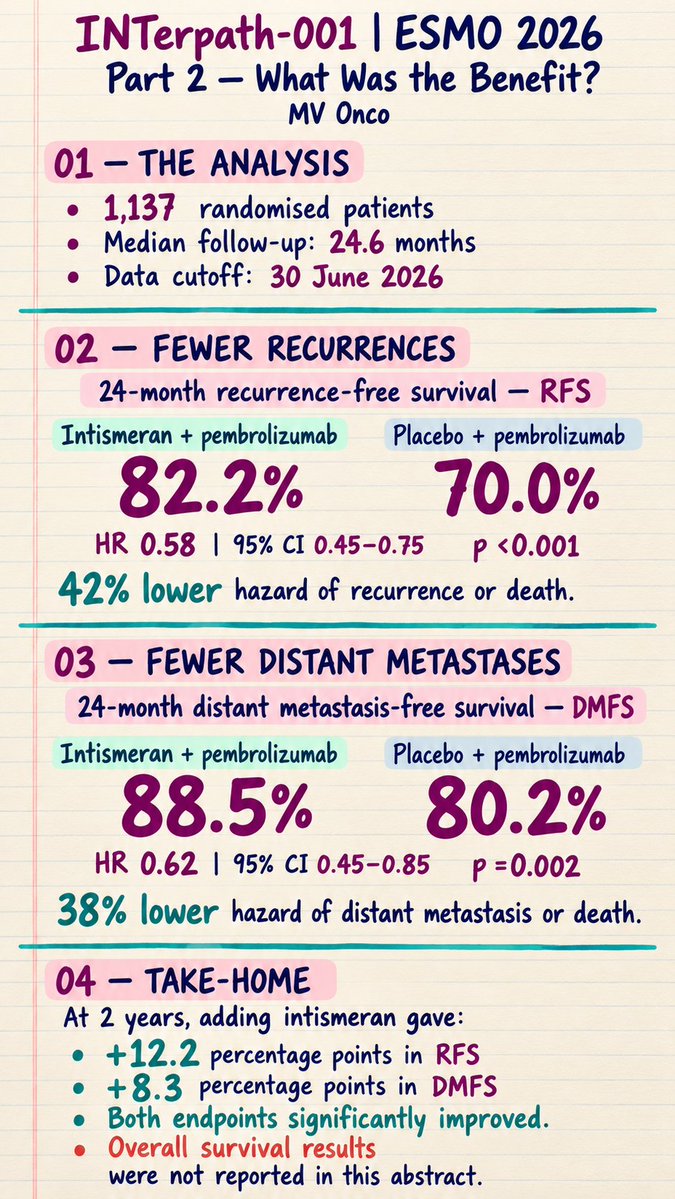
KNOWN RESULTS (Pre-Congress Topline): Recurrence-free survival (RFS) — Primary endpoint met, Significant improvement vs. pembrolizumab alone | Distant metastasis-free survival (DMFS) — Key secondary endpoint met, Significant improvement | Overall survival (OS) — Still immature, Full numerical data awaited
KEY QUESTIONS AT ESMO: Magnitude of benefit (HR, absolute rates) | Benefit across stages IIB/III/IV | Toxicity and feasibility | OS data and durability
2 VOLGA (Phase III) — LBA2 24 Oct 2026
Neoadjuvant Durvalumab + Enfortumab Vedotin ± Tremelimumab → Surgery → Adjuvant Durvalumab ± Tremelimumab in cisplatin-ineligible muscle invasive Bladder Cancer
CANCER SITE & DISEASE SETTING: Muscle-Invasive Bladder Cancer (MIBC) • Cisplatin-ineligible or cisplatin-declining • Planned radical cystectomy • Curative-intent perioperative setting
WHY IMPORTANT?: Large proportion of MIBC patients cannot receive cisplatin chemotherapy • Potential cisplatin-free perioperative strategy • May improve cure rates and expand options
TRIAL DESIGN: Phase III 695 patients | Multinational 182 centres 25 countries | Primary endpoint Event-free survival (EFS) | Key secondary Overall survival (OS)
TREATMENT ARMS (Three-arm study): Arm 1 – Triplet: Durvalumab + EV + Tremelimumab (2 cycles) → Radical cystectomy → Adjuvant: Durvalumab + Tremelimumab (1 cycle) → Durvalumab (9 cycles) | Arm 2 – Doublet: Durvalumab + EV (3 cycles) → Radical cystectomy → Adjuvant: Durvalumab (9 cycles) | Arm 3 – Control: Radical cystectomy with or without approved adjuvant treatment (standard of care)
KNOWN RESULTS (Pre-Congress Topline): Event-free survival (EFS) — Significant improvement in both experimental arms vs. control | Overall survival (OS) — Significant improvement for doublet arm; Favourable trend for triplet arm (not statistically significant at interim analysis) | Safety — No new safety signals reported
KEY QUESTIONS AT ESMO: Magnitude of EFS & OS (HR, absolute benefit) | Pathological response & downstaging | Added value of tremelimumab | Toxicity and treatment completion
3 ANZUP1801 / DASL-HiCaP (Phase III) — LBA4 25 Oct 2026
Darolutamide + ADT + Radiotherapy vs. ADT + Radiotherapy for very high risk localized Prostate Cancer
CANCER SITE & DISEASE SETTING: Prostate Cancer • Very high risk localized disease • Includes selected post-prostatectomy salvage RT patients • Non-metastatic, curative-intent
WHY IMPORTANT?: High risk of metastatic relapse despite ADT + RT • Tests benefit of adding darolutamide (potent AR inhibitor) in non-metastatic setting • Could change standard in very high risk prostate cancer
TRIAL DESIGN: Phase III 1,106 patients | International, randomized, double-blind | Primary endpoint To be confirmed (e.g. metastasis-free survival) | Key endpoints Metastasis-free survival, Biochemical progression, Overall survival
TREATMENT ARMS: Experimental Arm: Darolutamide + ADT + Radiotherapy | Control Arm: Placebo + ADT + Radiotherapy
PATIENT POPULATION (Key features): Definitive RT cohort: Very high risk (Grade Group 4–5, selected GG4, node-positive) | Post-prostatectomy cohort: Persistent/rising PSA with very high risk pathological features | Excludes distant metastatic disease
KNOWN RESULTS (Pre-Congress): Interim analysis results to be presented at ESMO 2026. Full numerical data (MFS, OS, toxicity) not yet available.
KEY QUESTIONS AT ESMO: Magnitude of MFS/OS and absolute benefit | Subgroup analysis (definitive vs. salvage, GG, nodal) | Toxicity and treatment duration | Long-term outcomes and change in practice
[Slide 3]
ESMO 2026 MADRID SPAIN ESMO CONGRESS · 23 – 27 October 2026 · IFEMA MADRID Madrid, Spain · SCIENCE BETTER MEDICINE BRIGHTER LIVES · ESMO CONGRESS 2026 MADRID
Top ESMO 2026 Abstracts to Watch – Detailed Overview (Abstracts 4 to 7)
4 LITESPARK-011 (Phase III)
Belzutifan + Lenvatinib vs. Cabozantinib in Advanced/Metastatic Renal Cell Carcinoma
RATIONALE: • After prior PD-1/PD-L1 immunotherapy, RCC remains challenging. • Combination of HIF-2α inhibition (belzutifan) and VEGF inhibition (lenvatinib) may be more effective than cabotantinib.
MECHANISM OF ACTION: Belzutifan (HIF-2α inhibitor) — VHL loss → HIF-2α ↑ Tumour growth, angiogenesis, metabolism | Lenvatinib (multikinase inhibitor) — Inhibits VEGFR and other kinases → reduces angiogenesis
TRIAL DESIGN: 747 patients | Phase III Randomized Open-label | Population: Advanced ccRCC after anti-PD-1/PD-L1 therapy
ARMS: Belzutifan + Lenvatinib — Belzutifan 120 mg OD + Lenvatinib 20 mg OD (1:1 randomization) | Cabozantinib — 60 mg OD
KEY RESULTS (Published): Progression-free survival (PFS) 14.8 months vs. 10.7 months, HR 0.70 (95% CI 0.59–0.84), p < 0.0001 | Overall survival (OS) 34.9 months vs. 27.6 months, HR 0.85 (95% CI 0.88–1.05), Not statistically significant (at interim analysis)
SAFETY (Grade ≥3 AEs): • 84% vs. 83% (experimental vs. control) • Hypertension: 31% vs. 29% • Monitor: hypertension, anemia, hypoxia, proteinuria, renal function
KEY TAKEAWAY: Significant PFS benefit; final OS results awaited at ESMO 2026.
5 DeLLphi-305 (Phase III)
Tarlatamab + Durvalumab vs. Durvalumab in Extensive-Stage Small Cell Lung Cancer
RATIONALE: • Extensive-stage SCLC displays high relapse rates after initial chemo + I/O. • DLL3-targeted T-cell engager may enhance immune response during maintenance.
MECHANISM OF ACTION: Tarlatamab (DLL3 × CD3 bispecific T-cell engager) — Brings T cells to DLL3-expressing tumour cells → T-cell mediated killing | Durvalumab (anti-PD-L1 antibody) — Blocks PD-L1 mediated immune inhibition
TRIAL DESIGN: 563 patients | Phase III Randomized Global study | Population: ES-SCLC without progression after platinum + etoposide + durvalumab induction
ARMS: Tarlatamab + Durvalumab — Maintenance until progression VS Durvalumab alone — Maintenance until progression
KEY RESULTS (Topline): Overall survival (OS) – primary endpoint met, Statistically significant improvement | Progression-free survival (PFS) – significant improvement | Objective response rate (ORR) – improved | Full numerical data awaited at ESMO 2026
SAFETY: • Consistent with known profiles • Key risks: cytokine-release syndrome (CRS), neurological toxicity (ICANS), infusion reactions
KEY TAKEAWAY: First-line maintenance with DLL3-targeted T-cell engager shows significant OS benefit (topline).
6 SAFFRON (Phase III)
Osimertinib + Savolitinib vs. Chemotherapy in EGFR-Mutated NSCLC with MET Overexpression/Amplification
RATIONALE: • MET overexpression or amplification is a key resistance mechanism after osimertinib. • Dual EGFR/MET inhibition may overcome resistance and delay chemotherapy.
MECHANISM OF ACTION: Osimertinib (EGFR TKI) — Continues inhibition of mutant EGFR signalling | Savolitinib (selective MET inhibitor) — Inhibits MET signalling bypass pathway
TRIAL DESIGN: (Number not publicly specified, large Phase III study) | Phase III Randomized Global study | Population: EGFR-mutated NSCLC with MET overexpression or amplification after osimertinib
ARMS: Osimertinib + Savolitinib (oral combination) VS Platinum + Pemetrexed (chemotherapy)
KEY RESULTS (Topline): Progression-free survival (PFS) – significant improvement | Overall survival (OS) – significant improvement | Consistent benefit across key subgroups (as per topline) | Full numerical data awaited at ESMO 2026
SAFETY: • Consistent with known profiles of osimertinib and savolitinib • Monitor: interstitial lung disease, hepatotoxicity, edema and other class-specific AEs
KEY TAKEAWAY: Potential new standard for EGFR-mutated NSCLC with MET-driven resistance after osimertinib, if OS benefit confirmed in full data.
7 CLARITY-Gastric01 (Phase III)
Sonesitatug Vedotin (CLDN18.2 ADC) vs. Physician's Choice in Advanced/Metastatic Gastric/GEJ Adenocarcinoma
RATIONALE: • Poor outcomes after first-line therapy in advanced gastric/GEJ cancer. • CLDN18.2 is a validated target. • Antibody–drug conjugate delivers cytotoxic payload directly to CLDN18.2-expressing tumour cells.
MECHANISM OF ACTION: 1 Target binding — Anti-CLDN18.2 antibody binds tumour cells | 2 Internalization — ADC internalized into tumour cell | 3 Cytotoxic effect — Release of MMAE payload → cell death
TRIAL DESIGN: ~600 patients | Phase III Randomized Global study | Population: CLDN18.2 positive (≥25% tumour cells) 2L+ advanced gastric/GEJ or oesophageal adenocarcinoma
ARMS: Sonesitatug Vedotin — 2.2 mg/kg IV Q3W VS Investigator's Choice — (Ramucirumab + paclitaxel, paclitaxel, docetaxel, irinotecan, TAS-102, or apatinib depending on line and region)
KEY RESULTS (Topline): Overall survival (OS) in 3L+ population – primary endpoint met | Overall survival (OS) in 2L+ population – significant improvement | Progression-free survival (PFS) – favourable trend, not statistically significant | Full numerical data to be presented at ESMO 2026
SAFETY: • No new safety signals reported • Main AEs: peripheral neuropathy, neutropenia, gastrointestinal toxicity (MMAE-related)
KEY TAKEAWAY: CLDN18.2-targeted ADC shows OS benefit in previously treated advanced gastric/GEJ cancer; full data needed to define magnitude, PFS and safety profile.
[Slide 4]
ESMO 2026 MADRID SPAIN ESMO CONGRESS · SCIENCE · BETTER MEDICINE · BRIGHTER LIVES · 23 – 27 October 2026 · IFEMA MADRID Madrid, Spain · ESMO CONGRESS 2026 MADRID
Top ESMO 2026 Abstracts to Watch – Detailed Overview (Abstracts 8 to 10)
8 BREAST CANCER – 4 KEY TRIALS From early stage to metastatic disease
8A TALENT (Phase II) Neoadjuvant T-DXd in HER2-low, HR+ early breast cancer
STUDY DESIGN: HER2-low, HR+ early breast cancer | Phase II (Neoadjuvant) | Arms: T-DXd alone, T-DXd + anastrozole, T-DXd → chemotherapy | Primary endpoint: pCR
MECHANISM: T-DXd — Anti-HER2 antibody; Topoisomerase-I payload; Bystander effect on neighbouring tumour cells
KEY QUESTIONS AT ESMO: Pathological complete response (pCR) rates | Residual cancer burden | Benefit of adding anastrozole | Can chemotherapy be reduced? | Safety (ILD, nausea, cytopenias)
8B NATALEE (Phase III) 6-year follow up of adjuvant ribociclib in HR+/HER2– early breast cancer
STUDY DESIGN: Stage II–III (incl. selected node-negative) HR+/HER2– | ~5,100 patients | Ribociclib 400 mg daily (3 weeks on/1 week off) × 3 years + endocrine therapy | Endpoint: iDFS (primary), OS
KEY RESULTS (5-year, published): Invasive disease-free survival (iDFS) 85.5% Ribociclib + ET vs 81.0% ET alone; Absolute difference: 4.5%; HR 0.716 (95% CI 0.618–0.829) | Overall survival (5-year) HR 0.800 (95% CI 0.637–1.003) Favourable trend, not statistically significant
KEY QUESTIONS AT ESMO (6-year update): Does OS become statistically significant? | Persistence of iDFS benefit after stopping ribociclib | Subgroup analysis (node-negative vs positive) | Long-term safety (QT prolongation, LFT, neutropenia)
8C postMONARCH (Phase III) Abemaciclib + fulvestrant after progression on prior CDK4/6 inhibitor
STUDY DESIGN: HR+/HER2– metastatic breast cancer after CDK4/6 inhibitor + endocrine therapy | 368 patients | Abemaciclib + fulvestrant vs placebo + fulvestrant | Primary endpoint: PFS; Key secondary endpoint: OS
KEY RESULTS (published): Median PFS 6.0 mo vs 5.3 mo; HR 0.73 (Investigator-assessed) | [header reads 'Coxicty (durvica)' — garbled] HR 0.55 (Blinded independent central review); HR 0.55 (Blinded independen[t])
KEY QUESTIONS AT ESMO (OS update): Overall survival benefit? | Consistency across subgroups | Toxicity (diarrhoea, neutropenia, VTE) | Positioning vs other post-CDK4/6 options (oral SERDs, ADCs)
8D VIKTORIA-1 (Phase III) Gedatolisib + fulvestrant ± palbociclib in HR+/HER2– advanced breast cancer
STUDY DESIGN: After endocrine therapy + CDK4/6 inhibitor | Gedatolisib + fulvestrant ± palbociclib vs fulvestrant (control) | Includes PIK3CA wild-type cohort
PREVIOUS KEY RESULTS [header partly garbled]: table — Median PFS | HR (vs fulvestrant): Gedatolisib + Fulv + Palbo 9.3 mo | 0.24; Gedatolisib + Fulv – | 0.33; Fulvestrant alone 2.0 mo | –
KEY QUESTIONS AT ESMO (Update): Updated PFS and OS | Incremental value of palbociclib | Toxicity (stomatitis, rash, [garbled]) | Role in PIK3CA WT disease
9 MOIO (Phase III) Reduced-frequency immunotherapy in multiple metastatic cancers
CLINICAL QUESTION: In patients with metastatic cancers who have achieved a partial or complete response after 6 months of standard immunotherapy, can treatment frequency be reduced to once every 3 months without compromising efficacy?
STUDY DESIGN: Phase III, randomized non-inferiority trial | Multiple solid tumours | Patients with CR or PR after 6 months of standard checkpoint inhibitor therapy | Reduced-frequency dosing (every 3 months, same dose) vs standard dosing frequency | Primary endpoint: Non-inferiority for efficacy
RATIONALE: Maintain durable response with lower treatment burden — Reduce hospital visits | Less treatment burden & cost | Potential for fewer immune-related AEs | Maintain long-term disease control
PATIENT POPULATION: Metastatic cancers (multiple primary sites) with partial or complete response after 6 months of standard immunotherapy
KEY EXCLUSIONS: • Selected melanoma CR • Selected favourable-risk RCC on TKI + IO • Other protocol-specified exclusions
KEY POINTS AT ESMO: Non-inferiority outcome (hazard ratio, confidence intervals) | Consistency across tumour types | Duration of follow-up and durability | Immune-related adverse events | Impact on real-world practice and cost
POTENTIAL IMPACT: If non-inferiority is shown: • Less frequent infusions • Reduced cost and logistical burden • May maintain efficacy • Could improve patient quality of life
IMPORTANT CONSIDERATIONS: • Non-inferiority trial (not superiority) • Predefined non-inferiority margin is critical • Results may not apply to all tumour types • Long-term outcomes and safety are key
10 TroFuse-005 (Phase III) Sacituzumab tirumotecan (Sac-TMT) in advanced/recurrent endometrial cancer
CLINICAL QUESTION: Can a TROP-2 targeted antibody–drug conjugate improve overall survival and progression-free survival in advanced or recurrent endometrial cancer after platinum-based chemotherapy and immunotherapy?
STUDY DESIGN: Phase III, randomized, global study | Advanced/recurrent endometrial cancer | Prior platinum-based chemotherapy and anti-PD-1/PD-L1 immunotherapy (together or sequentially) | Sacituzumab tirumotecan vs physician's-choice chemotherapy (doxorubicin or paclitaxel) | Primary endpoints: OS and PFS
MECHANISM OF ACTION: Sacituzumab tirumotecan (TROP-2 ADC) — Anti-TROP-2 antibody; Linker; Cytotoxic payload (TOP1 Inhibitor); TROP-2. Binds TROP-2 → internalization → release of payload → tumour cell death
KEY RESULTS (Pre-Congress Topline): Overall survival (OS) – primary endpoint met (statistically significant and clinically meaningful improvement) | Progression-free survival (PFS) – primary endpoint met | Full numerical data (median OS, PFS, HRs) to be presented at ESMO 2026
PATIENT POPULATION: ~600 patients Advanced/recurrent endometrial cancer after platinum chemotherapy and immunotherapy
CONTROL ARM: Physician's choice: Doxorubicin or paclitaxel (as per protocol and region)
KEY QUESTIONS AT ESMO: Magnitude of OS and PFS benefit (HR, medians, landmark rates) | Efficacy across histological subtypes and molecular subgroups | Safety (neutropenia, diarrhoea, nausea, neuropathy) | Positioning vs other therapies in this setting
POTENTIAL IMPACT: First positive Phase III ADC in this setting | Addresses unmet need after chemo + immunotherapy | Could establish new standard of care if benefit is confirmed
[Slide 1]
ESMO GOOD SCIENCE BETTER MEDICINE BEST PRACTICE
ESMO 2026 · MADRID
GUT ONC LAB
GI ABSTRACTS I'M WATCHING
Oct 23–27 · Times are Madrid local (CEST through Oct 24, CET from Oct 25)
BELOW THE BELT
AZUR-1 LBA87 Sun 25 11:00
Dostarlimab alone in stage II/III MSI-H rectal cancer
This will be positive. Incredibly positive. This is already what I'm doing in clinical practice and is a massive step forward for the 5–10% of rectal cancer patients that are MSI-H. Yay.
IROCAS LBA29 Sun 25 10:15
Adjuvant mFOLFIRINOX vs mFOLFOX6, T4/N2 colon
Important study, and honestly, it is going to predict if US-CIRCULATE will be positive. If this is negative, CIRCULATE will be a nail-biter.
CheckMate 8HW LBA32 Sat 24 15:42
Final OS: nivo/ipi vs nivo vs chemo, MSI-H mCRC
What happens when you do a trial with an agent that essentially cures a disease against another that cures most people? It is a really long damn trial. Excited for the final OS data. Will it be positive? TBD, but I certainly think the magnitude of benefit of dual IO makes it better than single agent, and this data could reinforce that practice.
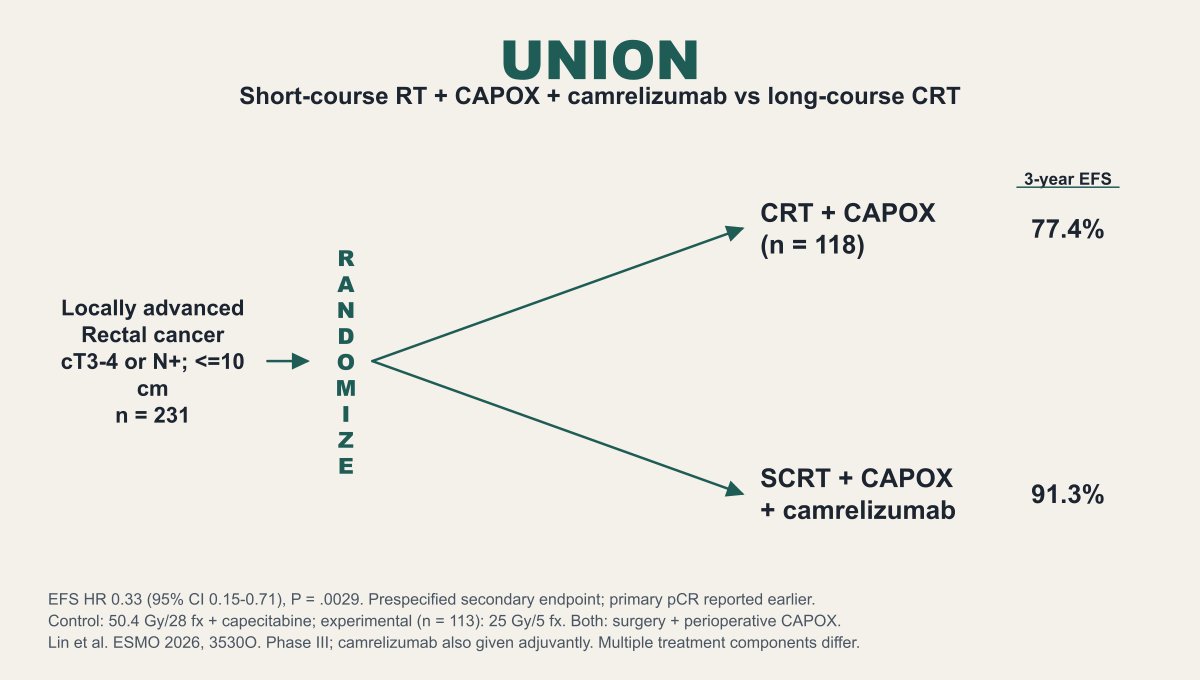
UNION 3530O Sun 25 11:10
SCRT → camrelizumab + CAPOX, locally advanced rectal
pCR reported at ~40% in 2024, let's see if more people were cured. Some criticism in changing radiation schedule and adding IO compared to standard, but will set the stage for future studies.
EMT2 LBA30 Sun 25 10:25
EPA vs placebo after CRC liver metastasis resection
It's like fish oil but better. File this in the ALASCCA category of "costs nothing, helps people" if positive. ALASCCA + CHALLENGE <3
QTX3034 790RO Sat 24 15:15
KRAS G12D inhibitor + cetuximab ± mFOLFOX6, mCRC
Sick study. Moving us to molecularly driven treatments in earlier line settings for CRC. Where the field MUST move. If this isn't positive I will eat a hat (a small one, preferably organic).
EC + FOLFIRI beyond PD 788RO Sat 24 14:50
Continuing encorafenib + cetuximab past progression, BRAF V600E mCRC
Already doing this in clinical practice with patients who have BRAF+ disease w/o resistance mechanism on ctDNA at progression. Data for its use is HUGELY welcome.
BOT/BAL in the real world
905eP ePoster · 3771P Mon 26 12:00
Botensilimab + balstilimab: refractory MSS mCRC (AGEO) and advanced sarcoma (Spanish EAP)
Gives us a look at Bot Bal in real world. Important data, multiple attempts to use CPI in advanced disease have provided mixed results, what happens when we use stronger agents?
RUNNER-UP
Biweekly TAS-102 + bev LBA31 Sat 24 15:37
Biweekly vs standard schedule, refractory mCRC
Runner up only because Cathy Eng already convincingly showed this is the dosing schedule we should be using. I already use this in clinical practice. Great to randomize but should be positive.
UPPER GI
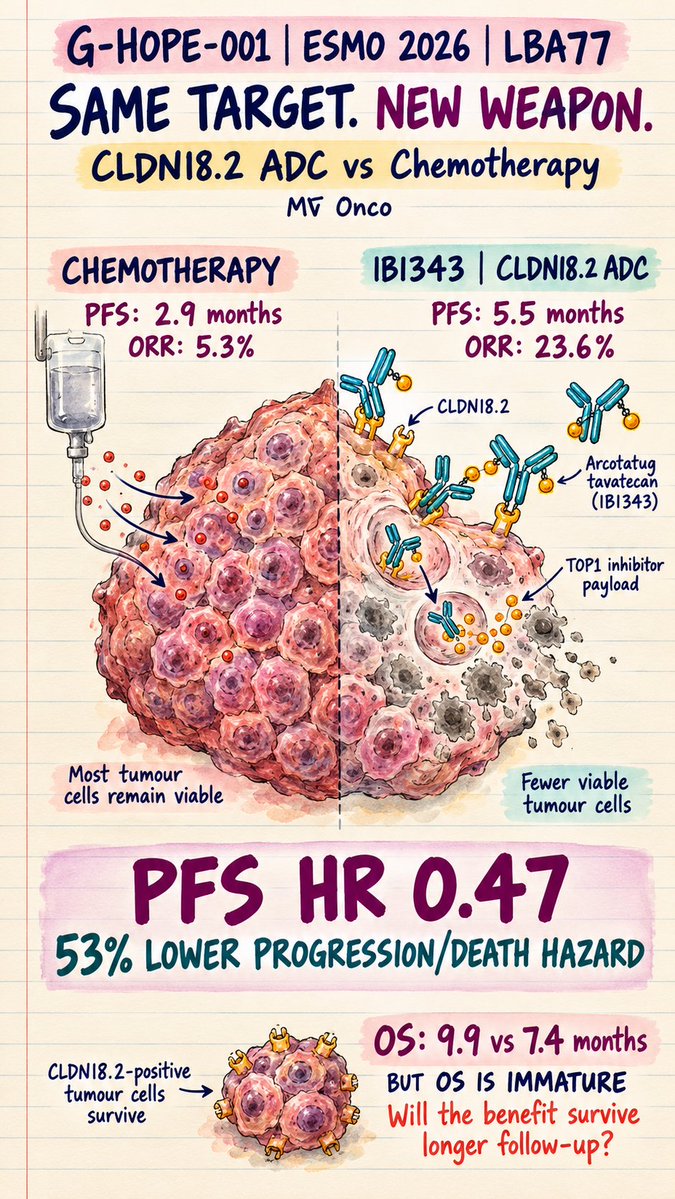
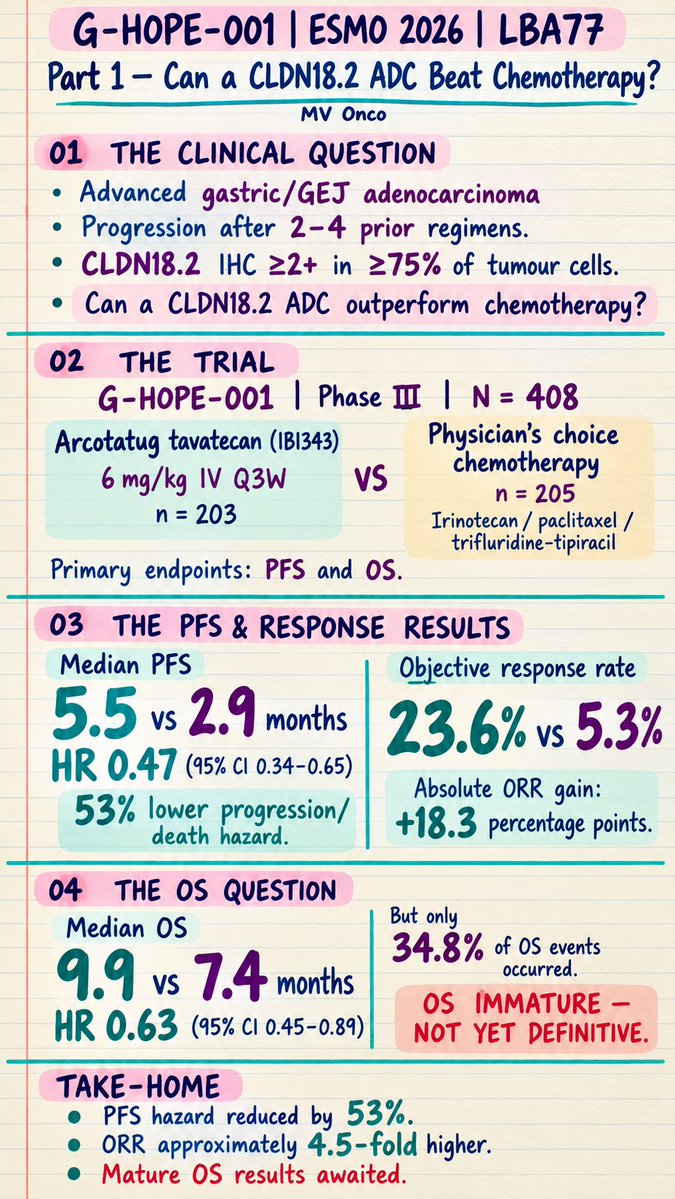
CLARITY-Gastric01 + G-HOPE-001
LBA7 Sun 25 17:18 · LBA77 Fri 23 13:30
CLDN18.2 ADCs, pretreated gastric/GEJ
The next generation of CLDN18.2 is here. Expect less explosive emesis and improved outcomes.
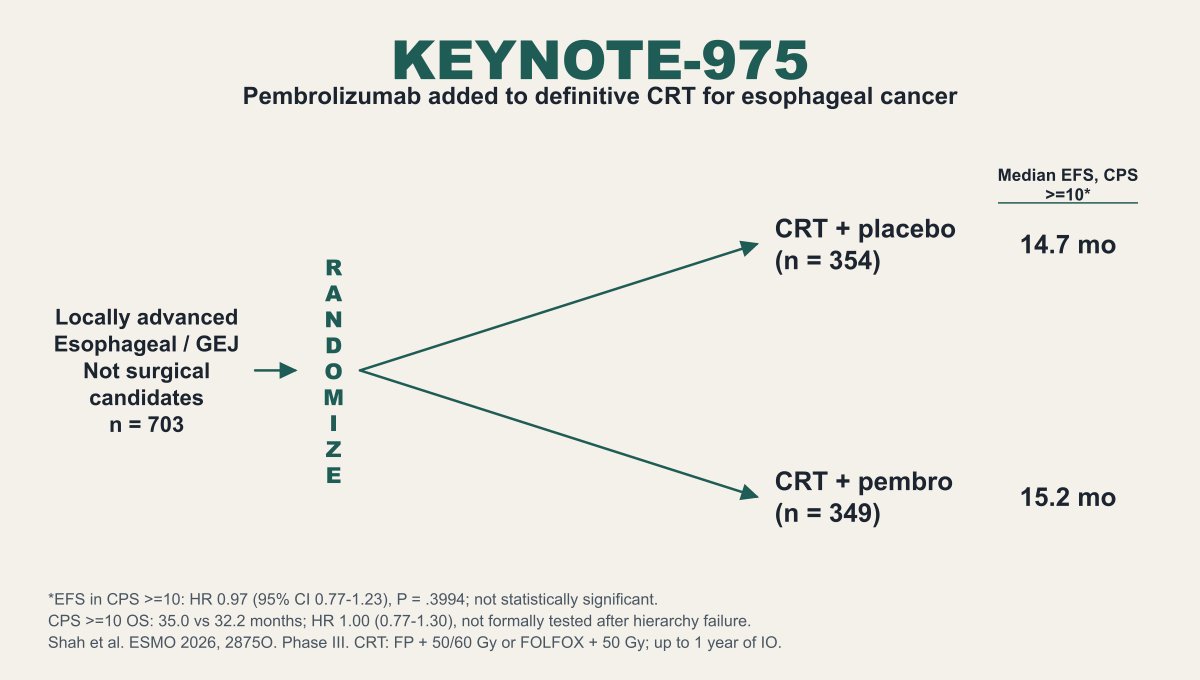
KEYNOTE-975 2875O Fri 23 13:50
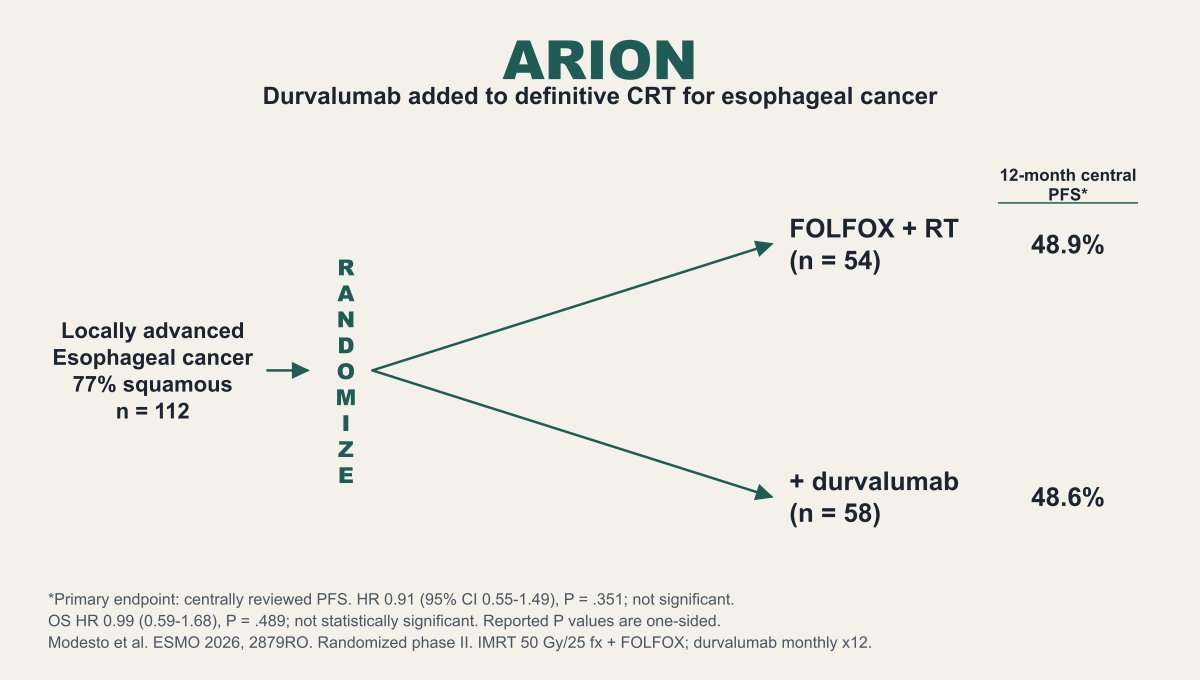
Pembro + definitive chemoRT, esophageal/GEJ
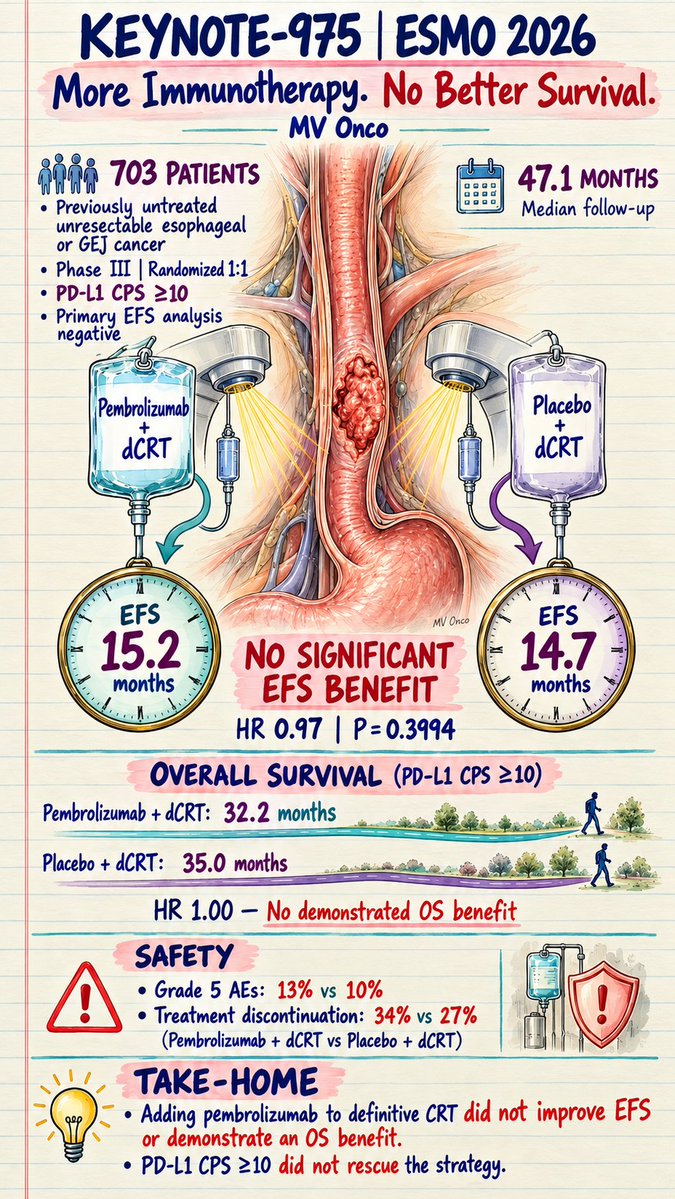
Merck joins the D-FLOT era for patients still receiving definitive chemoRT. After the CROSS/FLOT study the impact of this is going to be less, but still important for patients receiving definitive chemoRT.
HERIZON-GEA-01 LBA79 Fri 23 16:15
Zanidatamab ± tislelizumab, 1L HER2+ GEA
My practice in HER2+ upper GI/GEA has moved to Zani, will be helpful to see the longer-term outcomes here.
SANO LBA78 Fri 23 13:40
Active surveillance vs surgery after nCRT, long-term
People deserve to keep their organs. Our ability to offer this only improves when we layer in tools like ctDNA. Interested in what we can extrapolate to other organ systems (especially for MSI-H).
PANCREAS
RASolute 302 LBA82 Fri 23 14:22
Daraxonrasib subgroups, 2L+ metastatic PDAC
Every subgroup likely benefited. G12V more than others. Maybe there will be another standing ovation? Come for the science, stay for the clapping.
AMPLIFY-7P LBA83 Fri 23 14:32
mKRAS vaccine vs observation, resected PDAC
Vaccine therapies are the next frontier. Merck has pushed them forward in Melanoma where they are an amazing success, very interested in the randomized data here. Even if negative it will be critical data to learn from.
HCC / BILIARY
HARMONi-GI1 LBA8 Sun 25 17:42
Ivonescimab vs durvalumab + GemCis, 1L BTC
PD-1/VEGF emerges in GI. Let's see the benefit. China only.
ACTICCA-1 LBA21 Sat 24 10:25
Adjuvant GemCis vs capecitabine, resected BTC
Might immediately change the standard of care for resected BTC. Worth tuning in for.
Nicholas J. Hornstein, MD, PhD
Full abstracts online Oct 19 · LBAs at presentation
[Slide 1]
MY TOP 10 LUNG CANCER ABSTRACTS
#ESMO26
01 LBA3 DeLLphi-305
Phase III primary analysis: Tarlatamab + durvalumab vs durvalumab as 1L maintenance after durvalumab + platinum/etoposide in ES-SCLC
Jacob Sands
02 2614O PERSEE
Phase III pembrolizumab with or without platinum-based chemotherapy as 1L treatment in advanced NSCLC with PD-L1 ≥50%
Chantal Decroisette
03 LBA66 OptiTROP-Lung06
Phase III sacituzumab tirumotecan + pembrolizumab vs chemotherapy + pembrolizumab in 1L PD-L1-negative advanced non-squamous NSCLC
Caicun Zhou
04 LBA6 SAFFRON
Phase III primary results: Osimertinib + savolitinib vs platinum–pemetrexed in EGFR-mutant, MET-overexpressed/amplified advanced NSCLC after osimertinib
Shun Lu
05 LBA5 KRAScendo 1
Phase III divarasib vs sotorasib or adagrasib in previously treated advanced KRAS G12C-mutated NSCLC
Ferdinandos Skoulidis
06 LBA67 OptiTROP-Lung04
Final OS analysis: Sacituzumab tirumotecan vs platinum-based chemotherapy in EGFR-mutated NSCLC after EGFR-TKI progression
Wen Feng Fang
07 2613O SARON
Primary results: Randomized trial of consolidation radiotherapy for synchronous oligometastatic NSCLC
Fiona McDonald
08 LBA69 SANOVO
Phase III savolitinib or placebo + osimertinib in treatment-naïve advanced NSCLC with EGFR mutation and MET overexpression
Yi-Long Wu
09 LBA71 PANKU-Lung01
Phase III izalontamab brengitecan in EGFR-mutant non-squamous NSCLC after progression on a third-generation EGFR TKI
Li Zhang
10 LBA73 PACE-LUNG
Single-arm phase II: Adding chemotherapy for EGFR-mutant NSCLC with persistent plasma EGFR-mutant ctDNA at week 3 of 1L osimertinib
Martin Sebastian
@dr_yakupergun
[Slide 1]
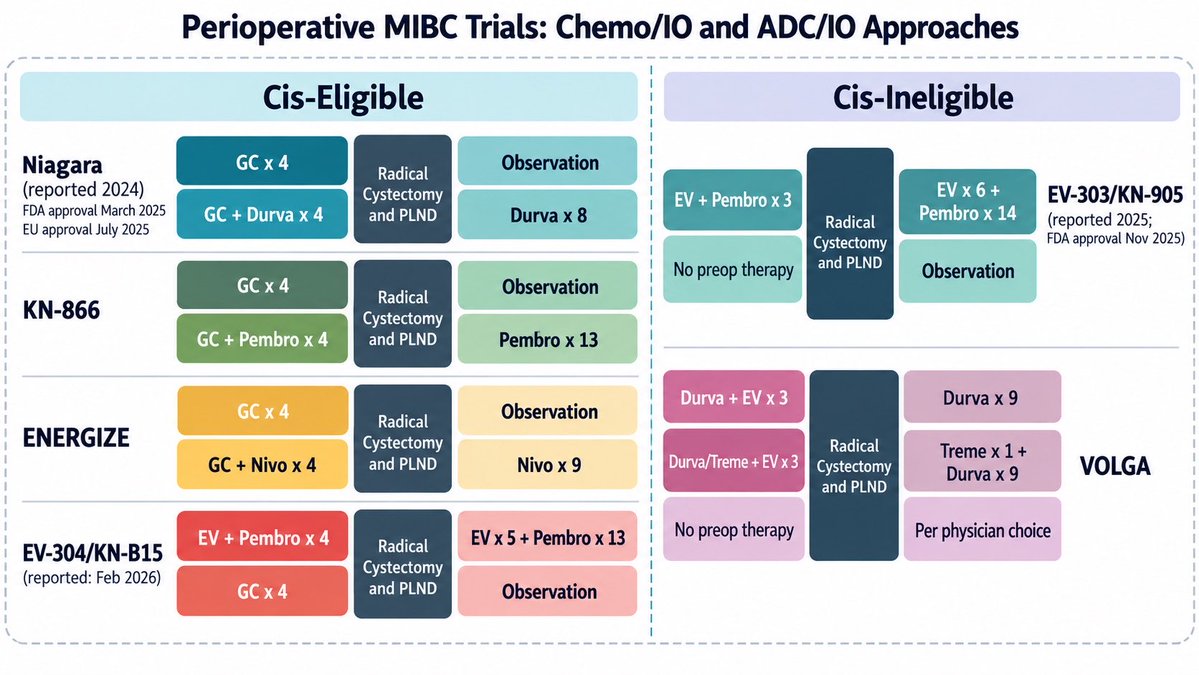
Perioperative MIBC Trials: Chemo/IO and ADC/IO Approaches
Cis-Eligible
Niagara (reported 2024) FDA approval March 2025 EU approval July 2025
GC x 4 | Radical Cystectomy and PLND | Observation
GC + Durva x 4 | Radical Cystectomy and PLND | Durva x 8
KN-866
GC x 4 | Radical Cystectomy and PLND | Observation
GC + Pembro x 4 | Radical Cystectomy and PLND | Pembro x 13
ENERGIZE
GC x 4 | Radical Cystectomy and PLND | Observation
GC + Nivo x 4 | Radical Cystectomy and PLND | Nivo x 9
EV-304/KN-B15 (reported: Feb 2026)
EV + Pembro x 4 | Radical Cystectomy and PLND | EV x 5 + Pembro x 13
GC x 4 | Radical Cystectomy and PLND | Observation
Cis-Ineligible
EV-303/KN-905 (reported 2025; FDA approval Nov 2025)
EV + Pembro x 3 | Radical Cystectomy and PLND | EV x 6 + Pembro x 14
No preop therapy | Radical Cystectomy and PLND | Observation
VOLGA
Durva + EV x 3 | Radical Cystectomy and PLND | Durva x 9
Durva/Treme + EV x 3 | Radical Cystectomy and PLND | Treme x 1 + Durva x 9
No preop therapy | Radical Cystectomy and PLND | Per physician choice
#ESMO26 - SPOTLIGHT ON KEY GI ABSTRACTS
(Abstracts to be released Oct 19th)
@GillSharlene
GI Upper Digestive
Presidential Symposium (Oct 25)
LBA7 - CLARITY-Gastric 01 (CG-01): a Phase 3 study of sonesitatug vedotin (Sone-Ve) in second or later-line (2L+) advanced or metastatic Claudin 18.2 (CLDN18.2) positive gastroesophageal carcinoma (GEC). Dr. Rui-Hua Xu (China)
LBA8 - HARMONi-GI1 - Ivonescimab plus chemotherapy versus durvalumab plus chemotherapy as first-line treatment for advanced biliary tract cancer: A randomized, controlled, double-blinded phase 3 trial. Dr. Jian Zhou (China)
Proffered Paper Session 1 (Oct 23)
LBA77 - G-HOPE-001 - Arcotatug tavatecan (IBI343/TAK-921) versus treatment of physician's choice in previously treated advanced gastric or gastroesophageal junction adenocarcinoma: First interim analysis of the randomized phase 3 G-HOPE-001 study. Dr. Kohei Shitara (Japan)
LBA78 - SANO - Active surveillance versus standard surgery after neoadjuvant chemoradiotherapy for oesophageal cancer: Long-term results of a cluster-randomised controlled trial. Dr. Sanjiv S. Gangaram-Panday (Netherlands)
2875O - KEYNOTE-975 - Pembrolizumab or placebo plus concurrent definitive chemoradiotherapy in esophageal and gastroesophageal junction cancer: The phase 3 randomized KEYNOTE-975 study. Dr. Manish Shah (USA)
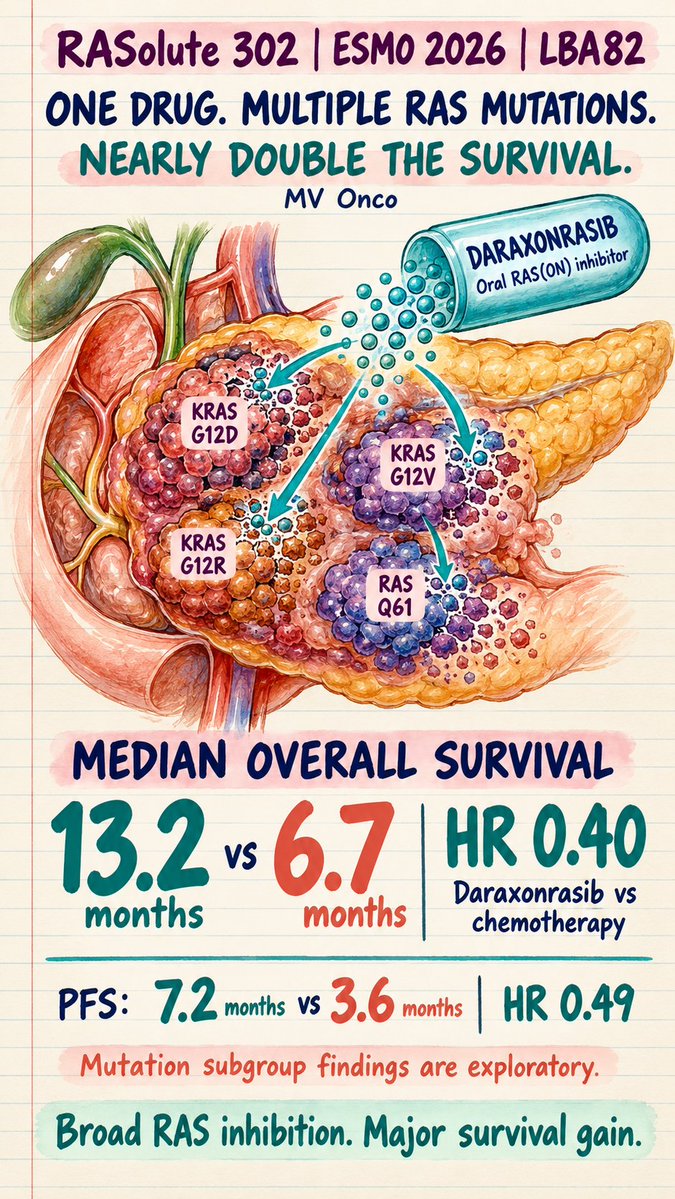
LBA82 - Daraxonrasib, a RAS(ON) multi-selective inhibitor vs chemotherapy in previously treated metastatic pancreatic adenocarcinoma (mPDAC): Additional subgroup analyses from the Ph3 RASolute 302 study. Dr. Zev Wainberg (USA)
Proffered Paper Session 2 (Oct 24)
LBA21 - ACTICCA-1 - Adjuvant chemotherapy with gemcitabine and cisplatin compared with standard of care after curative-intent resection of cholangiocarcinoma and gallbladder carcinoma. Dr. Henning Wege (Germany)
459O - A randomized trial of paclitaxel +/- tovecimig in previously treated patients with advanced biliary tract cancer. Dr. Nilofer Azad (USA)
LBA48 - Liver function trajectory and post-progression outcomes in the Phase 3 EMERALD-3 study of tremelimumab (T) + durvalumab (D) +/- lenvatinib (L) + transarterial chemoembolisation (TACE) in participants (pts) with embolisation-eligible hepatocellular carcinoma (eeHCC). Dr. Masatoshi Kudo (Japan)
1679O - Phase 1 study of BGB-B2033 (GPC3 x 4-1BB bispecific antibody) Monotherapy: First Disclosure of Dose Optimization (DO) and Dose Escalation (DE) Update in Advanced Hepatocellular Carcinoma (HCC)
[remainder of list obscured by chat-app UI overlay in the screenshot]
[Slide 1]
Presentations at
2026 ESMO Congress
October 23–27, 2026
*All times CEST/CET (Please note that the time zone will switch from CEST to CET between 24 and 25 October 2026, due to the end of daylight saving time.)
Dana-Farber Cancer Institute
PRESENTATION | SPEAKER | SESSION/TIME
Friday, October 23, 2026
Personalising vaccines using peptides, DNA, mRNA and more | Patrick Ott, MD, PhD | Special Symposium Melanoma: From standard fit to bespoke care/Leon Auditorium Hall 4 | 13:30-15:00
What oncologists should know about mRNA vaccines: Perspectives from the medical oncologist | Toni Choueiri, MD | Special Session What oncologists should know about mRNA vaccines Alicante Auditorium - Hall 6 | 15:15-16:00
The best is yet to come: Immune modulating approaches in neuro-oncology | Lakshmi Nayak, MD (Chair) | Challege Your Expert Salamanca Auditorium - Hall 10 |16:15-17:00
Saturday, October 24, 2026
1842O Efficacy and safety of atirmociclib (ATI) + fulvestrant (FUL) in patients (pts) with HR+/HER2– advanced/metastatic breast cancer (mBC) who progressed on prior CDK4/6 inhibitor (CDK4/6i) in a randomized phase 2 study (FOURLIGHT-1) | Antonio Giordano, MD, PhD Presenting Author | Proffered paper 2 Breast cancer, early and advanced stage Alicante Auditorium - Hall 6 | 8:30-10:00
LBA74 First-line (1L) trastuzumab deruxtecan (T-DXd) in patients (pts) with HER2-mutant (HER2m) NSCLC: patient-reported outcomes (PROs) from DESTINY-Lung04 (DL-04) | Pasi A. Jänne, MD, PhD Discussant (Chair) | Rapid oral 1 NSCLC, metastatic Almeria Auditorium - Hall 9 | 8:30-10:00
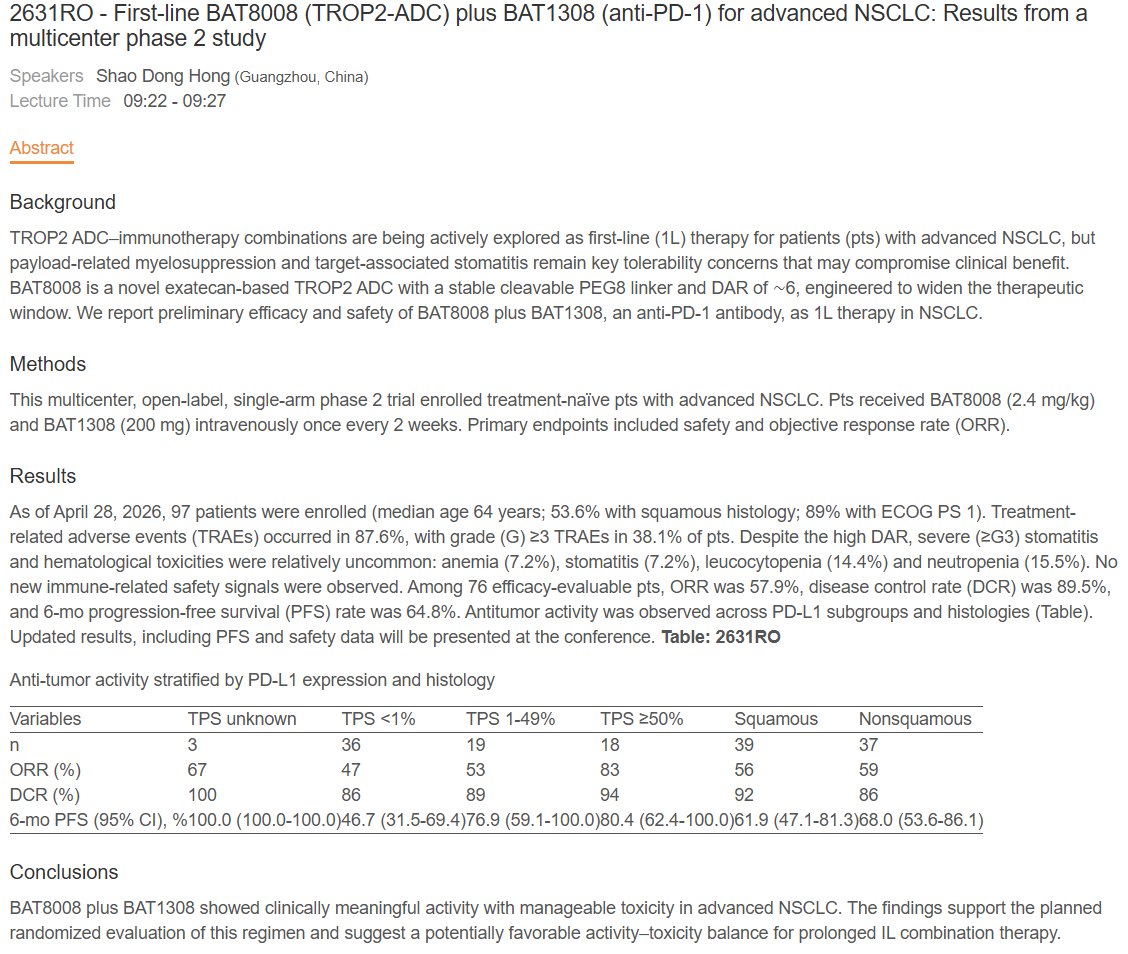
2631RO First-line BAT8008 (TROP2-ADC) plus BAT1308 (anti-PD-1) for advanced NSCLC: Results from a multicenter phase 2 study | Pasi A. Jänne, MD, PhD Discussant (Chair) | Rapid oral 1 NSCLC, metastatic Almeria Auditorium - Hall 9 | 8:30-10:00
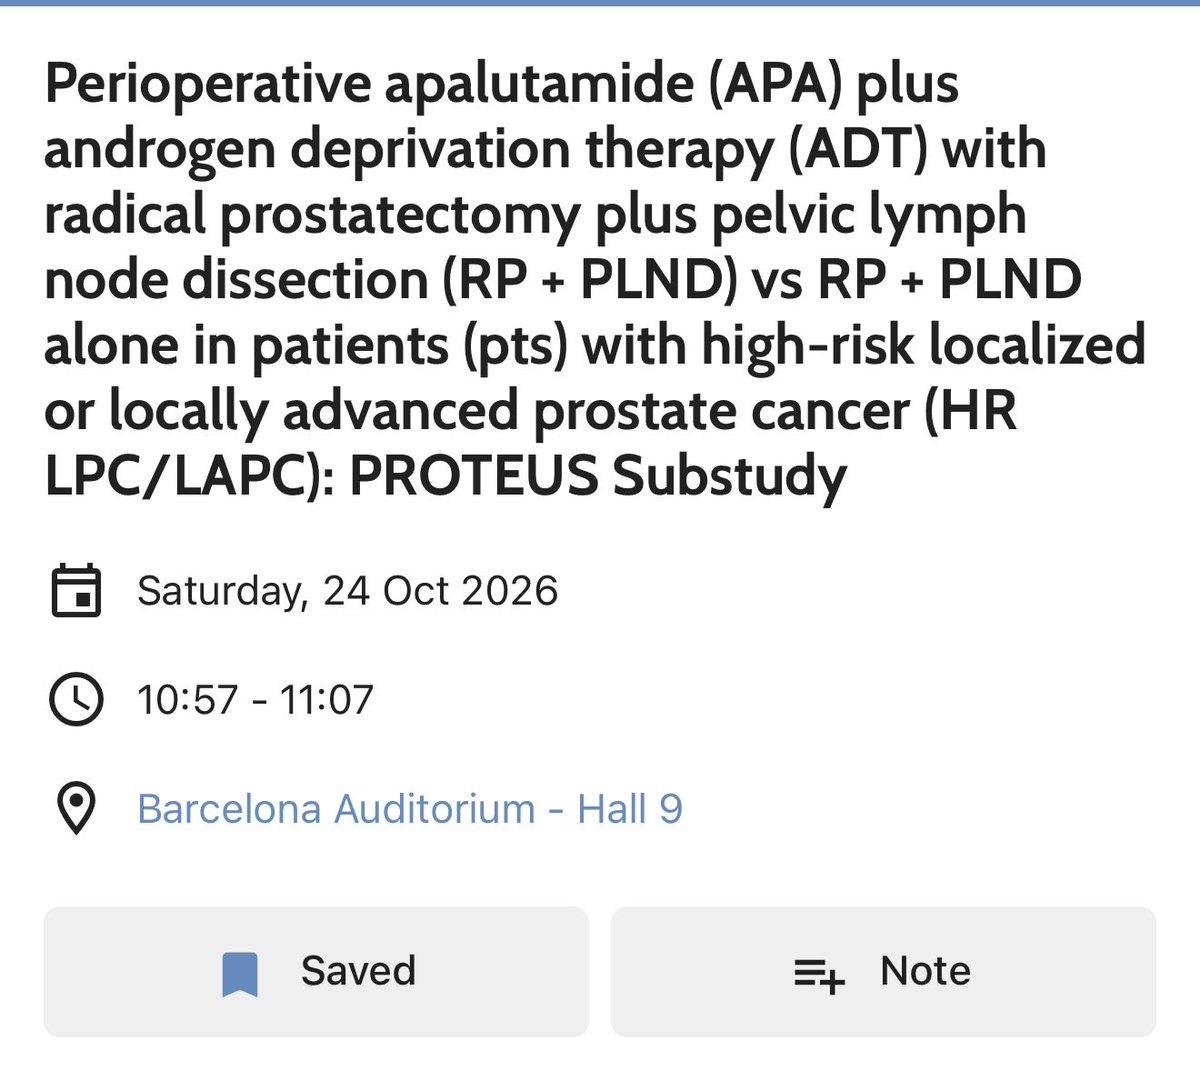
LBA53 Perioperative apalutamide (APA) plus androgen deprivation therapy (ADT) with radical prostatectomy plus pelvic lymph node dissection (RP + PLND) vs RP + PLND alone in patients (pts) with high-risk localized or locally advanced prostate cancer (HR LPC/LAPC): PROTEUS Substudy | Mary-Ellen Taplin, MD Senior Author | Proffered paper Genitourinary tumours, prostate, penile and testis Barcelona Auditorium - Hall 9 | 10:15-11:45
[Slide 2]
Presentations at
2026 ESMO Congress
October 23–27, 2026
*All times CEST/CET (Please note that the time zone will switch from CEST to CET between 24 and 25 October 2026, due to the end of daylight saving time.)
Dana-Farber Cancer Institute
PRESENTATION | SPEAKER | SESSION/TIME
Saturday, October 24, 2026 (continued)
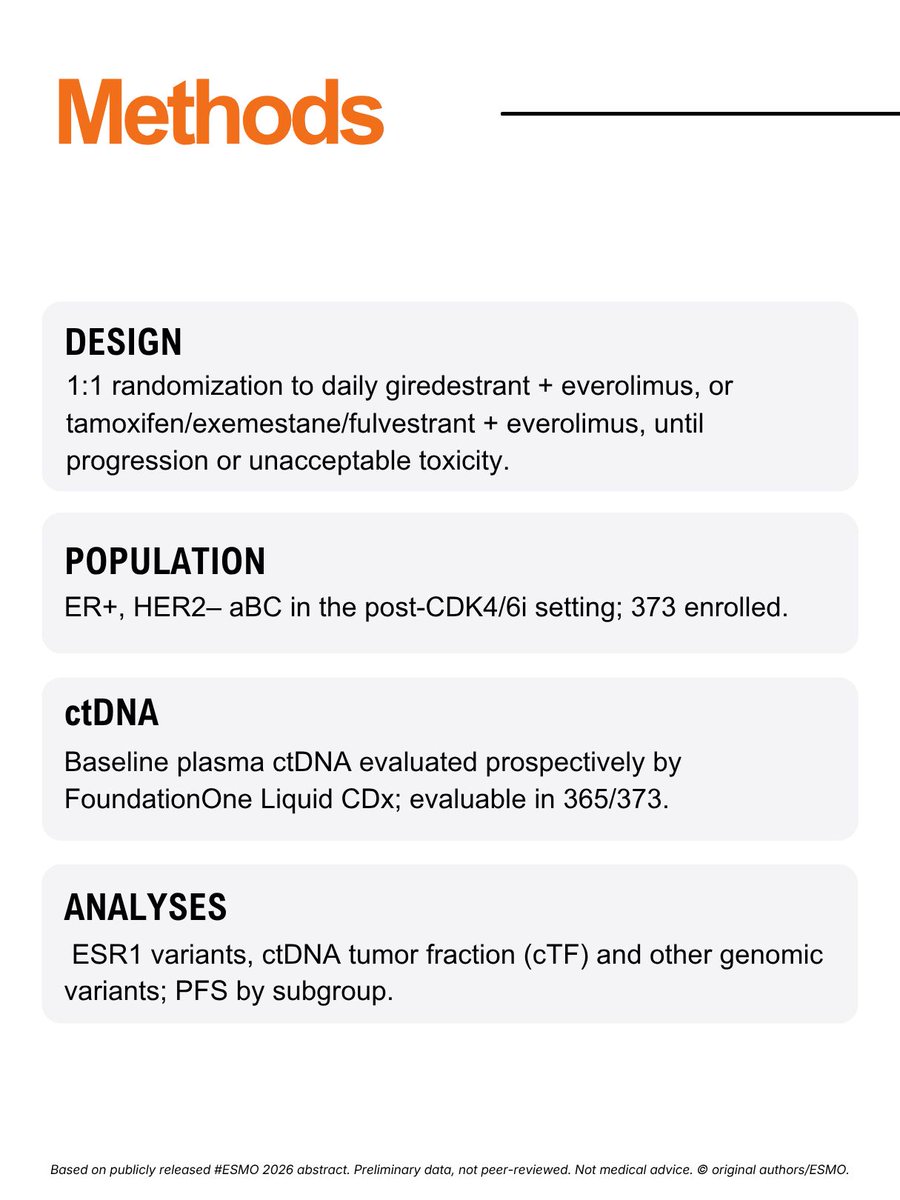
2RO Retrospective exploratory biomarker (BM) analyses from evERA Breast Cancer (BC): A Phase III trial of giredestrant (GIRE) + everolimus (E) in patients (pts) with oestrogen receptor-positive, HER2-negative advanced BC (ER+, HER2– aBC) in the post-CDK4/6 inhibitor (i) setting | Sara Tolaney, MD, MPH Presenting Author | Rapid oral 1 Breast cancer, advanced stage Almeria Auditorium - Hall 9 | 10:15-11:45
LBA3 Tarlatamab plus durvalumab (durva) vs durva as 1L maintenance (1LM) therapy following durva, platinum, and etoposide (1L durva + EP) in extensive-stage small cell lung cancer (ES-SCLC): Primary analysis of the phase 3 DeLLphi-305 trial | Jacob Sands, MD Presenting Author | Presidential Symposium 1 Alicante Auditorium - Hall 6 | 4:30-5:15
Sunday, October 25, 2026
3586O First-line pembrolizumab + lenvatinib + belzutifan or MK-1308A + lenvatinib in advanced RCC: randomized open-label phase 3 LITESPARK-012 study | Toni Choueiri, MD Presenting Author | Proffered paper 2 Genitourinary tumours, renal and urothelial Alicante Auditorium - Hall 6 | 8:30-10:00
Personalized cancer vaccines | Patrick Ott, MD, PhD | Educational Session All about cancer vaccines Almeria Auditorium - Hall 9 | 8:30-10:00
Optimising systemic therapy and sequence for stage I HER2-positive early breast cancer | Sara Tolaney, MD, MPH | Educational Session Optimising Systemic Therapy and sequence for stage I HER2-positive early breast cancer Almeria Auditorium - Hall 9 | 10:15-11:45
The modern oncologist: Leading teams in an era of complexity | Elizabeth Mittendorf, MD, PhD | Special Session ESMO-ASCO: The evolving definition of the modern oncologist Oviedo Auditorium - Hall 5 | 10:15-11:45
[Slide 3]
Presentations at
2026 ESMO Congress
October 23–27, 2026
*All times CEST/CET (Please note that the time zone will switch from CEST to CET between 24 and 25 October 2026, due to the end of daylight saving time.)
Dana-Farber Cancer Institute
PRESENTATION | SPEAKER | SESSION/TIME
Sunday, October 25, 2026 (continued)
690O Final results of the TUXEDO-3 phase II trial of patritumab deruxtecan (HER3-DXd) in active brain metastases (BMs) and leptomeningeal disease (LMD) | Nancy Lin, MD Discussant | Proffered paper CNS tumours Murcia Auditorium - Hall 3 | 10:15-11:45
691O A First in Human Phase 1 Study of Intrathecal Peptide-Pulsed Dendritic Cells for HER2+ and Triple Negative Breast Cancer Leptomeningeal Disease | Nancy Lin, MD Discussant | Proffered paper CNS tumours Murcia Auditorium - Hall 3 | 10:15-11:45
3589RO Final protocol-prespecified analysis of the phase 3 KEYNOTE-564 trial of adjuvant pembrolizumab versus placebo in clear cell renal cell carcinoma (ccRCC) | Toni Choueiri, MD Presenting Author | Rapid oral 2 Genitourinary tumours, renal and urothelial Burgos Auditorium - Hall 3 | 14:45-16:15
3593RO Plasma Kidney Injury Molecule-1 (KIM-1) Dynamics During First-Line Immunotherapy With or Without Cabozantinib in Advanced Renal Cell Carcinoma (aRCC) | Wenxin (Vincent) Xu, MD Presenting Author | Rapid oral 2 Genitourinary tumours, renal and urothelial Burgos Auditorium - Hall 3 | 14:45-16:15
Monday, October 26, 2026
4449RO Paired-biopsy multi-omic analysis reveals target-independent mechanisms of antibody–drug conjugate (ADC) resistance in metastatic breast cancer (MBC) | Paolo Tarantino, MD, PhD Presenting Author | Rapid oral 2 Breast cancer, advanced stage Alicante Auditorium - Hall 6 | 10:15-11:45
Challenges in the management of neuro-endocrine and small cell prostate cancer | Himisha Beltran, MD | Challenge Your Expert Granada Auditorium - Hall 4 | 10:15-11:00
Evolving surgical strategies after neoadjuvant immunotherapy: What should change? | Ravindra Uppaluri, MD, PhD | Special Symposium IO-based systemic therapy in head and neck cancers Granada Auditorium - Hall 4 | 16:30-18:00
[Slide 4]
Presentations at
2026 ESMO Congress
October 23–27, 2026
*All times CEST/CET (Please note that the time zone will switch from CEST to CET between 24 and 25 October 2026, due to the end of daylight saving time.)
Dana-Farber Cancer Institute
PRESENTATION | SPEAKER | SESSION/TIME
Monday, October 26, 2026 (continued)
LBA11 Sacituzumab Tirumotecan in Previously Treated Advanced or Recurrent Endometrial Cancer: Results from the Phase 3 TroFuse-005/ENGOT-en23/GOG-3095 Study | Joyce Liu, MD, MPH Discussant | Presidential Symposium III Alicante Auditorium - Hall 6 | 16:30-18:15
[Slide 1]
ESMO CONGRESS 2026 · MADRID · 23–27 OCTOBER | #ESMO2026
GU Oncology: 11 Trials I'm Watching
Presidential, late-breaking and proffered papers — sorted by tumour entity
PROSTATE 3 trials
1 DASL-HiCaP (ANZUP1801) [PRESIDENTIAL] — Darolutamide + ADT with definitive or salvage locoregional RT in localised, very high-risk prostate cancer. Presenter: Tamim Niazi
2 PROTEUS substudy [LBA 53] — Perioperative apalutamide + ADT around radical prostatectomy in high-risk localised disease. Presenter: Alberto Briganti · Sat 10:15, Proffered Paper
3 PEACE-1 — Long-term overall survival with abiraterone + prednisone in de novo metastatic castration-sensitive prostate cancer. Presenter: Karim Fizazi
"PROTEUS substudy (LBA 53) also a potential practice changer." — Prof. Boris Hadaschik, comment on the GU picks
BLADDER 4 trials
4 VOLGA [PRESIDENTIAL] — Perioperative durvalumab ± tremelimumab + neoadjuvant enfortumab vedotin in muscle-invasive bladder cancer. Presenter: Thomas B. Powles
5 KEYNOTE-866 — Perioperative pembrolizumab or placebo + neoadjuvant cisplatin/gemcitabine in MIBC. Presenter: Jens Bedke
6 Perioperative nivolumab (Ph 3) — Neoadjuvant chemotherapy alone vs chemo + nivolumab, followed by adjuvant nivolumab, in MIBC. Presenter: Andrea Necchi
7 POTOMAC — Durvalumab + BCG induction and maintenance in BCG-naïve, high-risk NMIBC. Presenter: Maria De Santis
KIDNEY 4 trials
8 LITESPARK-012 — First-line pembrolizumab + lenvatinib + belzutifan or MK-1308A + lenvatinib in advanced RCC. Presenter: Toni K. Choueiri
9 LITESPARK-011 — Final analysis: belzutifan + lenvatinib vs cabozantinib after anti-PD-(L)1 in advanced RCC. Presenter: Daniel Y. Heng
10 KEYNOTE-564 — Final protocol-prespecified analysis of adjuvant pembrolizumab vs placebo in clear-cell RCC. Presenter: Toni K. Choueiri
11 SWOG S2200 — Cabozantinib ± atezolizumab in metastatic papillary RCC. Presenter: Benjamin L. Maughan
Prof. Dr. Axel S. Merseburger
Department of Urology · UKSH Campus Lübeck
Selection builds on Toni Choueiri's GU picks + PROTEUS added · clinical trials only
[Slide 1]
ESMO 2026 — ABSTRACTS TO WATCH
MV Onco
PART 01/04 — PRESIDENTIAL SPOTLIGHT
LBA1 — INTerpath-001
MELANOMA | PERSONALIZED mRNA VACCINE
WHO? Resected stage IIB–IV melanoma.
WHAT? Intismeran autogene (V940) + pembrolizumab versus pembrolizumab alone.
WHY WATCH? Can personalized vaccination further reduce melanoma recurrence after surgery?
LBA2 — VOLGA
MUSCLE-INVASIVE BLADDER CANCER
WHO? Cisplatin-ineligible or cisplatin-declining MIBC.
WHAT? Neoadjuvant enfortumab vedotin + perioperative durvalumab, with or without tremelimumab, versus surgery-based control.
WHY WATCH? Does adding CTLA-4 blockade provide enough extra benefit to justify toxicity?
LBA3 — DeLLphi-305
EXTENSIVE-STAGE SCLC
WHO? Patients without progression after first-line durvalumab + platinum–etoposide.
WHAT? Tarlatamab (DLL3 × CD3 T-cell engager) + durvalumab versus durvalumab maintenance alone.
WHY WATCH? Can DLL3-directed T-cell engagement improve survival in first-line maintenance?
LBA4 — DASL-HiCaP
VERY-HIGH-RISK PROSTATE CANCER
WHO? Localized or locoregional very-high-risk prostate cancer receiving definitive or salvage RT.
WHAT? Darolutamide versus placebo, added to ADT + radiotherapy.
WHY WATCH? Does intensified androgen-receptor blockade improve outcomes beyond ADT + RT?
FINAL TAKE-HOME
FOUR PHASE III TRIALS. FOUR CLINICAL QUESTIONS.
Cancer vaccines • Perioperative ADCs • T-cell engagers • AR blockade
THE DATA WILL DECIDE.
[Slide 2]
ESMO 2026 — ABSTRACTS TO WATCH
PART 02/04 — LUNG & GI BREAKTHROUGHS
MV Onco
LBA5 — KRAScendo 1
KRAS G12C-MUTATED NSCLC
WHO? Previously treated advanced KRAS G12C-mutated NSCLC.
WHAT? Divarasib versus sotorasib or adagrasib.
WHY WATCH? Can a newer KRAS G12C inhibitor outperform existing drugs targeting the same mutation?
LBA6 — SAFFRON
EGFR-MUTATED NSCLC | MET RESISTANCE
WHO? Advanced EGFR-mutated NSCLC progressing after osimertinib, with MET overexpression and/or amplification.
WHAT? Osimertinib + savolitinib versus platinum–pemetrexed.
WHY WATCH? Can targeting both EGFR and MET overcome resistance better than chemotherapy?
LBA7 — CLARITY-Gastric 01
CLDN18.2-POSITIVE GASTROESOPHAGEAL CANCER
WHO? Advanced/metastatic CLDN18.2-positive gastroesophageal cancer after prior treatment (second line or later).
WHAT? Phase III evaluation of sonesitatug vedotin, a CLDN18.2-directed ADC.
WHY WATCH? Can an ADC targeting CLDN18.2 offer another treatment option after first-line therapy?
LBA8 — HARMONi-Gi1
ADVANCED BILIARY TRACT CANCER
WHO? Previously untreated advanced biliary tract cancer.
WHAT? Ivonescimab + chemotherapy versus durvalumab + chemotherapy.
WHY WATCH? Can dual PD-1/VEGF targeting improve outcomes beyond current immunochemotherapy?
FINAL TAKE-HOME
FOUR TRIALS. FOUR PRECISION-ONCOLOGY QUESTIONS.
KRAS G12C • EGFR/MET • CLDN18.2 ADC • PD-1/VEGF
THE DATA WILL DECIDE.
[Slide 3]
ESMO 2026 — ABSTRACTS TO WATCH
PART 03/04 — BREAST CANCER: THE NEXT QUESTIONS
MV Onco
LBA14 — FINER
HR+/HER2– METASTATIC BREAST CANCER
WHO? ER-positive/HER2-negative metastatic breast cancer.
WHAT? Fulvestrant + ipatasertib (AKT inhibitor) versus fulvestrant + placebo.
WHY WATCH? Can adding AKT inhibition improve overall survival with endocrine therapy?
LBA16 — VIKTORIA-1
ENDOCRINE-RESISTANT BREAST CANCER
WHO? HR+/HER2– advanced breast cancer after prior endocrine-based treatment.
WHAT? Gedatolisib (PI3K/mTOR inhibitor) + fulvestrant, with or without palbociclib, versus standard care.
WHY WATCH? Can targeting the PI3K/mTOR pathway improve outcomes after endocrine resistance?
LBA23 — TALENT
EARLY HER2-LOW BREAST CANCER
WHO? HR-positive/HER2-low early breast cancer before surgery.
WHAT? Neoadjuvant trastuzumab deruxtecan (T-DXd), with or without anastrozole, or sequenced with chemotherapy.
WHY WATCH? Could an ADC become part of curative-intent treatment before surgery?
LBA25 — NATALEE
HR+/HER2– EARLY BREAST CANCER
WHO? Stage II–III HR+/HER2– early breast cancer.
WHAT? Six-year follow-up of adjuvant ribociclib + aromatase inhibitor versus aromatase inhibitor alone.
WHY WATCH? Does the recurrence benefit translate into improved overall survival?
FINAL TAKE-HOME
FOUR TRIALS. FOUR QUESTIONS THAT MATTER.
AKT inhibition • PI3K/mTOR targeting • HER2-low ADCs • Adjuvant CDK4/6 inhibition
THE DATA WILL DECIDE.
[Slide 4]
ESMO 2026 — ABSTRACTS TO WATCH
PART 04/04 — NEW ADCs & IMMUNOTHERAPY
MV Onco
LBA50 — PANKU-Breast01
HR+/HER2– METASTATIC BREAST CANCER
WHO? Previously treated unresectable locally advanced or metastatic HR+/HER2– breast cancer.
WHAT? Izalontamab brengitecan (iza-bren), an EGFR×HER3 bispecific ADC, evaluated against chemotherapy in a randomized Phase III study.
WHY WATCH? Can a bispecific ADC improve outcomes after endocrine and targeted therapies?
LBA51 — KEYNOTE-B49
HR+/HER2– ADVANCED BREAST CANCER
WHO? Endocrine-resistant, advanced HR+/HER2– breast cancer.
WHAT? Pembrolizumab + chemotherapy versus placebo + chemotherapy.
WHY WATCH? Can immunotherapy finally establish a meaningful role in HR-positive metastatic breast cancer?
LBA67 — OptiTROP-Lung04
EGFR-MUTATED ADVANCED NSCLC
WHO? Advanced EGFR-mutated NSCLC after progression on EGFR-TKI therapy.
WHAT? Sacituzumab tirumotecan (sac-TMT), a TROP2-directed ADC, versus platinum-based chemotherapy.
WHY WATCH? Does the final overall survival analysis establish an advantage for sac-TMT after EGFR-TKI failure?
LBA68 — SigVie-002
PREVIOUSLY TREATED NONSQUAMOUS NSCLC
WHO? Advanced nonsquamous NSCLC after prior systemic therapy.
WHAT? Sigvotatug vedotin, an integrin β6-directed ADC, versus docetaxel.
WHY WATCH? Can a new integrin-targeting ADC outperform conventional second-line chemotherapy?
FINAL TAKE-HOME
FOUR TRIALS. FOUR QUESTIONS THAT MATTER.
Bispecific ADCs • Immunotherapy • TROP2 ADCs • Integrin β6 ADCs
THE DATA WILL DECIDE.
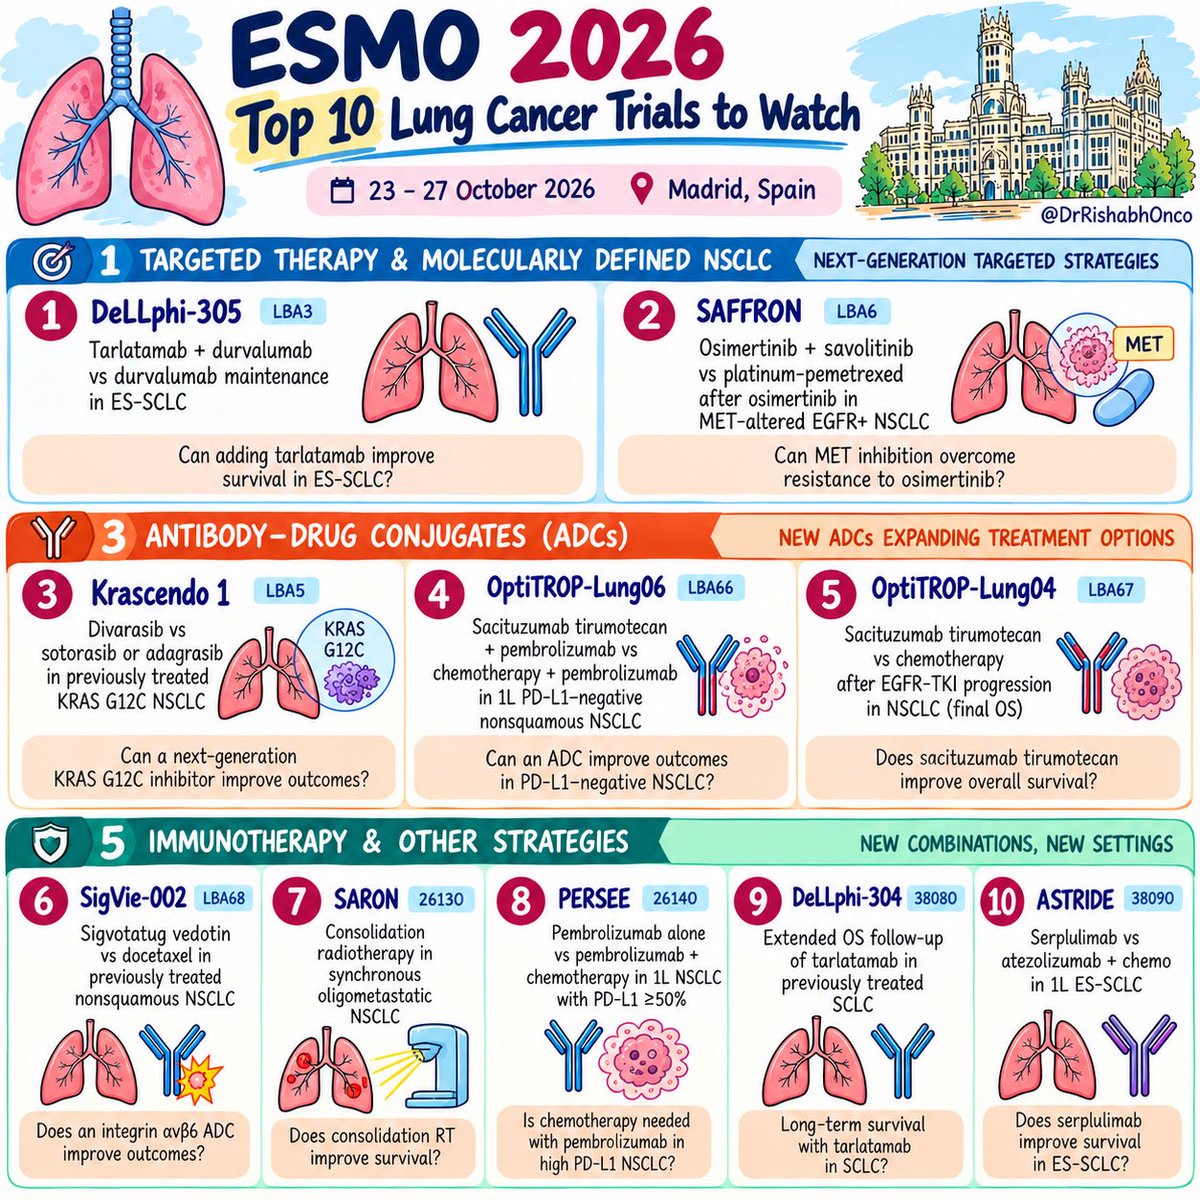
[Slide 1]
ESMO 2026
Top 10 Lung Cancer Trials to Watch
23 - 27 October 2026 | Madrid, Spain
@DrRishabhOnco
[illustrations: lungs, Madrid Cibeles palace]
1 TARGETED THERAPY & MOLECULARLY DEFINED NSCLC — NEXT-GENERATION TARGETED STRATEGIES
1 DeLLphi-305 LBA3
Tarlatamab + durvalumab vs durvalumab maintenance in ES-SCLC
Can adding tarlatamab improve survival in ES-SCLC?
2 SAFFRON LBA6
Osimertinib + savolitinib vs platinum-pemetrexed after osimertinib in MET-altered EGFR+ NSCLC
Can MET inhibition overcome resistance to osimertinib?
3 ANTIBODY-DRUG CONJUGATES (ADCs) — NEW ADCs EXPANDING TREATMENT OPTIONS
3 Krascendo 1 LBA5
Divarasib vs sotorasib or adagrasib in previously treated KRAS G12C NSCLC
Can a next-generation KRAS G12C inhibitor improve outcomes?
4 OptiTROP-Lung06 LBA66
Sacituzumab tirumotecan + pembrolizumab vs chemotherapy + pembrolizumab in 1L PD-L1-negative nonsquamous NSCLC
Can an ADC improve outcomes in PD-L1-negative NSCLC?
5 OptiTROP-Lung04 LBA67
Sacituzumab tirumotecan vs chemotherapy after EGFR-TKI progression in NSCLC (final OS)
Does sacituzumab tirumotecan improve overall survival?
5 IMMUNOTHERAPY & OTHER STRATEGIES — NEW COMBINATIONS, NEW SETTINGS
6 SigVie-002 LBA68
Sigvotatug vedotin vs docetaxel in previously treated nonsquamous NSCLC
Does an integrin αvβ6 ADC improve outcomes?
7 SARON 26130
Consolidation radiotherapy in synchronous oligometastatic NSCLC
Does consolidation RT improve survival?
8 PERSEE 26140
Pembrolizumab alone vs pembrolizumab + chemotherapy in 1L NSCLC with PD-L1 ≥50%
Is chemotherapy needed with pembrolizumab in high PD-L1 NSCLC?
9 DeLLphi-304 38080
Extended OS follow-up of tarlatamab in previously treated SCLC
Long-term survival with tarlatamab in SCLC?
10 ASTRIDE 38090
Serplulimab vs atezolizumab + chemo in 1L ES-SCLC
Does serplulimab improve survival in ES-SCLC?
[Slide 1]
MADRID 2026 ESMO congress
MADRID SPAIN 23-27 OCTOBER 2026
Hepatobiliopancreatic SELECTED ABSTRACTS
Presidential Symposium II | 25 October 2026 | 17:42-18:15
LBA8 - Ivonescimab plus chemotherapy versus durvalumab plus chemotherapy as first-line treatment for advanced biliary tract cancer: a randomized, controlled, double- blinded, phase 3 trial (HARMONi-GI1)
Proffered paper 1: Gastrointestinal tumour, upper digestive | 23 October 2026 | 13:30-15:00
LBA82 - Daraxonrasib, a RAS(ON) multi-selective inhibitor vs chemotherapy in previously treated metastatic pancreatic adenocarcinoma (mPDAC): Additional subgroup analyses from the Ph3 RASolute 302 study.
LBA83 - Seven-Valent mKRAS-specific Lymph Node Targeted Amphiphile Immunotherapy Versus Observation in Resected Pancreatic Ductal Adenocarcinoma (PDAC): the AMPLIFY-7P randomized Phase 2 study
Proffered paper 2: Gastrointestinal tumours, upper digestive | 24 October 2026 | 10:15-11:45
459O - A randomized trial of paclitaxel ± tovecimig in previously treated patients with advanced biliary tract cancer
LBA21 - Adjuvant chemotherapy with gemcitabine and cisplatin compared to standard of care after curative intent resection of cholangiocarcinoma and gallbladder carcinoma (ACTICCA-1 trial)
LBA48 - Liver function trajectory and post-progression outcomes in the Phase 3 EMERALD-3 study of tremelimumab (T) + durvalumab (D) ± lenvatinib (L) + transarterial chemoembolisation (TACE) in participants (pts) with embolisation-eligible hepatocellular carcinoma (eeHCC)
1679O - Phase I study of BGB-B2033 (GPC3 x 4-1BB bispecific antibody) monotherapy: First disclosure of dose optimization (DO) and dose escalation (DE) update in advanced hepatocellular carcinoma (HCC)
Rapid oral 1: Gastrointestinal tumour, upper digestive | 23 October 2026 | 16:45-18:15
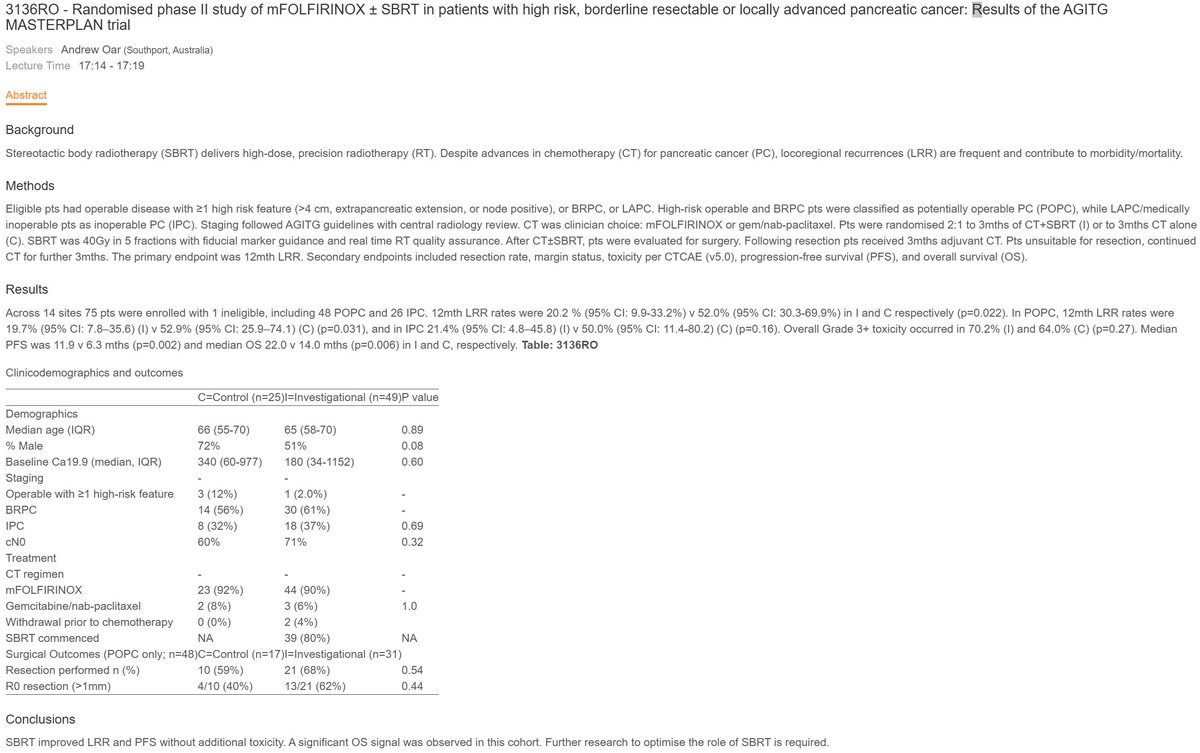
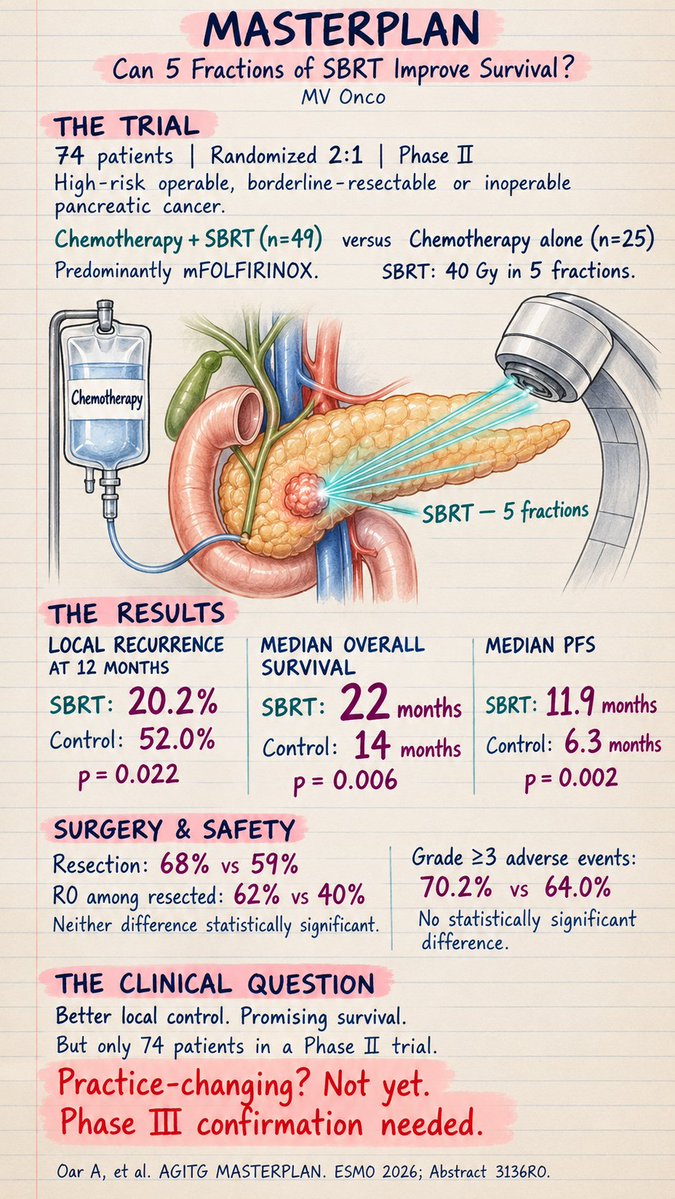
3136RO - Randomised phase II study of mFOLFIRINOX ± SBRT in patients with high risk, borderline resectable or locally advanced pancreatic cancer: Results of the AGITG MASTERPLAN trial
Rapid oral 2: Gastrointestinal tumour, upper digestive | 26 October 2026 | 14:45-16:15
LBA85 - HRS-4642 Plus Chemotherapy ± Adebrelimab as Perioperative Therapy in KRAS G12D-Mutant Pancreatic Cancer: Preliminary Results of a Phase 2 Study
3137RO - Safety and efficacy of INCB161734, a novel oral KRAS G12D inhibitor, in combination with chemotherapy in patients (pts) with advanced/metastatic pancreatic ductal adenocarcinoma (PDAC)
1678RO - Phase 3 LEAP-012 study of lenvatinib + pembrolizumab vs dual placebo with transarterial chemoembolization (TACE) for unresectable non-metastatic hepatocellular carcinoma: Long-term OS results
LBA22 - OPTIMUM: A randomized phase 2 study of maintenance olaparib (Ola) with or without durvalumab (Durva) in DDR gene-mutated advanced biliary tract cancer (aBTC)
473RO - Subcutaneous anti-PD-L1 monoclonal antibody envafolimab plus gemcitabine and oxaliplatin (GEMOX) versus GEMOX alone as first-line treatment for advanced biliary tract cancer in Chinese patients: A randomized, open-label, multicenter, registrational phase III trial
Nieves Martínez Lago · @DraMartinezLago | #ESMO26
[Slide 1]
KRASCENDO 1
Divarasib at ESMO 2026
Head-to-head phase III • KRAS G12C-mutated NSCLC
Conference preview • Full numerical data pending
[Lung / KRAS icon] A direct randomized comparison of next-generation divarasib versus first-generation KRAS G12C inhibitors in previously treated advanced NSCLC.
STUDY DESIGN
• Population: previously treated advanced KRAS G12C-mutated NSCLC
• Experimental arm: divarasib
• Comparator: sotorasib or adagrasib
• Trial: randomized phase III (KRASCENDO 1)
WHAT ROCHE HAS REPORTED
• Progression-free survival: clinically meaningful, statistically significant improvement
• Overall survival: statistical significance achieved at interim analysis
• Safety: consistent with prior data; no new safety signals reported
WHAT IS STILL NEEDED
• Effect sizes and hazard ratios
• Absolute PFS and OS outcomes
• Detailed toxicity and discontinuation data
• Subgroup analyses and follow-up context
ESMO 2026
Madrid, Spain
Late-breaking abstract: LBA5
Presentation date: October 25, 2026
WHY IT MATTERS
If the full results are convincing, divarasib could reshape treatment selection after progression in KRAS G12C-positive NSCLC. Until the full presentation, this remains a promising company-reported readout rather than a fully appraised practice-changing result.
Sources: Roche press release, July 2, 2026; Roche ESMO 2026 update, October 19, 2026.
[Tropical/Madrid skyline illustration]
[Slide 2]
The Uromigos™
Prostate Cancer.
Who benefits from
treatment intensification?
High-risk prostate cancer isn't one uniform patient population. Identifying who needs additional systemic treatment remains a central question.
DASL-HiCaP
New evidence on adding darolutamide in very high-risk localized disease.
PROTEUS
A subgroup analysis comparing intensified treatment around surgery with prostatectomy alone.
PEACE-1
Long-term survival findings that may help clarify the role of prostate-directed radiotherapy in metastatic disease.
Key theme:
Patient selection may be just as important as the treatment being added.
[prostate anatomy illustration]
[Slide 3]
The Uromigos™
Kidney Cancer.
Is there a future for
triplet therapy?
Triplet therapy continues to evolve in advanced kidney cancer. New data at ESMO 2026 may help define which patients benefit most and how to manage associated toxicity.
LITESPARK-012
First-line belzutifan + pembrolizumab + lenvatinib in advanced clear cell RCC.
Treatment sequences
How emerging data may inform optimal sequencing and patient selection.
Toxicity management
Balancing efficacy with tolerability remains a key consideration.
Key theme:
Better patient selection and thoughtful toxicity management will be essential.
[kidney anatomy illustration]
[Slide 4]
The Uromigos™
Bladder Cancer.
How much treatment
is enough?
At ESMO 2026, new data will help inform how to optimize perioperative strategies in bladder cancer, including the right intensity and sequencing of treatment.
VOLGA
Perioperative durvalumab + chemotherapy in muscle-invasive bladder cancer.
KEYNOTE-905
Perioperative pembrolizumab + chemotherapy and long-term outcomes.
Treatment decisions
Emerging data may help refine who benefits from perioperative therapy and how to balance efficacy with toxicity.
Key theme:
Finding the right patients — and the right amount of treatment — remains critical.
[bladder anatomy illustration]
[Slide 1]
5 LBAs to Watch Out for on Day 1
Friday, 23 October 2026
1 [pink ribbon] Early Breast Cancer
LBA23 – TALENT
Final results of TALENT: A neoadjuvant trial of T-DXd with or without anastrozole, or in sequence with chemotherapy for HER2-low, HR+ early-stage breast cancer
• Can ADCs move into the curative setting?
• Role of endocrine therapy with T-DXd
• Implications for treatment sequencing in HER2-low, HR+ disease
13:30 – 13:40
Alicante Auditorium (Hall 6)
Sara A. Hurvitz (Seattle, USA)
2 [pink ribbon] Early Breast Cancer
LBA25 – NATALEE
Adjuvant ribociclib (RIB) + nonsteroidal aromatase inhibitor (NSAI) in patients with HR+/HER2– early breast cancer: 6-year overall survival and efficacy outcomes
• Mature 6-year overall survival data
• Durability of benefit with adjuvant CDK4/6 inhibition
• Impact on high-risk subgroups and long-term safety
14:25 – 14:35
Alicante Auditorium (Hall 6)
Dennis J. Slamon (Los Angeles, USA)
3 [stomach icon] Oesophageal Cancer
LBA78 – SANO
Active surveillance versus standard surgery after neoadjuvant chemoradiotherapy for oesophageal cancer: Long-term results of a cluster-randomised controlled trial
• Can we safely avoid surgery in complete responders?
• Long-term survival and salvage outcomes
• Potential to change standard of care and preserve quality of life
13:40 – 13:50
Almeria Auditorium (Hall 9)
Sanjiv S. Gangaram-Panday (Rotterdam, Netherlands)
4 [pancreas icon] Pancreatic Cancer
LBA82 – RASolute 302
Daraxonrasib, a RAS(ON) multi-selective inhibitor vs chemotherapy in previously treated metastatic pancreatic adenocarcinoma: Additional subgroup analyses from the phase 3 RASolute 302 study
• Efficacy of a RAS(ON) inhibitor in mPDAC
• Key subgroup analyses and biomarker-defined populations
• Safety profile and potential new treatment avenue in a high unmet need setting
14:22 – 14:32
Almeria Auditorium (Hall 9)
Zev A. Wainberg (Los Angeles, USA)
5 [stomach icon] Gastric / GEJ Cancer
LBA77 – G-HOPE-001
Arcotatug tavatecan (IBI343/TAK-921) versus treatment of physician's choice in previously treated, advanced gastric or gastroesophageal junction adenocarcinoma: First interim analysis of the randomized, open-label, phase 3, G-HOPE-001 study
• Phase 3 data for a new ADC in advanced G/GEJ cancer
• Survival benefit and biomarker selection
• Positioning in the treatment landscape
13:30 – 13:40
Almeria Auditorium (Hall 9)
Kohei Shitara (Kashiwa, Japan)
[Slide 1]
ESMO 2026
TOP 10 GU CANCER TRIALS TO WATCH
Pre-congress watchlist | Grouped by GU subspecialty
23-27 October 2026 | Madrid, Spain
PROSTATE CANCER
1 DASL-HiCaP - Darolutamide + ADT + RT in very high-risk localized prostate cancer
2 PROTEUS - Perioperative apalutamide + ADT in high-risk localized prostate cancer
3 CAPItello-281 - Updated OS with capivasertib + abiraterone in PTEN-deficient mHSPC
4 PEACE-1 - Long-term OS benefit with abiraterone in de novo mCSPC
BLADDER / UROTHELIAL CANCER
5 VOLGA - Perioperative durvalumab ± tremelimumab with neoadjuvant enfortumab vedotin in cisplatin-ineligible MIBC
6 KEYNOTE-866 - Perioperative pembrolizumab + gem/cis in cisplatin-eligible MIBC
7 ENERGIZE / CA017-078 - Perioperative nivolumab + cisplatin-based chemotherapy in MIBC
KIDNEY CANCER (RCC)
8 LITESPARK-011 - Belzutifan + lenvatinib vs cabozantinib after prior PD-(L)1 in advanced RCC
9 LITESPARK-012 - Belzutifan- or quavonlimab-containing first-line regimens with pembrolizumab + lenvatinib in advanced RCC
10 KEYNOTE-564 - Final prespecified analysis of adjuvant pembrolizumab in clear-cell RCC
@DrRishabhOnco
OTHER GU ABSTRACTS TO WATCH: PE-PE | KEYNOTE-B15 | TALAPRO-3 | NIAGARA | SWOG S2200
[Madrid skyline line-art illustrations]
[Slide 1]
MADRID 2026 ESMO congress
MADRID SPAIN 23-27 OCTOBER 2026
Gastroesophageal | SELECTED ABSTRACTS
Presidential Symposium II | 25 October 2026 · 17:18-17:42
LBA7 - CLARITY-Gastric 01 (CG-01): a Phase 3 study of sonesitatug vedotin (Sone-Ve) in second or later-line (2L+) advanced or metastatic Claudin 18.2 (CLDN18.2) positive gastroesophageal carcinoma (GEC)
Proffered paper 1: Gastrointestinal tumour, upper digestive | 23 October 2026 · 13:30-15:00
LBA77 - Arcotatug tavatecan (IBI343/TAK-921) versus treatment of physician's choice (TPC) in previously treated, advanced gastric or gastroesophageal junction adenocarcinoma (G/GEJA): First interim analysis of the randomized, open-label, phase 3, G-HOPE-001 study
LBA78 - Active surveillance versus standard surgery after neoadjuvant chemoradiotherapy for oesophageal cancer: long-term results of a cluster-randomised controlled trial (SANO)
2875O - Pembrolizumab or placebo plus concurrent definitive chemoradiotherapy in esophageal and gastroesophageal junction (GEJ) cancer: The phase 3 randomized KEYNOTE-975 study
Rapid oral 1: Gastrointestinal tumour, upper digestive | 23 October 2026 · 16:45-18:15
LBA79 - Zanidatamab (zani) + chemotherapy (CT) ± tislelizumab (TIS) for first-line (1L) HER2-positive (HER2+) advanced/metastatic gastroesophageal adenocarcinoma (mGEA): second interim analysis (IA) from HERIZON-GEA-01
LBA80 - Anbenitamab plus chemotherapy for previously treated HER2-positive gastric or gastroesophageal carcinomas (GC/GEJC): Updated overall survival (OS) analysis of KC-WISE
2876RO - TQB2102, a novel HER2 bispecific antibody-drug conjugate, combined with bemotrizumab with or without capecitabine as first-line therapy for HER2-positive advanced gastric/gastroesophageal junction cancer: A phase II study
2877RO - Watch-and-wait (W&W) strategy for dostarlimab in localized deficient dMMR/MSI-H gastroesophageal adenocarcinoma (GEA): Results from the first interim analysis of the GERCOR-GONO DEWI phase II study
2878RO - FOLFIRI plus ramucirumab versus paclitaxel plus ramucirumab as second-line therapy for taxane-pretreated patients with advanced or metastatic gastroesophageal adenocarcinoma-Final results of the phase III IKFs602/AIO RAMIRIS Study
LBA81 - Four Months of Adjuvant XELOX versus Six Months in Stage II-IIIB Gastric Cancer - The LOMAC Randomized Trial
2879RO - Durvalumab plus definitive chemoradiotherapy versus definitive chemoradiotherapy in patients with locally advanced esophagus carcinoma: ARION PRODIGE 67 randomized phase 2 trial
2883RO - Efficacy of bemarituzumab in patients with advanced gastric and gastroesophageal junction cancer (GC/GEJ) by FGFR2 amplification status: Exploratory biomarker analysis from FORTITUDE-101 (F101) and FORTITUDE-102 (F102)
Nieves Martínez Lago · @DraMartinezLago | #ESMO26
[Slide 1]
ESMO CONGRESS 2026
Anticipated Highlights
Madrid · October 23-27
1 INTerpath-001 · LBA1 · Sat Presidential I
Intismeran plus pembrolizumab, resected IIB-IV melanoma. First phase 3 individualized neoantigen win: recurrence risk cut 42%.
2 VOLGA · LBA2 · Sat Presidential I
Perioperative durvalumab plus neoadjuvant EV in cisplatin-ineligible MIBC. EFS/OS positive at interim; FDA priority review.
3 LITESPARK-011 · 3587O · Renal proffered
Final: belzutifan plus lenvatinib held PFS post-immunotherapy in ccRCC; OS non-significant. QoL 3595RO may shape sequencing.
4 LITESPARK-012 · 3586O · Renal proffered
First-line belzutifan combinations vs pembrolizumab plus lenvatinib in ccRCC. Missed PFS and OS endpoints.
5 DASL-HiCaP · LBA4 · Prostate late-breaking
Interim: darolutamide plus ADT with radiotherapy in very-high-risk localized prostate cancer.
6 CAPItello-281 · LBA56 · Prostate late-breaking
Updated OS: capivasertib plus abiraterone in PTEN-deficient metastatic hormone-sensitive prostate cancer.
7 Perioperative bladder cancer · Fri orals
KEYNOTE-866, ENERGIZE, and KEYNOTE-905 ad hoc: refining immunotherapy around cystectomy.
8 AI in oncology · Fri 10:15 AM + LBA20 Sat
Educational session on digital health and AI, Barcelona Hall 9 Friday morning, plus the Agendia AI digital pathology late-breaker, Bilbao Hall 3 Saturday 2:45 PM.
Cross-tumor practice changers first, then GU depth · ESMO 2026, Madrid
[Slide 1]
Proffered Paper session
LBA7 - CLARITY-Gastric 01 (CG-01): a Phase 3 study of sonesitatug vedotin (Sone-Ve) in second or later-line (2L+) advanced or metastatic Claudin 18.2 (CLDN18.2) positive gastroesophageal carcinoma (GEC)
Speakers Rui-Hua Xu (Guangzhou, China)
Lecture Time 17:18 - 17:30
[Slide 2]
Proffered Paper session
LBA8 - Ivonescimab plus chemotherapy versus durvalumab plus chemotherapy as first-line treatment for advanced biliary tract cancer: a randomized, controlled, double- blinded, phase 3 trial (HARMONi-GI1)
Speakers Jian Zhou (Shanghai, China)
Lecture Time 17:42 - 17:54
[Slide 3]
Proffered Paper session
LBA10 - MOIO: Interim analyses of a Phase III Randomized Non Inferiority Trial Assessing Reduced Frequency Immune Checkpoint Inhibitors in Responding Patients with Advanced/Metastatic Cancer.
Speakers Gwenaëlle Gravis (Marseille, France)
Lecture Time 16:54 - 17:06
[Slide 4]
Proffered Paper session
LBA1 - INTerpath-001: Phase 3 study of the mRNA-based individualized neoantigen therapy (INT) intismeran autogene (intismeran) plus pembrolizumab (pembro) vs pembro alone for adjuvant treatment of resected stage IIB-IV melanoma (MEL)
Speakers Georgina V. Long (Sydney, Australia, NSW)
Lecture Time 16:30 - 16:42
[Slide 1]
MedShr
ESMO 2026
Top 10 Trial Predictions
The studies most likely to shape practice in Madrid
23–27 October 2026
Madrid, Spain
The full late-breaking abstract (LBA) list isn't public yet. ESMO keeps LBAs under embargo until presentation, so this ranking is based on company announcemen[ts] and preview coverage.
[ESMO 2026 MADRID logo; Madrid skyline photo]
# | Trial (abstract) | Setting | Why it matters
1 | INTerpath-001 (Presidential, 24 Oct) | Adjuvant stage IIB–IV melanoma — intismeran (mRNA neoantigen therapy) + pembrolizumab | First phase III of a personalised mRNA neoantigen therapy. If positive, this is the headline of the congress and opens a new kind of treatment.
2 | MOIO (LBA10, Presidential III, 26 Oct) | Immunotherapy given every 3 months vs standard schedule in responders — any solid tumour | Treatment de-escalation that applies to every tumour type. Large implications for cost, chair capacity and toxicity; directly relevant to the NHS.
3 | DeLLphi-305 (LBA3) | Extensive-stage SCLC maintenance — tarlatamab + durvalumab vs durvalumab | Moves a BiTE into first-line SCLC. An area where survival has barely moved.
4 | HARMONi-GI1 (LBA8, Presidential II, 25 Oct) | First-line biliary — ivonescimab + chemotherapy vs durvalumab + chemotherapy | Reported OS-positive. A PD-1 × VEGF bispecific beating the TOPAZ-1 standard; first proof against an active immunotherapy comparator outside lung.
5 | KRASCENDO 1 (LBA5) | Pretreated KRAS G12C NSCLC — divarasib vs sotorasib/adagrasib | Head-to-head between G12C inhibitors; could settle which one to use.
6 | CLARITY-Gastric 01 (LBA7) | CLDN18.2+ gastric, 3L+ — sonesitatug vedotin | OS-positive. Establishes a CLDN18.2 ADC as a new drug class.
7 | HERIZON-GEA-01 (LBA79) | First-line HER2+ GEA — zanidatamab ± tislelizumab + chemotherapy | Median OS 26.4 vs 19.2 months. Likely to displace trastuzumab.
8 | NATALEE 6-yr OS (LBA25) | Adjuvant HR+ early breast — ribociclib | An OS signal would settle debate over adjuvant CDK4/6 use; large audience.
9 | SAFFRON (LBA6) / SANOVO (LBA69) | MET-overexpressed EGFR+ NSCLC, after osimertinib / treatment-naïve | Chemo-free option for MET-driven resistance.
10 | KEYNOTE-B49 (LBA51) | HR+/HER2− advanced breast — pembrolizumab + chemotherapy | Would be the first immunotherapy win in luminal disease.
Please note:
This is a provisional ranking based on company announcements and preview coverage. The full LBA list and several Presidential slots are unconfirmed, and coverage of GU, gynae and colorectal is thin.
[Slide 1]
[search icon] Proffered Paper session
LBA50 - PANKU-Breast01: Randomized phase III study of izalontamab brengitecan (iza-bren) in previously treated unresectable locally advanced or metastatic (LA/M) hormone receptor-positive/HER2-negative (HR+/HER2-) breast cancer (BC)
Speakers Bo Lan (Beijing, China)
Lecture Time 14:35 - 14:45
Abstract
Background
Although first-line endocrine therapy plus CDK4/6 inhibitors has improved clinical outcome of HR+/HER2- BC, patients (pts) inevitably develop resistance and survival outcomes remain poor with subsequent therapy. Iza-bren is a first-in-class bispecific antibody-drug conjugate (ADC) against EGFR and HER3, containing a potent topoisomerase I inhibitor payload (Ed-04).
Methods
Eligible pts had unresectable LA/M HR+/HER2- BC (HR+, ER≥1% and/or PR≥1%; HER2-, IHC 0, 1+, or 2+/ISH-), progressed after at least 1L of endocrine therapy and 1 or 2L prior chemotherapy, and had previously received CDK4/6 inhibitors and taxanes. Pts were randomized 1:1 to receive iza-bren (2.5 mg/kg D1D8 Q3W) or TPC (eribulin, capecitabine, gemcitabine, or vinorelbine). The primary endpoint was PFS by blinded independent central review (BICR). Secondary endpoint included OS. The pre-planned final analysis for PFS serves as the interim analysis for OS.
Results
As of Jul 21, 2026, a total of 383 pts were randomized and treated (iza-bren/TPC, 190/193). Median follow-up for PFS was 15.24 vs 13.63 mo (iza-bren/TPC). Iza-bren significantly improved PFS by BICR vs TPC; mPFS was 8.18 mo (95% CI, 6.93-8.58) vs 4.01 mo (95% CI, 2.92-4.30) (HR, 0.41; 95% CI, 0.33-0.53; P<0.0001). OS was immature at the interim analysis, and no detrimental effect was observed. The cORR by BICR was 40.5% with iza-bren vs 20.2% with TPC, and mDOR was 6.93 vs 4.21 mo, respectively. Grade ≥3 TRAEs were predominantly hematologic in nature. TRAEs were manageable with standard supportive care, and only 1.6% of pts discontinued iza-bren treatment due to TRAEs. Adjudicated ILD occurred in 2 (1.1%) pts with iza-bren (grade 1 or 2). No new safety signals were identified.
Conclusions
The study met its primary endpoint at the prespecified analysis. Iza-bren demonstrated a statistically significant and clinically meaningful improvement in PFS vs TPC in previously treated HR+/HER2- BC. The safety profile was manageable and consistent with previous studies. The results support iza-bren as a new standard of care option in this population in China.
[Slide 2]
ESMO CONGRESS 2026 - MADRID - 23-27 OCTOBER
Ten trials to watch
A personal shortlist of the studies most likely to change practice in Madrid.
[Headshot] Dr Mario Balsa
Skin Cancer Unit
Clínic Comprehensive Cancer Center Barcelona
[Table columns: NO. | TRIAL | SETTING | WHY IT MATTERS]
01 | INTerpath-001 - LBA1 - Presidential I - 24 Oct | Resected melanoma, stage IIB-IV (adjuvant) - Intismeran autogene (mRNA) + pembrolizumab vs pembrolizumab | First phase III readout for an individualised neoantigen therapy. A positive result opens an entirely new class of treatment.
02 | MOIO - LBA10 - Presidential III - 26 Oct | Responders to immunotherapy, any solid tumour - Same dose every 3 months vs standard schedule | Tumour-agnostic de-escalation, with direct consequences for toxicity, cost and day-unit capacity.
03 | DeLLphi-305 - LBA3 - Presidential | Extensive-stage SCLC, maintenance - Tarlatamab + durvalumab vs durvalumab | OS benefit at interim analysis. Brings a DLL3-directed BiTE into first line, where survival has barely moved.
04 | HARMONi-GI1 - LBA8 - Presidential II - 25 Oct | First-line biliary tract cancer - Ivonescimab + chemo vs durvalumab + chemo | OS benefit over the TOPAZ-1 standard in a Chinese phase III: a PD-1 × VEGF bispecific beating active immunotherapy outside lung.
05 | KRASCENDO-1 - LBA5 - Presidential | Pretreated KRAS G12C NSCLC - Divarasib vs sotorasib or adagrasib | A true head-to-head within the G12C class: divarasib reported superior PFS over the first-generation inhibitors.
06 | CLARITY-Gastric 01 - LBA7 | CLDN18.2-positive gastric/GEJ, second line and beyond - Sonesitatug vedotin vs investigator's choice | OS benefit in third line and beyond, and across the wider pretreated population. Establishes CLDN18.2-directed ADCs as a class.
07 | HERIZON-GEA-01 - LBA79 - Second interim analysis | First-line HER2-positive GEA - Zanidatamab + chemo ± tislelizumab vs trastuzumab + chemo | Updated data for a regimen already approved by the FDA. Longer follow-up should firm up its place over trastuzumab.
08 | NATALEE - LBA25 - 6-year OS | Adjuvant HR-positive early breast cancer - Ribociclib | A survival signal would close the long-running debate on adjuvant CDK4/6 inhibition.
09 | SAFFRON / SANOVO - LBA6 - Presidential II / LBA69 | MET-overexpressed EGFR-mutant NSCLC - Savolitinib + osimertinib, after osimertinib / first line | A chemotherapy-free strategy for MET-driven disease, both at resistance and upfront.
10 | KEYNOTE-B49 - LBA51 | HR+/HER2- advanced breast, PD-L1 CPS ≥1 - Pembrolizumab vs placebo + chemotherapy | Would be the first immunotherapy win in luminal disease.
[OncoAlert360 logo]
[Slide 1]
ESMO 2026 / MADRID
EVIDENCE NOTES
[ESMO Congress Madrid 2026 logo]
PRESIDENTIAL SYMPOSIA / 1
WHICH DATA WILL ACTUALLY CHANGE CARE?
Five positive Phase 3 toplines • Effect sizes still await Madrid
01 INTerpath-001 | LBA1 · OCT 24
Resected stage IIB–IV melanoma · adjuvant · n=1,137
ARMS Intismeran + pembrolizumab ↔ pembrolizumab
KNOWN RFS + DMFS met
READOUT Phase 2b RFS HR 0.51; Phase 3 HR and absolute gain?
02 VOLGA | LBA2 · OCT 24
Cisplatin-ineligible MIBC · cystectomy · n=695
ARMS Durvalumab + enfortumab vedotin ↔ surgery ± adjuvant care
KNOWN EFS + OS met
READOUT Absolute OS, surgery completion and toxicity
03 DeLLphi-305 | LBA3 · OCT 24
Extensive-stage SCLC · first-line maintenance · n=563
ARMS Tarlatamab + durvalumab ↔ durvalumab
KNOWN OS + PFS met
READOUT Survival gain, CRS and monitoring burden
04 KRAScendo 1 | LBA5 · OCT 25
KRAS G12C NSCLC · head-to-head · n=338
ARMS Divarasib ↔ sotorasib / adagrasib
KNOWN PFS + OS met
READOUT Absolute gain over sotorasib/adagrasib
05 SAFFRON | LBA6 · OCT 25
EGFR-mutant NSCLC · MET resistance after osimertinib
ARMS Savolitinib + osimertinib ↔ platinum + pemetrexed
KNOWN PFS + OS met
READOUT MET threshold, OS magnitude and toxicity
Positive company toplines. Full HRs, confidence intervals and event counts are still needed.
19 OCT 2026 • ESMO programme + sponsor toplines
drozdogan.com
[Slide 1]
ESMO 2026 / MADRID
EVIDENCE NOTES
[ESMO Congress Madrid 2026 logo]
PRESIDENTIAL SYMPOSIA / 2
FIVE QUESTIONS BEHIND THE HEADLINES
Active comparators • Discordant endpoints • Less treatment
01 HARMONi-GI1 | LBA8 · OCT 25
Biliary tract cancer · first line
ARMS Ivonescimab + chemo ↔ durvalumab + chemo
KNOWN OS met
READOUT Absolute OS, bleeding and transfer beyond China
02 CLARITY-Gastric01 | LBA7 · OCT 25
CLDN18.2+ gastric cancer · antibody–drug conjugate
ARMS Sonesitatug vedotin ↔ investigator's choice
KNOWN OS positive · PFS not significant
READOUT Third-line OS vs PFS in the broader population
03 TroFuse-005 | LBA11 · OCT 26
Endometrial cancer after platinum + immunotherapy
ARMS Sacituzumab tirumotecan ↔ doxorubicin / paclitaxel
KNOWN OS + PFS met
READOUT Magnitude of TROP2 ADC benefit and toxicity
04 KEYNOTE-C93 | LBA12 · OCT 26
Advanced / recurrent dMMR endometrial cancer
ARMS Pembrolizumab ↔ carboplatin + paclitaxel
KNOWN PFS met · OS immature
READOUT Place alongside current chemo + IO practice
05 MOIO | LBA10 · OCT 26
ICI responders after 6 months
ARMS Standard schedule ↔ same ICI every 3 months
KNOWN RESULTS PENDING
READOUT Noninferiority margin, quality of life and cost
A positive press release is not a clinical verdict. Read the comparator, absolute benefit and harms.
19 OCT 2026 • ESMO programme + sponsor toplines
drozdogan.com
[Slide 1]
Dr. Aakash Desai
Associate Director, Phase 1 and Precision Oncology
@ADesaiMD
My Top Picks for ESMO 2026!
CLINICAL REVIEW
ESMO Congress 2026 · Madrid · Oct 23–27 · Thoracic phase 3 readouts and early-phase ADCs, ranked
7 | 2658RO | c-Met ADC
Temab-A
Telisotuzumab adizutecan: c-Met-directed ADC with a Top1i payload
Phase 1 first-in-human study, overall survival analysis in nonsquamous NSCLC
Rapid Oral 1: NSCLC, metastatic
Sat Oct 24 · 09:27 CEST
AbbVie reports:
EGFR wild-type (n=48): ORR 50%, median OS 13.8 mo
EGFR-mutant (n=41): ORR 63%, median OS 16.2 mo
EGFR wild-type, c-Met 3+ ≥25%: median OS ~19.2 mo
Watching: Does c-Met expression level select who benefits? Phase 3 AndroMETa-Lung-167 vs standard of care is underway.
1 | LBA6 | EGFR + MET
SAFFRON
Osimertinib + savolitinib vs platinum–pemetrexed
EGFRm, MET-overexpressed and/or amplified NSCLC after osimertinib
Presidential Symposium II
Sun Oct 25 · 16:54 CET
Sponsor topline: PFS and OS met (AstraZeneca / HUTCHMED)
Watching: How large is the benefit, and which MET IHC/FISH cutoff selects patients?
2 | LBA3 | DLL3×CD3
DeLLphi-305
Tarlatamab + durvalumab vs durvalumab
1L maintenance in ES-SCLC after durvalumab + platinum–etoposide
Presidential Symposium I
Sat Oct 24 · 17:18 CEST
Sponsor topline: OS met at interim; PFS and ORR also met (Amgen)
Watching: How big is the OS gain, and can clinics deliver T-cell engager monitoring in maintenance?
3 | LBA5 | KRAS G12C
Krascendo 1
Divarasib vs sotorasib or adagrasib
Previously treated KRAS G12C-mutated advanced NSCLC
Presidential Symposium II
Sun Oct 25 · 16:30 CET
Sponsor topline: PFS met; OS significant at interim (Roche)
Watching: How wide is the gap within the G12C class, and at what tolerability?
4 | LBA66 | TROP2 ADC
OptiTROP-Lung06
Sac-TMT + pembrolizumab vs chemo + pembrolizumab
1L PD-L1-negative (TPS <1%) nonsquamous NSCLC
Proffered Paper 1: NSCLC, metastatic
Sun Oct 25 · 10:53 CET
Sponsor topline: PFS met at interim; positive OS trend (Kelun-Biotech)
Watching: Can a TROP2 ADC replace the platinum doublet alongside IO?
5 | LBA71 | EGFR×HER3
PANKU-Lung01
Iza-bren (bispecific ADC) vs platinum–pemetrexed
EGFR-mutant nonsquamous NSCLC after a 3rd-gen EGFR TKI
Proffered Paper 2: NSCLC, metastatic
Mon Oct 26 · 09:14 CET
Sponsor topline: PFS met at interim (Sichuan Biokin)
Watching: First effect sizes: how big is the PFS gain, and at what toxicity?
6 | 3837RO | SEZ6 ADC
ABBV-706
SEZ6-directed Top1i ADC, phase 1
Relapsed/refractory SCLC
Rapid Oral: Non-metastatic NSCLC and other thoracic
Mon Oct 26 · 10:15 CET
AbbVie reports: ORR 56%, median OS 12.4 mo at 1.8 mg/kg (2L+, n=41)
Watching: Where does SEZ6 fit next to DLL3 and B7-H3 in SCLC?
Key Clinical Impacts & Future Directions
• After osimertinib: MET (SAFFRON), TROP2 (OptiTROP-Lung04 final OS, LBA67) or EGFR×HER3 (PANKU-Lung01): which patients get which next step?
• ES-SCLC: Does tarlatamab move into 1L maintenance, and how does that reshape later lines (DLL3, SEZ6, B7-H3)?
• KRAS G12C: Does a next-generation inhibitor reset the second-line standard?
• 1L PD-L1-negative: Can an ADC replace platinum chemotherapy alongside pembrolizumab?
• Biomarkers: MET IHC/FISH, c-Met level, SEZ6: which assays will we need at diagnosis and at progression?
• Phase 1 to phase 3: Will early ADC signals hold up against standard of care?
Times are Madrid local (CEST on Oct 24; CET from Oct 25). Toplines are as stated in sponsor releases; full data pending. Not medical advice.
Source: ESMO 2026 Congress program | Design: Dr. Aakash Desai
[Slide 1]
SWITCH | ESMO 2026
New Target. Same Payload. Same Resistance?
MV Onco
[illustration: ADC-resistant cancer cell with HER2 and TROP2 receptors]
HER2-targeted ADC
TOP1i
Different targets.
Same payload class.
TROP2-targeted ADC
TOP1i
ADC-resistant cancer cell
Different payload class may overcome resistance
Microtubule inhibitor (MMAE)
Microtubule inhibitor → TOP1i
TOP1i
Response observed (2/54)
54 patients | Phase II | 94.4% previously exposed to TOP1i ADCs
ONLY 2/54 RESPONDED
A: 0% | B: 8.3% | C: 0% | D: 5%
TAKE-HOME
• Changing the target alone produced limited responses.
• Payload cross-resistance may matter more than antigen switching.
• Change the weapon - not just the address?
• Small phase II trial. Hypothesis-generating.
[Slide 2]
SWITCH | ESMO 2026
PART 1/2
New Target. Same Payload. Does It Work?
MV Onco
01 WHY SWITCH?
• HER2-negative metastatic breast cancer
• Resistance to antibody-drug conjugates (ADCs) is an emerging challenge.
• After progression on an ADC, what should we change?
○ The antigen target?
○ The cytotoxic payload?
• Can changing the target alone overcome resistance?
[illustration: Before ADC response / After ADC progression (resistance)]
02 TRIAL DESIGN
• Phase II | Prospective | Open-label
• 54 patients | HER2-negative metastatic breast cancer
• Progression after ≥1 prior ADC
• Four investigational ADC cohorts assigned according to prior treatment history.
• Primary endpoint: Investigator-assessed ORR
[four bottles:]
SHR-A1811 Cohort A (n=10)
SHR-A1921 Cohort B (n=12)
SHR-A2009 Cohort C (n=12)
SHR-A2102 Cohort D (n=20)
All FOUR ADCs carried a TOP1 inhibitor payload
03 WHICH ADCs WERE TESTED?
• Four investigational ADCs with different targets and constructs.
• All used the SAME TOP1 inhibitor payload.
• Cohort A - SHR-A1811 (n=10)
• Cohort B - SHR-A1921 (n=12)
• Cohort C - SHR-A2009 (n=12)
• Cohort D - SHR-A2102 (n=20)
[ADC illustration] Different antigen targets and ADC constructs / Same cytotoxic payload (TOP1 inhibitor)
04 HOW HEAVILY PRETREATED?
• 94.4% had prior TOP1i-based ADC exposure.
• Most patients had already received an ADC with the same payload class.
• Could another TOP1i-based ADC restore sensitivity?
[pictogram] 94.4% had prior TOP1i-based ADC exposure
05 WHAT WERE THE RESULTS?
CONFIRMED OBJECTIVE RESPONSE RATE
• Cohort A - 0%
• Cohort B - 8.3%
• Cohort C - 0%
• Cohort D - 5%
Only 2 of 54 patients responded (3.7%).
TAKE-HOME
• Changing the ADC construct while retaining a TOP1i payload produced very limited responses.
• NEXT: Is payload cross-resistance the missing explanation?
[Slide 3]
SWITCH | ESMO 2026
Change the Target - Or Change the Payload?
PART 2/2
MV Onco
01 WHERE DID RESPONSES OCCUR?
ONLY AFTER SWITCHING PAYLOAD CLASS
Both responders had previously received:
Disitamab vedotin (RC48)
• Microtubule inhibitor payload (MMAE)
[ADC illustration] RC48 (Disitamab vedotin) Target: HER2 Payload: MMAE (microtubule inhibitor)
Then switched to: TOP1i-based ADC - Different target, Payload: TOP1 inhibitor
2 responses among 54 patients
→ No responses were observed after switching between ADCs with the same TOP1i payload class.
02 WHY DID TARGET SWITCHING FAIL?
POSSIBLE PAYLOAD CROSS-RESISTANCE
ADC resistance may involve:
• Antigen loss or downregulation
• Impaired internalization
• Drug efflux mechanisms
• Altered TOP1 activity
• Enhanced DNA damage repair
[cell illustration labelled: Antigen loss downregulation, Impaired internalization, Drug efflux, Altered TOP1 activity, Enhanced DNA damage repair]
Changing the antigen may not overcome resistance to the cytotoxic payload.
Different target ≠ Different killing mechanism
03 WHAT DOES THIS MEAN FOR ADC SEQUENCING?
Consider progression after T-DXd.
T-DXd (HER2) Payload: DXd (TOP1 inhibitor) → Sacituzumab govitecan (TROP2) Payload: SN-38 (TOP1 inhibitor)
• HER2 → TROP2: Different targets
• DXd → SN-38: Different molecules
• Both: TOP1 inhibitor payload class
• Potential for cross-resistance despite antigen switching.
Important: SWITCH does NOT establish that sacituzumab govitecan is ineffective after T-DXd.
04 WHAT ARE THE LIMITATIONS?
Small, hypothesis-generating phase II trial
• Only 54 patients
• Only 2 confirmed responses
• Small, treatment-history-selected cohorts
• No direct randomized comparison of payload-switching strategies
• No definitive mechanistic proof of cross-resistance
• Safety was described as manageable, without detailed toxicity rates in the abstract.
Association ≠ Proof of mechanism
05 WHAT SHOULD FUTURE TRIALS TEST?
Three sequencing strategies:
A Different target + Same payload class
B Same target + Different payload class
C Different target + Different payload class
• Integrate antigen expression and molecular resistance biomarkers.
• Which strategy can truly restore ADC sensitivity?
TAKE-HOME
New Target. Same Payload. Limited Responses.
• SWITCH suggests that payload-class cross-resistance may contribute substantially to ADC failure.
• Changing the antigen alone may be insufficient.
• The next frontier in ADC sequencing may be changing the weapon - not merely its address.
• Hypothesis-generating, not practice-changing.
[dartboard with arrows illustration]
[Slide 2]
TOPICS TO WATCH · 1 OF 2
[cartoon of skin/melanoma lesion]
INTerpath-001
Personalized mRNA vaccine +
pembrolizumab, adjuvant melanoma
Why it matters:
First Phase 3 test of a
personalized cancer vaccine
[cartoon of uterus]
TroFuse-005
Sacituzumab tirumotecan
(TROP2 ADC), endometrial cancer
Why it matters:
First TROP2 ADC to improve
overall survival here
[cartoon of uterus]
KEYNOTE-C93
Pembrolizumab alone,
first-line dMMR endometrial
Why it matters:
Could make chemo-free
first-line the new standard
@hemoncsimplified
[Slide 3]
TOPICS TO WATCH · 2 OF 2
[cartoon of lungs]
Krascendo 1
Divarasib vs sotorasib / adagrasib,
KRAS G12C lung cancer
Why it matters:
First head-to-head of KRAS
G12C inhibitors
[cartoon of a bladder]
VOLGA
Enfortumab vedotin + perioperative
durvalumab, bladder cancer
Why it matters:
Perioperative EV moves into
muscle-invasive disease
[cartoon of lungs]
DeLLphi-305
Tarlatamab (DLL3) + durva,
small-cell lung cancer
Why it matters:
DLL3 targeting moves earlier
[cartoon of lungs]
SAFFRON
Osimertinib + savolitinib,
EGFR/MET lung cancer
Why it matters:
MET resistance gets an answer
@hemoncsimplified
[Slide 1]
SWITCH vs SATEEN | ESMO 2026
ADC Sequencing: Is the Payload the Problem?
MV Onco
PARAMETER | SWITCH | SATEEN
Population | HER2-negative MBC | HER2-positive MBC
Design | Phase II platform | Phase II single-arm
Patients | 54 | 27
Prior ADC | ≥1 ADC | T-DXd
Strategy | Change ADC target/construct | Sacituzumab govitecan + trastuzumab
Payload | TOP1i → TOP1i in previously TOP1i-exposed patients | DXd → SN-38 (both TOP1i)
ORR | 3.7% (2/54) | 3.7% (1/27)
Key finding | No responses after same-class TOP1i switching. | Primary endpoint not met.
Additional result | Both responses after MMAE → TOP1i. | Median PFS: 2.3 months.
Conclusion | Possible payload cross-resistance. | Limited activity after T-DXd.
BOTH STUDIES → ORR 3.7%
Different populations. Similar concern about sequential TOP1i-based ADCs.
TAKE-HOME
1 TARGET SWITCHING MAY NOT BE ENOUGH.
Changing the antigen does not necessarily overcome resistance.
2 SAME PAYLOAD CLASS MAY MEAN CROSS-RESISTANCE.
Different TOP1 inhibitors may share resistance mechanisms.
3 PAYLOAD DIVERSIFICATION DESERVES STUDY.
Changing the cytotoxic mechanism may be more useful than changing the target alone.
4 NOT YET PRACTICE-CHANGING.
Small phase II studies; mechanistic cross-resistance remains unproven.
Different Targets. Same Payload Class. Limited Responses.
[Slide 1]
ESMO GOOD SCIENCE BETTER MEDICINE BEST PRACTICE
ESMO 2026 · MADRID
GUT ONC LAB
GI ABSTRACTS I'M WATCHING
Oct 23–27 · Times are Madrid local (CEST through Oct 24, CET from Oct 25)
BELOW THE BELT
AZUR-1 LBA87 Sun 25 11:00
Dostarlimab alone in stage II/III MSI-H rectal cancer
This will be positive. Incredibly positive. This is already what I'm doing in clinical practice and is a massive step forward for the 5–10% of rectal cancer patients that are MSI-H. Yay.
IROCAS LBA29 Sun 25 10:15
Adjuvant mFOLFIRINOX vs mFOLFOX6, T4/N2 colon
Important study, and honestly, it is going to predict if US-CIRCULATE will be positive. If this is negative, CIRCULATE will be a nail-biter.
CheckMate 8HW LBA32 Sat 24 15:42
Final OS: nivo/ipi vs nivo vs chemo, MSI-H mCRC
What happens when you do a trial with an agent that essentially cures a disease against another that cures most people? It is a really long damn trial. Excited for the final OS data. Will it be positive? TBD, but I certainly think the magnitude of benefit of dual IO makes it better than single agent, and this data could reinforce that practice.
UNION 3530O Sun 25 11:10
SCRT → camrelizumab + CAPOX, locally advanced rectal
pCR reported at ~40% in 2024, let's see if more people were cured. Some criticism in changing radiation schedule and adding IO compared to standard, but will set the stage for future studies.
EMT2 LBA30 Sun 25 10:25
EPA vs placebo after CRC liver metastasis resection
It's like fish oil but better. File this in the ALASCCA category of "costs nothing, helps people" if positive. ALASCCA + CHALLENGE <3
QTX3034 790RO Sat 24 15:15
KRAS G12D inhibitor + cetuximab ± mFOLFOX6, mCRC
Sick study. Moving us to molecularly driven treatments in earlier line settings for CRC. Where the field MUST move. If this isn't positive I will eat a hat (a small one, preferably organic).
EC + FOLFIRI beyond PD 788RO Sat 24 14:50
Continuing encorafenib + cetuximab past progression, BRAF V600E mCRC
Already doing this in clinical practice with patients who have BRAF+ disease w/o resistance mechanism on ctDNA at progression. Data for its use is HUGELY welcome.
BOT/BAL in the real world
905eP ePoster · 3771P Mon 26 12:00
Botensilimab + balstilimab: refractory MSS mCRC (AGEO) and advanced sarcoma (Spanish EAP)
Gives us a look at Bot Bal in real world. Important data, multiple attempts to use CPI in advanced disease have provided mixed results, what happens when we use stronger agents?
RUNNER-UP
Biweekly TAS-102 + bev LBA31 Sat 24 15:37
Biweekly vs standard schedule, refractory mCRC
Runner up only because Cathy Eng already convincingly showed this is the dosing schedule we should be using. I already use this in clinical practice. Great to randomize but should be positive.
UPPER GI
CLARITY-Gastric01 + G-HOPE-001
LBA7 Sun 25 17:18 · LBA77 Fri 23 13:30
CLDN18.2 ADCs, pretreated gastric/GEJ
The next generation of CLDN18.2 is here. Expect less explosive emesis and improved outcomes.
KEYNOTE-975 2875O Fri 23 13:50
Pembro + definitive chemoRT, esophageal/GEJ
Merck joins the D-FLOT era for patients still receiving definitive chemoRT. After the CROSS/FLOT study the impact of this is going to be less, but still important for patients receiving definitive chemoRT.
HERIZON-GEA-01 LBA79 Fri 23 16:15
Zanidatamab ± tislelizumab, 1L HER2+ GEA
My practice in HER2+ upper GI/GEA has moved to Zani, will be helpful to see the longer-term outcomes here.
SANO LBA78 Fri 23 13:40
Active surveillance vs surgery after nCRT, long-term
People deserve to keep their organs. Our ability to offer this only improves when we layer in tools like ctDNA. Interested in what we can extrapolate to other organ systems (especially for MSI-H).
PANCREAS
RASolute 302 LBA82 Fri 23 14:22
Daraxonrasib subgroups, 2L+ metastatic PDAC
Every subgroup likely benefited. G12V more than others. Maybe there will be another standing ovation? Come for the science, stay for the clapping.
AMPLIFY-7P LBA83 Fri 23 14:32
mKRAS vaccine vs observation, resected PDAC
Vaccine therapies are the next frontier. Merck has pushed them forward in Melanoma where they are an amazing success, very interested in the randomized data here. Even if negative it will be critical data to learn from.
HCC / BILIARY
HARMONi-GI1 LBA8 Sun 25 17:42
Ivonescimab vs durvalumab + GemCis, 1L BTC
PD-1/VEGF emerges in GI. Let's see the benefit. China only.
ACTICCA-1 LBA21 Sat 24 10:25
Adjuvant GemCis vs capecitabine, resected BTC
Might immediately change the standard of care for resected BTC. Worth tuning in for.
Nicholas J. Hornstein, MD, PhD
Full abstracts online Oct 19 · LBAs at presentation
[Slide 1]
2658RO - Overall survival (OS) analysis of telisotuzumab adizutecan in patients (pts) with nonsquamous non-small cell lung cancer (NSQ NSCLC): Phase 1 first-in-human study
Speakers David Sommerhalder (San Antonio, United States of America)
Lecture Time 09:27 - 09:32
Abstract
Background
c-Met (or MET) protein is highly expressed in NSCLC and has a poor prognosis. Telisotuzumab adizutecan (ABBV-400; Temab-A) is an antibody drug conjugate (ADC) consisting of an anti c-Met antibody conjugated to a Top1i payload. In an ongoing phase 1 study (NCT05029882), Temab-A showed promising efficacy and manageable safety in pts with NSQ NSCLC. Herein, we present OS for pts with NSQ NSCLC.
Methods
Enrolled pts with advanced EGFR wildtype (WT) or mutant (MUT) NSQ NSCLC that progressed after platinum-based chemotherapy and immune checkpoint or targeted therapy received Temab-A once every 21 days. Primary endpoint was confirmed investigator-assessed objective response rate (ORR) per RECIST v1.1. Secondary endpoints included duration of response (DOR), progression-free survival (PFS) and OS. Tumor tissue c-Met protein expression was retrospectively assessed by IHC via central laboratory.
Results
The EGFR WT cohort enrolled 48 pts (median follow-up: 27 months [mo]; median prior lines of therapy [LoT] 2 [range, 1–9]) and the EGFR MUT cohort enrolled 41 pts (median follow-up: 26 mo; median prior LoT: 3 [1–8]). Most pts received 2.4 mg/kg dose (EGFR WT: 81%, 39/48; EGFR MUT: 88%, 36/41); the remaining received 3.0 mg/kg. Median duration of treatment was 5.6 and 10 mo in the EGFR WT and EGFR MUT cohorts, respectively. Median OS for EGFR WT and EGFR MUT was 13.8 mo and 16.2 mo (Table). Among EGFR WT patients, the prevalence of c-MET expression ≥3+ staining intensity in ≥10% and ≥25% tumor cells was 43% (20/46) and 33% (15/46), respectively. Among EGFR MUT patients, it was 56% (19/34) and 41% (14/34), respectively. Median OS was longer in EGFR WT pts with c-MET above these thresholds (≥3+, ≥10%: 25.2 mo; ≥3+, ≥25%: 19.2 mo). No new safety signals were observed. Table: 2658RO
[columns: EGFR WT — Total N=48^a | ≥3+, ≥10% n=20^b | ≥3+, ≥25% n=15^b ; EGFR MUT — Total N=41^c | ≥3+, ≥10% n=24^b | ≥3+, ≥25% n=19^b]
ORR, n (%) | 24 (50) | 12 (60) | 9 (60) | 26 (63) | 17 (71) | 13 (68)
Median DOR, mo (95% CI) | 5.6 (4.2–12.3) | 5.6 (3.8–12.4) | 6.3 (2.8–21.8) | 9.7 (8.3–12.4) | 9.9 (6.9–13.5) | 10.9 (8.3–14.3)
Median PFS, mo (95% CI) | 6.8 (5.4–7.3) | 7.2 (5.5–9.0) | 8.0 (5.3–9.8) | 10.9 (8.3–12.3) | 11.0 (9.4–12.6) | 12.2 (9.6–14.7)
Median OS, mo (95% CI) | 13.8 (9.0–25.2) | 25.2 (7.5–NE) | 19.2 (7.1–NE) | 16.2 (11.6–19.9) | 15.6 (10.6–19.6) | 16.2 (10.6–21.0)
^a3.0 mg/kg (n=9). ^bAvailable IHC. ^c3.0 mg/kg (n=5). DOR, duration of response; IHC, immunohistochemistry; mo, months; NE, not estimable; ORR, objective response rate.
Conclusions
Temab-A exhibited promising OS in a heavily pretreated NSCLC population. OS rates compared favorably to those reported in the same indications with chemotherapy or other ADCs.
[Slide 1]
3837RO - ABBV-706: A first-in-class SEZ6-targeted topoisomerase 1 inhibitor (Top1i)-antibody-drug conjugate (ADC) with robust antitumour activity in relapsed/refractory small cell lung cancer (R/R SCLC)
Speakers Anne C. Chiang (New Heaven, United States of America)
Lecture Time 10:15 - 10:20
Abstract
Background
SEZ6 exhibits higher expression on SCLC cells than other SCLC therapeutic targets. ABBV-706 is a SEZ6-targeted ADC that selectively delivers a potent, cytotoxic Top1i payload (adizutecan) to SEZ6-expressing tumour cells. Phase (Ph) 1 results of ABBV-706 monotherapy in R/R SCLC (NCT05599984), including biomarker-response associations and ABBV-706 preclinical activity, are presented.
Methods
Archival tumour tissue was collected at baseline for immunohistochemistry (IHC) and RNA-Seq. Serum neuroendocrine proGRP and circulating tumour DNA (ctDNA) were assessed longitudinally. Binding and trafficking of SEZ6 on normal lung alveolar and SCLC cell lines were determined by flow cytometry and high content imaging. Adizutecan potency and activity was assessed in vitro; RNA-Seq was performed on SCLC cells.
Results
As of Sept 27, 2025, 124 patients (pts) with R/R SCLC received ABBV-706. Among pts with second-line plus (2L+) R/R SCLC who received the recommended Ph 3 dose of 1.8 mg/kg Q3W in Part 2a dose optimization (n=41), an objective response rate (ORR) of 56% and median overall survival (mOS) of 12.4 months (mo) was observed. In a subset with 2L R/R SCLC (n=17), ORR was 82% and mOS was 14.3 mo. Among 2L+ R/R SCLC, safety was comparable with prior data. ABBV-706 drove rapid declines in ctDNA and proGRP as early as cycle (C) 2 day (D) 1. At C3D1, 100% ctDNA clearance was associated with improved progression-free survival and OS. SEZ6 IHC expression was highly prevalent (93% above a 1% [1+ cutoff]), stable across therapy lines, and similar in responders and non-responders. SEZ6 was absent on human normal alveolar lung cells. Preclinically, SEZ6 antibody showed minimal binding and lysosomal trafficking in normal human pulmonary alveolar epithelial cells; significant trafficking in SEZ6-expressing SCLC cells was observed. Adizutecan potently reduced viability and increased expression of MHC-I, PD-L1, and key immune pathways in SCLC cell lines.
Conclusions
ABBV-706 monotherapy shows promising clinical benefit in heavily pretreated R/R SCLC with biomarker and preclinical data reinforcing its selective, differentiated, and potent antitumour profile.
[Slide 1]
ESMO CONGRESS 2026 · MADRID · 23-27 OCTOBER
10 breast cancer abstracts
I will not miss
Late-breaking phase III data, mature survival analyses and the next ADC questions
1 NATALEE LBA25
6-year OS with adjuvant ribociclib in HR+/HER2- early BC
Fri 23 Oct · 13:30 · Hall 6
2 TALENT LBA23
Neoadjuvant T-DXd ± anastrozole in HR+/HER2-low early BC: final results
Fri 23 Oct · 13:30 · Hall 6
3 PANKU-Breast01 LBA50
Iza-bren, an EGFR x HER3 bispecific ADC, phase III in pretreated HR+/HER2- MBC
Fri 23 Oct · 13:30 · Hall 6
4 KEYNOTE-B49 LBA51
Pembrolizumab + chemotherapy, phase III in HR+/HER2- advanced BC
Sat 24 Oct · 08:30 · Hall 6
5 FINER / MA.40 LBA14
Overall survival with ipatasertib + fulvestrant after CDK4/6i
Sat 24 Oct · 08:30 · Hall 6
6 FOURLIGHT-1 1842O
Selective CDK4 inhibition: atirmociclib + fulvestrant post CDK4/6i
Sat 24 Oct · 08:30 · Hall 6
7 postMONARCH 1RO
Overall survival with abemaciclib + fulvestrant after a prior CDK4/6i
Sat 24 Oct · 10:15 · Hall 9
8 VIKTORIA-1 LBA16
Gedatolisib + fulvestrant ± palbociclib: updated phase III results
Sat 24 Oct · 10:15 · Hall 9
9 DESTINY-Breast09 LBA49
T-DXd + pertuzumab vs THP in patients with baseline brain metastases
Mon 26 Oct · 10:15 · Hall 6
10 OptiTROP-Breast01 4639RO
Final OS: sacituzumab tirumotecan vs chemotherapy in pretreated mTNBC
Mon 26 Oct · 10:15 · Hall 6
Also on my list: HORIZON-Breast06 (LBA13) · TROPION-Breast02 brain mets (LBA96) · SWITCH (4RO) · lidERA PROs (538RO) · TOP-1 (545RO)
Madrid local time. No breast trial in the Presidential Symposia this year.
Halls: check the ESMO app on the day.
@nicolobattisti
[Slide 1]
PANKU-Breast01 | ESMO 2026 | LBA50
TWO TARGETS. DOUBLE THE PFS.
BUT WILL PATIENTS LIVE LONGER?
MV Onco
[illustration: breast cancer tumour; bispecific ADC binding EGFR and HER3; chemotherapy]
Breast cancer tumour
IZA-BREN
EGFR
HER3
Chemotherapy
IZA-BREN
MEDIAN PFS
IZA-BREN 8.18 MONTHS versus CHEMOTHERAPY 4.01 MONTHS
HR 0.41 | 59% LOWER HAZARD
ORR: 40.5% vs 20.2%
OVERALL SURVIVAL? STILL IMMATURE.
[Slide 2]
PANKU-Breast01 | ESMO 2026 | LBA50
Part 1 – Can a Bispecific ADC Double PFS?
MV Onco
01 THE CLINICAL QUESTION
• HR+/HER2- advanced breast cancer.
• Progression after endocrine therapy.
• Previously received CDK4/6 inhibitors and taxanes.
• 1-2 prior chemotherapy lines.
• Can a bispecific ADC outperform chemotherapy?
02 TRIAL DESIGN & TREATMENTS
Phase III | N = 383 | Randomized 1:1
▶ IZA-BREN (n = 190)
– EGFR + HER3 bispecific ADC.
– TOP1 inhibitor payload (Ed-04).
– 2.5 mg/kg IV, Days 1 & 8, every 3 weeks.
▶ PHYSICIAN'S CHOICE (n = 193)
– Eribulin / Capecitabine
– Gemcitabine / Vinorelbine
Primary endpoint → BICR-assessed PFS
03 DID IT DOUBLE PFS?
Median PFS
Iza-bren → 8.18 months
Chemotherapy → 4.01 months
HR 0.41 (95% CI 0.33–0.53)
P < 0.0001
59% LOWER HAZARD OF PROGRESSION OR DEATH
~2× MEDIAN PFS
04 DID MORE TUMOURS RESPOND?
Objective response rate
Iza-bren → 40.5% vs Chemotherapy → 20.2%
Median duration of response
Iza-bren → 6.93 months vs Chemotherapy → 4.21 months
TAKE-HOME
• Iza-bren nearly doubled median PFS and ORR versus chemotherapy.
• Overall survival remains immature.
[Slide 3]
PANKU-Breast01 | ESMO 2026 | LBA50
Part 2 – Is Iza-bren the Next ADC Standard?
MV Onco
01 HOW SAFE IS IZA-BREN?
• Grade ≥3 toxicities: Predominantly hematologic.
• ILD → 1.1% (2 patients) Both grade 1-2.
• Discontinuation due to TRAEs → 1.6%
✓ Manageable early safety profile.
• Long-term safety needs confirmation.
02 WHAT ABOUT OVERALL SURVIVAL?
OS DATA IMMATURE
• No detrimental OS effect observed at interim analysis.
• PFS HR → 0.41
• But PFS benefit ≠ proven OS benefit.
• Survival advantage NOT YET established.
03 HOW DOES IT FIT AMONG ADCs?
• T-DXd → HER2
• Sacituzumab govitecan → TROP2
• Iza-bren → EGFR + HER3
All deliver TOP1 inhibitor payloads.
• No head-to-head ADC comparison.
• Efficacy after prior ADCs remains unknown.
• Optimal ADC sequencing unresolved.
04 WHAT QUESTIONS REMAIN?
• Does PFS translate into OS?
• Does efficacy differ in HER2-zero vs HER2-low?
• Can it overcome resistance to prior ADCs?
• Will EGFR/HER3 expression predict benefit?
TAKE-HOME
• Iza-bren offers impressive PFS benefit with manageable reported toxicity.
• But OS, ADC sequencing and long-term safety remain unanswered.
[Slide 1]
My picks - CRC and PDAC - #ESMO26
Dr Jose Tapia · Barts Cancer Centre- X: @TapiajC1
MADRID 2026 ESMO congress · MADRID SPAIN 23-27 OCTOBER 2026
COLORECTAL CANCER
LBA32 | CheckMate 8HW | Mature OS data
Mature OS results from Nivolumab plus Ipilimumab vs Nivolumab vs Chemotherapy in MSI-H/dMMR mCRC. Relevant to inform patients. Keen to see updated data on subsequent therapies.
LBA87 | AZUR-1 | Organ preservation
Clinical CR with Dostarlimab monotherapy in dMMR/MSI-H locally advanced rectal cancer (LARC). First results from the global registrational trial. Potential to establish an organ-preserving treatment approach for selected patients.
LBA29 | IROCAS | Adjuvant intensification
RCT Ph3 of adjuvant intensification with mFOLFIRINOX vs mFOLFOX6 in high-risk stage III (T4 and/or N2) colon cancer. Does benefit justify additional toxicity?
788RO | ECLYPse | Beyond progression
Ph2 Encorafenib + Cetuximab (EC) + FOLFIRI beyond PD to EC in BRAF V600E mCRC. Particularly interested in pts who previously had IO. 787RO and 789RO are other interesting strategies in this setting.
790RO | QTX3034 | KRAS G12D in CRC
Preliminary clinical results. An oral G12D-preferring KRAS inhibitor + Cetuximab ± mFOLFOX6 in patients with KRAS G12D-mutated CRC. Data could inform development of targeted strategies.
PANCREATIC CANCER
LBA82 | RASolute 302 | RAS(ON) inhibition
Additional subgroup analyses from the Ph3 RASolute 302 study. Keen to see data on G12 variant subpopulation (G12D, G12V, and G12R), non-colon 12 mut (G14 and Q61) and RAS wild-type.
3137RO | INCB161734 | G12D plus chemo
Ph1 = Safety and efficacy. A novel oral KRAS G12D inhibitor + chemo advanced/metastatic PDAC. Will be interesting to see data on AE grades, interruptions and discontinuations. Are all the KRAS inh the same?
LBA85 | HRS-4642 | Perioperative G12D
Ph2. Perioperative strategy in KRAS-G12Dm PDAC. Non-covalent KRAS G12D inh + chemo ± adebrelimab (anti-PD-L1). Keen on seeing data on downstaging, % surgery/SBAR, and eradication of micrometastatic disease.
LBA83 | AMPLIFY-7P | Adjuvant vaccine
Ph2 RCT. Seven-valent mKRAS-specific lymph node targeted amphiphile immunotherapy vs AS in resected PDAC. Innovative immunotherapy. Does treatment intensification in selected population translate into clinical benefit?
Abstract titles as listed in the ESMO 2026 programme. Selection reflects titles only; data not yet reviewed.
[Slide 1]
ESMO CONGRESS 2026 · MADRID · 23-27 OCTOBER
Older adults with cancer at #ESMO26
10 presentations I will not miss
1 MOIO LBA10
Phase III non-inferiority trial of immune checkpoint inhibitors every 3 months in responding patients. Gwenaëlle Gravis.
Mon 26 Oct · 16:30-18:15 · Presidential Symposium III · Alicante Auditorium, Hall 6
2 TOP-1 (BOOG 2016-01) 545RO
5-year results of omitting radiotherapy after breast-conserving surgery in systemically untreated older women with ER+ early breast cancer. Lotte Bouwman.
Fri 23 Oct · 16:15-17:45 · Rapid oral, early breast cancer · Alicante Auditorium, Hall 6
3 NRG Oncology/NSABP B-42 LBA24
Final analysis of extended letrozole after 5 years of aromatase inhibitor-based therapy in postmenopausal women. Eleftherios P. Mamounas.
Fri 23 Oct · 13:30-15:00 · Proffered paper 1, breast cancer · Alicante Auditorium, Hall 6
4 GIM3 FATA 544RO
Final analysis: upfront versus switch schedule and three aromatase inhibitors head to head in postmenopausal HR+ early breast cancer. Pietro De Placido.
Fri 23 Oct · 16:15-17:45 · Rapid oral, early breast cancer · Alicante Auditorium, Hall 6
5 GERCOR-GONO DEWI 2877RO
Dostarlimab with watch-and-wait in localised dMMR/MSI-H gastro-oesophageal cancer, including a cohort of patients over 70 unfit for surgery. Thierry André.
Fri 23 Oct · 16:15-17:45 · Rapid oral, upper GI · hall to be confirmed
6 EV-302 in older patients 4761P
Updated exploratory analysis of enfortumab vedotin plus pembrolizumab in older patients and those with comorbidities. S. S. Sridhar.
Fri 23 Oct · poster on view 09:00-17:00, presenter 15:15-16:00 · Poster Area, Hall 5
7 KEYNOTE-C93 / GOG-3064 / ENGOT-en15 LBA12
Phase III first-line pembrolizumab versus carboplatin-paclitaxel in dMMR advanced or recurrent endometrial cancer. Brian M. Slomovitz.
Mon 26 Oct · 16:30-18:15 · Presidential Symposium III · Alicante Auditorium, Hall 6
8 AZUR-1 LBA87
First results of dostarlimab monotherapy for clinical complete response in dMMR/MSI-H locally advanced rectal cancer. Andrea Cercek.
Sun 25 Oct · 10:15-11:45 · Proffered paper, lower GI · hall to be confirmed
9 AIUR LBA28
Randomised trial of compression with standard surgical gloves to prevent paclitaxel-induced peripheral neuropathy. Young-Joon Kang.
Fri 23 Oct · 16:15-17:45 · Rapid oral, early breast cancer · Alicante Auditorium, Hall 6
10 HOPE LBA92
Phase III trial of a personalised digital supportive-care pathway for endocrine therapy symptoms in early breast cancer.
Mon 26 Oct · 08:30-10:00 · Proffered paper, supportive and palliative care · hall to be confirmed
Also on my list
Beyond guidelines: grey zones of oncology practice, with decision making in elderly and frail patients, Sat 24 Oct 10:15-11:45, Murcia Auditorium, Hall 3 · Overcoming barriers of access to clinical trials, Sat 24 Oct 08:30-10:00, Seville Auditorium · LOMAC (LBA81), 4 versus 6 months of adjuvant XELOX in gastric cancer · HER2CLIMB-05 HRQoL (1766RO), Sat 24 Oct 10:15-11:45, Almeria Auditorium, Hall 9 · lidERA (538RO) and DESTINY-Breast05 (539RO) patient-reported outcomes, Fri 23 Oct 16:15-17:45 · KEYNOTE-905 (4733O) and EV-103 (4740RO) in cisplatin-ineligible urothelial cancer · Dostarlimab real-world data by age (1286P), Mon 26 Oct poster · EONS19: quality of life for older adults with head and neck cancer (Cherith J. Semple), Sun 25 Oct 08:30 · TALENT (LBA23) and NATALEE 6-year OS (LBA25), Fri 23 Oct 13:30-15:00
Madrid local time. Clocks go back overnight on 24-25 October (CEST to CET). Late-breaking abstracts are embargoed until presentation; halls from secondary sources, check the programme app on the day.
@nicolobattisti
[Slide 1]
Dr. Aakash Desai
Associate Director, Phase 1 and Precision Oncology
@ADesaiMD
My Top Picks for ESMO 2026!
CLINICAL REVIEW
ESMO Congress 2026 · Madrid · Oct 23–27 · Thoracic phase 3 readouts and early-phase ADCs, ranked
7 | 2658RO | c-Met ADC
Temab-A
Telisotuzumab adizutecan: c-Met-directed ADC with a Top1i payload
Phase 1 first-in-human study, overall survival analysis in nonsquamous NSCLC
Rapid Oral 1: NSCLC, metastatic
Sat Oct 24 · 09:27 CEST
AbbVie reports:
EGFR wild-type (n=48): ORR 50%, median OS 13.8 mo
EGFR-mutant (n=41): ORR 63%, median OS 16.2 mo
EGFR wild-type, c-Met 3+ ≥25%: median OS ~19.2 mo
Watching: Does c-Met expression level select who benefits? Phase 3 AndroMETa-Lung-167 vs standard of care is underway.
1 | LBA6 | EGFR + MET
SAFFRON
Osimertinib + savolitinib vs platinum–pemetrexed
EGFRm, MET-overexpressed and/or amplified NSCLC after osimertinib
Presidential Symposium II
Sun Oct 25 · 16:54 CET
Sponsor topline: PFS and OS met (AstraZeneca / HUTCHMED)
Watching: How large is the benefit, and which MET IHC/FISH cutoff selects patients?
2 | LBA3 | DLL3×CD3
DeLLphi-305
Tarlatamab + durvalumab vs durvalumab
1L maintenance in ES-SCLC after durvalumab + platinum–etoposide
Presidential Symposium I
Sat Oct 24 · 17:18 CEST
Sponsor topline: OS met at interim; PFS and ORR also met (Amgen)
Watching: How big is the OS gain, and can clinics deliver T-cell engager monitoring in maintenance?
3 | LBA5 | KRAS G12C
Krascendo 1
Divarasib vs sotorasib or adagrasib
Previously treated KRAS G12C-mutated advanced NSCLC
Presidential Symposium II
Sun Oct 25 · 16:30 CET
Sponsor topline: PFS met; OS significant at interim (Roche)
Watching: How wide is the gap within the G12C class, and at what tolerability?
4 | LBA66 | TROP2 ADC
OptiTROP-Lung06
Sac-TMT + pembrolizumab vs chemo + pembrolizumab
1L PD-L1-negative (TPS <1%) nonsquamous NSCLC
Proffered Paper 1: NSCLC, metastatic
Sun Oct 25 · 10:53 CET
Sponsor topline: PFS met at interim; positive OS trend (Kelun-Biotech)
Watching: Can a TROP2 ADC replace the platinum doublet alongside IO?
5 | LBA71 | EGFR×HER3
PANKU-Lung01
Iza-bren (bispecific ADC) vs platinum–pemetrexed
EGFR-mutant nonsquamous NSCLC after a 3rd-gen EGFR TKI
Proffered Paper 2: NSCLC, metastatic
Mon Oct 26 · 09:14 CET
Sponsor topline: PFS met at interim (Sichuan Biokin)
Watching: First effect sizes: how big is the PFS gain, and at what toxicity?
6 | 3837RO | SEZ6 ADC
ABBV-706
SEZ6-directed Top1i ADC, phase 1
Relapsed/refractory SCLC
Rapid Oral: Non-metastatic NSCLC and other thoracic
Mon Oct 26 · 10:15 CET
AbbVie reports: ORR 56%, median OS 12.4 mo at 1.8 mg/kg (2L+, n=41)
Watching: Where does SEZ6 fit next to DLL3 and B7-H3 in SCLC?
Key Clinical Impacts & Future Directions
• After osimertinib: MET (SAFFRON), TROP2 (OptiTROP-Lung04 final OS, LBA67) or EGFR×HER3 (PANKU-Lung01): which patients get which next step?
• ES-SCLC: Does tarlatamab move into 1L maintenance, and how does that reshape later lines (DLL3, SEZ6, B7-H3)?
• KRAS G12C: Does a next-generation inhibitor reset the second-line standard?
• 1L PD-L1-negative: Can an ADC replace platinum chemotherapy alongside pembrolizumab?
• Biomarkers: MET IHC/FISH, c-Met level, SEZ6: which assays will we need at diagnosis and at progression?
• Phase 1 to phase 3: Will early ADC signals hold up against standard of care?
Times are Madrid local (CEST on Oct 24; CET from Oct 25). Toplines are as stated in sponsor releases; full data pending. Not medical advice.
Source: ESMO 2026 Congress program | Design: Dr. Aakash Desai
[Slide 1]
MADRID 2026 ESMO congress
GHG GoBroad Healthcare Group 高博医疗集团
38
Abstracts Accepted for ESMO Congress 2026
Research Highlights from GHG and Associated Expert Teams
[four stat tiles with icons]
3 LBA
6 Oral
24 Poster
5 E-Poster
[Madrid skyline silhouette graphic]
ESMO Congress 2026 | Madrid, Spain | 23–27 October 2026
[Slide 1]
ESMO26
TOP TEN BY ONCOALERT
GU ONCOLOGY
[OncoAlert 360 logo - Oncology / For Colleagues / By Colleagues]
WWW.ONCOALERT360.COM
LBA2 | VOLGA: PERIOPERATIVE DURVALUMAB WITH OR WITHOUT TREMELIMUMAB PLUS NEOADJUVANT ENFORTUMAB VEDOTIN IN MUSCLE-INVASIVE BLADDER CANCER: RESULTS FROM THE PHASE 3 VOLGA TRIAL
LBA4 | DASL-HICAP: DAROLUTAMIDE WITH ADT AND DEFINITIVE OR SALVAGE LOCOREGIONAL RADIATION THERAPY FOR LOCALISED, VERY HIGH-RISK PROSTATE CANCER: INTERIM ANALYSIS OF THE PHASE 3 DASL-HICAP TRIAL (ANZUP1801)
3586O | LITESPARK-012: FIRST-LINE PEMBROLIZUMAB + LENVATINIB + BELZUTIFAN OR MK-1308A + LENVATINIB IN ADVANCED RCC: RANDOMIZED OPEN-LABEL PHASE 3 LITESPARK-012 STUDY
3587O | LITESPARK-011: FINAL ANALYSIS OF THE PHASE 3 LITESPARK-011 STUDY: BELZUTIFAN PLUS LENVATINIB VERSUS CABOZANTINIB FOR ADVANCED RCC AFTER ANTI-PD-(L)1 THERAPY
LBA56 | CAPITELLO-281: CAPIVASERTIB + ABIRATERONE VS PLACEBO + ABIRATERONE IN PATIENTS WITH PTEN-DEFICIENT METASTATIC HORMONE-SENSITIVE PROSTATE CANCER: UPDATED OVERALL SURVIVAL FROM CAPITELLO-281
3592O | AK112: EFFICACY AND SAFETY OF AK112 (IVONESCIMAB), A PD-1/VEGF BISPECIFIC ANTIBODY, AS FIRST-LINE TREATMENT FOR IMDC FAVORABLE-RISK ADVANCED RCC: RESULTS FROM A PHASE IB/II STUDY
LBA53 | PROTEUS: PERIOPERATIVE APALUTAMIDE PLUS ADT WITH RADICAL PROSTATECTOMY AND PELVIC LYMPH NODE DISSECTION VS RP + PLND ALONE IN HIGH-RISK LOCALIZED OR LOCALLY ADVANCED PROSTATE CANCER: PROTEUS SUBSTUDY
LBA88 | PE-PE: PERIOPERATIVE PEMBROLIZUMAB PLUS METASTASIS-DIRECTED THERAPY VERSUS MDT ALONE IN OLIGOMETASTATIC RENAL CELL CARCINOMA: THE RANDOMIZED PHASE II PE-PE TRIAL
4734O | KEYNOTE-B15: CTDNA ANALYSIS OF THE PHASE 3 KEYNOTE-B15 TRIAL: NEOADJUVANT AND ADJUVANT ENFORTUMAB VEDOTIN + PEMBROLIZUMAB FOR CISPLATIN-ELIGIBLE MUSCLE-INVASIVE BLADDER CANCER
3591RO | SWOG S2200: FIRST RESULTS OF SWOG S2200, A RANDOMIZED PHASE II STUDY COMPARING CABOZANTINIB WITH OR WITHOUT ATEZOLIZUMAB IN METASTATIC PAPILLARY RENAL CELL CARCINOMA
3588O | XMAB819: PHASE 1 RESULTS OF XMAB819, A NOVEL ENPP3 X CD3 BISPECIFIC, IN ADVANCED CLEAR CELL RENAL CELL CARCINOMA
4736O | ENERGIZE: RESULTS FROM A PHASE 3 TRIAL OF NEOADJUVANT CHEMOTHERAPY ALONE VS IN COMBINATION WITH NIVOLUMAB FOLLOWED BY POSTSURGICAL ADJUVANT NIVOLUMAB IN MUSCLE-INVASIVE BLADDER CANCER
4735O | KEYNOTE-866: PERIOPERATIVE PEMBROLIZUMAB OR PLACEBO + NEOADJUVANT CISPLATIN AND GEMCITABINE IN PATIENTS WITH MUSCLE-INVASIVE BLADDER CANCER: THE DOUBLE-BLIND, PHASE 3 KEYNOTE-866 STUDY
Senior Faculty
[headshots] Dr Morgan Clin Onc | Dr Choueiri Med Onc | Dr Gillessen Med Onc | Dr Agarwal Med Onc | Dr Zhang Med Onc | Dr Powles Med Onc | Dr Rini Med Onc | Dr Grivas Med Onc | Dr Merseburger Urologist | Dr Omlin Med Onc | Dr Apolo Med Onc | Dr Necchi Med Onc | Dr Heng Med Onc | Dr Pal Med Onc | Dr Grande Med Onc | Dr Hammers Med Onc
Faculty
[headshots] Dr Gandur Med Onc | Dr Membribes Med Onc | Dr Nizam Med Onc
[Slide 1]
ESMO26
TOP TEN BY ONCOALERT
BREAST CANCER
OncoAlert 360° Oncology For Colleagues By Colleagues
WWW.ONCOALERT360.COM
LBA50 | PANKU-BREAST01: RANDOMIZED PHASE III STUDY OF IZALONTAMAB BRENGITECAN (IZA-BREN) IN PREVIOUSLY TREATED UNRESECTABLE LOCALLY ADVANCED OR METASTATIC (LA/M) HORMONE RECEPTOR-POSITIVE/HER2-NEGATIVE (HR+/HER2-) BREAST CANCER (BC)
1842O | FOURLIGHT-1: EFFICACY AND SAFETY OF ATIRMOCICLIB (ATI) + FULVESTRANT (FUL) IN PATIENTS (PTS) WITH HR+/HER2– ADVANCED/METASTATIC BREAST CANCER (MBC) WHO PROGRESSED ON PRIOR CDK4/6 INHIBITOR (CDK4/6I) IN A RANDOMIZED PHASE 2 STUDY (FOURLIGHT-1)
LBA25 | NATALEE: ADJUVANT RIBOCICLIB (RIB) + NONSTEROIDAL AROMATASE INHIBITOR (NSAI) IN PATIENTS (PTS) WITH HR+/HER2– EARLY BREAST CANCER (EBC): NATALEE 6-Y OVERALL SURVIVAL (OS) AND EFFICACY OUTCOMES
LBA27 | APEX-BREAST01: TQB2102 VERSUS CHEMOTHERAPY IN HER2-LOW RECURRENT OR METASTATIC BREAST CANCER (R/M BC) - RESULTS FROM A RANDOMIZED PHASE 3 STUDY
LBA51 | KEYNOTE-B49: RESULTS FROM KEYNOTE-B49: A PHASE 3, RANDOMIZED, DOUBLE-BLIND STUDY OF PEMBROLIZUMAB (PEMBRO) VS PLACEBO (PBO) PLUS CHEMOTHERAPY (CT) IN PARTICIPANTS (PTS) WITH HR+/HER2– ADVANCED BREAST CANCER (ABC)
LBA13 | HORIZON-BREAST06: TRASTUZUMAB REZETECAN (SHR-A1811) IN HER2-LOW ADVANCED BREAST CANCER (BC): A RANDOMIZED, PHASE 3 STUDY (HORIZON-BREAST06)
LBA26 | POP-DURVA: SHORT-TERM PREOPERATIVE DURVALUMAB FOR STAGE I TNBC: FIRST RESULTS FROM THE PHASE II UNLOCK 14 - POP-DURVA TRIAL
4RO | SWITCH: TARGET SWITCHING WITH CONSERVED-PAYLOAD NOVEL ADCS IN PATIENTS WITH METASTATIC BREAST CANCER FOLLOWING PRIOR ADC THERAPY (SWITCH): A PROSPECTIVE, OPEN-LABEL, PHASE 2 PLATFORM TRIAL
1RO | POSTMONARCH: OVERALL SURVIVAL FROM THE PHASE 3 POSTMONARCH TRIAL OF ABEMACICLIB + FULVESTRANT VS PLACEBO + FULVESTRANT FOR HR+, HER2- ADVANCED BREAST CANCER FOLLOWING PROGRESSION ON A PRIOR CDK4/6 INHIBITOR + ENDOCRINE THERAPY
LBA49 | DESTINY-BREAST09: A DESTINY-BREAST09 (DB-09) ANALYSIS OF TRASTUZUMAB DERUXTECAN (T-DXD) + PERTUZUMAB (P) VS TAXANE + TRASTUZUMAB + PERTUZUMAB (THP) FOR PATIENTS (PTS) WITH HER2+ ADVANCED/METASTATIC BREAST CANCER (A/MBC) AND BASELINE (BL) BRAIN METASTASES (BMS)
Senior Faculty
[Headshots] Dr Morgan Clin Onc · Dr Rugo Med Onc · Dr Lambertini Med Onc · Dr Loibl Med Onc · Dr Tolaney Med Onc · Dr Bianchini MedOnc · Dr Bartsch Med Onc · Dr. Hamilton Med Onc · Dr Graff Med Onc · Dr de Azambuja Med Onc · Dr Aftimos Med Onc · Dr Punie Med Onc
Faculty
[Headshots] Dr Agostinetto Med Onc · Dr Bonzano Rad Onc · Dr Griguolo Med Onc · Dr Jankovic Med Onc
[Slide 1]
ESMO26 TOP TEN BY ONCOALERT
GI CANCER
OncoAlert360 Oncology For Colleagues By Colleagues
LBA87 AZUR-1: CLINICAL COMPLETE RESPONSE WITH DOSTARLIMAB MONOTHERAPY IN DMMR/MSI-H LOCALLY ADVANCED RECTAL CANCER: FIRST RESULTS FROM THE GLOBAL REGISTRATIONAL TRIAL
LBA32 CHECKMATE 8HW: FINAL OVERALL SURVIVAL RESULTS: NIVOLUMAB PLUS IPILIMUMAB VERSUS NIVOLUMAB OR CHEMOTHERAPY IN MSI-H/DMMR METASTATIC COLORECTAL CANCER
789RO TRIDENTE: RECHALLENGE WITH ENCORAFENIB, BINIMETINIB AND CETUXIMAB IN BRAF V600E-MUTANT METASTATIC COLORECTAL CANCER: PHASE II STUDY
LBA79 HERIZON-GEA-01: ZANIDATAMAB + CHEMOTHERAPY ± TISLELIZUMAB FOR FIRST-LINE HER2-POSITIVE ADVANCED/METASTATIC GASTROESOPHAGEAL ADENOCARCINOMA: SECOND INTERIM ANALYSIS
2875O KEYNOTE-975: PEMBROLIZUMAB OR PLACEBO PLUS CONCURRENT DEFINITIVE CHEMORADIOTHERAPY IN ESOPHAGEAL AND GASTROESOPHAGEAL JUNCTION CANCER: PHASE 3 RANDOMIZED STUDY
2877RO GERCOR-GONO DEWI: WATCH-AND-WAIT STRATEGY FOR DOSTARLIMAB IN LOCALIZED DMMR/MSI-H GASTROESOPHAGEAL ADENOCARCINOMA: FIRST INTERIM ANALYSIS OF THE PHASE II STUDY
LBA77 G-HOPE-001: ARCOTATUG TAVATECAN (IBI343/TAK-921) VERSUS TREATMENT OF PHYSICIAN'S CHOICE IN PREVIOUSLY TREATED ADVANCED GASTRIC OR GEJ ADENOCARCINOMA: FIRST INTERIM ANALYSIS OF THE RANDOMIZED PHASE 3 STUDY
LBA8 HARMONI-GI1: IVONESCIMAB PLUS CHEMOTHERAPY VERSUS DURVALUMAB PLUS CHEMOTHERAPY AS FIRST-LINE TREATMENT FOR ADVANCED BILIARY TRACT CANCER: RANDOMIZED, DOUBLE-BLIND, PHASE 3 TRIAL
LBA21 ACTICCA-1: ADJUVANT GEMCITABINE PLUS CISPLATIN VERSUS CAPECITABINE IN RESECTED BILIARY TRACT CANCER: PHASE 3 TRIAL
LBA22 OPTIMUM: MAINTENANCE OLAPARIB WITH OR WITHOUT DURVALUMAB IN DDR GENE-MUTATED ADVANCED BILIARY TRACT CANCER: RANDOMIZED PHASE 2 STUDY
LBA82 RASOLUTE 302: DARAXONRASIB, A RAS(ON) MULTI-SELECTIVE INHIBITOR, VS CHEMOTHERAPY IN PREVIOUSLY TREATED METASTATIC PANCREATIC ADENOCARCINOMA: ADDITIONAL SUBGROUP ANALYSES FROM THE PHASE 3 STUDY
LBA83 AMPLIFY-7P: SEVEN-VALENT MKRAS-SPECIFIC LYMPH NODE TARGETED AMPHIPHILE IMMUNOTHERAPY VERSUS OBSERVATION IN RESECTED PANCREATIC DUCTAL ADENOCARCINOMA: RANDOMIZED PHASE 2 STUDY
Senior Faculty
Dr Morgan Clin Onc | Dr. Eng Med Onc | Dr Westphalen Med Onc | Dr O'Kane Med Onc
Faculty
Dr Akkus Med Onc | Dr Hornstein Med Onc | Dr Pacheco Med Onc
[faculty headshots]
WWW.ONCOALERT360.COM
[Slide 1]
ESMO26
TOP TEN BY ONCOALERT
LUNG CANCER
OncoAlert 360 [logo] Oncology For Colleagues By Colleagues
WWW.ONCOALERT360.COM
LBA3 DELLPHI-305: TARLATAMAB PLUS DURVALUMAB VS DURVALUMAB AS FIRST-LINE MAINTENANCE FOLLOWING DURVALUMAB, PLATINUM AND ETOPOSIDE IN EXTENSIVE-STAGE SCLC: PRIMARY ANALYSIS OF THE PHASE 3 TRIAL
LBA5 KRASCENDO 1: EFFICACY AND SAFETY OF DIVARASIB VS SOTORASIB OR ADAGRASIB IN PREVIOUSLY TREATED LOCALLY ADVANCED OR METASTATIC KRAS G12C-MUTATED NSCLC
LBA6 SAFFRON: OSIMERTINIB + SAVOLITINIB VS PLATINUM-PEMETREXED IN EGFRM MET-OVEREXPRESSED AND/OR -AMPLIFIED ADVANCED NSCLC POST-OSIMERTINIB: PHASE 3 PRIMARY RESULTS
LBA67 OPTITROP-LUNG04: FINAL OS ANALYSIS OF SACITUZUMAB TIRUMOTECAN VERSUS PLATINUM-BASED CHEMOTHERAPY IN EGFR-MUTATED NSCLC AFTER PROGRESSION ON EGFR-TKI: PHASE III STUDY
LBA66 OPTITROP-LUNG06: SACITUZUMAB TIRUMOTECAN PLUS PEMBROLIZUMAB VERSUS CHEMOTHERAPY PLUS PEMBROLIZUMAB AS FIRST-LINE TREATMENT FOR PD-L1-NEGATIVE ADVANCED NON-SQUAMOUS NSCLC: RANDOMIZED PHASE 3 STUDY
2614O PERSEE: PEMBROLIZUMAB WITH OR WITHOUT PLATINUM-BASED CHEMOTHERAPY AS FIRST-LINE TREATMENT IN ADVANCED NSCLC WITH PD-L1 ≥50%: PHASE 3 TRIAL
LBA69 SANOVO: SAVOLITINIB OR PLACEBO COMBINED WITH OSIMERTINIB IN TREATMENT-NAÏVE ADVANCED NSCLC WITH EGFR MUTATION AND MET OVEREXPRESSION: PHASE 3 RESULTS
2618RO IFCT-2103 DIAL: CONTINUATION PEMBROLIZUMAB (± PEMETREXED) UP TO 2 YEARS VERSUS OBSERVATION IN METASTATIC NSCLC WITH DISEASE CONTROL AT 6 MONTHS: PHASE 2 ANALYSIS
LBA71 PANKU-LUNG01: RANDOMIZED PHASE III STUDY OF IZALONTAMAB BRENGITECAN IN EGFR-MUTANT NON-SQUAMOUS NSCLC AFTER PROGRESSION ON A THIRD-GENERATION EGFR TKI
2613O SARON: PRIMARY RESULTS OF A RANDOMISED-CONTROLLED TRIAL OF CONSOLIDATION RADIOTHERAPY FOR SYNCHRONOUS OLIGOMETASTATIC NON-SMALL CELL LUNG CANCER
Senior Faculty
[headshots]
Dr Morgan Clin Onc
Dr Liu Med Onc
Dr Popat Med Onc
Dr Lovly Med Onc
Dr Lopes Med Onc
Dr Aggarwal Med Onc
Dr Reck Med Onc
Dr Massuti Med Onc
Dr Malapelle Pathologist
Ms Feldman Patient Advocate
Associate Faculty
Dr Mirallas Med Onc
Dr Özkerim Med Onc
[Slide 1]
ESMO 2026 KEY TRIALS
DAY 1 PREVIEW | 23 OCT
[Location/time | Tumor | Trial / regimen / abstract | Title | Presenter | institution logo]
Alicante Auditorium - Hall 6 13:30-13:40 | Breast Cancer | TALENT
T-DXd ± Anastrozole
LBA23 | Final results of TALENT: A neoadjuvant trial of T-DXd with or without anastrozole, or in sequence with chemotherapy for HER2-low, HR+ early-stage breast cancer | Sara A. Hurvitz | [UCLA Health Jonsson Comprehensive Cancer Center logo]
Alicante Auditorium - Hall 6 14:25-14:35 | Breast Cancer | NATALEE
Ribo + NSAI
LBA25 | Adjuvant ribociclib (RIB) + nonsteroidal aromatase inhibitor (NSAI) in patients (pts) with HR+/HER2- early breast cancer (EBC): NATALEE 6-y overall survival (OS) and efficacy outcomes | Dennis J. Slamon | [logo]
Alicante Auditorium - Hall 6 14:35-14:45 | Breast Cancer | PANKU-Breast01
Iza-bren
LBA50 | PANKU-Breast01: Randomized phase III study of izalontamab brengitecan (iza-bren) in previously treated unresectable locally advanced or metastatic (LA/M) hormone receptor-positive/HER2- negative (HR+/HER2-) breast cancer (BC) | Bo Lan | [logo]
Almeria Auditorium - Hall 9 13:30-13:40 | GI Cancer | G-HOPE-001
Arcotatug tavatecan vs TPC
LBA77 | Arcotatug tavatecan (IBI343/TAK-921) versus treatment of physician's choice (TPC) in previously treated, advanced gastric or gastroesophageal junction adenocarcinoma (G/GEJA): First interim analysis of the randomized, open-label, phase 3, G-HOPE-001 study | Kohei Shitara | [logo]
Almeria Auditorium - Hall 9 13:40-13:50 | GI Cancer | SANO
Active surveillance vs standard surgery (after neoadj CRT)
LBA78 | Active surveillance versus standard surgery after neoadjuvant chemoradiotherapy for oesophageal cancer: Long-term results of a cluster-randomised controlled trial (SANO) | Sanjiv S. Gangaram-Panday | [Erasmus MC logo]
Almeria Auditorium - Hall 9 13:50-14:00 | GI Cancer | KEYNOTE-975
Pembro + CRT
2875O | Pembrolizumab or placebo plus concurrent definitive chemoradiotherapy in esophageal and gastroesophageal junction (GEJ) cancer: The phase 3 randomized KEYNOTE-975 study | Manish A. Shah | [MSD logo]
Almeria Auditorium - Hall 9 14:22-14:32 | GI Cancer | RASolute 302
Daraxon vs Chemo
LBA82 | Daraxonrasib, a RAS(ON) multi-selective inhibitor vs chemotherapy in previously treated metastatic pancreatic adenocarcinoma (mPDAC): Additional subgroup analyses from the ph3 RASolute 302 study | Zev A. Wainberg | [logo]
Barcelona Auditorium - Hall 9 13:30-13:40 | GU Cancer | KEYNOTE-866
Pembro + Gem + Cis
4735O | Perioperative pembrolizumab (pembro) or placebo (pbo) + neoadjuvant cisplatin (cis) and gemcitabine (gem) in participants (pts) with muscle-invasive bladder cancer (MIBC): the double-blind, phase 3 KEYNOTE-866 study | Jens Bedke | [MSD logo]
Barcelona Auditorium - Hall 9 13:40-13:50 | GU Cancer | ENERGIZE
Nivo + Chemo -> Nivo
4736O | Results from a phase 3 trial of neoadjuvant (neoadj) chemotherapy alone vs in combination with nivolumab followed by postsurgical adjuvant nivolumab in patients (pts) with muscle-invasive bladder cancer (MIBC) | Andrea Necchi | [logo]
Barcelona Auditorium - Hall 9 14:22-14:32 | GU Cancer | KEYNOTE-905
Pembro or EV + Pembro
4733O | Perioperative pembrolizumab (pembro) or enfortumab vedotin (EV) plus pembro in pts with muscle-invasive bladder cancer (MIBC) who are cisplatin-ineligible: ad hoc analysis from KEYNOTE-905 | Anders Ullén | [MSD logo]
Barcelona Auditorium - Hall 9 14:32-14:42 | GU Cancer | KEYNOTE-B15
EV + Pembro
4734O | ctDNA analysis of the Phase 3 KEYNOTE-B15 trial: neoadjuvant and adjuvant (neoadj-adj) enfortumab vedotin (EV) + pembrolizumab (pembro) for participants (pts) with muscle-invasive bladder cancer (MIBC) who are eligible for cisplatin | Jonathan A. Chatzkel | [MSD logo]
Bilbao Auditorium - Hall 3 14:34-14:39 | GU Cancer | CAPItello-281
Capi + Abi vs Pbo +Abi
LBA56 | Capivasertib (capi) + abiraterone (abi) vs placebo (pbo) + abi in patients (pts) with PTEN-deficient metastatic hormone-sensitive prostate cancer (mHSPC): Updated overall survival (OS) from CAPItello-281 | Karim Fizazi | [AstraZeneca logo]
Almeria Auditorium - Hall 9 16:15-16:20 | GI Cancer | HERIZON-GEA-01
Zani + Chemo ± Tisle
LBA79 | Zanidatamab (zani) + chemotherapy (CT) ± tislelizumab (TIS) for first-line (1L) HER2-positive (HER2+) advanced/metastatic gastroesophageal adenocarcinoma (mGEA): Second interim analysis (IA) from HERIZON-GEA-01 | Kohei Shitara | [logo]
Almeria Auditorium - Hall 9 16:42-16:47 | GI Cancer | DEWI
Dosta (Watch-and-wait)
2877RO | Watch-and-wait (W&W) strategy for dostarlimab in localized deficient dMMR/MSI-H gastroesophageal adenocarcinoma (GEA): Results from the first interim analysis of the GERCOR-GONO DEWI phase II study | Thierry André | [GERCOR logo]
Almeria Auditorium - Hall 9 16:47-16:52 | GI Cancer | RAMIRIS
Ram + FOLFIRI vs Ram + Pacli
2878RO | FOLFIRI plus ramucirumab versus paclitaxel plus ramucirumab as second-line therapy for taxane-pretreated patients with advanced or metastatic gastroesophageal adenocarcinoma–Final results of the phase III IKFs602/AIO RAMIRIS Study | Sylvie Lorenzen | [IKF logo]
LARVOL
[Slide 1]
Breast Cancer: Top Trending Abstracts on X Ahead of ESMO 2026
[legend, color-coded] ADC | IO | CDK4/6i, SERD | HER2 TKI, Aromatase inhibitor | ctDNA surveillance, Ultrasensitive monitoring, Dx Radiopharmaceutical
[columns: Date | Abstract ID | Presenter | Phase | Abstract Title | Erika Hamilton | Mitsuo Terada | Paolo Tarantino | Yakup Ergün | ChatGPT 5.6 Sol | Gemini 3.8 Flash | Claude Opus 5.5 | Grok 4.7]
Oct 23 | LBA25 | Slamon | P3 | NATALEE: Adj RIB + NSAI in HR+/HER2 eBC - 6 yrs OS and efficacy outcomes | X | X | X | X | X | X | X | X
Oct 24 | LBA51 | Rugo | P3 | KEYNOTE-B49: Pembro vs Pbo + CT in HR+/HER2- AdvBC | X | X | X | X | X | X | X | X
Oct 23 | LBA50 | Bo Lan | P3 | PANKU-Breast01: Iza-bren in previously treated unresec LA/m HR+/HER2- BC | | | X | X | X | X | X | X
Oct 24 | LBA14 | Redfern | P3 | FINER: Fulv + Ipatasertib as tx for HER2- and ER+ mBC: OS Results | | | X | X | X | X | X | X
Oct 24 | LBA16 | Pistilli | P3 | VIKTORIA-1: Geda + fulv ± palbo vs SOC in HR+/HER2- AdvBC - Updated results | | | | X | X | X | X | X
Oct 24 | 1RO | Kalinsky | P3 | postMONARCH: Abema + fulv vs placebo + fulv for HR+ HER2- AdvBC following progression on a prior CDK4/6i + EC therapy - OS results | | | | X | X | X | X | X
Oct 26 | 4639RO | Man Li | P3 | OptiTROP-Breast01: Sacituzumab tirumotecan vs CT in previously treated loc recurr/mTNBC - Final OS analysis | | | X | | X | X | X | X
Oct 23 | LBA23 | Hurvitz | P2 | TRIO-US B-12 TALENT: Neoadj T-DXd ± anastrozole, or in seq with CT for HER2-low, HR+ eBC - Final results | X | X | X | X | | | |
Oct 23 | 538RO | Werutsky | P3 | lidERA BC: PROs trial of GIRE in pts with ER+ HER2- eBC | X | | X | | | | X | X
Oct 24 | 1842O | Giordano | P2 | FOURLIGHT-1: ATI + FULV in HR+/HER2- Adv/mBC who progressed on prior CDK4/6i - Efficacy and safety | X | | X | | | | X | X
Oct 23 | LBA24 | Mamounas | P3 | NSABP B-42: Ext letro in postmeno women with HR+ BC who have completed previous adj therapy with an AI - Final Analysis | X | X | X | | | | |
Oct 23 | 542RO | Ozaki | P3 | INSPIRE: Prognostic impact of postope ctDNA surveillance on RFS and molecular lead time in H-risk BC | X | X | X | | | | |
Oct 24 | 2RO | Tolaney | P3 | evERA BC: GIRE + E in ER+ HER2- AdvBC in the post-CDK4/6i setting - Retrospective exploratory biomarker analyses | | | | X | X | X | |
Oct 24 | LBA96 | Dent | P3 | TROPION-Breast02: 1L Dato-DXd vs CT in loc recurr inoperable or mTNBC for whom IO was not an option: Exploratory analysis of pts with brain met | X | | X | | | | |
Oct 24 | LBA26 | Ribeiro | P2 | POP-DURVA: Short-term preope durva for stage I TNBC - First results | | X | X | | | | |
Oct 26 | LBA49 | Saura Manich | P3 | DESTINY-Breast09: T-DXd + P vs THP in HER2+ Adv/mBC and BL BMs | X | | X | | | | |
Oct 26 | 1767RO | Sammons | P2 | BRIDGET: Tucatinib added to trastuzumab/pertuzumab/ado-trastuzumab emtansine after isolated intracranial progression in Adv HER2+ BC | | X | X | | | | |
Oct 23 | 544RO | De Placido | P3 | GIM3 FATA: Tx schedule and three AIs comparison in postmeno HR+ eBC - Final analysis | | | X | | | | |
Oct 23 | 539RO | Barrios | P3 | DESTINY-Breast05: HRQoL + T-DXd vs T-DM1 in H-Risk HER2+ eBC | | | X | | | | |
Oct 23 | 540RO | Barcenas | – | B-STRONGER-I: Ultrasensitive monitoring of early ctDNA dynamics during neoadj tx in eTNBC - Pre-Interim Results | | | X | | | | |
Oct 24 | 3RO | Gennari | P2 | 2013-000287-29: 18F-FES PET-defined whole-body ER heterogeneity identifies EC responsiveness and predicts survival in ER+/HER2- mBC | | | | X | | | |
Format and methodology credit: Dr. Mike Thompson
LARVOL
[Slide 1]
exclusive
FEATURING
[circular headshot] Balazs Halmos, MD, MS
[circular headshot] Dylan Fortman, MD
OncLive
Find out which lung cancer
presentations experts are
most excited to see at the
2026 ESMO Congress.
Sign up to read OncLive's preview of some of the
most anticipated abstracts ahead of the conference.
[Slide 1]
Lung Cancer: Top Trending Abstracts on X Ahead of ESMO 2026
[colour key:]
ADC
BsAb
IO
KRAS G12C, EGFR TKI, MET TKI
Radiotherapy
[column headers (voices):] Amol Akhade | Bijoy Telivala | Chandrakanth MV | Jose Fernando Moura | Mario Balsa | Masahiro Torasawa | Patrick Forde | Rishabh Jain | Riyaz Shah | Rohit Malde | Yakup Ergün | ChatGPT 5.6 Sol | Gemini 3.8 Flash | Claude Opus 5.5 | Grok 4.7
Date | Abstract ID | Presenter | Phase | Abstract Title
Oct 24 | LBA3 | Sands | P3 | DeLLphi-305: Tarlatamab + durva vs durva as 1LM therapy following durva + EP in ES-SCLC - Primary analysis | X X X X X X X X X X X X X X X
Oct 25 | LBA6 | Shun Lu | P3 | SAFFRON: Osi + savo vs plat-pem in EGFRm MET-OE and/or -amplified (AMP) adv NSCLC post-osi - Primary results | X X X X X X X X X X X X X X X
Oct 25 | LBA5 | Skoulidis | P3 | Krascendo 1: Diva vs Soto or Ada in previously treated LA/m KRAS G12C-mut NSCLC - Efficacy and safety results | X X X X X X X X X (Amol Akhade through Riyaz Shah) X X X X X (Yakup Ergün, ChatGPT 5.6 Sol, Gemini 3.8 Flash, Claude Opus 5.5, Grok 4.7)
Oct 25 | LBA67 | Feng Fang | P3 | OptiTROP-Lung04: Sac-TMT vs platinum-based CT in EGFRm NSCLC after progression on EGFR-TKI - Final OS analysis | X (Chandrakanth MV) X X X X X (Yakup Ergün, ChatGPT 5.6 Sol, Gemini 3.8 Flash, Claude Opus 5.5, Grok 4.7)
Oct 26 | LBA69 | Yi-Long Wu | P3 | SANOVO: Savo / pbo + osi in tx-naïve adv NSCLC with EGFRm and MET overexpression | X (Mario Balsa) X X X X X (Yakup Ergün, ChatGPT 5.6 Sol, Gemini 3.8 Flash, Claude Opus 5.5, Grok 4.7)
Oct 25 | LBA68 | Peters | P3 | SigVie-002: SV vs DTX in previously treated non-sqNSCLC | X (Chandrakanth MV) X (Rishabh Jain) X X X (ChatGPT 5.6 Sol, Gemini 3.8 Flash, Claude Opus 5.5)
Oct 25 | LBA66 | Caicun Zhou | P3 | OptiTROP-Lung06: Sac-TMT + pembro vs CT + pembro as 1L tx for PD-L1-neg adv non-sq NSCLC | X X X X X (Yakup Ergün, ChatGPT 5.6 Sol, Gemini 3.8 Flash, Claude Opus 5.5, Grok 4.7)
Oct 26 | LBA71 | Li Zhang | P3 | PANKU-Lung01: Iza-bren in EGFRm non-sq NSCLC after progression on a third-generation EGFR TKI | X X X X X (Yakup Ergün, ChatGPT 5.6 Sol, Gemini 3.8 Flash, Claude Opus 5.5, Grok 4.7)
Oct 25 | 2614O | Decroisette | P3 | PERSEE: Pembro ± platinum-based CT as 1L tx in adv NSCLC with PD-L1 ≥50% | X (Yakup Ergün) X (Grok 4.7)
Oct 24 | LBA73 | Sebastian | P2 | PACE-LUNG: Efficacy of additional CT for pts with EGFRm NSCLC with the continued presence of plasma ctDNA EGFRm at week 3 after start of osi 1L tx | X (Yakup Ergün)
Oct 25 | 2613O | McDonald | P2 | SARON: Consolidation radiotherapy for synchronous oligometastatic NSCLC - Primary Results | X (Yakup Ergün)
Format and methodology credit: Dr. Mike Thompson
LARVOL
[Slide 1]
[cancernetwork logo] cancernetwork
home of the journal ONCOLOGY
ESMO CONGRESS 2026 PREVIEW
GYNECOLOGIC ONCOLOGY
The Data to Watch at
ESMO 2026
De-Escalation and ADCs
1 KEYNOTE-C93 ENDOMETRIAL
First-line pembrolizumab vs chemotherapy in dMMR disease
2 TroFuse-005 ENDOMETRIAL
Sacituzumab tirumotecan after chemotherapy and immunotherapy
3 BEHOLD-1 OVARIAN
B7-H4–targeted mocertatug rezetecan in PROC
4 REJOICE-Ovarian01 OVARIAN
CDH6-directed raludotatug deruxtecan in PROC
5 DUO-E ENDOMETRIAL
Interim OS with durvalumab ± olaparib
Featuring insights from Eirwen M. Miller, MD, and Nujsaubnusi C. Vue, MD, of Allegheny Health Network
Read the full preview ›
CANCERNETWORK.COM
[Slide 1]
ESMO 2026
Breast Cancer Abstracts
[pink ribbon]
LBA25
NATALEE
Ribociclib + a nonsteroidal
aromatase inhibitor.
HR-positive, HER2-negative
early breast cancer.
[capsule and pill icons + breast icon labeled AI]
Focus:
Six-year efficacy and overall
survival outcomes following
adjuvant treatment.
LBA50
PANKU-Breast01
Izalontamab brengitecan.
Previously treated unresectable
locally advanced or metastatic
HR-positive, HER2-negative
breast cancer.
[antibody-drug conjugate icon]
Focus:
Randomized phase III evaluation
of treatment efficacy and safety.
538RO
PROs from lidERA
Giredestrant, an oral SERD.
ER-positive, HER2-negative
early breast cancer.
[capsule icon + patient icon]
Focus:
Patient-reported outcomes (PROs),
including quality of life, symptoms
and treatment tolerability versus
standard endocrine therapy.
1842O
FOURLIGHT-1
Atirmociclib (selective CDK4 inhibitor)
+ fulvestrant.
HR-positive, HER2-negative
advanced breast cancer after
CDK4/6 inhibitor treatment.
[capsule icon + antibody icon]
Key result:
Median PFS was 9.4 vs 6.6 months
(HR 0.60), according to previously
reported topline results.
[Slide 1]
ESMO 2026 BREAST CANCER PREVIEW • OCT 23-27 • MADRID
6 Breast Cancer Trials to Watch at ESMO 2026
3 breast oncologists on the data they are tracking in Madrid
cancernetwork® home of the journal ONCOLOGY
[headshot] Erika Hamilton, MD
Sarah Cannon Research Institute
[headshot] Jasmin Hundal, MD
Breast medical oncologist
[headshot] Nusrat Jahan, MD
University of Alabama at Birmingham
1 KEYNOTE-B49
Pembrolizumab plus chemotherapy in HR+/HER2− advanced disease (LBA51)
2 SWITCH
Switching to novel ADCs after prior ADC therapy (4RO)
3 PANKU-Breast01
Bispecific ADC iza-bren in HR+/HER2− disease (LBA50)
4 VIKTORIA-1
Updated gedatolisib data in HR+/HER2− advanced disease (LBA16)
5 evERA
ctDNA biomarker analyses of giredestrant plus everolimus (2RO)
6 DESTINY-Breast11
MRI responses during neoadjuvant T-DXd in HER2+ early disease (543RO)
cancernetwork.com
@cancernetwrk
[Slide 1]
ESMO 2026
Lung Cancer Abstract Highlights
DeLLphi-305 (LBA3)
Tarlatamab + durvalumab vs. durvalumab alone as first-line maintenance for ES-SCLC, testing DLL3-directed T-cell engagement earlier in treatment.
OptiTROP-Lung06 (LBA66)
Sacituzumab tirumotecan (TROP2 ADC) + pembrolizumab vs. chemotherapy + pembrolizumab in first-line PD-L1-negative advanced nonsquamous NSCLC.
OptiTROP-Lung04 (LBA67)
Final overall survival analysis of sacituzumab tirumotecan vs. platinum-based chemotherapy after EGFR-TKI progression in EGFR-mutated NSCLC.
Sigvotatug Vedotin (LBA68)
A phase III comparison with docetaxel in previously treated nonsquamous NSCLC, examining efficacy and safety.
KRASCENDO 1 (LBA5)
Divarasib vs. sotorasib or adagrasib in previously treated KRAS G12C-mutated NSCLC, offering a direct comparison within the targeted therapy class.
SAFFRON (LBA6)
Osimertinib + savolitinib vs. platinum-pemetrexed after osimertinib progression in EGFR-mutated NSCLC with MET overexpression and/or amplification.
SANOVO (LBA69)
Savolitinib + osimertinib vs. osimertinib alone in treatment-naïve EGFR-mutated NSCLC with MET overexpression, exploring upfront dual-target inhibition.
PANKU-Lung01 (LBA71)
Izalontamab brengitecan, a bispecific ADC, in EGFR-mutated nonsquamous NSCLC after progression on a third-generation EGFR-TKI.
HERON-Lung01 (LBA72)
Ruzaltatug rezetecan, a HER3-directed ADC, vs. platinum-based chemotherapy after EGFR-TKI progression in EGFR-mutated advanced NSCLC.
Neotorch (LBA64)
Final analysis of perioperative toripalimab + chemotherapy in resectable stage II–III NSCLC, focusing on long-term outcomes.
[icons: lungs, antibodies, DNA helix, pills, scalpel]
[Slide 1]
touchONCOLOGY [logo]
"
ESMO is always a highlight of the oncology calendar, bringing together the latest science, fresh perspectives and the experts shaping the future of cancer care. In genitourinary oncology, I am particularly looking forward to addressing key questions in perioperative and curative-intent treatment across muscle-invasive bladder cancer and high-risk localised prostate cancer. The real value of this meeting lies in turning scientific progress into better clinical decisions and, ultimately, better outcomes for our patients.
[headshot photo]
Prof Axel S Merseburger
Editor-in-Chief, touchONCOLOGY
ESMO 2026
MADRID, SPAIN
23-27 OCTOBER 2026
[Slide 1]
HUTCHMED Highlights Clinical Data to be Presented at
ESMO Congress 2026
October 23-27, 2026 | Madrid, Spain
HUTCHMED [logo]
Sponsored Studies
Abstract title | Presenter/ Lead author | Presentation details
Osimertinib (osi) + savolitinib (savo) vs platinum–pemetrexed (plat–pem) in EGFRm MET-overexpressed (OE) and/or -amplified (AMP) advanced NSCLC post-osi: SAFFRON Phase (Ph) 3 primary results | Shun Lu (Shanghai, China) | LBA6 Presidential Symposium II Alicante Auditorium - Hall 6 Sunday, October 25, 2026 16:30 - 18:15 CEST
Savolitinib or Placebo Combined with Osimertinib in Treatment-Naïve Advanced NSCLC with EGFR Mutation and MET Overexpression: Results from the Phase 3 SANOVO Study | Yi-Long Wu (Guangzhou, China) | LBA69 Proffered paper 2: NSCLC, metastatic Alicante Auditorium - Hall 6 Monday, October 26, 2026 08:30 - 10:00 CEST
Updated results from a fruquintinib Expanded Access Program for patients with previously treated metastatic colorectal cancer | Stefan Kasper (Essen, Germany) | 848P Poster Session: Colon cancer
Association between dose adjustment and treatment outcomes in patients with advanced renal cell carcinoma receiving fruquintinib plus sintilimab: A post-hoc analysis of the FRUSICA-2 trial | Yuanyuan Qu (Shanghai, China) | 3655eP E-poster Session: Renal cancer
Efficacy of fruquintinib plus sintilimab in special populations with advanced renal cell carcinoma: A subgroup analysis of FRUSICA-2 study | Kaiwei Yang (Beijing, China) | 3667eP E-poster Session: Renal cancer
Final phase 2 analysis of surufatinib plus camrelizumab, nab-paclitaxel and gemcitabine in first-line metastatic pancreatic cancer | Shukui Qin (Nanjing, China) | 3156P Poster Session: Pancreatic cancer
[Slide 2]
HUTCHMED Highlights Clinical Data to be Presented at
ESMO Congress 2026
October 23-27, 2026 | Madrid, Spain
HUTCHMED [logo]
Investigator-initiated Studies (1/2)
Abstract title | Presenter/ Lead author | Presentation details
Fruquintinib plus capecitabine maintenance after first-line anti-EGFR antibody plus chemotherapy in RAS/BRAF wild-type metastatic colorectal cancer: A phase Ib/II study | Lin Yang/ Letian Zhang (Beijing, China) | 877eP E-poster Session: Colon cancer
Real-world effectiveness and safety of fruquintinib in patients with metastatic colorectal cancer in Spain: The FrESP study | Ana Fernandez Montes (Ourense, Spain) | 880eP E-poster Session: Colon cancer
CONCEPT (COmbinatioN of CEtuximab Plus fruquintinib Treatment ± immunotherapy): A multicenter, randomized, open-label phase II trial in first-line pMMR RAS/BRAF wild-type unresectable metastatic colorectal cancer | Kefeng Ding (Hangzhou, China) | 890eP E-poster Session: Colon cancer
A real-world study of low-dose fruquintinib combined with trifluridine/tipiracil hydrochloride (TAS-102) in the third-line and beyond treatment of metastatic colorectal cancer | Yuehong Cui/ Li Liang (Shanghai, China) | 903eP E-poster Session: Colon cancer
Real-world outcomes with fruquintinib in heavily pretreated metastatic colorectal cancer: Impact of patient and disease characteristics | Maria Maddalena Laterza (Pozzuoli, Italy) | 964eP E-poster Session: Colon cancer
A phase II, open-label, randomized study of doublet chemotherapy (FOLFOX or FOLFIRI) plus fruquintinib compared with doublet chemotherapy (FOLFOX or FOLFIRI) plus bevacizumab in second line setting for a metastatic colorectal cancer: ULYSSE- FFCD2406 - PRODIGE115 (trials in progress) | Jean Marc Phelip (Saint-Étienne, France) | 991eTiP E-poster Session: Colon cancer
Phase II study of fruquintinib plus utidelone in platinum-resistant recurrent ovarian cancer (FRUTD Trial) | Zheng Feng (Shanghai, China) | 1283P Poster Session: Gynaecological cancers
Fruquintinib plus eribulin in patients with metastatic HR+, HER2-breast cancer after progression on endocrine therapy plus CDK4/6 inhibitor: Updated results from a phase II study | Yuan Yuan (Nanjing, China) | 1896eP E-poster Session: HR+ breast cancer
Fruquintinib plus sintilimab and XELOX as first-line treatment for advanced gastric or gastroesophageal junction adenocarcinoma: A single-arm, open-label, multicenter phase II study | Hua Wang (Nanchang, China) | 2980eP E-poster Session: Oesophagogastric cancer
Fruquintinib plus cadonilimab and S-1 in previously treated unresectable locally advanced or metastatic esophageal squamous cell carcinoma: preliminary efficacy and safety results from a phase Ib/II study | Huiyan Luo (Guangzhou, China) | 2981eP E-poster Session: Oesophagogastric cancer
Nanoliposomal irinotecan (nal-IRI) combined with fruquintinib as second-line treatment for advanced gastric cancer: A single-arm, open-label, dose-escalation and expansion phase I/II trial | Jieer Ying/ Qi Xu (Hangzhou, China) | 2986eP E-poster Session: Oesophagogastric cancer
FRUQUITAS trial: ENGIC intergroup randomized phase III of trifluridine/tipiracil +/- fruquintinib in pre-treated metastatic gastro-oesophageal adenocarcinoma | David Tougeron (Poitiers, France) | 3079eTiP E-poster Session: Oesophagogastric cancer
[Slide 3]
HUTCHMED Highlights Clinical Data to be Presented at
ESMO Congress 2026
October 23-27, 2026 | Madrid, Spain
HUTCHMED [logo]
Investigator-initiated Studies (2/2)
Abstract title | Presenter/Lead author | Presentation details
CHOICE III: short-course preoperative radiotherapy followed by fruquintinib plus anti–PD-1 antibody (serplulimab) for neoadjuvant treatment of pMMR/MSS mid-to-low locally advanced rectal cancer: A single-arm, single-center, prospective phase II study | Wei Zhang (Shanghai, China) | 3582eTiP E-poster Session: Rectal and anal cancer
First-line fruquintinib plus serplulimab for metastatic non-clear cell renal cell carcinoma: Updated results from the phase II FRONTIER study | Jiwei Huang (Shanghai, China) | 3614P Poster Session: Renal cancer
Latest efficacy and safety analysis of surufatinib combined with EP regimen and serplulimab as first-line treatment for extrapulmonary neuroendocrine carcinoma | Tao Zhang/ Zhenyu Lin (Wuhan, China) | 2394RO Rapid Oral Session: NETs and endocrine tumours Pamplona Auditorium - Hall 5 Friday, October 23, 2026 16:15 - 17:45 CEST
Surufatinib combined with toripalimab and nab-paclitaxel/ gemcitabine chemotherapy as first-line treatment for advanced pancreatobiliary-type ampullary carcinoma: A prospective phase II Clinical Trial | Juan Du (Nanjing, China) | 507eP E-poster Session: Biliary tract cancer, incl. cholangiocarcinoma
Efficacy and safety of surufatinib in combination with CAPTEM in advanced G2/G3 Neuroendocrine Tumors: Results from a single-arm, phase II Trial | Wei Wang (Guangzhou, China) | 2403P Poster Session: Neuroendocrine tumours
Surufatinib plus S-1/temozolomide as first-line therapy in MGMT-low advanced pancreatic neuroendocrine tumours (SUSTEM-p): An open-label, single-centre phase Ib/II trial | Yihebali Chi (Beijing, China) | 2411P Poster Session: Neuroendocrine tumours
Updated results of a prospective, open-label study of surufatinib plus CAPTEM as conversion therapy for unresectable pancreatic neuroendocrine tumors | Ziyao Wang (Chengdu, China) | 2412P Poster Session: Neuroendocrine tumours
Matching-adjusted indirect comparison of surufatinib versus high-dose OCT-LAR in patients with advanced GEP-NETs who progressed on prior SSA Therapy | Jianming Xu (Beijing, China) | 2415P Poster Session: Neuroendocrine tumours
Surufatinib combined with octreotide LAR for the treatment of G1/G2 GEP-NETs: A single-arm, prospective, open-label phase II study | Xiaofeng Sun (Nanjing, China) | 2439eP E-poster Session: Neuroendocrine tumours
Six weeks of induction gemcitabine plus nab paclitaxel (AG) followed by sequential surufatinib plus AG or AG alone as first line therapy for locally advanced or metastatic pancreatic ductal adenocarcinoma (mPDAC): A single center, two cohort, phase II study | Jin Xu/ Jialin Li (Shanghai, China) | 3168P Poster Session: Pancreatic cancer
A phase Ib/II study of radiotherapy combined with surufatinib and sintilimab for localized high-risk limb and trunk soft tissue sarcomas: A prospective single-center trial | Yan Wang (Shanghai, China) | 3739P Poster Session: Sarcoma
Surufatinib plus serplulimab, etoposide, and carboplatin as first-line treatment for extensive-stage small cell lung cancer (ES-SCLC): Updated results from a single-arm, phase Ia/Ib trial | Haipeng Xu/ Longfeng Zhang (Fuzhou, China) | 3831P Poster Session: Small cell lung cancer
[Slide 1]
#ESMO26 | #Oncology | #MedicalAffairs | #ClinicalTrials | #Pharma
10 DAYS UNTIL ESMO
THE 10 ABSTRACTS EVERYONE KEEPS TALKING ABOUT.
[Illustration of a printed booklet: ESMO 2026 CONGRESS PROGRAMME; tab labelled TOP 10]
Top 10 Abstracts
1 INTerpath-001 [circled]
2 VOLGA
3 DeLLphi-305
4 DASL-HiCaP
5 KRAScendo 1
6 SAFFRON
7 CLARITY-Gastric 01
8 HARMONi-GI1
9 TroFuse-005
10 OptiTROP-Lung06
Most talked about is not always most useful for patients.
[Slide 1]
NSCLC, metastatic
2805eP - First-line BRAF/MEK inhibition versus immune checkpoint inhibitor-based therapy in BRAF V600E-mutant metastatic NSCLC: A meta-analysis
Presentation Number 2805eP
Speakers Yakup Ergün (Diyarbakır, Türkiye)
Authors Yakup Ergün (Diyarbakır, Türkiye), Rohit Gosain (Buffalo, United States of America), Rahul Gosain (Rochester, United States of America)
Abstract
Background
The optimal first-line treatment for patients with BRAF V600E-mutant metastatic NSCLC remains unclear. While current ESMO and NCCN guidelines prioritize BRAF/MEK inhibition, no randomized trials have directly compared targeted therapy with immune checkpoint inhibitor (ICI)-based regimens. We performed a meta-analysis of retrospective studies to compare efficacy outcomes between these strategies.
Methods
A systematic literature search was conducted in PubMed, Embase, and the Cochrane Library. Retrospective studies comparing first-line BRAF/MEK inhibitor combinations versus ICI-based therapies (monotherapy or chemoimmunotherapy) were included. The primary endpoints were progression-free survival (PFS) and overall survival (OS), while objective response rate (ORR) was evaluated as a secondary endpoint. Effect sizes were pooled as hazard ratios (HRs) for survival outcomes and odds ratios (ORs) for ORR with 95% confidence intervals (CIs) using fixed- or random-effects models based on heterogeneity. Heterogeneity was assessed using the I² statistic.
Results
Four retrospective studies including 589 patients (BRAF/MEK: n=384; ICI-based: n=205) were analyzed. No statistically significant difference in PFS was observed between the two strategies (HR 1.22; 95% CI 0.89-1.68; p=0.22; I²=0%); however, a numerical trend favored BRAF/MEK inhibition. Similarly, OS did not differ significantly (HR 1.01; 95% CI 0.59-1.73; p=0.97), although substantial heterogeneity was present (I²=69%). In contrast, ORR was significantly higher with BRAF/MEK inhibition compared to ICI-based therapy (61% vs 48%, OR 0.60; 95% CI 0.37-0.97; p=0.04; I²=0%).
Conclusions
In this meta-analysis of retrospective data, BRAF/MEK inhibition was associated with significantly higher response rates, while no statistically significant differences were observed in survival outcomes. A consistent numerical trend in PFS favoring targeted therapy suggests a potential efficacy signal that may not reach statistical significance due to the limited number of studies and patients. The substantial heterogeneity observed in OS further limits definitive interpretation.
[Slide 1]
MY TOP 10 LUNG CANCER ABSTRACTS
#ESMO26
01 LBA3 DeLLphi-305
Phase III primary analysis: Tarlatamab + durvalumab vs durvalumab as 1L maintenance after durvalumab + platinum/etoposide in ES-SCLC
Jacob Sands
02 2614O PERSEE
Phase III pembrolizumab with or without platinum-based chemotherapy as 1L treatment in advanced NSCLC with PD-L1 ≥50%
Chantal Decroisette
03 LBA66 OptiTROP-Lung06
Phase III sacituzumab tirumotecan + pembrolizumab vs chemotherapy + pembrolizumab in 1L PD-L1-negative advanced non-squamous NSCLC
Caicun Zhou
04 LBA6 SAFFRON
Phase III primary results: Osimertinib + savolitinib vs platinum–pemetrexed in EGFR-mutant, MET-overexpressed/amplified advanced NSCLC after osimertinib
Shun Lu
05 LBA5 KRAScendo 1
Phase III divarasib vs sotorasib or adagrasib in previously treated advanced KRAS G12C-mutated NSCLC
Ferdinandos Skoulidis
06 LBA67 OptiTROP-Lung04
Final OS analysis: Sacituzumab tirumotecan vs platinum-based chemotherapy in EGFR-mutated NSCLC after EGFR-TKI progression
Wen Feng Fang
07 2613O SARON
Primary results: Randomized trial of consolidation radiotherapy for synchronous oligometastatic NSCLC
Fiona McDonald
08 LBA69 SANOVO
Phase III savolitinib or placebo + osimertinib in treatment-naïve advanced NSCLC with EGFR mutation and MET overexpression
Yi-Long Wu
09 LBA71 PANKU-Lung01
Phase III izalontamab brengitecan in EGFR-mutant non-squamous NSCLC after progression on a third-generation EGFR TKI
Li Zhang
10 LBA73 PACE-LUNG
Single-arm phase II: Adding chemotherapy for EGFR-mutant NSCLC with persistent plasma EGFR-mutant ctDNA at week 3 of 1L osimertinib
Martin Sebastian
@dr_yakupergun
[Slide 1]
ESMO 2026 Industry Satellite Symposium
Transforming the Treatment Journey in EGFR-Mutant NSCLC
Sunday, 25 October 2026, 13:00-14:30 CET
Cordoba Auditorium, Hall 4, IFEMA MADRID, Madrid, Spain
Faculty
Chaired by:
Lizza Hendriks
Maastricht University Medical Center, The Netherlands
Antonio Passaro
European Institute of Oncology, Milan, Italy
Presented by:
Stephen Liu
MedStar Georgetown University Hospital, United States
Antonio Calles
Gregorio Marañón University General Hospital, Madrid, Spain
Learning objectives
After attending this symposium, participants should be able to:
Evaluate emerging clinical evidence on targeted therapies supporting the management of patients with EGFR-mutant NSCLC
Apply recent data to optimize treatment strategies and patient outcomes in clinical practice
[Slide 1]
ESMO 2026
Top 10 Lung Cancer Trials to Watch
23 - 27 October 2026 | Madrid, Spain
@DrRishabhOnco
[illustrations: lungs, Madrid Cibeles palace]
1 TARGETED THERAPY & MOLECULARLY DEFINED NSCLC — NEXT-GENERATION TARGETED STRATEGIES
1 DeLLphi-305 LBA3
Tarlatamab + durvalumab vs durvalumab maintenance in ES-SCLC
Can adding tarlatamab improve survival in ES-SCLC?
2 SAFFRON LBA6
Osimertinib + savolitinib vs platinum-pemetrexed after osimertinib in MET-altered EGFR+ NSCLC
Can MET inhibition overcome resistance to osimertinib?
3 ANTIBODY-DRUG CONJUGATES (ADCs) — NEW ADCs EXPANDING TREATMENT OPTIONS
3 Krascendo 1 LBA5
Divarasib vs sotorasib or adagrasib in previously treated KRAS G12C NSCLC
Can a next-generation KRAS G12C inhibitor improve outcomes?
4 OptiTROP-Lung06 LBA66
Sacituzumab tirumotecan + pembrolizumab vs chemotherapy + pembrolizumab in 1L PD-L1-negative nonsquamous NSCLC
Can an ADC improve outcomes in PD-L1-negative NSCLC?
5 OptiTROP-Lung04 LBA67
Sacituzumab tirumotecan vs chemotherapy after EGFR-TKI progression in NSCLC (final OS)
Does sacituzumab tirumotecan improve overall survival?
5 IMMUNOTHERAPY & OTHER STRATEGIES — NEW COMBINATIONS, NEW SETTINGS
6 SigVie-002 LBA68
Sigvotatug vedotin vs docetaxel in previously treated nonsquamous NSCLC
Does an integrin αvβ6 ADC improve outcomes?
7 SARON 26130
Consolidation radiotherapy in synchronous oligometastatic NSCLC
Does consolidation RT improve survival?
8 PERSEE 26140
Pembrolizumab alone vs pembrolizumab + chemotherapy in 1L NSCLC with PD-L1 ≥50%
Is chemotherapy needed with pembrolizumab in high PD-L1 NSCLC?
9 DeLLphi-304 38080
Extended OS follow-up of tarlatamab in previously treated SCLC
Long-term survival with tarlatamab in SCLC?
10 ASTRIDE 38090
Serplulimab vs atezolizumab + chemo in 1L ES-SCLC
Does serplulimab improve survival in ES-SCLC?
[Slide 1]
DATA FEATURED AT ESMO 2026
Madrid, Spain | October 23-27, 2026
Booth #8014
ORAL PRESENTATION: 2072O [CLINICAL]
Efficacy and safety of lifileucel + pembrolizumab in ICI-naïve advanced melanoma: final results from IOV-COM-202
Date: Fri, Oct 23, 2026 Time: 16:15-17:45
RAPID ORAL PRESENTATION: 3725RO [CLINICAL]
Lifileucel in patients with undifferentiated pleomorphic sarcoma or dedifferentiated liposarcoma
Date: Mon, Oct 26, 2026 Time: 08:30-10:00
POSTER: 2125P [HEOR]
Lifileucel vs nivolumab + relatlimab in anti-PD-(L)1-resistant advanced melanoma: a match-adjusted indirect comparison (MAIC) of efficacy outcomes
POSTER: 2117P [HEOR]
Indirect comparison of overall survival between lifileucel vs standard of care in US real-world settings in anti-PD-1-resistant advanced melanoma
POSTER: 4359P [TRANSLATIONAL]
Enrichment of putative tumor-reactive clones in NSCLC patients responding to lifileucel: temporal single cell analysis from a clinical trial
HEOR, health economics and outcomes research
IOVANCE BIOTHERAPEUTICS
[Slide 1]
Proffered Paper session
2614O - Pembrolizumab with or without platinum-based chemotherapy as first-line treatment in advanced NSCLC with PD-L1 ≥50%: PERSEE phase 3 trial (GFPC 01-2020)
Speakers Chantal Decroisette (Lyon, France, CEDEX)
Lecture Time 10:25 - 10:35
Abstract
Background
Pembrolizumab (pembro) monotherapy or in combination with chemotherapy are standard first-line options in advanced PD-L1 ≥50% NSCLC. We evaluated whether adding platinum-based chemotherapy improves outcomes versus pembro monotherapy.
Methods
This multicentre open-label phase 3 trial enrolled patients (pts) with untreated stage IV or not amenable to radiotherapy stage III PD-L1 ≥50% NSCLC, PS 0-1 and no EGFR/ALK alterations. Pts, stratified by histology and presence of brain metastases, were randomised (1:1) to pembro plus platinum-based chemotherapy (pembro-CT) (paclitaxel for squamous, pemetrexed for non-squamous histology) for four cycles followed by maintenance pembro + pemetrexed, or pembro alone. Primary endpoint was progression free survival (PFS) by blinded central review (BCR) per RECIST v1.1. Key secondary endpoints included investigators assessed PFS, overall survival (OS), objective response rate (ORR), duration of response (DoR) and safety. The study was powered to test the superiority for PFS of pembro-CT over pembro (HR 0.70), with 80% power and a two-sided alpha of 5%.
Results
Between December 2020 and December 2023, 321 pts were randomised across 28 French centres. Median age was 64 years (59-69), 32.4% of pts were female, 2.2% were non-smokers, 23.4% had brain metastases, and 19.6% had squamous histology. At the cut-off date of 7 April 2026, the median follow-up was 38.7 (35.3-41.6) months. By BCR, pembro-CT significantly improved PFS compared with pembro: HR 0.56; 95% CI 0.43-0.74; p <0.001; median 16.1 (11.0-34.1) vs 6.9 (5.5-9.3) months. Median PFS by investigators was 13.7 (9.3-25.4) vs 6.9 (4.7-9.2) months (HR 0.60; 95% CI 0.46-0.78). Median OS was 50.2 (32.6-NR) vs 29.9 (23.4-47.9) months (HR 0.77; 95% CI 0.57-1.05), ORR 77.5% vs 50.3%, DoR 30 (13.1-NR) vs 15.6 (9.8-32.8) months (HR 0.86; 95% CI 0.59-1.24) for pembro-CT and pembro, respectively. Grade ≥ 3 TRAEs occurred in 53.8% and 19.3% of pts in the pembro-CT and pembro arms, respectively.
Conclusions
In first line treatment of advanced PD-L1 ≥50% NSCLC, PERSEE demonstrates a significant improvement of PFS with pembro-CT compared to pembro monotherapy and may help refine treatment selection.
Clinical trial identification [cut off]
[Slide 1]
Tarlatamab plus durvalumab (durva) vs durva as 1L maintenance (1LM) therapy following durva, platinum, and etoposide (1L durva + EP) in extensive-stage small cell lung cancer (ES-SCLC): Primary analysis of the phase 3 DeLLphi-305 trial
Saturday, 24 Oct 2026
17:18 - 17:30
Alicante Auditorium - Hall 6
Save
Note
Session
24 Oct 16:30
Presidential Symposium I
1h45m
[Slide 1]
MADRID 2026 ESMO
Liquid Biopsy oral presentations selection at #ESMO26
[X] @isliquidbiopsy @RobertoBoreaMD [LinkedIn] InternationalSocietyOfLiquidBiopsy
ISLB INTERNATIONAL SOCIETY OF LIQUID BIOPSY
Abstract | Tumor Type | Title | Presenter | Location | Day&Time
2219RO | mCSPC | Utility of ctDNA tumor fraction (TF) as a prognostic biomarker in TALAPRO-3: phase 3 study of talazoparib (TALA) + enzalutamide (ENZA) vs placebo (PBO) + ENZA in patients (pts) with homologous recombination repair (HRR) gene-mutated metastatic castration-sensitive prostate cancer (mCSPC) | Arun Azad (Australia) | Bilbao Auditorium Hall 3 | Fri, 23.10.26 14:02 - 14:07
4734O | Bladder Cancer | ctDNA analysis of the Phase 3 KEYNOTE-B15 trial: neoadjuvant and adjuvant (neoadj-adj) enfortumab vedotin (EV) + pembrolizumab (pembro) for participants (pts) with muscle-invasive bladder cancer (MIBC) who are eligible for cisplatin | Jonathan Chatzkel (USA) | Barcelona Auditorium Hall 9 | Fri, 23.10.26 14:32 - 14:42
540RO | TNBC | Ultrasensitive monitoring of early ctDNA dynamics during neoadjuvant treatment in early-stage triple-negative breast cancer: Pre-interim results from the B-STRONGER-I study | Carlos Barcenas (USA) | Alicante Auditorium Hall 6 | Fri, 23.10.26 16:47 - 16:52
LBA73 | NSCLC | PACE-LUNG: A multicenter, single-arm, phase II clinical trial evaluating the efficacy of additional chemotherapy for patients with EGFRm NSCLC with the continued presence of plasma ctDNA EGFRm at week 3 after start of osimertinib first-line treatment (AIO-TRK-0422/ass) | Martin Sebastian (Germany) | Almeria Auditorium Hall 9 | Sat, 24.10.26 08:30 - 08:35
2719RO | NSCLC | FLAURA2: Analysis of on-treatment plasma EGFRm dynamics and associated clinical outcomes in patients (pts) with EGFRm advanced NSCLC treated with first-line (1L) osimertinib (osi) ± platinum-pemetrexed (plat-pem) | David Planchard (France) | Almeria Auditorium Hall 9 | Sat, 24.10.26 08:35 - 08:40
2636RO | NSCLC | Characterizing resistance mechanisms and predictors of early progression and long-term response to lorlatinib: Circulating tumor DNA (ctDNA) analyses from the CROWN study | Ben Solomon (Australia) | Almeria Auditorium Hall 9 | Sat, 24.10.26 09:05 - 09:10
787RO | mCRC | Circulating tumor DNA (ctDNA)-guided re-treatment (re-tx) with encorafenib and cetuximab (EC) in patients (pts) with chemorefractory BRAFV600E mutated metastatic colorectal cancer (mCRC): The proof-of-concept single arm phase II BRICKET trial by GONO | Marco Maria Germani (Italy) | Alicante Auditorium Hall 6 | Sat, 24.10.26 14:45 - 14:50
LBA36 | Endometrial Cancer | Clinical utility of circulating tumor DNA (ctDNA) for participants with resected, high-risk dMMR endometrial cancer (EC) receiving adjuvant treatment: Results from the ENGOT-en11/GOG-3053/KEYNOTE-B21 study | Lubomir Bodnar (Poland) | Barcelona Auditorium Hall 9 | Sat, 24.10.26 14:55 - 15:05
4244RO | NSCLC | NeoCOAST-2: Association of ctDNA clearance with clinical outcomes in a global platform phase 2 perioperative trial | Tina Cascone (USA) | Leon Auditorium Hall 4 | Sun, 25.10.26 08:30 - 08:35
LBA59 | CSCC | C-POST phase 3 trial of adjuvant (adj) cemiplimab (cemi) vs placebo (pbo) for high-risk cutaneous squamous cell carcinoma (CSCC): Updated overall survival (OS) and outcomes from circulating tumour DNA (ctDNA) analyses | Danny Rischin (Australia) | Granada Auditorium Hall 4 | Sun, 25.10.26 10:42 - 10:47
LBA94 | NSCLC | Error-corrected plasma whole-genome sequencing for personalised and tumour-agnostic minimal residual disease detection in TRACERx | Jonathan Wan (UK) | Cordoba Auditorium Hall 4 | Sun, 25.10.26 14:45 - 14:55
LBA35 | Lung Cancer | Tumor intrinsic and extrinsic origins of circulating genomic and proteomic biomarkers for early detection of lung cancer | Victor Velculescu (USA) | Granada Auditorium Hall 4 | Sun, 25.10.26 14:45 - 14:55
1536RO | HNSCC | ctDNA analysis of the phase 3 KEYNOTE-412 trial: Pembrolizumab (pembro) or placebo (pbo) + concurrent chemoradiotherapy (CRT) for locally advanced head and neck squamous cell carcinoma (LA HNSCC) | Jean-Pascal Machiels (Belgium) | Madrid Auditorium Hall 4 | Sun, 25.10.26 14:50 - 14:55
4236O | CRC | Clinical significance of ultrasensitive ctDNA detection for molecular residual disease assessment in resectable colorectal cancer in MONSTAR-SCREEN-3 | Yuichiro Tsukada (Japan) | Cordoba Auditorium Hall 4 | Sun, 25.10.26 14:55 - 15:05
LBA62 | NSCLC | ctDNA clearance (CL) during neoadjuvant treatment (neoadj Tx) and its association with outcomes in patients (pts) with resectable/borderline resectable stage IIB-IIIB NSCLC from MDT-BRIDGE | Jonathan Spicer (Canada) | Burgos Auditorium Hall 3 | Mon, 26.10.26 10:35 - 10:40
1769RO | Breast Cancer | CTC characterization with the DETECT CTC score predicts therapy response in triple-positive aBC: Translational results of the phase III DETECT V study | Kerstin Pfister (Germany) | Alicante Auditorium Hall 6 | Mon, 26.10.26 11:17 - 11:22
1151RO | Multi-cancer | Efficiency and safety of cancer signal origin (CSO)-guided diagnostic workups following multi-cancer early detection (MCED) testing: Results from PATHFINDER 2 (PF2) | Dax Kurbegov (USA) | Salamanca Auditorium Hall 10 | Mon, 26.10.26 15:17 - 15:22
[Slide 2]
[Photo: two women talking in an office]
LATE-BREAKING ORAL PRESENTATION
First global Phase 2 clinical data
from ROSETTA Lung-107 evaluating an investigational PD-L1xVEGF-A bispecific immunomodulator plus chemotherapy in metastatic non-small cell lung cancer following prior immunotherapy
BIONTECH
[Slide 1]
Rapid Oral session
2618RO - Analysis of the phase 2 part of IFCT-2103 DIAL phase 2-3 randomized trial, comparing continuation pembrolizumab (± pemetrexed) up to 2 years versus observation (± pemetrexed), in patients with metastatic non-small cell lung cancer (mNSCLC) with disease control (DC) at 6 months
Speakers Anne Claire Toffart (La Tronche, France)
Lecture Time 09:14 - 09:19
Abstract
Background
Optimal duration of 1L immunotherapy (io) in mNSCLC patients, with DC remains debatable. We aimed to study de-escalation by stopping pembrolizumab in patients with 6-months DC after chemo-io induction, as compared to 24 months.
Methods
This randomized open-label trial included treatment-naïve 18-75 yrs. mNSCLC patients (pts), ECOG PS 0-1, w/o actionable tumor molecular alteration, stratified according to PS, histology (SCC. vs. non-SCC), PD-L1 tumor level, sex and quality of response (stable vs. objective response). They received 4 cycles of 1L platinum-based chemo doublet+pembro, either paclitaxel-carboplatin, followed by maintenance pembro, for SCC patients or pemetrexed-platinum, followed by pembro + pemetrexed continuation for non-SCC patients. At 6 months, patients with DC were randomized 1:1 either to pembrolizumab (± pemetrexed in non-SCC patients) continuation until 2 years, or to observation (± pemetrexed). Primary outcome was 18-mo. overall survival (OS) from inclusion. Secondary outcomes included safety from randomization.
Results
From May 2022 to March 2024, 197 patients (68.0% male, 63.3y median age, 66% stage IVB, 70.6% adenocarcinoma), were accrued. 93 (47.2%) patients were randomized: to the continuation control arm (n=47) or the de-escalation arm (n=46). In Dec. 2025, the phase II analysis involved 84 first eligible patients (42 in each arm). Both arms were well balanced according to clinical and biological characteristics. Median follow-up was 27.9 months 95%CI [25.0 - 31.1]. At 18 months, 83.3%, 95%CI [72.1 - 94.6] were alive in the continuation arm vs. 88.1%, 95%CI [78.3 - 97.9] in the de-escalation arm. In the 93 randomized patients, grade 3-4 rates from randomization were 14.9% and 6.5%, while all-grade irAEs were 85.1% and 47.8%, in the continuation arms and the de-escalation arms, respectively.
Conclusions
In patients with 6-mo DC, similar rates of 18-mo OS were observed in both arms, while leading to lower frequency of irAEs in the de-escalation arm. Accrual in the trial phase 3 part is continuing.
[Slide 1]
2614O - Pembrolizumab with or without platinum-based chemotherapy as first-line treatment in advanced NSCLC with PD-L1 ≥50%: PERSEE phase 3 trial (GFPC 01-2020)
Speakers Chantal Decroisette (Lyon, France, CEDEX)
Lecture Time 10:25 - 10:35
Abstract
Background
Pembrolizumab (pembro) monotherapy or in combination with chemotherapy are standard first-line options in advanced PD-L1 ≥50% NSCLC. We evaluated whether adding platinum-based chemotherapy improves outcomes versus pembro monotherapy.
Methods
This multicentre open-label phase 3 trial enrolled patients (pts) with untreated stage IV or not amenable to radiotherapy stage III PD-L1 ≥50% NSCLC, PS 0-1 and no EGFR/ALK alterations. Pts, stratified by histology and presence of brain metastases, were randomised (1:1) to pembro plus platinum-based chemotherapy (pembro-CT) (paclitaxel for squamous, pemetrexed for non-squamous histology) for four cycles followed by maintenance pembro + pemetrexed, or pembro alone. Primary endpoint was progression free survival (PFS) by blinded central review (BCR) per RECIST v1.1. Key secondary endpoints included investigators assessed PFS, overall survival (OS), objective response rate (ORR), duration of response (DoR) and safety. The study was powered to test the superiority for PFS of pembro-CT over pembro (HR 0.70), with 80% power and a two-sided alpha of 5%.
Results
Between December 2020 and December 2023, 321 pts were randomised across 28 French centres. Median age was 64 years (59-69), 32.4% of pts were female, 2.2% were non-smokers, 23.4% had brain metastases, and 19.6% had squamous histology. At the cut-off date of 7 April 2026, the median follow-up was 38.7 (35.3-41.6) months. By BCR, pembro-CT significantly improved PFS compared with pembro: HR 0.56; 95% CI 0.43-0.74; p <0.001; median 16.1 (11.0-34.1) vs 6.9 (5.5-9.3) months. Median PFS by investigators was 13.7 (9.3-25.4) vs 6.9 (4.7-9.2) months (HR 0.60; 95% CI 0.46-0.78). Median OS was 50.2 (32.6-NR) vs 29.9 (23.4-47.9) months (HR 0.77; 95% CI 0.57-1.05), ORR 77.5% vs 50.3%, DoR 30 (13.1-NR) vs 15.6 (9.8-32.8) months (HR 0.86; 95% CI 0.59-1.24) for pembro-CT and pembro, respectively. Grade ≥ 3 TRAEs occurred in 53.8% and 19.3% of pts in the pembro-CT and pembro arms, respectively.
Conclusions
In first line treatment of advanced PD-L1 ≥50% NSCLC, PERSEE demonstrates a significant improvement of PFS with pembro-CT compared to pembro monotherapy and may help refine treatment selection.
[Slide 1]
MADRID 2026 ESMO congress
MADRID SPAIN 23-27 OCTOBER 2026
Neuroendocrine SELECTED ABSTRACTS
Proffered paper: NETs and endocrine tumours | 26 October 2026 · 10:15-11:45
LBA57 - Opamtistomig (LBL-024) monotherapy in advanced extra-pulmonary neuroendocrine carcinoma (EP-NEC) after ≥2 prior lines of therapies: results from a pivotal, registrational phase IIb study of a novel PD-L1×4-1BB bispecific antibody
2392O - Opamtistomig (LBL-024), a novel PD-L1×4-1BB bispecific antibody, combined with chemotherapy as first-line treatment for advanced extrapulmonary neuroendocrine carcinoma: Results from a phase Ib/II trial
2393O - First results from a phase 2 trial of second-line pumitamig (PD-L1 × VEGF-A bsAb) plus chemotherapy in unresectable neuroendocrine neoplasms
4208O - Updated results of randomized phase 3 study of selpercatinib vs cabozantinib or vandetanib (C/V) in advanced, kinase inhibitor-naïve, RET-mutant medullary thyroid cancer (MTC)
4209O - Primary results from the SETHY trial: Sacituzumab govitecan (SG) in advanced/metastatic differentiated thyroid carcinoma (DTC) and anaplastic thyroid carcinoma (ATC)
Rapid oral: NETs and endocrine tumours | 23 October 2026 · 16:15-17:45
2394RO - Latest efficacy and safety analysis of surufatinib combined with EP regimen and serplulimab as first-line treatment for extrapulmonary neuroendocrine carcinoma
2395RO - Concomitant somatostatin analog use in second-line therapy of gastroenteropancreatic neuroendocrine tumors: Survival results from the retrospective RetroSAUNA study
2396RO - Cohort level safety and efficacy results for [212Pb]VMT-a-NET in advanced somatostatin receptor subtype 2 (SSTR2+)-expressing neuroendocrine tumors (NETs): Cohorts 1-3
2397RO - Subgroup analysis of the ongoing phase Ib DAREON-7 study: Outcomes with first-line (1L) obrixtamig plus standard of care (SoC) in neuroendocrine carcinomas (NECs) by DLL3 expression status
1202RO - Pembrolizumab plus lenvatinib in advanced adrenocortical carcinoma after failure of mitotane- and platinum-based chemotherapy: Phase II ACCOMPLISH trial (KCSG GU21-14)
4210RO - I-124 PET-guided risk-adapted versus broad adjuvant radioiodine therapy in differentiated thyroid carcinoma: Results from the randomized CLERAD-PROBE trial
4211RO - The efficacy and safety of becotatug vedotin and pucotenlimab in EGFR-positive unresectable anaplastic/poorly differentiated thyroid cancer: Preliminary results from a phase II clinical trial
4212RO - Molecular determinants of cabozantinib efficacy in advanced radioiodine-refractory (RAIR) differentiated thyroid cancer (DTC): The GETNE-CABOTHYROID trial
4213RO - BRAF V600E-mutant anaplastic thyroid carcinoma: Real-world outcomes of BRAF/MEK inhibition - A multicentre retrospective study from the French ENDOCAN-TUTHYREF network
Nieves Martínez Lago · @DraMartinezLago | #ESMO26
[Slide 1]
KRASCENDO 1
Divarasib at ESMO 2026
Head-to-head phase III • KRAS G12C-mutated NSCLC
Conference preview • Full numerical data pending
[Lung / KRAS icon] A direct randomized comparison of next-generation divarasib versus first-generation KRAS G12C inhibitors in previously treated advanced NSCLC.
STUDY DESIGN
• Population: previously treated advanced KRAS G12C-mutated NSCLC
• Experimental arm: divarasib
• Comparator: sotorasib or adagrasib
• Trial: randomized phase III (KRASCENDO 1)
WHAT ROCHE HAS REPORTED
• Progression-free survival: clinically meaningful, statistically significant improvement
• Overall survival: statistical significance achieved at interim analysis
• Safety: consistent with prior data; no new safety signals reported
WHAT IS STILL NEEDED
• Effect sizes and hazard ratios
• Absolute PFS and OS outcomes
• Detailed toxicity and discontinuation data
• Subgroup analyses and follow-up context
ESMO 2026
Madrid, Spain
Late-breaking abstract: LBA5
Presentation date: October 25, 2026
WHY IT MATTERS
If the full results are convincing, divarasib could reshape treatment selection after progression in KRAS G12C-positive NSCLC. Until the full presentation, this remains a promising company-reported readout rather than a fully appraised practice-changing result.
Sources: Roche press release, July 2, 2026; Roche ESMO 2026 update, October 19, 2026.
[Tropical/Madrid skyline illustration]
[Slide 1]
SAFFRON | THE MET ESCAPE
Can Dual Blockade Beat Chemotherapy?
MV Onco
[Diagram: lung tumour between EGFR and MET receptor schematics]
EGFR-mutated NSCLC → Osimertinib → EGFR [blocked] → EGFR signalling blocked ✓
Acquired MET-mediated resistance → MET amplification / overexpression → MET bypass signalling → MET → Tumour growth continues
Osimertinib + Savolitinib → OSIMERTINIB + SAVOLITINIB → DUAL EGFR + MET INHIBITION
① HOW COMMON IS MET-HIGH?
Approximately 34%
High MET overexpression and/or amplification after third-generation EGFR-TKI progression.
② HOW IS MET-HIGH DETECTED?
• IHC: MET 3+ in ≥90% tumour cells
OR
• FISH: MET gene copy number ≥10
MET amplification ≠ MET exon 14 skipping.
③ SAVANNAH | PHASE II
Osimertinib + savolitinib
• ORR 56%
• Median PFS 7.4 months
④ SAFFRON | PHASE III
• 338 patients | Randomized
• Osimertinib + savolitinib
VS
• Platinum + pemetrexed
• PFS and OS superiority reported. Sponsor-reported topline findings.
⑤ ESMO 2026
• LBA6 | 25 OCTOBER
• Presidential Symposium II
• Prof. Shun Lu
HOW LARGE IS THE SURVIVAL BENEFIT?
Detailed numerical results awaited.
FINAL TAKE-HOME
SAVANNAH FOUND THE SIGNAL.
SAFFRON REPORTED THE SURVIVAL BENEFIT.
ESMO WILL REVEAL THE MAGNITUDE.
[Slide 2]
SAFFRON | PHASE III
Why MET? Who Qualifies? How Was the Trial Designed?
ESMO 2026 • LBA6
MV Onco
01 - WHY DOES OSIMERTINIB FAIL?
EGFR-mutated advanced NSCLC
↓
Osimertinib blocks EGFR signalling
↓
Tumour activates MET bypass signalling
↓
MET-driven acquired resistance
Approximately 34% may develop high MET overexpression and/or amplification after third-generation EGFR-TKI progression. Prevalence depends on biomarker thresholds.
02 - WHAT EXACTLY IS MET-HIGH?
MET AMPLIFICATION
• Increased MET gene copy number.
• Detected by FISH.
MET OVEREXPRESSION
• Increased MET protein expression.
• Detected by IHC.
SAFFRON MET-HIGH CRITERIA
• IHC: 3+ staining in ≥90% of tumour cells
OR
• FISH: MET gene copy number ≥10
Either criterion can qualify.
MET exon 14 skipping ≠ MET amplification. MET exon 14 skipping was NOT the selection biomarker.
03 - WHO ENTERED SAFFRON?
• 338 patients | Global Phase III
• Advanced EGFR-mutated NSCLC
• Common sensitizing EGFR mutations: Exon 19 deletion / L858R
• Progression after first- or second-line osimertinib
• High MET overexpression and/or amplification
↓
RANDOMIZATION 1:1
04 - WHAT WERE THE TWO ARMS?
ARM A - DUAL TARGETED THERAPY: Osimertinib 80 mg OD + Savolitinib 300 mg BD
VERSUS
ARM B - CHEMOTHERAPY: Platinum + pemetrexed
05 - WHAT WAS THE TRIAL TESTING?
• Primary endpoint: Progression-free survival (PFS)
• Key secondary endpoint: Overall survival (OS)
• Additional efficacy and safety assessments.
THE CENTRAL QUESTION
Can blocking EGFR + MET outperform chemotherapy after osimertinib resistance?
BOTTOM TAKE-HOME
EGFR remains the driver.
MET becomes the escape route.
SAFFRON targets both.
PART 2 → SAVANNAH SIGNAL TO SAFFRON SURVIVAL RESULTS
[Slide 3]
SAFFRON | PHASE III
From SAVANNAH Signal to Survival Benefit
ESMO 2026 • LBA6
MV Onco
01 - WHAT DID SAVANNAH SHOW?
Phase II | MET-high EGFR-mutated NSCLC
After progression on first-line osimertinib.
Osimertinib + savolitinib
Primary efficacy population:
• ORR 56%
• Median PFS 7.4 months
High MET defined by:
• IHC 3+ in ≥90% tumour cells
OR
• FISH MET copy number ≥10
The biological signal was encouraging.
02 - DID RANDOMIZED PHASE II DATA SUPPORT IT?
SAVANNAH randomized subset | n = 73
• Savolitinib + osimertinib (n = 48)
vs
• Savolitinib + placebo (n = 25)
ORR: 58% vs 16%
Median PFS: 8.3 vs 3.6 months
Blinded independent central review.
Exploratory randomized evidence supporting continued EGFR blockade alongside MET inhibition.
03 - WHAT HAS SAFFRON REPORTED?
Global Phase III | 338 patients
• Osimertinib + savolitinib
vs
• Platinum-pemetrexed
August 2026 sponsor announcement:
✔ Statistically significant PFS improvement
✔ Statistically significant OS improvement
✔ Clinically meaningful benefit reported
Important: Sponsor-reported topline results. Exact survival medians and HRs awaited.
04 - WHAT MUST ESMO REVEAL?
Five questions that matter
1. How much longer is median PFS?
2. What is the PFS hazard ratio?
3. How large is the OS benefit?
4. What are the grade ≥3 toxicities?
5. Does benefit differ by MET IHC vs FISH status?
Additional clinical question:
Will dual EGFR/MET blockade become a preferred option after osimertinib progression?
05 - WATCH AT ESMO 2026
LBA6 | PRESIDENTIAL SYMPOSIUM II
• 25 October 2026
• 16:30-18:15 CEST
• Madrid, Spain
• Presenter: Prof. Shun Lu
• SAFFRON Phase III primary results.
FINAL TAKE-HOME
SAVANNAH identified the signal.
SAFFRON reported a survival advantage.
ESMO will tell us how much it matters.
Positive topline ≠ complete clinical evidence.
[Slide 1]
Rapid Oral session
789RO - TRIDENTE: A phase II study of rechallenge with encorafenib (ENCO), binimetinib (BINI), and cetuximab (CET) in BRAF V600E-mutant metastatic colorectal cancer (mCRC)
Speakers Daisuke Kotani (Kashiwa, Japan)
Lecture Time 14:55 - 15:00
Abstract
Background
The BEACON CRC and BREAKWATER trials established ENCO + CET-based therapy as a standard-of-care for BRAF V600-mutant mCRC. Based on the efficacy of BRAF/MEK inhibitor rechallenge in BRAF V600-mutant melanoma, TRIDENTE trial evaluated the clinical utility of rechallenge with ENCO + BINI + CET in patients with BRAF V600E mutant mCRC who previously responded and then progressed on ENCO + CET-based therapy.
Methods
TRIDENTE (jRCTs031210511) is a multicenter, single-arm, phase II study. Key eligibility criteria included: RAS WT/BRAF V600E-mutant mCRC; ECOG PS 0-1; refractory or intolerant to fluoropyrimidine-based regimens and anti-PD-1 therapy (if MSI-H); and history of prior ENCO + CET-based therapy with at least a partial response (PR) followed by disease progression. A ENCO-free interval of ≥ 4 months after the last ENCO dose was required. The primary endpoint was investigator-assessed objective response rate (ORR). With a threshold ORR of 3% and an expected ORR of 20%, 21 patients were required (one-sided alpha = 0.05, power 80%). In exploratory analysis using circulating tumor DNA (ctDNA), resistance genomic alterations were defined as mutations in KRAS, NRAS, MAP2K1, EGFR or amplifications in MET, BRAF, KRAS.
Results
Between Jan 2022 and Apr 2025, 21 patients were enrolled across 12 institutions. Median age was 58 years; 17 patients (81%) had ECOG PS 0. The median number of prior lines was 3. Previous ENCO + CET-based regimens were ENCO + CET (62%) and ENCO + CET + BINI (38%). The primary endpoint was met; ORR was 19.0% (90%CI, 6.8-38.4%), including 4 PRs. Stable disease was observed in 12 patients, and tumor shrinkage occurred in 11 patients (52.4%). Median PFS and OS were 2.8 and 9.6 months, respectively. No unexpected adverse events were observed. Among 20 patients with baseline ctDNA results, the ORR was 25.0% (3/12) in those without genomic alterations versus 12.5% (1/8) in those with alterations.
Conclusions
Rechallenge with ENCO + BINI + CET demonstrated clinical activity and manageable safety profile in patients with BRAF V600E-mutant mCRC who were initially sensitive but subsequently progressed on ENCO + CET-based therapy.
[Slide 1]
[Roche logo]
ESMO 2026 Industry Satellite Symposium
Advancing the Frontiers of Lung Cancer Care
Monday, 26 October 2026, 13:00–14:30 CET
Oviedo Auditorium, Hall 5, IFEMA Madrid, Madrid, Spain
Meeting Chair: Faculty:
[headshots]
Stephen V Liu — USA
Ferdinandos Skoulidis — USA
Terri Conneran — USA
Margarita Majem — Spain
Agenda:
Welcome and Introduction: the Evolving Map of Lung Cancer
Stephen V Liu
Charting the Path Forward in KRAS G12C Lung Cancer
Ferdinandos Skoulidis
Walking the Path: a Patient Perspective of Living with KRAS-mutated Lung Cancer
Terri Conneran
Mapping the Role of Immunotherapy in Frail & Elderly Patients
Margarita Majem
Shifting Paradigms in ES-SCLC and the Next Wave of ADCs in Lung Cancer
Stephen V Liu and Margarita Majem
Panel Discussion, Q&A and Meeting Close
Stephen V Liu, Ferdinandos Skoulidis and Margarita Majem
[illustration: purple lung-tree with two clinicians]
This scientific meeting is sponsored by F. Hoffmann-La Roche Ltd.
It is intended for healthcare professionals outside the United States of America (US).
Date of preparation: September 2026
M-XX-00024512
[Slide 1]
ESMO EUROPEAN SOCIETY FOR MEDICAL ONCOLOGY | ESMO 2026 MADRID, SPAIN 23 – 27 OCTOBER 2026
RAPID ORAL SESSION
Analysis of the phase 2 part of IFCT-2103 DIAL phase 2-3 randomized trial, comparing continuation pembrolizumab (± pemetrexed) up to 2 years versus observation (± pemetrexed), in patients with metastatic NSCLC with disease control (DC) at 6 months
Anne Claire Toffart (Grenoble, France)
Sunday, 26.10.2026 (09:14 - 09:19) | Rapid oral session: 09:14 - 09:19
POSTER
Encorafenib plus binimetinib in patients (pts) with BRAFV600E-mutant advanced non-small cell lung cancer: updated efficacy and safety results from the IFCT-1904 ENCO-BRAF phase 2 trial
Charles Ricordel (Rennes, France)
Monday, 26.10.2026 (12:00 - 12:45)
POSTER
Quality assurance of delineation and dosimetry of the RTEP7-IFCT-1402 multicentre randomised phase II trial
Laura Haas (Rouen, France)
Monday, 26.10.2026 (12:00 - 12:45)
POSTER (TRIAL IN PROGRESS)
IFCT-2404 COMET: a phase III trial of tepotinib versus investigator's choice treatment in patients with pre-treated MET exon 14 skipping NSCLC
Alexis Cortot (Lille, France)
Monday, 26.10.2026 (12:00 - 12:45)
[Slide 1]
2719RO - FLAURA2: Analysis of on-treatment plasma EGFRm dynamics and associated clinical outcomes in patients (pts) with EGFRm advanced NSCLC treated with first-line (1L) osimertinib (osi) ± platinum–pemetrexed (plat–pem)
Speakers David Planchard (Villejuif, France)
Lecture Time 08:35 - 08:40
Abstract
Background
In the phase III FLAURA2 trial (NCT04035486), 1L osi + plat–pem led to significantly improved PFS and OS vs osi mono in pts with EGFRm advanced NSCLC. In our previous analysis, EGFRm clearance at Week (Wk) 3 and 6 was prognostic, but not predictive of a PFS benefit with osi + plat–pem vs osi mono. We report exploratory analyses of PFS and OS by plasma EGFRm clearance at Wks 1, 2, 3 and 6 to understand if EGFRm clearance rates differ between treatment arms, and to evaluate the use of early EGFRm circulating tumour DNA (ctDNA) dynamics for identifying pts most likely to benefit from osi + plat–pem.
Methods
Pts with untreated EGFRm (Ex19del or L858R) advanced NSCLC were randomised 1:1 to receive either osi (80 mg QD) + plat–pem (Q3W; 4 cycles) followed by osi (QD) + pem (Q3W), or osi (QD) mono, until PD or discontinuation. BL and Wks 1, 2, 3 and 6 plasma EGFRm were analysed by ddPCR (Biodesix). Clearance was defined as undetected EGFRm ctDNA post-treatment start, where it was detected at BL. Association between clearance and PFS (by investigator assessment; DCO: 03 April 2023) and OS (DCO: 12 June 2025) was examined.
Results
Among pts with evaluable BL and Wk 1, 2, 3 and 6 plasma ddPCR results, the rate of clearance was 38%, 64%, 81%, and 88%, in the osi + plat–pem arm, respectively, and 42%, 64%, 71%, and 89%, in the osi mono arm, respectively. A consistent PFS and OS benefit was seen with osi + plat–pem vs osi mono, irrespective of clearance status (Table).
Conclusions
On-treatment EGFRm clearance was prognostic, but not predictive of PFS or OS benefit with osi + plat–pem at all timepoints; efficacy of osi + plat–pem was superior to osi mono regardless of clearance status. Clearance rates were comparable across treatment arms and timepoints. Studies using ultra-sensitive multi-marker ctDNA assays are planned to investigate early ctDNA dynamics as a predictive biomarker. Table: 2719RO
[columns: Timepoint, Week | EGFRm clearance (Y/N) | Osi + plat–pem, n (%) | Osi mono, n (%) | Osi + plat–pem vs osi mono PFS HR (95% CI) | Osi + plat–pem vs osi mono OS HR (95% CI)]
1 | Y | 39 (38) | 55 (42) | 0.56 (0.31, 1.03) | 0.79 (0.45, 1.37)
| N | 65 (63) | 76 (58) | 0.52 (0.34, 0.81) | 0.69 (0.47, 1.02)
2 | Y | 72 (64) | 85 (64) | 0.52 (0.34, 0.81) | 0.69 (0.46, 1.03)
| N | 41 (36) | 48 (36) | 0.56 (0.33, 0.96) | 0.78 (0.48, 1.26)
3 | Y | 88 (81) | 100 (71) | 0.50 (0.34, 0.75) | 0.84 (0.58, 1.21)
| N | 21 (19) | 40 (29) | 0.59 (0.30, 1.16) | 0.65 (0.36, 1.20)
6 | Y | 92 (88) | 122 (89) | 0.52 (0.36, 0.76) | 0.73 (0.52, 1.04)
| N | 13 (12) | 15 (11) | 0.40 (0.16, 0.97) | 0.50 (0.22, 1.13)
CI, confidence interval; HR, hazard ratio; N, no; Y, yes.
[Slide 1]
DeLLphi-305
CAN WE DELAY THE NEXT RELAPSE?
Final results awaited at ESMO 2026
MV Onco
WHO ENTERED?
EXTENSIVE-STAGE SCLC
[Illustration: patient receiving infusion]
After 3-4 cycles: Platinum + etoposide + durvalumab
Disease controlled • ECOG 0-1
↓
563 patients → Randomized 1:1
TARLATAMAB + DURVALUMAB | DURVALUMAB ALONE
[Mechanism diagram: T cell (CD3) - Tarlatamab - SCLC cell (DLL3, PD-L1) - Durvalumab] Recruit T cells + release the brake
[Mechanism diagram: SCLC cell (PD-L1) - Durvalumab] Release the PD-L1 brake
01 THE QUESTION
Does adding tarlatamab during maintenance help patients live longer?
02 WHAT IS ANNOUNCED?
Sponsor reports improved: Overall survival • PFS • Response
03 WHAT DO WE STILL NEED?
• Exact benefit
• CRS / neurological toxicity
• Quality of life
• Treatment after progression
Bring tarlatamab in before relapse?
Positive topline announcement. Full numerical results awaited at ESMO 2026.
[Slide 1]
Results
Between December 2020 and December 2023,
321 pts were randomised across 28 French
centres. Median age was 64 years (59-69),
32.4% of pts were female, 2.2% were non-
smokers, 23.4% had brain metastases, and
19.6% had squamous histology. At the cut-off
date of 7 April 2026, the median follow-up was
38.7 (35.3-41.6) months. By BCR, pembro-CT
significantly improved PFS compared with
pembro: HR 0.56; 95% CI 0.43-0.74; p <0.001;
median 16.1 (11.0-34.1) vs 6.9 (5.5-9.3) months.
Median PFS by investigators was 13.7 (9.3-25.4)
vs 6.9 (4.7-9.2) months (HR 0.60; 95% CI 0.46-
0.78). Median OS was 50.2 (32.6-NR) vs 29.9
(23.4-47.9) months (HR 0.77; 95% CI 0.57-
1.05), ORR 77.5% vs 50.3%, DoR 30 (13.1-NR)
vs 15.6 (9.8-32.8) months (HR 0.86; 95% CI
0.59-1.24) for pembro-CT and pembro,
respectively. Grade ≥ 3 TRAEs occurred in
53.8% and 19.3% of pts in the pembro-CT and
pembro arms, respectively.
[Slide 1]
Primary results of SARON: a randomised-controlled trial of consolidation radiotherapy for synchronous oligometastatic non-small cell lung cancer
Sunday, 25 Oct 2026
10:15 - 10:25
Alicante Auditorium - Hall 6
[Slide 1]
2700RO - Improving prevention of moderate to severe dermatologic adverse events in EGFR-mutant advanced NSCLC treated with first-line (1L) subcutaneous (SC) amivantamab + lazertinib: First results from a new COCOON cohort
Speakers Byoung Chul Cho (Seoul, Republic of Korea)
Lecture Time 08:40 - 08:45
Abstract
Background
Dermatologic AEs are associated with EGFR-targeted therapies such as amivantamab (ami) + lazertinib (laz). EGFR inhibitor-associated secondary zinc deficiency is linked to increased risk of severe skin AEs. In the phase 2 COCOON study (NCT06120140), enhanced dermatologic management (DM; tetracycline for 12 wks, ceramide-based moisturizer, topical clindamycin, chlorhexidine) led to significantly reduced grade ≥2 dermatologic AEs of interest (DAEIs) by Wk 12 vs standard of care DM (42% vs 75%; P<0.0001) in pts receiving 1L intravenous (IV) ami + laz; scalp DAEIs were also meaningfully reduced (10% vs 26%; P=0.005). With COCOON DM, dose interruptions, reductions and discontinuations due to AEs were 55%, 27% and 12% (Cho JTO 2025). SC ami has shown shorter administration time (<5 min) and higher pt convenience vs IV (Leighl JCO 2024). Here are first results from a new COCOON cohort using an optimized DM regimen with zinc supplementation in pts receiving SC ami + laz.
Methods
70 pts receiving SC ami on standard Q4W dosing + oral laz were enrolled. Pts also received optimized COCOON DM (oral tetracycline for 24 wks; ceramide-based moisturizer + oral zinc gluconate throughout the study; chlorhexidine for nails and clindamycin for scalp were omitted). Primary endpoint was incidence of grade ≥2 DAEIs by Wk 12.
Results
As of 24-Apr-26, 70 pts (median age, 63 y; 66% female) received ≥1 dose of SC ami + laz plus optimized COCOON DM (median follow-up, 3.8 mo). Among 65 pts with ≥12 wks of follow-up, overall incidence of grade ≥2 DAEIs by Wk 12 was 34%; 1 pt had grade 3 DAEIs; no grade 4–5 DAEIs were reported. Incidence of grade ≥2 DAEIs by Wk 12 was 5% for scalp and 18% for paronychia. Few pts had dose reductions (11%) or discontinuations (3%) due to AEs; 29% had interruptions. Updated results will be presented at the meeting.
Conclusions
These results suggest that SC ami + laz with an optimized COCOON DM regimen led to numerical reductions in grade ≥2 DAEIs vs IV ami + laz with standard COCOON DM. Few AE-related dose modifications/discontinuations were observed, supporting the benefit of proactive DM in pts receiving SC ami + laz.
[Slide 1]
2511O - Final analysis of adjuvant pembrolizumab (pembro) in resected early-stage non–small-cell lung cancer (NSCLC): Phase 3 PEARLS/KEYNOTE-091 study
Speakers Mary E. O'Brien (London, United Kingdom)
Lecture Time 15:43 - 15:53
Abstract
Background
At the second interim analysis (IA2) of PEARLS/KEYNOTE-091 of participants (pts) with resected, stage IB–IIIA NSCLC, adjuvant pembro improved DFS vs placebo in the ITT population (HR, 0.76; 95% CI, 0.63–0.91; P = 0.0014) and in the subgroup that received chemotherapy (chemo; HR, 0.73; 95% CI, 0.60–0.89). We report results, including OS, from the final analysis (FA) of PEARLS/KEYNOTE-091 (NCT02504372).
Methods
Eligible pts aged ≥18 y with completely resected, pathologically confirmed stage IB (T ≥4 cm), II, or IIIA NSCLC per AJCC v7 received ≤4 cycles of adjuvant chemo per local guidelines and were randomized 1:1 to 18 cycles (~1 y) of adjuvant pembro 200 mg or placebo Q3W. Primary endpoints were DFS per RECIST v1.1 by investigator assessment in the ITT and PD-L1 TPS ≥50% populations. Secondary endpoints included OS, lung cancer–specific survival (LCSS), and safety.
Results
1177 pts were included in the ITT population (pembro, n = 590; placebo, n = 587). Median follow-up from randomization to data cutoff (Jan 21, 2026) was 87.7 (range, 68.6–120.1) mo. 6-y OS (95% CI) was 68.5% (64.5%–72.1%) for pembro and 66.4% (62.4%–70.1%) for placebo (HR, 0.98; 95% CI, 0.81–1.18; P = 0.41826) in the ITT population and 68.9% (64.6%–72.8%) and 65.4% (61.0%–69.4%), respectively, in pts who received chemo (HR, 0.91; 95% CI, 0.74–1.12). DFS and LCSS results are in the table. Grade ≥3 AEs occurred in 197/580 pts (34.0%) with pembro and 149/581 (25.6%) with placebo. Grade ≥3 immune-mediated AEs and infusion reactions occurred in 46 (7.9%) and 11 pts (1.9%), respectively.
Conclusions
At the final analysis of PEARLS/KEYNOTE-091, adjuvant pembrolizumab continued to demonstrate a consistent DFS benefit versus placebo in resected early-stage NSCLC, with a favorable trend in LCSS. Safety remained manageable. While OS did not show a statistically significant improvement, it was a secondary endpoint and the study was not powered to detect an OS benefit.
Table: 2511O
[columns: ITT Population — Pembro (n = 590) | Placebo (n = 587) ; Pts Who Received Chemo — Pembro (n = 506) | Placebo (n = 504)]
DFS
Median (95% CI), mo | 58.7 (47.0–70.4) | 43.3 (35.0–55.6) | 58.7 (47.0–70.5) | 39.1 (31.3–51.7)
6-y DFS (95% CI), % | 44.0 (39.7–48.2) | 39.2 (35.0–43.2) | 43.6 (38.9–48.1) | 38.1 (33.7–42.5)
HR (95% CI) | 0.85 (0.73–0.98) [ITT] | 0.80 (0.68–0.94) [received chemo]
LCSS
Median (95% CI), mo | NR (NR–NR) | NR (NR–NR) | NR (NR–NR) | NR (NR–NR)
6-y LCSS (95% CI), % | 81.3 (77.7–84.4) | 76.9 (73.1–80.2) | 81.6 (77.7–84.9) | 75.0 (70.8–78.7)
HR (95% CI) | 0.81 (0.63–1.03) [ITT] | 0.69 (0.53–0.91) [received chemo]
NR, not reached.
[Slide 1]
3809O - Randomized trial of serplulimab or atezolizumab plus chemotherapy in USA patients with extensive-stage small cell lung cancer (ASTRIDE)
Speakers David R. Gandara (Sacramento, United States of America)
Lecture Time 14:55 - 15:05
Abstract
Background
Serplulimab (serplu), a programmed death 1 inhibitor, demonstrated significant survival benefits in the international, randomized phase 3 ASTRUM-005 study. ASTRIDE aims to evaluate the efficacy and safety of serplu vs atezolizumab (atezo), in USA patients (pts) with extensive-stage small cell lung cancer (ES-SCLC), per FDA request.
Methods
Pts with histologically or cytologically confirmed ES-SCLC and ≤1 prior cycle of chemotherapy (chemo) for ES-SCLC were randomized 1:1 to receive up to 4 cycles of serplu (300 mg) or atezo, each in combination with carboplatin and etoposide, followed by maintenance serplu or atezo, respectively. Allowing 1 prior cycle of chemo reflected real-world practice. Treatments were administered intravenously every 3 weeks. The primary endpoint was overall survival (OS). As a bridging study, the statistical design was descriptive only.
Results
From July 2022 to October 2025, 201 USA pts were enrolled at 63 centers and randomized to the serplu (n=101) or atezo (n=100) group. As of February 18, 2026, median follow-up was 14.1 months (mo, 95% CI, 11.4–18.5). The proportion of pts with liver metastasis was higher in the serplu group (49.5% vs 40.0%). Other baseline characteristics were balanced. In the ITT, median OS was 12.4 mo with serplu and 10.2 mo with atezo; 24-mo OS rates were 32.2% and 17.6%, respectively. Detailed efficacy results are shown below (Table). Outcomes also appeared more favorable with serplu in pts without prior 1-cycle chemo (Table). The incidence and severity of adverse events were comparable between groups, with no new safety signals identified. Table: 3809O
Summary of efficacy
[columns: ITT — Serplulimab (n=101) | Atezolizumab (n=100) ; Without 1-cycle chemo — Serplulimab (n=82) | Atezolizumab (n=76)]
IRRC assessed ORR, % | 64.4 | 67.0 | 68.3 | 64.5
IRRC assessed DOR, months | 4.2 | 4.0 | 4.4 | 4.1
IRRC assessed median PFS, months | 5.4 | 4.9 | 5.5 | 5.2
HR (95% CI) | 0.95 (0.67, 1.35) [ITT] | 0.97 (0.65, 1.45) [without 1-cycle chemo]
Median OS, months | 12.4 | 10.2 | 13.4 | 10.8
HR (95% CI) | 0.82 (0.56, 1.20) [ITT] | 0.77 (0.50, 1.17) [without 1-cycle chemo]
OS rate at 24 months, % | 32.2 | 17.6 | 34.8 | 17.2
Median OS in pts without liver metastasis, months | 18.9 | 13.2 | 18.9 | 13.2
HR (95% CI) | 0.60 (0.33, 1.09) [ITT] | 0.63 (0.33, 1.19) [without 1-cycle chemo]
Median OS in pts with liver metastasis, months | 8.6 | 8.2 | 9.0 | 8.4
HR (95% CI) | 0.85 (0.51, 1.42) [ITT] | 0.77 (0.43, 1.37) [without 1-cycle chemo]
Conclusions
Serplu plus chemo compared favorably with the comparator in this bridging trial, showing numerically longer OS and higher 24-mo OS rates vs atezo plus chemo in USA pts with ES-SCLC. These results support the benefit of serplu and the applicability of ASTRUM-005 findings to the USA population.
[Slide 1]
ESMO 2026 / MADRID
EVIDENCE NOTES
[ESMO Congress Madrid 2026 logo]
PRESIDENTIAL SYMPOSIA / 1
WHICH DATA WILL ACTUALLY CHANGE CARE?
Five positive Phase 3 toplines • Effect sizes still await Madrid
01 INTerpath-001 | LBA1 · OCT 24
Resected stage IIB–IV melanoma · adjuvant · n=1,137
ARMS Intismeran + pembrolizumab ↔ pembrolizumab
KNOWN RFS + DMFS met
READOUT Phase 2b RFS HR 0.51; Phase 3 HR and absolute gain?
02 VOLGA | LBA2 · OCT 24
Cisplatin-ineligible MIBC · cystectomy · n=695
ARMS Durvalumab + enfortumab vedotin ↔ surgery ± adjuvant care
KNOWN EFS + OS met
READOUT Absolute OS, surgery completion and toxicity
03 DeLLphi-305 | LBA3 · OCT 24
Extensive-stage SCLC · first-line maintenance · n=563
ARMS Tarlatamab + durvalumab ↔ durvalumab
KNOWN OS + PFS met
READOUT Survival gain, CRS and monitoring burden
04 KRAScendo 1 | LBA5 · OCT 25
KRAS G12C NSCLC · head-to-head · n=338
ARMS Divarasib ↔ sotorasib / adagrasib
KNOWN PFS + OS met
READOUT Absolute gain over sotorasib/adagrasib
05 SAFFRON | LBA6 · OCT 25
EGFR-mutant NSCLC · MET resistance after osimertinib
ARMS Savolitinib + osimertinib ↔ platinum + pemetrexed
KNOWN PFS + OS met
READOUT MET threshold, OS magnitude and toxicity
Positive company toplines. Full HRs, confidence intervals and event counts are still needed.
19 OCT 2026 • ESMO programme + sponsor toplines
drozdogan.com
[Slide 1]
3816RO - SKB500 (a novel B7-H3–targeted antibody-drug conjugate) in patients with extensive-stage small cell lung cancer (ES-SCLC): Results from a phase I study
Speakers Haifeng Liu (Changchun, China)
Lecture Time 10:20 - 10:25
Abstract
Background
SKB500 is an antibody-drug conjugate (ADC) targeting B7 homolog 3 (B7-H3), an antigen overexpressed in many solid tumors, comprising an antibody conjugated to a topoisomerase I inhibitor payload via a cleavable pyrimidine-tripeptide linker. Here we present updated safety and antitumor activity of SKB500 in small cell lung cancer (SCLC) from the multicenter, open-label phase I study (NCT06736327).
Methods
In this phase I study, heavily pretreated patients (pts) with unresectable SCLC were enrolled in expansion cohorts and received SKB500 at 12 mg/kg or 16 mg/kg every three weeks (Q3W) until disease progression or unacceptable toxicity. The primary efficacy endpoint was investigator-assessed objective response rate (ORR) per RECIST v1.1.
Results
As of April 20, 2026, 61 pts were treated and followed up for ≥6 weeks at 12 mg/kg (n=40) and 16 mg/kg (n=21), with a median follow-up of 4.6 months. All pts had received platinum-based therapy, with 85.2% having previously received PD-(L)1 inhibitor therapy. The ORR was 67.2% (70.0% for 12 mg/kg vs 61.9% for 16 mg/kg), with a median DoR of 5.8 months and a median PFS of 7.2 months (Table). Biomarker analysis indicated that B7-H3 expression showed no significant predictive value for treatment outcomes, while preliminary data suggested a correlation between SLFN11 levels and clinical activity. A lower frequency of Grade ≥3 treatment-related adverse events (TRAEs) was observed in the 12 mg/kg than in the 16 mg/kg cohort (Table). The most common Grade ≥3 TRAEs were white blood cell count decreased (12 mg/kg: 15.0% vs 16 mg/kg: 28.6%), lymphocyte count decreased (10.0% vs 28.6%), platelet count decreased (10.0% vs 9.5%), and anemia (7.5% vs 19.0%).
Table: 3816RO
| 12 mg/kg Q3W (N=40) | 16 mg/kg Q3W (N=21)
ORR, % (95% CI) | 70.0 (53.5, 83.4) | 61.9 (38.4, 81.9)
cORR, % (95% CI) | 55.0 (38.5, 70.7) | 47.6 (25.7, 70.2)
DCR, % (95% CI) | 95.0 (83.1, 99.4) | 81.0 (58.1, 94.6)
mDoR, mo (95% CI) | 5.8 (3.1, NE) | 5.8 (2.6, NE)
mPFS, mo (95% CI) | 7.2 (4.3, NE) | 5.6 (3.9, NE)
6-mo PFS rate, % (95% CI) | 57.6 (34.6, 75.0) | 41.8 (14.9, 67.1)
mOS, mo (95% CI) | NR (NE, NE) | NR (4.4, NE)
6-mo OS rate, % (95% CI) | 84.2 (65.3, 93.3) | 60.2 (26.8, 82.2)
Grade ≥3 TRAEs, n (%) | 19 (47.5) | 13 (61.9)
TRAEs leading to dose discontinuation, n (%) | 1 (2.5) | 0
DCR, disease control rate; DoR, duration of response; PFS, progression-free survival; OS, overall survival.
Conclusions
SKB500 demonstrated a more favorable safety profile and better clinical activity at 12 mg/kg than at 16 mg/kg in pts with SCLC, supporting further clinical development.
[Slide 1]
3808O - Tarlatamab in previously treated SCLC: Extended follow-up of overall survival from the phase 3 DeLLphi-304 trial
Speakers Charles M. Rudin (New York, United States of America)
Lecture Time 14:45 - 14:55
Abstract
Background
Tarlatamab, a DLL3-targeting bispecific T-cell engager (BiTE®) immunotherapy, demonstrated a 40% reduced risk of death and a favorable safety profile vs chemotherapy (CTx) in patients (pts) with small cell lung cancer (SCLC) after first-line (1L) platinum-based CTx. The initial publication was based on a median follow-up of only 11.2 months (mo). We now report long-term efficacy and safety data from DeLLphi-304.
Methods
Pts were randomized 1:1 to tarlatamab or CTx (topotecan, lurbinectedin or amrubicin). The primary endpoint was overall survival (OS); secondary endpoints included progression-free survival (PFS), disease control (DC), duration of response (DOR), and safety.
Results
With extended follow-up (median 23 mo), tarlatamab continued to show lower risk of death vs CTx (HR 0.62; 95% CI, 0.51–0.76), with longer OS (median 13.6 vs 8.4 mo). The reduced mortality risk was maintained across high-risk subgroups, including pts with baseline platinum-resistant disease and those with brain metastases (Table). Tarlatamab showed consistent benefit in PFS vs CTx (HR 0.69; 95% CI, 0.57–0.84; median 4.2 vs 3.2 mo). OS at 18 mo was higher with tarlatamab (42% vs 24%), as was 12-mo PFS (21% vs 6%), indicating sustained benefit. DOR was longer with tarlatamab vs CTx (Table), with more ongoing responses at 12 mo (42% vs 10% of responders), and a higher proportion with sustained (≥ 52 week) DC (24% vs 4%).
Grade ≥ 3 treatment-related adverse events (TRAEs; 28% vs 63%) and discontinuations due to TRAEs (3% vs 7%) were less frequent with tarlatamab vs CTx. Tarlatamab showed long-term tolerability with TRAEs decreasing over time and no new safety signals. Table: 3808O
Long-term Efficacy Outcomes | Tarlatamab n = 254 | CTx n = 255
OS
Median, mo | 13.6 (11.9–15.8) | 8.4 (7.2–10.2)
HR overall | 0.62 (0.51–0.76)
HR (subgroup): platinum-resistant disease† | 0.65 (0.48–0.86)
HR (subgroup): baseline brain metastases | 0.52 (0.38–0.70)
12-mo OS, % | 56 (50–62) | 39 (33–45)
18-mo OS, % | 42 (36–48) | 24 (19–29)
PFS*
Median, mo | 4.2 (3.0–4.4) | 3.2 (2.9–4.2)
HR overall | 0.69 (0.57–0.84)
12-mo PFS, % | 21 (16–26) | 6 (3–10)
DOR,* median, mo | 7.1 (4.5–12.4) | 5.5 (4.2–5.7)
DC Rate,* % | 68 (62–74) | 64 (58–70)
Sustained DC* (≥ 52 weeks), n (%) | 62 (24) | 11 (4)
*Per Response Evaluation Criteria in Solid Tumors (RECIST) 1.1 †Platinum-resistant: chemotherapy-free interval < 90 days Parentheses show 95% CI unless noted
Conclusions
With extended follow-up, tarlatamab demonstrated a durable survival benefit with a manageable safety profile vs CTx, with no new safety signals, reinforcing its role as the standard of care treatment in pts with SCLC after 1L platinum-based CTx, including those with high-risk disease.
[Slide 1]
Dr. Aakash Desai
Associate Director, Phase 1 and Precision Oncology
@ADesaiMD
My Top Picks for ESMO 2026!
CLINICAL REVIEW
ESMO Congress 2026 · Madrid · Oct 23–27 · Thoracic phase 3 readouts and early-phase ADCs, ranked
7 | 2658RO | c-Met ADC
Temab-A
Telisotuzumab adizutecan: c-Met-directed ADC with a Top1i payload
Phase 1 first-in-human study, overall survival analysis in nonsquamous NSCLC
Rapid Oral 1: NSCLC, metastatic
Sat Oct 24 · 09:27 CEST
AbbVie reports:
EGFR wild-type (n=48): ORR 50%, median OS 13.8 mo
EGFR-mutant (n=41): ORR 63%, median OS 16.2 mo
EGFR wild-type, c-Met 3+ ≥25%: median OS ~19.2 mo
Watching: Does c-Met expression level select who benefits? Phase 3 AndroMETa-Lung-167 vs standard of care is underway.
1 | LBA6 | EGFR + MET
SAFFRON
Osimertinib + savolitinib vs platinum–pemetrexed
EGFRm, MET-overexpressed and/or amplified NSCLC after osimertinib
Presidential Symposium II
Sun Oct 25 · 16:54 CET
Sponsor topline: PFS and OS met (AstraZeneca / HUTCHMED)
Watching: How large is the benefit, and which MET IHC/FISH cutoff selects patients?
2 | LBA3 | DLL3×CD3
DeLLphi-305
Tarlatamab + durvalumab vs durvalumab
1L maintenance in ES-SCLC after durvalumab + platinum–etoposide
Presidential Symposium I
Sat Oct 24 · 17:18 CEST
Sponsor topline: OS met at interim; PFS and ORR also met (Amgen)
Watching: How big is the OS gain, and can clinics deliver T-cell engager monitoring in maintenance?
3 | LBA5 | KRAS G12C
Krascendo 1
Divarasib vs sotorasib or adagrasib
Previously treated KRAS G12C-mutated advanced NSCLC
Presidential Symposium II
Sun Oct 25 · 16:30 CET
Sponsor topline: PFS met; OS significant at interim (Roche)
Watching: How wide is the gap within the G12C class, and at what tolerability?
4 | LBA66 | TROP2 ADC
OptiTROP-Lung06
Sac-TMT + pembrolizumab vs chemo + pembrolizumab
1L PD-L1-negative (TPS <1%) nonsquamous NSCLC
Proffered Paper 1: NSCLC, metastatic
Sun Oct 25 · 10:53 CET
Sponsor topline: PFS met at interim; positive OS trend (Kelun-Biotech)
Watching: Can a TROP2 ADC replace the platinum doublet alongside IO?
5 | LBA71 | EGFR×HER3
PANKU-Lung01
Iza-bren (bispecific ADC) vs platinum–pemetrexed
EGFR-mutant nonsquamous NSCLC after a 3rd-gen EGFR TKI
Proffered Paper 2: NSCLC, metastatic
Mon Oct 26 · 09:14 CET
Sponsor topline: PFS met at interim (Sichuan Biokin)
Watching: First effect sizes: how big is the PFS gain, and at what toxicity?
6 | 3837RO | SEZ6 ADC
ABBV-706
SEZ6-directed Top1i ADC, phase 1
Relapsed/refractory SCLC
Rapid Oral: Non-metastatic NSCLC and other thoracic
Mon Oct 26 · 10:15 CET
AbbVie reports: ORR 56%, median OS 12.4 mo at 1.8 mg/kg (2L+, n=41)
Watching: Where does SEZ6 fit next to DLL3 and B7-H3 in SCLC?
Key Clinical Impacts & Future Directions
• After osimertinib: MET (SAFFRON), TROP2 (OptiTROP-Lung04 final OS, LBA67) or EGFR×HER3 (PANKU-Lung01): which patients get which next step?
• ES-SCLC: Does tarlatamab move into 1L maintenance, and how does that reshape later lines (DLL3, SEZ6, B7-H3)?
• KRAS G12C: Does a next-generation inhibitor reset the second-line standard?
• 1L PD-L1-negative: Can an ADC replace platinum chemotherapy alongside pembrolizumab?
• Biomarkers: MET IHC/FISH, c-Met level, SEZ6: which assays will we need at diagnosis and at progression?
• Phase 1 to phase 3: Will early ADC signals hold up against standard of care?
Times are Madrid local (CEST on Oct 24; CET from Oct 25). Toplines are as stated in sponsor releases; full data pending. Not medical advice.
Source: ESMO 2026 Congress program | Design: Dr. Aakash Desai
[Slide 1]
ESMO 2026 | MADRID
EVIDENCE NOTES
MADRID 2026 ESMO congress [logo]
PRESIDENTIAL SYMPOSIA / 2
SAFFRON
Targeting MET-driven resistance after osimertinib in EGFR-mutated NSCLC
MET overexpression/amplification • Targeted combination • OS and PFS positive
[lung illustration with inset: MET overexpression / amplification]
01 DISEASE & PATIENT POPULATION
• EGFR-mutated advanced NSCLC
• Progressed after osimertinib
• MET overexpression and/or gene amplification
• Second-line setting
Why it matters?
• MET activation is a key resistance mechanism after osimertinib.
• A targeted strategy in a biomarker-selected population addresses an important unmet need.
02 STUDY DESIGN
Phase 3 Randomized open-label
n = 345 MET overexpression and/or amplification
International multicenter
Second-line after osimertinib
03 TREATMENT ARMS
Osimertinib + savolitinib (MET inhibitor)
VS
Platinum + pemetrexed (investigator's choice)
04 KEY RESULTS (Company topline, presented at ESMO 2026)
Progression-free survival (PFS)
POSITIVE
HR, median values and 95% CI not yet disclosed
Overall survival (OS)
POSITIVE
HR, median values and 95% CI not yet disclosed
05 TAKE-HOME POINTS
Addresses a key resistance mechanism
Targets MET overexpression/amplification after osimertinib in EGFR-mutated NSCLC.
Both PFS and OS met primary endpoints
First randomized data showing improvement in both PFS and OS in this biomarker-selected setting.
Key questions remain
• Magnitude of benefit (HR, medians)
• Safety profile and grade ≥3 AEs
• Access and regulatory strategy
• Generalizability beyond the study population
! A positive press release is not a clinical verdict.
Read the full data, absolute benefit, toxicity and patient selection when results are presented.
19 OCT 2026 • ESMO program + company press release
drozdogan.com
[Slide 1]
4156RO - Ivonescimab plus chemotherapy as first-line treatment in recurrent/metastatic thymic carcinoma: Results from the iTHYM phase II study
Speakers Xue Hou (Guangzhou, China)
Lecture Time 11:07 - 11:12
Abstract
Background
Recurrent or metastatic thymic carcinoma is a rare and aggressive malignancy with limited prospective evidence for systemic treatment. Platinum-based chemotherapy remains a standard first-line option, but durable disease control remains suboptimal. This study aimed to evaluate ivonescimab, a PD-1/VEGF bispecific antibody, combined with chemotherapy as first-line treatment for this population.
Methods
iTHYM is a prospective, multi-center, single-arm phase II study of ivonescimab plus carboplatin and paclitaxel or nab-paclitaxel as first-line treatment for recurrent/metastatic thymic carcinoma, followed by ivonescimab maintenance until progression or unacceptable toxicity. The primary endpoint was 6-month progression-free survival rate (PFS6m); secondary endpoints included ORR, DCR, DoR, PFS, OS, and safety. Simon's two-stage design defined success as no more than 10 progression events at 6 months among 24 treated patients (NCT06750952).
Results
As of July 31, 2026, 24 patients were enrolled and treated. Among 24 evaluable for response, 20 achieved partial response and 4 had stable disease, yielding an ORR of 83.3% and a DCR of 100.0%. Nineteen patients were evaluable for the primary endpoint, and all 19 remained progression-free at 6 months. After a median follow-up of 10.2 months, four patients experienced progression at 7.0, 8.1, 10.8, and 18.2 months. Based on the pre-specified Simon decision rule, the study met its primary endpoint of PFS6m. Median PFS and OS were not reached. Safety was manageable and consisted mainly of chemotherapy-related hematologic toxicities; ivonescimab-related adverse events were mostly low-grade, including hemorrhage (oral hemorrhage and epistaxis) (9/24, 37.5%), rash/pruritus (8/24, 33.3%), and proteinuria (3/24, 12.5%). Grade 3 proteinuria occurred in 2/24 (8.3%); Grade 3 acute coronary syndrome occurred in 1/24 (4.2%), leading to permanent discontinuation of ivonescimab.
Conclusions
Ivonescimab plus taxanes and carboplatin showed encouraging antitumor activity and manageable safety as first-line treatment for recurrent/metastatic thymic carcinoma. The iTHYM study met its pre-specified primary endpoint of 6-month PFS rate. Longer follow-up is ongoing to define the final PFS6m estimate, durability of benefit, and long-term outcomes.
[Slide 1]
2519O - Association of biomarkers with efficacy in the phase 3 KEYNOTE-671 study of perioperative pembrolizumab (Pembro) plus neoadjuvant chemotherapy (Chemo) in early-stage non–small-cell lung cancer (NSCLC)
Speakers Marina C. Garassino (Chicago, United States of America)
Lecture Time 15:33 - 15:43
Abstract
Background
In KEYNOTE-671, perioperative pembro plus neoadjuvant chemo improved EFS, OS, major pathological response (MPR), and pathological complete response (pCR) vs neoadjuvant chemo and surgery in resectable stage II–IIIB (N2) NSCLC. We report associations of 18-gene T-cell–inflamed gene expression profile (TcellinfGEP) and tumor mutational burden (TMB) with efficacy in KEYNOTE-671, and present EFS and OS by TcellinfGEP, TMB, and KRAS mutation status.
Methods
Participants (pts) in this post hoc analysis had an evaluable baseline tumor sample, which was used for RNA sequencing (RNAseq) to assess TcellinfGEP and whole exome sequencing (WES) for TMB and KRAS mutation status (also with matched-normal sample). Associations of TcellinfGEP and TMB with EFS and OS were analyzed by an adjusted Cox proportional hazards model and with MPR and pCR by a logistic regression model; 1-sided (pembro) and 2-sided (placebo) P values were calculated (prespecified α = 0.05). Analyses of EFS and OS in biomarker-based subgroups were performed.
Results
Of 797 pts, 387 had RNAseq data (pembro, n = 198; placebo, n = 189) and 459 had WES data (pembro, n = 230; placebo, n = 229). TcellinfGEP was positively associated with EFS (P = 0.021) and MPR (P = 0.019) for pembro, with OS for placebo (P = 0.002). TMB was positively associated with EFS (P = 0.000164) and OS (P = 0.005) for pembro and with MPR (pembro, P = 0.001; placebo, P = 0.014) and pCR (pembro, P = 0.000695; placebo, P = 0.044) for both arms. EFS and OS HRs were generally comparable across subgroups by TcellinfGEP, TMB, and KRAS mutation status (Table). Table: 2519O
Associations of biomarkers with EFS and OS in the pembro vs placebo arm
[columns: N | EFS^a HR (95% CI) | OS HR (95% CI)]
TcellinfGEP low (<1st tertile) | 129 | 0.71 (0.46–1.11) | 0.59 (0.36–0.97)
TcellinfGEP high (≥1st tertile) | 258 | 0.53 (0.38–0.75) | 0.82 (0.55–1.22)
TMB low (<175 mutation/exome) | 266 | 0.63 (0.47–0.86) | 0.70 (0.49–1.01)
TMB high (≥175 mutation/exome) | 193 | 0.49 (0.32–0.73) | 0.67 (0.40–1.12)
KRAS mutation^b | 86 | 0.73 (0.42–1.28) | 0.88 (0.45–1.75)
KRAS wild-type^b | 169 | 0.75 (0.50–1.12) | 0.85 (0.49–1.47)
^aPer RECIST version 1.1 by investigator. ^bMatched normal nonsquamous only.
Conclusions
Positive associations of baseline TcellinfGEP and TMB with efficacy were observed for both treatment arms. The benefits of perioperative pembro vs neoadjuvant chemo were observed regardless of TcellinfGEP, TMB, and KRAS mutation status, supporting its use for early-stage NSCLC.
[Slide 1]
2617RO - Phase I study of TIL therapy in combination with chemoimmunotherapy in ≥2nd line advanced NSCLC patients
Speakers Laurie Steinbusch (Leiden, Netherlands)
Lecture Time 08:57 - 09:02
Abstract
Background
Based on (pre)clinical studies Tumor-Infiltrating Lymphocytes (TIL) treatment may be a potent therapeutic option in non-small cell lung cancer (NSCLC). However toxicities associated with preconditioning treatment is a limiting factor for elderly patients (pts) with comorbid conditions such as NSCLC pts. Our group has shown that carboplatin and paclitaxel is a less toxic option while preserving optimal conditions for the infused TIL. We assessed safety of TIL therapy preceded by chemotherapy with or without (w/wo) immunotherapy.
Methods
This is a single-arm, single-center, phase 1 study, evaluating TIL therapy in adult pts with advanced NSCLC with progressive disease on first-line treatment of (chemo)immunotherapy and at least one lesion suitable for resection or biopsy for TIL retrieval. Pts received 3 cycles of IV Carboplatin AUC 5 plus Paclitaxel 175mg/m2 (cohort 1) and pembrolizumab every 3 weeks 100-200mg based on weight (cohort 2). On day 7 after the second and after the third course of chemotherapy patients received 2,5-10 x 10^8 TIL as an IV infusion. The primary endpoint was safety of TIL therapy. Anti-tumor activity and feasibility of study procedure were key secondary objectives.
Results
Between Dec 20, 2023 and Nov 26, 2025, 13 pts were included (median age 68 years [IQR 61- 71]). Treatment-related grade 3 or 4 adverse events included anemia, thrombocytopenia (both in 2 patients [15%]), febrile neutropenia and nausea (both in 1 patient [8%]), all chemotherapy related. Immunotherapy related toxicity hepatitis grade 3 and renal tubular acidosis grade 1 occurred in 1 pt. No toxicity of the TIL infusion and no grade 5 toxicity was observed. At data cutoff (May 12, 2026), 3 of 13 patients (23%) had an objective response per RECIST v1.1 and a disease control rate of 69%. Median progression free survival is 3.4 months (IQR 2.1-6.2) and overall survival 8 months (IQR 4.1-19.7). In 85% (17/20 patients, 11 biopsies, 6 resections) TIL product was successfully produced.
Conclusions
This phase 1 study of TIL therapy preceded by Carboplatin and Paclitaxel w/wo Pembrolizumab in patients with NSCLC in ≥2nd line demonstrated manageable safety and encouraging anti-tumor activity and supports further investigation of this combination.
[Slide 1]
Professional Reviewed Abstracts | AMCP Nexus 2026 | October 26-29 S71
[phone overlay: 73 de 128]
[Left column — end of preceding, unrelated abstract on BCG-unresponsive HR-NMIBC:]
10/31/2024). Patients with HR-NMIBC with CIS (as of the HR-NMIBC diagnosis date) were assessed for BCG discontinuation (last instillation before a gap of >180 days, following adequate induction [≥5 instillations in 70 days] and maintenance [≥2 instillations in 180 days]). BCG-unresponsive was defined as receiving subsequent guideline-recommended treatment (index date) within 365 days of BCG discontinuation. EFS (i.e., time without disease recurrence or progression) was defined based on codes for transurethral resection of bladder tumor, biopsy, systemic chemotherapy, non-index intravesical therapy, radiotherapy, radical cystectomy, pembrolizumab, diagnosis of muscle-invasive or metastatic bladder cancer, or death. EFS was described using Kaplan-Meier analyses among patients with bladder-sparing therapy after BCG discontinuation.
RESULTS: Overall, there were 130 patients with BCG-unresponsive HR-NMIBC with CIS ± PAP (mean age: 70 years; 77% male; 78% White). Among 108 patients initiating bladder-sparing therapies as next treatment, gemcitabine (52%), mitomycin (16%), pembrolizumab (15%), gemcitabine/docetaxel (14%), nadofaragene firadenovec-vncg (2%), docetaxel (1%), and doxorubicin (1%) were used. Among these patients, median EFS was 5.9 months (95% CI: 4.7, 12.1). The proportion of patients with recurrence, progression, or death was 28% at 3 months, 50% at 6 months, 59% at 12 months, 69% at 24 months and 74% at 36 months.
CONCLUSIONS: Treatment choice varied among patients with BCG-unresponsive HR-NMIBC with CIS. Despite radical cystectomy being recommended for BCG-unresponsive patients, most received bladder-sparing therapy, with 50% having disease recurrence, progression, or death within 6 months. These findings highlight a significant unmet need for more effective bladder-sparing therapies among BCG-unresponsive patients with HR-NMIBC with CIS ± PAP.
SPONSORSHIP: Johnson & Johnson
269 IMforte: Characterization of hospitalization and health care resource utilization with lurbinectedin + atezolizumab maintenance therapy for extensive-stage small cell lung cancer in a phase 3 randomized trial
Nguyen A1, Paz-Ares L2, Borghaei H3, Liu S4, Peters S5, Reck M6, Cuchelkar V7, Mohan S7, Lin Y7, Fuller D1, Profant D8, Bhatt K1, Herbst R9; amy.nguyen@jazzpharma.com
1Jazz Pharmaceuticals, Philadelphia, PA, USA; 2Department of Medical Oncology, Hospital Universitario 12 de Octubre, H12O-CNIO Lung Cancer Unit, Universidad Complutense and Ciberonc, Madrid, Spain; 3Department of Hematology and Oncology, Fox Chase Cancer Center, Philadelphia, PA, USA; 4Department of Medical Oncology, Lombardi Comprehensive Cancer Center, Georgetown University, Washington, DC, USA; 5Department of Oncology, Centre Hospitalier Universitaire Vaudois, Lausanne, Switzerland; 6LungenClinic, Airway Research Center North, German Center for Lung Research, Grosshansdorf, Germany; 7Genentech, Inc., South San Francisco, CA, USA; 8Jazz Pharmaceuticals, Carlsbad, CA, USA; 9Department of Medical Oncology and Hematology, Yale School of Medicine, New Haven, CT, USA
BACKGROUND: Extensive-stage small cell lung cancer (ES-SCLC) is an aggressive disease with poor prognosis. Among patients (pts) with ES-SCLC, rates of complications that drive health care resource utilization (HCRU) are high. The phase 3 IMforte (NCT05091567) trial demonstrated statistically significant and clinically meaningful improvements in progression-free and overall survival with lurbinectedin + atezolizumab (L+A) vs atezolizumab alone (A) for first-line maintenance treatment (1Lm) of ES-SCLC.
OBJECTIVE: To describe hospitalizations and HCRU from IMforte pts receiving 1Lm with L+A vs A.
METHODS: Eligible pts with ES-SCLC who were progression free after induction with atezolizumab, carboplatin, and etoposide were randomized 1:1 to receive 1Lm L+A or A every 3 weeks. Details of all-cause and treatment-related inpatient hospitalizations and supportive care during 1Lm were summarized descriptively.
RESULTS: As of February 12, 2025, the median treatment duration was 4.4 (L)/4.8 (A) and 2.1 months in the L+A and A arms. One or more treatment-related hospitalizations occurred in 25/242 (10%) pts in the L+A arm and 6/240 (3%) pts in the A arm. The median (quartile 1 [Q1]–Q3) number and total length of treatment-related hospitalizations were 1 (1–1) admission and 7 (4–14) days in the L+A arm and 1 (1–1) admission and 7 (2–13) days in the A arm, respectively. Regardless of relationship to study drug, 60/242 (25%) and 34/240 (14%) pts had an all-cause hospitalization in the L+A and A arms, respectively. The median (Q1–Q3) number and total length of all-cause hospitalizations were 1 (1–2) admission and 7 (5–14) days in the L+A arm and 1 (1–1) admission and 9 (4–17) days in the A arm, respectively. The most common preferred term used among all-cause hospitalizations was pneumonia (L+A, n=5 [2%]; A, n=6 [3%]). Most pts (215/242 [89%]) in the L+A arm used granulocyte colony-stimulating factor, compared to 28/240 (12%) in the A arm.
CONCLUSIONS: Consistent with the extended treatment duration, L+A appeared to be associated with a higher incidence of hospitalization than A. Nonetheless, the frequency remained low: 90% of all pts in the L+A arm did not experience a treatment-related hospitalization. Among pts who were hospitalized, the number of visits and lengths of stay were similar
Vol. 33, No. 10-d | October 2026 | JMCP.org
S72 Professional Reviewed Abstracts | AMCP Nexus 2026 | October 26-29
between treatment arms, suggesting L+A did not increase inpatient burden on a per-event basis. Overall, L+A showed a manageable and predictable HCRU pattern, supporting its feasibility from clinical and health economic perspectives.
SPONSORSHIP: F. Hoffmann-La Roche Ltd and Jazz Pharmaceuticals
[right column of S72 — start of unrelated abstract:] perceived benefits of switching from bid to qd varied depending on overall pill burden and daily routines.
CONCLUSIONS: Treatment frequency, disease severity, and pill burden influence patient preference and anticipated adherence in MF, PV, and GVHD. Patients demonstrated a clear preference for qd regimens, which may support adherence through simplified treatment routines. Willingness to switch [cut off]
[Slide 1]
ESMO 2026 / MADRID
EVIDENCE NOTES
23–27 OCT 2026 MADRID, SPAIN
PRESIDENTIAL SYMPOSIUM I / LBA3 · 24 OCT
DeLLphi-305
TARLATAMAB + DURVALUMAB MAINTENANCE MET THE OS ENDPOINT
Post-induction ES-SCLC • first-line maintenance
24 OCT 2026, Saturday 16:30 Madrid | 17:30 TSİ
Presenter Jacob Sands
OS met · PFS met · ORR met · effect size pending
01 PATIENTS
• Extensive-stage small-cell lung cancer (ES-SCLC)
• No progression after 3–4 cycles of platinum + etoposide + durvalumab
• ECOG PS 0–1
02 ARMS
Tarlatamab + durvalumab (maintenance)
• Tarlatamab (DLL3-directed T-cell engager) + Durvalumab (PD-L1 inhibitor)
→ R 1:1 → n = 563
Durvalumab alone (maintenance)
• Durvalumab (PD-L1 inhibitor)
PHASE 3 | RANDOMIZED | OPEN-LABEL | MULTICENTER | n = 563
03 KNOWN NOW
✓ Prespecified interim analysis met the primary endpoint: overall survival (OS)
✓ Progression-free survival (PFS) also met its endpoint
✓ Objective response rate (ORR) also improved significantly
04 NOT YET DISCLOSED
? Hazard ratio and 95% CI
? Median OS and median PFS
? Absolute survival differences
? Detailed CRS/ICANS rates
? Grade 3+ toxicity and treatment discontinuation
05 CLINICAL READOUT
Key question: How much OS is gained by moving a DLL3-directed T-cell engager into maintenance before relapse, and is that gain large enough to justify CRS/ICANS monitoring and added treatment burden?
Data status: company topline + ESMO 2026 programme; full LBA3 presentation pending.
Sources: Amgen/AstraZeneca topline, 8 Sep 2026; DeLLphi-305 / NCT06211036; ESMO 2026 programme.
drozdogan.com
Congress news · Scientific summaries · Clinical perspective
[Slide 1]
MADRID 2026 ESMO congress | Madrid, Spain
24–28 October 2026
Selected presentations on
BRAF-mutant NSCLC
Clinical trials – Targeted therapies
• 2651P – Encorafenib plus binimetinib in patients (pts) with BRAF V600E-mutant advanced non-small cell lung cancer: Updated efficacy and safety results from the IFCT-1904 ENCO-BRAF phase 2 trial
Therapy sequence and clinical management of BRAF V600E-NSCLC
• 2840eP – Real-world management of BRAF-mutated NSCLC in Italy: National and macroregional patterns from an oncologist survey
• 2805eP – First-line BRAF/MEK inhibition versus immune checkpoint inhibitor–based therapy in BRAF V600E-mutant metastatic NSCLC: A meta-analysis
• 2791eP – First-line immunotherapy with or without chemotherapy versus BRAF plus MEK inhibitors in BRAF V600-mutated metastatic non-small cell lung cancer: A systematic review and meta-analysis
• 4292P – Multi-omics identifies predictive markers for BRAF/MEK inhibitors used outside labelled indications in patients with BRAF-V600E mutated solid tumors
Translational research and biomarkers
• 4368P – Clinical and molecular heterogeneity of BRAF non-V600E alterations across solid tumors: A nationwide Japanese C-CAT registry study
[Slide 1]
2616RO - A phase 2 study of CS2009, a first-in-class PD-1/VEGF/CTLA-4 trispecific antibody, in patients with advanced non-small cell lung cancer (NSCLC)
Speakers Anwen Xiong (Shanghai, China)
Lecture Time 08:35 - 08:40
Abstract
Background
CS2009 is a novel PD-1/VEGF/CTLA-4 trispecific antibody. Preclinical and clinical studies demonstrated promising anti-tumor activity in solid tumors. Here, we report the safety and efficacy data from a phase 2 study of CS2009 in advanced NSCLC.
Methods
Patients (pts) with advanced NSCLC were enrolled across different lines of therapy. In the first-line (1L) setting, pts without actionable genomic alterations received either CS2009 monotherapy (mono) or CS2009 + chemotherapy (chemo) (pemetrexed + carboplatin for non-squamous [NSQ] pts; paclitaxel + carboplatin for squamous [SQ] pts.) In the second- or third-line (2/3L) setting, pts who had received prior platinum-based chemo and anti-PD-(L)1 therapy were treated with CS2009 + docetaxel. CS2009 was dosed at 20 or 30 mg/kg Q3W. The primary endpoint was investigator-assessed ORR per RECIST v1.1.
Results
As of April 19, 2026, 86 pts were treated (median age 65.6 [range 38-82]; 77.9% male; 82.6% with ECOG PS 1; 40.7% NSQ; 76.7% PD-L1 TPS≥1%). In pts receiving CS2009 mono (n=46), any-grade and grade ≥3 TRAEs occurred in 67.4% and 6.5% of pts, respectively. The most common TRAEs were AST increased (17.4%), ALT increased (15.2%), hyperthyroidism (13.0%) and rash (13.0%); all grade ≥3 TRAEs were single-case events. In pts receiving CS2009 + chemo (n=40), any-grade and grade ≥3 TRAEs occurred in 65.0% and 30.0% of pts, respectively. The most common TRAEs were neutrophil count decreased (35.0%), WBC count decreased (30.0%) and anaemia (30.0%). CS2009 did not appear to increase chemo-associated toxicity. No unexpected safety signals were observed. In preliminary efficacy assessment among evaluable pts, ORR/DCR in 1L mono (PD-L1 TPS ≥50%) and 1L SQ combination (PD-L1 TPS <50%) cohorts were 81.3%/100% (n=16) and 75.0%/100% (n=8), respectively. Encouraging responses have been observed in other cohorts. Updated data from the 1L mono (n ~ 60, PD-L1 TPS ≥1%) and combination (n ~ 60, SQ & NSQ) cohorts will be presented at the congress.
Conclusions
CS2009 mono and CS2009 + chemo were both well tolerated and demonstrated promising anti-tumor activity in NSCLC. Phase 3 studies of CS2009 + chemo in advanced NSCLC are planned.
[Slide 1]
2618RO - Analysis of the phase 2 part of IFCT-2103 DIAL phase 2-3 randomized trial, comparing continuation pembrolizumab (± pemetrexed) up to 2 years versus observation (± pemetrexed), in patients with metastatic non-small cell lung cancer (mNSCLC) with disease control (DC) at 6 months
Speakers Anne Claire Toffart (La Tronche, France)
Lecture Time 09:14 - 09:19
Abstract
Background
Optimal duration of 1L immunotherapy (io) in mNSCLC patients. with DC remains debatable. We aimed to study de-escalation by stopping pembrolizumab in patients with 6-months DC after chemo-io induction, as compared to 24 months.
Methods
This randomized open-label trial included treatment-naïve 18-75 yrs. mNSCLC patients (pts), ECOG PS 0-1, w/o actionable tumor molecular alteration, stratified according to PS, histology (SCC. vs. non-SCC), PD-L1 tumor level, sex and quality of response (stable vs. objective response). They received 4 cycles of 1L platinum-based chemo doublet+pembro, either paclitaxel-carboplatin, followed by maintenance pembro, for SCC patients or pemetrexed-platinum, followed by pembro + pemetrexed continuation for non-SCC patients. At 6 months, patients with DC were randomized 1:1 either to pembrolizumab (± pemetrexed in non-SCC patients) continuation until 2 years, or to observation (± pemetrexed). Primary outcome was 18-mo. overall survival (OS) from inclusion. Secondary outcomes included safety from randomization.
Results
From May 2022 to March 2024, 197 patients (68.0% male, 63.3y median age, 66% stage IVB, 70.6% adenocarcinoma), were accrued. 93 (47.2%) patients were randomized: to the continuation control arm (n=47) or the de-escalation arm (n=46). In Dec. 2025, the phase II analysis involved 84 first eligible patients (42 in each arm). Both arms were well balanced according to clinical and biological characteristics. Median follow-up was 27.9 months 95%CI [25.0 - 31.1]. At 18 months, 83.3%, 95%CI [72.1 - 94.6] were alive in the continuation arm vs. 88.1%, 95%CI [78.3 - 97.9] in the de-escalation arm. In the 93 randomized patients, grade 3-4 rates from randomization were 14.9% and 6.5%, while all-grade irAEs were 85.1% and 47.8%, in the continuation arms and the de-escalation arms, respectively.
Conclusions
In patients with 6-mo DC, similar rates of 18-mo OS were observed in both arms, while leading to lower frequency of irAEs in the de-escalation arm. Accrual in the trial phase 3 part is continuing.
[Slide 1]
2615O - Dalmelitinib plus aumolertinib versus platinum-based chemotherapy in advanced NSCLC patients with MET amplification post EGFR TKI: A randomized, phase 3 study
Speakers Ziming Li (Shanghai, China)
Lecture Time 08:40 - 08:50
Abstract
Background
MET amplification (MET-amp) is a key resistance mechanism to EGFR TKIs. Dalmelitinib (HS-10241), a novel oral MET TKI, demonstrated promising efficacy when combined with Aumolertinib in MET-amplified advanced NSCLC post EGFR TKIs in a phase 1b study (NCT05430386). Here, we reported the phase 3 results of this combination.
Methods
This randomized, open-label, multicenter, phase 3 study (NCT06110663) enrolled advanced NSCLC patients (pts) with EGFR mutation-positive and MET-amp (GCN ≥5 or MET/CEP7 ≥2) post EGFR TKIs. Eligible pts were randomized 1:1 to receive either Dalmelitinib plus Aumolertinib (TKI-combo) or platinum-based chemotherapy (Chemo). The primary endpoint was PFS assessed by IRC and analyzed in all randomized pts.
Results
As of Dec 10, 2025, 314 pts were randomized (156/158 in TKI-combo/Chemo group). Baseline characteristics between two groups were balanced, with 296 pts (94.3%) having received prior 3rd-generation EGFR TKI. Primary analysis demonstrated superior efficacy of TKI-combo over chemo with significant improvement in PFS (mPFS-IRC 6.2 vs. 4.4 months, HR 0.601, P<0.001; mPFS-Investigator 6.9 vs. 4.6 months), and clinical benefit was observed across all efficacy endpoints (Table), including a trend toward survival benefit based on preliminary OS results. No obvious difference was observed in overall severity (grade ≥3: 50.0% vs. 51.0%) of treatment-emergent adverse events (TEAEs) between two groups with different safety profiles. In TKI-combo group, most TEAEs were low grade, reversible and manageable without new safety signal; most common grade ≥3 TEAEs were liver enzyme elevations. Table: 2615O
Efficacy accessed by IRC
[columns: TKI-combo group (N=156) | Chemo group (N=158)]
Primary endpoint
mPFS, months (95% CI) | 6.2 (5.6, 9.7) | 4.4 (4.2, 5.5)
HR (95% CI) | 0.601 (0.448, 0.805)
Secondary endpoints
ORR, % (95% CI) | 59.6 (51.5, 67.4) | 38.6 (31.0, 46.7)
mDoR, months (95% CI) | 9.7 (7.0, 14.0) | 4.4 (3.0, 8.4)
DCR, % (95% CI) | 84.6 (78.0, 89.9) | 74.1 (66.5, 80.7)
mOS&, months (95% CI) | NR (17.5, NE) | 19.6 (14.6, NE)
HR (95% CI) | 0.840 (0.524, 1.346)
&46.8% pts in Chemo group were crossed over to TKI-combo. HR, hazard rate; IRC, independent review committee; m, median; NE, not estimable; NR, not reached.
Conclusions
Dalmelitinib plus Aumolertinib showed superior clinical benefit in advanced NSCLC pts with EGFR mutation-positive and MET-amp (GCN ≥5), majority of whom failed 3rd-generation EGFR TKIs. This suggested a new treatment option for this population.
[Slide 1]
LA FDA RETIRA LA APROBACIÓN DE LURBINECTEDIN ( ZEPZELCA ) PARA EL CÁNCER DE PULMÓN DE CÉLULAS PEQUEÑAS PREVIAMENTE TRATADO .
CURE TODAY : 9 DE SEPTIEMBRE 2026 .
[Embedded small version of the wide summary infographic - same graphic as image _s4; too small to read here]
Su estudio confirmatorio fue el ensayo LAGOON de FASE III , que no alcanzó su objetivo principal .
En sus resultados financieros del segundo trimestre, publicados el 3 de agosto de 2026, Jazz Pharmaceuticals anunció que, basándose en los resultados de LAGOON y en consonancia con la FDA, planeaba solicitar a la agencia que eliminara la indicación de segunda línea de la ficha técnica .
Ninguno de los grupos tratados con Zepzelca vivió más tiempo que el grupo tratado con quimioterapia .
[Embedded dark graphic with FDA logo - same graphic as image _s3]
LA MEDIANA DE SUPERVIVENCIA GLOBAL, EL PUNTO EN EL QUE LA MITAD DE LAS PERSONAS DE UN GRUPO SEGUÍAN VIVAS , FUE :
· 8,7 MESES SOLO CON LURBINECTEDIN ( ZEPZELCA ) .
· 10,9 MESES CON LURBINECTEDIN ( ZEPZELCA ) MÁS IRINOTECÁN .
· 10,7 MESES CON TOPOTECAN O IRINOTECÁN .
ENTRE LAS PERSONAS CUYO CÁNCER SE HABÍA EXTENDIDO al CEREBRO O la MÉDULA ESPINAL, UN GRUPO MÁS PEQUEÑO , LA MEDIANA DE SUPERVIVENCIA FUE DE 7,1 MESES CON ZEPZELCA SOLO ( 58 PERSONAS ) EN COMPARACIÓN CON 10,3 MESES CON QUIMIOTERAPIA ( 56 PERSONAS ) .
EFECTOS SECUNDARIOS :
JAZZPHARMA NO INFORMÓ DE NUEVOS PROBLEMAS DE SEGURIDAD .
Se observaron efectos secundarios graves (de grado 3 o superior) relacionados con el tratamiento en el 35 % de las personas que recibieron Zepzelca sola, en el 62,6 % de las que recibieron Zepzelca más irinotecán y en el 64,4 % de las que recibieron quimioterapia .
[Slide 2]
ESTÁ RETIRADA DE MERCADO COMO TRATAMIENTO DE SEGUNDA LÍNEA DE SMALL CELL LUNG CANCER EXTENSIVE-STAGE.
NO AFECTA AL TRATAMIENTO DE MANTENIMIENTO DE PRIMERA LÍNEA ... QUE SIGUE EN PIE.
A TENER MUY EN CUENTA : ESTA RETIRADA NO AFECTA NI MODIFICA PARA NADA A LA APROBACIÓN DEL TRATAMIENTO IMFORTE ( LURBINECTEDIN MAS ATEZOLIZUMAB ) PARA MANTENIMIENTO EN PRIMERA LINEA SMALL CELL LUNG CANCER .
[Left screenshot - cure]
cure | News | Articles | October 9, 2026
FDA Withdraws Zepzelca Approval for Previously Treated Small Cell Lung Cancer
Author(s) Quincy Attobrah
The FDA withdrew Zepzelca's accelerated approval for small cell lung cancer after the LAGOON trial failed to show longer survival. Its maintenance use with Tecentriq is unaffected.
Neither Zepzelca group lived longer than the chemotherapy group. Median overall survival, the point at which half the people in a group were alive, was:
• 8.7 months with Zepzelca alone
• 10.9 months with Zepzelca plus irinoteca[n]
• 10.7 months with topotecan or irinotecan
[Right screenshot - MedPath]
MedPath
FDA Pulls Zepzelca Approval in Previously Treated Small Cell Lung Cancer
KEY INSIGHTS
• The FDA withdrew the accelerated approval of Zepzelca (lurbinectedin) for metastatic small cell lung cancer that progressed during or after platinum-based chemotherapy, effective Sept. 30, 2026.
• The confirmatory phase 3 LAGOON trial did not meet its primary overall survival endpoint, with median survival of 8.7 months for Zepzelca alone versus 10.7 months for chemotherapy.
• The withdrawal does not affect Zepzelca plus Tecentriq (atezolizumab) as maintenance treatment for extensive-stage small cell lung cancer, an approval based on the separate IMforte trial.
[Slide 3]
FDA U.S. FOOD & DRUG ADMINISTRATION
# LA FDA RETIRA LA APROBACIÓN DE LURBINECTEDIN ( ZEPZELCA ) PARA EL CÁNCER DE PULMÓN DE CÉLULAS PEQUEÑAS PREVIAMENTE TRATADO .
CURE : 9 DE SEPTIEMBRE 2026 .
En sus resultados financieros del segundo trimestre, publicados el 3 de agosto de 2026, Jazz Pharmaceuticals anunció que, basándose en los resultados de LAGOON y en consonancia con la FDA, planeaba solicitar a la agencia que eliminara la indicación de segunda línea de la ficha técnica .
EFECTOS SECUNDARIOS :
JAZZPHARMA No informó de nuevos problemas de seguridad .
Se observaron efectos secundarios graves (de grado 3 o superior) relacionados con el tratamiento en el 35 % de las personas que recibieron Zepzelca sola,
en el 62,6 % de las que recibieron Zepzelca más irinotecán y en el 64,4 % de las que recibieron quimioterapia .
[Red warning triangle; red stamp: SIN BENEFICIO EN SUPERVIVENCIA]
[Slide 4]
LA FDA RETIRA LA APROBACIÓN DE LURBINECTEDIN ( ZEPZELCA ) PARA EL CÁNCER DE PULMÓN DE CÉLULAS PEQUEÑAS PREVIAMENTE TRATADO .
CURE : 9 DE SEPTIEMBRE 2026 .
SU ESTUDIO CONFIRMATORIO FUE EL ENSAYO LAGOON DE FASE III , QUE NO ALCANZÓ SU OBJETIVO PRINCIPAL .
En sus resultados financieros del segundo trimestre, publicados el 3 de agosto de 2026, Jazz Pharmaceuticals anunció que, basándose en los resultados de LAGOON y en consonancia con la FDA, planeaba solicitar a la agencia que eliminara la indicación de segunda línea de la ficha técnica .
SUPERVIVENCIA GLOBAL (MEDIANA)
Ninguno de los grupos tratados con Zepzelca vivió más tiempo que el grupo tratado con quimioterapia .
8,7 MESES SOLO CON LURBINECTEDIN ( Zepzelca )
10,9 MESES CON LURBINECTEDIN ( ZEPZELCA ) + IRINOTECAN
10,7 MESES CON TOPOTECAN O IRINOTECAN
ENTRE LAS PERSONAS CUYO CÁNCER SE HABÍA EXTENDIDO AL CEREBRO O A LA MÉDULA ESPINAL , LA MEDIANA DE SUPERVIVENCIA FUE DE :
7,1 MESES CON Zepzelca SOLO ( 58 personas )
10,3 MESES CON QUIMIOTERAPIA ( 56 personas )
EFECTOS SECUNDARIOS :
JAZZPHARMA No informó de nuevos problemas de seguridad .
Se observaron efectos secundarios graves (de grado 3 o superior) relacionados con el tratamiento en el 35 % de las personas que recibieron Zepzelca sola, en el 62,6 % de las que recibieron Zepzelca más irinotecán y en el 64,4 % de las que recibieron quimioterapia .
[Three red circles] 35% ZEPZELCA SOLA · 62,6% ZEPZELCA + IRINOTECAN · 64,4% QUIMIOTERAPIA
LO IMPORTANTE A RECORDAR :
LA RETIRADA DE LURBINECTEDIN ( ZEPZELCA ) NO AFECTA AL TRATAMIENTO DE MANTENIMIENTO DE PRIMERA LÍNEA ... QUE SIGUE EN PIE.
[Green check] EL TRATAMIENTO DE MANTENIMIENTO DE PRIMERA LÍNEA CONTINÚA VIGENTE.
[Slide 1]
2574RO - Neoadjuvant toripalimab plus chemotherapy with or without tifcemalimab (anti-BTLA antibody) in potentially resectable stage III non-small cell lung cancer (LungMate-014): A randomized, phase II trial
Speakers Peng Zhang (Shanghai, China)
Lecture Time 10:45 - 10:50
Abstract
Background
Perioperative toripalimab plus chemotherapy has improved outcomes in resectable stage III non-small cell lung cancer (NSCLC), and tifcemalimab combined with toripalimab has shown promising activity in advanced disease. Here, we first evaluated the addition of tifcemalimab to neoadjuvant toripalimab plus chemotherapy in patients with potentially resectable stage III NSCLC.
Methods
In this open-label, single-center, phase II trial, patients with potentially resectable disease were randomized 1:1 to receive toripalimab plus chemotherapy with tifcemalimab (TCT) or without tifcemalimab (TC) for 4 cycles. Surgical resectability was reassessed by multidisciplinary discussion. The primary endpoint was pathological complete response (pCR). Secondary endpoints included major pathological response (MPR), objective response rate (ORR), R0 resection, safety, event-free survival (EFS) and overall survival (OS).
Results
As of August 29, 2024, 118 patients were randomized in two arms. Patient characteristics were well balanced between the arms. pCR rates were 32.2% vs. 25.4% in the TCT and TC arms, respectively. Subgroup analyses showed higher pCR rates in patients with non-squamous histology (31.6% vs. 15.0%) and those with PD-L1 TPS <1% (35.7% vs. 25.9%). Surgery was performed in 67.8% and 59.3% of patients in the TCT and TC arms, with all achieving R0 resection. Grade ≥3 TRAEs occurred in 77.6% and 75.4% of patients, with no new safety signals. At a median follow-up of 26.6 months, 24-month EFS rates were 71.1% vs. 66.0%, and 24-month OS rates were 83.0% vs. 76.1% in the TCT and TC arms. Subgroup analyses suggested a trend toward improved survival in patients with non-squamous histology (24-month OS: 89.5% vs. 79.4%) and those with PD-L1 TPS <1% (24-month OS: 88.1% vs. 69.6%).
Conclusions
The addition of tifcemalimab to neoadjuvant toripalimab plus chemotherapy showed encouraging efficacy and manageable safety in potentially resectable stage III NSCLC. Notably, this strategy revealed enhanced benefit in patients with non-squamous histology and those with PD-L1 TPS <1%, supporting further evaluation in larger randomized trials.
[Slide 1]
KEYNOTE-671 | ESMO 2026
The Biomarker Detective Story
MV Onco
T-CELL INFLAMMATION — HIGH TcellinfGEP
"Better outcomes!"
[Cartoon T cell with magnifying glass over a tumor]
EFS HR: High 0.53 / Low 0.71
TMB — HIGH TMB
"Better outcomes in BOTH arms!"
[Cartoon tumor with mutation flags]
EFS HR: High 0.49 / Low 0.63
KRAS
"KRAS didn't distinguish benefit!"
[Cartoon: KRAS MUTATED (PEMBRO BENEFIT) and KRAS WILD-TYPE (PEMBRO BENEFIT)]
EFS HR: 0.73 / 0.75
[Cartoon: doctor in detective hat in front of a locked door "WHO REALLY NEEDS PEMBROLIZUMAB?" with sign "PREDICTIVE BIOMARKER NOT FOUND"; thought bubble TcellinfGEP? TMB? KRAS?]
TAKE-HOME
PROGNOSTIC ≠ PREDICTIVE
• Biomarkers were associated with outcomes.
• None was validated to select or exclude patients from perioperative pembrolizumab.
[Slide 2]
KEYNOTE-671 | ESMO 2026
What Did the Biomarkers Reveal?
MV Onco
01 WHY THIS ANALYSIS?
KEYNOTE-671 established:
• Perioperative pembrolizumab + chemotherapy improves EFS and OS in resectable NSCLC.
THE QUESTION:
• Can biomarkers identify who benefits most?
02 WHICH BIOMARKERS?
• TcellinfGEP – 18-gene T-cell inflammation signature.
• TMB – Tumor mutational burden.
• KRAS – Mutated versus wild-type.
• 797 randomized patients.
• Exploratory biomarker analysis.
03 WHAT DID T-CELL INFLAMMATION REVEAL?
Higher TcellinfGEP was associated with:
• Pembrolizumab arm : Better EFS and MPR.
• Placebo arm : Better OS.
INSIGHT
→ Immune inflammation may reflect favorable tumor biology, not necessarily greater pembrolizumab benefit.
04 WHAT DID TMB REVEAL?
Higher TMB was associated with:
• Pembrolizumab arm : Better EFS, OS, MPR and pCR.
• Placebo arm : Better MPR and pCR.
INSIGHT → Higher TMB was associated with better pathological responses in BOTH arms.
PART 2 → Can biomarkers predict pembrolizumab benefit?
[Slide 3]
KEYNOTE-671 | ESMO 2026
Can Biomarkers Predict Pembrolizumab Benefit?
MV Onco
01 DID T-CELL INFLAMMATION CHANGE BENEFIT?
EFS HR: Pembrolizumab vs placebo
• TcellinfGEP HIGH → 0.53
• TcellinfGEP LOW → 0.71
• Both estimates favored pembrolizumab.
• Higher inflammation showed numerically greater EFS benefit.
• But predictive value was NOT established.
02 DID HIGH TMB CHANGE BENEFIT?
EFS HR: Pembrolizumab vs placebo
• TMB HIGH → 0.49
• TMB LOW → 0.63
• Both estimates favored pembrolizumab.
• Low TMB did NOT eliminate treatment benefit.
• No proven predictive TMB cutoff.
03 DID KRAS STATUS MATTER?
EFS HR: Pembrolizumab vs placebo
• KRAS MUTATED → 0.73
• KRAS WILD-TYPE → 0.75
• Nearly identical hazard ratios.
• KRAS mutation did NOT demonstrate differential pembrolizumab benefit.
• Subgroup numbers were small.
04 CAN BIOMARKERS GUIDE TREATMENT?
PROGNOSTIC ≠ PREDICTIVE
• Prognostic → Indicates likely outcomes.
• Predictive → Identifies differential treatment benefit.
• No biomarker demonstrated validated predictive utility in this exploratory analysis.
TAKE-HOME
• TcellinfGEP, TMB and KRAS cannot currently select who should receive or omit perioperative pembrolizumab.
[Slide 1]
2613O - Primary results of SARON: A randomised-controlled trial of consolidation radiotherapy for synchronous oligometastatic non-small cell lung cancer
Speakers Fiona McDonald (London, United Kingdom)
Lecture Time 10:15 - 10:25
Abstract
Background
Standard first-line systemic anti-cancer therapy (SACT) for advanced non-small cell lung cancer (NSCLC) without actionable genomic alteration (AGA-negative) is chemotherapy and/or immunotherapy. We investigated whether patients with synchronous oligometastatic (OM) AGA-negative NSCLC benefit from the addition of consolidation radiotherapy (RT).
Methods
SARON, a multicentre phase II trial, randomised (1:1) patients with NSCLC, 1–5 metastases in ≤3 organs, to SACT with or without radical RT. The control arm changed to include immunotherapy in January 2020. The experimental arm received radical RT to the lung primary ± locoregional lymph nodes, and stereotactic ablative RT (SABR) to OM sites. Stratification included SACT, histology, N-stage, number of metastases, brain metastases and recruiting site. Primary and major secondary endpoints were overall (OS) and progression-free survival (PFS).
Results
140 patients were randomised across 22 UK centres (October 2016 to July 2023). Median age was 68 years (range 45–85), 59.3% male, 58.6% adenocarcinoma, 52.9% N-stage 2/3, 62.9% 1x OM site (23.6% 2x, 9.3% 3x, 3.6% 4x, 0.7% 5x OM sites), and 6.4% brain metastases. SACT was 40.0% chemotherapy, 15.0% immunotherapy and 45.0% combination. Median SACT cycles received in both arms was 4, and 62/70 (88.6%) received RT (51 conventional and 11 SABR to primary, 54 SABR to ≥1 OM site). After 37.4 months median follow-up, median OS was 31.0 versus 28.0 months (HR=0.99, 95%CI 0.63–1.55, p=0.95) and median PFS 13.9 versus 8.9 months (HR=0.64, 95%CI 0.43–0.95, p=0.03) in the SACT+RT and SACT arms, respectively. The cumulative incidence of local failure within 12 months was 13.0% versus 39.5% (p<0.01), compared to 36.2% versus 32.3% (p=0.28) for new distant metastasis, respectively. The grade ≥3 adverse event rate was 28.6% in both arms; 6 patients had a grade 3 event possibly related to RT. EORTC QLQ-C30 and LC13 quality of life measures were similar in both arms.
Conclusions
Patients with synchronous OM AGA-negative NSCLC receiving first-line SACT+RT achieved better local disease control and longer PFS than SACT alone with acceptable side-effects, however, this did not translate into survival benefit.
[Slide 1]
PERSEE | ESMO 2026
PD-L1 ≥50% NSCLC:
Is Adding Chemo Worth It?
MV Onco
Pembrolizumab
Alone
[illustration of lungs with large tumour]
PFS: 6.9 months
Response: 50%
Severe toxicity: 19%
Pembrolizumab
+ Chemotherapy
[illustration of lungs with smaller tumour]
PFS: 16.1 months
Response: 78%
Severe toxicity: 54% [warning icon]
DID PATIENTS LIVE LONGER?
OS: 50.2 vs 29.9 months
Not statistically significant
TAKE-HOME
✓ MORE CHEMO = BETTER DISEASE CONTROL
✓ BUT MORE TOXICITY
✓ OS BENEFIT NOT PROVEN
[Slide 2]
PERSEE | ESMO 2026
PART 1/3 — PD-L1 ≥50% NSCLC:
Is Pembrolizumab Alone Enough?
MV Onco
01 WHY PERSEE?
Advanced NSCLC | PD-L1 ≥50%
Two established first-line options:
• Pembrolizumab alone
• Pembrolizumab + platinum chemotherapy
THE BIG QUESTION
Does adding chemotherapy improve outcomes enough to justify its toxicity?
No previous definitive head-to-head phase III comparison in this population.
02 TRIAL DESIGN
PERSEE (GFPC 01-2020)
Phase III | Randomized | Open-label
• 321 patients | 28 French centres
• Randomization 1:1
• Median follow-up: 38.7 months
Primary endpoint:
PFS by blinded central review
Secondary endpoints:
OS, ORR, DoR and safety.
03 WHO WERE THE PATIENTS?
Previously untreated advanced NSCLC
• PD-L1 TPS ≥50%
• Stage IV or stage III unsuitable for radiotherapy
• ECOG PS 0–1
• No EGFR/ALK alterations
• Brain metastases: 23.4%
• Squamous histology: 19.6%
• Median age: 64 years.
04 WHAT WAS COMPARED?
ARM A — PEMBRO + CHEMO
Pembrolizumab + platinum doublet × 4 cycles
• Squamous: paclitaxel-based
• Nonsquamous: pemetrexed-based
↓
Maintenance pembrolizumab ± pemetrexed
ARM B — PEMBRO ALONE
Pembrolizumab monotherapy
No upfront chemotherapy.
TAKE-HOME
• PD-L1 ≥50% does not automatically mean chemotherapy is unnecessary.
• PERSEE directly tested whether adding chemotherapy improves outcomes.
• NEXT: Better PFS – But Better Survival?
[Slide 3]
PERSEE | ESMO 2026
PART 2/3 — PD-L1 ≥50% NSCLC:
Does Adding Chemotherapy Improve Survival?
MV Onco
01 DID CHEMOTHERAPY IMPROVE PFS?
Median PFS | Blinded Central Review
Pembro + chemo 16.1 months
Pembro alone 6.9 months
HR 0.56
(95% CI 0.43–0.74)
P < .001
✓ 44% relative reduction in progression/death hazard.
✓ Primary endpoint MET.
02 DID OVERALL SURVIVAL IMPROVE?
Median OS
Pembro + chemo 50.2 months
Pembro alone 29.9 months
HR 0.77
(95% CI 0.57–1.05)
Numerical OS difference: +20.3 months.
[warning icon] No statistically significant OS advantage demonstrated.
03 DID MORE PATIENTS RESPOND?
Objective Response Rate (ORR)
Pembro + chemo 77.5%
Pembro alone 50.3%
Absolute improvement: +27.2 percentage points
Median Duration of Response (DoR)
Pembro + chemo 30 months
Pembro alone 15.6 months
HR 0.86
(95% CI 0.59–1.24)
[warning icon] DoR difference not statistically established.
04 WHAT WAS THE TOXICITY COST?
Grade ≥3 Treatment-Related Adverse Events
Pembro + chemo 53.8%
Pembro alone 19.3%
+34.5 percentage points
[warning icon] Severe treatment-related toxicity was substantially higher with chemotherapy.
TAKE-HOME
Better PFS. Higher Response. More Toxicity.
• Adding chemotherapy significantly improved PFS and ORR.
• An OS advantage remains unproven.
• The decision requires balancing disease control against toxicity.
[Slide 4]
PERSEE | ESMO 2026
PART 3/3 — PD-L1 ≥50% NSCLC:
Who Really Needs Chemotherapy?
MV Onco
01 SHOULD EVERY PATIENT RECEIVE CHEMO?
NO — NOT AUTOMATICALLY.
PERSEE demonstrated:
• Significantly better PFS
• Higher response rate
• No statistically established OS benefit
• Substantially greater severe toxicity
} Better disease control ≠ Proven survival benefit.
02 WHO MAY BENEFIT FROM UPFRONT CHEMO?
Consider Pembro + Chemotherapy
• High tumour burden
• Rapidly progressive disease
• Symptomatic visceral metastases
• Need for rapid tumour shrinkage
• ECOG 0–1 and chemotherapy-fit
} Clinical considerations — not validated predictive subgroups.
03 WHO MAY RECEIVE PEMBRO ALONE?
Consider Pembrolizumab Momotherapy
• Low-volume disease
• Relatively indolent progression
• Minimal cancer-related symptoms
• Higher concern about chemotherapy toxicity
• Strong preference to avoid chemotherapy
} Patient selection remains essential.
04 WHAT QUESTIONS REMAIN?
Important Limitations
• Open-label trial
• OS benefit not statistically demonstrated
• Subsequent treatment may influence OS
• Limited information on predictive subgroups
• ECOG 0–1 population limits generalizability
} Can we identify patients who truly need chemotherapy upfront?
TAKE-HOME
✓ PD-L1 ≥50% Is Not a Chemo-Free Guarantee.
✓ PERSEE supports better disease control with chemoimmunotherapy.
✓ But more treatment ≠ better survival for everyone.
✓ Individualize treatment based on disease aggressiveness, fitness and toxicity.
[Slide 1]
4158RO - Clinicopathological and transcriptomic characteristics of mesotheliomas with MTAP loss: From the NETMESO MESOPATH and RENAPE networks' experience in 1433 pleural and peritoneal mesothelioma
Speakers Sylvie Lantuejoul (Lyon, France)
Lecture Time 11:12 - 11:17
Abstract
Background
The loss of 5 methylthioadenosine phosphorylase (MTAP) is a CDKN2A/B homozygous deletion (HD) surrogate marker in mesothelioma. It has been suggested as a predictive biomarker for PRMT5/MAT2A inhibitors, and as a poor prognostic factor in small series of mesothelioma. We describe here the clinicopathological and transcriptomic characteristics of mesotheliomas with MTAP loss in the largest real-world cohort.
Methods
A total of 1433 mesotheliomas, including 1232 pleural (PM), 201 peritoneal (PeM) mesothelioma and 41 fibroses, were retrieved from the MESOBANK database between 2024 and 2026. All diagnoses were certified by NETMESO-MESOPATH and RENAPE pathologists. MTAP immunohistochemistry was carried out with the RBT-MTAP mAb (BioSB) for all cases, and CDKN2A FISH for 99 cases. Exome RNA sequencing was performed for 203 cases, including 104 with MTAP loss and 99 with MTAP retained.
Results
MTAP cytoplasmic and nuclear staining was lost in 48% PM and 16% of PeM cases, and in 42% Epithelioid (E-PM), 70% Biphasic (B-PM), and 73% Sarcomatoid (S-PM) subtypes (p<0,0001). Nearly 10% of the cases showed heterogeneous MTAP expression. Concordance between MTAP IHC and CDKN2A/B FISH was 80%. In multivariable analyses, MTAP loss was more frequent in males (p=0,001) and older patients (p<0,001). There was no correlation with asbestose exposure, grade or pattern in EM, nor with BAP1 or NF2 alterations. There was no correlation either with survival, except for S-PM with MTAP loss with a better ovserall survival (p=0,0001). Mesothelioma with MTAP under-expressed exhibited low CDKN2A/B, innate and adaptative immunity and fibroblast differentiation gene expressions, and SATB2, WNT and TGFbeta pathways' overexpression.
Conclusions
MTAP IHC is an easy interpretable and reliable marker with a concordance of 80% with CDKN2A/B HD. MTAP loss predominates in the pleural M, and in BM and SM subtypes. It does not correlate with survival, except in S-PM where MTAP loss is associated with a better survival.
[Slide 1]
ESMO 2026
BARCELONA | 24 – 28 OCTOBER 2026
SAFFRON TRIAL
Osimertinib + Savolitinib after Osimertinib Resistance in EGFR-mutant Non-Small Cell Lung Cancer
A TARGETED SOLUTION FOR MET-MEDIATED RESISTANCE
1. BACKGROUND & RATIONALE
• Osimertinib is standard first-line therapy for EGFR-mutant NSCLC, but most patients ultimately develop resistance.
• MET amplification or overexpression is a common mechanism of acquired resistance (≈ 10–20%).
• Dual inhibition of EGFR and MET may overcome this resistance.
Initial response to osimertinib
EGFR mutation (eg. exon 19 del, L858R) EGFR Osimertinib Tumour cell survival inhibited
Acquired resistance: MET activation
EGFR MET amplification or overexpression MET Osimertinib MET signalling bypasses EGFR inhibition Tumour cell proliferation and survival
Dual targeting strategy
Osimertinib (EGFR TKI) + Savolitinib (MET inhibitor) EGFR MET Dual blockade suppresses tumour growth
MET alterations in osimertinib resistance
[pie chart] MET [illegible] 10–15% Other mechanisms 60–70% MET amplification 5–10%
MET-driven resistance occurs in ~10-20% of patients progressing on osimertinib
2. TRIAL DESIGN
Trial name: SAFFRON
Phase: Phase III
Registry: NCT05261399
Design: Randomised, open-label, multicentre, global
Population: Locally advanced or metastatic EGFR-mutant NSCLC progressing on osimertinib with MET amplification or overexpression
Sample size: ~345 patients
Primary endpoints: Progression-free survival (PFS) and overall survival (OS)
Key secondary endpoints: Objective response rate (ORR), safety, duration of response
3. PATIENT ELIGIBILITY (KEY CRITERIA)
Inclusion criteria (example)
• EGFR-mutant NSCLC (eg. exon 19 del, L858R)
• Radiological progression on osimertinib
• Evidence of MET overexpression and/or MET amplification (as per trial assay)
• Measurable disease (RECIST 1.1)
• Adequate organ function
• ECOG 0–1 (typical)
Key exclusion criteria (example)
• Concurrent targetable alterations requiring alternative therapy
• Prior MET inhibitor therapy
• Symptomatic or uncontrolled CNS metastases
• Significant comorbidities
4. TREATMENT ARMS
A. Osimertinib + Savolitinib
Osimertinib 80 mg once daily (standard dose)
+
Savolitinib 300 mg once daily (typical dose used in trial)
B. Platinum-based chemotherapy (Investigator's choice)
Platinum + pemetrexed (± maintenance pemetrexed) or other platinum doublet as per protocol
5. ENDPOINTS
Primary endpoints
• Progression-free survival (PFS)
• Overall survival (OS)
Secondary endpoints
• Objective response rate (ORR)
• Duration of response
• Disease control rate (DCR)
• Safety and tolerability
• Quality of life (may be included)
6. KEY RESULTS
The SAFFRON trial has been reported to meet its primary endpoints of PFS and OS compared with platinum-based chemotherapy in patients with MET-altered EGFR-mutant NSCLC after osimertinib progression.
Detailed numerical results (median PFS, median OS, hazard ratios, confidence intervals, subgroup analyses and toxicity) will be presented at ESMO 2026.
7. SAFETY PROFILE (EXPECTED)
Common adverse events with savolitinib (in addition to osimertinib toxicities)
• Peripheral oedema • Nausea, diarrhoea • Increased creatinine • Proteinuria • Fatigue • Anemia
Known osimertinib adverse events
• Rash • Diarrhoea • QT prolongation • Interstitial lung disease (rare)
8. POTENTIAL ADVANTAGES
• Targets a defined resistance mechanism (MET-driven)
• Oral targeted combination
• May delay need for chemotherapy
• Maintains EGFR inhibition
• Potential for better PFS and OS compared to chemotherapy (as reported)
9. KEY QUESTIONS
• Magnitude of PFS and OS benefit
• Which MET alterations derive the most benefit (amplification vs overexpression)
• Assay used for MET detection and positivity threshold
• Intracranial efficacy
• Toxicity profile and dose modifications
• Sequencing with other targeted options
• Applicability to Indian and global patient populations
10. CLINICAL IMPLICATIONS
• Potential to establish a biomarker-directed treatment option after osimertinib in MET-altered EGFR-mutant NSCLC.
• Should be used only in patients with confirmed MET amplification or overexpression as per trial criteria.
• May change the treatment algorithm if a clinically meaningful OS benefit is confirmed.
• Final adoption will depend on full data, regulatory approval, availabilty and local guidelines.
Take Home Message: SAFFRON represents a promising targeted strategy to address MET-mediated resistance after osimertinib in EGFR-mutant NSCLC. Await full ESMO 2026 presentation for detailed efficacy and safety results.
Credit: Dr Rohit Malde MD DNB FRCR (UK) | CONSULTANT CLINICAL ONCOLOGIST
[Slide 1]
2636RO - Characterizing resistance mechanisms and predictors of early progression and long-term response to lorlatinib: Circulating tumor DNA (ctDNA) analyses from the CROWN study
Speakers Ben J. Solomon (Melbourne, Australia)
Lecture Time 09:05 - 09:10
Abstract
Background
In the phase 3 CROWN study (NCT03052608), lorlatinib showed unprecedented progression-free survival (PFS) benefit in patients (pts) with previously untreated advanced ALK+ NSCLC, with median PFS not reached after 7 y of follow-up. Despite durable outcomes, a minority of pts (≈20%) experienced disease progression or death within 1 y of treatment. We analyzed ctDNA from pts in CROWN to identify potential resistance mechanisms and predictors of early progression and long-term response to lorlatinib.
Methods
296 pts were randomized 1:1 to lorlatinib 100 mg QD or crizotinib 250 mg BID. In the lorlatinib arm (n=149), blood samples collected at baseline (BL; n=120) and end of treatment from pts with progression (EOT; n=18) were used for ctDNA analyses (Guardant Infinity). Early progressors (EPs) are pts with PFS events at ≤1 y; long-term responders (LTRs) are pts without PFS events at 7 y. Analyses included characterization of resistance mechanisms at EOT; comparisons of BL genomic alterations in EPs and LTRs, and between pts with and without intracranial (IC) progression; and efficacy analyses by longitudinal assessment of methylation-based tumor fraction (TF).
Results
Analyses of paired BL and EOT ctDNA samples (n=17) revealed no new ALK resistance mutations and showed that bypass (RTK/RAS/MAPK) and other cancer-related pathways, eg, inflammatory response and angiogenesis pathway, may lead to resistance to lorlatinib. BL ctDNA analyses showed more genomic alterations in EPs than LTRs (median 10 vs 6). FGFR4, DICER1, and ARAF genomic alterations were more frequent in pts with vs without IC progression (25-38% vs ≤3%). BL TF level was prognostic for PFS. On-treatment decrease in TF at wk 4 and wk 24 was associated with longer PFS. Additional pathway analyses in EPs will be presented.
Conclusions
ctDNA analyses from CROWN suggest lorlatinib resistance is primarily mediated through bypass pathway and other potential tumorigenic inflammatory and angiogenic mechanisms rather than on-target ALK mutations. BL genomic complexity and on-treatment changes in methylation-based TF may help identify pts at risk of early progression.
[Slide 1]
2652RO - First-line (1L) olomorasib + chemoimmunotherapy (chemo-IO) in KRAS G12C-mutant NSCLC: Updated results from the LOXO-RAS-20001 and SUNRAY-01 trials
Speakers Marcelo V. Negrao (Houston, United States of America, SP)
Lecture Time 09:19 - 09:24
Abstract
Background
Olomorasib, a potent, selective next-generation KRAS G12C inhibitor with CNS activity, has demonstrated promising efficacy and durability in patients (pts) with advanced KRAS G12C-mutant NSCLC in combination with chemo-IO, the current 1L standard of care (SOC) for pts with NSCLC and PD-L1 expression 0-100%. Here, with an additional 9 mo of follow-up, we report updated results in 1L pts from LOXO-RAS-20001 and the SUNRAY-01 safety lead-in.
Methods
Pts with advanced KRAS G12C-mutant NSCLC, PD-L1 0-100%, and ECOG PS 0-1 received olomorasib 50 or 100 mg orally BID with pembrolizumab + chemotherapy (per label). Pts who received one cycle of SOC prior to enrollment were eligible. Safety was the primary endpoint. Key secondary endpoints were ORR per RECIST v1.1, DOR, and PFS.
Results
As of 5 March 2026, 77 pts received olomorasib + chemo-IO; 25 pts (32%) received 1 prior cycle of SOC; PD-L1 expression: 34% were <1%, 40% were 1-49%, and 23% were ≥50%, (3% unknown). Median follow-up was 18.7 mo (IQR, 16.8-20.3). ORR was 61% (47/77), with a median DOR of 14.5 mo and median PFS of 11.8 mo (Table). Efficacy by PD-L1 expression is shown in the Table. No new safety signals were identified. Any grade TRAEs (≥20% of pts) were nausea (44%), anemia (39%), fatigue (39%), diarrhea (32%), and AST/ALT increased (31%/27%). The most common grade ≥3 TRAEs were anemia (16%), neutrophil count decreased (12%), and ALT/AST increased (12%/10%). TRAEs were manageable with supportive care, dose adjustments, and/or corticosteroids. TRAEs led to olomorasib dose reduction in 21% of pts; and discontinuation of all study treatment in 8% of pts. Table: 2652RO
Response and time-to-event endpoints (efficacy evaluable pts)
Endpoint | Olomorasib (50 or 100 mg BID) + Chemo-IO All pts* PD-L1 0-100% N = 77 | Pts with PD-L1 <1% n = 26 | Pts with PD-L1 1-49% n = 31 | Pts with PD-L1 ≥50% n = 18
ORR**,†, % (n/N) | 61 (47/77) | 50 (13/26) | 68 (21/31) | 67 (12/18)
BOR, n (%)
PR† | 47 (61) | 13 (50) | 21 (68) | 12 (67)
SD | 19 (25) | 8 (31) | 7 (23) | 4 (22)
PD | 3 (4) | 2 (8) | 0 (0) | 0 (0)
NE | 6 (8) | 3 (12) | 2 (6) | 1 (6)
DCR, % (n/N) | 88 (68/77) | 81 (21/26) | 94 (29/31) | 94 (17/18)
mDOR**, mo (95% CI) | 14.5 (10.3 - NE) | 14.4 (5.6 - NE) | NE (8.5 - NE) | NE (6.1 - NE)
mPFS**, mo (95% CI) | 11.8 (9.6 - 21.5) | 9.7 (5.9 - 15.9) | 12.1 (5.9 - NE) | NE (7.7 - NE)
*PD-L1 status unknown for 2 pts **ORR per RECIST v1.1, DOR, and PFS were investigator assessed †Confirmed responses.
Conclusions
Olomorasib + chemo-IO continues to demonstrate durable efficacy and a manageable safety profile across PD-L1 levels, including in higher-risk pts with PD-L1 0-49%. These updated findings support the ongoing phase 3 SUNRAY-01 trial comparing 1L chemo-IO + olomorasib or placebo in pts with KRAS G12C-mutant NSCLC and PD-L1 0-100%.
[Slide 1]
ESMO 2026
ORAL PRESENTATIONS
LUNG CANCER
FPN: 2652P
RAPID ORAL
First-line (1L) Olomorasib + Chemoimmunotherapy (Chemo-IO) in KRAS G12C-Mutant NSCLC: Updated Results from the LOXO-RAS-20001 and SUNRAY-01 Trials
Rapid oral 2: NSCLC, metastatic
Presenter: Marcelo Negrao
October 25 | Barcelona Auditorium - Hall 9 | 8:30 AM - 10:00 AM
Intended for HCPs only
Lilly A MEDICINE COMPANY
[Slide 1]
2658RO - Overall survival (OS) analysis of telisotuzumab adizutecan in patients (pts) with nonsquamous non-small cell lung cancer (NSQ NSCLC): Phase 1 first-in-human study
Speakers David Sommerhalder (San Antonio, United States of America)
Lecture Time 09:27 - 09:32
Abstract
Background
c-Met (or MET) protein is highly expressed in NSCLC and has a poor prognosis. Telisotuzumab adizutecan (ABBV-400; Temab-A) is an antibody drug conjugate (ADC) consisting of an anti c-Met antibody conjugated to a Top1i payload. In an ongoing phase 1 study (NCT05029882), Temab-A showed promising efficacy and manageable safety in pts with NSQ NSCLC. Herein, we present OS for pts with NSQ NSCLC.
Methods
Enrolled pts with advanced EGFR wildtype (WT) or mutant (MUT) NSQ NSCLC that progressed after platinum-based chemotherapy and immune checkpoint or targeted therapy received Temab-A once every 21 days. Primary endpoint was confirmed investigator-assessed objective response rate (ORR) per RECIST v1.1. Secondary endpoints included duration of response (DOR), progression-free survival (PFS) and OS. Tumor tissue c-Met protein expression was retrospectively assessed by IHC via central laboratory.
Results
The EGFR WT cohort enrolled 48 pts (median follow-up: 27 months [mo]; median prior lines of therapy [LoT] 2 [range, 1–9]) and the EGFR MUT cohort enrolled 41 pts (median follow-up: 26 mo; median prior LoT: 3 [1–8]). Most pts received 2.4 mg/kg dose (EGFR WT: 81%, 39/48; EGFR MUT: 88%, 36/41); the remaining received 3.0 mg/kg. Median duration of treatment was 5.6 and 10 mo in the EGFR WT and EGFR MUT cohorts, respectively. Median OS for EGFR WT and EGFR MUT was 13.8 mo and 16.2 mo (Table). Among EGFR WT patients, the prevalence of c-MET expression ≥3+ staining intensity in ≥10% and ≥25% tumor cells was 43% (20/46) and 33% (15/46), respectively. Among EGFR MUT patients, it was 56% (19/34) and 41% (14/34), respectively. Median OS was longer in EGFR WT pts with c-MET above these thresholds (≥3+, ≥10%: 25.2 mo; ≥3+, ≥25%: 19.2 mo). No new safety signals were observed. Table: 2658RO
[columns: EGFR WT — Total N=48^a | ≥3+, ≥10% n=20^b | ≥3+, ≥25% n=15^b ; EGFR MUT — Total N=41^c | ≥3+, ≥10% n=24^b | ≥3+, ≥25% n=19^b]
ORR, n (%) | 24 (50) | 12 (60) | 9 (60) | 26 (63) | 17 (71) | 13 (68)
Median DOR, mo (95% CI) | 5.6 (4.2–12.3) | 5.6 (3.8–12.4) | 6.3 (2.8–21.8) | 9.7 (8.3–12.4) | 9.9 (6.9–13.5) | 10.9 (8.3–14.3)
Median PFS, mo (95% CI) | 6.8 (5.4–7.3) | 7.2 (5.5–9.0) | 8.0 (5.3–9.8) | 10.9 (8.3–12.3) | 11.0 (9.4–12.6) | 12.2 (9.6–14.7)
Median OS, mo (95% CI) | 13.8 (9.0–25.2) | 25.2 (7.5–NE) | 19.2 (7.1–NE) | 16.2 (11.6–19.9) | 15.6 (10.6–19.6) | 16.2 (10.6–21.0)
^a3.0 mg/kg (n=9). ^bAvailable IHC. ^c3.0 mg/kg (n=5). DOR, duration of response; IHC, immunohistochemistry; mo, months; NE, not estimable; ORR, objective response rate.
Conclusions
Temab-A exhibited promising OS in a heavily pretreated NSCLC population. OS rates compared favorably to those reported in the same indications with chemotherapy or other ADCs.
[Slide 1]
3837RO - ABBV-706: A first-in-class SEZ6-targeted topoisomerase 1 inhibitor (Top1i)-antibody-drug conjugate (ADC) with robust antitumour activity in relapsed/refractory small cell lung cancer (R/R SCLC)
Speakers Anne C. Chiang (New Heaven, United States of America)
Lecture Time 10:15 - 10:20
Abstract
Background
SEZ6 exhibits higher expression on SCLC cells than other SCLC therapeutic targets. ABBV-706 is a SEZ6-targeted ADC that selectively delivers a potent, cytotoxic Top1i payload (adizutecan) to SEZ6-expressing tumour cells. Phase (Ph) 1 results of ABBV-706 monotherapy in R/R SCLC (NCT05599984), including biomarker-response associations and ABBV-706 preclinical activity, are presented.
Methods
Archival tumour tissue was collected at baseline for immunohistochemistry (IHC) and RNA-Seq. Serum neuroendocrine proGRP and circulating tumour DNA (ctDNA) were assessed longitudinally. Binding and trafficking of SEZ6 on normal lung alveolar and SCLC cell lines were determined by flow cytometry and high content imaging. Adizutecan potency and activity was assessed in vitro; RNA-Seq was performed on SCLC cells.
Results
As of Sept 27, 2025, 124 patients (pts) with R/R SCLC received ABBV-706. Among pts with second-line plus (2L+) R/R SCLC who received the recommended Ph 3 dose of 1.8 mg/kg Q3W in Part 2a dose optimization (n=41), an objective response rate (ORR) of 56% and median overall survival (mOS) of 12.4 months (mo) was observed. In a subset with 2L R/R SCLC (n=17), ORR was 82% and mOS was 14.3 mo. Among 2L+ R/R SCLC, safety was comparable with prior data. ABBV-706 drove rapid declines in ctDNA and proGRP as early as cycle (C) 2 day (D) 1. At C3D1, 100% ctDNA clearance was associated with improved progression-free survival and OS. SEZ6 IHC expression was highly prevalent (93% above a 1% [1+ cutoff]), stable across therapy lines, and similar in responders and non-responders. SEZ6 was absent on human normal alveolar lung cells. Preclinically, SEZ6 antibody showed minimal binding and lysosomal trafficking in normal human pulmonary alveolar epithelial cells; significant trafficking in SEZ6-expressing SCLC cells was observed. Adizutecan potently reduced viability and increased expression of MHC-I, PD-L1, and key immune pathways in SCLC cell lines.
Conclusions
ABBV-706 monotherapy shows promising clinical benefit in heavily pretreated R/R SCLC with biomarker and preclinical data reinforcing its selective, differentiated, and potent antitumour profile.
[Slide 1]
2661RO - Results of a multicenter, phase II, open-label, randomized trial evaluating OSE2101 plus docetaxel or OSE2101 plus nivolumab as second-line therapy in metastatic non-small cell lung cancer (NSCLC) progressing after first-line chemo-immunotherapy
Speakers Federico Cappuzzo (Rome, Italy)
Lecture Time 08:52 - 08:57
Abstract
Background
OSE2101 is a neo-epitope vaccine designed to induce antigen-specific cytotoxic T lymphocyte responses in HLA-A2 positive patients. Prognosis after progression following first-line chemo-immunotherapy for metastatic NSCLC remains poor. Combi-TED evaluated OSE2101 combined with docetaxel or nivolumab in this setting.
Methods
Adults with metastatic/unresectable HLA-A2 positive NSCLC, without actionable EGFR mutations or ALK/ROS1 rearrangements, progressing after at least 4 cycles of chemo- immunotherapy or 2 cycles of chemo-immunotherapy followed by 2 cycles of immunotherapy, were randomized (1:1:1) to OSE2101+docetaxel (O+D), OSE2101+nivolumab (O+N), or docetaxel alone (D). Primary endpoint was 1-year overall survival (OS). Secondary endpoints included OS, progression-free survival (PFS), and safety. A one-sided exact binomial test evaluated whether 1-year OS exceeded the predefined 20% threshold. Bayesian analyses assessed the probability of improved 1-year OS versus D. Final results will be available in SEP2026.
Results
At the cut-off date (30MAR2026), 106 patients were randomized (35 in T+D, 34 in T+N, and 29 in D) and 93 reached 1-year of follow-up. 1-year, OS rates are 15/34: 44% (90% confidence interval [CI], 30–60) for O+D, 14/32: 44% (CI, 29–60) for O+N, and 7/27: 26% (CI, 13–43) for D. The statistical significance is confirmed for O+D (p=0.001), O+N (p=0.002), but not for D (p=0.287). Bayesian analyses suggested posterior probability >90% of improved 1-year survival versus docetaxel alone for both OSE2101-based combinations. Treatment-related adverse events occurred in 89%, 82%, and 79% of patients. Drug-related serious adverse events were reported in 17%, 24%, and 17% of patients. No unexpected safety signals were observed.
Conclusions
OSE2101-based combinations showed improved 1-year overall survival compared with docetaxel alone in metastatic NSCLC progressing after first-line chemo-immunotherapy, without increasing toxicity, supporting further evaluation of vaccine-based immunotherapy strategies in this setting.
[Slide 1]
2631RO - First-line BAT8008 (TROP2-ADC) plus BAT1308 (anti-PD-1) for advanced NSCLC: Results from a multicenter phase 2 study
Speakers Shao Dong Hong (Guangzhou, China)
Lecture Time 09:22 - 09:27
Abstract
Background
TROP2 ADC–immunotherapy combinations are being actively explored as first-line (1L) therapy for patients (pts) with advanced NSCLC, but payload-related myelosuppression and target-associated stomatitis remain key tolerability concerns that may compromise clinical benefit. BAT8008 is a novel exatecan-based TROP2 ADC with a stable cleavable PEG8 linker and DAR of ~6, engineered to widen the therapeutic window. We report preliminary efficacy and safety of BAT8008 plus BAT1308, an anti-PD-1 antibody, as 1L therapy in NSCLC.
Methods
This multicenter, open-label, single-arm phase 2 trial enrolled treatment-naïve pts with advanced NSCLC. Pts received BAT8008 (2.4 mg/kg) and BAT1308 (200 mg) intravenously once every 2 weeks. Primary endpoints included safety and objective response rate (ORR).
Results
As of April 28, 2026, 97 patients were enrolled (median age 64 years; 53.6% with squamous histology; 89% with ECOG PS 1). Treatment-related adverse events (TRAEs) occurred in 87.6%, with grade (G) ≥3 TRAEs in 38.1% of pts. Despite the high DAR, severe (≥G3) stomatitis and hematological toxicities were relatively uncommon: anemia (7.2%), stomatitis (7.2%), leucocytopenia (14.4%) and neutropenia (15.5%). No new immune-related safety signals were observed. Among 76 efficacy-evaluable pts, ORR was 57.9%, disease control rate (DCR) was 89.5%, and 6-mo progression-free survival (PFS) rate was 64.8%. Antitumor activity was observed across PD-L1 subgroups and histologies (Table). Updated results, including PFS and safety data will be presented at the conference. Table: 2631RO
Anti-tumor activity stratified by PD-L1 expression and histology
Variables | TPS unknown | TPS <1% | TPS 1-49% | TPS ≥50% | Squamous | Nonsquamous
n | 3 | 36 | 19 | 18 | 39 | 37
ORR (%) | 67 | 47 | 53 | 83 | 56 | 59
DCR (%) | 100 | 86 | 89 | 94 | 92 | 86
6-mo PFS (95% CI), % | 100.0 (100.0-100.0) | 46.7 (31.5-69.4) | 76.9 (59.1-100.0) | 80.4 (62.4-100.0) | 61.9 (47.1-81.3) | 68.0 (53.6-86.1)
Conclusions
BAT8008 plus BAT1308 showed clinically meaningful activity with manageable toxicity in advanced NSCLC. The findings support the planned randomized evaluation of this regimen and suggest a potentially favorable activity–toxicity balance for prolonged IL combination therapy.
[Slide 1]
ESMO 2026 / MADRID
EVIDENCE NOTES
23–27 OCT 2026 MADRID, SPAIN
PRESIDENTIAL SYMPOSIUM II / LBA5
KRAScendo 1
DIVARASIB BEATS SOTORASIB/ADAGRASIB ON PFS AND INTERIM OS
Previously treated KRAS G12C-mutant advanced/metastatic NSCLC
25 OCT 2026, Sunday 16:30 Madrid | 18:30 TSİ
Presenter To be confirmed
✓ PFS superior ✓ Interim OS significant ✓ Effect size pending
01 PATIENTS
• Previously treated locally advanced or metastatic non-small cell lung cancer (NSCLC)
• KRAS G12C mutation positive
02 ARMS
Divarasib — Orally once daily (KRAS G12C inhibitor)
↔
Active comparator — Sotorasib Orally once daily OR Adagrasib Orally twice daily
Phase 3 | Randomized | Open-label | Global multicenter | n = 338 1:1
03 KNOWN NOW
• Primary endpoint of BICR-assessed PFS favored divarasib.
• Prespecified interim OS analysis was statistically significant.
• No new safety signals reported in the topline release.
04 NOT YET DISCLOSED
• Hazard ratios and 95% CIs
• Median PFS and median OS
• Absolute survival differences
• ORR and duration of response
• Detailed grade 3+ toxicity and discontinuation rates
• Distribution of sotorasib vs adagrasib in the active-control arm
05 CLINICAL READOUT
The key question is magnitude, not positivity: against a strong active-control arm, how large are the PFS/OS gains, and do they justify toxicity and daily treatment burden?
This is a direct within-class randomized comparison; do not compare earlier phase 1 medians head-to-head.
Data status: Company topline + ESMO 2026 programme; full LBA5 presentation pending.
Sources: drozdogan.com; Genentech/Roche topline, 1 Jul 2026; KRAScendo 1 / NCT06497556; ESMO 2026 programme.
drozdogan.com
[Slide 1]
ESMO 2026 - Conference Cal...
cslide.ctimeetingtech.com
Proffered Paper session
Results
As of April 2, 2026, 149 pts were enrolled (40 colorectal cancer [CRC], 40 gastric cancer [GC], 27 lung squamous cell carcinoma [SQCC], 23 lung adenocarcinoma [LUAD], and 19 other solid tumors). No dose limiting toxicity occurred. Maximum tolerated dose was not reached. Treatment-related adverse events (TRAEs) occurred in 137 (91.9%) pts, of whom 76 (51.0%) were grade ≥3. TRAEs with incidence >20% were anemia (33.6%), and aspartate aminotransferase increased (21.5%). Twenty-five (16.8%) pts discontinued any of the study treatment due to TRAEs. TRAEs leading to death occurred in 5 (3.4%) pts. Efficacy for these cohorts in the efficacy-evaluable set was shown in the table. CCR8-positive was defined as tumor-associated positive immune cell count proportion ≥1. Table: 1949O
Efficacy in advanced solid tumors
| | Total | GC | CRC | SQCC | LUAD |
| ORR across all dose level, % | 23.0% (N=135) | 18.4% (N=38) | 23.5% (N=34) | 24.0% (N=25, all received prior immunotherapy) | 23.8% (N=21) |
| ORR at 500 mg, % | 27.1% (N=70) | 19.0% (N=21) | 36.4% (N=11) | 41.7% (N=12) | 15.4% (N=13) |
| ORR at 500 mg who had positive CCR8 expression, % | 37.8% (N=45) | 23.5% (N=17) | 50.0% (N=8) | 83.3% (N=6) | 16.7% (N=6) |
[Red hand-drawn arrow pointing at the SQCC column and a red box around the CRC 50.0% (N=8) and SQCC 83.3% (N=6) cells]
[Slide 2]
#ESMO26 KEY PRESENTATIONS
Rapid Oral 283RO
Assessing bemarituzumab in patients with advanced gastric and gastroesophageal junction cancer by fibroblast growth factor receptor 2 (FGFR2) amplification status in the FORTITUDE study, which suggests that FGFR2 amplification may identify a more treatment-sensitive subgroup.
Friday, Oct 23, 2026
Location: Almeria Auditorium - Hall 9
Session: 4:15-5:45pm
Presentation: 5:19-5:24pm
Rapid Oral LBA73
Evaluating ctDNA-guided treatment intensification in untreated advanced or metastatic EGFR-mutant non-small cell lung cancer (NSCLC) to identify patients who may benefit from intensified first-line therapy in the PACE-LUNG study—a multicenter, Phase II trial of additional chemotherapy for patients with persistent EGFR-mutant ctDNA in plasma at Week 3 after starting first-line osimertinib.
Saturday, Oct 24, 2026
Location: Almeria Auditorium - Hall 9
Session: 8:30-10:00am
Presentation: 8:30-8:35am
Rapid Oral 263RO
Characterizing resistance mechanisms and predictors of early progression and long-term response to lorlatinib from the CROWN study. Findings suggest that baseline genomic complexity and on-treatment changes in methylation-based tissue-free assays may help identify patients at risk of early progression.
Saturday, Oct 24, 2026
Location: Almeria Auditorium - Hall 9
Session: 8:30-10:00am
Presentation: 9:05-9:10am
Poster 4403P
Using serial Guardant360 Liquid testing in a Phase 2 study with MD Anderson to examine clonal and subclonal resistance during anti-EGFR rechallenge in metastatic colorectal cancer to distinguish genuine resistance evolution from changes caused by fluctuating ctDNA levels, potentially improving patient selection for anti-EGFR rechallenge.
Friday, Oct 23, 2026
Session: 3:15-4:00pm
Poster 2566P
Exploring post-surgical MRD and pathological complete response (pCR) after perioperative nivolumab in resectable Stage III NSCLC. In this exploratory analysis from NADIM II, pCR was associated with MRD negativity and excellent 5-year survival. In non-pCR patients, MRD negativity identified patients with favorable long-term outcomes, whereas detectable MRD defined a high-risk subgroup with early recurrence.
Monday, Oct 26, 2026
Session: 12:00-12:45pm
[blue carousel back-arrow icon at right edge]
[Slide 1]
#ESMO26 · PUBLISHED TOPLINE
DeLLphi-305
LBA3
Presidential Symposium I
Sat Oct 24 · 17:18 CEST
Tarlatamab + durvalumab vs durvalumab
1L maintenance in ES-SCLC without progression after durvalumab + platinum–etoposide
DESIGN
• Phase 3, randomized 1:1, open-label, global
• N = 563
• Treated and untreated asymptomatic brain mets allowed
• Monitoring 1–2 h after C1D1 and C1D8 tarlatamab (6–8 h in some regions incl. Europe)
• Primary: OS · Secondary: PFS, ORR
PUBLISHED TOPLINE
OS Met at prespecified interim (primary)
PFS Significant improvement (secondary)
ORR Significant improvement (secondary)
"statistically significant and clinically meaningful improvement in overall survival ... compared to durvalumab alone"
No hazard ratios, medians or response rates disclosed yet. Full results at ESMO.
Source: Amgen press release, 8 Sep 2026 (AstraZeneca release same day). Sponsor: Amgen, partial funding by AstraZeneca.
Dr. Aakash Desai | @ADesaiMD
[Slide 1]
#ESMO26 · PUBLISHED TOPLINE
SAFFRON
LBA6
Presidential Symposium II
Sun Oct 25 · 16:54 CET
Osimertinib + savolitinib vs platinum–pemetrexed
EGFRm NSCLC, MET-overexpressed and/or amplified, after osimertinib
DESIGN
• Phase 3, randomized, open-label, global
• N = 338; 230 centers, 29 countries
• Savolitinib 300 mg BID + osimertinib 80 mg QD vs platinum doublet
• Progression on 1L or 2L osimertinib; high MET cutoffs (IHC/FISH) from SAVANNAH
• Primary: PFS · Key secondary: OS, ORR
PUBLISHED TOPLINE
PFS Met (primary endpoint)
OS Met (key secondary)
Safety No new safety findings
"statistically significant and clinically meaningful improvement in both PFS and OS versus doublet platinum-based chemotherapy"
No hazard ratios, medians or response rates disclosed yet. Full results at ESMO.
Source: AstraZeneca and HUTCHMED press releases, 17 Aug 2026 (high-level results). Design details: same releases.
Dr. Aakash Desai | @ADesaiMD
[Slide 1]
Optimizing the NSCLC Treatment Landscape: Impact for Today and Insights for Tomorrow
A Bristol Myers Squibb Sponsored Industry Satellite Symposium at the ESMO Congress 2026
Friday, 23 October 2026 | 9:45 – 11:15 AM CEST
Madrid Auditorium, Hall 4, IFEMA Madrid
Bristol Myers Squibb
Mariano Provencio, MD, PhD
Hospital Universitario Puerta de Hierro
Madrid, Spain
Antonio Passaro, MD, PhD
Istituto Europeo di Oncologia IRCCS
Milan, Italy
Enriqueta Felip, MD, PhD
Vall d'Hebron University Hospital
Vall d'Hebron Institute of Oncology
Universitat Autònoma de Barcelona
Autonomy, Spain
Marcia K. Horn, JD
International Cancer Advocacy Network (ICAN)
Phoenix, AZ, USA
Speakers are paid consultants of Bristol Myers Squibb
This satellite symposium is not eligible for CME credits.
[Slide 1]
Dr. Aakash Desai
Associate Director, Phase 1 and Precision Oncology
@ADesaiMD
My Top Picks for ESMO 2026!
CLINICAL REVIEW
ESMO Congress 2026 · Madrid · Oct 23–27 · Thoracic phase 3 readouts and early-phase ADCs, ranked
7 | 2658RO | c-Met ADC
Temab-A
Telisotuzumab adizutecan: c-Met-directed ADC with a Top1i payload
Phase 1 first-in-human study, overall survival analysis in nonsquamous NSCLC
Rapid Oral 1: NSCLC, metastatic
Sat Oct 24 · 09:27 CEST
AbbVie reports:
EGFR wild-type (n=48): ORR 50%, median OS 13.8 mo
EGFR-mutant (n=41): ORR 63%, median OS 16.2 mo
EGFR wild-type, c-Met 3+ ≥25%: median OS ~19.2 mo
Watching: Does c-Met expression level select who benefits? Phase 3 AndroMETa-Lung-167 vs standard of care is underway.
1 | LBA6 | EGFR + MET
SAFFRON
Osimertinib + savolitinib vs platinum–pemetrexed
EGFRm, MET-overexpressed and/or amplified NSCLC after osimertinib
Presidential Symposium II
Sun Oct 25 · 16:54 CET
Sponsor topline: PFS and OS met (AstraZeneca / HUTCHMED)
Watching: How large is the benefit, and which MET IHC/FISH cutoff selects patients?
2 | LBA3 | DLL3×CD3
DeLLphi-305
Tarlatamab + durvalumab vs durvalumab
1L maintenance in ES-SCLC after durvalumab + platinum–etoposide
Presidential Symposium I
Sat Oct 24 · 17:18 CEST
Sponsor topline: OS met at interim; PFS and ORR also met (Amgen)
Watching: How big is the OS gain, and can clinics deliver T-cell engager monitoring in maintenance?
3 | LBA5 | KRAS G12C
Krascendo 1
Divarasib vs sotorasib or adagrasib
Previously treated KRAS G12C-mutated advanced NSCLC
Presidential Symposium II
Sun Oct 25 · 16:30 CET
Sponsor topline: PFS met; OS significant at interim (Roche)
Watching: How wide is the gap within the G12C class, and at what tolerability?
4 | LBA66 | TROP2 ADC
OptiTROP-Lung06
Sac-TMT + pembrolizumab vs chemo + pembrolizumab
1L PD-L1-negative (TPS <1%) nonsquamous NSCLC
Proffered Paper 1: NSCLC, metastatic
Sun Oct 25 · 10:53 CET
Sponsor topline: PFS met at interim; positive OS trend (Kelun-Biotech)
Watching: Can a TROP2 ADC replace the platinum doublet alongside IO?
5 | LBA71 | EGFR×HER3
PANKU-Lung01
Iza-bren (bispecific ADC) vs platinum–pemetrexed
EGFR-mutant nonsquamous NSCLC after a 3rd-gen EGFR TKI
Proffered Paper 2: NSCLC, metastatic
Mon Oct 26 · 09:14 CET
Sponsor topline: PFS met at interim (Sichuan Biokin)
Watching: First effect sizes: how big is the PFS gain, and at what toxicity?
6 | 3837RO | SEZ6 ADC
ABBV-706
SEZ6-directed Top1i ADC, phase 1
Relapsed/refractory SCLC
Rapid Oral: Non-metastatic NSCLC and other thoracic
Mon Oct 26 · 10:15 CET
AbbVie reports: ORR 56%, median OS 12.4 mo at 1.8 mg/kg (2L+, n=41)
Watching: Where does SEZ6 fit next to DLL3 and B7-H3 in SCLC?
Key Clinical Impacts & Future Directions
• After osimertinib: MET (SAFFRON), TROP2 (OptiTROP-Lung04 final OS, LBA67) or EGFR×HER3 (PANKU-Lung01): which patients get which next step?
• ES-SCLC: Does tarlatamab move into 1L maintenance, and how does that reshape later lines (DLL3, SEZ6, B7-H3)?
• KRAS G12C: Does a next-generation inhibitor reset the second-line standard?
• 1L PD-L1-negative: Can an ADC replace platinum chemotherapy alongside pembrolizumab?
• Biomarkers: MET IHC/FISH, c-Met level, SEZ6: which assays will we need at diagnosis and at progression?
• Phase 1 to phase 3: Will early ADC signals hold up against standard of care?
Times are Madrid local (CEST on Oct 24; CET from Oct 25). Toplines are as stated in sponsor releases; full data pending. Not medical advice.
Source: ESMO 2026 Congress program | Design: Dr. Aakash Desai
[Slide 1]
Aulos Bioscience to Present Phase 2 Data for Imneskibart With Avelumab in Adenocarcinoma Non-Small Cell Lung Cancer at ESMO Congress 2026
#ESMO26
aulos™
[background: 3D rendering of red antibody molecules on blue]
[Slide 1]
[Henlius logo] Henlius
ESMO 2026
Serplulimab
ESMO Proffered Paper
U.S. Bridging Study: ASTRIDE
[3D antibody molecule illustration]
● Head-to-head comparison in 1L ES-SCLC, with numerically longer OS
● Supports the applicability of ASTRUM-005 findings to the U.S. population
First report on ASTRIDE Study Results
(Serplulimab + Chemo vs. Atezolizumab + Chemo in 1L ES-SCLC)
Largest U.S. Enrollment in an ES-SCLC Bridging Study
201 ES-SCLC Pts Enrolled in the U.S.
63 U.S. Enrollment Sites
Longer Survival
Median OS:
12.4 months vs. 10.2 months
24-month OS rate:
32.2% vs. 17.6%
Median PFS per IRRC assessment:
5.4 months vs. 4.9 months
Comparable Safety Profile
Comparable incidence and severity of adverse events
No new safety signals identified
[Badge: ESMO 2026 BREAKTHROUGH ★★★]
[calendar icon] Presentation Time: Local time 14:55–15:05, October 26, 2026
[person icon] Leading PI: Dr. David R. Gandara, UC Davis Comprehensive Cancer Center
A Differentiated PD-1 Inhibitor
Approved indications: sqNSCLC, ES-SCLC, ESCC, nsqNSCLC and GC
A Distinct Mechanism Advancing Treatment in Lung and Gastrointestinal Cancers
Approved in 50+ countries and regions, covering nearly half of the world's population
Included in reimbursement or public healthcare coverage systems in 10+ European countries
Serplulimab is not approved in the U.S.
[Slide 1]
PEARLS / KEYNOTE-091 ESMO 2026
Recurrence Delayed. Survival Unchanged.
MV Onco
[Hand-drawn illustration: IV bag labelled PEMBROLIZUMAB dripping into a pair of lungs with a tumour; two alarm clocks labelled RECURRENCE CLOCK (teal) and SURVIVAL CLOCK (red)]
DFS HR 0.85
Recurrence delayed ✓
OS HR 0.98
No proven survival gain
WE DELAYED THE RECURRENCE CLOCK...
BUT DID WE EXTEND THE SURVIVAL CLOCK?
[IV bag labelled 1 YEAR OF PEMBROLIZUMAB]
Grade ≥3 AEs:
34% vs 25.6%
[Slide 2]
PEARLS / KEYNOTE-091 | ESMO 2026
Did Adjuvant Pembrolizumab Prevent Recurrence?
MV Onco
① WHY KEYNOTE-091?
• Completely resected early-stage NSCLC
• Recurrence remains common after surgery.
• Can ONE YEAR of adjuvant pembrolizumab reduce recurrence?
② WHO ENTERED?
• Stage IB (≥4 cm), II or IIIA — AJCC v7
• Completely resected NSCLC
• Any PD-L1 expression
• Adjuvant chemotherapy permitted
• N = 1,177 patients
③ RANDOMIZATION
N = 1,177 | 1:1
PEMBROLIZUMAB 200 mg IV Q3W × 18 cycles, n = 590
VS
PLACEBO Q3W × 18 cycles, n = 587
Duration ≈ 1 year
④ WHAT DID EARLIER ANALYSIS SHOW?
SIGNIFICANT DFS BENEFIT
ITT population:
• HR 0.76 (95% CI 0.63–0.91)
• P = 0.0014
Prior chemotherapy subgroup:
• HR 0.73 (95% CI 0.60–0.89)
→ Early recurrence benefit established.
⑤ DID DFS BENEFIT PERSIST?
Median follow-up: 87.7 months
6-YEAR DFS
• Pembrolizumab → 44.0%
• Placebo → 39.2%
HR 0.85 (95% CI 0.73–0.98)
Median DFS: 58.7 vs 43.3 months
TAKE-HOME
• DFS benefit persists after 7 years.
• But HR shifts 0.76 → 0.85.
• Does this translate into LONGER SURVIVAL?
Continued in Part 2 →
[Slide 3]
PEARLS / KEYNOTE-091 | ESMO 2026
PART 2/3
Better DFS – But Are Patients Living Longer?
MV Onco
① DID OVERALL SURVIVAL IMPROVE?
NO SIGNIFICANT OS BENEFIT
6-year OS:
• Pembrolizumab → 68.5%
• Placebo → 66.4%
• HR 0.98 (95% CI 0.81–1.18)
• P = 0.418
→ Only 2.1% absolute difference.
② WHAT ABOUT PRIOR CHEMOTHERAPY?
6-year OS:
• Pembrolizumab → 68.9%
• Placebo → 65.4%
• HR 0.91 (95% CI 0.74–1.12)
→ Numerical advantage.
→ Still NO demonstrated OS benefit.
③ DID LUNG CANCER DEATHS DECREASE?
6-year lung cancer-specific survival:
• Pembrolizumab → 81.3%
• Placebo → 76.9%
• HR 0.81 (95% CI 0.63–1.03)
→ Favorable trend.
→ NOT statistically significant.
④ WHAT ABOUT LCSS AFTER CHEMO?
6-year lung cancer-specific survival:
• Pembrolizumab → 81.6%
• Placebo → 75.0%
• HR 0.69 (95% CI 0.53–0.91)
→ 6.6% absolute difference.
→ Encouraging subgroup finding.
But secondary endpoint – interpret cautiously.
⑤ WHY IS THIS IMPORTANT?
Median follow-up: 87.7 months
DFS benefit persists:
• HR 0.85
But overall survival:
• HR 0.98
TAKE-HOME
Better DFS ≠ Proven OS Benefit
After 7.3 years, pembrolizumab delays recurrence.
But patients have NOT been shown to live longer overall.
Continued in Part 3 →
Toxicity & Practice Implications
[Slide 4]
PEARLS / KEYNOTE-091 | ESMO 2026
DFS Benefit Without OS Benefit — Is It Worth It?
MV Onco
1. WHAT WAS THE PRICE OF BENEFIT?
• Grade ≥3 adverse events:
– Pembrolizumab → 34.0%
– Placebo → 25.6%
• Grade ≥3 immune-mediated AEs / infusion reactions:
– 7.9% vs 1.9%
→ More severe toxicity with pembrolizumab.
2. WHY DID DFS NOT TRANSLATE INTO OS?
• Possible explanations:
• Effective treatment after recurrence
• Competing non-cancer deaths
• Delayed recurrence ≠ prevented death
• Trial not powered for OS
These explanations remain unproven.
3. IS KEYNOTE-091 STILL POSITIVE?
• YES — FOR DFS
• Final DFS: HR 0.85 (95% CI 0.73–0.98)
→ Persistent recurrence benefit.
• But final OS: HR 0.98 (95% CI 0.81–1.18)
→ NO demonstrated survival advantage.
DFS-positive ≠ OS-positive.
4. SHOULD THIS CHANGE PRACTICE?
• Adjuvant pembrolizumab remains an option for eligible patients.
• But consider:
• Absolute DFS benefit
• Stage and recurrence risk
• PD-L1 and driver mutation status
• Prior platinum chemotherapy
• Immune toxicity and patient preference
Do NOT compare trials indirectly.
5. WHAT IS THE REAL LESSON?
• After 7.3 YEARS:
• 6-year DFS → 44.0% vs 39.2%
• 6-year OS → 68.5% vs 66.4%
• Severe AEs → 34.0% vs 25.6%
TAKE-HOME
PEMBROLIZUMAB DELAYS RECURRENCE.
LONGER OVERALL SURVIVAL REMAINS UNPROVEN.
The question is no longer simply: "Does it improve DFS?"
But: "How much benefit justifies one year of immunotherapy?"
[Slide 1]
UPCOMING FDA DECISION
PDUFA: NOVEMBER 14, 2026
Ivonescimab
PD-1/VEGF Bispecific Antibody
FOR ADVANCED
EGFR-MUTATED
LUNG CANCER
AFTER PROGRESSION ON
THIRD-GENERATION EGFR-TKI
(e.g., osimertinib)
HARMONi PHASE III TRIAL
438 patients with advanced EGFR-mutated NSCLC
6.8 months
Ivonescimab + chemotherapy
4.4 months
Placebo + chemotherapy
Median Progression-Free Survival (PFS)
48% lower risk of progression or death
(HR 0.52)
P < 0.0001
16.8 vs 14.0 months
Median Overall Survival
(not statistically significant; HR 0.79)
28% vs 15%
Serious treatment-related adverse events
Dual action: PD-1 blockade + VEGF inhibition in a single antibody
ECHELON MEDICAL & AESTHETICS
www.echelonmedicalnyc.com
DR. NICOLE M. BATTY
MEDICAL ONCOLOGIST & HEMATOLOGIST
ECHELON MEDICAL & AESTHETICS
[lung illustration; portrait of a woman in glasses and white coat]
[Slide 1]
#ESMO26 · PUBLISHED TOPLINE
Krascendo 1
LBA5
Presidential Symposium II
Sun Oct 25 · 16:30 CET
Divarasib vs sotorasib or adagrasib
Previously treated advanced KRAS G12C-mutated NSCLC (head-to-head)
DESIGN
• Phase 3, randomized, open-label, multicentre
• N = 338
• Divarasib QD vs sotorasib QD or adagrasib BID
• Primary: PFS by BICR
• Secondary: OS, confirmed ORR, DoR, safety
PUBLISHED TOPLINE
PFS Met (primary, BICR)
OS Significant at interim analysis
Safety No new findings; common TRAEs manageable, reversible
"clinically meaningful and statistically significant improvements in both progression-free survival (PFS) and overall survival (OS)"
No hazard ratios, medians or response rates disclosed yet. Full results at ESMO.
Source: Roche press release (ad hoc announcement), 2 Jul 2026; Genentech release 1 Jul 2026 (US).
Dr. Aakash Desai | @ADesaiMD
[Slide 2]
HAYSTACK MRD®
by Quest Diagnostics®
"Circulating tumor DNA as a marker of
durable remission after non-operative
management of mismatch repair
deficient rectal cancer"
October 23, 3:15PM-4:00 PM
Presentation number: 4389P
Session: Translational research
and biomarker
[Slide 3]
HAYSTACK MRD®
by Quest Diagnostics®
"Clinical utility of ultra-sensitive
ctDNA MRD monitoring in
advanced NSCLC"
E-poster
Presentation number: 2728eP
Session: NSCLC, metastatic
[Slide 1]
ESMO26
TOP TEN BY ONCOALERT
LUNG CANCER
OncoAlert 360 [logo] Oncology For Colleagues By Colleagues
WWW.ONCOALERT360.COM
LBA3 DELLPHI-305: TARLATAMAB PLUS DURVALUMAB VS DURVALUMAB AS FIRST-LINE MAINTENANCE FOLLOWING DURVALUMAB, PLATINUM AND ETOPOSIDE IN EXTENSIVE-STAGE SCLC: PRIMARY ANALYSIS OF THE PHASE 3 TRIAL
LBA5 KRASCENDO 1: EFFICACY AND SAFETY OF DIVARASIB VS SOTORASIB OR ADAGRASIB IN PREVIOUSLY TREATED LOCALLY ADVANCED OR METASTATIC KRAS G12C-MUTATED NSCLC
LBA6 SAFFRON: OSIMERTINIB + SAVOLITINIB VS PLATINUM-PEMETREXED IN EGFRM MET-OVEREXPRESSED AND/OR -AMPLIFIED ADVANCED NSCLC POST-OSIMERTINIB: PHASE 3 PRIMARY RESULTS
LBA67 OPTITROP-LUNG04: FINAL OS ANALYSIS OF SACITUZUMAB TIRUMOTECAN VERSUS PLATINUM-BASED CHEMOTHERAPY IN EGFR-MUTATED NSCLC AFTER PROGRESSION ON EGFR-TKI: PHASE III STUDY
LBA66 OPTITROP-LUNG06: SACITUZUMAB TIRUMOTECAN PLUS PEMBROLIZUMAB VERSUS CHEMOTHERAPY PLUS PEMBROLIZUMAB AS FIRST-LINE TREATMENT FOR PD-L1-NEGATIVE ADVANCED NON-SQUAMOUS NSCLC: RANDOMIZED PHASE 3 STUDY
2614O PERSEE: PEMBROLIZUMAB WITH OR WITHOUT PLATINUM-BASED CHEMOTHERAPY AS FIRST-LINE TREATMENT IN ADVANCED NSCLC WITH PD-L1 ≥50%: PHASE 3 TRIAL
LBA69 SANOVO: SAVOLITINIB OR PLACEBO COMBINED WITH OSIMERTINIB IN TREATMENT-NAÏVE ADVANCED NSCLC WITH EGFR MUTATION AND MET OVEREXPRESSION: PHASE 3 RESULTS
2618RO IFCT-2103 DIAL: CONTINUATION PEMBROLIZUMAB (± PEMETREXED) UP TO 2 YEARS VERSUS OBSERVATION IN METASTATIC NSCLC WITH DISEASE CONTROL AT 6 MONTHS: PHASE 2 ANALYSIS
LBA71 PANKU-LUNG01: RANDOMIZED PHASE III STUDY OF IZALONTAMAB BRENGITECAN IN EGFR-MUTANT NON-SQUAMOUS NSCLC AFTER PROGRESSION ON A THIRD-GENERATION EGFR TKI
2613O SARON: PRIMARY RESULTS OF A RANDOMISED-CONTROLLED TRIAL OF CONSOLIDATION RADIOTHERAPY FOR SYNCHRONOUS OLIGOMETASTATIC NON-SMALL CELL LUNG CANCER
Senior Faculty
[headshots]
Dr Morgan Clin Onc
Dr Liu Med Onc
Dr Popat Med Onc
Dr Lovly Med Onc
Dr Lopes Med Onc
Dr Aggarwal Med Onc
Dr Reck Med Onc
Dr Massuti Med Onc
Dr Malapelle Pathologist
Ms Feldman Patient Advocate
Associate Faculty
Dr Mirallas Med Onc
Dr Özkerim Med Onc
[Slide 1]
[Photo: lab scientist in white coat and black gloves holding up a sample cartridge with blue-lit channels]
TEMPUS
ESMO CONGRESS 2026
Tempus announces 13 abstracts accepted for presentation at the European Society for Medical Oncology Congress 2026
Insilico Medicine (HKEX: 3696) | ESMO
Sunday, October 25, 2026, 08:30-10:00, Madrid, Spain
Cordoba Auditorium - Hall 4
Insilico Medicine to Present First-in-Human Data for AI-Designed Pan-TEAD Inhibitor ISM6331 at ESMO 2026
[Slide 1]
exclusive
FEATURING
[circular headshot] Balazs Halmos, MD, MS
[circular headshot] Dylan Fortman, MD
OncLive
Find out which lung cancer
presentations experts are
most excited to see at the
2026 ESMO Congress.
Sign up to read OncLive's preview of some of the
most anticipated abstracts ahead of the conference.
[Slide 1]
[ESMO Congress Madrid 2026 logo]
3836P - Real-world treatment patterns among
European patients with extensive-stage small cell
lung cancer (ES-SCLC): Insights from the
RESONANCE study
Presentation Number 3836P
Speakers Nicolas Girard (Paris, France)
Results
Overall, 623 pts were identified. At diagnosis, the median (IQR)
age was 67 (61–73) years, 57.8% were male and 23.1% had brain
metastases; median (IQR) follow-up was 8.3 (4.1–14.6) months. At
1L (N=551), most pts received platinum-based CT + IO (62.8%);
tx patterns in the 2L+ setting were more variable (Table). For pts
who were platinum-sensitive post-1L, the most common 2L and
third-line (3L) tx were platinum-based CT without IO (47.5%,
58/122) and topotecan monotherapy (22%, 13/59), respectively;
for pts who were platinum-resistant/refractory, topotecan
monotherapy was the most common tx at 2L (41%, 43/105) and
3L (22.2%, 8/36).
Conclusions
The RESONANCE study suggests no tx consensus exists in the
2L+ setting for ES-SCLC, potentially due to few effective options.
Recent approvals of tarlatamab and lurbinectedin, along with
ongoing evaluations of novel therapies, may reshape tx patterns.
[Slide 1]
ESMO 2026 INDUSTRY SATELLITE SYMPOSIUM
OCT 25 SUNDAY 13:00 – 14:30
[Headshot photograph of a woman with long reddish-blonde hair, dark top, grey background]
"SCLC has been treated with chemotherapy, with or without ICIs, with very minimal advances in the last decades. But nowadays, we need to face absolute changes with the introduction of TCEs and ADCs.
SOLANGE PETERS, SWITZERLAND
[Slide 1]
Lung Cancer: Top Trending Abstracts on X Ahead of ESMO 2026
[colour key:]
ADC
BsAb
IO
KRAS G12C, EGFR TKI, MET TKI
Radiotherapy
[column headers (voices):] Amol Akhade | Bijoy Telivala | Chandrakanth MV | Jose Fernando Moura | Mario Balsa | Masahiro Torasawa | Patrick Forde | Rishabh Jain | Riyaz Shah | Rohit Malde | Yakup Ergün | ChatGPT 5.6 Sol | Gemini 3.8 Flash | Claude Opus 5.5 | Grok 4.7
Date | Abstract ID | Presenter | Phase | Abstract Title
Oct 24 | LBA3 | Sands | P3 | DeLLphi-305: Tarlatamab + durva vs durva as 1LM therapy following durva + EP in ES-SCLC - Primary analysis | X X X X X X X X X X X X X X X
Oct 25 | LBA6 | Shun Lu | P3 | SAFFRON: Osi + savo vs plat-pem in EGFRm MET-OE and/or -amplified (AMP) adv NSCLC post-osi - Primary results | X X X X X X X X X X X X X X X
Oct 25 | LBA5 | Skoulidis | P3 | Krascendo 1: Diva vs Soto or Ada in previously treated LA/m KRAS G12C-mut NSCLC - Efficacy and safety results | X X X X X X X X X (Amol Akhade through Riyaz Shah) X X X X X (Yakup Ergün, ChatGPT 5.6 Sol, Gemini 3.8 Flash, Claude Opus 5.5, Grok 4.7)
Oct 25 | LBA67 | Feng Fang | P3 | OptiTROP-Lung04: Sac-TMT vs platinum-based CT in EGFRm NSCLC after progression on EGFR-TKI - Final OS analysis | X (Chandrakanth MV) X X X X X (Yakup Ergün, ChatGPT 5.6 Sol, Gemini 3.8 Flash, Claude Opus 5.5, Grok 4.7)
Oct 26 | LBA69 | Yi-Long Wu | P3 | SANOVO: Savo / pbo + osi in tx-naïve adv NSCLC with EGFRm and MET overexpression | X (Mario Balsa) X X X X X (Yakup Ergün, ChatGPT 5.6 Sol, Gemini 3.8 Flash, Claude Opus 5.5, Grok 4.7)
Oct 25 | LBA68 | Peters | P3 | SigVie-002: SV vs DTX in previously treated non-sqNSCLC | X (Chandrakanth MV) X (Rishabh Jain) X X X (ChatGPT 5.6 Sol, Gemini 3.8 Flash, Claude Opus 5.5)
Oct 25 | LBA66 | Caicun Zhou | P3 | OptiTROP-Lung06: Sac-TMT + pembro vs CT + pembro as 1L tx for PD-L1-neg adv non-sq NSCLC | X X X X X (Yakup Ergün, ChatGPT 5.6 Sol, Gemini 3.8 Flash, Claude Opus 5.5, Grok 4.7)
Oct 26 | LBA71 | Li Zhang | P3 | PANKU-Lung01: Iza-bren in EGFRm non-sq NSCLC after progression on a third-generation EGFR TKI | X X X X X (Yakup Ergün, ChatGPT 5.6 Sol, Gemini 3.8 Flash, Claude Opus 5.5, Grok 4.7)
Oct 25 | 2614O | Decroisette | P3 | PERSEE: Pembro ± platinum-based CT as 1L tx in adv NSCLC with PD-L1 ≥50% | X (Yakup Ergün) X (Grok 4.7)
Oct 24 | LBA73 | Sebastian | P2 | PACE-LUNG: Efficacy of additional CT for pts with EGFRm NSCLC with the continued presence of plasma ctDNA EGFRm at week 3 after start of osi 1L tx | X (Yakup Ergün)
Oct 25 | 2613O | McDonald | P2 | SARON: Consolidation radiotherapy for synchronous oligometastatic NSCLC - Primary Results | X (Yakup Ergün)
Format and methodology credit: Dr. Mike Thompson
LARVOL
[Slide 1]
ESMO 2026 INDUSTRY SATELLITE SYMPOSIUM
OCT 25 SUNDAY 13:00 - 14:30
[Headshot of Solange Peters]
SOLANGE PETERS, SWITZERLAND
REDEFINING THE STANDARDS: THE ERA OF DLL3 T-CELL ENGAGERS
Talk at 13:20 · Salamanca Auditorium · Hall 10 · IFEMA Madrid
[Slide 1]
ESMO 2026 INDUSTRY SATELLITE SYMPOSIUM
OCT 25 SUNDAY 13:00 - 14:30
[Headshot of Martin Reck]
MARTIN RECK, GERMANY
THE ROLE OF IMMUNE CHECKPOINT BLOCKADE IN SCLC: ACHIEVEMENTS & LIMITATIONS
Talk at 13:05 · Salamanca Auditorium · Hall 10 · IFEMA Madrid
[Slide 1]
ESMO 2026 INDUSTRY SATELLITE SYMPOSIUM
OCT 25 SUNDAY 13:00 – 14:30
[headshot of Giannis Mountzios]
"SCLC is a very rapidly evolving field. We will highlight the recent advances, including TCEs, ADCs and the combinations that are coming in the first-line setting of this disease.
GIANNIS MOUNTZIOS, GREECE
[Slide 1]
ESMO 2026 INDUSTRY SATELLITE SYMPOSIUM
OCT 25 SUNDAY 13:00 - 14:30
[Headshot of Martin Reck]
"We are going to discuss the most recent data on SCLC. There is so much going on, and it is very much in favor of our patients with advanced SCLC."
MARTIN RECK, GERMANY
[Slide 1]
ESMO 2026
OCT 24 SATURDAY 17:18 – 17:30
JACOB SANDS, USA
ES-SCLC: TARLATAMAB + DURVALUMAB AS 1L MAINTENANCE
LBA3 · PRESIDENTIAL SYMPOSIUM I · HALL 6
[Figure: headshot of Jacob Sands.]
[Slide 1]
ESMO 2026
Lung Cancer Abstract Highlights
DeLLphi-305 (LBA3)
Tarlatamab + durvalumab vs. durvalumab alone as first-line maintenance for ES-SCLC, testing DLL3-directed T-cell engagement earlier in treatment.
OptiTROP-Lung06 (LBA66)
Sacituzumab tirumotecan (TROP2 ADC) + pembrolizumab vs. chemotherapy + pembrolizumab in first-line PD-L1-negative advanced nonsquamous NSCLC.
OptiTROP-Lung04 (LBA67)
Final overall survival analysis of sacituzumab tirumotecan vs. platinum-based chemotherapy after EGFR-TKI progression in EGFR-mutated NSCLC.
Sigvotatug Vedotin (LBA68)
A phase III comparison with docetaxel in previously treated nonsquamous NSCLC, examining efficacy and safety.
KRASCENDO 1 (LBA5)
Divarasib vs. sotorasib or adagrasib in previously treated KRAS G12C-mutated NSCLC, offering a direct comparison within the targeted therapy class.
SAFFRON (LBA6)
Osimertinib + savolitinib vs. platinum-pemetrexed after osimertinib progression in EGFR-mutated NSCLC with MET overexpression and/or amplification.
SANOVO (LBA69)
Savolitinib + osimertinib vs. osimertinib alone in treatment-naïve EGFR-mutated NSCLC with MET overexpression, exploring upfront dual-target inhibition.
PANKU-Lung01 (LBA71)
Izalontamab brengitecan, a bispecific ADC, in EGFR-mutated nonsquamous NSCLC after progression on a third-generation EGFR-TKI.
HERON-Lung01 (LBA72)
Ruzaltatug rezetecan, a HER3-directed ADC, vs. platinum-based chemotherapy after EGFR-TKI progression in EGFR-mutated advanced NSCLC.
Neotorch (LBA64)
Final analysis of perioperative toripalimab + chemotherapy in resectable stage II–III NSCLC, focusing on long-term outcomes.
[icons: lungs, antibodies, DNA helix, pills, scalpel]
[Slide 2]
RESEARCH UPDATES IN MTAP LOSS
• Genomic and biomarker landscape of MTAP loss/KRAS G12D mutant vs. MTAP loss/KRAS non-mutated advanced NSCLC
• MTAP loss and HPV status in head and neck squamous cell carcinoma (HNSCC): A genomic landscape study
[blurred photo of glittering coloured spheres]
[Foundation Medicine icon]
[Slide 1]
ESMO 2026 INDUSTRY SATELLITE SYMPOSIUM
OCT
25
SUNDAY
13:00 - 14:30
[headshot photo]
"
There is so much going on in small cell lung cancer, and it is very much in favor of our patients.
MARTIN RECK, GERMANY
[Slide 1]
ESMO 2026 INDUSTRY SATELLITE SYMPOSIUM
OCT 25 SUNDAY 13:00 – 14:30
"With T-cell engagers arriving in small cell lung cancer, the question is no longer only which treatment to give, but in which order, and for which patient."
NOEMÍ REGUART, SPAIN
[Figure: headshot of Noemí Reguart.]
[Slide 1]
ESMO 2026 INDUSTRY SATELLITE SYMPOSIUM
OCT 25 SUNDAY 13:00 – 14:30
[portrait of Noemí Reguart]
"The question is no longer only which treatment to give, but in which order."
NOEMÍ REGUART, SPAIN
[Slide 1]
HUTCHMED Highlights Clinical Data to be Presented at
ESMO Congress 2026
October 23-27, 2026 | Madrid, Spain
HUTCHMED [logo]
Sponsored Studies
Abstract title | Presenter/ Lead author | Presentation details
Osimertinib (osi) + savolitinib (savo) vs platinum–pemetrexed (plat–pem) in EGFRm MET-overexpressed (OE) and/or -amplified (AMP) advanced NSCLC post-osi: SAFFRON Phase (Ph) 3 primary results | Shun Lu (Shanghai, China) | LBA6 Presidential Symposium II Alicante Auditorium - Hall 6 Sunday, October 25, 2026 16:30 - 18:15 CEST
Savolitinib or Placebo Combined with Osimertinib in Treatment-Naïve Advanced NSCLC with EGFR Mutation and MET Overexpression: Results from the Phase 3 SANOVO Study | Yi-Long Wu (Guangzhou, China) | LBA69 Proffered paper 2: NSCLC, metastatic Alicante Auditorium - Hall 6 Monday, October 26, 2026 08:30 - 10:00 CEST
Updated results from a fruquintinib Expanded Access Program for patients with previously treated metastatic colorectal cancer | Stefan Kasper (Essen, Germany) | 848P Poster Session: Colon cancer
Association between dose adjustment and treatment outcomes in patients with advanced renal cell carcinoma receiving fruquintinib plus sintilimab: A post-hoc analysis of the FRUSICA-2 trial | Yuanyuan Qu (Shanghai, China) | 3655eP E-poster Session: Renal cancer
Efficacy of fruquintinib plus sintilimab in special populations with advanced renal cell carcinoma: A subgroup analysis of FRUSICA-2 study | Kaiwei Yang (Beijing, China) | 3667eP E-poster Session: Renal cancer
Final phase 2 analysis of surufatinib plus camrelizumab, nab-paclitaxel and gemcitabine in first-line metastatic pancreatic cancer | Shukui Qin (Nanjing, China) | 3156P Poster Session: Pancreatic cancer
[Slide 2]
HUTCHMED Highlights Clinical Data to be Presented at
ESMO Congress 2026
October 23-27, 2026 | Madrid, Spain
HUTCHMED [logo]
Investigator-initiated Studies (1/2)
Abstract title | Presenter/ Lead author | Presentation details
Fruquintinib plus capecitabine maintenance after first-line anti-EGFR antibody plus chemotherapy in RAS/BRAF wild-type metastatic colorectal cancer: A phase Ib/II study | Lin Yang/ Letian Zhang (Beijing, China) | 877eP E-poster Session: Colon cancer
Real-world effectiveness and safety of fruquintinib in patients with metastatic colorectal cancer in Spain: The FrESP study | Ana Fernandez Montes (Ourense, Spain) | 880eP E-poster Session: Colon cancer
CONCEPT (COmbinatioN of CEtuximab Plus fruquintinib Treatment ± immunotherapy): A multicenter, randomized, open-label phase II trial in first-line pMMR RAS/BRAF wild-type unresectable metastatic colorectal cancer | Kefeng Ding (Hangzhou, China) | 890eP E-poster Session: Colon cancer
A real-world study of low-dose fruquintinib combined with trifluridine/tipiracil hydrochloride (TAS-102) in the third-line and beyond treatment of metastatic colorectal cancer | Yuehong Cui/ Li Liang (Shanghai, China) | 903eP E-poster Session: Colon cancer
Real-world outcomes with fruquintinib in heavily pretreated metastatic colorectal cancer: Impact of patient and disease characteristics | Maria Maddalena Laterza (Pozzuoli, Italy) | 964eP E-poster Session: Colon cancer
A phase II, open-label, randomized study of doublet chemotherapy (FOLFOX or FOLFIRI) plus fruquintinib compared with doublet chemotherapy (FOLFOX or FOLFIRI) plus bevacizumab in second line setting for a metastatic colorectal cancer: ULYSSE- FFCD2406 - PRODIGE115 (trials in progress) | Jean Marc Phelip (Saint-Étienne, France) | 991eTiP E-poster Session: Colon cancer
Phase II study of fruquintinib plus utidelone in platinum-resistant recurrent ovarian cancer (FRUTD Trial) | Zheng Feng (Shanghai, China) | 1283P Poster Session: Gynaecological cancers
Fruquintinib plus eribulin in patients with metastatic HR+, HER2-breast cancer after progression on endocrine therapy plus CDK4/6 inhibitor: Updated results from a phase II study | Yuan Yuan (Nanjing, China) | 1896eP E-poster Session: HR+ breast cancer
Fruquintinib plus sintilimab and XELOX as first-line treatment for advanced gastric or gastroesophageal junction adenocarcinoma: A single-arm, open-label, multicenter phase II study | Hua Wang (Nanchang, China) | 2980eP E-poster Session: Oesophagogastric cancer
Fruquintinib plus cadonilimab and S-1 in previously treated unresectable locally advanced or metastatic esophageal squamous cell carcinoma: preliminary efficacy and safety results from a phase Ib/II study | Huiyan Luo (Guangzhou, China) | 2981eP E-poster Session: Oesophagogastric cancer
Nanoliposomal irinotecan (nal-IRI) combined with fruquintinib as second-line treatment for advanced gastric cancer: A single-arm, open-label, dose-escalation and expansion phase I/II trial | Jieer Ying/ Qi Xu (Hangzhou, China) | 2986eP E-poster Session: Oesophagogastric cancer
FRUQUITAS trial: ENGIC intergroup randomized phase III of trifluridine/tipiracil +/- fruquintinib in pre-treated metastatic gastro-oesophageal adenocarcinoma | David Tougeron (Poitiers, France) | 3079eTiP E-poster Session: Oesophagogastric cancer
[Slide 3]
HUTCHMED Highlights Clinical Data to be Presented at
ESMO Congress 2026
October 23-27, 2026 | Madrid, Spain
HUTCHMED [logo]
Investigator-initiated Studies (2/2)
Abstract title | Presenter/Lead author | Presentation details
CHOICE III: short-course preoperative radiotherapy followed by fruquintinib plus anti–PD-1 antibody (serplulimab) for neoadjuvant treatment of pMMR/MSS mid-to-low locally advanced rectal cancer: A single-arm, single-center, prospective phase II study | Wei Zhang (Shanghai, China) | 3582eTiP E-poster Session: Rectal and anal cancer
First-line fruquintinib plus serplulimab for metastatic non-clear cell renal cell carcinoma: Updated results from the phase II FRONTIER study | Jiwei Huang (Shanghai, China) | 3614P Poster Session: Renal cancer
Latest efficacy and safety analysis of surufatinib combined with EP regimen and serplulimab as first-line treatment for extrapulmonary neuroendocrine carcinoma | Tao Zhang/ Zhenyu Lin (Wuhan, China) | 2394RO Rapid Oral Session: NETs and endocrine tumours Pamplona Auditorium - Hall 5 Friday, October 23, 2026 16:15 - 17:45 CEST
Surufatinib combined with toripalimab and nab-paclitaxel/ gemcitabine chemotherapy as first-line treatment for advanced pancreatobiliary-type ampullary carcinoma: A prospective phase II Clinical Trial | Juan Du (Nanjing, China) | 507eP E-poster Session: Biliary tract cancer, incl. cholangiocarcinoma
Efficacy and safety of surufatinib in combination with CAPTEM in advanced G2/G3 Neuroendocrine Tumors: Results from a single-arm, phase II Trial | Wei Wang (Guangzhou, China) | 2403P Poster Session: Neuroendocrine tumours
Surufatinib plus S-1/temozolomide as first-line therapy in MGMT-low advanced pancreatic neuroendocrine tumours (SUSTEM-p): An open-label, single-centre phase Ib/II trial | Yihebali Chi (Beijing, China) | 2411P Poster Session: Neuroendocrine tumours
Updated results of a prospective, open-label study of surufatinib plus CAPTEM as conversion therapy for unresectable pancreatic neuroendocrine tumors | Ziyao Wang (Chengdu, China) | 2412P Poster Session: Neuroendocrine tumours
Matching-adjusted indirect comparison of surufatinib versus high-dose OCT-LAR in patients with advanced GEP-NETs who progressed on prior SSA Therapy | Jianming Xu (Beijing, China) | 2415P Poster Session: Neuroendocrine tumours
Surufatinib combined with octreotide LAR for the treatment of G1/G2 GEP-NETs: A single-arm, prospective, open-label phase II study | Xiaofeng Sun (Nanjing, China) | 2439eP E-poster Session: Neuroendocrine tumours
Six weeks of induction gemcitabine plus nab paclitaxel (AG) followed by sequential surufatinib plus AG or AG alone as first line therapy for locally advanced or metastatic pancreatic ductal adenocarcinoma (mPDAC): A single center, two cohort, phase II study | Jin Xu/ Jialin Li (Shanghai, China) | 3168P Poster Session: Pancreatic cancer
A phase Ib/II study of radiotherapy combined with surufatinib and sintilimab for localized high-risk limb and trunk soft tissue sarcomas: A prospective single-center trial | Yan Wang (Shanghai, China) | 3739P Poster Session: Sarcoma
Surufatinib plus serplulimab, etoposide, and carboplatin as first-line treatment for extensive-stage small cell lung cancer (ES-SCLC): Updated results from a single-arm, phase Ia/Ib trial | Haipeng Xu/ Longfeng Zhang (Fuzhou, China) | 3831P Poster Session: Small cell lung cancer
[Slide 1]
OPTIMUM-01 | POSTER 2086P
Darovasertib and Crizotinib for HLA-A*02–Positive Metastatic Uveal Melanoma: Results from the Phase 2 OptimUM-01 Study
24 October 2026 | 12:00–12:45 p.m. CEST
[IDEAYA BIOSCIENCES logo]
[Slide 2]
OPTIMUM-02 | POSTER 2104P
Darovasertib with Crizotinib vs Investigator's Choice as First-Line Treatment for Patients with HLA-A2-Negative Metastatic Uveal Melanoma (OptimUM-02): A Subgroup Analysis
24 October 2026 | 12:00–12:45 p.m. CEST
[IDEAYA BIOSCIENCES logo]
[Slide 3]
OPTIMUM-09 | POSTER 2092P
Neoadjuvant Darovasertib in Primary Uveal Melanoma: Follow-Up Data from the Phase 2 OptimUM-09 Study
24 October 2026 | 12:00–12:45 p.m. CEST
[IDEAYA BIOSCIENCES logo]
[Slide 4]
IDE849 | POSTER 3815P
SHR-4849 (IDE849), an ADC Targeting Delta-Like Ligand 3 (DLL3), in Relapsed Small Cell Lung Carcinoma (SCLC) and Other Neuroendocrine Carcinomas (NECs): Long-Term Results from the Phase 1 Study
24 October 2026 | 12:00–12:45 p.m. CEST
[IDEAYA BIOSCIENCES logo]
[Slide 1]
ESMO 2026 INDUSTRY SATELLITE SYMPOSIUM
LUNG SUMMIT ON SCLC
FROM IO-STANDARDS TO THE TCE ERA
SUNDAY, 25 OCTOBER 2026
13:00 – 14:30 CET
SALAMANCA AUDITORIUM, HALL 10
IFEMA MADRID, MADRID, SPAIN
[Four headshots]
GIANNIS MOUNTZIOS GREECE
NOEMÍ REGUART SPAIN
SOLANGE PETERS SWITZERLAND
MARTIN RECK GERMANY
13:00 WELCOME & INTRODUCTION
SCLC JOURNEY AS AN IMMUNOTHERAPY CONTINUUM — S. PETERS
13:05 THE ROLE OF ICB IN SCLC: ACHIEVEMENTS & LIMITATIONS
THE CURRENT AND ESTABLISHED ROLE OF ICIs IN ES-SCLC — M. RECK
13:20 REDEFINING THE STANDARDS: THE ERA OF DLL3 T-CELL ENGAGERS
INTRODUCING DLL3-TARGETING TCEs AS DRIVER OF A PARADIGM SHIFT — S. PETERS
13:40 PRACTICAL MANAGEMENT OF DLL3 T-CELL ENGAGERS
HOW MANAGING T-CELL ENGAGERS DIFFERS FROM MANAGING ICIs — G. MOUNTZIOS
14:00 THE EVOLVING ALGORITHM: SEQUENCING INNOVATIVE STRATEGIES
INTEGRATION OF DLL3 TCEs INTO PATIENT MANAGEMENT SCENARIOS — N. REGUART
14:15 FACULTY ROUNDTABLE & AUDIENCE Q&A
OPEN DISCUSSION, AUDIENCE QUESTIONS & PATIENT CASES — ALL SPEAKERS
ESMO 2026
Top 10 (ish) Breast Cancer Abstracts
@PTarantinoMD
1. FOURLIGHT-1 (A. Giordano et al.) -> Announced to be positive, this randomized phase 2 trial evaluated the benefit of selective CDK4 inhibition with atirmociclib (+fulvestrant) in 2L HR+ MBC. Highly awaited.
2. BRIDGET (S. Sammons et al.) -> Could the addition of tucatinib to HP (or T-DM1) lead to favorable outcomes among pts with isolated PD from HER2+ MBC? Important data on an understudied setting.
3. TALENT (S. Hurvitz et al.) -> Preliminary results from TALENT were quite disappointing, with neoadjuvant T-DXd/AI showing low pCR rate in HR+/HER2- breast cancer. At ESMO, we will see updated results, including the first data with T-DXd used in sequence with chemo in this setting.
4. SWITCH (L. Fan et al.) -> Could keeping the payload (TOPO1i) but switching the target enable for continued efficacy with ADCs? SATEEN suggested limited benefit for this strategy in HER2+ disease. The SWITCH phase 2 trial tests this strategy with 4 novel TOPO1 ADCs in HR+/HER2- disease.
5. KEYNOTE-B49 (H. Rugo et al.) -> Immunotherapy has struggled to find its place in HR+ disease. This phase 3 trial tested whether using pembro early (added to 1L chemo) and in a selected population (PD-L1+) could prove beneficial for patients with HR+ MBC.
6. POP-DURVA (J. Ribeiro et al.) -> Standard treatment for stage I TNBC remains undefined. POP-DURVA tests 2 infusions of neoadjuvant durva in stage I TNBC with sTIL of >= 5%, with primary endpoint pCR
7. NSABP B42 (E. Mamounas et al.) -> The prior 10-year analysis of NSABP B42 demonstrated a significant DFS (but not OS) advantage with 10 vs 5 years of adjuvant AI in postmenopausal patients. This final analysis will clarify the long-term impact of extended AI therapy, which is increasingly utilized in practice.
8. MRD studies -> Interesting studies evaluating the prognostic role of MRD in HER2+ MBC with exceptional response (Nozawa et al.), neoadjuvant TNBC (Barcenas et al') and in the surveillance setting (Ozaki et al.)
9. Exotic TOPO 1 ADC phase 3 trials -> At ESMO, we will see primary results of multiple phase 3 trials of TOP1 ADCs vs chemo conducted in China, including HORIZON-Breast06 (SHR-A1811 for HER2-low MBC), APEX-Breast01 (TQB2102 for HER2-low MBC) and PANKU-Breast01 (Iza-Bren for HR+/HER2- MBC)
10. Updates from NATALEE (6y), FINER (OS), TROPION-Breast02 (brain mets), DESTINY-Breast09 (brain mets), GIM3 FATA (AI comparison), lidERA (PROs), DESTINY-Breast05 (PROs), OptiTROP-Breast01 (OS)
Bonus: CHARISMA (P. Tarantino et al.) -> How does breast cancer escape ADC treatment? We conducted multiomic profiling of biopsies collected pre/post-ADCs, with identification of novel mechanisms of resistance.
[Slide 1]
Rapid Oral session
4RO - Target switching with conserved-payload novel ADCs in patients with metastatic breast cancer following prior ADC therapy (SWITCH): A prospective, open-label, phase 2 platform trial
Speakers Lei Fan (Shanghai, China)
Lecture Time 10:20 - 10:25
Abstract
Background
Resistance to antibody-drug conjugates (ADCs) is an inevitable challenge in metastatic breast cancer (MBC), but the optimal post-progression sequencing strategy remains unclear. The SWITCH trial evaluated the efficacy and safety of a "target/payload switching" strategy using novel ADCs in patients with ADC-refractory MBC.
Methods
SWITCH is a prospective, open-label, phase 2 platform trial. Patients with human epidermal growth factor receptor 2-negative (HER2-negative) MBC who progressed on at least one prior ADC were enrolled. Based on prior treatment history, participants were randomly assigned to four novel ADC cohorts: SHR-A1811 (Cohort A), SHR-A1921 (Cohort B), SHR-A2009 (Cohort C), or SHR-A2102 (Cohort D), all carrying a topoisomerase I inhibitor (TOP1i) payload. The primary endpoint was investigator-assessed objective response rate (ORR).
Results
Between Oct 21, 2024, and Dec 30, 2025, 58 HER2-negative patients were screened, 54 of whom were randomly assigned (Cohort A: n=10; B: n=12; C: n=12; D: n=20). The population was heavily pretreated, with the majority (94.4%) having prior exposure to TOP1i-based ADCs. Confirmed ORRs were limited across all cohorts: 0% in Cohort A, 8.3% in Cohort B, 0% in Cohort C, and 5% in Cohort D. Responses were observed only in patients switching from the microtubule inhibitor-based ADC disitamab vedotin (RC48) to a TOP1 inhibitor-based ADC, whereas no responses occurred after switching between ADCs with the same payload class despite antigen switching. Treatment-related adverse events were consistent with known profiles of each ADC and manageable.
Conclusions
Rechallenging ADC-refractory MBC with novel agents targeting alternative antigens yielded limited responses, which suggested that payload cross-resistance was a primary driver of resistance. Diversified payload mechanisms in subsequent ADC sequencing were important to restore therapeutic sensitivity.
ESMO CONGRESS 2026 - MADRID - 23-27 OCTOBER
BREAST CANCER
My Top 10 Oral Presentations to Watch
Personal picks from Erika P. Hamilton, MD - Chief Development Officer, Late Phase & Director, Breast Cancer Research Program
Proffered Paper & Rapid Oral sessions - All in Alicante Auditorium - Hall 6 - Times in Madrid local time
Sarah Cannon Research Institute
Clocks change from CEST to CET overnight 24-25 Oct
FRIDAY - 23 OCTOBER 2026
LBA23 (Abstract) - Final results of TALENT: A neoadjuvant trial of T-DXd with or without anastrozole, or in sequence with chemotherapy for HER2-low, HR+ early-stage breast cancer. Sara A. Hurvitz - Seattle, USA. Proffered Paper 1: Breast cancer, early and advanced stage. Why it matters: Can an ADC move into the curative HR+ setting? 13:30 to 13:40 CEST est. slot
LBA24 (Abstract) - Final Analysis of NRG Oncology/NSABP B-42, a Randomized, Double-blinded, Placebo-controlled Trial of Extended Letrozole in Postmenopausal Women with Hormone-receptor Positive Breast Cancer Who Have Completed Previous Adjuvant Therapy with an Aromatase Inhibitor. Eleftherios P. Mamounas - Orlando, USA. Proffered Paper 1: Breast cancer, early and advanced stage. Why it matters: The final long-term answer on extended letrozole. 14:15 to 14:25 CEST est. slot
LBA25 (Abstract) - Adjuvant ribociclib (RIB) + nonsteroidal aromatase inhibitor (NSAI) in patients (pts) with HR+/HER2- early breast cancer (EBC): NATALEE 6-y overall survival (OS) and efficacy outcomes. Dennis J. Slamon - Los Angeles, USA. Proffered Paper 1: Breast cancer, early and advanced stage. Why it matters: Our first look at OS for ribociclib; an OS benefit has already been seen with abemaciclib. 14:25 to 14:35 CEST est. slot
538RO (Abstract) - Patient (pt)-reported outcomes (PROs) from the Phase III lidERA Breast Cancer (BC) trial of giredestrant (GIRE) in pts with oestrogen receptor-positive, HER2-negative early BC (ER+, HER2- eBC). Gustavo Werutsky - Porto Alegre, Brazil. Rapid Oral: Breast cancer, early stage. Why it matters: Tolerability of the first adjuvant oral SERD: key to 5+ years of adherence. 16:20 to 16:25 CEST est. slot
542RO (Abstract) - Prognostic impact of postoperative ctDNA surveillance on relapse-free survival and molecular lead time in high-risk breast cancer: JCOG1204A1. Yukinori Ozaki - Koto-ku, Japan. Rapid Oral: Breast cancer, early stage. Why it matters: How much lead time does ctDNA surveillance buy after surgery? 16:42 to 16:47 CEST est. slot
SATURDAY - 24 OCTOBER 2026
LBA51 (Abstract) - Results From KEYNOTE-B49: A Phase 3, Randomized, Double-Blind Study of Pembrolizumab (Pembro) vs Placebo (Pbo) Plus Chemotherapy (CT) in Participants (Pts) With HR+/HER2- Advanced Breast Cancer (ABC). Hope S. Rugo - Duarte, USA. Proffered Paper 2: Breast cancer, early and advanced stage. Why it matters: Does immunotherapy have a place in metastatic HR+ disease? 08:30 to 08:40 CEST est. slot
1842O (Abstract) - Efficacy and safety of atirmociclib (ATI) + fulvestrant (FUL) in patients (pts) with HR+/HER2- advanced/metastatic breast cancer (mBC) who progressed on prior CDK4/6 inhibitor (CDK4/6i) in a randomized phase 2 study (FOURLIGHT-1). Antonio Giordano - Boston, USA. Proffered Paper 2: Breast cancer, early and advanced stage. Why it matters: Randomized data for a CDK4-selective inhibitor after CDK4/6. 08:50 to 09:00 CEST est. slot
LBA96 (Abstract) - First-line (1L) datopotamab deruxtecan (Dato-DXd) vs chemotherapy in patients (pts) with locally recurrent inoperable or metastatic triple-negative breast cancer (mTNBC) for whom immunotherapy was not an option: Exploratory analysis of pts with brain metastases in TROPION-Breast02. Rebecca A. Dent - Singapore. Proffered Paper 2: Breast cancer, early and advanced stage. Why it matters: CNS activity of first-line Dato-DXd in TNBC. 09:25 to 09:35 CEST est. slot
MONDAY - 26 OCTOBER 2026
4RO (Abstract) - Target switching with conserved-payload novel ADCs in patients with metastatic breast cancer following prior ADC therapy (SWITCH): a prospective, open-label, phase 2 platform trial. Lei Fan - Shanghai, China. Rapid Oral 2: Breast cancer, advanced stage. Why it matters: Prospective data on ADC sequencing: switch the target, keep the payload. 10:20 to 10:25 CET est. slot
LBA49 (Abstract) - A DESTINY-Breast09 (DB-09) analysis of trastuzumab deruxtecan (T-DXd) + pertuzumab (P) vs taxane + trastuzumab + pertuzumab (THP) for patients (pts) with HER2+ advanced/metastatic breast cancer (a/mBC) and baseline (BL) brain metastases (BMs). Cristina Saura Manich - Barcelona, Spain. Rapid Oral 2: Breast cancer, advanced stage. Why it matters: First-line T-DXd + pertuzumab in patients with brain metastases. 11:00 to 11:05 CET est. slot
Source: ESMO Congress 2026 online programme. Session times are official; individual slots are estimated from presentation order and durations.
My personal selection and opinions; not an official ESMO or Sarah Cannon Research Institute list or endorsement.
[Slide 1]
Rapid Oral session
4640RO - Bulumtatug fuvedotin (BFv, 9MW2821), a nectin-4-directed antibody-drug conjugate (ADC), in patients with locally advanced or metastatic triple negative breast cancer (la/mTNBC) previously treated with topoisomerase I inhibitor (TopI)-based ADCs: Results from a phase 2 study
Speakers Yanchun Meng (Shanghai, China)
Lecture Time 10:30 - 10:35
Abstract
Background
BFv is an ADC delivering monomethyl auristatin E (MMAE) to Nectin-4-expressing cells, a target highly expressed in TNBC. For patients with prior exposure to TopI-based ADCs, switching to a Nectin-4-targeted ADC with a distinct payload (MMAE) represents a rational therapeutic strategy. We report efficacy and safety data from the cohort of la/mTNBC patients previously treated with TopI-based ADCs in the phase 2 study of BFv (NCT06492005).
Methods
Cohort A enrolled la/mTNBC patients with prior TopI-based ADC therapy. BFv was given intravenously at 1.25 mg/kg on days 1 and 8 every 21 days. Primary endpoint was objective response rate (ORR). Secondary endpoints included duration of response (DOR), disease control rate (DCR), progression-free survival (PFS), overall survival (OS), and safety.
Results
As of April 10, 2026, 62 patients were enrolled, of whom 60 were evaluable for response. Median age was 50.5 years (range 32-73). Liver metastases were present in 33% of patients, and 42% had received ≥3 prior lines of therapy. All patients (100%) had received prior TopI-based ADCs: 48% received TROP-2-targeted ADCs, and 33% received HER2-targeted ADCs. All patients had prior taxane-based chemotherapy; 35% also received immune checkpoint inhibitors. The ORR was 30.0% (95% CI 18.85%-43.21%) and DCR was 80.0% (95% CI 67.67%-89.22%). Median PFS was 3.7 months (95% CI 2.96-4.34), and median DOR was 8.7 months (95% CI 2.79-NR). OS data were not mature. Common TRAEs (≥20%) included increased AST/ALT, neutropenia, leukopenia, hypertriglyceridemia, rash, hypercholesterolemia, hyperglycemia, anemia, thrombocytopenia, asthenia, and increased GGT. Grade ≥3 TRAEs (≥5%) included neutropenia, leukopenia, and increased AST.
Conclusions
BFv demonstrated promising antitumor activity with a manageable safety profile in heavily pretreated patients with la/mTNBC who had all received prior TopI-based ADCs. The first pivotal trial for this indication worldwide is underway.
[Slide 1]
ESMO 2026
TOP 15 BREAST CANCER TRIALS TO WATCH
Pre-congress watchlist | Grouped by breast cancer subtype
23 - 27 OCTOBER 2026 | MADRID, SPAIN
[Photo of Madrid Metropolis building]
HR+ / HER2- BREAST CANCER
Endocrine therapy, targeted combinations and immunotherapy
1 FOURLIGHT-1 - Atirmociclib + fulvestrant in 2L HR+/HER2- MBC [CDK4 icon]
2 PANKU-Breast01 - EGFRxHER3 bispecific ADC in HR+/HER2- MBC
3 KEYNOTE-B49 - Pembrolizumab + chemotherapy in PD-L1+ HR+/HER2- MBC
4 NATALEE - 6-year outcomes of adjuvant ribociclib in HR+/HER2- early breast cancer [KM curve icon, "6 YEARS" calendar icon]
5 FINER / MA.40 - Overall survival with ipatasertib + fulvestrant after CDK4/6i [AKT icon]
6 NSABP B-42 - Long-term outcomes of extended adjuvant aromatase inhibition
7 TALENT - Neoadjuvant T-DXd-based sequencing in HR+/HER2-low early breast cancer
8 SWITCH - ADC sequencing after prior ADC exposure in HR+/HER2- MBC
HER2-POSITIVE / HER2-LOW BREAST CANCER
Next-generation ADCs and targeted approaches
9 BRIDGET - Tucatinib-based treatment for isolated progression in HER2+ MBC [HER2 icon]
10 DESTINY-Breast09 - CNS outcomes update with first-line T-DXd + pertuzumab in HER2+ MBC [brain icon]
11 HORIZON-Breast06 - Trastuzumab rezetecan in HER2-low MBC
12 APEX-Breast01 - Novel TOP1 ADC in HER2-low MBC
TRIPLE-NEGATIVE BREAST CANCER
Immunotherapy and next-generation ADCs
13 TROPION-Breast02 - CNS outcomes update with datopotamab deruxtecan in TNBC [brain icon]
14 POP-DURVA - Neoadjuvant durvalumab in stage I TNBC
15 OptiTROP-Breast01 - Final overall survival with sacituzumab tirumotecan in TNBC
OTHER IMPORTANT ABSTRACTS TO WATCH
VIKTORIA-1 - After CDK4/6i | postMONARCH - After CDK4/6i | lidERA - Patient-reported outcomes | DESTINY-Breast05 - Patient-reported outcomes | GIM3 FATA - AI comparison | MRD studies - Prognostic role across settings | CHARISMA - Mechanisms of ADC resistance
[ESMO logo] GOOD SCIENCE BETTER MEDICINE BEST PRACTICE
@DrRishabhOnco DM - Medical Oncology (AIIMS, New Delhi) [X logo]
[Slide 1]
MADRID 2026 ESMO congress | MADRID SPAIN 23-27 OCTOBER 2026 | ESMO
Rapid Oral session
4449RO - Paired-biopsy multi-omic analysis reveals target-independent mechanisms of antibody-drug conjugate (ADC) resistance in metastatic breast cancer (MBC)
Speakers Paolo Tarantino (Boston, United States of America)
Lecture Time 11:27 - 11:47
Abstract
Background
Resistance mechanisms to ADCs remain poorly characterized. We sought to define molecular adaptations associated with ADC resistance through integrated multi-omic profiling of paired tumor samples collected from patients treated with ADCs.
[Slide 1]
Proffered Paper session
LBA25 - Adjuvant ribociclib (RIB) + nonsteroidal aromatase inhibitor (NSAI) in patients (pts) with HR+/HER2− early breast cancer (EBC): NATALEE 6-y overall survival (OS) and efficacy outcomes
Speakers Dennis J. Slamon (Los Angeles, United States of America)
Lecture Time 14:25 - 14:35
[Abstract]
Background
The phase 3 NATALEE trial demonstrated a statistically significant invasive disease−free survival (iDFS) benefit with adjuvant RIB + NSAI in pts with high-risk stage II/III HR+/HER2− EBC. We present a prespecified analysis of OS and efficacy outcomes with 6 y of follow-up.
[Slide 2]
Results
At the data cutoff (15 May 2026), all pts were off RIB for a median of 38 mo and beyond the predefined NSAI study regimen. With a median OS follow-up of 66.5 mo, RIB + NSAI showed an OS benefit over NSAI alone (HR, 0.809 [95% CI: 0.661-0.989]; nominal 1-sided P=.019), with increasing absolute benefit over time from 1.2% (93.89% vs 92.73%) at 5 y to 2.1% (91.86% vs 89.73%) at 6 y, that was consistent across key subgroups. BCSS (HR, 0.706 [95% CI: 0.559-0.890]) was supportive of OS benefit. With a median iDFS follow-up of 66.3 mo, RIB + NSAI demonstrated a persistent iDFS benefit over NSAI alone (HR, 0.741 [95% CI: 0.646-0.849]; nominal 1-sided P<.0001), with the absolute iDFS benefit increasing from 4.1% (85.32% vs 81.24%) at 5 y to 5.3% (83.23% vs 77.92%) at 6 y. DDFS (HR, 0.744 [95% CI: 0.646-0.858]) and DRFS (HR, 0.738 [95% CI: 0.634-0.858]) benefits were also maintained. No new safety signals were observed.
Conclusions
With 6 y of follow-up and all pts off RIB (median, ≈3 y), the sustained reduction in recurrence risk and positive OS results with RIB + NSAI over NSAI alone continue to demonstrate a substantial and clinically relevant benefit for pts with high-risk stage II/III HR+/HER2− EBC, supporting the use of RIB + NSAI in the adjuvant setting across the broad NATALEE-eligible population.
[Slide 3]
Methods
Pts with HR+/HER2− EBC were randomized 1:1 to receive RIB (400 mg/d; 3 wk on/1 wk off for 3 y) + NSAI (letrozole 2.5 mg/d or anastrozole 1 mg/d for 5 y) or NSAI alone. Premenopausal women and men also received goserelin. Pts had stage IIA (if N1 or if N0 with additional high-risk factors), stage IIB, or stage III disease per AJCC, 8th ed. OS, breast cancer−specific survival (BCSS), iDFS, distant disease−free survival (DDFS), and distant recurrence−free survival (DRFS) were evaluated via Kaplan-Meier methods. Statistical comparisons were conducted by stratified log-rank test.
[Slide 1]
Rapid Oral session
543RO - DESTINY-Breast11: MRI-assessed objective responses during neoadjuvant treatment (NAT) with trastuzumab deruxtecan (T-DXd) followed by paclitaxel + trastuzumab + pertuzumab (THP) vs dose-dense doxorubicin + cyclophosphamide followed by THP (ddAC-THP) in HER2+ early breast cancer (eBC)
Speakers Jean-Francois Boileau (Montreal, Canada, QC)
Lecture Time 17:09 - 17:14
Abstract
Background
In the Phase 3 DESTINY-Breast11 study (NCT05113251), NAT with T-DXd-THP showed a statistically significant, clinically meaningful improvement in pathologic complete response (pCR) rate and improved safety profile vs ddAC-THP in high-risk, HER2+ eBC. We report analyses of radiological assessments conducted by breast MRI and association with pCR.
Methods
Patients (pts) were randomized to one of three arms, including T-DXd-THP (4+4 cycles) and ddAC-THP (4+4 cycles). Breast MRI scans were taken at screening, mid-NAT (after Cycle 4), and end of treatment (EOT). Objective response rate (ORR; per RECIST 1.1 per investigator; prespecified exploratory endpoint) was analyzed in pts with baseline scans, and association of response with pCR (ypT0/Tis ypN0) was assessed post hoc.
Results
Mid-NAT ORR and complete response [CR] rate were higher with T-DXd-THP (N=309) vs ddAC-THP (N=313) overall (ΔORR: 26.5%; ΔCR: 10.7%; Table), and across hormone receptor (HR) status (ORR: HR-, 80.0% [64/80] vs 57.3% [47/82]; HR+, 76.2% [173/227] vs 48.5% [112/231]). At EOT, ORRs were higher vs mid-NAT. Median best % change in target lesion size was greater with T-DXd-THP vs ddAC-THP at mid-NAT (-59% vs -35%) and further increased through EOT (-81% vs -74%). The positive predictive value of mid-NAT CR for pCR was 90.2% (T-DXd-THP) and 87.5% (ddAC-THP), but negative predictive value was lower at 36.6% and 43.6%, respectively. Table: 543RO
[Table - column alignment is collapsed in the screenshot; raw text as rendered:]
T-DXd-THP N=309 | Overall n % | pCR n %* | Non-pCR n %*
Mid-NAT objective response 239 77.3 13.3169 70.7 90.270 29.3
CR 41 64.1 22.737 66.7 54.34 9.8
PR 198 132 66 33.3 45.7
NR 70 38 32
EOT objective response 287 92.9 27.8202 70.4 83.785 29.6 16.3
CR 86 65.0 72 64.7 22.714 35.3 77.3
PR 201 7.1 130 71
NR 22 5 17
ddAC-THP N=313 | Overall n % | pCR n %* | Non-pCR n %*
Mid-NAT objective response 159 50.8 115 72.3 87.544 27.7 12.5
CR 8 2.6 7 71.5 41.61 28.5 58.4
PR 151 48.2 49.2108 43
NR 154 64 90
EOT objective response 273 87.2 24.6172 63.0 75.310137.0 24.7
CR 77 62.6 12.858 58.2 17.519 41.8 82.5
PR 196 114 82
NR 40 7 33
*Percentages based on the overall number of pts in the response category. NR, non-response; PR, partial response
[Slide 1]
1RO - Overall survival from the phase 3 postMONARCH trial of abemaciclib + fulvestrant vs placebo + fulvestrant for HR+, HER2- advanced breast cancer following progression on a prior CDK4/6 inhibitor + endocrine therapy
Speakers Kevin Kalinsky (Atlanta, United States of America)
Lecture Time 10:59 - 11:04
Abstract
Background
The phase 3 postMONARCH trial demonstrated a statistically significant improvement in progression-free survival (PFS) with abemaciclib + fulvestrant vs placebo + fulvestrant in HR+, HER2- advanced breast cancer (ABC) following progression on a prior CDK4/6i + endocrine therapy (ET). Here we report the final overall survival (OS) analysis.
Methods
postMONARCH was a global, double-blind, placebo-controlled study. Eligible patients had disease progression on a CDK4/6i + aromatase inhibitor as initial therapy for ABC or recurrence on/after adjuvant CDK4/6i + ET; no other prior therapy for ABC was permitted. Patients were randomized 1:1 to receive abemaciclib + fulvestrant or placebo + fulvestrant. The final OS analysis was pre-specified at 200 OS events (one-sided p-value boundary p = 0.023). Time-to-event analyses used Kaplan-Meier methods and stratified Cox models to estimate the HR and 95% confidence intervals (CI).
Results
368 patients were randomized 1:1 (abemaciclib + fulvestrant, n = 182; placebo + fulvestrant, n = 186). At data cutoff (06 Mar 2026), median follow-up was approximately 36 months with 200 events observed (90 [49.5%] vs 110 [59.1%]). Median OS was numerically longer with abemaciclib + fulvestrant vs placebo + fulvestrant: 32.1 months (95% CI 27.2-38.1) vs 24.6 months (95% CI 22.5-28.8); however, statistical significance was not reached (HR: 0.80, 95% CI 0.60-1.06; p=0.1145). Consistent OS differences were observed across subgroups. Updated PFS was consistent with the primary analysis (HR: 0.78, 95% CI 0.62-0.99; nominal p = 0.0390). PFS by blinded independent central review, time to second progression, and chemotherapy-free survival also favored abemaciclib. Safety was consistent with the established abemaciclib profile; no new signals were identified.
Conclusions
Abemaciclib + fulvestrant resulted in numerically longer median OS vs placebo + fulvestrant, however statistical significance was not reached. While absolute PFS benefit was modest, the overall evidence supports consideration of abemaciclib-based treatment for patients with HR+, HER2- ABC after disease progression on prior CDK4/6i + ET.
[Slide 1]
Rapid Oral session
4639RO - Final OS analysis of sacituzumab tirumotecan versus chemotherapy in previously treated locally recurrent or metastatic triple-negative breast cancer: Phase III OptiTROP-Breast01
Speakers Man Li (Dalian, China)
Lecture Time 10:15 - 10:20
Abstract
Background
Sacituzumab tirumotecan (sac-TMT) is a TROP2-directed ADC with a unique bifunctional linker and a belotecan-derivative topoisomerase I inhibitor payload. In phase III OptiTROP-Breast01, sac-TMT significantly improved PFS and demonstrated a statistically significant OS benefit vs physician's choice chemotherapy at the prespecified interim OS analysis (HR, 0.53; 95% CI, 0.36-0.78; one-sided p=0.0005) in previously treated locally recurrent/metastatic TNBC. Here, we report final OS with extended follow-up.
Methods
Pts with mTNBC who had received ≥ 2 prior systemic therapies, including ≥ 1 in the metastatic setting, were randomized 1:1 to sac-TMT or physician's choice chemotherapy. OS was a key secondary endpoint. OS was adjusted for subsequent ADC therapy using RPSFT model; censoring at subsequent ADC initiation was performed as a sensitivity analysis.
Results
A total of 263 pts were randomized to sac-TMT (n=130) or chemotherapy (n=133). As of Sep 17, 2025, the median follow-up was 29.4 mo. The statistically significant OS benefit observed at interim analysis was sustained in the final analysis. Median OS was 14.7 mo (95% CI, 12.1-20.1) with sac-TMT vs 9.9 mo (95% CI, 8.6-11.8) with chemotherapy (HR, 0.60; 95% CI, 0.45-0.80). The survival benefit was durable, with 24-mo OS rates of 33.8% vs 21.4% and 30-mo OS rates of 26.8% vs 13.2%. OS benefit was generally consistent across prespecified subgroups, including prior PD-1/PD-L1 inhibitor exposure and HER2-low disease. Subsequent ADC therapy was received by 27.8% of pts in the chemotherapy arm. After adjustment for subsequent ADC therapy, median OS was 14.7 vs 9.4 mo, with an adjusted HR of 0.55 (95% CI, 0.39-0.73); sensitivity analysis censoring pts at subsequent ADC initiation was consistent. No new safety signals were observed.
Conclusions
With nearly 30 mo of follow-up, sac-TMT sustained the statistically significant OS benefit previously observed at interim analysis. Sac-TMT provided durable survival benefit vs chemotherapy, including across clinically relevant subgroups and after adjustment for subsequent ADC therapy, supporting the use of sac-TMT in previously treated mTNBC.
[Slide 1]
681eP - Effect of adding carboplatin to taxane plus dual HER2 blockade on pathologic complete response in Neoadjuvant HER2-positive breast cancer: A meta-analysis
Presentation Number 681eP
Speakers Yakup Ergün (Diyarbakır, Türkiye)
Authors Yakup Ergün (Diyarbakır, Türkiye), Hayati Arvas (Mardin, Türkiye)
Abstract
Background
To evaluate whether the addition of carboplatin to taxane plus trastuzumab and pertuzumab (THP) in the neoadjuvant treatment of HER2-positive early breast cancer provides an incremental benefit in terms of pathologic complete response (pCR).
Methods
A systematic literature search was conducted from inception in PubMed, Embase, and the Cochrane Library. Studies comparing neoadjuvant TCHP versus THP were included. The primary endpoint was pCR in the intention-to-treat (ITT) population. Prespecified subgroup analyses were performed according to hormone receptor (HR) status, lymph node status, clinical stage, and tumor grade. Effect sizes were calculated as odds ratios (ORs) with 95% confidence intervals (CIs) using a random-effects model. Heterogeneity was assessed using the I² statistic.
Results
A total of 8 studies (2 prospective and 6 retrospective), comprising 2,529 patients, were included. In the ITT population, pCR rates were 62.2% in the TCHP arm and 61.7% in the THP arm. The addition of carboplatin did not result in a statistically significant improvement in pCR (OR 1.15; 95% CI 0.82-1.60; p=0.42; I²=68%). In the HR-negative subgroup, pCR rates were 74.5% versus 78.6% (OR 0.98; 95% CI 0.35-2.76), while in the HR-positive subgroup they were 54.4% versus 54.2% (OR 1.01; 95% CI 0.78-1.30), with no significant differences observed. Among node-negative patients, pCR rates were 67.8% and 67.3% (OR 1.09; 95% CI 0.60-1.98), and among node-positive patients 59.9% and 63.4% (OR 0.87; 95% CI 0.64-1.19). In clinical stage II disease, pCR rates were 63.0% and 65.7% (OR 0.88; 95% CI 0.60-1.29), and in stage III disease 59.8% and 63.6% (OR 0.87; 95% CI 0.48-1.55).
Conclusions
In neoadjuvant HER2-positive breast cancer, the addition of carboplatin to taxane plus dual HER2 blockade does not significantly improve pCR rates in the overall population or in any of the evaluated clinical subgroups. Based on the available evidence, a patient-tailored, selective approach appears more rational than the routine use of carboplatin.
[Slide 1]
Rapid Oral session
544RO - Final analysis of the GIM3 FATA trial: Treatment schedule and three aromatase inhibitors (AIs) comparison in postmenopausal HR-positive (HR+) early breast cancer (eBC)
Speakers Pietro De Placido (Napoli, Italy)
Lecture Time 16:15 - 16:20
Abstract
Background
Adjuvant AI therapy is standard for postmenopausal women with HR+ eBC. The optimal schedule [upfront vs sequential AI use after tamoxifen (T)] and the relative efficacy of the three third-generation AIs: anastrozole (A), exemestane (E), letrozole (L) remain unresolved. GIM3 FATA is the only randomized trial prospectively powered to address both questions in parallel, fully investigator-initiated and academically funded.
Methods
Postmenopausal women with HR+ eBC were randomly assigned 1:1:1:1:1:1 to 5 years of A, E, or L, given upfront or after 2 years of T. Co-primary endpoints were disease-free survival (DFS) for upfront vs switch and DFS across the three AIs. Secondary endpoints included overall survival (OS), distant DFS, distant relapse-free survival, relapse-free survival, and breast cancer-free interval, analyzed under updated STEEP 2.0 criteria.
Results
Between March 2007 and July 2012, 3697 patients were enrolled at 76 Italian centers; median age was 64 years. At a median follow-up of 88.9 months, 796 DFS (792 required) events and 491 deaths had occurred. For upfront vs switch there was no statistically significant difference for DFS (HR 0.95, 95% CI 0.82-1.09) and OS (HR 0.88, 95% CI 0.74-1.06). The 10-year DFS was 79.1% (95% CI 76.1-81.7) with A, 74.2% (95% CI 70.9-77.2) with E, and 76.6% (95% CI 73.3-79.5) with L (global log-rank p=0.028; pairwise comparison: E vs A statistically significant p=0.010, E vs L p=0.06, L vs A p=0.51). In the adjusted Cox model stratified by treatment schedule, the HR for DFS for E vs A was 1.23 (95% CI 1.04-1.46). 10-year OS was not different among A, E and L (global log-rank p=0.25). Toxicity differed by schedule (more musculoskeletal events with upfront; more T-related events with switch) and by AI (more hypercholesterolemia with non-steroidal AIs).
Conclusions
No schedule was superior, but E was associated with worse DFS. Schedule and AI choice should be individualized by tolerability and comorbidities. Pharmaco-economic considerations are advised since both E and L are nearly twice as expensive as A in most countries.
Clinical trial identification
This trial is registered with the European Clinical Trials Database, number 2006-004018-42, NCT00541086.
[Slide 1]
TOP-1
Breast-conserving surgery without RT or endocrine therapy
Age 70+; ER+ / HER2-
Small, low-grade breast cancer
n = 792
→ BCS alone | 5-year invasive local recurrence* 14.8%
*Ipsilateral invasive recurrence: 95% CI 12.3-17.5%; competing-risk estimate. Median follow-up 5.1 years.
Prospective observational cohort; no randomized comparator. 114/123 recurrences underwent salvage surgery.
Bouwman et al. ESMO 2026, 545RO. Eligibility: <=1 cm, grade 1/2 or <=2 cm, grade 1; clear margins.
[Slide 1]
[search icon] Proffered Paper session
LBA23 - Final results of TALENT: A neoadjuvant trial of T-DXd with or without anastrozole, or in sequence with chemotherapy for HER2-low, HR+ early-stage breast cancer
Speakers Sara A. Hurvitz (Seattle, United States of America)
Lecture Time 13:30 - 13:40
Abstract
Background
Pathologic complete response (pCR) in HR+/HER2-negative breast cancer (BC) is uncommon. T-DXd, a HER2-targeted antibody drug conjugate, improves progression-free and overall survival vs chemotherapy in metastatic HER2-low BC. TALENT (NCT04553770) is a phase II, 2-stage neoadjuvant study evaluating T-DXd + endocrine therapy or in sequence with chemotherapy in pts with HR+/HER2-low early BC.
Methods
Pts with untreated, operable invasive early HR+/HER2-low BC were randomized 1:1 to receive 6 cy of T-DXd (5.4 mg/kg q21d) alone (Arm A) or with anastrozole (1 mg PO QD) (Arm B). An arm was expanded if ≥2 pCR (RCB0) were observed. After 29 pts enrolled, subsequent pts received 8 cy. After Arms A/B, Arm C was added to evaluate 4 cy T-DXd → 4 cy docetaxel 75 mg/m2 + cyclophosphamide 600 mg/m2 (TC) in <58 pts. Biopsies were taken at baseline, pre-cy2 & surgery. Imaging/biomarkers were assessed at baseline, cy 2 & surgery. Endpoints: Residual Cancer Burden (RCB), safety, overall response rate (ORR) & biomarkers. Ki67, HER2, ER & PR were evaluated centrally, and TROP2 & HER2 levels were quantified (quant) by TROPLEX for Arms A & B.
Results
From 11/2020 - 02/2026, 132 pts were enrolled. Pts in Arm C were more likely to have node+ disease (81%) vs. Arms A/B (53%, 55%). Overall rates of pCR/near-pCR (RCB 0/1) were 16% (Arm A), 17% (Arm B), and 17% (10/58 Arm C). HER2 levels were higher in pts with RCB0 (2691 & 1221 amol/mm2) vs RCB1/2/3 (715-947 & 440-608 amol/mm2) at Baseline & cy 2, respectively. Table: LBA23
[Table]
| Arm A (N=45) n (%) | Arm B (N=29) n (%) | Arm C (N=58) n (%)
Baseline characteristics
Stage I/II/III | 0/32 (71)/13 (29) | 0/26 (90)/3 (10) | 2 (3)/43 (74)/13 (22)
Node+ | 24 (53) | 16 (55) | 47 (81)
Grade III | 19 (42) | 11 (38) | 29 (50)
Ki67>20% (central) | 33 (73) | 24 (83) | 43 (74)
Antigen quant (med amol/mm2)
Baseline→Cy2→Surgery
HER2 | 707→334→150 | 778→331→83 | -
TROP2 | 1097→1371→10011001→952→925- [as printed; columns run together]
Results: Evaluable
RCB0 | 3/42 (7) | 1/29 (3) | 5/55 (9)
ORR | 28/42 (67) | 19/29 (66) | 37/57 (65)
Results ITT | 6 cycles (N=15) | 8 cycles (N=30) | 6 cycles (N=14) | 8 cycles (N=15) | 8 cycles (N=58)
RCB0 | 0 | 3 (10) | 0 | 1 (7) | 5 (9)
RCB1 | 2 (13) | 2 (7) | 1 (7) | 3 (20) | 5 (9)
Gr >3 Treatment Emergent AE | 3 (20) | 8 (27) | 3 (21) | 2 (13) | 16 (28)
Interstitial Lung Disease (all Gr 2) | 0 | 0 | 1 (7) | 0 | 2 (3)
Conclusions
In this first study to report outcomes with neoadjuvant T-DXd in HR+/HER2-low BC, T-DXd–based therapy was associated with low pCR rates. ILD was rare. HER2 was higher in tumors with RCB0 versus RCB1/2/3, suggesting HER2 level may correlate with treatment outcome. HER2 levels declined significantly on treatment, whereas TROP2 expression remained stable. ER, PR, & Ki67 analyses will be presented.
[Slide 1]
Proffered Paper session
LBA50 - PANKU-Breast01: Randomized phase III study of izalontamab brengitecan (iza-bren) in previously treated unresectable locally advanced or metastatic (LA/M) hormone receptor-positive/HER2-negative (HR+/HER2-) breast cancer (BC)
Speakers Bo Lan (Beijing, China)
Lecture Time 14:35 - 14:45
[Abstract]
Background
Although first-line endocrine therapy plus CDK4/6 inhibitors has improved clinical outcome of HR+/HER2- BC, patients (pts) inevitably develop resistance and survival outcomes remain poor with subsequent therapy. Iza-bren is a first-in-class bispecific antibody-drug conjugate (ADC) against EGFR and HER3, containing a potent topoisomerase I inhibitor payload (Ed-04).
[Slide 2]
Methods
Eligible pts had unresectable LA/M HR+/HER2- BC (HR+, ER≥1% and/or PR≥1%; HER2-, IHC 0, 1+, or 2+/ISH-), progressed after at least 1L of endocrine therapy and 1 or 2L prior chemotherapy, and had previously received CDK4/6 inhibitors and taxanes. Pts were randomized 1:1 to receive iza-bren (2.5 mg/kg D1D8 Q3W) or TPC (eribulin, capecitabine, gemcitabine, or vinorelbine). The primary endpoint was PFS by blinded independent central review (BICR). Secondary endpoint included OS. The pre-planned final analysis for PFS serves as the interim analysis for OS.
[Slide 3]
Results
As of Jul 21, 2026, a total of 383 pts were randomized and treated (iza-bren/TPC, 190/193). Median follow-up for PFS was 15.24 vs 13.63 mo (iza-bren/TPC). Iza-bren significantly improved PFS by BICR vs TPC; mPFS was 8.18 mo (95% CI, 6.93-8.58) vs 4.01 mo (95% CI, 2.92-4.30) (HR, 0.41; 95% CI, 0.33-0.53; P<0.0001). OS was immature at the interim analysis, and no detrimental effect was observed. The cORR by BICR was 40.5% with iza-bren vs 20.2% with TPC, and mDOR was 6.93 vs 4.21 mo, respectively. Grade ≥3 TRAEs were predominantly hematologic in nature. TRAEs were manageable with standard supportive care, and only 1.6% of pts discontinued iza-bren treatment due to TRAEs. Adjudicated ILD occurred in 2 (1.1%) pts with iza-bren (grade 1 or 2). No new safety signals were identified.
Conclusions
The study met its primary endpoint at the prespecified analysis. Iza-bren demonstrated a statistically significant and clinically meaningful improvement in PFS vs TPC in previously treated HR+/HER2- BC. The safety profile was manageable and consistent with previous studies. The results support iza-bren as a new standard of care option in this population in China.
[Slide 1]
[search icon] Proffered Paper session
LBA25 - Adjuvant ribociclib (RIB) + nonsteroidal aromatase inhibitor (NSAI) in patients (pts) with HR+/HER2− early breast cancer (EBC): NATALEE 6-y overall survival (OS) and efficacy outcomes
Speakers Dennis J. Slamon (Los Angeles, United States of America)
Lecture Time 14:25 - 14:35
Abstract
Background
The phase 3 NATALEE trial demonstrated a statistically significant invasive disease–free survival (iDFS) benefit with adjuvant RIB + NSAI in pts with high-risk stage II/III HR+/HER2− EBC. We present a prespecified analysis of OS and efficacy outcomes with 6 y of follow-up.
Methods
Pts with HR+/HER2− EBC were randomized 1:1 to receive RIB (400 mg/d; 3 wk on/1 wk off for 3 y) + NSAI (letrozole 2.5 mg/d or anastrozole 1 mg/d for 5 y) or NSAI alone. Premenopausal women and men also received goserelin. Pts had stage IIA (if N1 or if N0 with additional high-risk factors), stage IIB, or stage III disease per AJCC, 8th ed. OS, breast cancer–specific survival (BCSS), iDFS, distant disease–free survival (DDFS), and distant recurrence–free survival (DRFS) were evaluated via Kaplan-Meier methods. Statistical comparisons were conducted by stratified log-rank test.
Results
At the data cutoff (15 May 2026), all pts were off RIB for a median of 38 mo and beyond the predefined NSAI study regimen. With a median OS follow-up of 66.5 mo, RIB + NSAI showed an OS benefit over NSAI alone (HR, 0.809 [95% CI: 0.661-0.989]; nominal 1-sided P=.019), with increasing absolute benefit over time from 1.2% (93.89% vs 92.73%) at 5 y to 2.1% (91.86% vs 89.73%) at 6 y, that was consistent across key subgroups. BCSS (HR, 0.706 [95% CI: 0.559-0.890]) was supportive of OS benefit. With a median iDFS follow-up of 66.3 mo, RIB + NSAI demonstrated a persistent iDFS benefit over NSAI alone (HR, 0.741 [95% CI: 0.646-0.849]; nominal 1-sided P<.0001), with the absolute iDFS benefit increasing from 4.1% (85.32% vs 81.24%) at 5 y to 5.3% (83.23% vs 77.92%) at 6 y. DDFS (HR, 0.744 [95% CI: 0.646-0.858]) and DRFS (HR, 0.738 [95% CI: 0.634-0.858]) benefits were also maintained. No new safety signals were observed.
Conclusions
With 6 y of follow-up and all pts off RIB (median, ≈3 y), the sustained reduction in recurrence risk and positive OS results with RIB + NSAI over NSAI alone continue to demonstrate a substantial and clinically relevant benefit for pts with high-risk stage II/III HR+/HER2− EBC, supporting the use of RIB + NSAI in the adjuvant setting across the broad NATALEE-eligible population.
[Slide 1]
GIM3 FATA | ESMO 2026
Are All AIs Equal - Or Is One Better?
MV Onco
[large question mark illustration]
[three pill bottles labelled:]
ANASTROZOLE
LETROZOLE
EXEMESTANE
10 YEARS LATER...
Did the choice of AI really matter?
The Results May Surprise You.
[Slide 2]
GIM3 FATA | ESMO 2026
PART 1/2
Upfront AI or Tamoxifen First - Does Sequencing Matter?
MV Onco
01 WHY GIM3 FATA?
• Postmenopausal HR+ early breast cancer.
• Adjuvant aromatase inhibitors (AIs) are standard.
• But TWO questions remained:
• Upfront AI or tamoxifen → AI?
• Are all three AIs equally effective?
• GIM3 FATA tested BOTH questions.
[illustration of woman at a signpost: "Upfront AI (5 years)" OR "Tamoxifen (2 years) → AI (3 years)"]
02 TRIAL DESIGN
• Phase III | Randomized | 3,697 patients
• 76 Italian centres | Median age 64 years
• SIX ARMS - 1:1:1:1:1:1
UPFRONT: 5 years of AI
SWITCH: Tamoxifen 2 years → AI 3 years
• Three AIs evaluated:
• Anastrozole
• Letrozole
• Exemestane
• Co-primary endpoints: DFS by schedule and DFS by AI.
[boxes:]
Upfront AI
5 years
• Anastrozole
• Letrozole
• Exemestane
Tamoxifen → AI
Tamoxifen 2 years → AI 3 years
• Anastrozole
• Letrozole
• Exemestane
03 DID UPFRONT AI IMPROVE DFS?
NO SIGNIFICANT DIFFERENCE
• Upfront AI vs tamoxifen → AI
• DFS HR 0.95
• 95% CI 0.82 - 1.09
• Neither schedule demonstrated superiority.
[calendar graphic:]
Disease-Free Survival (DFS)
HR 0.95
95% CI 0.82 - 1.09
04 DID OVERALL SURVIVAL IMPROVE?
NO SIGNIFICANT OS BENEFIT
• OS HR 0.88
• 95% CI 0.74 - 1.06
• Median follow-up: 88.9 months
• 796 DFS events
• 491 deaths
• No demonstrated survival advantage with upfront AI.
[calendar graphic:]
Overall Survival (OS)
HR 0.88
95% CI 0.74 - 1.06
Median follow-up 88.9 months
05 TAKE-HOME
Upfront AI ≠ Proven Superior Survival
• Starting with an AI did not significantly improve DFS or OS compared with tamoxifen followed by AI.
• Both schedules remain reasonable options.
• Individualize sequencing by recurrence risk, tolerability and comorbidities.
NEXT: Are all three aromatase inhibitors equally effective?
[Slide 3]
GIM3 FATA | ESMO 2026
PART 2/2
Three Aromatase Inhibitors - Are They Really Equal?
MV Onco
01 WHICH AI PERFORMED BEST?
10-YEAR DISEASE-FREE SURVIVAL
• Anastrozole - 79.1%
• Letrozole - 76.6%
• Exemestane - 74.2%
Global log-rank p = 0.028
Anastrozole showed the highest DFS.
[three pill bottles: Anastrozole, Letrozole, Exemestane]
02 WERE DIFFERENCES SIGNIFICANT?
Exemestane vs Anastrozole
• DFS HR 1.23 (95% CI 1.04 - 1.46)
• 23% higher relative hazard of a DFS event with exemestane.
Pairwise comparisons:
• Exemestane vs Anastrozole: p = 0.010
• Exemestane vs Letrozole: p = 0.060
• Letrozole vs Anastrozole: p = 0.510
Only E vs A was statistically significant.
[balance scale graphic: A vs E] Exemestane had worse DFS than Anastrozole
03 DID BETTER DFS TRANSLATE INTO OS?
NO SIGNIFICANT OS DIFFERENCE
• 10-year OS across the three AIs:
Global log-rank p = 0.25
Better DFS with anastrozole vs exemestane did NOT establish longer survival.
[hourglass graphic] DFS benefit ≠ Proven OS benefit
04 WHAT ABOUT TOXICITY?
UPFRONT AI
• More musculoskeletal adverse events.
TAMOXIFEN → AI
• More tamoxifen-related adverse events.
NONSTEROIDAL AIs
• Anastrozole and letrozole:
- More hypercholesterolemia.
AI choice should consider toxicity, comorbidities and adherence.
05 TAKE-HOME
Are All Aromatase Inhibitors Equal?
Not necessarily.
• Anastrozole showed significantly better DFS than exemestane.
• Letrozole was not significantly different from either AI.
• No demonstrated OS advantage among the three.
• DFS differences require interpretation alongside distant-recurrence outcomes and other trials.
• Choose the AI thoughtfully - not solely by class.
[dartboard graphic with labels Anastrozole, Letrozole, Exemestane]
[Slide 1]
NATALEE | ESMO 2026
Part 1 – Has Ribociclib Finally Improved Overall Survival?
MV Onco
01 — THE TRIAL
• NATALEE | Phase III
• Stage II-III HR+/HER2- early breast cancer
• Ribociclib 400 mg/day
3 weeks ON / 1 week OFF × 3 years
+ nonsteroidal aromatase inhibitor
VS
• Aromatase inhibitor alone
02 — SIX-YEAR OVERALL SURVIVAL
Ribociclib + AI vs AI alone
91.86% vs 89.73%
Absolute OS gain: +2.1 percentage points
HR 0.809 | 95% CI 0.661 – 0.989
Approximately 19% lower hazard of death.
03 — IS OS STATISTICALLY SIGNIFICANT?
• Nominal one-sided P = 0.019
• 95% CI excludes 1.
• BUT...
• Did OS cross the prespecified multiplicity-adjusted significance boundary?
• Formal OS significance not yet established from the abstract.
04 — TAKE-HOME
• An encouraging OS signal at 6 years.
• Absolute OS difference: +2.1 percentage points.
• iDFS benefit was already established.
• Nominal significance ≠ Confirmed formal OS success.
• Await full statistical analysis.
[Slide 2]
NATALEE | ESMO 2026
Part 2 – Does the Benefit Persist After Ribociclib Stops?
MV Onco
1. SIX-YEAR iDFS
Ribociclib + AI vs AI alone
83.23% vs 77.92%
Absolute iDFS gain: +5.3 percentage points
HR 0.741 95% CI 0.646–0.849
Approximately 26% lower hazard of invasive disease or death.
2. DISTANT RECURRENCE & CANCER DEATH
Distant disease-free survival (DDFS) : HR 0.744
Distant recurrence-free survival (DRFS) : HR 0.738
Breast cancer-specific survival (BCSS) : HR 0.706
All favour ribociclib.
3. DOES THE BENEFIT LAST?
Ribociclib treatment: 3 years
Median time off ribociclib: 38 months
Absolute iDFS benefit:
At 5 years: +4.1 percentage points → At 6 years: +5.3 percentage points
Benefit persists after treatment stops.
No new safety signals observed.
4. TAKE-HOME
• Three years of ribociclib.
• Sustained iDFS benefit at six years.
• Absolute iDFS separation continues to increase.
• But longer follow-up is needed to distinguish delayed recurrence from durable prevention.
[Slide 1]
postMONARCH | ESMO 2026
After CDK4/6 Progression: Does Abemaciclib Help?
MV Onco
HR-positive / HER2-negative advanced breast cancer
Progression after CDK4/6 inhibitor + endocrine therapy
368 patients • Randomised 1:1
Abemaciclib - fulvestrant 182 patients
Placebo - fulvestrant 186 patients
Original median PFS
6.0 months vs 5.3 months
Modest but statistically significant benefit
HR 0.73
Final median OS
32.1 months vs 24.6 months
Numerically longer; not statistically significant
HR 0.80 • p = 0.1145
Better disease control. Survival benefit remains unproven.
An option to consider in selected patients after prior CDK4/6 progression.
[cartoon illustrations of patient and physician]
[Slide 2]
postMONARCH | Part 1
Abemaciclib After CDK4/6 Progression?
MV Onco
01 — THE QUESTION
• HR-positive, HER2-negative advanced breast cancer
• Cancer progresses on a CDK4/6 inhibitor + endocrine therapy.
• Can adding abemaciclib to fulvestrant improve disease control?
02 — WHO WAS INCLUDED?
• Progression on: CDK4/6 inhibitor + aromatase inhibitor as first treatment for advanced disease
OR
• Recurrence during or after adjuvant CDK4/6 inhibitor + endocrine therapy
• No other prior treatment for advanced disease.
03 — WHAT WAS COMPARED?
• 368 patients • Randomised 1:1
Abemaciclib + fulvestrant 182 patients
versus
Placebo + fulvestrant 186 patients
• Phase III • Double-blind
04 — TAKE-HOME
• The trial tested adding abemaciclib to a new endocrine backbone after progression on prior CDK4/6 therapy.
• Does CDK4/6 inhibition still have a role after progression?
[Slide 3]
postMONARCH | Part 2
PFS Benefit. Survival Benefit Unproven.
MV Onco
01 ORIGINAL PFS RESULTS
Median progression-free survival
• Abemaciclib + fulvestrant: 6.0 months
• Placebo + fulvestrant: 5.3 months
HR 0.73 | 95% CI 0.57–0.95
Statistically significant benefit.
Median difference: 0.7 months.
02 UPDATED PFS
The PFS benefit persisted.
HR 0.78 | 95% CI 0.62–0.99
Nominal p = 0.0390
03 FINAL OVERALL SURVIVAL
Median overall survival
• Abemaciclib + fulvestrant: 32.1 months
• Placebo + fulvestrant: 24.6 months
HR 0.80 | 95% CI 0.60–1.06
p = 0.1145
Numerically longer survival.
NOT statistically significant.
04 TAKE-HOME
• Modest absolute PFS benefit.
• Overall survival numerically favoured abemaciclib + fulvestrant.
• A survival benefit remains UNPROVEN.
[Slide 4]
postMONARCH | Part 3
What Does It Mean for Practice?
MV Onco
01 — WHAT THE TRIAL SUPPORTS
• Abemaciclib + fulvestrant can improve disease control after prior CDK4/6 inhibitor therapy.
• The absolute PFS benefit was modest.
02 — WHAT IT DOES NOT PROVE
• Longer overall survival was NOT statistically established.
• A 7.5-month difference in median OS does not mean a proven 7.5-month survival gain.
03 — KNOW THE LIMITS
• Compared with fulvestrant alone.
• No direct comparison with other active treatment options.
• No other prior treatment for advanced disease was permitted.
• No new safety signals identified.
04 — TAKE-HOME
• Reasonable option after prior CDK4/6 progression.
• PFS benefit remains consistent.
• Numerically longer OS, but not statistically significant.
• Supports considering abemaciclib + fulvestrant in selected patients.
[Slide 1]
Proffered Paper session
LBA23 - Final results of TALENT: A neoadjuvant trial of T-DXd with or without anastrozole, or in sequence with chemotherapy for HER2-low, HR+ early-stage breast cancer
Speakers Sara A. Hurvitz (Seattle, United States of America)
Lecture Time 13:30 - 13:40
[Abstract]
Background
Pathologic complete response (pCR) in HR+/HER2-negative breast cancer (BC) is uncommon. T-DXd, a HER2-targeted antibody drug conjugate, improves progression-free and overall survival vs chemotherapy in metastatic HER2-low BC. TALENT (NCT04553770) is a phase II, 2-stage neoadjuvant study evaluating T-DXd + endocrine therapy or in sequence with chemotherapy in pts with HR+/HER2-low early BC.
[Slide 2]
Conclusions
In this first study to report outcomes with neoadjuvant T-DXd in HR+/HER2-low BC, T-DXd−based therapy was associated with low pCR rates. ILD was rare. HER2 was higher in tumors with RCB0 versus RCB1/2/3, suggesting HER2 level may correlate with treatment outcome. HER2 levels declined significantly on treatment, whereas TROP2 expression remained stable. ER, PR, & Ki67 analyses will be presented.
Clinical trial identification
NCT04553770.
Legal entity responsible for the study
Translational Research In Oncology - US (TRIO-US).
[Slide 3]
TALENT Trial | ESMO 2026 | LBA23
HR+/HER2-low early breast cancer
Outcome | T-DXd | T-DXd + AI | T-DXd → TC
N | 45 | 29 | 58
ORR | 67% | 66% | 65%
pCR | 7% | 3% | 9%
pCR + near-pCR | 16% | 17% | 17%
[Slide 1]
ESMO CONGRESS | MADRID 2026
Sara Tolaney, MD, MPH
HER2-Positive Breast Cancer: ADC Strategies for First Line Metastatic and Early Disease
Industry Sponsored Satelite Symposium:
Redrawing the Breast Cancer Roadmap Advancing Novel Therapies Into First-Line and Early Disease
Date: Friday, October 23, 2026
Time: 09:45 - 11:15 CEST | 3:45 - 5:15 AM EST
Location: Pamplona Auditorium, Hall 5
[headshot]
Dana-Farber Cancer Institute
[Slide 1]
Proffered Paper session
LBA24 - Final analysis of NRG oncology/NSABP B-42, a randomized, double-blinded, placebo-controlled trial of extended letrozole in postmenopausal women with hormone-receptor positive breast cancer who have completed previous adjuvant therapy with an aromatase inhibitor
Speakers Eleftherios P. Mamounas (Orlando, United States of America)
Lecture Time 14:15 - 14:25
Abstract
Background
NSABP B-42 evaluated whether 5 yrs of letrozole (L) vs placebo (P) improves disease-free survival (DFS) in patients who received 5 yrs of endocrine therapy. Previous 10-yr results showed that L significantly improved the primary endpoint of DFS and secondary endpoints of breast cancer-free interval (BCFI) and distant recurrence (DR) with no significant improvement in overall survival (OS). Here we report the final trial analysis of 15-yr outcome data.
Methods
A total of 3,966 postmenopausal patients with stage I-III, hormone-receptor positive breast cancer, disease-free after 5 yrs of an aromatase inhibitor (AI) or ≤3 yrs of tamoxifen à AI for total of 5 yrs, were randomized 1:1 to 5 yrs of L 2.5 mg PO daily or P. Stratification was by pathologic nodal status, prior tamoxifen or not, and baseline DEXA T scores (>-2.0, ≤-2.0 SD). Primary endpoint was DFS. Secondary endpoints included OS, BCFI and DR. Differences in outcomes between L and P were assessed by stratified log-rank tests and Cox proportional hazards models.
Results
Follow-up of trial patients was completed in 08/26, with median follow-up of 15.9 yrs. Since the 10-yr update, 538 additional DFS events were recorded. The 15-yr results continue to show a modest but significant improvement in DFS (HR=0.85, 95%CI=0.77 to 0.94,15-yr DFS: P=56.5%, L=61.6%), BCFI (HR=0.78, 95%CI=0.67 to 0.92,15-yr BCFI risk: P=18.3%, L=14.7%) and DR (HR=0.72, 95%CI=0.57 to 0.91,15-yr DR risk: P=9.7%, L=6.9%). The L effect on DFS was consistent across subgroups by stratification factors. There was no significant improvement in OS (HR=0.92, 95%CI=0.82 to 1.05, 15-yr OS: P=72.3%, L=74.0%).
Conclusions
With over 15 yrs of follow-up, the B-42 trial continues to demonstrate a sustained and clinically meaningful benefit with extended letrozole therapy on DFS and key secondary endpoints consistent with the original and 10-yr updated results. No attenuation of treatment effect was observed from year 10 to year 15.
[Slide 1]
Proffered Paper session
LBA13 - Trastuzumab rezetecan (SHR-A1811) in HER2-low advanced breast cancer (BC): A randomized, phase 3 study (HORIZON-Breast06)
Speakers Ying Fan (Beijing, China)
Lecture Time 13:40 - 13:50
Abstract
Background
HORIZON-Breast06 is a pivotal, randomized, multicenter, open-label, phase 3 study comparing trastuzumab rezetecan (a HER2 ADC) with physician's choice of chemotherapy in patients (pts) with HER2-low advanced BC who had received ≤1 prior line of chemotherapy for metastatic disease, with prior endocrine therapy required for hormone receptor (HR)-positive disease.
Methods
Pts were randomized (1:1) to receive trastuzumab rezetecan (6.4 mg/kg IV, Q3W) or physician's choice of chemotherapy (taxanes, eribulin, capecitabine, or gemcitabine). The co-primary endpoints were PFS by blinded independent central review (BICR) in chemo-naïve (0 prior line of chemotherapy for metastatic disease) and overall pts.
Results
As of Mar 20, 2026, 551 pts were randomized (trastuzumab rezetecan, n=277; chemotherapy, n=274; chemo-naïve: 81.5%; HR-positive: 73.0%; prior CDK4/6 inhibitor: 64.8%). Median follow-up was 18.0 months (95% CI 16.8–19.3) for all patients. Trastuzumab rezetecan significantly prolonged PFS by BICR in both chemo-naïve (median 16.6 vs. 6.8 months; HR 0.25, 95% CI 0.19–0.33; P<0.0001; table) and overall pts (median 16.4 vs. 6.8 months; HR 0.27, 95% CI 0.21–0.34; P<0.0001). The PFS benefit was consistent across all prespecified subgroups, including HR-negative disease (16.5 vs. 6.8 months; HR 0.34) and HR-positive disease (16.4 vs. 6.7 months; HR 0.24). OS data remain immature, with a trend favoring trastuzumab rezetecan. Grade ≥3 treatment-related adverse events occurred in 84.1% (trastuzumab rezetecan) and 67.9% (chemotherapy) of patients, respectively. Interstitial lung disease (ILD) was reported in only 7 pts (2.5%) with trastuzumab rezetecan. Table: LBA13
[Table] Chemo-naïve patients: Trastuzumab rezetecan (N=225) | Chemotherapy (N=224) | Overall patients: Trastuzumab rezetecan (N=277) | Chemotherapy (N=274)
PFS
Events, n (%) | 91 (40.4) | 146 (65.2) | 130 (46.9) | 185 (67.5)
Median (95% CI), months | 16.6 (14.0–19.4) | 6.8 (5.7–7.0) | 16.4 (14.0–16.8) | 6.8 (5.7–6.9)
12-mo rate, % (95% CI) | 65.2 (57.6–71.8) | 18.9 (12.8–25.8) | 63.1 (56.4–69.1) | 18.0 (12.7–24.1)
HR (95% CI); 1-sided P | 0.25 (0.19–0.33); P<0.0001 | 0.27 (0.21–0.34); P<0.0001
OS
Events, n (%) | 43 (19.1) | 55 (24.6) | 66 (23.8) | 77 (28.1)
12-mo rate, % (95% CI) | 92.0 (87.3–95.1) | 83.0 (76.9–87.6) | 90.6 (86.2–93.6) | 81.4 (75.9–85.8)
ORR, % (95% CI) | 76.0 (69.9–81.4) | 43.3 (36.7–50.1) | 75.5 (69.9–80.4) | 41.2 (35.4–47.3)
Conclusions
Trastuzumab rezetecan significantly improved PFS over physician's choice of chemotherapy in pts with HER2-low advanced BC regardless of prior lines of chemotherapy or HR status, with a trend toward OS benefit and a favorable safety profile including a low incidence of ILD.
[Slide 1]
[search icon] Proffered Paper session
LBA50 - PANKU-Breast01: Randomized phase III study of izalontamab brengitecan (iza-bren) in previously treated unresectable locally advanced or metastatic (LA/M) hormone receptor-positive/HER2-negative (HR+/HER2-) breast cancer (BC)
Speakers Bo Lan (Beijing, China)
Lecture Time 14:35 - 14:45
Abstract
Background
Although first-line endocrine therapy plus CDK4/6 inhibitors has improved clinical outcome of HR+/HER2- BC, patients (pts) inevitably develop resistance and survival outcomes remain poor with subsequent therapy. Iza-bren is a first-in-class bispecific antibody-drug conjugate (ADC) against EGFR and HER3, containing a potent topoisomerase I inhibitor payload (Ed-04).
Methods
Eligible pts had unresectable LA/M HR+/HER2- BC (HR+, ER≥1% and/or PR≥1%; HER2-, IHC 0, 1+, or 2+/ISH-), progressed after at least 1L of endocrine therapy and 1 or 2L prior chemotherapy, and had previously received CDK4/6 inhibitors and taxanes. Pts were randomized 1:1 to receive iza-bren (2.5 mg/kg D1D8 Q3W) or TPC (eribulin, capecitabine, gemcitabine, or vinorelbine). The primary endpoint was PFS by blinded independent central review (BICR). Secondary endpoint included OS. The pre-planned final analysis for PFS serves as the interim analysis for OS.
Results
As of Jul 21, 2026, a total of 383 pts were randomized and treated (iza-bren/TPC, 190/193). Median follow-up for PFS was 15.24 vs 13.63 mo (iza-bren/TPC). Iza-bren significantly improved PFS by BICR vs TPC; mPFS was 8.18 mo (95% CI, 6.93-8.58) vs 4.01 mo (95% CI, 2.92-4.30) (HR, 0.41; 95% CI, 0.33-0.53; P<0.0001). OS was immature at the interim analysis, and no detrimental effect was observed. The cORR by BICR was 40.5% with iza-bren vs 20.2% with TPC, and mDOR was 6.93 vs 4.21 mo, respectively. Grade ≥3 TRAEs were predominantly hematologic in nature. TRAEs were manageable with standard supportive care, and only 1.6% of pts discontinued iza-bren treatment due to TRAEs. Adjudicated ILD occurred in 2 (1.1%) pts with iza-bren (grade 1 or 2). No new safety signals were identified.
Conclusions
The study met its primary endpoint at the prespecified analysis. Iza-bren demonstrated a statistically significant and clinically meaningful improvement in PFS vs TPC in previously treated HR+/HER2- BC. The safety profile was manageable and consistent with previous studies. The results support iza-bren as a new standard of care option in this population in China.
[Slide 1]
FOURLIGHT-1 | ESMO 2026
After CDK4/6 Progression...
Can CDK4 Still Be Targeted?
MV Onco
HR+/HER2− advanced breast cancer
Progression on prior adjuvant or first-line CDK4/6 inhibitor
Randomized phase II • Open-label • 263 patients
Atirmociclib 300 mg twice daily
+ fulvestrant
n = 126
versus
Investigator's choice
Fulvestrant OR
everolimus + exemestane
n = 137
[illustration: cell-cycle wheel (G1, S, G2, M, "Cancer cell cycle") with a broken brake labeled "Prior CDK4/6 inhibitor" / "Disease progressed" and a new brake labeled "Atirmociclib Selective CDK4 inhibitor" plus a lever "+ Fulvestrant Endocrine suppression"]
MEDIAN PFS
Atirmociclib +
fulvestrant
9.4
months
vs
6.6
months
Investigator's
choice
HR 0.60 | 95% CI 0.440 – 0.825
40% lower hazard of progression or death
OTHER EFFICACY OUTCOMES
Numerically higher ORR
19.3% vs 11.3%
Median response duration
14.8 vs 9.3 months
Clinical benefit ≥24 weeks
61.9% vs 46.0%
SAFETY
[blood cell illustration]
Treatment-related:
• Neutropenia 46.4%
• Leukopenia 32.8%
4.0% discontinued atirmociclib
because of treatment-related
adverse events
Cytopenia grades not specified in abstract
TAKE-HOME
✓ CDK4 can remain a therapeutic target after CDK4/6 inhibitor progression.
✓ Promising phase II PFS benefit.
✓ Overall survival immature.
[Slide 1]
ESMO 2026 / BREAST CANCER
24 OCT 2026 / PRE-CONGRESS WATCH
RIBOCICLIB + NSAI • NATALEE • PHASE 3
DOES ADJUVANT BENEFIT LAST?
6-year follow-up in HR-positive / HER2-negative early breast cancer
[illustration of tumor cells and antibody]
WHO IS THIS ABOUT?
Stage II–III HR+/HER2– early breast cancer
Adjuvant ribociclib + nonsteroidal aromatase inhibitor vs NSAI alone
Ribociclib 400 mg (3 weeks on / 1 week off) + endocrine therapy
Question now: does earlier iDFS benefit remain durable at 6 years?
LBA25 • 6-YEAR FOLLOW-UP • PRESENTATION PENDING
KEY READOUT
OS maturity • absolute iDFS difference • late recurrences
Grade 3+ toxicity • treatment discontinuation • clinical relevance
WHAT WE NEED TO SEE IN MADRID
DURABILITY: Is the early iDFS gain sustained over time?
SURVIVAL: Is there an emerging OS signal, or is follow-up still immature?
TRADE-OFF: How should efficacy be weighed against toxicity and treatment burden?
Presented data pending • Do not infer OS benefit before the full readout
Source: ESMO 2026 programme listing • NATALEE study context • drozdogan.com
[Slide 1]
ESMO 2026 / BREAST CANCER
23 OCT 2026 / PRE-CONGRESS WATCH
TRASTUZUMAB DERUXTECAN • TALENT • LBA23
ARE ADCs MOVING INTO CURATIVE CARE?
A neoadjuvant strategy in HER2-low / HR-positive early breast cancer
[illustration: ADC binding HER2-low tumor cell; labels "ADC", "HER2-low tumor cell"]
WHO IS THIS FOR?
HER2-low / HR+ early breast cancer
TALENT: neoadjuvant trastuzumab deruxtecan ± anastrozole or sequenced with chemotherapy
Core question: Can T-DXd move from metastatic disease into the preoperative curative setting?
And where should it sit relative to endocrine therapy or chemotherapy?
LBA23 • PRESENTATION PENDING • FULL DATA NOT YET DISCLOSED
KEY READOUT
• pathologic response / residual disease
• chemotherapy-free activity
• endocrine contribution
• ILD / pneumonitis and toxicity
• future treatment architecture
WHAT SHOULD WE LOOK FOR IN MADRID?
ACTIVITY: Will we see meaningful preoperative tumor response?
POSITIONING: What is the best sequence among the ADC, anastrozole and chemotherapy?
BALANCE: How should efficacy, toxicity and treatment burden be weighed in early disease?
No full presentation yet • pCR, survival or practice change should not be assumed before the full readout
Source: ESMO 2026 programme listing • TALENT study context • drozdogan.com
PRE-CONGRESS WATCH
[Slide 1]
SWITCH | ESMO 2026
New Target. Same Payload. Same Resistance?
MV Onco
[illustration: ADC-resistant cancer cell with HER2 and TROP2 receptors]
HER2-targeted ADC
TOP1i
Different targets.
Same payload class.
TROP2-targeted ADC
TOP1i
ADC-resistant cancer cell
Different payload class may overcome resistance
Microtubule inhibitor (MMAE)
Microtubule inhibitor → TOP1i
TOP1i
Response observed (2/54)
54 patients | Phase II | 94.4% previously exposed to TOP1i ADCs
ONLY 2/54 RESPONDED
A: 0% | B: 8.3% | C: 0% | D: 5%
TAKE-HOME
• Changing the target alone produced limited responses.
• Payload cross-resistance may matter more than antigen switching.
• Change the weapon - not just the address?
• Small phase II trial. Hypothesis-generating.
[Slide 2]
SWITCH | ESMO 2026
PART 1/2
New Target. Same Payload. Does It Work?
MV Onco
01 WHY SWITCH?
• HER2-negative metastatic breast cancer
• Resistance to antibody-drug conjugates (ADCs) is an emerging challenge.
• After progression on an ADC, what should we change?
○ The antigen target?
○ The cytotoxic payload?
• Can changing the target alone overcome resistance?
[illustration: Before ADC response / After ADC progression (resistance)]
02 TRIAL DESIGN
• Phase II | Prospective | Open-label
• 54 patients | HER2-negative metastatic breast cancer
• Progression after ≥1 prior ADC
• Four investigational ADC cohorts assigned according to prior treatment history.
• Primary endpoint: Investigator-assessed ORR
[four bottles:]
SHR-A1811 Cohort A (n=10)
SHR-A1921 Cohort B (n=12)
SHR-A2009 Cohort C (n=12)
SHR-A2102 Cohort D (n=20)
All FOUR ADCs carried a TOP1 inhibitor payload
03 WHICH ADCs WERE TESTED?
• Four investigational ADCs with different targets and constructs.
• All used the SAME TOP1 inhibitor payload.
• Cohort A - SHR-A1811 (n=10)
• Cohort B - SHR-A1921 (n=12)
• Cohort C - SHR-A2009 (n=12)
• Cohort D - SHR-A2102 (n=20)
[ADC illustration] Different antigen targets and ADC constructs / Same cytotoxic payload (TOP1 inhibitor)
04 HOW HEAVILY PRETREATED?
• 94.4% had prior TOP1i-based ADC exposure.
• Most patients had already received an ADC with the same payload class.
• Could another TOP1i-based ADC restore sensitivity?
[pictogram] 94.4% had prior TOP1i-based ADC exposure
05 WHAT WERE THE RESULTS?
CONFIRMED OBJECTIVE RESPONSE RATE
• Cohort A - 0%
• Cohort B - 8.3%
• Cohort C - 0%
• Cohort D - 5%
Only 2 of 54 patients responded (3.7%).
TAKE-HOME
• Changing the ADC construct while retaining a TOP1i payload produced very limited responses.
• NEXT: Is payload cross-resistance the missing explanation?
[Slide 3]
SWITCH | ESMO 2026
Change the Target - Or Change the Payload?
PART 2/2
MV Onco
01 WHERE DID RESPONSES OCCUR?
ONLY AFTER SWITCHING PAYLOAD CLASS
Both responders had previously received:
Disitamab vedotin (RC48)
• Microtubule inhibitor payload (MMAE)
[ADC illustration] RC48 (Disitamab vedotin) Target: HER2 Payload: MMAE (microtubule inhibitor)
Then switched to: TOP1i-based ADC - Different target, Payload: TOP1 inhibitor
2 responses among 54 patients
→ No responses were observed after switching between ADCs with the same TOP1i payload class.
02 WHY DID TARGET SWITCHING FAIL?
POSSIBLE PAYLOAD CROSS-RESISTANCE
ADC resistance may involve:
• Antigen loss or downregulation
• Impaired internalization
• Drug efflux mechanisms
• Altered TOP1 activity
• Enhanced DNA damage repair
[cell illustration labelled: Antigen loss downregulation, Impaired internalization, Drug efflux, Altered TOP1 activity, Enhanced DNA damage repair]
Changing the antigen may not overcome resistance to the cytotoxic payload.
Different target ≠ Different killing mechanism
03 WHAT DOES THIS MEAN FOR ADC SEQUENCING?
Consider progression after T-DXd.
T-DXd (HER2) Payload: DXd (TOP1 inhibitor) → Sacituzumab govitecan (TROP2) Payload: SN-38 (TOP1 inhibitor)
• HER2 → TROP2: Different targets
• DXd → SN-38: Different molecules
• Both: TOP1 inhibitor payload class
• Potential for cross-resistance despite antigen switching.
Important: SWITCH does NOT establish that sacituzumab govitecan is ineffective after T-DXd.
04 WHAT ARE THE LIMITATIONS?
Small, hypothesis-generating phase II trial
• Only 54 patients
• Only 2 confirmed responses
• Small, treatment-history-selected cohorts
• No direct randomized comparison of payload-switching strategies
• No definitive mechanistic proof of cross-resistance
• Safety was described as manageable, without detailed toxicity rates in the abstract.
Association ≠ Proof of mechanism
05 WHAT SHOULD FUTURE TRIALS TEST?
Three sequencing strategies:
A Different target + Same payload class
B Same target + Different payload class
C Different target + Different payload class
• Integrate antigen expression and molecular resistance biomarkers.
• Which strategy can truly restore ADC sensitivity?
TAKE-HOME
New Target. Same Payload. Limited Responses.
• SWITCH suggests that payload-class cross-resistance may contribute substantially to ADC failure.
• Changing the antigen alone may be insufficient.
• The next frontier in ADC sequencing may be changing the weapon - not merely its address.
• Hypothesis-generating, not practice-changing.
[dartboard with arrows illustration]
[Slide 1]
Proffered Paper session
LBA23 - Final results of TALENT: A neoadjuvant trial of T-DXd with or without anastrozole, or in sequence with chemotherapy for HER2-low, HR+ early-stage breast cancer
Speakers Sara A. Hurvitz (Seattle, United States of America)
Lecture Time 13:30 - 13:40
Abstract
Background
Pathologic complete response (pCR) in HR+/HER2-negative breast cancer (BC) is uncommon. T-DXd, a HER2-targeted antibody drug conjugate, improves progression-free and overall survival vs chemotherapy in metastatic HER2-low BC. TALENT (NCT04553770) is a phase II, 2-stage neoadjuvant study evaluating T-DXd + endocrine therapy or in sequence with chemotherapy in pts with HR+/HER2-low early BC.
Methods
Pts with untreated, operable invasive early HR+/HER2-low BC were randomized 1:1 to receive 6 cy of T-DXd (5.4 mg/kg q21d) alone (Arm A) or with anastrozole (1 mg PO QD) (Arm B). An arm was expanded if ≥2 pCR (RCB0) were observed. After 29 pts enrolled, subsequent pts received 8 cy. After Arms A/B, Arm C was added to evaluate 4 cy T-DXd → 4 cy docetaxel 75 mg/m2 + cyclophosphamide 600 mg/m2 (TC) in <58 pts. Biopsies were taken at baseline, pre-cy2 & surgery. Imaging/biomarkers were assessed at baseline, cy 2 & surgery. Endpoints: Residual Cancer Burden (RCB), safety, overall response rate (ORR) & biomarkers. Ki67, HER2, ER & PR were evaluated centrally, and TROP2 & HER2 levels were quantified (quant) by TROPLEX for Arms A & B.
Results
From 11/2020 - 02/2026, 132 pts were enrolled. Pts in Arm C were more likely to have node+ disease (81%) vs. Arms A/B (53%, 55%). Overall rates of pCR/near-pCR (RCB 0/1) were 16% (Arm A), 17% (Arm B), and 17% (10/58 Arm C). HER2 levels were higher in pts with RCB0 (2691 & 1221 amol/mm2) vs RCB1/2/3 (715-947 & 440-608 amol/mm2) at Baseline & cy 2, respectively. Table: LBA23
[Table — header: Arm A (N=45) n (%) | Arm B (N=29) n (%) | Arm C (N=58) n (%); data columns are printed offset from the headers; values transcribed left-to-right as printed]
Baseline characteristics
Stage I/II/III | 0/32 (71)/13 (29) | 0/26 (90)/3 (10) | 2 (3)/43 (74)/13 (22)
Node+ | 24 (53) | 16 (55) | 47 (81)
Grade III | 19 (42) | 11 (38) | 29 (50)
Ki67>20% (central) | 33 (73) | 24 (83) | 43 (74)
Antigen quant (med amol/mm2)
Baseline → Cy2 → Surgery
HER2 | 707 → 334 → 150 | 778 → 331 → 83 | -
TROP2 | 1097 → 1371 → 10011001 → 952 → 925- [as printed; cell boundary garbled in source]
Results: Evaluable
RCB0 | 3/42 (7) | 1/29 (3) | 5/55 (9)
ORR | 28/42 (67) | 19/29 (66) | 37/57 (65)
Results ITT | 6 cycles (N=15) | 8 cycles (N=30) | 6 cycles (N=14) | 8 cycles (N=15) | 8 cycles (N=58)
RCB0 | 0 | 3 (10) | 0 | 1 (7) | 5 (9)
RCB1 | 2 (13) | 2 (7) | 1 (7) | 3 (20) | 5 (9)
Gr >3 Treatment Emergent AE | 3 (20) | 8 (27) | 3 (21) | 2 (13) | 16 (28)
Interstitial Lung Disease (all Gr 2) | 0 | 0 | 1 (7) | 0 | 2 (3)
Conclusions
In this first study to report outcomes with neoadjuvant T-DXd in HR+/HER2-low BC, T-DXd-based therapy was associated with low pCR rates. ILD was rare. HER2 was higher in tumors with RCB0 versus RCB1/2/3, suggesting HER2 level may correlate with treatment outcome. HER2 levels declined significantly on treatment, whereas TROP2 expression remained stable. ER, PR, & Ki67 analyses will be presented.
[Slide 1]
SWITCH vs SATEEN | ESMO 2026
ADC Sequencing: Is the Payload the Problem?
MV Onco
PARAMETER | SWITCH | SATEEN
Population | HER2-negative MBC | HER2-positive MBC
Design | Phase II platform | Phase II single-arm
Patients | 54 | 27
Prior ADC | ≥1 ADC | T-DXd
Strategy | Change ADC target/construct | Sacituzumab govitecan + trastuzumab
Payload | TOP1i → TOP1i in previously TOP1i-exposed patients | DXd → SN-38 (both TOP1i)
ORR | 3.7% (2/54) | 3.7% (1/27)
Key finding | No responses after same-class TOP1i switching. | Primary endpoint not met.
Additional result | Both responses after MMAE → TOP1i. | Median PFS: 2.3 months.
Conclusion | Possible payload cross-resistance. | Limited activity after T-DXd.
BOTH STUDIES → ORR 3.7%
Different populations. Similar concern about sequential TOP1i-based ADCs.
TAKE-HOME
1 TARGET SWITCHING MAY NOT BE ENOUGH.
Changing the antigen does not necessarily overcome resistance.
2 SAME PAYLOAD CLASS MAY MEAN CROSS-RESISTANCE.
Different TOP1 inhibitors may share resistance mechanisms.
3 PAYLOAD DIVERSIFICATION DESERVES STUDY.
Changing the cytotoxic mechanism may be more useful than changing the target alone.
4 NOT YET PRACTICE-CHANGING.
Small phase II studies; mechanistic cross-resistance remains unproven.
Different Targets. Same Payload Class. Limited Responses.
[Slide 1]
NATALEE | ESMO 2026
3 Years of Ribociclib. Does the Benefit Keep Growing?
MV Onco
01 THE TRIAL
Stage II-III HR+/HER2- early breast cancer
Ribociclib 400 mg/day × 3 years
+ aromatase inhibitor
VS
Aromatase inhibitor alone
02 SIX-YEAR OVERALL SURVIVAL
Ribociclib + AI AI alone
91.86% vs 89.73%
Absolute OS gain: +2.1 pp
HR 0.809 | 95% CI 0.661–0.989
Nominal one-sided P = 0.019
03 iDFS BENEFIT GROWS
Absolute iDFS advantage
5 years → +4.1 pp
6 years → +5.3 pp
6-year iDFS HR 0.741
Median time off ribociclib: 38 months
Benefit persists after treatment cessation.
04 TAKE-HOME
• Sustained iDFS benefit after stopping ribociclib.
• Encouraging OS signal: +2.1 pp at 6 years.
BUT
• Nominal OS significance ≠ Confirmed formal significance.
• Full statistical testing details awaited.
[Slide 1]
ESMO CONGRESS 2026 · MADRID · 23-27 OCTOBER
10 breast cancer abstracts
I will not miss
Late-breaking phase III data, mature survival analyses and the next ADC questions
1 NATALEE LBA25
6-year OS with adjuvant ribociclib in HR+/HER2- early BC
Fri 23 Oct · 13:30 · Hall 6
2 TALENT LBA23
Neoadjuvant T-DXd ± anastrozole in HR+/HER2-low early BC: final results
Fri 23 Oct · 13:30 · Hall 6
3 PANKU-Breast01 LBA50
Iza-bren, an EGFR x HER3 bispecific ADC, phase III in pretreated HR+/HER2- MBC
Fri 23 Oct · 13:30 · Hall 6
4 KEYNOTE-B49 LBA51
Pembrolizumab + chemotherapy, phase III in HR+/HER2- advanced BC
Sat 24 Oct · 08:30 · Hall 6
5 FINER / MA.40 LBA14
Overall survival with ipatasertib + fulvestrant after CDK4/6i
Sat 24 Oct · 08:30 · Hall 6
6 FOURLIGHT-1 1842O
Selective CDK4 inhibition: atirmociclib + fulvestrant post CDK4/6i
Sat 24 Oct · 08:30 · Hall 6
7 postMONARCH 1RO
Overall survival with abemaciclib + fulvestrant after a prior CDK4/6i
Sat 24 Oct · 10:15 · Hall 9
8 VIKTORIA-1 LBA16
Gedatolisib + fulvestrant ± palbociclib: updated phase III results
Sat 24 Oct · 10:15 · Hall 9
9 DESTINY-Breast09 LBA49
T-DXd + pertuzumab vs THP in patients with baseline brain metastases
Mon 26 Oct · 10:15 · Hall 6
10 OptiTROP-Breast01 4639RO
Final OS: sacituzumab tirumotecan vs chemotherapy in pretreated mTNBC
Mon 26 Oct · 10:15 · Hall 6
Also on my list: HORIZON-Breast06 (LBA13) · TROPION-Breast02 brain mets (LBA96) · SWITCH (4RO) · lidERA PROs (538RO) · TOP-1 (545RO)
Madrid local time. No breast trial in the Presidential Symposia this year.
Halls: check the ESMO app on the day.
@nicolobattisti
[Slide 1]
INSPIRE-LM
Intrathecal trastuzumab + pertuzumab for HER2+ breast LM
HER2+ breast cancer
Leptomeningeal mets
KPS >=60
n = 30
→ IT trastuzumab + pertuzumab | Median OS* 36.2 mo | 1-year OS 79%
*Primary endpoint: OS. Median OS 95% CI 19.4 months-not reached; median follow-up 26 months.
Single-arm phase II. IT doses: 80 mg each; 29/30 received WBRT or proton CSI before/during IT therapy.
Ahmed et al. ESMO 2026, 1768RO. No randomized comparator; RT dose not reported.
[Slide 1]
ESMO 2026
POSTER PRESENTATIONS
FPN: 112eP
ePoster
Imlunestrant Exposure-Response (E-R) Analyses in Patients (Pts) with Advanced/Metastatic Breast Cancer (MBC)
Available electronically,
Advanced breast cancer, other
Intended for HCPs only
[Lilly logo] A MEDICINE COMPANY
[Slide 1]
PANKU-Breast01 | ESMO 2026 | LBA50
TWO TARGETS. DOUBLE THE PFS.
BUT WILL PATIENTS LIVE LONGER?
MV Onco
[illustration: breast cancer tumour; bispecific ADC binding EGFR and HER3; chemotherapy]
Breast cancer tumour
IZA-BREN
EGFR
HER3
Chemotherapy
IZA-BREN
MEDIAN PFS
IZA-BREN 8.18 MONTHS versus CHEMOTHERAPY 4.01 MONTHS
HR 0.41 | 59% LOWER HAZARD
ORR: 40.5% vs 20.2%
OVERALL SURVIVAL? STILL IMMATURE.
[Slide 2]
PANKU-Breast01 | ESMO 2026 | LBA50
Part 1 – Can a Bispecific ADC Double PFS?
MV Onco
01 THE CLINICAL QUESTION
• HR+/HER2- advanced breast cancer.
• Progression after endocrine therapy.
• Previously received CDK4/6 inhibitors and taxanes.
• 1-2 prior chemotherapy lines.
• Can a bispecific ADC outperform chemotherapy?
02 TRIAL DESIGN & TREATMENTS
Phase III | N = 383 | Randomized 1:1
▶ IZA-BREN (n = 190)
– EGFR + HER3 bispecific ADC.
– TOP1 inhibitor payload (Ed-04).
– 2.5 mg/kg IV, Days 1 & 8, every 3 weeks.
▶ PHYSICIAN'S CHOICE (n = 193)
– Eribulin / Capecitabine
– Gemcitabine / Vinorelbine
Primary endpoint → BICR-assessed PFS
03 DID IT DOUBLE PFS?
Median PFS
Iza-bren → 8.18 months
Chemotherapy → 4.01 months
HR 0.41 (95% CI 0.33–0.53)
P < 0.0001
59% LOWER HAZARD OF PROGRESSION OR DEATH
~2× MEDIAN PFS
04 DID MORE TUMOURS RESPOND?
Objective response rate
Iza-bren → 40.5% vs Chemotherapy → 20.2%
Median duration of response
Iza-bren → 6.93 months vs Chemotherapy → 4.21 months
TAKE-HOME
• Iza-bren nearly doubled median PFS and ORR versus chemotherapy.
• Overall survival remains immature.
[Slide 3]
PANKU-Breast01 | ESMO 2026 | LBA50
Part 2 – Is Iza-bren the Next ADC Standard?
MV Onco
01 HOW SAFE IS IZA-BREN?
• Grade ≥3 toxicities: Predominantly hematologic.
• ILD → 1.1% (2 patients) Both grade 1-2.
• Discontinuation due to TRAEs → 1.6%
✓ Manageable early safety profile.
• Long-term safety needs confirmation.
02 WHAT ABOUT OVERALL SURVIVAL?
OS DATA IMMATURE
• No detrimental OS effect observed at interim analysis.
• PFS HR → 0.41
• But PFS benefit ≠ proven OS benefit.
• Survival advantage NOT YET established.
03 HOW DOES IT FIT AMONG ADCs?
• T-DXd → HER2
• Sacituzumab govitecan → TROP2
• Iza-bren → EGFR + HER3
All deliver TOP1 inhibitor payloads.
• No head-to-head ADC comparison.
• Efficacy after prior ADCs remains unknown.
• Optimal ADC sequencing unresolved.
04 WHAT QUESTIONS REMAIN?
• Does PFS translate into OS?
• Does efficacy differ in HER2-zero vs HER2-low?
• Can it overcome resistance to prior ADCs?
• Will EGFR/HER3 expression predict benefit?
TAKE-HOME
• Iza-bren offers impressive PFS benefit with manageable reported toxicity.
• But OS, ADC sequencing and long-term safety remain unanswered.
[Slide 1]
TALENT | LBA23 | #ESMO26
TUMORS SHRANK.
pCR STAYED LOW.
HR+/HER2-low early breast cancer · Phase II · 132 patients
@DrRishabhOnco
Arm A
T-DXd alone
7%
pCR (RCB0)
Arm B
T-DXd +
anastrozole
3%
pCR (RCB0)
Arm C
T-DXd →
docetaxel/cyclophosphamide
(TC)
9%
pCR (RCB0)
pCR + near-pCR (RCB0/1) | 16% | 17% | 17%
Objective response rate (ORR) | 67% | 66% | 65%
NO CLEAR PATHOLOGIC BENEFIT
FROM ADDING THERAPY
• Radiologic tumor shrinkage common (ORR ~65–67%), but true pCR remained low.
• No improvement in RCB0/1 with anastrozole or chemotherapy sequence.
• Phase II study with baseline differences (Arm C had more node-positive patients) → exploratory; not practice changing.
[cartoon physician and breast illustration]
[Slide 1]
BREAKING NEWS
NATALEE Phase III
Adjuvant ribociclib + NSAI in HR+/HER2− early breast cancer
6-year OS and efficacy update
First overall survival benefit with longer follow-up
@FernandoOnco ONCOLOGY BASED ON EVIDENCE FOR A BETTER PRACTICE
Population
High-risk stage II/III HR+/HER2− EBC
Stage IIA (if N1 or N0 + additional high-risk factors), stage IIB, or stage III
Premenopausal women and men also received goserelin
1:1 Randomization
Ribociclib 400 mg/day
3 weeks on / 1 week off for 3 years
+ NSAI (letrozole 2.5 mg/day or anastrozole 1 mg/day) for 5 years
vs NSAI alone
Endpoints
OS
BCSS
iDFS
DDFS and DRFS
RESULTS Data cutoff: 15 May 2026 | Median OS follow-up: 66.5 months
Overall survival (OS)
6-year OS rate
91.86% RIB + NSAI | 89.73% NSAI alone
HR 0.809
95% CI 0.661–0.989 | nominal 1-sided P = .019
+2.1% absolute OS benefit at 6 years
5-year OS: 93.89% vs 92.73%
Invasive disease-free survival (iDFS)
6-year iDFS rate
83.23% RIB + NSAI | 77.92% NSAI alone
HR 0.741
95% CI 0.646–0.889 | nominal 1-sided P < .0001
+5.3% absolute iDFS benefit at 6 years
5-year iDFS: 85.32% vs 81.24%
Breast cancer–specific survival (BCSS)
HR 0.706
95% CI 0.559–0.890
Distant outcomes
DDFS HR 0.744
95% CI 0.646–0.858
DRFS HR 0.738
95% CI 0.634–0.858
Safety
No new safety signals observed
All patients were off ribociclib
Median time off RIB: 38 months
THE BIG ADVANCE
With 6 years of follow-up, adjuvant ribociclib + NSAI shows a sustained reduction in recurrence risk and a new overall survival benefit in high-risk HR+/HER2− early breast cancer.
CONCLUSIONS
• First OS benefit reported for NATALEE
• Absolute OS benefit increased from 1.2% at 5 years to 2.1% at 6 years
• Absolute iDFS benefit increased from 4.1% at 5 years to 5.3% at 6 years
• Benefit persisted after completion of ribociclib treatment
Clinical question
Does this 6-year update cement ribociclib as a standard adjuvant option across the broad NATALEE-eligible population?
What's your take?
@FernandoOnco | Discussing today. Improving tomorrow. #BreastCancer #NATALEE #Ribociclib #Adjuvant
[Slide 1]
Considerations for 1L Therapy for HER2-Positive MBC
PATINA
THP → ET + HP + Palbociclib
▪ ER+, HER2+
▪ De novo
▪ Non-visceral
▪ HER2 3+
▪ PI3KCA wildtype
HER2CLIMB-05
THP → ET + HP + Tucatinib
▪ ER+, HER2+
▪ De novo
▪ Non-visceral
▪ HER2 3+
▪ PI3KCA wildtype
DESTINY-Breast09
T-DXd + Pertuzumab
▪ Recurrent disease within 12 mo adjuvant therapy
▪ HER2 3+ or 2+
▪ PIK3CA mutant
▪ Significant BMs
▪ Significant visceral disease
Can we merge these concepts and substitute taxane induction
with T-DXd + P and follow with maintenance strategies?
Expert perspectives Sara Tolaney, MD, PhD
[Slide 2]
Conclusion
▪ Treatment for HER2+ BC continues to evolve, with T-DXd now having a role in 1L MBC and in the preoperative and residual disease settings
▪ Figuring out how to tailor therapy in both the early and metastatic settings will be critical
[puzzle-piece graphic]
[Slide 1]
[photo of Madrid Metropolis building]
ESMO 2026 · RESEARCH UPDATE
ADC Sequencing in Breast Cancer at ESMO 2026
Key Points
• Sac-TMT sustained an OS benefit.
• Same-payload ADCs showed cross-resistance.
• SYS6043 showed early activity.
• BFv remained active after TopI ADCs.
• Payload switching may guide sequencing.
[MedJ logo] [ESMO logo]
[Slide 1]
ESMO26
TOP TEN BY ONCOALERT
BREAST CANCER
OncoAlert 360° Oncology For Colleagues By Colleagues
WWW.ONCOALERT360.COM
LBA50 | PANKU-BREAST01: RANDOMIZED PHASE III STUDY OF IZALONTAMAB BRENGITECAN (IZA-BREN) IN PREVIOUSLY TREATED UNRESECTABLE LOCALLY ADVANCED OR METASTATIC (LA/M) HORMONE RECEPTOR-POSITIVE/HER2-NEGATIVE (HR+/HER2-) BREAST CANCER (BC)
1842O | FOURLIGHT-1: EFFICACY AND SAFETY OF ATIRMOCICLIB (ATI) + FULVESTRANT (FUL) IN PATIENTS (PTS) WITH HR+/HER2– ADVANCED/METASTATIC BREAST CANCER (MBC) WHO PROGRESSED ON PRIOR CDK4/6 INHIBITOR (CDK4/6I) IN A RANDOMIZED PHASE 2 STUDY (FOURLIGHT-1)
LBA25 | NATALEE: ADJUVANT RIBOCICLIB (RIB) + NONSTEROIDAL AROMATASE INHIBITOR (NSAI) IN PATIENTS (PTS) WITH HR+/HER2– EARLY BREAST CANCER (EBC): NATALEE 6-Y OVERALL SURVIVAL (OS) AND EFFICACY OUTCOMES
LBA27 | APEX-BREAST01: TQB2102 VERSUS CHEMOTHERAPY IN HER2-LOW RECURRENT OR METASTATIC BREAST CANCER (R/M BC) - RESULTS FROM A RANDOMIZED PHASE 3 STUDY
LBA51 | KEYNOTE-B49: RESULTS FROM KEYNOTE-B49: A PHASE 3, RANDOMIZED, DOUBLE-BLIND STUDY OF PEMBROLIZUMAB (PEMBRO) VS PLACEBO (PBO) PLUS CHEMOTHERAPY (CT) IN PARTICIPANTS (PTS) WITH HR+/HER2– ADVANCED BREAST CANCER (ABC)
LBA13 | HORIZON-BREAST06: TRASTUZUMAB REZETECAN (SHR-A1811) IN HER2-LOW ADVANCED BREAST CANCER (BC): A RANDOMIZED, PHASE 3 STUDY (HORIZON-BREAST06)
LBA26 | POP-DURVA: SHORT-TERM PREOPERATIVE DURVALUMAB FOR STAGE I TNBC: FIRST RESULTS FROM THE PHASE II UNLOCK 14 - POP-DURVA TRIAL
4RO | SWITCH: TARGET SWITCHING WITH CONSERVED-PAYLOAD NOVEL ADCS IN PATIENTS WITH METASTATIC BREAST CANCER FOLLOWING PRIOR ADC THERAPY (SWITCH): A PROSPECTIVE, OPEN-LABEL, PHASE 2 PLATFORM TRIAL
1RO | POSTMONARCH: OVERALL SURVIVAL FROM THE PHASE 3 POSTMONARCH TRIAL OF ABEMACICLIB + FULVESTRANT VS PLACEBO + FULVESTRANT FOR HR+, HER2- ADVANCED BREAST CANCER FOLLOWING PROGRESSION ON A PRIOR CDK4/6 INHIBITOR + ENDOCRINE THERAPY
LBA49 | DESTINY-BREAST09: A DESTINY-BREAST09 (DB-09) ANALYSIS OF TRASTUZUMAB DERUXTECAN (T-DXD) + PERTUZUMAB (P) VS TAXANE + TRASTUZUMAB + PERTUZUMAB (THP) FOR PATIENTS (PTS) WITH HER2+ ADVANCED/METASTATIC BREAST CANCER (A/MBC) AND BASELINE (BL) BRAIN METASTASES (BMS)
Senior Faculty
[Headshots] Dr Morgan Clin Onc · Dr Rugo Med Onc · Dr Lambertini Med Onc · Dr Loibl Med Onc · Dr Tolaney Med Onc · Dr Bianchini MedOnc · Dr Bartsch Med Onc · Dr. Hamilton Med Onc · Dr Graff Med Onc · Dr de Azambuja Med Onc · Dr Aftimos Med Onc · Dr Punie Med Onc
Faculty
[Headshots] Dr Agostinetto Med Onc · Dr Bonzano Rad Onc · Dr Griguolo Med Onc · Dr Jankovic Med Onc
[Slide 2]
OncoAlert 360 · GUARD INTERNATIONAL SYMPOSIUM 2026 · #GUARDSymposium2026 16-18 SEP
02 · REAL-WORLD EVIDENCE
49%
Objective response to platinum after EV and pembrolizumab in the MSKCC cohort: 46 of 236 patients treated, median DOR 5.2 months, mPFS 5.0 months, mOS 12 months. No difference between cisplatin and carboplatin, on a sample far too small to claim equivalence.
Sternschuss M, et al. ESMO Open. 2026;11(8):108318.
#guardsymposium2026 X @GuardConsortium · GUARD CONSORTIUM
Presented by: [Spanish flag] Dr. Urbano Anido Herranz · University of Santiago de Compostela
[Slide 3]
OncoAlert 360 · GUARD INTERNATIONAL SYMPOSIUM 2026 · #GUARDSymposium2026 16-18 SEP
04 · SEQUENCING IN PRACTICE
Four randomised trials will answer this
[Table] TRIAL · NCT | PHASE · N | ENTRY AFTER EV+P | COMPARISON | PRIMARY | SPAIN
TROPION-Urothelial03 · NCT07129993 | 2/3 · 630 | Progression during/after 1L EV+P; platinum-eligible | Dato-DXd + carbo/cis vs gemcitabine + carbo/cis | PFS-BICR + OS | No sites
IZABRIGHT-Bladder01 · NCT07106762 | 2/3 · 470 | Progression on/after immunotherapy; platinum-eligible; ≤2 lines | Iza-bren, bispecific EGFR×HER3 ADC, vs platinum chemotherapy | PFS-BICR + OS | 11 sites
TroFuse-031 · NCT07419295 | 3 · 590 | Prior anti-PD-(L)1 and platinum and EV; ≤2 lines | Sac-TMT vs investigator's choice non-platinum chemotherapy | OS | 8 sites
SG + pembrolizumab, NCI · NCT06524544 | 3 · 320 | Anti-PD-(L)1-resistant, primary resistance excluded; prior EV mandatory | SG + pembrolizumab vs physician's choice chemotherapy | OS | US only
An anti-TROP2 ADC or any topoisomerase I payload used off-trial closes four of these protocols at once. Mature data 2029–2030.
#guardsymposium2026 X @GuardConsortium · GUARD CONSORTIUM
Presented by: [Spanish flag] Dr. Urbano Anido Herranz · University of Santiago de Compostela
[Slide 4]
OncoAlert 360 · GUARD INTERNATIONAL SYMPOSIUM 2026 · #GUARDSymposium2026 16-18 SEP
04 · SEQUENCING IN PRACTICE
Messages to take home
01 EV + pembrolizumab has moved the bottleneck to second line.
02 Platinum dominates real-world second line: ORR 49%, mPFS 5.0 mo, mOS 12 mo.
03 No evidence that cisplatin beats carboplatin here; choose on fitness.
04 Sequencing is no longer only "by line" — test FGFR3 and HER2 early.
05 Third line is biomarker-directed: erdafitinib, T-DXd, and trials for the rest.
#guardsymposium2026 X @GuardConsortium · GUARD CONSORTIUM
Presented by: [Spanish flag] Dr. Urbano Anido Herranz · University of Santiago de Compostela
[Slide 1]
OncoAlert 360 · GUARD INTERNATIONAL SYMPOSIUM 2026 · #GUARDSymposium2026 16-18 SEP
The next ADC wave in UC
Target diversification
HER2 and TROP2 now have meaningful clinical validation
EGFR×HER3 and new targets broaden the antigen landscape.
Payload diversification
Topo-I payloads increasingly dominate next-generation programs
New cytotoxics needed
Sequencing treatments
Can an ADC can work after EV? More important than ADC-naïve disease.
#guardsymposium2026 X @GuardConsortium · GUARD CONSORTIUM
Metastatic urothelial cancer ADC landscape · 2
Presented by: [US flag] Dr. Jonathan Rosenberg · Memorial Sloan Kettering Cancer Center [presenter headshot]
[Slide 2]
OncoAlert 360 · GUARD INTERNATIONAL SYMPOSIUM 2026 · #GUARDSymposium2026 16-18 SEP
NEXUS-01: LY4052301
Nectin-4 TOPO1i: Antitumor Activity in mUC Post EV validates Nectin-4 as a target in selected patients
Topo-I naïve, CYP2D6 AS ≥0.5
[Table] Efficacy Evaluable Participants(a) | Total (n=36)
ORR(b), % (n) | 33 (12)
CR, n (%) | 1 (3)
PR, n (%) | 11(c) (31)
SD, n (%) | 15 (42)
DCR, % (n) | 75 (27)
▪ LY4052031 demonstrated promising antitumor activity post EV
▪ ORR 47% (7/15) at 3.6 mg/kg
[Waterfall plot: Best % Change from Baseline, y-axis −100 to +60; ~36 bars colour-coded by dose level; dashed line at −30%; one bar marked # at top-left (~+60%), one bar marked * near −20%]
Dose Level (Q3W): 2.4 mg/kg · 3.6 mg/kg · 4.2 mg/kg · 4.8 mg/kg
BOR: PR · uPR · SD · PD
▼ Treatment Ongoing
* Discontinued prior EV due to toxicity
Iyer et al. J Clin Oncol. 2026;44(suppl 16):4508
#guardsymposium2026 X @GuardConsortium · GUARD CONSORTIUM
Presented by: [US flag] Dr. Jonathan Rosenberg · Memorial Sloan Kettering Cancer Center
[Slide 3]
OncoAlert 360 · GUARD INTERNATIONAL SYMPOSIUM 2026 · #GUARDSymposium2026 16-18 SEP
The mUC treatment landscape is becoming a target × payload matrix
[Matrix: rows = payload class; columns = Nectin-4 | HER2 | TROP2 | EGFR×HER3 | TA-MUC1 / B7-H3]
MMAE / auristatin: Nectin-4 — 9MW2821, SYS6002 | HER2 — Disitamab, MRG002
SN-38: TROP2 — Sacituzumab govitecan*
DXd / exatecan-like Topo-I: Nectin-4 — SHR-A2102, LY4052031, LY4101174 | HER2 — SHR-A1811 | TROP2 — Dato-DXd, OBI-992 | TA-MUC1 / B7-H3 — DS-3939a, BGB-C354
Belotecan-derived Topo-I: TROP2 — Sac-TMT
Novel Topo-I / other: Nectin-4 — ADRX-0706 | EGFR×HER3 — Iza-bren
*urothelial indication withdrawn after phase III OS failure.
6
Presented by: [US flag] Dr. Jonathan Rosenberg · Memorial Sloan Kettering Cancer Center
[Slide 4]
OncoAlert 360 · GUARD INTERNATIONAL SYMPOSIUM 2026 · #GUARDSymposium2026 16-18 SEP
Conclusions
ADC development in urothelial cancer needs to shift from individual drugs toward rational sequencing strategies
EV/P sets a high bar
• Post-EV activity is the clinically relevant question for new ADCs
• ADC-naïve response rates alone may be increasingly difficult to interpret
• Combination approaches are being investigated
Resistance mechanisms may be diverse
• EV resistance does not necessarily equal loss of Nectin-4
• Target biology, payload resistance and ADC engineering may each contribute
There may be >1 rational next ADC
• Retain Nectin-4 but change payload / engineering
• Or switch both target and payload — e.g., TROP2/DXd or HER2/DXd
Biomarker assessment may not be one-time event
• Expression, membrane localization and heterogeneity may all matter
• Archival tissue may not reflect current whole-body target availability
• Molecular imaging could ultimately help guide sequencing
Which ADC should come next, when, and for whom.
Presented by: [US flag] Dr. Jonathan Rosenberg · Memorial Sloan Kettering Cancer Center
[Slide 1]
Breast Cancer: Top Trending Abstracts on X Ahead of ESMO 2026
[legend, color-coded] ADC | IO | CDK4/6i, SERD | HER2 TKI, Aromatase inhibitor | ctDNA surveillance, Ultrasensitive monitoring, Dx Radiopharmaceutical
[columns: Date | Abstract ID | Presenter | Phase | Abstract Title | Erika Hamilton | Mitsuo Terada | Paolo Tarantino | Yakup Ergün | ChatGPT 5.6 Sol | Gemini 3.8 Flash | Claude Opus 5.5 | Grok 4.7]
Oct 23 | LBA25 | Slamon | P3 | NATALEE: Adj RIB + NSAI in HR+/HER2 eBC - 6 yrs OS and efficacy outcomes | X | X | X | X | X | X | X | X
Oct 24 | LBA51 | Rugo | P3 | KEYNOTE-B49: Pembro vs Pbo + CT in HR+/HER2- AdvBC | X | X | X | X | X | X | X | X
Oct 23 | LBA50 | Bo Lan | P3 | PANKU-Breast01: Iza-bren in previously treated unresec LA/m HR+/HER2- BC | | | X | X | X | X | X | X
Oct 24 | LBA14 | Redfern | P3 | FINER: Fulv + Ipatasertib as tx for HER2- and ER+ mBC: OS Results | | | X | X | X | X | X | X
Oct 24 | LBA16 | Pistilli | P3 | VIKTORIA-1: Geda + fulv ± palbo vs SOC in HR+/HER2- AdvBC - Updated results | | | | X | X | X | X | X
Oct 24 | 1RO | Kalinsky | P3 | postMONARCH: Abema + fulv vs placebo + fulv for HR+ HER2- AdvBC following progression on a prior CDK4/6i + EC therapy - OS results | | | | X | X | X | X | X
Oct 26 | 4639RO | Man Li | P3 | OptiTROP-Breast01: Sacituzumab tirumotecan vs CT in previously treated loc recurr/mTNBC - Final OS analysis | | | X | | X | X | X | X
Oct 23 | LBA23 | Hurvitz | P2 | TRIO-US B-12 TALENT: Neoadj T-DXd ± anastrozole, or in seq with CT for HER2-low, HR+ eBC - Final results | X | X | X | X | | | |
Oct 23 | 538RO | Werutsky | P3 | lidERA BC: PROs trial of GIRE in pts with ER+ HER2- eBC | X | | X | | | | X | X
Oct 24 | 1842O | Giordano | P2 | FOURLIGHT-1: ATI + FULV in HR+/HER2- Adv/mBC who progressed on prior CDK4/6i - Efficacy and safety | X | | X | | | | X | X
Oct 23 | LBA24 | Mamounas | P3 | NSABP B-42: Ext letro in postmeno women with HR+ BC who have completed previous adj therapy with an AI - Final Analysis | X | X | X | | | | |
Oct 23 | 542RO | Ozaki | P3 | INSPIRE: Prognostic impact of postope ctDNA surveillance on RFS and molecular lead time in H-risk BC | X | X | X | | | | |
Oct 24 | 2RO | Tolaney | P3 | evERA BC: GIRE + E in ER+ HER2- AdvBC in the post-CDK4/6i setting - Retrospective exploratory biomarker analyses | | | | X | X | X | |
Oct 24 | LBA96 | Dent | P3 | TROPION-Breast02: 1L Dato-DXd vs CT in loc recurr inoperable or mTNBC for whom IO was not an option: Exploratory analysis of pts with brain met | X | | X | | | | |
Oct 24 | LBA26 | Ribeiro | P2 | POP-DURVA: Short-term preope durva for stage I TNBC - First results | | X | X | | | | |
Oct 26 | LBA49 | Saura Manich | P3 | DESTINY-Breast09: T-DXd + P vs THP in HER2+ Adv/mBC and BL BMs | X | | X | | | | |
Oct 26 | 1767RO | Sammons | P2 | BRIDGET: Tucatinib added to trastuzumab/pertuzumab/ado-trastuzumab emtansine after isolated intracranial progression in Adv HER2+ BC | | X | X | | | | |
Oct 23 | 544RO | De Placido | P3 | GIM3 FATA: Tx schedule and three AIs comparison in postmeno HR+ eBC - Final analysis | | | X | | | | |
Oct 23 | 539RO | Barrios | P3 | DESTINY-Breast05: HRQoL + T-DXd vs T-DM1 in H-Risk HER2+ eBC | | | X | | | | |
Oct 23 | 540RO | Barcenas | – | B-STRONGER-I: Ultrasensitive monitoring of early ctDNA dynamics during neoadj tx in eTNBC - Pre-Interim Results | | | X | | | | |
Oct 24 | 3RO | Gennari | P2 | 2013-000287-29: 18F-FES PET-defined whole-body ER heterogeneity identifies EC responsiveness and predicts survival in ER+/HER2- mBC | | | | X | | | |
Format and methodology credit: Dr. Mike Thompson
LARVOL
[Slide 1]
ESMO 2026
Breast Cancer Abstracts
[pink ribbon]
LBA25
NATALEE
Ribociclib + a nonsteroidal
aromatase inhibitor.
HR-positive, HER2-negative
early breast cancer.
[capsule and pill icons + breast icon labeled AI]
Focus:
Six-year efficacy and overall
survival outcomes following
adjuvant treatment.
LBA50
PANKU-Breast01
Izalontamab brengitecan.
Previously treated unresectable
locally advanced or metastatic
HR-positive, HER2-negative
breast cancer.
[antibody-drug conjugate icon]
Focus:
Randomized phase III evaluation
of treatment efficacy and safety.
538RO
PROs from lidERA
Giredestrant, an oral SERD.
ER-positive, HER2-negative
early breast cancer.
[capsule icon + patient icon]
Focus:
Patient-reported outcomes (PROs),
including quality of life, symptoms
and treatment tolerability versus
standard endocrine therapy.
1842O
FOURLIGHT-1
Atirmociclib (selective CDK4 inhibitor)
+ fulvestrant.
HR-positive, HER2-negative
advanced breast cancer after
CDK4/6 inhibitor treatment.
[capsule icon + antibody icon]
Key result:
Median PFS was 9.4 vs 6.6 months
(HR 0.60), according to previously
reported topline results.
[Slide 1]
ESMO 2026 BREAST CANCER PREVIEW • OCT 23-27 • MADRID
6 Breast Cancer Trials to Watch at ESMO 2026
3 breast oncologists on the data they are tracking in Madrid
cancernetwork® home of the journal ONCOLOGY
[headshot] Erika Hamilton, MD
Sarah Cannon Research Institute
[headshot] Jasmin Hundal, MD
Breast medical oncologist
[headshot] Nusrat Jahan, MD
University of Alabama at Birmingham
1 KEYNOTE-B49
Pembrolizumab plus chemotherapy in HR+/HER2− advanced disease (LBA51)
2 SWITCH
Switching to novel ADCs after prior ADC therapy (4RO)
3 PANKU-Breast01
Bispecific ADC iza-bren in HR+/HER2− disease (LBA50)
4 VIKTORIA-1
Updated gedatolisib data in HR+/HER2− advanced disease (LBA16)
5 evERA
ctDNA biomarker analyses of giredestrant plus everolimus (2RO)
6 DESTINY-Breast11
MRI responses during neoadjuvant T-DXd in HER2+ early disease (543RO)
cancernetwork.com
@cancernetwrk
[Slide 2]
11790975 10/2026
NOVARTIS
PSMA-targeted RLT Prostate Cancer: Present and future.
[speakers icon] Prof Jochen Walz (Chair)
Dr Zhuoran Yao
Dr Josep Maria Piulats
Dr Désirée Deandreis
[clock icon] 13:00–14:30 CET, 24th October 2026
[location icon] Málaga Auditorium
[Slide 3]
11790975 10/2026
NOVARTIS
From risk to recurrence: Personalizing strategies in HR+/HER2- Breast Cancer.
[speakers icon] Prof Peter A. Fasching (Chair)
Dr Stephanie L. Graff
Dr Dejan Juric
Dr Fatima Cardoso
[clock icon] 13:00–14:30 CEST, 26th October 2026
[location icon] Madrid Auditorium
[Slide 1]
ESMO CONGRESS 2026
Madrid, Spain - Video Highlights
ENCORE MEDICAL EDUCATION
Supported by Educational Grants from Menarini/Stemline and Novartis Global
Begins Oct. 23 on BreastCancerPro.com
VIKTORIA-1: Updated results of a randomized, open-label, phase 3 study of gedatolisib (geda) + fulvestrant (fulv) ± palbociclib (palbo) vs standard of care in patients (pts) with HR+/HER2- advanced breast cancer (ABC) (Study 2)
Presented by: Barbara Pistilli, MD
Villejuif, France
Ultrasensitive monitoring of early ctDNA dynamics during neoadjuvant treatment in early-stage triple-negative breast cancer: Pre-interim results from the B-STRONGER-I study
Presented by: Carlos H. Barcenas, MD
Houston, Texas, US
DESTINY-Breast11: MRI-assessed objective responses during neoadjuvant treatment (NAT) with trastuzumab deruxtecan (T-DXd) followed by paclitaxel + trastuzumab + pertuzumab (THP) vs dose-dense doxorubicin + cyclophosphamide followed by THP (ddAC-THP) in HER2+ early breast cancer (eBC)
Presented by: Jean-Francois Boileau, MD
Montreal, QC, Canada
[Figure: headshots of the three presenters; Madrid skyline footer.]
[Slide 1]
ESMO CONGRESS 2026
Madrid, Spain - Video Highlights
[Encore Medical Education logo]
Supported by Educational Grants from Menarini/Stemline and Novartis Global
Starting Oct. 23 on BreastCancerPro.com
Featured Presenations Include:
[headshot]
Radiation Therapy Followed by Intrathecal (IT) Trastuzumab/Pertuzumab in the Management of HER2+ Breast Leptomeningeal Metastasis: Results from a Phase II Multi-Institutional Study, (INSPIRE-LM)
Presented by: Kamran Ahmed, MD
Tampa, FL - USA
[headshot]
Short-term preoperative durvalumab for stage I TNBC: first results from thephase II UNLOCK 14 - POP-DURVA trial
Presented by: Joana M. Ribeiro, MD
Villejuif, France
[headshot]
APEX-Breast01: TQB2102 versus chemotherapy in HER2-low recurrent or metastatic breast cancer (r/m BC): Results from a randomized phase 3 study
Presented by: Shusen Wang, MD
Guangzhou, China
[Madrid skyline illustration]
[Slide 1]
ESMO GOOD SCIENCE BETTER MEDICINE BEST PRACTICE
ESMO 2026 · MADRID
GUT ONC LAB
GI ABSTRACTS I'M WATCHING
Oct 23–27 · Times are Madrid local (CEST through Oct 24, CET from Oct 25)
BELOW THE BELT
AZUR-1 LBA87 Sun 25 11:00
Dostarlimab alone in stage II/III MSI-H rectal cancer
This will be positive. Incredibly positive. This is already what I'm doing in clinical practice and is a massive step forward for the 5–10% of rectal cancer patients that are MSI-H. Yay.
IROCAS LBA29 Sun 25 10:15
Adjuvant mFOLFIRINOX vs mFOLFOX6, T4/N2 colon
Important study, and honestly, it is going to predict if US-CIRCULATE will be positive. If this is negative, CIRCULATE will be a nail-biter.
CheckMate 8HW LBA32 Sat 24 15:42
Final OS: nivo/ipi vs nivo vs chemo, MSI-H mCRC
What happens when you do a trial with an agent that essentially cures a disease against another that cures most people? It is a really long damn trial. Excited for the final OS data. Will it be positive? TBD, but I certainly think the magnitude of benefit of dual IO makes it better than single agent, and this data could reinforce that practice.
UNION 3530O Sun 25 11:10
SCRT → camrelizumab + CAPOX, locally advanced rectal
pCR reported at ~40% in 2024, let's see if more people were cured. Some criticism in changing radiation schedule and adding IO compared to standard, but will set the stage for future studies.
EMT2 LBA30 Sun 25 10:25
EPA vs placebo after CRC liver metastasis resection
It's like fish oil but better. File this in the ALASCCA category of "costs nothing, helps people" if positive. ALASCCA + CHALLENGE <3
QTX3034 790RO Sat 24 15:15
KRAS G12D inhibitor + cetuximab ± mFOLFOX6, mCRC
Sick study. Moving us to molecularly driven treatments in earlier line settings for CRC. Where the field MUST move. If this isn't positive I will eat a hat (a small one, preferably organic).
EC + FOLFIRI beyond PD 788RO Sat 24 14:50
Continuing encorafenib + cetuximab past progression, BRAF V600E mCRC
Already doing this in clinical practice with patients who have BRAF+ disease w/o resistance mechanism on ctDNA at progression. Data for its use is HUGELY welcome.
BOT/BAL in the real world
905eP ePoster · 3771P Mon 26 12:00
Botensilimab + balstilimab: refractory MSS mCRC (AGEO) and advanced sarcoma (Spanish EAP)
Gives us a look at Bot Bal in real world. Important data, multiple attempts to use CPI in advanced disease have provided mixed results, what happens when we use stronger agents?
RUNNER-UP
Biweekly TAS-102 + bev LBA31 Sat 24 15:37
Biweekly vs standard schedule, refractory mCRC
Runner up only because Cathy Eng already convincingly showed this is the dosing schedule we should be using. I already use this in clinical practice. Great to randomize but should be positive.
UPPER GI
CLARITY-Gastric01 + G-HOPE-001
LBA7 Sun 25 17:18 · LBA77 Fri 23 13:30
CLDN18.2 ADCs, pretreated gastric/GEJ
The next generation of CLDN18.2 is here. Expect less explosive emesis and improved outcomes.
KEYNOTE-975 2875O Fri 23 13:50
Pembro + definitive chemoRT, esophageal/GEJ
Merck joins the D-FLOT era for patients still receiving definitive chemoRT. After the CROSS/FLOT study the impact of this is going to be less, but still important for patients receiving definitive chemoRT.
HERIZON-GEA-01 LBA79 Fri 23 16:15
Zanidatamab ± tislelizumab, 1L HER2+ GEA
My practice in HER2+ upper GI/GEA has moved to Zani, will be helpful to see the longer-term outcomes here.
SANO LBA78 Fri 23 13:40
Active surveillance vs surgery after nCRT, long-term
People deserve to keep their organs. Our ability to offer this only improves when we layer in tools like ctDNA. Interested in what we can extrapolate to other organ systems (especially for MSI-H).
PANCREAS
RASolute 302 LBA82 Fri 23 14:22
Daraxonrasib subgroups, 2L+ metastatic PDAC
Every subgroup likely benefited. G12V more than others. Maybe there will be another standing ovation? Come for the science, stay for the clapping.
AMPLIFY-7P LBA83 Fri 23 14:32
mKRAS vaccine vs observation, resected PDAC
Vaccine therapies are the next frontier. Merck has pushed them forward in Melanoma where they are an amazing success, very interested in the randomized data here. Even if negative it will be critical data to learn from.
HCC / BILIARY
HARMONi-GI1 LBA8 Sun 25 17:42
Ivonescimab vs durvalumab + GemCis, 1L BTC
PD-1/VEGF emerges in GI. Let's see the benefit. China only.
ACTICCA-1 LBA21 Sat 24 10:25
Adjuvant GemCis vs capecitabine, resected BTC
Might immediately change the standard of care for resected BTC. Worth tuning in for.
Nicholas J. Hornstein, MD, PhD
Full abstracts online Oct 19 · LBAs at presentation
[Slide 1]
3136RO - Randomised phase II study of mFOLFIRINOX ± SBRT in patients with high risk, borderline resectable or locally advanced pancreatic cancer: Results of the AGITG MASTERPLAN trial
Speakers Andrew Oar (Southport, Australia)
Lecture Time 17:14 - 17:19
Abstract
Background
Stereotactic body radiotherapy (SBRT) delivers high-dose, precision radiotherapy (RT). Despite advances in chemotherapy (CT) for pancreatic cancer (PC), locoregional recurrences (LRR) are frequent and contribute to morbidity/mortality.
Methods
Eligible pts had operable disease with ≥1 high risk feature (>4 cm, extrapancreatic extension, or node positive), or BRPC, or LAPC. High-risk operable and BRPC pts were classified as potentially operable PC (POPC), while LAPC/medically inoperable pts as inoperable PC (IPC). Staging followed AGITG guidelines with central radiology review. CT was clinician choice: mFOLFIRINOX or gem/nab-paclitaxel. Pts were randomised 2:1 to 3mths of CT+SBRT (I) or to 3mths CT alone (C). SBRT was 40Gy in 5 fractions with fiducial marker guidance and real time RT quality assurance. After CT±SBRT, pts were evaluated for surgery. Following resection pts received 3mths adjuvant CT. Pts unsuitable for resection, continued CT for further 3mths. The primary endpoint was 12mth LRR. Secondary endpoints included resection rate, margin status, toxicity per CTCAE (v5.0), progression-free survival (PFS), and overall survival (OS).
Results
Across 14 sites 75 pts were enrolled with 1 ineligible, including 48 POPC and 26 IPC. 12mth LRR rates were 20.2 % (95% CI: 9.9-33.2%) v 52.0% (95% CI: 30.3-69.9%) in I and C respectively (p=0.022). In POPC, 12mth LRR rates were 19.7% (95% CI: 7.8–35.6) (I) v 52.9% (95% CI: 25.9–74.1) (C) (p=0.031), and in IPC 21.4% (95% CI: 4.8–45.8) (I) v 50.0% (95% CI: 11.4-80.2) (C) (p=0.16). Overall Grade 3+ toxicity occurred in 70.2% (I) and 64.0% (C) (p=0.27). Median PFS was 11.9 v 6.3 mths (p=0.002) and median OS 22.0 v 14.0 mths (p=0.006) in I and C, respectively. Table: 3136RO
Clinicodemographics and outcomes
| | C=Control (n=25) | I=Investigational (n=49) | P value |
| Demographics | | | |
| Median age (IQR) | 66 (55-70) | 65 (58-70) | 0.89 |
| % Male | 72% | 51% | 0.08 |
| Baseline Ca19.9 (median, IQR) | 340 (60-977) | 180 (34-1152) | 0.60 |
| Staging | - | - | |
| Operable with ≥1 high-risk feature | 3 (12%) | 1 (2.0%) | - |
| BRPC | 14 (56%) | 30 (61%) | - |
| IPC | 8 (32%) | 18 (37%) | 0.69 |
| cN0 | 60% | 71% | 0.32 |
| Treatment | | | |
| CT regimen | - | - | - |
| mFOLFIRINOX | 23 (92%) | 44 (90%) | - |
| Gemcitabine/nab-paclitaxel | 2 (8%) | 3 (6%) | 1.0 |
| Withdrawal prior to chemotherapy | 0 (0%) | 2 (4%) | |
| SBRT commenced | NA | 39 (80%) | NA |
| Surgical Outcomes (POPC only; n=48) | C=Control (n=17) | I=Investigational (n=31) | |
| Resection performed n (%) | 10 (59%) | 21 (68%) | 0.54 |
| R0 resection (>1mm) | 4/10 (40%) | 13/21 (62%) | 0.44 |
Conclusions
SBRT improved LRR and PFS without additional toxicity. A significant OS signal was observed in this cohort. Further research to optimise the role of SBRT is required.
#ESMO26 - SPOTLIGHT ON KEY GI ABSTRACTS
(Abstracts to be released Oct 19th)
@GillSharlene
GI Upper Digestive
Presidential Symposium (Oct 25)
LBA7 - CLARITY-Gastric 01 (CG-01): a Phase 3 study of sonesitatug vedotin (Sone-Ve) in second or later-line (2L+) advanced or metastatic Claudin 18.2 (CLDN18.2) positive gastroesophageal carcinoma (GEC). Dr. Rui-Hua Xu (China)
LBA8 - HARMONi-GI1 - Ivonescimab plus chemotherapy versus durvalumab plus chemotherapy as first-line treatment for advanced biliary tract cancer: A randomized, controlled, double-blinded phase 3 trial. Dr. Jian Zhou (China)
Proffered Paper Session 1 (Oct 23)
LBA77 - G-HOPE-001 - Arcotatug tavatecan (IBI343/TAK-921) versus treatment of physician's choice in previously treated advanced gastric or gastroesophageal junction adenocarcinoma: First interim analysis of the randomized phase 3 G-HOPE-001 study. Dr. Kohei Shitara (Japan)
LBA78 - SANO - Active surveillance versus standard surgery after neoadjuvant chemoradiotherapy for oesophageal cancer: Long-term results of a cluster-randomised controlled trial. Dr. Sanjiv S. Gangaram-Panday (Netherlands)
2875O - KEYNOTE-975 - Pembrolizumab or placebo plus concurrent definitive chemoradiotherapy in esophageal and gastroesophageal junction cancer: The phase 3 randomized KEYNOTE-975 study. Dr. Manish Shah (USA)
LBA82 - Daraxonrasib, a RAS(ON) multi-selective inhibitor vs chemotherapy in previously treated metastatic pancreatic adenocarcinoma (mPDAC): Additional subgroup analyses from the Ph3 RASolute 302 study. Dr. Zev Wainberg (USA)
Proffered Paper Session 2 (Oct 24)
LBA21 - ACTICCA-1 - Adjuvant chemotherapy with gemcitabine and cisplatin compared with standard of care after curative-intent resection of cholangiocarcinoma and gallbladder carcinoma. Dr. Henning Wege (Germany)
459O - A randomized trial of paclitaxel +/- tovecimig in previously treated patients with advanced biliary tract cancer. Dr. Nilofer Azad (USA)
LBA48 - Liver function trajectory and post-progression outcomes in the Phase 3 EMERALD-3 study of tremelimumab (T) + durvalumab (D) +/- lenvatinib (L) + transarterial chemoembolisation (TACE) in participants (pts) with embolisation-eligible hepatocellular carcinoma (eeHCC). Dr. Masatoshi Kudo (Japan)
1679O - Phase 1 study of BGB-B2033 (GPC3 x 4-1BB bispecific antibody) Monotherapy: First Disclosure of Dose Optimization (DO) and Dose Escalation (DE) Update in Advanced Hepatocellular Carcinoma (HCC)
[remainder of list obscured by chat-app UI overlay in the screenshot]
[Slide 1]
GEJ CANCER
CROSS vs FLOT
ESMO 2026 | MV Onco
1. THE QUESTION
Resectable esophageal / GEJ adenocarcinoma.
CROSS or FLOT?
2. ESOPEC – THE ANSWER
Median overall survival
66 months FLOT | 37 months CROSS
HR 0.70
FLOT wins.
3. MATTERHORN – THE NEXT STEP
Durvalumab + FLOT improves survival in gastric/GEJ cancer.
D-FLOT → Preferred where eligible
FLOT → Standard alternative
No direct D-FLOT vs CROSS trial.
4. THE TAKE-HOME
Fit, eligible GEJ patient → D-FLOT / FLOT
FLOT unsuitable → Consider CROSS if appropriate
Siewert type | Fitness | MDT decision
[Slide 1]
Rapid Oral session
2878RO - FOLFIRI plus ramucirumab versus paclitaxel plus ramucirumab as second-line therapy for taxane-pretreated patients with advanced or metastatic gastroesophageal adenocarcinoma-Final results of the phase III IKFs602/AIO RAMIRIS Study
Speakers Sylvie Lorenzen (Munich, Germany)
Lecture Time 16:47 - 16:52
Abstract
Background
Ramucirumab (Ram) as monotherapy or plus paclitaxel is approved as 2nd-line treatment for advanced gastroesophageal adenocarcinoma (GEA). Many patients (pts) are pretreated with a taxane in previous lines, these may benefit from a non-cross resistant chemotherapy backbone regimen which was indicated by results from the phase II part of this trial.
Methods
This is an international, randomized, investigator initiated, phase II/III trial. Taxane-pretreated pts with GEA who have progressed after a fluoropyrimidine/platinum-containing regimen were randomized 1:1 to either FOLFIRI plus Ram q2w (Arm A) or paclitaxel (d 1, 8, 15 q28d) plus Ram q2w (Arm B). Co-primary endpoints were overall survival (OS) and objective overall response rate (ORR), further endpoints included DCR, PFS, quality of life and safety. Efficacy was assessed in the intention-to-treat (ITT) population.
Results
319 pts were enrolled between 2019 and 2024 and 317 analyzed within ITT (Arm A, 158; Arm B, 159; median age 60 years, 76% male). There was no significant difference in median OS (A, 8.7 vs. B, 7.5 mo, HR 0.95, p=.33, median FU A, 52, B, 31 mo) and ORR (A, 25.3% vs. B, 22.6%, p=.29 ). Median PFS was longer in Arm A with 5.5 vs. B, 3.7 mo (HR 0.7, p=.003) and DCR was A, 64% and B, 61%. Combination of Ram and FOLFIRI was not associated with more grade 3-5 adverse events in Arm A vs. B (70% vs. 68% of safety population N=304). Most common grade 3/4 adverse events included neutropenia (A, 17%, B, 12%), hypertension (A, 10%, B, 8%), anemia (A, B, 6%), and lung infection (A, 3%, B, 6%). 47% of the pts in Arm A and 55% in Arm B had at least one serious adverse event.
Conclusions
The RAMIRIS trial demonstrated feasibility of the combination of FOLFIRI and Ram. The co-primary endpoints were not met, however, PFS was clearly improved and trends towards a benefit of Ram/FOLFIRI regarding all other efficacy endpoints were seen. These findings support the personalization of treatment decisions in pts with taxane-pretreated advanced GEA after failure of standard therapy. More data will be presented at the meeting.
[Slide 1]
MADRID 2026 ESMO congress
MADRID SPAIN 23-27 OCTOBER 2026
Hepatobiliopancreatic SELECTED ABSTRACTS
Presidential Symposium II | 25 October 2026 | 17:42-18:15
LBA8 - Ivonescimab plus chemotherapy versus durvalumab plus chemotherapy as first-line treatment for advanced biliary tract cancer: a randomized, controlled, double- blinded, phase 3 trial (HARMONi-GI1)
Proffered paper 1: Gastrointestinal tumour, upper digestive | 23 October 2026 | 13:30-15:00
LBA82 - Daraxonrasib, a RAS(ON) multi-selective inhibitor vs chemotherapy in previously treated metastatic pancreatic adenocarcinoma (mPDAC): Additional subgroup analyses from the Ph3 RASolute 302 study.
LBA83 - Seven-Valent mKRAS-specific Lymph Node Targeted Amphiphile Immunotherapy Versus Observation in Resected Pancreatic Ductal Adenocarcinoma (PDAC): the AMPLIFY-7P randomized Phase 2 study
Proffered paper 2: Gastrointestinal tumours, upper digestive | 24 October 2026 | 10:15-11:45
459O - A randomized trial of paclitaxel ± tovecimig in previously treated patients with advanced biliary tract cancer
LBA21 - Adjuvant chemotherapy with gemcitabine and cisplatin compared to standard of care after curative intent resection of cholangiocarcinoma and gallbladder carcinoma (ACTICCA-1 trial)
LBA48 - Liver function trajectory and post-progression outcomes in the Phase 3 EMERALD-3 study of tremelimumab (T) + durvalumab (D) ± lenvatinib (L) + transarterial chemoembolisation (TACE) in participants (pts) with embolisation-eligible hepatocellular carcinoma (eeHCC)
1679O - Phase I study of BGB-B2033 (GPC3 x 4-1BB bispecific antibody) monotherapy: First disclosure of dose optimization (DO) and dose escalation (DE) update in advanced hepatocellular carcinoma (HCC)
Rapid oral 1: Gastrointestinal tumour, upper digestive | 23 October 2026 | 16:45-18:15
3136RO - Randomised phase II study of mFOLFIRINOX ± SBRT in patients with high risk, borderline resectable or locally advanced pancreatic cancer: Results of the AGITG MASTERPLAN trial
Rapid oral 2: Gastrointestinal tumour, upper digestive | 26 October 2026 | 14:45-16:15
LBA85 - HRS-4642 Plus Chemotherapy ± Adebrelimab as Perioperative Therapy in KRAS G12D-Mutant Pancreatic Cancer: Preliminary Results of a Phase 2 Study
3137RO - Safety and efficacy of INCB161734, a novel oral KRAS G12D inhibitor, in combination with chemotherapy in patients (pts) with advanced/metastatic pancreatic ductal adenocarcinoma (PDAC)
1678RO - Phase 3 LEAP-012 study of lenvatinib + pembrolizumab vs dual placebo with transarterial chemoembolization (TACE) for unresectable non-metastatic hepatocellular carcinoma: Long-term OS results
LBA22 - OPTIMUM: A randomized phase 2 study of maintenance olaparib (Ola) with or without durvalumab (Durva) in DDR gene-mutated advanced biliary tract cancer (aBTC)
473RO - Subcutaneous anti-PD-L1 monoclonal antibody envafolimab plus gemcitabine and oxaliplatin (GEMOX) versus GEMOX alone as first-line treatment for advanced biliary tract cancer in Chinese patients: A randomized, open-label, multicenter, registrational phase III trial
Nieves Martínez Lago · @DraMartinezLago | #ESMO26
[Slide 1]
SANO
Surgery vs surveillance after CRT (41.4 Gy in 23 fractions)
Locally advanced esophageal cancer
~75% adenocarcinoma
cCR after CRT
n = 309
→ RANDOMIZE
Standard surgery (n = 111) | 5-year OS 54% | 5-year distant metastases 29%
Active surveillance (n = 198) | 5-year OS 50% | 5-year distant metastases 46%
Hospital-level randomization
12 hospitals; stepped-wedge
Counts include crossover
OS: HR 1.17 (95% CI 0.77-1.77), surveillance vs surgery; not statistically significant.
Distant metastases: cumulative incidence; P < .01. Primary endpoint: 2-year OS (NI margin: 15 points).
van der Wilk et al. Lancet Oncol 2025;26:425-436. 5-year update: ESMO 2026, LBA78.
[Slide 1]
Abstract
Proffered Paper session
LBA78 - Active surveillance versus standard surgery after neoadjuvant chemoradiotherapy for oesophageal cancer: Long-term results of a cluster-randomised controlled trial (SANO)
Speakers Sanjiv S. Gangaram-Panday (Rotterdam, Netherlands)
Lecture Time 13:40 - 13:50
Abstract
Background
The Surgery As Needed for Oesophageal cancer (SANO)-trial demonstrated that active surveillance is non-inferior to standard surgery in terms of two-year overall survival in patients with a complete clinical response after neoadjuvant chemoradiotherapy (nCRT). Active surveillance resulted in improved quality of life. Here, we report 5-year outcomes.
[Slide 2]
Methods
From 2017 to 2021, a multicentre stepped-wedge cluster-randomised non-inferiority trial was conducted. Patients with locally advanced oesophageal cancer who achieved complete clinical response (defined as no tumour detected on endoscopic biopsies, -ultrasound, or PET-CT) underwent active surveillance or standard surgery. Cox regression was used to compare 5-year overall and disease-free survival, and the cumulative incidence of distant metastases was estimated using competing risk analysis.
[Slide 3]
Results
A total of 309 patients were included, 198 underwent active surveillance and 111 underwent standard surgery. Median follow-up was 76 months (IQR 67–86). Five-year overall survival was not statistically significantly different between active surveillance and standard surgery (50%, 95%CI 34-57 vs. 54%, 95%CI 46-64; HR 1.17, 95%CI 0.77-1.77) with similar results across histologic subtypes. Disease-free survival was not statistically significantly different (HR 1.39, 95% CI 0.94-2.06). The cumulative incidence of distant metastases at five years was significantly higher in the active surveillance group compared to the standard surgery group (46%, 95%CI 39-53 vs. 29%, 95%CI 21-37; P<.01). Overall, 85 of 198 patients (43%) were spared non-beneficial oesophagectomy, including those with sustained complete clinical response at last follow-up or distant metastases detected within six months after nCRT.
Conclusions
Overall survival at 5 years is not statistically significantly different between active surveillance and standard surgery in patients with oesophageal cancer and a complete clinical response after nCRT, despite a higher incidence of distant metastases in the active surveillance group. These findings support active surveillance as a feasible treatment strategy in these patients.
[Slide 1]
2877RO - Watch-and-wait (W&W) strategy for dostarlimab in localized deficient dMMR/MSI-H gastroesophageal adenocarcinoma (GEA): Results from the first interim analysis of the GERCOR-GONO DEWI phase II study
Speakers Thierry André (Paris, France, CEDEX 12)
Lecture Time 16:42 - 16:47
Abstract
Background
Patients (Pts) with dMMR/MSI-H localized GEA have better survival after surgery and scant/no benefit from chemotherapy. Preoperative immune checkpoint inhibitors demonstrated high rates of pathologic complete response (CR), supporting chemotherapy/surgery-free strategies. DEWI trial evaluates whether surgery can be omitted in Pts achieving clinical CR (cCR), defined as CR on endoscopy with tumor-free biopsies and normal CT imaging after dostarlimab, using a W&W strategy.
Methods
Pts with localized dMMR/MSI-H GEA, PS 0-1, and clinical stage T2-T4 NxM0 were included and received dostarlimab 500 mg q3w for 4 cycles. An adaptive treatment strategy was defined based on assessment at 12 and 24 weeks (w) according to cCR to decide to continue dostarlimab for 24w with a W&W strategy or to operate. The primary endpoint is the rate of cCR at 1 year (1y-cCR) without GEA surgery, with the objective of demonstrating a 1y-cCR rate >25% (50% expected). Secondary endpoints include survival outcomes and safety.
Results
Between Jan 2024 and Dec 2025, 60 Pts were included; one was excluded prior to treatment. A planned first interim analysis of the primary endpoint was conducted in the first 24 evaluable Pts for 1y-cCR. The median age was 65 years; 18/6 Pts were male/female, oesogastric junction/stomach in 9/15 Pts. The 1y-cCR rate was 62.5% (15/24), and continuation of enrollment was recommended by the Independent Data Monitoring Committee. No events (relapse or death) occurred in Pts with 1y-cCR with a median follow-up of 16.20 months (95%CI 12.22-17.22). Two events were observed in Pts without 1y-cCR: one metastatic progression and one postoperative death. Overall grade 3-4 dostarlimab-related adverse events occurred in 5 Pts (21%). Nine/24 Pts underwent surgery, all achieving R0 with TNM: yT1N0 (n=2), yT1N1 (n=1), yT3-N1-2 (n=4), and yT4N0 (n=2); TRG (Becker): TRG2 (n=3), TRG 3 (n=6). Three Pts had anastomotic fistula.
Conclusions
Dostarlimab in Pts with localized dMMR/MSI-H GEA led to a 62.5% 1y-cCR at the first interim analysis, enabling organ preservation. An update on the 60 included Pts is planned for the meeting.
[Slide 1]
3530O - Neoadjuvant short-course radiotherapy followed by camrelizumab and chemotherapy in locally advanced rectal cancer (LARC): The phase 3 UNION trial
Speakers Zhen Yu Lin (Wuhan, China)
Lecture Time 11:10 - 11:20
Abstract
Background
Despite the use of neoadjuvant chemoradiotherapy, recurrence and distant metastasis remain common in LARC. Effective immunotherapy-based strategies for the predominantly proficient mismatch repair/microsatellite-stable population remain limited. UNION is the first phase 3 trial to evaluate a neoadjuvant strategy incorporating radiotherapy, immunotherapy, and chemotherapy in LARC. Here we present the prespecified event-free survival (EFS) analysis.
Methods
Patients with cT3-4 or N+ rectal adenocarcinoma (tumor located ≤10 cm from the anal verge) were randomly assigned (1:1) to receive short-course radiotherapy (SCRT; 25 Gy/5f; experimental group) or long-course chemoradiotherapy (50.4 Gy/28f with concurrent capecitabine 825 mg/m2 twice daily; standard of care group) followed by 2 neoadjuvant cycles and 6 adjuvant cycles of capecitabine and oxaliplatin (CAPOX). The experimental group additionally received neoadjuvant and adjuvant camrelizumab (200 mg, day 1) since CAPOX treatment for up to 17 cycles. The primary endpoint was blinded independent review committee (BIRC)-assessed pathological complete response rate. Key secondary endpoints with prespecified α allocation were investigator-assessed EFS and overall survival.
Results
Between July 2021 and March 2023, 231 patients were randomized to the experimental group (n=113) and standard of care group (n=118). As of October 1, 2025, the median follow-up duration was 36.8 months (95% CI, 34.8-37.8) and 35.6 months (95% CI, 34.3-36.9), respectively. The 3-year EFS rate was significantly higher in the experimental group compared with standard of care (91.3% [95% CI, 83.9-95.4] vs 77.4% [95% CI, 67.9-84.4], hazard ratio=0.33 [95% CI, 0.15-0.71], P=0.0029). BIRC-assessed EFS consistently favored the experimental group. During the whole treatment period, the incidence of grade ≥3 treatment-related adverse events was 51.3% (59/115) and 48.2% (54/112), respectively.
Conclusions
UNION is the first phase 3 trial to demonstrate a significant improvement in EFS with an immunotherapy-based regimen in LARC. This neoadjuvant strategy represents a new standard of care.
[Slide 1]
Proffered Paper session
LBA82 - Daraxonrasib, a RAS(ON) multi-selective inhibitor vs chemotherapy in previously treated metastatic pancreatic adenocarcinoma (mPDAC): Additional subgroup analyses from the ph3 RASolute 302 study
Speakers Zev A. Wainberg (Los Angeles, United States of America)
Lecture Time 14:22 - 14:32
Abstract
Background
Multiagent systemic chemo offers limited benefit in mPDAC. Aberrant RAS(ON) signaling drives PDAC; >90% of cases harbor mutant (mut) RAS, and RAS WT PDAC remains dependent on RAS pathway signaling. Daraxonrasib is an oral, RAS(ON) multi-selective, tri-complex inhibitor of active, GTP-bound mut and WT RAS. Daraxonrasib significantly improved OS and PFS vs SOC chemo in pts with previously treated mPDAC overall (with or without an identified tumor RAS mut; mOS 13.2 vs 6.7 mo; HR, 0.40; mPFS 7.2 vs 3.6 mo; HR, 0.49) and in pts with RAS G12 mut mPDAC (OS HR, 0.40; PFS HR, 0.45) with manageable safety in the RASolute 302 primary analysis (NCT06625320). We report additional subgroup analyses from RASolute 302.
[Slide 2]
OS in subgroups
| | n (%) Daraxonrasib n=248 | Chemo n=252 | OS HR (95% CI) |
Tumor RAS mut status
| G12D | 95 (38) | 121 (48) | 0.49 (0.33-0.74) |
| G12V | 102 (41) | 76 (30) | 0.32 (0.19-0.54) |
| G12R | 30 (12) | 31 (12) | 0.61 (0.29-1.30) |
| RAS Q61 | 11 (4) | 11 (4) | 0.37 (0.09-1.44) |
| No RAS mut identified | 9 (4) | 7 (3) | 0.43 (0.09-1.98) |
Conclusions
Daraxonrasib demonstrated OS benefit vs chemo across clinically relevant subgroups including pts with or without an identified tumor RAS mut. Directionally consistent OS benefit across these subgroups further reinforces the potential for daraxonrasib to be a new SOC for eligible pts with mPDAC.
[Slide 3]
Methods
Pts with previously treated mPDAC were randomized 1:1 to daraxonrasib 300 mg PO QD or investigator's choice of SOC chemo (GnP, mFOLFIRINOX, Nal-IRI+5-FU/LV, or FOLFOX). Dual primary endpoints (EPs) were OS and PFS in the RAS G12 mut population; key secondary EPs included OS and PFS in the overall population. Additional analyses evaluated OS in clinically relevant subgroups by locally determined tumor RAS mut status, preselected chemo regimen, and disease setting of prior treatment.
Results
At data cutoff (10 Feb 2026), median follow-up was 8.5 mo (range, 3.2-15.9). OS benefit with daraxonrasib vs chemo was observed across all RAS mut subgroups (Table). Daraxonrasib showed a consistent OS treatment effect across preselected chemo subgroups (HRs, 0.32-0.46). OS data by disease setting of prior treatment will also be presented.
Table: LBA82
[Slide 1]
2879RO - Durvalumab plus definitive chemoradiotherapy versus definitive chemoradiotherapy in patients with locally advanced esophagus carcinoma: ARION PRODIGE 67 randomized phase 2 trial
Speakers Marie-Anouchka Modesto (Toulouse, France)
Lecture Time 17:09 - 17:14
Abstract
Background
In locally advanced or unresectable esophageal cancer, definitive chemoradiotherapy (CRT) is the standard of care (SoC) combining radiotherapy with platinum-based chemotherapy, resulting in a 2-year disease-free survival of 25%, which remains an unmet medical need. As immune checkpoint inhibitors increase survival in the metastatic setting, a multicentric, this open-label, comparative phase II ARION trial was designed to assess efficacy and safety of PD1/PDL1 blockade by durvalumab (D) added to SoC.
Methods
Patients (pts) ≥18 years old, WHO performance status ≤1, non-metastatic, locally advanced squamous cell carcinoma (SCC) or unresectable adenocarcinoma (ADK), (stratified by tumor stage, histology, centers) were randomized between arm A with 12 monthly 1500 mg (D) infusions added to SoC (IMRT 50 Gy/25 daily fractions over 5 weeks) and 6 cycles of FOLFOX regimen: oxaliplatin 85 mg/m2, Leucovorin 200 mg/m2, 5-FU 400 mg/m2 bolus then continuous 2400 mg/m2 over 46 h) or arm B (SoC). Primary endpoint was centrally reviewed progression-free survival (cPFS). Overall survival (OS), PFS and safety were secondary endpoints. 74 cPFS events were required to detect a hazard ratio (HR) of 0.55 with 90% power (10% one-sided alpha).
Results
Between May 2019 and May 2024, 112 pts were randomized (Arm A: SoC + D, n=58 / Arm B: SoC, n=54) in 13 French sites. Analysis was performed after a 24-month follow-up. Median age was 67 years, 68% were male, 77% were SCC, 70% had nodal extension. There was no significant difference between arms for cPFS, PFS and OS (table). Treatment-related adverse events (AE) were higher in arm A. Grade ≥ 3 AE rates were similar in both arms. Table: 2879RO
| | Arm A (exp) 12-month rate [95%CI] | Arm B (SoC) 12-month rate [95%CI] | Adjusted HR* [95%CI] [80%CI] | 1-sided p-value |
| cPFS | 48.6% [34.6; 61.3] | 48.9% [34.7; 61.7] | 0.91 [0.55; 1.49] [0.66; 1.25] | 0.351 |
| PFS | 50.1% [36.2; 62.5] | 48.1% [33.7; 61.2] | 0.92 [0.56; 1.50] [0.67; 1.27] | 0.369 |
| OS | 75.1% [61.6; 84.4] | 67.9% [53.6; 78.7] | 0.99 [0.59; 1.68] [0.70; 1.40] | 0.489 |
*for Histological subtype, Stage
Conclusions
In this indication, Durvalumab with CRT compared to SoC did not improve PFS. There was no new safety signal. Longer survival, follow-up and predictive factors for treatment efficacy will be presented.
[Slide 1]
MADRID 2026 ESMO congress
MADRID SPAIN 23-27 OCTOBER 2026
Gastroesophageal | SELECTED ABSTRACTS
Presidential Symposium II | 25 October 2026 · 17:18-17:42
LBA7 - CLARITY-Gastric 01 (CG-01): a Phase 3 study of sonesitatug vedotin (Sone-Ve) in second or later-line (2L+) advanced or metastatic Claudin 18.2 (CLDN18.2) positive gastroesophageal carcinoma (GEC)
Proffered paper 1: Gastrointestinal tumour, upper digestive | 23 October 2026 · 13:30-15:00
LBA77 - Arcotatug tavatecan (IBI343/TAK-921) versus treatment of physician's choice (TPC) in previously treated, advanced gastric or gastroesophageal junction adenocarcinoma (G/GEJA): First interim analysis of the randomized, open-label, phase 3, G-HOPE-001 study
LBA78 - Active surveillance versus standard surgery after neoadjuvant chemoradiotherapy for oesophageal cancer: long-term results of a cluster-randomised controlled trial (SANO)
2875O - Pembrolizumab or placebo plus concurrent definitive chemoradiotherapy in esophageal and gastroesophageal junction (GEJ) cancer: The phase 3 randomized KEYNOTE-975 study
Rapid oral 1: Gastrointestinal tumour, upper digestive | 23 October 2026 · 16:45-18:15
LBA79 - Zanidatamab (zani) + chemotherapy (CT) ± tislelizumab (TIS) for first-line (1L) HER2-positive (HER2+) advanced/metastatic gastroesophageal adenocarcinoma (mGEA): second interim analysis (IA) from HERIZON-GEA-01
LBA80 - Anbenitamab plus chemotherapy for previously treated HER2-positive gastric or gastroesophageal carcinomas (GC/GEJC): Updated overall survival (OS) analysis of KC-WISE
2876RO - TQB2102, a novel HER2 bispecific antibody-drug conjugate, combined with bemotrizumab with or without capecitabine as first-line therapy for HER2-positive advanced gastric/gastroesophageal junction cancer: A phase II study
2877RO - Watch-and-wait (W&W) strategy for dostarlimab in localized deficient dMMR/MSI-H gastroesophageal adenocarcinoma (GEA): Results from the first interim analysis of the GERCOR-GONO DEWI phase II study
2878RO - FOLFIRI plus ramucirumab versus paclitaxel plus ramucirumab as second-line therapy for taxane-pretreated patients with advanced or metastatic gastroesophageal adenocarcinoma-Final results of the phase III IKFs602/AIO RAMIRIS Study
LBA81 - Four Months of Adjuvant XELOX versus Six Months in Stage II-IIIB Gastric Cancer - The LOMAC Randomized Trial
2879RO - Durvalumab plus definitive chemoradiotherapy versus definitive chemoradiotherapy in patients with locally advanced esophagus carcinoma: ARION PRODIGE 67 randomized phase 2 trial
2883RO - Efficacy of bemarituzumab in patients with advanced gastric and gastroesophageal junction cancer (GC/GEJ) by FGFR2 amplification status: Exploratory biomarker analysis from FORTITUDE-101 (F101) and FORTITUDE-102 (F102)
Nieves Martínez Lago · @DraMartinezLago | #ESMO26
[Slide 1]
Proffered Paper session
2875O - Pembrolizumab or placebo plus concurrent definitive chemoradiotherapy in esophageal and gastroesophageal junction (GEJ) cancer: The phase 3 randomized KEYNOTE-975 study
Speakers Manish A. Shah (New York, United States of America)
Lecture Time 13:50 - 14:00
Abstract
Background
The role of immunotherapy in participants (pts) with locally advanced, esophageal cancer (EC) treated with definitive chemoradiotherapy (dCRT) is not established. KEYNOTE-975 (NCT04210115) is an international phase 3, randomized, double-blind, placebo (pbo) controlled multicenter study that examines dCRT ± pembro in pts with previously untreated locally advanced unresectable esophageal and GEJ cancer. We report results from the second interim analysis (IA2).
Methods
Eligible pts with histologically confirmed cTX N+ M0 or cT2-T4a NX M0 esophageal squamous cell cancer (ESCC) or adenocarcinoma (EAC) or GEJ cancer, or cTX N+ M1 cervical or upper thoracic EC with supraclavicular lymph node metastases only, ECOG PS 0-1, and who were ineligible for curative surgery but suitable for dCRT, were randomized 1:1 to 200 mg pembro or pbo Q3W for 8 cycles then 400 mg pembro or pbo Q6W for 5 cycles + site choice of dCRT (5-fluorouracil + cisplatin [FP] with radiotherapy [RT] 50 Gy or 60 Gy, or FOLFOX with RT 50 Gy). Dual-primary endpoints were event-free survival (EFS) by investigator and OS in pts with PD-L1 combined positive score (CPS) ≥10, CPS ≥1, and all pts. Data cut-off was Jan 21, 2026.
Results
A total of 703 pts were randomized (349 pembro + dCRT; 354 pbo + dCRT). Median follow-up was 47.1 mo (range, 21.7-70.2) in all pts. At IA2, in pts with PD-L1 CPS ≥10, EFS was not improved with pembro + dCRT vs pbo + dCRT (median 15.2 vs 14.7 mo; HR 0.97; 95% CI, 0.77-1.23 [P=0.3994; P-value boundary for significance 0.0193]). In pts with PD-L1 CPS ≥10, median OS was 32.2 mo vs 35.0 mo (HR 1.00; 95% CI, 0.77-1.30 [nominal P-value 0.5003]). As EFS was not positive in PD-L1 CPS ≥10, EFS in PD-L1 CPS ≥1 and all pts, and OS were not tested for statistical significance, and the study was stopped. Grade ≥3 AEs occurred in 100% of pts in each arm, with grade 5 AEs in 44 (13%) vs 37 (10%) pts. Discontinuation due to any AE occurred in 117 (34%) vs 97 (27%) pts.
Conclusions
Pembrolizumab + dCRT vs pbo + dCRT did not significantly improve EFS in untreated unresectable esophageal or GEJ cancer with PD-L1 CPS ≥10. No new safety signals were observed.
[Slide 1]
Can SBRT Improve Pancreatic Cancer Outcomes?
MV Onco
01 - THE CLINICAL QUESTION
Chemotherapy treats systemic disease. But local recurrence remains common. Can adding SBRT improve outcomes?
02 - WHO WAS STUDIED?
74 eligible patients | 14 centres
• High-risk operable pancreatic cancer
• Borderline-resectable disease
• Locally advanced / inoperable disease
03 - RANDOMISED 2:1
SBRT ARM - 49 patients: 3 months chemotherapy → SBRT: 40 Gy / 5 fractions
CONTROL - 25 patients: 3 months chemotherapy → No planned SBRT
04 - WHICH CHEMOTHERAPY?
• Predominantly mFOLFIRINOX (~90%)
• Alternative: Gemcitabine + nab-paclitaxel
05 - WHAT WAS MEASURED?
Primary endpoint: Locoregional recurrence at 12 months
Secondary endpoints: PFS • OS • Surgery • Toxicity
BOTTOM TAKE-HOME
MASTERPLAN tested whether adding just 5 fractions of SBRT could improve outcomes beyond chemotherapy alone.
[Slide 2]
Did SBRT Really Improve Local Control?
MV Onco
01 - PRIMARY ENDPOINT
Locoregional recurrence at 12 months (lower is better)
SBRT + chemotherapy: 20.2%
Chemotherapy alone: 52.0%
p = 0.022
Absolute reduction: 31.8 percentage points
02 - POTENTIALLY OPERABLE
High-risk operable + borderline-resectable (lower is better)
SBRT: 19.7%
Control: 52.9%
p = 0.031
Significant improvement in local control.
03 - INOPERABLE DISEASE
Locally advanced / medically inoperable (lower is better)
SBRT: 21.4%
Control: 50.0%
p = 0.16
Numerically better, but not statistically significant.
04 - WHAT DOES THIS MEAN?
• Adding SBRT reduced locoregional recurrence.
• The overall primary endpoint was met.
• Subgroup results need cautious interpretation.
BOTTOM TAKE-HOME
SBRT significantly improved 12-month locoregional control - but does better local control translate into longer survival?
[Slide 3]
Did SBRT Improve Survival?
MV Onco
01 - OVERALL SURVIVAL
Median OS
SBRT: 22 months
Control: 14 months
P = 0.006
8-month longer median survival.
02 - PROGRESSION-FREE SURVIVAL
Median PFS
SBRT: 11.9 months
Control: 6.3 months
P = 0.002
5.6-month improvement.
03 - DID MORE PATIENTS UNDERGO SURGERY?
Among potentially operable patients:
Resection: 68% vs 59%
R0 among resected: 62% vs 40%
Neither difference was stattistically significant.
04 - WHAT ABOUT TOXICITY?
Grade ≥3 adverse events:
SBRT: 70.2%
Control: 64.0%
P = 0.27
No stattistically significant difference.
BOTTOM TAKE-HOME
SBRT improved PFS and showed an encouraging OS signal.
But this was a small phase II trial.
[Slide 4]
Is SBRT Ready to Change Practice?
MV Onco
01 - WHY IS MASTERPLAN IMPORTANT?
• Randomized phase II trial.
• Better local control.
• Encouraging PFS and OS signals.
• But only 74 eligible patients.
02 - WHAT ABOUT ALLIANCE A021501?
• Alliance A021501: Adding hypofractionated radiation after mFOLFIRINOX did not improve outcomes.
• MASTERPLAN: SBRT improved local control, with encouraging survival results.
• Different trials. Different populations.
• Direct comparison is inappropriate.
03 - WHAT ARE THE LIMITATIONS?
• Small phase II study.
• Mixed resectability groups.
• Only 80% started assigned SBRT.
• OS was a secondary endpoint.
• Phase III confirmation is needed.
04 - SHOULD PRACTICE CHANGE TODAY?
• Not routinely.
• Consider SBRT selectively after MDT discussion.
• Patient selection remains crucial.
• Await mature data and larger trials.
BOTTOM TAKE-HOME
• MASTERPLAN strengthens the case for SBRT in selected pancreatic cancer patients.
• Promising evidence ≠ New standard of care.
[Slide 2]
RASolute 302:
RAS subgroup analysis
late-breaking abstract
LBA82
October 23, 1:30–3:00 p.m. CEST
Almeria Auditorium, Hall 9
RevMed
[Slide 3]
Industry Sponsored Satellite Symposium:
Advances in RAS-targeted therapies in NSCLC and PDAC
October 26, 6:30–8:00 p.m. CEST
Salamanca Auditorium, Hall 10
RevMed
[Slide 1]
HARMONi-GI1
IS DURVALUMAB'S THRONE UNDER THREAT?
MV Onco
[Cartoon: antibody on a throne labelled DURVALUMAB + CHEMO saying "I'm the established standard!"; bispecific antibody labelled PD-1 / VEGF, IVONESCIMAB + CHEMO saying "I may improve survival!"; frightened tumour labelled Biliary tract cancer]
PHASE III | ADVANCED BILIARY TRACT CANCER
Ivonescimab + chemotherapy vs Durvalumab + chemotherapy
WHAT WE KNOW
☑ OS superiority met - sponsos-reported
☑ PFS endpoint met
☑ Response-rate endpoint met
⚠ Sponsor-reported topline results. Actual survival numbers and detailed safety data awaited.
WATCH OUT AT ESMO 2026!
OCTOBER 25, 2026
PRESIDENTIAL SYMPOSIUM II
LATE-BREAKING ABSTRACT: LBA8
Presenter: Jian Zhou | Madrid | 4:30-6:15 PM CEST
? HOW MANY EXTRA MONTHS OF SURVIVAL? | ? WILL GALLBLADDER CANCER BENEFIT TOO?
Could BTC get a new first-line standard? The numbers will decide.
[Slide 1]
Proffered Paper session
3530O - Neoadjuvant short-course radiotherapy followed by camrelizumab and chemotherapy in locally advanced rectal cancer (LARC): The phase 3 UNION trial
Speakers Zhen Yu Lin (Wuhan, China)
Lecture Time 11:10 - 11:20
Abstract
Background
Despite the use of neoadjuvant chemoradiotherapy, recurrence and distant metastasis remain common in LARC. Effective immunotherapy-based strategies for the predominantly proficient mismatch repair/microsatellite-stable population remain limited. UNION is the first phase 3 trial to evaluate a neoadjuvant strategy incorporating radiotherapy, immunotherapy, and chemotherapy in LARC. Here we present the prespecified event-free survival (EFS) analysis.
Methods
Patients with cT3-4 or N+ rectal adenocarcinoma (tumor located ≤10 cm from the anal verge) were randomly assigned (1:1) to receive short-course radiotherapy (SCRT; 25 Gy/5f; experimental group) or long-course chemoradiotherapy (50.4 Gy/28f with concurrent capecitabine 825 mg/m² twice daily; standard of care group) followed by 2 neoadjuvant cycles and 6 adjuvant cycles of capecitabine and oxaliplatin (CAPOX). The experimental group additionally received neoadjuvant and adjuvant camrelizumab (200 mg, day 1) since CAPOX treatment for up to 17 cycles. The primary endpoint was blinded independent review committee (BIRC)-assessed pathological complete response rate. Key secondary endpoints with prespecified α allocation were investigator-assessed EFS and overall survival.
Results
Between July 2021 and March 2023, 231 patients were randomized to the experimental group (n=113) and standard of care group (n=118). As of October 1, 2025, the median follow-up duration was 36.8 months (95% CI, 34.8-37.8) and 35.6 months (95% CI, 34.3-36.9), respectively. The 3-year EFS rate was significantly higher in the experimental group compared with standard of care (91.3% [95% CI, 83.9-95.4] vs 77.4% [95% CI, 67.9-84.4], hazard ratio=0.33 [95% CI, 0.15-0.71], P=0.0029). BIRC-assessed EFS consistently favored the experimental group. During the whole treatment period, the incidence of grade ≥3 treatment-related adverse events was 51.3% (59/115) and 48.2% (54/112), respectively.
Conclusions
UNION is the first phase 3 trial to demonstrate a significant improvement in EFS with an immunotherapy-based regimen in LARC. This neoadjuvant strategy represents a new standard of care.
[Slide 1]
Rapid Oral session
Rapid oral 1: Gastrointestinal tumour, upper digestive
Date Fri, 23.10.2026
Chairs Maria Ignez Braghiroli (Sao Paulo, Brazil, SP), Feng Wang (Guangzhou, China), Lucjan S. Wyrwicz (Warsaw, Poland)
Room Almeria Auditorium - Hall 9
Time 16:15 - 17:45
Rapid Oral session
LBA79 - Zanidatamab (zani) + chemotherapy (CT) ± tislelizumab (TIS) for first-line (1L) HER2-positive (HER2+) advanced/metastatic gastroesophageal adenocarcinoma (mGEA): second interim analysis (IA) from HERIZON-GEA-01
Speakers Kohei Shitara (Kashiwa, Japan, Chiba)
Lecture Time 16:15 - 16:20
Rapid Oral session
LBA80 - Anbenitamab plus chemotherapy for previously treated HER2-positive gastric or gastroesophageal carcinomas (GC/GEJC): Updated overall survival (OS) analysis of KC-WISE
Speakers Ruixing Zhang (Shijiazhuang, China, Hebei)
Lecture Time 16:20 - 16:25
Rapid Oral session
2876RO - TQB2102, a Novel HER2 Bispecific Antibody-Drug Conjugate, Combined with Bemotrizumab with or without Capecitabine as First-Line Therapy for HER2-Positive Advanced Gastric/Gastroesophageal Junction Cancer: A Phase II Study
Speakers Miaozhen Qiu (Guangzhou, China)
Lecture Time 16:25 - 16:30
Rapid Oral session
Invited Discussant LBA79, LBA80 and 2876RO
Speakers Maria Ignez Braghiroli (Sao Paulo, Brazil, SP)
Lecture Time 16:30 - 16:42
Rapid Oral session
2877RO - Watch-and-wait (W&W) strategy for dostarlimab in localized deficient dMMR/MSI-H gastroesophageal adenocarcinoma (GEA): Results from the first interim analysis of the GERCOR-GONO DEWI phase II study
Speakers Thierry André (Paris, France, CEDEX 12)
Lecture Time 16:42 - 16:47
Rapid Oral session
2878RO - FOLFIRI plus ramucirumab versus paclitaxel plus ramucirumab as second-line therapy for taxane-pretreated patients with advanced or metastatic gastroesophageal adenocarcinoma–Final results of the phase III IKFs602/AIO RAMIRIS Study
Speakers Sylvie Lorenzen (Munich, Germany)
Lecture Time 16:47 - 16:52
Rapid Oral session
LBA81 - Four Months of Adjuvant XELOX versus Six Months in Stage II–IIIB Gastric Cancer — The LOMAC Randomized Trial
Speakers Dazhi Xu (Shanghai, China)
Lecture Time 16:52 - 16:57
[Slide 1]
MADRID 2026 ESMO congress
MADRID SPAIN 23-27 OCTOBER 2026
Colorectal SELECTED ABSTRACTS
Proffered paper: Gastrointestinal tumours, lower digestive | 25 October 2026 · 10:15-11:45
LBA29 | IROCAS: A randomized phase III trial of adjuvant treatment intensification with mFOLFIRINOX versus mFOLFOX6 in high-risk stage III (T4 and/or N2) colon cancer.
LBA30 | Omega-3 polyunsaturated fatty acid eicosapentaenoic acid (EPA) versus placebo after resection of colorectal cancer liver metastases (EMT2): A multicentre, double-blind, randomised phase 3 trial
LBA87 | Clinical Complete Response With Dostarlimab Monotherapy in dMMR/MSI-H Locally Advanced Rectal Cancer (LARC): First Results From the Global Registrational AZUR-1 Trial
3530O | Neoadjuvant short-course radiotherapy followed by camrelizumab and chemotherapy in locally advanced rectal cancer (LARC): The phase 3 UNION trial
Rapid oral: Gastrointestinal tumours, lower digestive | 24 October 2026 · 14:45-16:15
787RO | Circulating tumor DNA (ctDNA)-guided re-treatment (re-tx) with encorafenib and cetuximab (EC) in patients (pts) with chemorefractory BRAFV600E mutated metastatic colorectal cancer (mCRC): The proof-of-concept single arm phase II BRICKET trial by GONO
788RO | Encorafenib plus cetuximab (EC) beyond progression in combination with FOLFIRI in BRAF V600E metastatic colorectal cancer (mCRC) patients (pts) progressing on EC: Results from the ECLYPse phase II trial
789RO | TRIDENTE: A phase II study of rechallenge with encorafenib (ENCO), binimetinib (BINI), and cetuximab (CET) in BRAF V600E-mutant metastatic colorectal cancer (mCRC)
790RO | Preliminary clinical results of QTX3034, an oral G12D-preferring KRAS inhibitor, in combination with cetuximab ± mFOLFOX6 in patients with KRASG12D-mutated colorectal cancer (CRC)
791RO | Long-term follow-up of telisotuzumab adizutecan (ABBV-400, Temab-A) in combination with bevacizumab (Bev) vs standard of care (SOC) in patients (pts) with 3L+ colorectal cancer (CRC): Updated results of a phase 1 study
LBA31 | Biweekly versus conventional trifluridine/tipiracil plus bevacizumab for refractory metastatic colorectal cancer: the pragmatic phase 3 PRABITAS trial
LBA32 | Final overall survival results from CheckMate 8HW: nivolumab plus ipilimumab versus nivolumab or chemotherapy in MSI-H/dMMR metastatic colorectal cancer
Nieves Martínez Lago · @DraMartinezLago | #ESMO26
[Slide 1]
Proffered Paper session
LBA77 - Arcotatug tavatecan (IBI343/TAK-921) versus treatment of physician's choice (TPC) in previously treated, advanced gastric or gastroesophageal junction adenocarcinoma (G/GEJA): First interim analysis of the randomized, open-label, phase 3, G-HOPE-001 study
Speakers Kohei Shitara (Kashiwa, Japan, Chiba)
Lecture Time 13:30 - 13:40
[Abstract]
Background
Arcotatug tavatecan is a novel CLDN18.2-targeted ADC comprising an Fc-silenced antibody designed to reduce on target, off-tumor toxicity and conjugated to an exatecan-derived TOPO I inhibitor payload for selective delivery to tumor cells. Here, we report the prespecified first interim analysis (IA1) of the G-HOPE-001 study.
[Slide 2]
Results
In IA1, 408 pts from China and Japan (male: 62.0%, median age: 58.0, ECOG PS 1: 71.6%, primary tumor at stomach: 81.6%, primary tumor resection: 43.6%) were randomized to arcotatug tavatecan (N=203) and TPC (N=205) arms. IRRC-assessed median PFS was 5.5 months vs 2.9 months (HR: 0.47 [95% CI: 0.34-0.65], p-value <0.0001). With 34.8% of events, median OS was 9.9 months vs 7.4 months (HR: 0.63 [95% CI: 0.45-0.89]). IRRC-assessed ORR was 23.6% in arcotatug tavatecan and 5.3% in TPC. Grade ≥3 (G3+) TEAEs occurred in 45.8% pts with arcotatug tavatecan vs 57.9% pts with TPC. Common gastrointestinal TEAEs (≥10%) with arcotatug tavatecan vs TPC were nausea (38.9% vs 40.6%), vomiting (22.2% vs 28.4%) and diarrhea (12.8% vs 34.5%). Interstitial lung disease was not observed. TRAEs leading to treatment discontinuation occurred in 1.0% of pts in each arm. No TRAE led to death.
Conclusions
Arcotatug tavatecan demonstrated a statistically significant and clinically meaningful improvement in PFS with a manageable safety profile versus TPC for CLDN18.2+ G/GEJA in the 3L+ setting. OS results will be evaluated at the prespecified IA2.
[Slide 3]
Methods
Patients (pts) with unresectable or metastatic G/GEJA, CLDN18.2 IHC ≥2+ in ≥75% of tumor cells who had progressed on 2-4 prior regimens were randomized 1:1 to arcotatug tavatecan 6mg/kg Q3W or TPC (irinotecan, paclitaxel or trifluridine/tipiracil) until progression or unacceptable toxicity. Stratification factors were regions, primary tumor site and prior gastrectomy. Primary endpoints were IRRC-assessed PFS per RECIST v1.1 and OS. The prespecified IA1 included the PFS final analysis and an OS futility analysis, with a data cutoff of February 13, 2026.
[Slide 1]
Rapid Oral session
788RO - Encorafenib plus cetuximab (EC) beyond progression in combination with FOLFIRI in BRAF V600E metastatic colorectal cancer (mCRC) patients (pts) progressing on EC: Results from the ECLYPse phase II trial
Speakers Maria Alessandra Calegari (Rome, Italy)
Lecture Time 14:50 - 14:55
Abstract
Background
There is an unmet need for effective treatments in pts with BRAF V600E mCRC progressing on targeted therapy. ECLYPse was designed to address this issue based on two key premises: first, the hypothesis that due to intratumoral heterogeneity at progression, a disease subset may remain sensitive to EC; and second, the evidence of a synergistic activity of targeted agents in combination with chemotherapy (Cht) in first-line setting.
Methods
ECLYPse (NCT06640166) is a multicenter, single-arm, phase II study evaluating EC continuation beyond progression (E 300 mg daily, C 500mg/m2 i.v. every 2 weeks) in combination with FOLFIRI in pts with BRAF V600E mCRC progressing on second-line EC. The primary endpoint was investigator-assessed 6-month PFS rate in the ITT population. The study design (single-stage, α=0.05, 80% power) required enrolling 25 patients and observing ≥7 patients alive without progression at 6 months to reject the null hypothesis (H0: 6-month PFS ≤10%). Secondary endpoints included OS and safety.
Results
Between June 12, 2024 and April 15, 2026, 25 patients were enrolled. Main pts' characteristics were: men 68%, median age 65 yrs (range 37–84 yrs), ECOG PS 0 68%, right-sided primary tumor 64%, synchronous metastases 72%, peritoneal metastases 64%, liver metastases 64%, pMMR tumor 92%. As of May 8, 2026, with a median follow-up of 7.6 months, 14 disease progression events were observed. The investigator-assessed 6-month PFS rate was 69.5% (95% CI, 51.7–93.6%), and the mPFS was 7.1 months (95% CI, 6.2–NE months). Median OS was not reached; 6- and 12-month OS rates were 94.1% (95% CI, 83.6–100%) and 83.7% (95% CI, 64.5–100%), respectively. No new safety signal were observed, with adverse events occurring with the expected frequency and grade.
Conclusions
ECLYPse met its primary endpoint, with about two-thirds of the pts progression-free at 6 months. Continuing EC beyond progression on second-line plus Cht appears to extend disease control in this poor-prognosis population. These findings may serve as a pathfinder to guide future research in the post-BREAKWATER era and help identify the optimal therapeutic strategy.
[Slide 1]
Proffered Paper session
Proffered paper: Gastrointestinal tumours, lower digestive
Date Sun, 25.10.2026
Chairs Guillermo Argiles Martinez (New York, United States of America)
Room Almeria Auditorium - Hall 9
Time 10:15 - 11:45
Proffered Paper session
LBA29 - IROCAS: A randomized phase III trial of adjuvant treatment intensification with mFOLFIRINOX versus mFOLFOX6 in high-risk stage III (T4 and/or N2) colon cancer.
Speakers Jaafar Bennouna (Suresnes, France)
Lecture Time 10:15 - 10:25
Proffered Paper session
LBA30 - Omega-3 polyunsaturated fatty acid eicosapentaenoic acid (EPA) versus placebo after resection of colorectal cancer liver metastases (EMT2): A multicentre, double-blind, randomised phase 3 trial
Speakers Mark A. Hull (Leeds, United Kingdom)
Lecture Time 10:25 - 10:35
Proffered Paper session
Invited Discussant LBA29 and LBA30
Lecture Time 10:35 - 10:47
Proffered Paper session
Q&A and discussion
Lecture Time 10:47 - 11:00
Proffered Paper session
LBA87 - Clinical Complete Response With Dostarlimab Monotherapy in dMMR/MSI-H Locally Advanced Rectal Cancer (LARC): First Results From the Global Registrational AZUR-1 Trial
Speakers Andrea Cercek (New York, United States of America, NY)
Lecture Time 11:00 - 11:10
Proffered Paper session
3530O - Neoadjuvant short-course radiotherapy followed by camrelizumab and chemotherapy in locally advanced rectal cancer (LARC): The phase 3 UNION trial
Speakers Zhen Yu Lin (Wuhan, China)
Lecture Time 11:10 - 11:20
Proffered Paper session
Invited Discussant LBA87 and 353O
Speakers David Tougeron (Poitiers, France, CEDEX)
Lecture Time 11:20 - 11:32
Proffered Paper session
Q&A and discussion
Lecture Time 11:32 - 11:45
[Slide 1]
MASTERPLAN
Can 5 Fractions of SBRT Improve Survival?
MV Onco
THE TRIAL
74 patients | Randomized 2:1 | Phase II
High-risk operable, borderline-resectable or inoperable pancreatic cancer.
Chemotherapy + SBRT (n=49) versus Chemotherapy alone (n=25)
Predominantly mFOLFIRINOX. SBRT: 40 Gy in 5 fractions.
[Illustration: chemotherapy IV bag connected to a pancreas with a tumor, and a linear accelerator head delivering beams labeled "SBRT – 5 fractions"]
THE RESULTS
LOCAL RECURRENCE AT 12 MONTHS
SBRT: 20.2%
Control: 52.0%
p = 0.022
MEDIAN OVERALL SURVIVAL
SBRT: 22 months
Control: 14 months
p = 0.006
MEDIAN PFS
SBRT: 11.9 months
Control: 6.3 months
p = 0.002
SURGERY & SAFETY
Resection: 68% vs 59%
R0 among resected: 62% vs 40%
Neither difference statistically significant.
Grade ≥3 adverse events: 70.2% vs 64.0%
No statistically significant difference.
THE CLINICAL QUESTION
Better local control. Promising survival.
But only 74 patients in a Phase II trial.
Practice-changing? Not yet.
Phase III confirmation needed.
Oar A, et al. AGITG MASTERPLAN. ESMO 2026; Abstract 3136RO.
[Slide 1]
Rapid Oral session
787RO - Circulating tumor DNA (ctDNA)-guided re-treatment (re-tx) with encorafenib and cetuximab (EC) in patients (pts) with chemorefractory BRAFV600E mutated metastatic colorectal cancer (mCRC): The proof-of-concept single arm phase II BRICKET trial by GONO
Speakers Marco Maria Germani (Pisa, Italy)
Lecture Time 14:45 - 14:50
Abstract
Background
Current therapies for BRAFV600E-mutant mCRC after progression (PD) to EC are modestly effective. Resistance is largely driven by genomic alterations that can potentially decay after EC withdrawal, providing a rationale for ctDNA-guided EC re-tx.
Methods
BRICKET (NCT06578559) is a proof-of-concept single arm phase II trial where BRAFV600E mut mCRC pts who achieved disease control for ≥ 6 months (mos) with previous EC and then experienced PD underwent centralized ctDNA analysis (GUARDANT360 CDx, Guardant Health) after failure of one intervening EC-free line of therapy. Only pts with BRAFV600E mutation (mut), and no KRAS, NRAS, MAP2K1 mut and MET amplification (ampl) in their ctDNA were eligible. The primary endpoint was objective response rate (ORR). With an ORR of 0.05 for p0 (null hypothesis) and 0.25 for p1 (alternative hypothesis), and 2-sided-α and β errors of 0.05 and 0.20, 16 pts were required and p0 could be rejected if ≥ 3 had an objective response.
Results
Between August 2024 and December 2025, 30 pts underwent molecular screening and ctDNA was successfully detected in 29 cases (96.7%). One or more resistance alterations were found in 11 (37.9%) of them, being KRAS mut (N=17), NRAS mut (N=3) and MET ampl (N=2) the most frequent. In other 2 pts (6.9%), BRAFV600E mut was not detectable. 14 (87.5%) out of 16 enrolled pts had received previous EC without concomitant chemotherapy and 13 (81.3%) were re-treated after the 3rd line. No objective responses were reported. 6 pts (37.5%) had disease stabilization, lasting a median of 2.9 mos (95% CI: 1.0 – not assessable). All pts experienced PD and 11 (68.8%) died, resulting in median PFS and OS of 2.9 (95% CI: 2.0 – 3.4) and 9.1 mos (95% CI: 4.0 – 13.0), respectively. No new safety signals were observed.
Conclusions
EC re-tx did not show signals of activity in BRAFV600E-mutant mCRC pts without common genomic drivers of resistance to EC in their ctDNA. Whether pts treated upfront with chemotherapy plus EC as per current guidelines, potentially less likely to develop genomic resistance, may benefit from ctDNA-guided EC re-tx, could be object of future studies.
[Slide 1]
Background
The Surgery As Needed for Oesophageal cancer (SANO)-trial demonstrated that active surveillance is non-inferior to standard surgery in terms of two-year overall survival in patients with a complete clinical response after neoadjuvant chemoradiotherapy (nCRT). Active surveillance resulted in improved quality of life. Here, we report 5-year outcomes.
Methods
From 2017 to 2021, a multicentre stepped-wedge cluster-randomised non-inferiority trial was conducted. Patients with locally advanced oesophageal cancer who achieved complete clinical response (defined as no tumour detected on endoscopic biopsies, -ultrasound, or PET-CT) underwent active surveillance or standard surgery. Cox regression was used to compare 5-year overall and disease-free survival, and the cumulative incidence of distant metastases was estimated using competing risk analysis.
Results
A total of 309 patients were included, 198 underwent active surveillance and 111 underwent standard surgery. Median follow-up was 76 months (IQR 67–86). Five-year overall survival was not statistically significantly different between active surveillance and standard surgery (50%, 95%CI 34-57 vs. 54%, 95%CI 46-64; HR 1.17, 95%CI 0.77-1.77) with similar results across histologic subtypes. Disease-free survival was not statistically significantly different (HR 1.39, 95% CI 0.94-2.06). The cumulative incidence of distant metastases at five years was significantly higher in the active surveillance group compared to the standard surgery group (46%, 95%CI 39-53 vs. 29%, 95%CI 21-37; P<.01). Overall, 85 of 198 patients (43%) were spared non-beneficial oesophagectomy, including those with sustained complete clinical response at last follow-up or distant metastases detected within six months after nCRT.
Conclusions
Overall survival at 5 years is not statistically significantly different between active surveillance and standard surgery in patients with oesophageal cancer and a complete clinical response after nCRT, despite a higher incidence of distant metastases in the active surveillance group. These findings support active surveillance as a feasible treatment strategy in these patients.
[Slide 1]
MADRID 2026 ESMO congress
MADRID SPAIN 23-27 OCTOBER 2026
Sarcoma SELECTED ABSTRACTS
Presidential Symposium III | 26 October 2026 · 16:30-16:54
LBA9 - Risvutatug Rezetecan (Ris-Rez) versus Gemcitabine and Docetaxel (GD) in Heavily Pretreated Patients (pts) with Relapsed or Refractory (R/R) Osteosarcoma: Primary Results from the Phase 3 ARTEMIS-011 Study
Proffered paper: Sarcoma | 24 October 2026 · 14:45-16:15
LBA89 - Primary Analysis of TANGENT: A Phase 3 Randomised Trial Evaluating the Safety and Efficacy of Emactuzumab in Patients With Tenosynovial Giant Cell Tumours
3715O - A phase 1/2 trial of zolucatetide, a first-in-class direct β-catenin:TCF inhibitor: Updated safety and efficacy in patients with desmoid tumors
3714O - HH2853, an EZH1/2 inhibitor, in patients with epithelioid sarcoma: Promising anti-tumor activity results from the pivotal phase II (HH2853-G101 cohort 2) study
3716O - SELNET 7.2: A phase II trial exploring cirtuvivint in certain translocation-related soft-tissue sarcomas
Rapid oral: Sarcoma | 08:30-10:00
3717RO - Phase 3 peak crossover: Bezuclastinib + sunitinib combination following sunitinib monotherapy in patients with GIST
3718RO - Molecular response (MR) in KIT circulating tumor DNA (ctDNA) from StrateGIST 1: A phase 1/1b study of velzatinib (IDRX-42) in patients (pts) with advanced gastrointestinal stromal tumors (GIST)
3719RO - Final results from the first-in-human phase I trial of NB003, a potent and selective KIT inhibitor, in patients (pts) with advanced gastrointestinal stromal tumors (GIST)
3720RO - Nab-paclitaxel plus pegylated liposomal doxorubicin in advanced or unresectable malignant vascular tumors: Results from a phase II study
3721RO - Quantitative PARP1 H-score as a predictive biomarker for trabectedin plus olaparib combination in advanced soft tissue sarcoma: Exploratory analysis of the TOMAS2 study
3722RO - Trastuzumab deruxtecan in patients with desmoplastic small round cell tumors (DSRCT): A retrospective analysis from the French Sarcoma Group
3723RO - Desmoid tumors (DTs) from the NETSARC+ registry: Tumor characteristics, management strategies, and outcomes in 3457 patients
3724RO - Patient reported outcomes (PROs) with varegacestat versus placebo (PBO) in progressing desmoid tumors: Results from RINGSIDE Part B
3725RO - Lifileucel in patients with undifferentiated pleomorphic sarcoma (UPS) or dedifferentiated liposarcoma (DDLS)
Nieves Martínez Lago · @DraMartinezLago | #ESMO26
[Slide 1]
Background
Arcotatug tavatecan is a novel CLDN18.2-targeted ADC comprising an Fc-silenced antibody designed to reduce on target, off-tumor toxicity and conjugated to an exatecan-derived TOPO I inhibitor payload for selective delivery to tumor cells. Here, we report the prespecified first interim analysis (IA1) of the G-HOPE-001 study.
Methods
Patients (pts) with unresectable or metastatic G/GEJA, CLDN18.2 IHC ≥2+ in ≥75% of tumor cells who had progressed on 2-4 prior regimens were randomized 1:1 to arcotatug tavatecan 6mg/kg Q3W or TPC (irinotecan, paclitaxel or trifluridine/tipiracil) until progression or unacceptable toxicity. Stratification factors were regions, primary tumor site and prior gastrectomy. Primary endpoints were IRRC-assessed PFS per RECIST v1.1 and OS. The prespecified IA1 included the PFS final analysis and an OS futility analysis, with a data cutoff of February 13, 2026.
Results
In IA1, 408 pts from China and Japan (male: 62.0%, median age: 58.0, ECOG PS 1: 71.6%, primary tumor at stomach: 81.6%, primary tumor resection: 43.6%) were randomized to arcotatug tavatecan (N=203) and TPC (N=205) arms. IRRC-assessed median PFS was 5.5 months vs 2.9 months (HR: 0.47 [95% CI: 0.34-0.65], p-value <0.0001). With 34.8% of events, median OS was 9.9 months vs 7.4 months (HR: 0.63 [95% CI: 0.45-0.89]). IRRC-assessed ORR was 23.6% in arcotatug tavatecan and 5.3% in TPC. Grade ≥3 (G3+) TEAEs occurred in 45.8% pts with arcotatug tavatecan vs 57.9% pts with TPC. Common gastrointestinal TEAEs (≥10%) with arcotatug tavatecan vs TPC were nausea (38.9% vs 40.6%), vomiting (22.2% vs 28.4%) and diarrhea (12.8% vs 34.5%). Interstitial lung disease was not observed. TRAEs leading to treatment discontinuation occurred in 1.0% of pts in each arm. No TRAE led to death.
Conclusions
Arcotatug tavatecan demonstrated a statistically significant and clinically meaningful improvement in PFS with a manageable safety profile versus TPC for CLDN18.2+ G/GEJA in the 3L+ setting. OS results will be evaluated at the prespecified IA2.
[Slide 1]
SANO | ESMO 2026 | LBA78
Save the Oesophagus.
But at what cost?
MV Onco
COMPLETE CLINICAL RESPONSE (cCR)
[illustration: oesophagus branching to two strategies]
ACTIVE SURVEILLANCE
OESOPHAGECTOMY
OESOPHAGUS PRESERVED
5-year OS: 50%
5-year OS: 54%
[illustrations: liver, lungs, bone with metastases]
Distant metastases: 46%
Distant metastases: 29%
SIMILAR SURVIVAL.
+17% POINTS DISTANT METASTASES.
Does organ preservation compromise distant disease control?
Association observed; causality not established.
[Slide 2]
SANO | ESMO 2026 | LBA78
Part 1 – Can We Avoid Oesophagectomy After Complete Response?
MV Onco
01 THE CLINICAL QUESTION
• Locally advanced oesophageal cancer.
• Complete clinical response (cCR) after neoadjuvant chemoradiotherapy:
• Must everyone undergo oesophagectomy?
• Or can we monitor and operate only when needed?
02 THE SANO TRIAL
• Multcicentre, cluster-randomised trial.
• N = 309
• Active surveillance: 198 patients
• Standard surgery: 111 patients
• Median follow-up: 76 months
• cCR assessed by endoscopic biopsies, EUS and PET-CT.
03 FIVE-YEAR SURVIVAL
Active Surveillance vs Surgery
• 5-year OS:
50% vs 54%
HR 1.17 (95% CI 0.77–1.77)
No statistically significant difference.
• DFS:
HR 1.39 (95% CI 0.94–2.06)
No statistically significant difference.
No significant difference ≠ Proven equivalence.
04 HOW MANY AVOIDED SURGERY?
43% (85/198)
• Avoided an oesophagectomy classified as non-beneficial.
• Included patients with sustained cCR or early distant metastatic progression.
Organ preservation is feasible in selected patients.
BUT THERE IS A CATCH...
SAME SURVIVAL. MORE METASTASES?
Continued in Part 2.
[Slide 3]
SANO | ESMO 2026 | LBA78
Part 2 – Same Survival. More Metastases?
MV Onco
01 THE DISTANT METASTASIS PARADOX
5-year cumulative incidence:
Active Surveillance vs Surgery
46% vs 29%
+17 percentage points
P < 0.01
Significantly MORE distant metastases with surveillance.
Yet 5-year OS was not significantly different.
02 HOW CAN THIS HAPPEN?
Possible explanations:
• Subsequent treatments may influence survival.
• Longer follow-up may reveal survival differences.
• The study may lack precision to detect an OS difference.
The mechanism remains unproven.
Does residual local disease contribute to distant spread?
An important hypothesis — NOT established.
03 THE ORGAN-PRESERVATION TRADE-OFF
WHAT WE GAIN
• 43% avoided an oesophagectomy classified as non-beneficial.
• Earlier results showed better quality of life.
WHAT CONCERNS US
• Higher distant-metastasis incidence.
• Uncertain long-term oncological equivalence.
Organ preservation ≠ Risk-free surveillance.
04 TAKE-HOME
Active surveillance is a feasible option in carefully selected patients achieving cCR after nCRT.
Requires:
• Expert multidisciplinary assessment.
• Intensive surveillance.
• Timely salvage surgery when indicated.
5-year OS: No significant difference.
Distant metastases: Significantly higher.
THE KEY QUESTION: Are we preserving the oesophagus at the cost of distant disease control?
[Slide 1]
ESMO 2026 / MADRID
REPORTING FROM MADRID
ESMO 2026 / DAY ONE
LIVE CONGRESS NOTES
[MADRID 2026 ESMO congress logo]
MADRID • CONGRESS NOTES
MUSTAFA ÖZDOĞAN
MD · MADRID 2026
FRIDAY 23 OCTOBER MADRID TIME · CEST (UTC+2)
WHAT I'M FOLLOWING TODAY
11:30 OPENING SESSION
The scientific programme begins
13:30 //
ESMO-MCBS
How large must a benefit be to matter?
UPPER GI ORAL ABSTRACTS
KEYNOTE-975 on the agenda
15:15 mRNA VACCINES
Context ahead of Saturday's INTerpath-001 (LBA1)
I'M HERE IN THE HALLS
I'll share the results, absolute gains and clinical implications.
ESMO 2026 • Madrid • 23–27 October 2026 | drozdogan.com
[Slide 1]
ESMO GOOD SCIENCE BETTER MEDICINE BEST PRACTICE
ESMO 2026 · MADRID
GUT ONC LAB
GI ABSTRACTS I'M WATCHING
Oct 23–27 · Times are Madrid local (CEST through Oct 24, CET from Oct 25)
BELOW THE BELT
AZUR-1 LBA87 Sun 25 11:00
Dostarlimab alone in stage II/III MSI-H rectal cancer
This will be positive. Incredibly positive. This is already what I'm doing in clinical practice and is a massive step forward for the 5–10% of rectal cancer patients that are MSI-H. Yay.
IROCAS LBA29 Sun 25 10:15
Adjuvant mFOLFIRINOX vs mFOLFOX6, T4/N2 colon
Important study, and honestly, it is going to predict if US-CIRCULATE will be positive. If this is negative, CIRCULATE will be a nail-biter.
CheckMate 8HW LBA32 Sat 24 15:42
Final OS: nivo/ipi vs nivo vs chemo, MSI-H mCRC
What happens when you do a trial with an agent that essentially cures a disease against another that cures most people? It is a really long damn trial. Excited for the final OS data. Will it be positive? TBD, but I certainly think the magnitude of benefit of dual IO makes it better than single agent, and this data could reinforce that practice.
UNION 3530O Sun 25 11:10
SCRT → camrelizumab + CAPOX, locally advanced rectal
pCR reported at ~40% in 2024, let's see if more people were cured. Some criticism in changing radiation schedule and adding IO compared to standard, but will set the stage for future studies.
EMT2 LBA30 Sun 25 10:25
EPA vs placebo after CRC liver metastasis resection
It's like fish oil but better. File this in the ALASCCA category of "costs nothing, helps people" if positive. ALASCCA + CHALLENGE <3
QTX3034 790RO Sat 24 15:15
KRAS G12D inhibitor + cetuximab ± mFOLFOX6, mCRC
Sick study. Moving us to molecularly driven treatments in earlier line settings for CRC. Where the field MUST move. If this isn't positive I will eat a hat (a small one, preferably organic).
EC + FOLFIRI beyond PD 788RO Sat 24 14:50
Continuing encorafenib + cetuximab past progression, BRAF V600E mCRC
Already doing this in clinical practice with patients who have BRAF+ disease w/o resistance mechanism on ctDNA at progression. Data for its use is HUGELY welcome.
BOT/BAL in the real world
905eP ePoster · 3771P Mon 26 12:00
Botensilimab + balstilimab: refractory MSS mCRC (AGEO) and advanced sarcoma (Spanish EAP)
Gives us a look at Bot Bal in real world. Important data, multiple attempts to use CPI in advanced disease have provided mixed results, what happens when we use stronger agents?
RUNNER-UP
Biweekly TAS-102 + bev LBA31 Sat 24 15:37
Biweekly vs standard schedule, refractory mCRC
Runner up only because Cathy Eng already convincingly showed this is the dosing schedule we should be using. I already use this in clinical practice. Great to randomize but should be positive.
UPPER GI
CLARITY-Gastric01 + G-HOPE-001
LBA7 Sun 25 17:18 · LBA77 Fri 23 13:30
CLDN18.2 ADCs, pretreated gastric/GEJ
The next generation of CLDN18.2 is here. Expect less explosive emesis and improved outcomes.
KEYNOTE-975 2875O Fri 23 13:50
Pembro + definitive chemoRT, esophageal/GEJ
Merck joins the D-FLOT era for patients still receiving definitive chemoRT. After the CROSS/FLOT study the impact of this is going to be less, but still important for patients receiving definitive chemoRT.
HERIZON-GEA-01 LBA79 Fri 23 16:15
Zanidatamab ± tislelizumab, 1L HER2+ GEA
My practice in HER2+ upper GI/GEA has moved to Zani, will be helpful to see the longer-term outcomes here.
SANO LBA78 Fri 23 13:40
Active surveillance vs surgery after nCRT, long-term
People deserve to keep their organs. Our ability to offer this only improves when we layer in tools like ctDNA. Interested in what we can extrapolate to other organ systems (especially for MSI-H).
PANCREAS
RASolute 302 LBA82 Fri 23 14:22
Daraxonrasib subgroups, 2L+ metastatic PDAC
Every subgroup likely benefited. G12V more than others. Maybe there will be another standing ovation? Come for the science, stay for the clapping.
AMPLIFY-7P LBA83 Fri 23 14:32
mKRAS vaccine vs observation, resected PDAC
Vaccine therapies are the next frontier. Merck has pushed them forward in Melanoma where they are an amazing success, very interested in the randomized data here. Even if negative it will be critical data to learn from.
HCC / BILIARY
HARMONi-GI1 LBA8 Sun 25 17:42
Ivonescimab vs durvalumab + GemCis, 1L BTC
PD-1/VEGF emerges in GI. Let's see the benefit. China only.
ACTICCA-1 LBA21 Sat 24 10:25
Adjuvant GemCis vs capecitabine, resected BTC
Might immediately change the standard of care for resected BTC. Worth tuning in for.
Nicholas J. Hornstein, MD, PhD
Full abstracts online Oct 19 · LBAs at presentation
[Slide 1]
ESMO 2026 | Negative Phase 3
KEYNOTE-975
Unresectable oesophagual / GEJ cancer • Definitive chemoradiotherapy ± pembrolizumab • n=703 • 17:30 • Abstract 2875O
Study question
[illustration of oesophagus and stomach with tumour at GEJ]
Does adding pembrolizumab to definitive chemoradiotherapy improve outcomes in unresectable oesophageal/GEJ cancer?
Key results / Efficacy
PD-L1 CPS ≥10
EFS: HR 0,97 (0.77–1.23)
OS: HR 1.00
No meaningful benefit
A clear negative phase 3 result
Safety profile
[skull icon] Grade 5 AEs:
13% vs 10%
[IV bag icon] Discontinued any study drug due to AEs:
34% vs 27%
Higher toxicity with pembrolizumab
Take-home message
Adding pembrolizumab to definitive chemoradiotherapy did not improve EFS or OS, with higher rates of fatal toxicity and treatment discontinuation.
A clean negative, at a cost.
[lightbulb icon] Why does this matter?
Even in phase 3 studies, more therapy is not always better.
The balance between treatment intensification and real clinical benefit must be cafefully considered.
Source: #ESMO26 • Abstract 2875O • KEYNOTE-975 • Presenter: Manish A. Shah
[Slide 1]
KEYNOTE-975
Pembrolizumab added to definitive CRT for esophageal cancer
Locally advanced
Esophageal / GEJ
Not surgical
candidates
n = 703
→ RANDOMIZE
CRT + placebo (n = 354) | Median EFS, CPS >=10* 14.7 mo
CRT + pembro (n = 349) | Median EFS, CPS >=10* 15.2 mo
*EFS in CPS >=10: HR 0.97 (95% CI 0.77-1.23), P = .3994; not statistically significant.
CPS >=10 OS: 35.0 vs 32.2 months; HR 1.00 (0.77-1.30), not formally tested after hierarchy failure.
Shah et al. ESMO 2026, 2875O. Phase III. CRT: FP + 50/60 Gy or FOLFOX + 50 Gy; up to 1 year of IO.
[Slide 1]
ESMO 2026 / MADRID
EVIDENCE NOTES
[Madrid skyline silhouette] [ESMO congress Madrid 2026 logo]
PRESIDENTIAL SYMPOSIUM II / LBA8
25 OCT 2026, SUNDAY
16:30 Madrid | 18:30 Istanbul
HARMONi-GI1
CAN A PD-1/VEGF BISPECIFIC BEAT AN ACTIVE STANDARD IN ADVANCED BILIARY TRACT CANCER?
1L advanced BTC • ivonescimab + chemotherapy vs durvalumab + chemotherapy
[illustration of liver/biliary tract with bispecific antibody icon] PD-1 / VEGF bispecific
01 DISEASE & PATIENT POPULATION
[liver illustration]
• Unresectable locally advanced or metastatic biliary tract cancer
• First-line systemic treatment
• Randomized study in advanced BTC
• BTC population including gallbladder cancer and intra/extrahepatic cholangiocarcinoma subtypes
02 STUDY DESIGN
Phase 3
Randomized / double-blind
n = 682
China / multicentre
Primary endpoint: OS
03 TREATMENT ARMS
Experimental arm
Ivonescimab + chemotherapy
PD-1 / VEGF bispecific
VS
Control arm
Durvalumab + chemotherapy
active immunotherapy standard
04 WHAT WE KNOW NOW
[bar chart icon with rising arrow]
• Primary OS endpoint met at a pre-specified interim analysis
• Clinically meaningful and statistically significant superiority reported
• Key secondary endpoints PFS and ORR were also positive
• Data source: company topline announcement + ESMO programme
✓ OS superiority signal against an active standard.
NOT YET DISCLOSED
[document with question mark icon]
• OS HR and 95% CI
• Median OS / PFS and absolute differences
• Magnitude of ORR and duration of response
• Grade ≥3 toxicity and discontinuation
• Generalisability beyond China
Awaiting full LBA8 presentation.
05 CLINICAL READING
[magnifying glass icon]
Key question: not just whether it is positive, but how large the gain is against an active control — and how far a single-region dataset can be generalised.
Positive PFS/OS signals matter; absolute benefit, toxicity balance and external validity will determine practice impact.
Data status: company topline announcement + ESMO 2026 programme; full presentation and detailed outcomes awaited.
Sources: drozdogan.com • Akeso/Summit topline, 25 Aug 2026 • HARMONi-GI1 (AK112-309) • ESMO 2026 programme
drozdogan.com
[Slide 1]
LBA79 - Zanidatamab (zani) + chemotherapy (CT) ± tislelizumab (TIS) for first-line (1L) HER2-positive (HER2+) advanced/metastatic gastroesophageal adenocarcinoma (mGEA): Second interim analysis (IA) from HERIZON-GEA-01
Speakers Kohei Shitara (Kashiwa, Japan, Chiba)
Lecture Time 16:15 - 16:20
[Abstract button]
Background
In the primary analysis of progression-free survival (PFS) and first IA (IA1) of overall survival (OS) of the phase 3 HERIZON-GEA-01 trial (NCT05152147), zani + CT ± TIS significantly prolonged PFS and, with TIS, provided a significant OS benefit (HR 0.72) vs trastuzumab (tras) + CT (Shitara, et al. NEJM. 2026), supporting the US approval of these regimens in 1L HER2+ mGEA. Here, we present the planned second IA of OS (IA2).
Methods
Patients (pts) with untreated HER2+ mGEA were randomized 1:1:1 to zani (1800 mg [<70 kg]/2400 mg [≥70 kg] IV every 3 weeks [Q3W]) + CT (capecitabine/oxaliplatin or 5-FU/cisplatin) ± TIS (200 mg IV Q3W) or tras + CT. PFS (by blinded independent central review) and OS were primary endpoints. At IA2, formal OS comparisons were tested in sequence: zani + CT vs tras + CT, then zani + CT + TIS vs zani + CT.
Results
914 pts were randomized. With a median follow-up of 35.3 mo (data cutoff: 15 July 2026; 9.4 mo longer than IA1), zani + CT significantly improved OS vs tras + CT (HR 0.76 [95% CI: 0.62–0.93]; P = 0.0088; median OS, 22.9 mo [95% CI: 19.9–27.6] vs 19.6 mo [95% CI: 16.9–22.2]). A 4-mo longer median OS was observed with zani + TIS + CT (27.0 mo [95% CI: 23.7–32.2]) vs zani + CT (HR 0.81 [95% CI: 0.65–1.00]), although the difference was not statistically significant (P = 0.0502). The OS benefit of zani + TIS + CT vs tras + CT observed at IA1 (HR 0.72) was sustained at IA2 with an improved HR (0.65 [95% CI: 0.52–0.80]). Estimated 36-mo OS was 39.8% for zani + CT + TIS, 31.5% for zani + CT, and 22.9% for tras + CT. Median duration of treatment was 46.6 (40.5 for zani) wks with zani + CT + TIS, 31.1 (30.1 for zani) wks with zani + CT, and 30.0 (28.2 for tras) wks with tras + CT. The safety profiles were consistent with IA1.
Conclusions
At IA2, zani + CT led to a statistically significant and clinically meaningful OS improvement vs tras + CT. With longer follow-up, zani + CT + TIS showed improved OS benefit over tras + CT and there was a meaningful trend for OS improvement vs zani + CT. Unchanged safety profiles support the tolerability of prolonged treatment. These results continue to support zani combined with CT ± TIS as a new HER2-directed 1L standard of care in HER2+ mGEA.
[Slide 1]
My picks - CRC and PDAC - #ESMO26
Dr Jose Tapia · Barts Cancer Centre- X: @TapiajC1
MADRID 2026 ESMO congress · MADRID SPAIN 23-27 OCTOBER 2026
COLORECTAL CANCER
LBA32 | CheckMate 8HW | Mature OS data
Mature OS results from Nivolumab plus Ipilimumab vs Nivolumab vs Chemotherapy in MSI-H/dMMR mCRC. Relevant to inform patients. Keen to see updated data on subsequent therapies.
LBA87 | AZUR-1 | Organ preservation
Clinical CR with Dostarlimab monotherapy in dMMR/MSI-H locally advanced rectal cancer (LARC). First results from the global registrational trial. Potential to establish an organ-preserving treatment approach for selected patients.
LBA29 | IROCAS | Adjuvant intensification
RCT Ph3 of adjuvant intensification with mFOLFIRINOX vs mFOLFOX6 in high-risk stage III (T4 and/or N2) colon cancer. Does benefit justify additional toxicity?
788RO | ECLYPse | Beyond progression
Ph2 Encorafenib + Cetuximab (EC) + FOLFIRI beyond PD to EC in BRAF V600E mCRC. Particularly interested in pts who previously had IO. 787RO and 789RO are other interesting strategies in this setting.
790RO | QTX3034 | KRAS G12D in CRC
Preliminary clinical results. An oral G12D-preferring KRAS inhibitor + Cetuximab ± mFOLFOX6 in patients with KRAS G12D-mutated CRC. Data could inform development of targeted strategies.
PANCREATIC CANCER
LBA82 | RASolute 302 | RAS(ON) inhibition
Additional subgroup analyses from the Ph3 RASolute 302 study. Keen to see data on G12 variant subpopulation (G12D, G12V, and G12R), non-colon 12 mut (G14 and Q61) and RAS wild-type.
3137RO | INCB161734 | G12D plus chemo
Ph1 = Safety and efficacy. A novel oral KRAS G12D inhibitor + chemo advanced/metastatic PDAC. Will be interesting to see data on AE grades, interruptions and discontinuations. Are all the KRAS inh the same?
LBA85 | HRS-4642 | Perioperative G12D
Ph2. Perioperative strategy in KRAS-G12Dm PDAC. Non-covalent KRAS G12D inh + chemo ± adebrelimab (anti-PD-L1). Keen on seeing data on downstaging, % surgery/SBAR, and eradication of micrometastatic disease.
LBA83 | AMPLIFY-7P | Adjuvant vaccine
Ph2 RCT. Seven-valent mKRAS-specific lymph node targeted amphiphile immunotherapy vs AS in resected PDAC. Innovative immunotherapy. Does treatment intensification in selected population translate into clinical benefit?
Abstract titles as listed in the ESMO 2026 programme. Selection reflects titles only; data not yet reviewed.
[Slide 1]
October 22, 2026
Myriad Genetics Releases New MONSTAR-SCREEN-3 Data Demonstrating the Potential of Ultra-Sensitive MRD Detection in Colorectal and Pancreatic Cancers
Myriad genetics
[Slide 1]
ESMO26 TOP TEN BY ONCOALERT
GI CANCER
OncoAlert360 Oncology For Colleagues By Colleagues
LBA87 AZUR-1: CLINICAL COMPLETE RESPONSE WITH DOSTARLIMAB MONOTHERAPY IN DMMR/MSI-H LOCALLY ADVANCED RECTAL CANCER: FIRST RESULTS FROM THE GLOBAL REGISTRATIONAL TRIAL
LBA32 CHECKMATE 8HW: FINAL OVERALL SURVIVAL RESULTS: NIVOLUMAB PLUS IPILIMUMAB VERSUS NIVOLUMAB OR CHEMOTHERAPY IN MSI-H/DMMR METASTATIC COLORECTAL CANCER
789RO TRIDENTE: RECHALLENGE WITH ENCORAFENIB, BINIMETINIB AND CETUXIMAB IN BRAF V600E-MUTANT METASTATIC COLORECTAL CANCER: PHASE II STUDY
LBA79 HERIZON-GEA-01: ZANIDATAMAB + CHEMOTHERAPY ± TISLELIZUMAB FOR FIRST-LINE HER2-POSITIVE ADVANCED/METASTATIC GASTROESOPHAGEAL ADENOCARCINOMA: SECOND INTERIM ANALYSIS
2875O KEYNOTE-975: PEMBROLIZUMAB OR PLACEBO PLUS CONCURRENT DEFINITIVE CHEMORADIOTHERAPY IN ESOPHAGEAL AND GASTROESOPHAGEAL JUNCTION CANCER: PHASE 3 RANDOMIZED STUDY
2877RO GERCOR-GONO DEWI: WATCH-AND-WAIT STRATEGY FOR DOSTARLIMAB IN LOCALIZED DMMR/MSI-H GASTROESOPHAGEAL ADENOCARCINOMA: FIRST INTERIM ANALYSIS OF THE PHASE II STUDY
LBA77 G-HOPE-001: ARCOTATUG TAVATECAN (IBI343/TAK-921) VERSUS TREATMENT OF PHYSICIAN'S CHOICE IN PREVIOUSLY TREATED ADVANCED GASTRIC OR GEJ ADENOCARCINOMA: FIRST INTERIM ANALYSIS OF THE RANDOMIZED PHASE 3 STUDY
LBA8 HARMONI-GI1: IVONESCIMAB PLUS CHEMOTHERAPY VERSUS DURVALUMAB PLUS CHEMOTHERAPY AS FIRST-LINE TREATMENT FOR ADVANCED BILIARY TRACT CANCER: RANDOMIZED, DOUBLE-BLIND, PHASE 3 TRIAL
LBA21 ACTICCA-1: ADJUVANT GEMCITABINE PLUS CISPLATIN VERSUS CAPECITABINE IN RESECTED BILIARY TRACT CANCER: PHASE 3 TRIAL
LBA22 OPTIMUM: MAINTENANCE OLAPARIB WITH OR WITHOUT DURVALUMAB IN DDR GENE-MUTATED ADVANCED BILIARY TRACT CANCER: RANDOMIZED PHASE 2 STUDY
LBA82 RASOLUTE 302: DARAXONRASIB, A RAS(ON) MULTI-SELECTIVE INHIBITOR, VS CHEMOTHERAPY IN PREVIOUSLY TREATED METASTATIC PANCREATIC ADENOCARCINOMA: ADDITIONAL SUBGROUP ANALYSES FROM THE PHASE 3 STUDY
LBA83 AMPLIFY-7P: SEVEN-VALENT MKRAS-SPECIFIC LYMPH NODE TARGETED AMPHIPHILE IMMUNOTHERAPY VERSUS OBSERVATION IN RESECTED PANCREATIC DUCTAL ADENOCARCINOMA: RANDOMIZED PHASE 2 STUDY
Senior Faculty
Dr Morgan Clin Onc | Dr. Eng Med Onc | Dr Westphalen Med Onc | Dr O'Kane Med Onc
Faculty
Dr Akkus Med Onc | Dr Hornstein Med Onc | Dr Pacheco Med Onc
[faculty headshots]
WWW.ONCOALERT360.COM
ESMO 2026: 10 GU Clinical Trials I'm Watching
Presidential + selected oral / proffered presentations
Clinical trials only - translational work excluded.
PRESIDENTIAL (2 PRESENTATIONS)
1. VOLGA - Perioperative durvalumab with or without tremelimumab plus neoadjuvant enfortumab vedotin in muscle-invasive bladder cancer | Bladder | Presenter: Thomas B. Powles
2. DASL-HiCaP (ANZUP1801) - Darolutamide with ADT and definitive or salvage locoregional radiation therapy for localized, very high-risk prostate cancer | Prostate | Presenter: Tamim Niazi
SELECTED ORAL / PROFFERED (8 PRESENTATIONS)
3. LITESPARK-012 - First-line pembrolizumab + lenvatinib + belzutifan or MK-1308A + lenvatinib in advanced RCC | Kidney | Presenter: Toni K. Choueiri
4. LITESPARK-011 - Final analysis: belzutifan + lenvatinib versus cabozantinib after anti-PD-(L)1 therapy in advanced RCC | Kidney | Presenter: Daniel Y. Heng
5. KEYNOTE-564 - Final protocol-prespecified analysis of adjuvant pembrolizumab versus placebo in clear-cell RCC | Kidney | Presenter: Toni K. Choueiri
6. SWOG S2200 - Cabozantinib with or without atezolizumab in metastatic papillary RCC | Kidney | Presenter: Benjamin L. Maughan
7. KEYNOTE-866 - Perioperative pembrolizumab or placebo plus neoadjuvant cisplatin/gemcitabine in muscle-invasive bladder cancer | Bladder | Presenter: Jens Bedke
8. Phase 3 perioperative nivolumab study - Neoadjuvant chemotherapy alone versus chemotherapy + nivolumab followed by adjuvant nivolumab in muscle-invasive bladder cancer | Bladder | Presenter: Andrea Necchi
9. PEACE-1 - Long-term overall survival with abiraterone acetate + prednisone in de novo metastatic castration-sensitive prostate cancer | Prostate | Presenter: Karim Fizazi
10. POTOMAC - Durvalumab in combination with BCG induction and maintenance for BCG-naive, high-risk non-muscle-invasive bladder cancer | Bladder | Presenter: Maria De Santis
Curated from ESMO 2026 presidential, oral and proffered GU sessions.
ESMO 2026, Madrid, 23-27 October 2026
@DrChoueiri
[Slide 1]
Proffered Paper session
4735O - Perioperative pembrolizumab (pembro) or placebo (pbo) + neoadjuvant cisplatin (cis) and gemcitabine (gem) in participants (pts) with muscle-invasive bladder cancer (MIBC): the double-blind, phase 3 KEYNOTE-866 study
Speakers Jens Bedke (Stuttgart, Germany)
Lecture Time 13:30 - 13:40
Proffered Paper session
4736O - Results from a phase 3 trial of neoadjuvant (neoadj) chemotherapy alone vs in combination with nivolumab followed by postsurgical adjuvant nivolumab in patients (pts) with muscle-invasive bladder cancer (MIBC)
Speakers Andrea Necchi (Milan, Italy)
Lecture Time 13:40 - 13:50
Proffered Paper session
4742O - Sacituzumab Govitecan (SG) Combined With Enfortumab Vedotin (EV) and Zimberelimab (ZIM) in Treatment-Naive Metastatic Urothelial Cancer (mUC): Interim Results From Phase 1b TROPHY-U-01 Cohort 7
Speakers Randy Sweis (Chicago, United States of America)
Lecture Time 13:50 - 14:00
Proffered Paper session
Invited Discussant 4735O, 4736O and 4742O
Speakers Robert Jones (Bearsden, United Kingdom)
Lecture Time 14:00 - 14:12
[Slide 2]
Proffered Paper session
4733O - Perioperative pembrolizumab (pembro) or enfortumab vedotin (EV) plus pembro in pts with muscle-invasive bladder cancer (MIBC) who are cisplatin-ineligible: ad hoc analysis from KEYNOTE-905
Speakers Anders Ullén (Stockholm, Sweden)
Lecture Time 14:22 - 14:32
Proffered Paper session
4734O - ctDNA analysis of the Phase 3 KEYNOTE-B15 trial: neoadjuvant and adjuvant (neoadj-adj) enfortumab vedotin (EV) + pembrolizumab (pembro) for participants (pts) with muscle-invasive bladder cancer (MIBC) who are eligible for cisplatin
Speakers Jonathan A. Chatzkel (Tampa, United States of America)
Lecture Time 14:32 - 14:42
Proffered Paper session
Invited Discussant 4733O and 4734O
Speakers Min Yuen Teo (New York, United States of America, NY)
Lecture Time 14:42 - 14:52
Proffered Paper session
Q&A and discussion
Lecture Time 14:52 - 15:00
[Slide 3]
Rapid Oral session
4739RO - Sacituzumab Tirumotecan (Sac-TMT) + Pembrolizumab (Pembro) for Locally Advanced or Metastatic Urothelial Carcinoma (la/mUC): Results From a Phase 2 Study (2870-002/SKB264-II-06)
Speakers Xiaojie Bian (Shanghai, China)
Lecture Time 10:45 - 10:50
Rapid Oral session
4740RO - Enfortumab Vedotin (EV) With or Without Pembrolizumab (P) as First-Line (1L) Treatment for Cisplatin (cis)-Ineligible Locally Advanced Or Metastatic Urothelial Carcinoma (la/mUC): Long-Term Follow-up Analysis from EV-103 Cohorts DE/A and K
Speakers Jose Pablo Maroto Rey (Barcelona, Spain)
Lecture Time 10:50 - 10:55
Rapid Oral session
4749RO - Neoadjuvant Tislelizumab plus Disitamab Vedotin for UTUC: Mid-term Results of the Phase II WUTSUP-02 Trial
Speakers Tiancheng Liu (Chengdu, China)
Lecture Time 10:55 - 11:00
Rapid Oral session
Invited Discussant 4739RO, 4740RO and 4749RO
Speakers Britt B. Suelmann (Utrecht, Netherlands)
Lecture Time 11:00 - 11:15
[Slide 1]
Proffered Paper session
3588O - Phase 1 results of XmAb819, a novel ENPP3 x CD3 bispecific, in advanced clear cell renal cell carcinoma (ccRCC)
Speakers Sumanta K. Pal (Duarte, United States of America)
Lecture Time 09:22 - 09:32
Proffered Paper session
3592O - Efficacy and Safety of AK112 (Ivonescimab), a PD-1/VEGF Bispecific Antibody, as First-Line Treatment for Patients with IMDC Favorable-Risk Advanced Renal Cell Carcinoma (aRCC): Results from a Phase Ib/II Study
Speakers Jun Guo (Beijing, China)
Lecture Time 09:32 - 09:42
Proffered Paper session
Invited Discussant 3588O and 3592O
Speakers Manuela Schmidinger (Vienna, Austria)
Lecture Time 09:42 - 09:52
Proffered Paper session
Q&A and discussion
Lecture Time 09:52 - 10:00
[Slide 2]
Proffered Paper session
3586O - First-line pembrolizumab + lenvatinib + belzutifan or MK-1308A + lenvatinib in advanced RCC: randomized open-label phase 3 LITESPARK-012 study
Speakers Toni K. Choueiri (Boston, United States of America)
Lecture Time 08:30 - 08:40
Proffered Paper session
3587O - Final analysis of the phase 3 LITESPARK-011 study: belzutifan (bel) plus lenvatinib (len) versus cabozantinib (cabo) for advanced renal cell carcinoma (RCC) after anti–PD-(L)1 therapy
Speakers Daniel Y. Heng (Calgary, Canada, OH)
Lecture Time 08:40 - 08:50
Proffered Paper session
LBA88 - PErioperative PEmbrolizumab (P) plus metastasis-directed therapy (MDT) versus MDT alone in patients (pts) with oligometastatic renal cell carcinoma (omRCC): the randomized phase II PE-PE trial.
Speakers Roberto Iacovelli (Rome, Italy)
Lecture Time 08:50 - 09:00
[Slide 3]
14:01 5G
Rapid Oral session
Time 14:45 - 16:15
Rapid Oral session
3589RO - Final protocol-prespecified analysis of the phase 3 KEYNOTE-564 trial of adjuvant pembrolizumab versus placebo in clear cell renal cell carcinoma (ccRCC)
Speakers Toni K. Choueiri (Boston, United States of America)
Lecture Time 14:45 - 14:50
Rapid Oral session
3590RO - Patient reported outcomes in resected renal cell carcinoma: adjuvant durvalumab versus active monitoring in the RAMPART trial
Speakers Sophie Merrick (London, United Kingdom)
Lecture Time 14:50 - 14:55
Rapid Oral session
3604RO - Diagnostic and Staging Performance of CAIX-Targeted [68Ga]Ga-DPI-4452 PET/CT in Clear Cell Renal Cell Carcinoma: A Prospective Trial
Speakers Liangyou Gu (Beijing, China)
Lecture Time 14:55 - 15:00
Rapid Oral session
Invited Discussant 3589RO, 3590RO and 3604RO
Speakers Camillo Guglielmo Porta (Bari, Italy)
Lecture Time 15:00 - 15:12
Rapid Oral session [partially clipped at bottom]
Close Session Details
cslide.ctimeetingtech.com — Private
[Slide 1]
[Photo: speaker at a lectern (badge reads 'URO-ONKO FORUM 2026' — partly legible) presenting a slide; four panellists seated]
Cisplatin eligible
[blue, top — trial name not printed]: GC x 4 | Radical Cystectomy and PLND | Observation ; GC + Durva x 4 | Radical Cystectomy and PLND | Durva x 8 [red check mark]
KN-866 NCT03924856: GC x 4 | Radical Cystectomy and PLND | Observation ; GC + Pembro x 4 | Radical Cystectomy and PLND | Pembro x 13
ENERGIZE NCT03661320: GC x 4 | Radical Cystectomy and PLND | Observation ; GC + Nivo x 4 | Radical Cystectomy and PLND | Nivo x [number clipped]
[red box around KN-866 and ENERGIZE rows]
[orange, bottom — trial name not printed]: EV + Pembro x 4 | Radical Cystectomy and PLND | EV x 5 + Pembro x 13 ; GC x 4 | Radical Cystectomy and PLND | Observation [red check mark]
Cisplatin ineligible
KN-905/EV-303 NCT03924895 [red check mark]: EV + Pembro x 3 | Radical Cystectomy and PLND | EV x 6 + Pembro x 14 ; No preop therapy | Radical Cystectomy and PLND | Observation
Volga NCT04960709 [red box]: Durva + EV x 3 | Radical Cystectomy and PLND | Durva x 9 ; Durva/Treme + EV x 3 | Radical Cystectomy and PLND | Treme x 1 + Durva x 9 ; No preop therapy | Radical Cystectomy and PLND | Per physician choice
Modified from Rosenberg [J.] Presented at ESMO 2025
[... c]ombination with pembro is not registered by EMA f[or the] treatment of cis[platin-eligible] MIBC patients. [bottom line partly obscured by panellists]
[Slide 1]
Perioperative MIBC Trials: Chemo/IO and ADC/IO Approaches
Cis-Eligible
Niagara (reported 2024) FDA approval March 2025 EU approval July 2025
GC x 4 | Radical Cystectomy and PLND | Observation
GC + Durva x 4 | Radical Cystectomy and PLND | Durva x 8
KN-866
GC x 4 | Radical Cystectomy and PLND | Observation
GC + Pembro x 4 | Radical Cystectomy and PLND | Pembro x 13
ENERGIZE
GC x 4 | Radical Cystectomy and PLND | Observation
GC + Nivo x 4 | Radical Cystectomy and PLND | Nivo x 9
EV-304/KN-B15 (reported: Feb 2026)
EV + Pembro x 4 | Radical Cystectomy and PLND | EV x 5 + Pembro x 13
GC x 4 | Radical Cystectomy and PLND | Observation
Cis-Ineligible
EV-303/KN-905 (reported 2025; FDA approval Nov 2025)
EV + Pembro x 3 | Radical Cystectomy and PLND | EV x 6 + Pembro x 14
No preop therapy | Radical Cystectomy and PLND | Observation
VOLGA
Durva + EV x 3 | Radical Cystectomy and PLND | Durva x 9
Durva/Treme + EV x 3 | Radical Cystectomy and PLND | Treme x 1 + Durva x 9
No preop therapy | Radical Cystectomy and PLND | Per physician choice
[Slide 1]
Merck
European Commission Approves KEYTRUDA® (pembrolizumab) Plus Padcev® (enfortumab vedotin-ejfv) as Perioperative Treatment for Adults With Resectable Muscle-Invasive Bladder Cancer (MIBC) - Merck.com
[Slide 1]
ESMO CONGRESS 2026 · MADRID · 23–27 OCTOBER | #ESMO2026
GU Oncology: 11 Trials I'm Watching
Presidential, late-breaking and proffered papers — sorted by tumour entity
PROSTATE 3 trials
1 DASL-HiCaP (ANZUP1801) [PRESIDENTIAL] — Darolutamide + ADT with definitive or salvage locoregional RT in localised, very high-risk prostate cancer. Presenter: Tamim Niazi
2 PROTEUS substudy [LBA 53] — Perioperative apalutamide + ADT around radical prostatectomy in high-risk localised disease. Presenter: Alberto Briganti · Sat 10:15, Proffered Paper
3 PEACE-1 — Long-term overall survival with abiraterone + prednisone in de novo metastatic castration-sensitive prostate cancer. Presenter: Karim Fizazi
"PROTEUS substudy (LBA 53) also a potential practice changer." — Prof. Boris Hadaschik, comment on the GU picks
BLADDER 4 trials
4 VOLGA [PRESIDENTIAL] — Perioperative durvalumab ± tremelimumab + neoadjuvant enfortumab vedotin in muscle-invasive bladder cancer. Presenter: Thomas B. Powles
5 KEYNOTE-866 — Perioperative pembrolizumab or placebo + neoadjuvant cisplatin/gemcitabine in MIBC. Presenter: Jens Bedke
6 Perioperative nivolumab (Ph 3) — Neoadjuvant chemotherapy alone vs chemo + nivolumab, followed by adjuvant nivolumab, in MIBC. Presenter: Andrea Necchi
7 POTOMAC — Durvalumab + BCG induction and maintenance in BCG-naïve, high-risk NMIBC. Presenter: Maria De Santis
KIDNEY 4 trials
8 LITESPARK-012 — First-line pembrolizumab + lenvatinib + belzutifan or MK-1308A + lenvatinib in advanced RCC. Presenter: Toni K. Choueiri
9 LITESPARK-011 — Final analysis: belzutifan + lenvatinib vs cabozantinib after anti-PD-(L)1 in advanced RCC. Presenter: Daniel Y. Heng
10 KEYNOTE-564 — Final protocol-prespecified analysis of adjuvant pembrolizumab vs placebo in clear-cell RCC. Presenter: Toni K. Choueiri
11 SWOG S2200 — Cabozantinib ± atezolizumab in metastatic papillary RCC. Presenter: Benjamin L. Maughan
Prof. Dr. Axel S. Merseburger
Department of Urology · UKSH Campus Lübeck
Selection builds on Toni Choueiri's GU picks + PROTEUS added · clinical trials only
[Slide 1]
available at www.sciencedirect.com
journal homepage: euoncology.europeanurology.com
eau European Association of Urology
[EUROPEAN UROLOGY ONCOLOGY journal cover thumbnail]
Clinical Outcomes of Bladder-sparing Management Versus Early Radical Cystectomy in cT1 Micropapillary Bladder Cancer: A Systematic Review and Meta-analysis
Sagar R. Patel a, Mikael Rauf a, Yimin Geng b, David Hinojosa-Gonzalez c, Joseph B. Black a, Taeweon Lee a, Amanda A. Myers d, Charles Guo e, Roger Li f, Joshua J. Meeks g, Piyush Agarwal h, Stephen Williams i, Omar Alhalabi j, Andrea Necchi k, Laura S. Mertens l, Paolo Gontero m, Neema Navai a, Ashish M. Kamat a,*
[Slide 1]
PERIOPERATIVE IMMUNOTHERAPY IN MIBC
Cross-trial comparison | Phase III
Study populations were not identical; cross-trial comparisons are descriptive, not head-to-head.
NIAGARA (Durvalumab)
N = 1,063
Durvalumab arm: 533 | Control arm: 530
INCLUSION CRITERIA
• Adults; resectable MIBC cT2–T4a, N0/1, M0
• Urothelial or mixed transitional histology
• Candidate for radical cystectomy
• ECOG 0–1
• CrCl ≥40 mL/min
• No prior systemic chemotherapy/immunotherapy for MIBC
TREATMENT ARMS
ARM A (n = 533): Durvalumab + gemcitabine/cisplatin × 4 cycles → radical cystectomy → adjuvant durvalumab × 8 cycles
ARM B (n = 530): Gemcitabine/cisplatin × 4 cycles → radical cystectomy; no adjuvant treatment
KEY RESULTS
Pathological complete response (pCR)
33.8% vs 25.8%
(formal analysis; not statistically significant)
Exploratory later reanalysis: 37.3% vs 27.5%
Event-free survival (EFS)
HR 0.68
(95% CI 0.56–0.82); P < 0.001
24-month EFS: 67.8% vs 59.8%
Overall survival (OS)
HR 0.75
(95% CI 0.59–0.93); P = 0.0106
24-month OS: 82.2% vs 75.2%
KEYNOTE-866 (Pembrolizumab)
N = 907
Pembrolizumab arm: 453 | Control arm: 454
INCLUSION CRITERIA
• Adults; MIBC T2–T4aN0M0 or T1–T4aN1M0
• ≥50% urothelial histology
• Clinically non-metastatic
• Eligible for radical cystectomy + pelvic lymph-node dissection
• ECOG 0–1
• Adequate organ function
• Cisplatin eligible
• No prior systemic therapy for MIBC
TREATMENT ARMS
ARM A (n = 453): Pembrolizumab + gemcitabine/cisplatin × 4 cycles → surgery → adjuvant pembrolizumab × 13 cycles
ARM B (n = 454): Placebo + gemcitabine/cisplatin × 4 cycles → surgery → adjuvant placebo × 13 cycles
KEY RESULTS
Pathological complete response (pCR)
44.4% vs 35.8%
(estimated difference 8.9 points; 95% CI 2.5–15.1)
Event-free survival (EFS)
HR 0.88
(95% CI 0.71–1.10); P = 0.1366
Median EFS: 74.1 mo vs not reached (NR)
Overall survival (OS)
HR 1.00
(95% CI 0.79–1.27)
Not formally tested in this analysis
CA017-078 (Nivolumab)
N = 653
Nivolumab arm: 325 | Control arm: 328
INCLUSION CRITERIA
• Adults with previously untreated resectable MIBC
• Eligible for radical cystectomy and agreed to surgery
• ECOG 0–1
• No clinically significant node-positive or metastatic disease
• No prior systemic therapy or radiotherapy for bladder cancer
• Note: trial protocol included multiple arms overall, but the displayed abstract compares the nivolumab + GC arm with GC control.
TREATMENT ARMS
ARM A (n = 325): Nivolumab + gemcitabine/cisplatin × 4 cycles → surgery → adjuvant nivolumab × 9 cycles
ARM B (n = 328): Gemcitabine/cisplatin × 4 cycles → surgery; no adjuvant nivolumab in control arm
KEY RESULTS
Pathological complete response (pCR)
39.1% vs 29.6%
Event-free survival (EFS)
HR 0.94
(95.74% CI 0.71–1.25); P = 0.67
Median EFS: not reached (NR) vs 67.6 mo
Overall survival (OS)
HR 0.88
(95% CI 0.64–1.21)
Immature
Primary endpoints not statistically significant
KEY TAKEAWAY
Similar ~9–10 percentage-point pCR gains; only NIAGARA demonstrated statistically significant EFS and OS benefit in the reported analysis.
GC = gemcitabine/cisplatin. Eligibility criteria are concise summaries, not full protocols. Arm order is experimental vs control. [footer partially cut off]
[Slide 1]
Perioperative IMFINZI® (durvalumab) plus neoadjuvant enfortumab vedotin granted Priority Review in the US for patients with muscle-invasive bladder cancer
[Slide 1]
MADRID 2026 ESMO
Liquid Biopsy oral presentations selection at #ESMO26
[X] @isliquidbiopsy @RobertoBoreaMD [LinkedIn] InternationalSocietyOfLiquidBiopsy
ISLB INTERNATIONAL SOCIETY OF LIQUID BIOPSY
Abstract | Tumor Type | Title | Presenter | Location | Day&Time
2219RO | mCSPC | Utility of ctDNA tumor fraction (TF) as a prognostic biomarker in TALAPRO-3: phase 3 study of talazoparib (TALA) + enzalutamide (ENZA) vs placebo (PBO) + ENZA in patients (pts) with homologous recombination repair (HRR) gene-mutated metastatic castration-sensitive prostate cancer (mCSPC) | Arun Azad (Australia) | Bilbao Auditorium Hall 3 | Fri, 23.10.26 14:02 - 14:07
4734O | Bladder Cancer | ctDNA analysis of the Phase 3 KEYNOTE-B15 trial: neoadjuvant and adjuvant (neoadj-adj) enfortumab vedotin (EV) + pembrolizumab (pembro) for participants (pts) with muscle-invasive bladder cancer (MIBC) who are eligible for cisplatin | Jonathan Chatzkel (USA) | Barcelona Auditorium Hall 9 | Fri, 23.10.26 14:32 - 14:42
540RO | TNBC | Ultrasensitive monitoring of early ctDNA dynamics during neoadjuvant treatment in early-stage triple-negative breast cancer: Pre-interim results from the B-STRONGER-I study | Carlos Barcenas (USA) | Alicante Auditorium Hall 6 | Fri, 23.10.26 16:47 - 16:52
LBA73 | NSCLC | PACE-LUNG: A multicenter, single-arm, phase II clinical trial evaluating the efficacy of additional chemotherapy for patients with EGFRm NSCLC with the continued presence of plasma ctDNA EGFRm at week 3 after start of osimertinib first-line treatment (AIO-TRK-0422/ass) | Martin Sebastian (Germany) | Almeria Auditorium Hall 9 | Sat, 24.10.26 08:30 - 08:35
2719RO | NSCLC | FLAURA2: Analysis of on-treatment plasma EGFRm dynamics and associated clinical outcomes in patients (pts) with EGFRm advanced NSCLC treated with first-line (1L) osimertinib (osi) ± platinum-pemetrexed (plat-pem) | David Planchard (France) | Almeria Auditorium Hall 9 | Sat, 24.10.26 08:35 - 08:40
2636RO | NSCLC | Characterizing resistance mechanisms and predictors of early progression and long-term response to lorlatinib: Circulating tumor DNA (ctDNA) analyses from the CROWN study | Ben Solomon (Australia) | Almeria Auditorium Hall 9 | Sat, 24.10.26 09:05 - 09:10
787RO | mCRC | Circulating tumor DNA (ctDNA)-guided re-treatment (re-tx) with encorafenib and cetuximab (EC) in patients (pts) with chemorefractory BRAFV600E mutated metastatic colorectal cancer (mCRC): The proof-of-concept single arm phase II BRICKET trial by GONO | Marco Maria Germani (Italy) | Alicante Auditorium Hall 6 | Sat, 24.10.26 14:45 - 14:50
LBA36 | Endometrial Cancer | Clinical utility of circulating tumor DNA (ctDNA) for participants with resected, high-risk dMMR endometrial cancer (EC) receiving adjuvant treatment: Results from the ENGOT-en11/GOG-3053/KEYNOTE-B21 study | Lubomir Bodnar (Poland) | Barcelona Auditorium Hall 9 | Sat, 24.10.26 14:55 - 15:05
4244RO | NSCLC | NeoCOAST-2: Association of ctDNA clearance with clinical outcomes in a global platform phase 2 perioperative trial | Tina Cascone (USA) | Leon Auditorium Hall 4 | Sun, 25.10.26 08:30 - 08:35
LBA59 | CSCC | C-POST phase 3 trial of adjuvant (adj) cemiplimab (cemi) vs placebo (pbo) for high-risk cutaneous squamous cell carcinoma (CSCC): Updated overall survival (OS) and outcomes from circulating tumour DNA (ctDNA) analyses | Danny Rischin (Australia) | Granada Auditorium Hall 4 | Sun, 25.10.26 10:42 - 10:47
LBA94 | NSCLC | Error-corrected plasma whole-genome sequencing for personalised and tumour-agnostic minimal residual disease detection in TRACERx | Jonathan Wan (UK) | Cordoba Auditorium Hall 4 | Sun, 25.10.26 14:45 - 14:55
LBA35 | Lung Cancer | Tumor intrinsic and extrinsic origins of circulating genomic and proteomic biomarkers for early detection of lung cancer | Victor Velculescu (USA) | Granada Auditorium Hall 4 | Sun, 25.10.26 14:45 - 14:55
1536RO | HNSCC | ctDNA analysis of the phase 3 KEYNOTE-412 trial: Pembrolizumab (pembro) or placebo (pbo) + concurrent chemoradiotherapy (CRT) for locally advanced head and neck squamous cell carcinoma (LA HNSCC) | Jean-Pascal Machiels (Belgium) | Madrid Auditorium Hall 4 | Sun, 25.10.26 14:50 - 14:55
4236O | CRC | Clinical significance of ultrasensitive ctDNA detection for molecular residual disease assessment in resectable colorectal cancer in MONSTAR-SCREEN-3 | Yuichiro Tsukada (Japan) | Cordoba Auditorium Hall 4 | Sun, 25.10.26 14:55 - 15:05
LBA62 | NSCLC | ctDNA clearance (CL) during neoadjuvant treatment (neoadj Tx) and its association with outcomes in patients (pts) with resectable/borderline resectable stage IIB-IIIB NSCLC from MDT-BRIDGE | Jonathan Spicer (Canada) | Burgos Auditorium Hall 3 | Mon, 26.10.26 10:35 - 10:40
1769RO | Breast Cancer | CTC characterization with the DETECT CTC score predicts therapy response in triple-positive aBC: Translational results of the phase III DETECT V study | Kerstin Pfister (Germany) | Alicante Auditorium Hall 6 | Mon, 26.10.26 11:17 - 11:22
1151RO | Multi-cancer | Efficiency and safety of cancer signal origin (CSO)-guided diagnostic workups following multi-cancer early detection (MCED) testing: Results from PATHFINDER 2 (PF2) | Dax Kurbegov (USA) | Salamanca Auditorium Hall 10 | Mon, 26.10.26 15:17 - 15:22
[Slide 1]
Event-free survival probability
HR 1.33 (95% CI 0.87–2.03)
Log-rank p=0.181
Time (months)
Legend: EV + pembrolizumab | Pembrolizumab
Number at risk
P: 155, 135, 126, 120, 115, 110, 104, 102
EVP: 170, 140, 116, 56, 56, 42, 35, 3
Time (months) [0, 6, 12, 18, 24, 30, 36, 42]
[Survival data captured as a table — no point estimates read from the curve]
Endpoint: Event-free survival (reconstructed IPD indirect comparison)
EV + pembrolizumab (EVP) | 170 | not printed
Pembrolizumab (P) | 155 | not printed
HR: 1.33
HR CI: 0.87–2.03
P: Log-rank p=0.181
Note: n taken from the number-at-risk row at time 0. Reference arm for the HR is not stated on the figure.
[Slide 2]
The Uromigos™
Prostate Cancer.
Who benefits from
treatment intensification?
High-risk prostate cancer isn't one uniform patient population. Identifying who needs additional systemic treatment remains a central question.
DASL-HiCaP
New evidence on adding darolutamide in very high-risk localized disease.
PROTEUS
A subgroup analysis comparing intensified treatment around surgery with prostatectomy alone.
PEACE-1
Long-term survival findings that may help clarify the role of prostate-directed radiotherapy in metastatic disease.
Key theme:
Patient selection may be just as important as the treatment being added.
[prostate anatomy illustration]
[Slide 3]
The Uromigos™
Kidney Cancer.
Is there a future for
triplet therapy?
Triplet therapy continues to evolve in advanced kidney cancer. New data at ESMO 2026 may help define which patients benefit most and how to manage associated toxicity.
LITESPARK-012
First-line belzutifan + pembrolizumab + lenvatinib in advanced clear cell RCC.
Treatment sequences
How emerging data may inform optimal sequencing and patient selection.
Toxicity management
Balancing efficacy with tolerability remains a key consideration.
Key theme:
Better patient selection and thoughtful toxicity management will be essential.
[kidney anatomy illustration]
[Slide 4]
The Uromigos™
Bladder Cancer.
How much treatment
is enough?
At ESMO 2026, new data will help inform how to optimize perioperative strategies in bladder cancer, including the right intensity and sequencing of treatment.
VOLGA
Perioperative durvalumab + chemotherapy in muscle-invasive bladder cancer.
KEYNOTE-905
Perioperative pembrolizumab + chemotherapy and long-term outcomes.
Treatment decisions
Emerging data may help refine who benefits from perioperative therapy and how to balance efficacy with toxicity.
Key theme:
Finding the right patients — and the right amount of treatment — remains critical.
[bladder anatomy illustration]
[Slide 1]
ESMO 2026
TOP 10 GU CANCER TRIALS TO WATCH
Pre-congress watchlist | Grouped by GU subspecialty
23-27 October 2026 | Madrid, Spain
PROSTATE CANCER
1 DASL-HiCaP - Darolutamide + ADT + RT in very high-risk localized prostate cancer
2 PROTEUS - Perioperative apalutamide + ADT in high-risk localized prostate cancer
3 CAPItello-281 - Updated OS with capivasertib + abiraterone in PTEN-deficient mHSPC
4 PEACE-1 - Long-term OS benefit with abiraterone in de novo mCSPC
BLADDER / UROTHELIAL CANCER
5 VOLGA - Perioperative durvalumab ± tremelimumab with neoadjuvant enfortumab vedotin in cisplatin-ineligible MIBC
6 KEYNOTE-866 - Perioperative pembrolizumab + gem/cis in cisplatin-eligible MIBC
7 ENERGIZE / CA017-078 - Perioperative nivolumab + cisplatin-based chemotherapy in MIBC
KIDNEY CANCER (RCC)
8 LITESPARK-011 - Belzutifan + lenvatinib vs cabozantinib after prior PD-(L)1 in advanced RCC
9 LITESPARK-012 - Belzutifan- or quavonlimab-containing first-line regimens with pembrolizumab + lenvatinib in advanced RCC
10 KEYNOTE-564 - Final prespecified analysis of adjuvant pembrolizumab in clear-cell RCC
@DrRishabhOnco
OTHER GU ABSTRACTS TO WATCH: PE-PE | KEYNOTE-B15 | TALAPRO-3 | NIAGARA | SWOG S2200
[Madrid skyline line-art illustrations]
[Slide 1]
NIAGARA vs KEYNOTE-866
Same Cancer. Different Trial Outcomes.
MV Onco
[Cartoon: bladder illustration; left stage - physician in 'DURVA' lab coat holding a trophy; right stage - physician in 'PEMBRO' lab coat holding a sheet reading 'Higher pCR ✓' with a histology image]
NIAGARA
EFS improved ✓
OS improved ✓
POSITIVE TRIAL
KEYNOTE-866
EFS endpoint not met ✗
NEGATIVE PRIMARY ENDPOINT
Better pCR ≠ Proven Survival Benefit
Separate trials. Not a head-to-head comparison.
[Slide 2]
KEYNOTE-866 | ESMO 2026
Does Adding Pembrolizumab Improve Outcomes in Bladder Cancer?
MV Onco
01 - WHAT WAS THE QUESTION?
In muscle-invasive bladder cancer (MIBC):
Does adding pembrolizumab to chemotherapy before surgery and continuing it after surgery improve outcomes?
02 - WHO WERE THE PATIENTS?
• 907 patients
• Cisplatin-eligible MIBC
• ECOG 0-1
• Randomized Phase III trial.
03 - WHAT WAS COMPARED?
Standard treatment:
Gemcitabine + cisplatin x 4 cycles
→ Radical cystectomy
→ Placebo
Experimental treatment:
Same chemotherapy + pembrolizumab
→ Radical cystectomy
→ Pembrolizumab x 13 cycles
04 - WHAT DID WE WANT TO IMPROVE?
Primary endpoint:
• Event-free survival (EFS)
Other important outcomes:
• Pathological complete response (pCR)
• Overall survival (OS)
TAKE-HOME
Can adding immunotherapy before and after surgery improve long-term outcomes?
That was the KEYNOTE-866 question.
[Slide 3]
KEYNOTE-866 | ESMO 2026
Better Tumour Response. But Better Survival?
MV Onco
01 DID MORE TUMOURS DISAPPEAR?
Pathological complete response (pCR)
• Pembrolizumab: 44.4%
• Placebo: 35.8%
→ Yes - higher pCR with pembrolizumab.
→ But pCR was not formally tested.
02 DID PATIENTS REMAIN EVENT-FREE LONGER?
Event-free survival
• HR 0.88
• P = 0.1366
→ No statistically significant benefit.
→ This was the primary endpoint.
03 DID PATIENTS LIVE LONGER?
Overall survival
• HR 1.00
• Median OS not reached in either arm.
→ No demonstrated survival advantage.
→ OS was not formally tested.
04 WHAT ABOUT TOXICITY?
Grade 3-5 adverse events:
• Pembrolizumab: 80.2%
• Placebo: 75.1%
→ Numerically more severe toxicity with pembrolizumab.
TAKE-HOME
Better pCR ≠ Proven Survival Benefit
• KEYNOTE-866 failed to meet its primary EFS endpoint.
• No demonstrated EFS or OS advantage with perioperative pembrolizumab.
• Higher pCR alone is insufficient to change practice.
[Slide 1]
ESMO CONGRESS 2026
Anticipated Highlights
Madrid · October 23-27
1 INTerpath-001 · LBA1 · Sat Presidential I
Intismeran plus pembrolizumab, resected IIB-IV melanoma. First phase 3 individualized neoantigen win: recurrence risk cut 42%.
2 VOLGA · LBA2 · Sat Presidential I
Perioperative durvalumab plus neoadjuvant EV in cisplatin-ineligible MIBC. EFS/OS positive at interim; FDA priority review.
3 LITESPARK-011 · 3587O · Renal proffered
Final: belzutifan plus lenvatinib held PFS post-immunotherapy in ccRCC; OS non-significant. QoL 3595RO may shape sequencing.
4 LITESPARK-012 · 3586O · Renal proffered
First-line belzutifan combinations vs pembrolizumab plus lenvatinib in ccRCC. Missed PFS and OS endpoints.
5 DASL-HiCaP · LBA4 · Prostate late-breaking
Interim: darolutamide plus ADT with radiotherapy in very-high-risk localized prostate cancer.
6 CAPItello-281 · LBA56 · Prostate late-breaking
Updated OS: capivasertib plus abiraterone in PTEN-deficient metastatic hormone-sensitive prostate cancer.
7 Perioperative bladder cancer · Fri orals
KEYNOTE-866, ENERGIZE, and KEYNOTE-905 ad hoc: refining immunotherapy around cystectomy.
8 AI in oncology · Fri 10:15 AM + LBA20 Sat
Educational session on digital health and AI, Barcelona Hall 9 Friday morning, plus the Agendia AI digital pathology late-breaker, Bilbao Hall 3 Saturday 2:45 PM.
Cross-tumor practice changers first, then GU depth · ESMO 2026, Madrid
[Slide 1]
Merck
European Commission Approves KEYTRUDA® (pembrolizumab) Plus Padcev® (enfortumab vedotin-ejfv) as Perioperative Treatment for Adults With Resectable Muscle-Invasive Bladder Cancer (MIBC) - Merck.com
[Slide 1]
PEACE-1 | ESMO 2026
Does Triplet Therapy Improve Survival? The Long-Term Update
MV Onco
01 - WHAT CHANGED?
Same PEACE-1 trial. Longer follow-up.
2022 → 4.4 years follow-up
ESMO 2026 → 7.7 years follow-up
Now we have more mature survival data.
02 - WHAT WAS COMPARED?
710 patients in the docetaxel-based group.
Doublet: ADT + Docetaxel
versus
Triplet: ADT + Docetaxel + Abiraterone
03 - DID PATIENTS LIVE LONGER?
Updated median overall survival:
Doublet → 4.4 YEARS
Triplet → 6.2 YEARS
NEARLY 22 MONTHS LONGER with triplet therapy.
04 - DOES THE BENEFIT LAST?
At 8 years:
Doublet → 27% ALIVE
Triplet → 40% ALIVE
Approximately 13 more patients alive per 100 treated.
TAKE-HOME
→ Adding abiraterone improves survival.
→ The benefit persists with long-term follow-up.
[Slide 1]
KEYNOTE-B15 | ESMO 2026
The ctDNA Detective Story
MV Onco
[Cartoon: detective physician with magnifying glass over two blood tubes; speech bubble: "I can predict RISK... not prescribe the NEXT MOVE!"; characters labelled EV, PEMBRO, CHEMOTHERAPY]
EV + PEMBRO: 82.1% CLEARED ✓
CHEMOTHERAPY: 66.7% CLEARED
ctDNA: PROGNOSTIC ✓ | PREDICTIVE ?
[Slide 2]
KEYNOTE-B15 | ESMO 2026
Does EV + Pembrolizumab Clear ctDNA Better?
MV Onco
01 - WHAT WAS STUDIED?
• KEYNOTE-B15 / EV-304
• 808 patients with cisplatin-eligible muscle-invasive bladder cancer.
• 405 → EV + pembrolizumab
• 403 → Cisplatin + gemcitabine
• Perioperative treatment with radical cystectomy.
02 - WHAT WAS THE QUESTION?
• Can EV + pembrolizumab eliminate circulating tumour DNA (ctDNA) more effectively than chemotherapy?
• ctDNA measured using the Signatera assay.
03 - WHAT HAPPENED TO ctDNA?
Patients remaining ctDNA-positive:
• Before treatment: EV + Pembro: 52.4% | Chemotherapy: 56.8%
• Before surgery: EV + Pembro: 13.0% | Chemotherapy: 19.7%
• After surgery: EV + Pembro: 4.8% | Chemotherapy: 13.5%
[Illustration: bladder with two blood tubes labelled EV + PEMBRO and CHEMOTHERAPY] Less detectable ctDNA with EV + Pembro (symbolic depiction, not individual patient samples)
04 - THE MOST IMPORTANT RESULT
ctDNA CLEARANCE
• 82.1% - EV + Pembrolizumab
• 66.7% - Chemotherapy
• 15.4 percentage points higher with EV + pembrolizumab.
TAKE-HOME
• EV + pembrolizumab achieves greater ctDNA clearance and lower postsurgical ctDNA positivity than cisplatin-gemcitabine.
Exploratory biomarker analysis. ctDNA negativity does not necessarily mean cure.
[Slide 3]
KEYNOTE-B15 | ESMO 2026
Does ctDNA Status Predict Better Outcomes?
MV Onco
01 - DOES ctDNA STATUS MATTER?
YES.
Patients with detectable ctDNA had poorer outcomes.
ctDNA-negative patients had:
• Better event-free survival (EFS).
• Higher pathological complete response (pCR).
Observed in both treatment arms.
[Illustration: ctDNA negative → Lower recurrence risk; ctDNA positive → Higher recurrence risk]
02 - WHAT IF ctDNA WAS POSITIVE BEFORE TREATMENT?
EV + Pembrolizumab vs Chemotherapy
EFS HR: 0.54
95% CI: 0.37-0.80
Approximately 46% lower hazard of an EFS event with EV + pembrolizumab.
03 - WHAT IF ctDNA WAS NEGATIVE BEFORE TREATMENT?
EV + Pembrolizumab vs Chemotherapy
EFS HR: 0.68
95% CI: 0.37-1.26
Favourable point estimate. But confidence interval crosses 1.
04 - WHAT ABOUT ctDNA AFTER SURGERY?
EV + Pembrolizumab vs Chemotherapy
ctDNA-positive: EFS HR: 0.63, 95% CI: 0.30-1.35
ctDNA-negative: EFS HR: 0.48, 95% CI: 0.29-0.81
Treatment effect estimates favour EV + pembrolizumab in both groups.
TAKE-HOME
• ctDNA status is prognostic.
• Detectable ctDNA identifies patients with poorer outcomes.
• EV + pembrolizumab shows favourable EFS estimates across ctDNA subgroups.
Small scientific caution:
• Exploratory subgroup analysis. Some confidence intervals cross 1; differential treatment benefit by ctDNA status is not established.
[Slide 4]
KEYNOTE-B15 | ESMO 2026
PART 3 - Can ctDNA Guide Treatment Decisions?
MV Onco
01 IS ctDNA PROGNOSTIC? YES ✓
• ctDNA-positive → Poorer outcomes.
• ctDNA-negative → Better outcomes.
• ctDNA clearance → Associated with improved EFS and pCR.
• ctDNA helps estimate recurrence risk.
02 IS ctDNA PREDICTIVE? NOT ESTABLISHED
• Does ctDNA identify who benefits MORE from EV + pembrolizumab? Not proven.
• EV + pembrolizumab showed favourable EFS estimates across ctDNA subgroups.
• Prognostic ≠ Predictive.
03 CAN WE CHANGE TREATMENT BASED ON ctDNA? NOT YET
• ctDNA-negative after surgery? → Cannot safely omit adjuvant treatment based on this result alone.
• ctDNA-positive after surgery? → No validated ctDNA-guided escalation strategy from this analysis.
• ctDNA negativity ≠ Cure.
[Illustration: physician holding a ctDNA report; signpost RISK ESTIMATION ✓ / TREATMENT SELECTION ?] A useful compass, not yet a treatment roadmap.
04 WHAT ARE THE LIMITATIONS?
• Exploratory biomarker analysis.
• Not all patients had evaluable ctDNA.
• Small postsurgical ctDNA-positive subgroups.
• No randomized ctDNA-guided treatment decisions.
↳ Clinical utility requires prospective validation.
TAKE-HOME
☑ ctDNA is a promising prognostic biomarker in MIBC.
☑ But it is NOT yet validated to select, escalate or omit perioperative treatment.
☑ Better molecular clearance ≠ Proof that ctDNA-guided treatment improves survival.
[Slide 1]
VOLGA (Imfinzi + neoadjuvant EV only)
• Neoadjuvant: 3 cycles (21 days each) of durvalumab 1500 mg Day 1 + EV 1.25 mg/kg Days 1 and 8.
• Adjuvant: 9 cycles (28 days each) of durvalumab 1500 mg Day 1 only. No EV after surgery. cancernetwork.com
EV + pembrolizumab (KEYNOTE-905/EV-303)
• Neoadjuvant: 3 cycles (21 days each) of pembrolizumab 200 mg Day 1 + EV 1.25 mg/kg Days 1 and 8.
• Adjuvant: 6 more cycles of EV + pembrolizumab, then pembrolizumab monotherapy to complete 17 total pembrolizumab cycles (~1 year). Total EV = 9 cycles. nejm.org
[clipped last line:] The practical difference is that VOLGA stops EV after[...]
[Slide 1]
Acknowledgements
@WyattLab
Vancouver Prostate Centre
Andrew Murtha
Asli Munzur
Catherine Wang
Cecily Bernales
David Müller
Grainne Donnellan
Jack Bacon
Jan Pieter Vanwelkenhuyzen
John Pham
Karan Parekh
Kamal Azzam
Maria Stephenson
Melissa Koudjanian
Ruby Liao
Sarah Ng
Sofie Tolmeijer
Tiffany Xie
Zoe Shong
+ recent alumni: E Kwan, G Vandekerkh[obscured], … Warner, E Ritch, T Sumiyoshi, K Rostin, [obscured]
Kim Chi; BC Cancer
Corinne Maurice-Dror
Bernie Eigl
Matti Annala; U of Tampere
Joonatan Sipola
Tuomo Virtanen
Jussi Nikkola
Matti Nykter
Felix Feng; UCSF
David Quigley
Martin Gleave; UBC
Peter Black
Nathan Lack
Gillian Vandekerkhove
Nicolette Fonseca; Uvic
Piet Ost; UGent
Niven Mehra; RadboudUMC
Nielka van Erp
David Takeda; NCI/NIH
ANZUP investigators
Michael Hofman;
Arun Azad
Ian Davis
Ed Kwan
Shahneen Sandhu
Louise Emmett
Andre Bergman & Wilbert Zwart
Thank you to all patients and their families!
[funder logos: Vancouver Coastal Health Research Institute, BC Cancer Foundation, Movember, Canadian Cancer Society, Canadian Cancer Trials Group, CIHR IRSC, Prostate Cancer Foundation, BCAN, Cancer Research Society]
alexander.wyatt@ubc.ca
blogs.ubc.ca/wyattlab
VANCOUVER PROSTATE CENTRE
BC CANCER
THE UNIVERSITY OF BRITISH COLUMBIA
[photo: presenter at podium in front of screen]
[Slide 1]
LITESPARK-012 | ESMO 2026
Why Did Two Triplets Fail in Advanced RCC?
MV Onco
The Idea
Pembrolizumab + lenvatinib works well in advanced ccRCC. Can adding another mechanism do better?
[Signpost] PFS / OS / Tumor response
[Cartoon: three teams of drug characters crossing a crumbling bridge toward a boulder labeled "Advanced ccRCC"]
Arm A Triplet: Pembro + Lenvatinib + Belzutifan (HIF-2α)
Arm B Triplet: Pembro + Lenvatinib + Quavonlimab (CTLA-4)
Control Standard doublet: Pembro + Lenvatinib
Pembrolizumab + Lenvatinib + Belzutifan
PFS 20.8 mo
HR 1.08
P = 0.84
No improvement ✗
MK-1308A (Pembrolizumab + Quavonlimab) + Lenvatinib
PFS 20.7 mo
HR 1.07
P = 0.82
No improvement ✗
Pembrolizumab + Lenvatinib
PFS 23.7 mo
New standard remains strong ✓
OS 52.0 mo
HR 1.04
No improvement ✗
OS Not reached
HR 1.12
No improvement ✗
OS Not reached
Continues to do well
ORR 69.1%
ORR 69.0%
ORR 76.3%
Highest response rate!
TAKE-HOME
More drugs ≠ Better outcomes
Neither adding belzutifan nor CTLA-4 blockade improved PFS or OS.
Pembrolizumab + lenvatinib remains an established first-line standard in advanced ccRCC.
LITESPARK-012 | NCT04736706 | ESMO 2026
[Slide 2]
LITESPARK-012 | ESMO 2026
Why Did Two Triplets Fail in Advanced RCC?
MV Onco
01 WHY THIS TRIAL?
• Pembrolizumab + lenvatinib is an established first-line regimen in advanced ccRCC.
• Can adding another mechanism improve outcomes?
• Belzutifan → HIF-2α inhibition
• Quavonlimab → CTLA-4 blockade
[Cartoon: kidney labeled RCC with Pembro, Lenvatinib, Belzutifan (HIF-2α inhibition), Quavonlimab (CTLA-4 blockade) characters]
02 HOW WAS THE TRIAL DESIGNED?
• Phase III | Open-label | 1,688 patients
• Previously untreated advanced ccRCC.
• Randomization 1:1:1
• Dual primary endpoints: PFS and OS.
• Median follow-up: 43.6 months.
ARM A (n = 560): Pembrolizumab + Lenvatinib + Belzutifan
ARM B (n = 562): MK-1308A (Pembrolizumab + Quavonlimab) + Lenvatinib
CONTROL (n = 566): Pembrolizumab + Lenvatinib
03 DID ADDING BELZUTIFAN IMPROVE PFS?
• Median PFS:
• Triplet: 20.8 months
• Control: 23.7 months
HR 1.08 (95% CI 0.93–1.26)
P = 0.84
NO PFS BENEFIT ✗
04 DID CTLA-4 BLOCKADE IMPROVE PFS?
• Median PFS:
• Triplet: 20.7 months
• Control: 23.7 months
HR 1.07 (95% CI 0.92–1.25)
P = 0.82
NO PFS BENEFIT ✗
05 DID PATIENTS LIVE LONGER?
• Median OS:
• Belzutifan triplet: 52.0 months
• CTLA-4 triplet: Not reached
• Control: Not reached
OS HR:
• Belzutifan triplet: 1.04
• CTLA-4 triplet: 1.12
NEITHER TRIPLET IMPROVED OS.
TAKE-HOME
Adding HIF-2α or CTLA-4 inhibition failed to improve efficacy over pembrolizumab + lenvatinib.
LITESPARK-012 | NCT04736706 | ESMO 2026
[Slide 3]
LITESPARK-012 | ESMO 2026
Why Did Two Triplets Fail in Advanced RCC?
MV Onco
01 DID MORE DRUGS SHRINK MORE TUMORS?
Objective response rate (ORR):
• Belzutifan triplet → 69.1%
• CTLA-4 triplet → 69.0%
• Standard doublet → 76.3%
Surprisingly, the standard doublet had the highest numerical response rate!
[Cartoon: three tumor characters holding signs 69.1%, 69.0%, 76.3%]
02 DID CTLA-4 HELP INTERMEDIATE/POOR-RISK PATIENTS?
IMDC intermediate/poor risk:
Median PFS:
• CTLA-4 triplet: 20.5 months
• Control: 23.5 months
HR 1.12
Median OS:
• CTLA-4 triplet: 39.1 months
• Control: 46.2 months
HR 1.17
No demonstrated benefit even in this higher-risk population.
03 WAS TREATMENT DISCONTINUATION HIGHER?
Patients discontinuing any study drug due to adverse events:
• Belzutifan triplet → 51.6%
• CTLA-4 triplet → 51.4%
• Standard doublet → 36.2%
Both triplets caused substantially more treatment discontinuation.
Grade ≥3 adverse events:
• Belzutifan triplet → 87.2%
• CTLA-4 triplet → 88.7%
• Standard doublet → 84.8%
(Same treatment order)
04 WHY MIGHT BOTH TRIPLETS HAVE FAILED?
Reason 1 — Strong control arm
Pembrolizumab + lenvatinib already achieved:
• PFS 23.7 months
• ORR 76.3%
Reason 2 — Reduced drug exposure
Median pembrolizumab/MK-1308A duration:
• Belzutifan triplet → 14.1 months
• CTLA-4 triplet → 11.8 months
• Control → 21.2 months
Higher discontinuation may have reduced effective treatment exposure.
Reason 3 — More mechanisms ≠ More efficacy
Adding HIF-2α or CTLA-4 inhibition did not translate into improved outcomes.
These are plausible explanations, not proven causes.
05 DOES THIS INVALIDATE BELZUTIFAN?
NO.
• This trial tested belzutifan in a specific first-line triplet.
• It does not negate its benefit in other established RCC settings.
• Treatment line, combination partners and tolerability matter.
[Cartoon kidney holding sign: Belzutifan still has a role in other RCC settings]
TAKE-HOME
MORE DRUGS ≠ BETTER OUTCOMES
• Neither triplet improved PFS or OS.
• Both increased treatment discontinuation.
• Pembrolizumab + lenvatinib remains an established first-line standard.
LITESPARK-012 | NCT04736706 | ESMO 2026
[Slide 1]
NIAGARA vs CA017-078
SAME CANCER. DIFFERENT OUTCOMES.
MV Onco
[Cartoon: bladder illustration; a doctor labeled "DURVA" holding a trophy "EFS + OS ✓" standing on a podium labeled NIAGARA in front of a waterfall; a doctor labeled "NIVO" holding a ribbon "pCR ↑" next to an empty trophy pedestal reading "NO EFS WIN", on a podium labeled CA017-078]
NIAGARA — POSITIVE TRIAL
CA017-078 — NEGATIVE TRIAL
HIGHER pCR ≠ PROVEN SURVIVAL BENEFIT
Different trials. No head-to-head comparison.
[Slide 2]
CA017-078 | ESMO 2026
NIVOLUMAB + CHEMOTHERAPY IN MIBC
MV Onco
PART 1/2
1 WHY THIS TRIAL?
Cisplatin-based chemotherapy → Surgery
Standard treatment for eligible MIBC.
THE QUESTION
Can adding NIVOLUMAB before and after surgery improve outcomes?
2 WHO ENTERED?
• Phase III randomized trial
• N = 653
• Previously untreated MIBC
• cT2–T4a N0 M0
• Resectable disease
• Cisplatin eligible
3 RANDOMIZATION
N = 653 | 1:1
ARM A — n = 325
GC + NIVOLUMAB × 4 cycles
↓
SURGERY
↓
Adjuvant NIVOLUMAB × 9 cycles
VS
ARM B — n = 328
GC × 4 cycles
↓
SURGERY
GC = Gemcitabine + Cisplatin
4 DID NIVOLUMAB IMPROVE EFS?
NO SIGNIFICANT BENEFIT
EFS HR = 0.94
95.74% CI 0.71–1.25
P = 0.67
Median EFS:
NIVO arm → Not reached
GC arm → 67.6 months
Median follow-up: 54.5 months
5 DID NIVOLUMAB IMPROVE pCR?
NIVO + GC → 39.1%
GC alone → 29.6%
Absolute difference = 9.5 percentage points
NOT STATISTICALLY SIGNIFICANT
TAKE-HOME
Higher numerical pCR ≠ Proven EFS benefit.
CA017-078 failed to meet its primary endpoints.
[Slide 3]
WHY DID NIVOLUMAB FAIL?
MV Onco | PART 2/2
1 DID PATIENTS LIVE LONGER?
Overall survival (OS)
• HR = 0.88
• 95% CI 0.64 – 1.21
• OS data immature.
• NO PROVEN SURVIVAL BENEFIT.
2 WAS TOXICITY HIGHER?
Grade ≥3 treatment-related adverse events:
• NIVO + GC → 45.9%
• GC alone → 49.5%
• No numerical increase in severe treatment-related toxicity.
3 WHY IS THIS SURPRISING?
NIAGARA
Durvalumab + GC → Surgery → Durvalumab
• EFS improved ✓
• OS improved ✓
CA017-078
Nivolumab + GC → Surgery → Nivolumab
• EFS not significantly improved ✗
• pCR not significantly improved ✗
Different trials. No head-to-head comparison.
4 DOES THIS CONTRADICT CHECKMATE 274?
NO.
• CheckMate 274:
Adjuvant nivolumab after surgery in high-risk urothelial carcinoma.
→ Disease-free survival improved.
• CA017-078:
Perioperative nivolumab in resectable MIBC.
→ Primary endpoints not met.
Different populations. Different strategies.
5 WHAT SHOULD CHANGE IN PRACTICE?
• Do not routinely adopt this perioperative nivolumab regimen based on CA017-078.
• NIAGARA supports perioperative durvalumab in eligible patients.
• Adjuvant nivolumab retains its evidence in the appropriate high-risk postoperative setting.
• ctDNA-guided treatment selection remains unvalidated.
TAKE-HOME
NOT ALL PERIOPERATIVE IMMUNOTHERAPY TRIALS ARE POSITIVE.
• NIAGARA → Positive EFS and OS results.
• CA017-078 → No significant EFS or pCR benefit.
• Cross-trial differences do not prove one antibody is superior.
[Slide 1]
LIVE INTERACTIVE WEBINAR
Bladder cancer updates from the second half of 2026
[Five circular headshots of the panellists]
Q&A with global experts:
Dr Alison Birtle
Rosemere Cancer Centre, Lancashire Teaching Hospitals, Preston, UK
Dr Ignacio Durán
Hospital Universitario Marqués de Valdecilla, Santander, Spain
Prof Axel Merseburger
Universitätsklinikum Schleswig-Holstein, Lübeck, Germany
Dr José Domínguez-Escrig
Fundación Instituto Valenciano de Oncología (IVO), Valencia, Spain
Prof Morgan Rouprêt
Pitié-Salpétrière Hospital, Paris, France
16th November 2026
17:00 GMT / 18:00 CET
Register now:
ecancer.org/bladder
To help improve the quality of bladder cancer care globally, this webinar, sponsored by Johnson & Johnson, will address the care of bladder cancer patients and available treatment options.
Data from the ESMO and EMUC meetings will be covered, along with the potential impact of key research, and the chance for the audience to pose questions.
ecancer.org
UK Charity number 1176307
Supported by an independent educational grant from Johnson & Johnson
[Slide 1]
SWOG S2200 | ESMO 2026
A PFS Win. But Is It Enough?
MV Onco
OS BENEFIT? NOT PROVEN
[Cartoon: superhero doctor labeled CABO with a shield; a pair labeled CABO and ATEZO holding a trophy "PFS ✓"]
HR 0.46
[Cartoon: doctor with magnifying glass reading a sheet "ONLY 33 PATIENTS!"]
Promising... but we need more evidence!
PFS WIN ✓
OS NOT PROVEN
NOT PRACTICE-CHANGING YET
[Slide 2]
SWOG S2200 | ESMO 2026
Does Adding Atezolizumab Improve Outcomes in Papillary RCC?
MV Onco
01 — WHY THIS TRIAL?
PAPMET established cabozantinib as an effective treatment for metastatic papillary RCC.
The unanswered question:
Does adding immunotherapy improve outcomes further?
02 — WHAT WAS COMPARED?
Randomized Phase II | SWOG S2200
33 eligible patients with metastatic papillary RCC.
• Arm A (n = 16)
Cabozantinib 60 mg daily.
• Arm B (n = 17)
Cabozantinib 60 mg daily + atezolizumab 1200 mg IV every 3 weeks.
Median follow-up: 24 months.
[Cartoon: capsule characters "Cabozantinib alone" and "Cabozantinib + atezolizumab" with flag PFS ✓ and signpost "OS ?"]
03 — DID ADDING ATEZOLIZUMAB IMPROVE PFS?
YES — Nominally significant
PFS HR 0.46
90% CI: 0.22–0.97
One-sided p = 0.043
54% lower hazard of progression or death.
04 — DID PATIENTS LIVE LONGER?
NO OS BENEFIT DEMONSTRATED
OS HR 1.67
90% CI: 0.59–4.70
One-sided p = 0.79
Survival advantage not established.
TAKE-HOME
• PFS improved, but OS benefit was not demonstrated.
• A promising signal from a very small randomized trial.
[Slide 3]
SWOG S2200 | ESMO 2026
Is This a Practice-Changing Trial?
MV Onco
01 — WAS TOXICITY HIGHER?
Grade 3–4 adverse events:
• Cabozantinib + Atezolizumab: 65% (11/17)
• Cabozantinib alone: 75% (12/16)
• No obvious increase in severe toxicity.
• Small numbers limit interpretation.
02 — WHAT WAS THE BIGGEST PROBLEM?
SEVERE UNDER-ACCRUAL
• Planned: 180 patients
• Enrolled: 36 patients
• Eligible: 33 patients
• Trial terminated in January 2026 due to poor recruitment.
• The study was substantially underpowered.
03 — HOW STRONG IS THE EVIDENCE?
• PFS met the prespecified nominal significance threshold.
• BUT:
– Only 33 eligible patients.
– One-sided statistical testing.
– Wide confidence intervals.
– No demonstrated OS benefit.
• Statistically positive ≠ Definitively practice-changing.
04 — SHOULD WE ADD ATEZOLIZUMAB ROUTINELY?
• NOT YET.
• Cabozantinib remains an evidence-supported treatment option.
• Adding atezolizumab showed a promising PFS signal.
• However, routine adoption requires stronger confirmatory evidence.
TAKE-HOME
• Promising PFS signal.
• No proven survival advantage.
• Too few patients for definitive conclusions.
• SWOG S2200 is hypothesis-generating, not practice-changing.
[Cartoon: doctor with magnifying glass over "33 PATIENTS" sheet; flag PFS ✓; warning sign MORE EVIDENCE NEEDED]
[Slide 1]
LITESPARK-011 | ESMO 2026
Better Tumor Control. But Longer Survival?
MV Onco
BELZUTIFAN + LENVATINIB
Belzutifan inhibits HIF-2α
Lenvatinib inhibits VEGFR angiogenic signalling
[Illustration: kidney with tumor shrinking] Smaller tumor Better control
PFS: 14.8 months
ORR: 53.1%
DOR: 22.0 months
CABOZANTINIB
Inhibits multiple TK receptors (eg, VEGFR, MET, AXL)
[Illustration: kidney with tumor] Residual disease persists
PFS: 10.8 months
ORR: 40.2%
DOR: 11.9 months
OVERALL SURVIVAL
33.7 vs 28.6 months
HR 0.85 (95% CI 0.70–1.03)
OS NOT STATISTICALLY SIGNIFICANT
[Cartoon: doctor with magnifying glass comparing sheets "Belzutifan + Lenvatinib 33.7 mo" and "Cabozantinib 28.6 mo"]
One-sided P = 0.04689
Required P ≤ 0.0223
Grade ≥3 adverse events: 85.4% (Belzutifan + Lenvatinib) | 83.0% (Cabozantinib) — High in both arms
TAKE-HOME
Better PFS. More Responses. Longer DOR.
But No Proven OS Benefit.
[Slide 2]
LITESPARK-011 | ESMO 2026
Did Belzutifan + Lenvatinib Improve Disease Control?
MV Onco
01 WHY THIS TRIAL?
• Advanced clear-cell RCC frequently progresses after immunotherapy.
• Cabozantinib is an established post-IO option.
QUESTION:
Can adding HIF-2α inhibition to VEGFR blockade improve outcomes?
[Illustration: kidney "Post Immunotherapy progression" → HIF-2α inhibition + VEGFR blockade]
02 WHO WERE THE PATIENTS?
• Phase III | N = 747
• Advanced ccRCC after anti-PD-(L)1 therapy.
• Progression after first- or second-line immunotherapy, or within 6 months of adjuvant immunotherapy.
03 WHAT WERE THE TREATMENTS?
Randomisation 1:1
Belzutifan + Lenvatinib (n = 371)
120 mg + 20 mg orally daily
VERSUS
Cabozantinib (n = 376)
60 mg orally daily
Belzutifan → HIF-2α inhibitor
Lenvatinib → Multikinase inhibitor targeting VEGFR
04 WHAT WAS THE TRIAL TESTING?
• Dual primary endpoints:
– PFS – blinded independent central review
– Overall survival (OS)
• Key secondary endpoint: ORR
• Other endpoints: DOR and safety.
• Median follow-up: 38.8 months
• Data cutoff: 2 February 2026
[Clipboard: Endpoints ☑ PFS (BICR) ☑ OS ☑ ORR ☑ DOR ☑ Safety]
05 DID PFS IMPROVE? YES – PFS BENEFIT MAINTAINED!
Median PFS:
• Belzutifan + Lenvatinib → 14.8 months
• Cabozantinib → 10.8 months
HR 0.74 (95% CI 0.62–0.88)
26% relative reduction in progression/death hazard.
36-month PFS:
20.5% vs 12.6%
PFS significance was established at an earlier analysis; not formally retested at final analysis.
BOTTOM TAKE-HOME
Belzutifan + Lenvatinib delivers superior disease control compared with cabozantinib after immunotherapy.
But does better PFS translate into longer survival?
Continued in Part 2 →
[Slide 3]
LITESPARK-011 | ESMO 2026
Better Tumor Control – But Longer Survival?
MV Onco
01 DID PATIENTS LIVE LONGER?
Median overall survival (OS):
• Belzutifan + Lenvatinib → 33.7 months
• Cabozantinib → 28.6 months
• Numerical difference → +5.1 months
• HR 0.85 (95% CI 0.70 – 1.03)
• OS favored the combination numerically.
• But OS superiority was NOT statistically demonstrated.
[Illustration: balance scale 33.7 months (Belzutifan + Lenvatinib) vs 28.6 months (Cabozantinib), labeled OS]
02 WHY WAS P = 0.04689 NOT SIGNIFICANT?
• Observed one-sided P = 0.04689
• Prespecified significance boundary = 0.0223
• 0.04689 > 0.0223
• The required statistical threshold was NOT crossed.
• Also, the 95% CI included 1.
• OS primary endpoint NOT MET.
03 WHAT HAPPENED AT 3 YEARS?
Estimated 36-month overall survival:
• Belzutifan + Lenvatinib → 48.9%
• Cabozantinib → 40.6%
• Absolute numerical difference → +8.3 percentage points
• More patients were estimated to be alive at 3 years with the combination.
• However, this does not establish statistically significant OS superiority.
04 DID MORE TUMORS RESPOND?
Objective response rate (ORR):
• Belzutifan + Lenvatinib → 53.1%
• Cabozantinib → 40.2%
• Absolute improvement → +12.9 percentage points
• More than half of patients responded with the combination.
• ORR benefit was established at an earlier analysis and maintained at final analysis.
05 WERE RESPONSES MORE DURABLE?
Median duration of response (DOR):
• Belzutifan + Lenvatinib → 22.0 months
• Cabozantinib → 11.9 months
• Numerical difference → +10.1 months
• Median response duration was nearly doubled.
• Better response durability – but no proven OS advantage.
TAKE-HOME
Better PFS + Higher ORR + Longer DOR ≠ Proven Overall Survival Benefit
• LITESPARK-011 improved tumor control but missed its prespecified OS significance boundary.
• Next: Toxicity, subsequent therapy and clinical implications.
Continued in Part 3 →
[Slide 4]
LITESPARK-011 | ESMO 2026
Is Belzutifan + Lenvatinib Practice-Changing?
MV Onco
01 WAS TOXICITY HIGHER?
Grade ≥3 treatment-emergent adverse events:
• Belzutifan + Lenvatinib → 85.4%
• Cabozantinib → 83.0%
Severe adverse-event rates were broadly similar, but high in both arms.
Different toxicity profiles:
• Belzutifan → Anemia, hypoxia
• Lenvatinib → Hypertension, diarrhea, fatigue
Similar severe-event rates ≠ Identical tolerability.
02 COULD SUBSEQUENT THERAPY AFFECT OS?
Among patients who discontinued treatment, subsequent therapy was received by:
• Belzutifan + Lenvatinib → 63.4% (173/273)
• Cabozantinib → 62.7% (203/324)
Rates were similar.
But subsequent treatment regimens were not detailed.
Could later HIF-2α inhibitor exposure dilute OS differences?
Possible — but unproven.
03 WHY DID PFS BENEFIT NOT TRANSLATE INTO PROVEN OS BENEFIT?
Three possible explanations:
1 Subsequent treatments
Effective later-line therapy may reduce OS differences.
2 Modest OS effect
HR 0.85 did not cross the prespecified statistical boundary.
3 PFS ≠ OS
Delaying progression does not guarantee longer survival.
These are hypotheses, not proven explanations.
04 WHAT QUESTIONS REMAIN?
• Which subsequent treatments were received?
• Did OS differ by IMDC risk or prior therapy?
• What were the quality-of-life outcomes?
• How often were doses reduced or interrupted?
• Is upfront combination better than sequential treatment?
Optimal treatment sequencing remains uncertain.
05 IS THIS PRACTICE-CHANGING?
YES — stronger evidence for disease control.
• PFS benefit → Established
• ORR benefit → Established
• DOR → Numerically longer
BUT:
• OS superiority → NOT demonstrated
• Grade ≥3 toxicity → High in both arms
Belzutifan + lenvatinib is an effective post-IO treatment option, but selection requires balancing efficacy, toxicity and patient factors.
TAKE-HOME
Better Tumor Control ≠ Proven Longer Survival
• LITESPARK-011 supports belzutifan + lenvatinib after immunotherapy in advanced ccRCC.
• The strongest evidence is for PFS and response benefit — NOT overall survival superiority.
[Slide 1]
ESMO 2026
MADRID, SPAIN
KEYNOTE-866
Perioperative Pembrolizumab or Placebo
+ Neoadjuvant Cisplatin and Gemcitabine
in Muscle-Invasive Bladder Cancer
[ESMO 2026 MADRID stamp; Madrid Metropolis building photo]
Study Design
Phase III, randomized, double-blind, placebo-controlled
907 patients randomized (453 vs 454)
Data cutoff: January 26, 2026
Median follow-up: 60.9 months
Patient Population
• Muscle-invasive bladder cancer (MIBC)
• cT2–T4aN0M0 or cT1–T4aN1M0
• ≥50% urothelial histology (centrally assessed)
• ECOG PS 0–1
• No prior systemic therapy
• Cisplatin-eligible
• Suitable for radical cystectomy and pelvic lymph node dissection
[illustration of a bladder with tumor]
Randomization (n = 907)
Pembrolizumab + Gemcitabine + Cisplatin n = 453 ← 1:1 → Placebo + Gemcitabine + Cisplatin n = 454
Treatment Regimen
Experimental Arm – Pembrolizumab (n = 453)
Neoadjuvant (4 cycles, Q3W)
• Pembrolizumab 200 mg IV (day 1)
• Gemcitabine 1000 mg/m² (day 1, 8)
• Cisplatin 70 mg/m² (day 1)
→ Radical cystectomy + PLND → Adjuvant: Pembrolizumab 200 mg IV Q3W × 13 cycles
Control Arm – Placebo (n = 454)
Neoadjuvant (4 cycles, Q3W)
• Placebo (day 1)
• Gemcitabine 1000 mg/m² (day 1, 8)
• Cisplatin 70 mg/m² (day 1)
→ Radical cystectomy + PLND → Adjuvant: Placebo Q3W × 13 cycles
Endpoints
Primary endpoint
Investigator-assessed Event-Free Survival (EFS)
Key secondary endpoints
• Pathological complete response (pCR) (by central review)
• Overall survival (OS)
Secondary endpoint
• Safety
Results
Event-Free Survival (Primary Endpoint)
[Kaplan-Meier curves, two arms: Pembrolizumab, Placebo; x-axis Months 0–84; y-axis Event-free survival (%)]
Median EFS
74.1 mo
vs NR
HR 0.88
(95% CI 0.71–1.10)
P = 0.1366
Pathological Complete Response (pCR)
[bar chart: pCR rate (%)]
44.4% Pembrolizumab (n = 453)
35.8% Placebo (n = 454)
Absolute difference 8.9%
(95% CI 2.5–15.1)
Overall Survival (OS)
[Kaplan-Meier curves, two arms: Pembrolizumab, Placebo; x-axis Months 0–84; y-axis Overall survival (%)]
Median OS
NR in both arms
HR 1.00
(95% CI 0.79–1.27)
Not formally tested due to statistical design
Surgery Rate
Underwent surgery (pembrolizumab vs placebo)
[bar chart] 91.6% Pembrolizumab | 87.9% Placebo
Safety
| | Pembrolizumab (n = 453) | Placebo (n = 454) |
Any treatment-emergent AE | 99.8% | 98.7%
Grade 3–5 AE | 80.2% | 75.1%
Grade 5 AE | 3.8% | 4.5%
Hypothyroidism (any grade) | 10.4% | –
Grade 3–5 hypothyroidism | 0% | –
Most frequent immune-mediated AE with pembrolizumab: hypothyroidism 10.4% (grade 3–5: 0%)
Key Take Home Messages
Perioperative pembrolizumab did NOT significantly improve event-free survival in cisplatin-eligible MIBC.
Pathological complete response rate was higher with pembrolizumab (44.4% vs 35.8%), but not formally tested.
No overall survival benefit at this analysis (HR 1.00).
Safety profile was manageable but with higher grade 3–5 toxicity in the pembrolizumab arm.
These results do not establish a new standard of care. Await full publication and guideline updates.
Conclusion
• Perioperative pembrolizumab did not significantly improve EFS in cisplatin-eligible MIBC.
• Higher pCR rate observed, but secondary and not formally tested.
• No OS benefit demonstrated at current follow-up.
• Safety consistent with known pembrolizumab profile and manageable.
Dr Rohit Malde MD DNB FRCR (UK)
Consultant Clinical Oncologist
[Survival data captured as a table — no point estimates read from the curve]
Endpoint: Event-Free Survival (EFS), investigator-assessed, primary endpoint
Pembrolizumab + gemcitabine + cisplatin | 453 | 74.1 mo
Placebo + gemcitabine + cisplatin | 454 | NR
HR: 0.88
HR CI: 95% CI 0.71–1.10
P: 0.1366
Note: Second KM panel on the same image: Overall Survival — median NR in both arms; HR 1.00 (95% CI 0.79–1.27); not formally tested due to statistical design. No landmark percentages printed. Data cutoff January 26, 2026; median follow-up 60.9 months. KOL-made infographic (Rohit Malde), not a conference slide.
[Slide 1]
VOLGA | ESMO 2026
Cisplatin-Free. Adjuvant EV-Free.
MV Onco
VOLGA IS A RIVER!
Europe's longest river — flowing through Russia to the Caspian Sea.
[Map sketch: Volga River, RUSSIA, Caspian Sea]
[Illustration: bladder with tumor; crossed-out CISPLATIN vial labeled "CISPLATIN-FREE!"; boat carrying EV and DURVALUMAB vials "EV before surgery" toward a bridge labeled CYSTECTOMY; "Durvalumab after surgery"; crossed-out EV vial "ADJUVANT EV-FREE!"; sunrise labeled "LONGER SURVIVAL"]
A NEW COURSE FOR BLADDER CANCER?
EV before surgery. Durvalumab after surgery.
VOLGA | ESMO 2026 | MV Onco
[Slide 2]
VOLGA | ESMO 2026
PART 1/3
Can We Treat MIBC Without Cisplatin?
MV Onco
1. WHY VOLGA?
Muscle-invasive bladder cancer (MIBC)
• Up to 50% cannot receive cisplatin
• ~50% recur after cystectomy
• NIAGARA → cisplatin-eligible patients
THE GAP: CISPLATIN-INELIGIBLE MIBC
2. THE QUESTION
Can neoadjuvant ENFORTUMAB VEDOTIN + DURVALUMAB ± TREMELIMUMAB followed by surgery and immunotherapy IMPROVE SURVIVAL?
3. WHO ENTERED?
• MIBC planned for radical cystectomy
• Cisplatin-ineligible OR declined cisplatin
• Curative-intent treatment
4. RANDOMIZATION
N = 695 | 1 : 1 : 1
ARM 1 — TRIPLET
Neoadjuvant: EV + Durvalumab × 3 cycles, Tremelimumab × 2 cycles
↓ CYSTECTOMY ↓
Adjuvant: Durvalumab × 9 cycles, Tremelimumab × 1 cycle
ARM 2 — DOUBLET
Neoadjuvant: EV + Durvalumab × 3 cycles
↓ CYSTECTOMY ↓
Adjuvant: Durvalumab × 9 cycles
ARM 3 — CONTROL
Radical cystectomy ± Approved adjuvant therapy
5. WHAT WERE WE MEASURING?
DUAL PRIMARY
• EFS — Arm 1 vs Control
• EFS — Arm 2 vs Control
KEY SECONDARY
OS • pCR • DFS • Downstaging
EFS EVENTS:
• Recurrence after surgery
• Progression without surgery
• Failure of surgery with residual disease
• Death
VOLGA | Phase III • Open-label • 182 centres • 25 countries | NCT04960709 | PART 1/3
[Slide 3]
VOLGA | ESMO 2026
Did Patients Live Longer?
MV Onco
PART 2/3
1 DID EVENT-FREE SURVIVAL IMPROVE?
YES — BOTH EXPERIMENTAL ARMS
• EV + Durvalumab → Significant EFS improvement
• EV + Durvalumab + Tremelimumab → Significant EFS improvement
} Both compared with surgery-based control.
2 DID PATIENTS LIVE LONGER?
• EV + DURVALUMAB
→ Significant OS benefit
→ Clinically meaningful improvement
• EV + DURVA + TREME
→ Favorable OS trend
→ NOT statistically significant at interim
3 DID TREMELIMUMAB ADD BENEFIT?
• Triplet → EFS positive
• Triplet → OS not yet significant
MORE IMMUNOTHERAPY ≠ MORE SURVIVAL
Incremental benefit remains uncertain.
4 WHAT ABOUT SAFETY?
• EV + Durvalumab: No new safety signals reported.
• Known toxicities:
• EV → Rash • Neuropathy • Hyperglycemia
• Durvalumab → Immune-related adverse events
• Tremelimumab → Additional immune toxicity risk
5 WHAT NUMBERS ARE STILL AWAITED?
• Full ESMO presentation pending:
• EFS and OS hazard ratios
• Absolute survival benefit
• pCR and downstaging rates
• Grade ≥3 adverse events
• Treatment discontinuations
POSITIVE TOPLINE ≠ COMPLETE DATA
VOLGA | ESMO 2026 • Powles et al. • LBA2
Full presentation: 24 October 2026
PART 2/3
[Slide 4]
VOLGA | ESMO 2026
PART 3/3
Is This a New Standard of Care?
MV Onco
1 WHAT MAKES VOLGA UNIQUE?
• ENFORTUMAB VEDOTIN → Given ONLY before surgery
• After cystectomy: → Durvalumab maintenance
• NO ADJUVANT EV
• Potentially less cumulative toxicity.
2 HOW IS IT DIFFERENT FROM NIAGARA?
NIAGARA
• Cisplatin-ELIGIBLE MIBC
• Gemcitabine + Cisplatin + Durvalumab
VOLGA
• Cisplatin-INELIGIBLE / DECLINING MIBC
• EV + Durvalumab
• DIFFERENT PATIENT POPULATIONS.
• No direct cross-trial comparison.
3 WHAT ABOUT EV + PEMBROLIZUMAB?
EV + PEMBROLIZUMAB
• EV before AND after surgery
VOLGA
• EV ONLY before surgery
• Can postoperative EV be avoided?
• NOT PROVEN BY CROSS-TRIAL COMPARISON.
4 WHAT IS THE FDA STATUS?
• 25 SEPTEMBER 2026
• FDA granted PRIORITY REVIEW EV + Durvalumab
• For cisplatin-ineligible / declining MIBC
• Decision expected: Q4 2026
• PRIORITY REVIEW ≠ APPROVAL.
5 TAKE-HOME
• CISPLATIN-FREE PERIOPERATIVE THERAPY
• EV + Durvalumab → Significant EFS benefit → Significant OS benefit
• EV restricted to neoadjuvant phase.
• POTENTIAL NEW STANDARD OF CARE.
• Await full efficacy and safety data.
VOLGA | Powles et al. | ESMO 2026 • LBA2 | NCT04960709 | PART 3/3
[Slide 1]
UrologyWatch.com
ESMO 2026
Oct 23 to 27, Madrid
10 GU trials to watch | Live coverage
Follow ESMO 2026 on
UrologyWatch
▶ VOLGA, DASL-HiCaP, LITESPARK, KEYNOTE-564, PEACE-1
▶ Study summaries and takeaways for urologists
Built by urologists, for urologists
urologywatch.com
[Slide 2]
Proffered paper 1: Genitourinary tumour, renal
and urothelial
Date Fri, 23.10.2026
Chairs Anja Lorch (Zurich, Switzerland),
Axel Bex (London, United Kingdom)
Room Barcelona Auditorium - Hall 9
Time 13:30 - 15:00
[Slide 3]
Rapid oral: Genitourinary tumours, prostate,
penile and testis
Date Fri, 23.10.2026
Chairs Thomas Hwang (Boston, United States of America),
Edmond M. Kwan (Melbourne, Australia),
Alison H. Reid (Sutton, United Kingdom)
Room Bilbao Auditorium - Hall 3
Time 13:30 - 15:00
[Slide 1]
ESMO 2026 / MADRID
EVIDENCE NOTES
[ESMO Congress Madrid 2026 logo]
PRESIDENTIAL SYMPOSIUM I / LBA2
VOLGA
Perioperative durvalumab with neoadjuvant enfortumab vedotin is topline-positive for EFS and OS in cisplatin-ineligible or cisplatin-declining muscle-invasive bladder cancer.
Presentation 24 October 2026 16:30 Madrid | 17:30 Istanbul
Presenter Thomas Powles
01 PATIENTS
• Muscle-invasive bladder cancer (MIBC)
• Ineligible for or declined cisplatin-based chemotherapy
• Planned for curative-intent radical cystectomy
02 STUDY DESIGN
• Phase 3, randomized, open-label
• Global
• n = 695 (three arms)
• Randomization 1:1:1
03 TREATMENT ARMS
Arm 1 EV + durvalumab + tremelimumab
• Neoadjuvant enfortumab vedotin + durvalumab + tremelimumab
• Radical cystectomy
• Adjuvant durvalumab + tremelimumab
Arm 2 EV + durvalumab
• Neoadjuvant enfortumab vedotin + durvalumab
• Radical cystectomy
• Adjuvant durvalumab
Control Surgery ± approved adjuvant therapy
• Radical cystectomy
• With or without approved adjuvant therapy (according to current standards)
04 WHAT IS KNOWN
• Planned interim analysis / company topline.
• Arm 2 (EV + durvalumab) vs control: met EFS and showed a statistically significant and clinically meaningful OS benefit.
• Arm 1 (EV + durvalumab + tremelimumab) vs control: met EFS, but OS showed only a favourable trend and was not statistically significant at this interim analysis.
NOT YET DISCLOSED
• Hazard ratios, 95% confidence intervals and p values
• Absolute EFS and OS differences
• Pathologic complete response (pCR) and downstaging rates
• Detailed grade 3+ toxicity and discontinuation rates
05 CLINICAL READOUT
The key issue is not only that the study is positive.
How large is the absolute EFS/OS gain when enfortumab vedotin is given only neoadjuvantly, and does the added treatment burden and toxicity justify the regimen?
Does adding tremelimumab provide meaningful additional value?
Data status: company topline + ESMO 2026 programme. Full LBA2 presentation pending.
Source: AstraZeneca topline (14 May & 25 Sep 2026) | ESMO 2026 programme | VOLGA (NCT04960709)
drozdogan.com
Congress news · Scientific summaries · Clinical perspective
[Slide 1]
Perioperative apalutamide (APA) plus androgen deprivation therapy (ADT) with radical prostatectomy plus pelvic lymph node dissection (RP + PLND) vs RP + PLND alone in patients (pts) with high-risk localized or locally advanced prostate cancer (HR LPC/LAPC): PROTEUS Substudy
Saturday, 24 Oct 2026
10:57 - 11:07
Barcelona Auditorium - Hall 9
[buttons:] Saved | Note
[Slide 1]
KEYNOTE-564
ESMO 2026
Seven Years Later... Are Patients Living Longer?
MV Onco
[Illustration: sutured kidney, vial labeled "ONE YEAR OF PEMBROLIZUMAB", a path with milestone stones 1 YEAR, 2, 3, 5, 6, 7 YEARS leading to a figure walking toward a sunrise]
7-YEAR DISEASE-FREE SURVIVAL
57.2% vs 44.6%
7-YEAR OVERALL SURVIVAL
82.3% vs 76.6%
Pembrolizumab vs Placebo
LESS RECURRENCE. MORE PATIENTS ALIVE.
KEYNOTE-564 — The survival benefit endures.
[Slide 2]
KEYNOTE-564 | ESMO 2026
PART 1/2
Seven Years Later — Are Patients Living Longer?
MV Onco
1. WHY KEYNOTE-564?
• Clear-cell renal cell carcinoma (ccRCC).
• Recurrence remains a concern after nephrectomy.
• Adjuvant pembrolizumab improved DFS and OS in earlier analyses.
THE QUESTION: DOES THE BENEFIT LAST?
2. WHAT WAS THE STUDY?
Phase III | Randomized | N = 994
PEMBROLIZUMAB (n = 496) 200 mg IV every 3 weeks
versus
PLACEBO (n = 498)
Up to 17 cycles (~1 year).
• Primary endpoint → DFS
• Key secondary endpoint → OS
3. WHY IS THIS UPDATE IMPORTANT?
• Earlier analyses established DFS and OS benefit.
• ESMO 2026 — FINAL ANALYSIS
• Median follow-up: 85.9 months
Approximately 7.2 years.
• Data cutoff: February 4, 2026.
DO THE BENEFITS REMAIN DURABLE?
4. DID RECURRENCE DECREASE?
YES — DFS BENEFIT MAINTAINED
• 7-year DFS: 57.2% vs 44.6%
Pembrolizumab vs Placebo
• HR 0.68 (95% CI 0.56–0.82)
→ 32% lower DFS-event hazard.
→ 12.6 percentage-point absolute difference.
• Median DFS: NR vs 68.3 months.
5. DID PATIENTS LIVE LONGER?
YES — OS BENEFIT MAINTAINED
• 7-year OS: 82.3% vs 76.6%
Pembrolizumab vs Placebo
• HR 0.70 (95% CI 0.53–0.92)
→ 30% lower death hazard.
→ 5.7 percentage-point absolute difference.
• Median OS: NR in both arms.
TAKE-HOME
One year of adjuvant pembrolizumab delivers durable DFS and OS benefit in appropriately selected high-risk ccRCC.
KEYNOTE-564 | Phase III | NCT03142334 | ESMO 2026 | PART 1/2
[Slide 3]
KEYNOTE-564 | ESMO 2026
PART 2/2
Who Benefits Most — And Is Practice Changing?
MV Onco
1. WHO BENEFITED FROM PEMBROLIZUMAB?
DFS BENEFIT ACROSS RISK GROUPS
Intermediate-high risk → HR 0.71 (95% CI 0.58–0.87)
High risk → HR 0.54 (95% CI 0.31–0.94)
M1 NED → HR 0.50 (95% CI 0.26–0.96)
All three DFS estimates favor pembrolizumab.
2. DID EVERY SUBGROUP LIVE LONGER?
OVERALL SURVIVAL — IMPORTANT DIFFERENCE
Intermediate-high risk → HR 0.66 (95% CI 0.48–0.91)
High risk → HR 0.92 (95% CI 0.44–1.90)
M1 NED → HR 0.54 (95% CI 0.19–1.53)
CAUTION: OS benefit is established overall, but NOT statistically demonstrated in every subgroup.
3. WHAT ABOUT M1 NED?
M1 NED = METASTATIC, NO EVIDENCE OF DISEASE
Metastases completely resected.
DFS HR → 0.50
OS HR → 0.54
→ Encouraging recurrence reduction.
→ OS estimate remains uncertain.
DFS BENEFIT ≠ PROVEN SUBGROUP OS BENEFIT
4. ANY NEW SAFETY CONCERNS?
Median follow-up: 85.9 months
No new serious treatment-related adverse events reported.
However:
• Immune-related toxicity remains relevant.
• Some endocrine toxicities may be permanent.
Adjuvant treatment requires careful patient selection.
5. TAKE-HOME
KEYNOTE-564 REINFORCES THE STANDARD OF CARE
At approximately 7 years:
DFS HR → 0.68 OS HR → 0.70
One year of pembrolizumab provides durable DFS and OS benefit.
Subgroup OS estimates require cautious interpretation.
THE MESSAGE:
Adjuvant pembrolizumab remains a standard option for appropriately selected high-risk ccRCC after surgery.
KEYNOTE-564 | Phase III | NCT03142334 | ESMO 2026 | PART 2/2
[Slide 1]
The drug's own target predicts who it works for.
322 people with metastatic urothelial cancer treated in routine care. Median survival 21.5 months with high tumour NECTIN4 RNA versus 14.2 months with low. NECTIN4 did not track outcomes in 232 people given pembrolizumab alone.
[Forest plot, x-axis log scale 0.3 / 0.5 / 0.7 / 1.0, dashed line at 1.0 labelled "no difference"]
NECTIN4 high vs low unadjusted | 0.67 (0.46 to 0.98)
NECTIN4 high vs low adjusted | 0.62 (0.41 to 0.93)
Mutation burden high vs low | 0.57 (0.33 to 0.96)
Either marker high vs both low | 0.61 (0.42 to 0.88)
Hazard ratio for death, first-line enfortumab vedotin + pembrolizumab
Source: Cho et al., Eur Urol 2026, doi 10.1016/j.eururo.2026.08.005. Retrospective, not a randomised comparison.
[Slide 1]
Perioperative IMFINZI® (durvalumab) plus neoadjuvant enfortumab vedotin granted Priority Review in the US for patients with muscle-invasive bladder cancer
PUBLISHED
25 September 2026
Based on VOLGA Phase III trial results which demonstrated statistically significant and clinically meaningful improvements in event-free survival and overall survival
[Slide 1]
De Novo vs Metachronous Metastatic Prostate Cancer (mPC): A Comprehensive Clinicogenomic Analysis
ESMO 2026 Poster #2225
Panagiotis J. Vlachostergios, Anthony V. Serritella, Amy K. Taylor, John M. Floberg, Yingying Yu, Stamatina Fragkogianni, Kayla Viets Layng, Rana R. McKay, David F. Jarrard, Glenn Liu, Joshua M. Lang, Christos E. Kyriakopoulos
[affiliations: University of Ioannina; Weill Cornell Medicine; University of Wisconsin; Tempus AI; UC San Diego; Henry Dunant Hospital Center, Athens — small text]
INTRODUCTION
❑ The differences between de novo and metachronous mPC are incompletely characterized.
❑ This study compared demographic, clinical, molecular, and immunologic features between de novo and metachronous mPC.
METHODS
The Tempus Lens Platform was used to query the multimodal de-identified database to establish and subsequently analyze a cohort of patients diagnosed with mPC who underwent genomic profiling with xT (DNA) and xR (RNA) (n = 6,306).
Patients were classified as de novo (Stage IV at diagnosis) or metachronous (Stage I–III at diagnosis with progression to Stage IV >180 days later).
De Novo n = 6,171 Metachronous n = 135
❑ Immune cell proportions were estimated from RNA using quanTIseq.
❑ Differential gene expression analyses were conducted using Wilcoxon rank-sum tests with Benjamini-Hochberg correction.
❑ Gene set enrichment analysis was conducted using the Hallmark libraries.
❑ Groups were compared using Wilcoxon rank-sum tests or chi-squared tests as appropriate.
RESULTS
Figure 1. Treatment with prostatectomy or radiation was more common in patients with metachronous disease (prostatectomy: 57% vs 5.2%, radiotherapy: 92% vs 22%, p<0.001).
Figure 2. Treatment with upfront chemotherapy with ADT +/- ARPI was more common in de-novo metastatic pts (15.7% vs 8.1%, p=0.037).
Figure 3. Metachronous pts were enriched for APLNR (13% vs 4.7%, p<0.001) and ZMYM3 somatic alterations (11% vs 4.8%, p<0.001), while most canonical prostate cancer drivers (e.g., TP53, PTEN, ERG) had a similar frequency between groups.
[Fig 3 bar labels, de novo/metachronous %: APLNR 4.5/12.6; ZMYM3 4.7/11.1; LRP1B 9.4/14.8; FOXA1 13.9/20.0; SPOP 10.6/10.4; TP53 32.2/34.1; PTEN 25.6/26.7; ERG 36.1/39.3 — small text, verify against source]
Figure 4. Metachronous pts demonstrated increased regulatory T cell and natural killer cell infiltration as estimated by quanTIseq (p<0.001).
Figure 5. Inflammatory signaling (TNFα/NF-κB) and KRAS-related pathways were enriched in metachronous pts.
SUMMARY
❑ Metachronous mPC is a distinct entity characterized by lower PSA at diagnosis, greater prior local therapy exposure, unique genomic alterations, and a more immunologically suppressed tumor microenvironment compared to de novo disease.
❑ Future work should investigate therapeutic vulnerabilities and differences in survival associated with metachronous vs. de novo disease.
ACKNOWLEDGMENTS: We thank Vanessa Nepomuceno, PhD for assistance with poster preparation.
[Slide 2]
Clinicogenomic Differences Between Early-Onset (EO-PCa) and Average-Onset Prostate Cancer (AO-PCa): A Large-Scale Retrospective Cohort Study
ESMO 2026 Poster #2256
Christos E. Kyriakopoulos, Panagiotis J. Vlachostergios, Anthony V. Serritella, Amy K. Taylor, John M. Floberg, Yingying Yu, Stamatina Fragkogianni, Kayla Viets Layng, Rana R. McKay, David F. Jarrard, Glenn Liu, Joshua M. Lang
[affiliations: UW–Madison; Henry Dunant Hospital Center, Athens; University of Ioannina; Weill Cornell; Tempus AI; UC San Diego — small text]
INTRODUCTION
❑ Early-onset prostate cancer (EO-PCa) is increasingly recognized as biologically distinct, but its clinical behavior, molecular features, and outcomes relative to average-onset (AO-PCa) disease remain incompletely characterized.
SUMMARY
• EO-PCa exhibits distinct clinical and molecular characteristics compared to AO-PCa.
• OS appears to be driven by a combination of age and tumor biology.
METHODS
The Tempus Lens platform was used to query the de-identified, multimodal database for patients diagnosed with metastatic prostate cancer (N= 6,967) tested with Tempus xT (DNA-seq) and xR (RNA-seq).
Eligible de novo metastatic patients had a sample collected within 60 days of diagnosis and were stratified by onset age (EO-PCa ≤55 years; AO-PCa >55 years).
❑ Clinicogenomic characteristics were compared using Wilcoxon rank-sum tests or chi-squared tests as appropriate.
❑ Real-world overall survival (rwOS) was defined as the time from sample collection to death or loss to follow up.
❑ Median rwOS (mOS) was estimated using Kaplan-Meier (KM) curves and compared using log-rank tests. Hazard ratios (HR) were estimated using Cox proportional hazards models. Risk set adjustment was used to account for immortal time bias.
RESULTS
Figure 1. Frequency of primary radiotherapy or prostatectomy treatment in EO-PCa vs. AO-PCa. Patients with EO-PCa were more likely to undergo primary treatment (radiotherapy: 37.2% vs 26.4%; prostatectomy: 18.7% vs 10.4%, p<0.001).
Figure 2. Selected molecular differences between EO-PCa and AO-PCa. EO-PCa was enriched for germline BRCA2 variants (4.8% vs 2.6%, p=0.019), TMPRSS2 fusions (39.7% vs 34.7%, p=0.015), and ERG fusions (41.1% vs 36.6%, p=0.031). Somatic FOXA1 (15.4% vs 9.4%, p<0.001) and SPOP mutations (11.1% vs. 8.2%, p=0.033) were more common in AO-PCa.
Figure 3. Median real-world OS for EO-PCa vs. AO-PCa. EO-PCa was associated with longer mOS in the overall cohort [42 vs 32 months, HR = 1.51 (95% CI 1.26-1.81), p<0.001] and in SPOP-alt and TP53-alt sub-cohorts.
[Fig 3 bars, EO/AO months: Overall 42.0/32.0; SPOP alt 67.1/52.0; TP53 alt 33.8/25.9]
Figure 4. Association of SPOP and TP53 alterations with real-world OS in AO-PCa and EO-PCa. SPOP alterations were prognostic for favorable mOS compared to wild-type (AO-PCa: 52 months vs 30.7 months, p<0.001; EO-PCa: 67.1 months vs 41.7 months, p= 0.41). TP53 alterations were prognostic for worse mOS compared to wild-type (AO-PCa: mOS 25.9 months vs 37.9 months, p<0.001; EO-PCa: mOS 33.8 vs 55.9 months, p<0.001).
[Fig 4: four KM panels — A. SPOP Alterations in AO-PCa (Age >55); B. SPOP Alterations in EO-PCa (Age <=55); C. TP53 Alterations in AO-PCa (Age >55); D. TP53 Alterations in EO-PCa (Age <=55); panel p-values printed: A p = 1.79e-09, B p = 0.414, C p = 2.4e-25, D p = 0.000649 — small text]
ACKNOWLEDGMENTS: We thank Vanessa Nepomuceno, PhD for assistance with poster preparation.
[Slide 1]
BIOTECH NEWS
[Circular illustration of a translucent human torso showing the bladder with a glowing orange tumour]
FDA grants Priority Review for perioperative immunotherapeutic combination in bladder cancer
NeoBiotechnologies
Your Partner in Proteome Research
Source: OncLive
[Slide 1]
ESMO26
TOP TEN BY ONCOALERT
GU ONCOLOGY
[OncoAlert 360 logo - Oncology / For Colleagues / By Colleagues]
WWW.ONCOALERT360.COM
LBA2 | VOLGA: PERIOPERATIVE DURVALUMAB WITH OR WITHOUT TREMELIMUMAB PLUS NEOADJUVANT ENFORTUMAB VEDOTIN IN MUSCLE-INVASIVE BLADDER CANCER: RESULTS FROM THE PHASE 3 VOLGA TRIAL
LBA4 | DASL-HICAP: DAROLUTAMIDE WITH ADT AND DEFINITIVE OR SALVAGE LOCOREGIONAL RADIATION THERAPY FOR LOCALISED, VERY HIGH-RISK PROSTATE CANCER: INTERIM ANALYSIS OF THE PHASE 3 DASL-HICAP TRIAL (ANZUP1801)
3586O | LITESPARK-012: FIRST-LINE PEMBROLIZUMAB + LENVATINIB + BELZUTIFAN OR MK-1308A + LENVATINIB IN ADVANCED RCC: RANDOMIZED OPEN-LABEL PHASE 3 LITESPARK-012 STUDY
3587O | LITESPARK-011: FINAL ANALYSIS OF THE PHASE 3 LITESPARK-011 STUDY: BELZUTIFAN PLUS LENVATINIB VERSUS CABOZANTINIB FOR ADVANCED RCC AFTER ANTI-PD-(L)1 THERAPY
LBA56 | CAPITELLO-281: CAPIVASERTIB + ABIRATERONE VS PLACEBO + ABIRATERONE IN PATIENTS WITH PTEN-DEFICIENT METASTATIC HORMONE-SENSITIVE PROSTATE CANCER: UPDATED OVERALL SURVIVAL FROM CAPITELLO-281
3592O | AK112: EFFICACY AND SAFETY OF AK112 (IVONESCIMAB), A PD-1/VEGF BISPECIFIC ANTIBODY, AS FIRST-LINE TREATMENT FOR IMDC FAVORABLE-RISK ADVANCED RCC: RESULTS FROM A PHASE IB/II STUDY
LBA53 | PROTEUS: PERIOPERATIVE APALUTAMIDE PLUS ADT WITH RADICAL PROSTATECTOMY AND PELVIC LYMPH NODE DISSECTION VS RP + PLND ALONE IN HIGH-RISK LOCALIZED OR LOCALLY ADVANCED PROSTATE CANCER: PROTEUS SUBSTUDY
LBA88 | PE-PE: PERIOPERATIVE PEMBROLIZUMAB PLUS METASTASIS-DIRECTED THERAPY VERSUS MDT ALONE IN OLIGOMETASTATIC RENAL CELL CARCINOMA: THE RANDOMIZED PHASE II PE-PE TRIAL
4734O | KEYNOTE-B15: CTDNA ANALYSIS OF THE PHASE 3 KEYNOTE-B15 TRIAL: NEOADJUVANT AND ADJUVANT ENFORTUMAB VEDOTIN + PEMBROLIZUMAB FOR CISPLATIN-ELIGIBLE MUSCLE-INVASIVE BLADDER CANCER
3591RO | SWOG S2200: FIRST RESULTS OF SWOG S2200, A RANDOMIZED PHASE II STUDY COMPARING CABOZANTINIB WITH OR WITHOUT ATEZOLIZUMAB IN METASTATIC PAPILLARY RENAL CELL CARCINOMA
3588O | XMAB819: PHASE 1 RESULTS OF XMAB819, A NOVEL ENPP3 X CD3 BISPECIFIC, IN ADVANCED CLEAR CELL RENAL CELL CARCINOMA
4736O | ENERGIZE: RESULTS FROM A PHASE 3 TRIAL OF NEOADJUVANT CHEMOTHERAPY ALONE VS IN COMBINATION WITH NIVOLUMAB FOLLOWED BY POSTSURGICAL ADJUVANT NIVOLUMAB IN MUSCLE-INVASIVE BLADDER CANCER
4735O | KEYNOTE-866: PERIOPERATIVE PEMBROLIZUMAB OR PLACEBO + NEOADJUVANT CISPLATIN AND GEMCITABINE IN PATIENTS WITH MUSCLE-INVASIVE BLADDER CANCER: THE DOUBLE-BLIND, PHASE 3 KEYNOTE-866 STUDY
Senior Faculty
[headshots] Dr Morgan Clin Onc | Dr Choueiri Med Onc | Dr Gillessen Med Onc | Dr Agarwal Med Onc | Dr Zhang Med Onc | Dr Powles Med Onc | Dr Rini Med Onc | Dr Grivas Med Onc | Dr Merseburger Urologist | Dr Omlin Med Onc | Dr Apolo Med Onc | Dr Necchi Med Onc | Dr Heng Med Onc | Dr Pal Med Onc | Dr Grande Med Onc | Dr Hammers Med Onc
Faculty
[headshots] Dr Gandur Med Onc | Dr Membribes Med Onc | Dr Nizam Med Onc
[Slide 1]
CLINICAL CANCER RESEARCH
ARTICLE NAVIGATION
RESEARCH ARTICLE | SEPTEMBER 09 2026
Integrating NECTIN4 Amplification With Membranous Nectin-4 Expression to Develop a Scoring System for Predicting Enfortumab Vedotin Response in Urothelial Carcinoma [open access icon]
Niklas Klümper; Thomas Büttner; Sebastian Rauch; Stefanie Zschäbitz; Florian Roghmann; Christian Bolenz; Fabienne Lange; Patricia Rausch; Friedemann Zengerling; Nadine Gaisa; Oliver Hahn; Constantin Schwab; Anna Scherping; Marieta Toma; Hendrik Heers; Phillipp Ivanyi; Guenter Niegisch; Camilla Marisa Grunewald; Christopher Darr; Pia Paffenholz; Richard Weiten; Susanne Füssel; Christian Thomas; Marcus Sondermann; Ulrich Sommer; Kerstin Junker; Katrin Schlack; Jozefina Casuscelli; Can Aydogdu; Dora Niedersüß-Beke; Steffen Rausch; Christoph Kuppe; Joshua Meeks; Bonnie Choy; Sarmad Sadeghi; Parkash Gill; Manuel Ritter; Johannes Brägelmann; Michael Hölzel; Arndt Hartmann; Viktor Grünwald; Jonas Saal; Markus Eckstein
Check for updates
+ Author & Article Information
Clin Cancer Res (2026)
https://doi.org/10.1158/1078-0432.CCR-26-0093
Article history
[Slide 2]
OncoAlert 360 · GUARD INTERNATIONAL SYMPOSIUM 2026 · #GUARDSymposium2026 16-18 SEP
Basic principles guiding a modern approach to patients with MIBC
▪ MIBC: ~25% de novo + ~20% progressing from NMIBC (implications for therapeutic attrition (impact of prior IO/ADCs exposure on subsequent strategies)1,2
▪ The (old) pardigm of cisplatin eligibility: 50% of pts with MIBC slated to start neoadjuvant chemotherapy
▪ Expanding eligibility of neoadjuvant therapies due to IO/ADC use
▪ The growing % of chemotherapy refusals due to alternative options
▪ The evolving paradigm from exclusive neoadjuvant/adjuvant approach to a sandwich strategy (with future implications for surgery)
#guardsymposium2026 X @GuardConsortium · GUARD CONSORTIUM
1. Roviello G, et al. Nat Rev Urol. 2024 Oct;21(10):580-592; 2. https://uroweb.org/guidelines/non-muscle-invasive-bladder-cancer
Presented by: [Italian flag] Dr. Andrea Necchi · IRCCS San Raffaele Hospital
[Slide 3]
OncoAlert 360 · GUARD INTERNATIONAL SYMPOSIUM 2026 · #GUARDSymposium2026 16-18 SEP
Unmet Needs Across the Disease Spectrum
[Three columns]
▪ Only one-third of patients with NMIBC receive IVS BCG according to guidelines[1]
▪ Many of those with NMIBC who are unresponsive to BCG experience recurrence or progression[2]
[highlighted box] ▪ Close to half of patients with MIBC worldwide may not receive curative-intent therapy[3]
▪ Patients who have undergone RC for MIBC often have impaired HRQoL and a high risk of recurrence[4,5]
▪ More than half of patients with mUC may not receive 1L systemic treatment[6,7]
▪ Many patients with mUC who progress on 1L or 2L therapy do not receive subsequent treatment[6,7]
[Bottom box]
▪ Development of effective, safe, and durable IVS treatment remains a critical unmet clinical need for patients who want to avoid RC
▪ Effective approaches post-RC are key to lowering the risk of recurrence
▪ Strategies for treatment sequencing after metastatic progression are needed
▪ Clinical trial enrollment allows for modern advances to reach patients
1L, first line; 2L, second line; BCG, bacille Calmette-Guérin; HRQoL, health-related quality of life; IVS, intravesical; MIBC, muscle-invasive bladder cancer; mUC, metastatic urothelial carcinoma; NMIBC, non–muscle-invasive bladder cancer; RC, radical cystectomy.
1. Tyson M, et al. J Clin Oncol. 2019;37(suppl 15):e16012; 2. Shore ND, et al. Urol Oncol. 2021;39:642-663; 3. Westergren DO, et al. J Urol. 2019;202:905-912; 4. Choi H, et al. Transl Androl Urol. 2020;9:2997-3006; 5. Rouprêt M, et al. Eur Urol. 2021;79:62-79; 6. Morgans AK. Ann Oncol. 2021;32(suppl 5):704P; 7. Bilen M. Ann Oncol. 2021;32(suppl 5):701P.
#guardsymposium2026 X @GuardConsortium · GUARD CONSORTIUM
Presented by: [Italian flag] Dr. Andrea Necchi · IRCCS San Raffaele Hospital
[Slide 4]
OncoAlert 360 · GUARD INTERNATIONAL SYMPOSIUM 2026 · #GUARDSymposium2026 16-18 SEP
Conclusions
▪ Sandwich (perioperative) therapy remains the standard of care for patients with muscle-invasive bladder cancer (MIBC), supported by level 1 evidence
▪ Current data do not yet support safe de-escalation of perioperative systemic therapy whenever EVP or Durva-GC is initiated
▪ Since pCR is achieved in ~35-60% of patients treated with neoadjuvant therapy, a selected cohort of patients may forgo radical cystectomy and remain on stringent surveillance
▪ Several attemps have been/are being undertaken with the aim of removing the adjuvant or surgical component in selected patients
▪ Future strategies may focus on building from neoadjuvant EVP backbone
#guardsymposium2026 X @GuardConsortium · GUARD CONSORTIUM
Presented by: [Italian flag] Dr. Andrea Necchi · IRCCS San Raffaele Hospital
[Slide 1]
MIBC
VOLGA
Sep 25, 2026
BREAKING
[stamp graphic] FDA PRIORITY REVIEW
AstraZeneca [logo]
Perioperative Imfinzi plus neoadjuvant enfortumab vedotin granted Priority Review in the US for patients with muscle-invasive bladder cancer
LARVOL
[Slide 1]
EUROPEAN UROLOGY | LeapSpace
[search bar: Search for...]
BRIEF REPORT · Articles in Press, September 24, 2026
Pretreatment Tumor NECTIN4 RNA Expression Is Associated with First-line Enfortumab Vedotin Plus Pembrolizumab Efficacy in Metastatic Urothelial Cancer
Byuri Angela Cho a · Curtis J. Perry b · Seong-Keun Yoo c · Jacob Mercer d · Christina Thai d · Guru Sonpavde e · Paul A. Fields d · Alan Tan d · Daniel P. Petrylak f · Matthew D. Galsky g Show less
Affiliations & Notes | Article Info
[Slide 1]
#ESMO2026
Jonathan Chatzkel, MD
Presents: ctDNA analysis of the
Phase 3 KEYNOTE-B15 trial:
neoadjuvant and adjuvant
(neoadj-adj) enfortumab vedotin
(EV) + pembrolizumab (pembro)
for participants (pts) with
muscle-invasive bladder cancer
(MIBC) who are eligible for
cisplatin
Fri., Oct. 23
1:30 to 3:00 p.m. CEST
Bilboa Auditorium - Hall 3
MOFFITT CANCER CENTER
MOFFITT AT ESMO 2026
[headshot of presenter]
[Slide 1]
FDA Grants
Priority Review to Durvalumab + Enfortumab Vedotin in Muscle-Invasive Bladder Cancer
OncoDaily
[background: globe over stock-ticker/candlestick chart graphic]
[Slide 1]
OncoDaily
EVOLUTE
Enfortumab Vedotin in Older Adults With Advanced Urothelial Carcinoma
[illustration: older man in suit at the entrance of a circular maze with a tumour-cell sphere at its centre]
[Slide 2]
RAPID ORAL PRESENTATIONS
• Distinguishing clonal hematopoiesis (CH) from tumor homologous recombination repair (HRR) alterations in liquid biopsy: Implications for PARP inhibitor (PARPi) use in metastatic castration-resistant prostate cancer (mCRPC)
[Foundation Medicine logo mark, bottom right; decorative glass-bauble background]
[Slide 3]
RAPID ORAL PRESENTATIONS
• Utility of ctDNA tumor fraction (TF) as a prognostic biomarker in TALAPRO-3: Phase 3 study of talazoparib (TALA) + enzalutamide (ENZA) vs placebo (PBO) + ENZA in patients (pts) with homologous recombination repair (HRR) gene–mutated metastatic castration-sensitive prostate cancer (mCSPC)
[Foundation Medicine logo mark, bottom right; decorative glass-bauble background]
[Slide 1]
touchONCOLOGY [logo]
"
ESMO is always a highlight of the oncology calendar, bringing together the latest science, fresh perspectives and the experts shaping the future of cancer care. In genitourinary oncology, I am particularly looking forward to addressing key questions in perioperative and curative-intent treatment across muscle-invasive bladder cancer and high-risk localised prostate cancer. The real value of this meeting lies in turning scientific progress into better clinical decisions and, ultimately, better outcomes for our patients.
[headshot photo]
Prof Axel S Merseburger
Editor-in-Chief, touchONCOLOGY
ESMO 2026
MADRID, SPAIN
23-27 OCTOBER 2026
[Slide 1]
PRESS RELEASE
Merck and Moderna Will Present Results From Landmark Phase 3 INTerpath-001 Trial for Intismeran Autogene Plus KEYTRUDA® (pembrolizumab) at ESMO 2026 Presidential Symposium
moderna
MERCK
[Slide 1]
Recurrence-Free Survival, ITT Population
HR 0.58 (95% CI 0.45–0.75)
P < 0.001 (two sided)a
24-month landmark (dashed line): 82.2% (95% CI 79.3–84.8) [intismeran arm, teal]; 70.0% (95% CI 65.0–74.5) [placebo arm, blue]
N | Events, n (%)
Intismeran + pembrolizumab | 757 | 136 (18.0%)
Placebo + pembrolizumab | 380 | 111 (29.2%)
No. at risk (months 0/6/12/18/24/30/35):
Intismeran + pembrolizumab: 757, 683, 646, 618, 136, 10, 0
Placebo + pembrolizumab: 380, 341, 302, 282, 72, 3, 0
aMultiplicity-adjusted significance level: two-sided 0.024692.
ITT: all randomized patients according to the arm to which they were assigned.
RFS: time from randomization to the first occurrence of any recurrence or death from any cause. Data cutoff date: June 30, 2026 (median study follow-up, 24.6 mo).
Presented by: Georgina V. Long, Melanoma Institute Australia
Content of this presentation is copyright and responsibility of the author. Permission is required for re-use.
[ESMO Congress Madrid 2026 logo]
[Survival data captured as a table — no point estimates read from the curve]
Endpoint: Recurrence-free survival (RFS), ITT population
Intismeran + pembrolizumab | 757
Placebo + pembrolizumab | 380
HR: 0.58
HR CI: 0.45–0.75
P: <0.001 (two sided); multiplicity-adjusted significance level two-sided 0.024692
{'timepoint': '24 months', 'arm': 'Intismeran + pembrolizumab', 'value': '82.2%', 'ci': '79.3–84.8'}
{'timepoint': '24 months', 'arm': 'Placebo + pembrolizumab', 'value': '70.0%', 'ci': '65.0–74.5'}
Note: Data cutoff June 30, 2026; median study follow-up 24.6 mo. Presented by Georgina V. Long. Medians not printed.
[Slide 1]
WHEN ONCOLOGY MOVES WALL STREET
MV Onco
PART 01/04 — WHY DID MODERNA STOCK JUMP?
[Cartoon of a surprised man in a suit at a desk looking at a screen; speech bubble: "Why the sudden jump?"]
[Screen graphic:] moderna (MRNA) $168.32 ↑ 9.27% September 21, 2026 • Intraday snapshot [rising green line/bar chart]
1 WHAT TRIGGERED THE RISE?
• PERSONALIZED mRNA CANCER VACCINE
Intismeran autogene (V940)
• Moderna + Merck
• Phase III — Melanoma
• RFS + DMFS endpoints already met.
• Now selected for ESMO 2026 Presidential Symposium.
• October 24 — Detailed results expected.
3 WHAT HAPPENS NEXT?
OCTOBER 24, 2026
4:30 PM CEST — ESMO Presidential Symposium
7:00 PM CEST — Moderna investor webcast
Investors will watch:
• Magnitude of clinical benefit
• Safety and approval prospects
• Commercial potential
4 FINAL STORY HOOK
HOW CAN AN mRNA VACCINE FIGHT CANCER?
Part 02 — The Science
[Slide 2]
WHEN ONCOLOGY MOVES WALL STREET
MV Onco
PART 02/04 — HOW DOES THE mRNA CANCER VACCINE WORK?
1 THE BIG QUESTION
Tumors already have neoantigens. Why vaccinate?
Tumor mutations → abnormal proteins → neoantigen peptides → HLA-I presentation.
But antigen presence ≠ effective immunity. Why?
Weak T-cell priming • Few tumor-reactive T cells • Immune suppression.
Vaccine goal → strengthen tumor-specific T-cell immunity.
2 HOW IS THE VACCINE MADE?
INTISMERAN AUTOGENE (V940)
Moderna + Merck
Tumor tissue + normal blood
↓
Identify tumor-specific mutations
↓
Select up to 34 patient-specific neoantigen sequences.
↓
Encode selected antigens into synthetic mRNA
↓
Package mRNA inside lipid nanoparticles
LNP = lipid nanoparticle; protects and delivers mRNA.
One patient → one individualized vaccine design.
3 WHAT HAPPENS AFTER INJECTION?
Intramuscular mRNA-LNP injection
↓
Uptake by local cells and antigen-presenting cells
↓
mRNA released into cytoplasm
↓
Ribosomes produce encoded neoantigen proteins
↓
Proteins processed into peptides
↓
Dendritic cells present neoantigen peptides
HLA-I → CD8+ T-cell activation
HLA-II → CD4+ T-cell activation
Direct presentation or cross-presentation.
Important: mRNA does not alter DNA.
4 HOW DOES THE TUMOR GET KILLED?
Activated CD8+ T cells enter circulation
↓
Reach residual tumor cells
↓
Recognize matching neoantigen-HLA-I complexes on tumor cells
↓
Perforin + granzymes → induce tumor-cell apoptosis.
5 WHY COMBINE WITH PEMBROLIZUMAB?
Vaccine → primes tumor-specific T cells.
Pembrolizumab → blocks PD-1 signaling, helping restore T-cell activity.
Together → potentially stronger antitumor immunity.
After surgery, the goal is to eliminate microscopic residual disease and reduce recurrence.
Pembrolizumab cannot overcome every immune-escape mechanism.
The vaccine remains investigational.
FINAL TAKE-HOME
The vaccine does not create new tumor targets.
It strengthens T-cell recognition of neoantigens already present in the cancer.
NEXT: DID IT ACTUALLY WORK?
Part 03 — The Clinical Evidence.
[Slide 3]
WHEN ONCOLOGY MOVES WALL STREET
PART 03/04 — DID THE mRNA VACCINE ACTUALLY WORK?
MV Onco
1. THE FIRST RANDOMIZED TEST
KEYNOTE-942 / mRNA-4157-P201
Phase IIb • 157 patients
Completely resected high-risk melanoma.
INTISMERAN AUTOGENE + PEMBROLIZUMAB versus PEMBROLIZUMAB ALONE
The question:
Can personalized vaccination reduce recurrence beyond PD-1 blockade?
2. DID IT PREVENT RECURRENCE?
RECURRENCE-FREE SURVIVAL (RFS)
At approximately five-year follow-up:
HR 0.51
95% CI 0.294—0.887
49% relative reduction in hazard of recurrence or death.
3. DID IT REDUCE DISTANT METASTASES?
DISTANT METASTASIS-FREE SURVIVAL (DMFS)
HR 0.41
95% CI approximately 0.20—0.84
59% relative reduction in hazard of distant metastasis or death.
4. HOW DURABLE WAS THE BENEFIT?
Four-year recurrence-free survival:
72.4% vs 49.1%
Vaccine + pembrolizumab versus pembrolizumab.
A meaningful absolute separation in the reported estimate.
The favorable recurrence and distant-metastasis signals persisted with longer follow-up.
But overall survival benefit was not established.
5. WHY DID THIS MATTER?
A personalized mRNA vaccine demonstrated encouraging randomized clinical activity.
Not simply an immune response in the laboratory.
But Phase IIb was relatively small.
A larger Phase III confirmation was essential.
FINAL TAKE-HOME
RFS HR 0.51 DMFS HR 0.41
Encouraging durable Phase IIb evidence for personalized mRNA vaccination in melanoma.
NEXT — PHASE III, ESMO 2026 AND THE FUTURE
Part 04 — The Big Test.
[Slide 4]
WHEN ONCOLOGY MOVES WALL STREET
MV Onco
PART 04/04 — THE PHASE III MOMENT
1 FROM PHASE IIb TO PHASE III
INTerpath-001 – Phase III • 1,137 patients
• Completely resected stage IIB–IV melanoma.
• Intismeran autogene + pembrolizumab vs pembrolizumab alone.
• Randomized, double-blind trial.
• The question: Can Phase IIb benefit be confirmed?
2 THE BIG ANNOUNCEMENT
AUGUST 19, 2026 Phase III topline results announced.
• RFS endpoint MET • DMFS endpoint MET
• Statistically significant and clinically meaningful improvements reported.
• Detailed hazard ratios and absolute survival benefits not yet publicly presented.
• Positive topline ≠ complete clinical assessment.
3 WHY ESMO 2026 MATTERS
OCTOBER 24, 2026 Late-breaking Presidential Symposium.
INTerpath-001 — LBA1
What should oncologists examine?
• RFS HR + absolute benefit
• DMFS HR + absolute benefit
• Overall survival maturity
• Grade ≥3 toxicity and discontinuations
• Stage-specific outcomes
• The magnitude of benefit matters.
4 BEYOND MELANOMA
Personalized mRNA vaccination is also being investigated in other cancers.
• PANCREATIC CANCER – Phase I development.
Intismeran autogene + FOLFIRINOX.
• EARLY-STAGE NSCLC – INTerpath-014 • Phase III.
High-risk resected stage I NSCLC.
Vaccine-based adjuvant strategies under investigation.
• Success in melanoma does not guarantee success in other cancers.
5 FROM SCIENCE TO WALL STREET
MODERNA + MERCK
• Positive clinical findings create potential for:
– Regulatory submissions • New oncology treatments • Future commercial revenue
• Important questions remain:
– Can individualized manufacturing scale? • How long does production take?
– What will treatment cost? • Will the benefit justify widespread adoption?
• Moderna investor webcast — October 24, 7 PM CEST.
FINAL TAKE-HOME
PHASE IIb PROMISE
↓
PHASE III ENDPOINTS MET
↓
ESMO 2026 — DETAILED RESULTS AWAITED
↓
POTENTIAL NEW ERA OF PERSONALIZED IMMUNOTHERAPY
THE SCIENCE MOVED WALL STREET.
NOW THE DATA MUST JUSTIFY THE EXCITEMENT.
[Slide 1]
ESMO 2026 — LBA1
A CANCER VACCINE TAKES CENTRE STAGE!
— MV Onco —
PART 01/02 — THE PRESIDENTIAL OPENING
[AI-style illustration of a woman speaking at a podium in a conference hall; podium sign "ESMO 2026 SCIENCE BETTER MEDICINE BRIGHTER LIVES"; screen reads "ESMO 2026 PRESIDENTIAL SYMPOSIUM I LBA1 — INTerpath-001"; audience member thought bubble "A personalized CANCER vaccine?"]
1 WHY IS EVERYONE WATCHING?
• INTISMERAN AUTOGENE (V940)
• Moderna + Merck
• Personalized mRNA neoantigen vaccine.
• Phase III — Melanoma
• 1,137 patients.
• Resected stage IIB–IV.
• Vaccine + pembrolizumab versus pembrolizumab alone.
• Positive topline RFS + DMFS results reported.
2 THE BIG REVEAL
• OCTOBER 24, 2026
• Presidential Symposium I
• Persenter: Prof. Georgina V. Long
• Detailed Phase III results expected.
• Key questions:
• How large is the benefit?
• What about safety?
• Will practice change?
3 FINAL HOOK
CAN WE TRAIN THE IMMUNE SYSTEM TO PREVENT CANCER RECURRENCE?
Part 02 — The Evidence.
[Slide 2]
ESMO 2026 — LBA1
INTerpath-001: WILL THE VACCINE CHANGE PRACTICE?
PART 02/02 — THE EVIDENCE
MV Onco
1. THE BIOLOGICAL IDEA
Tumor mutations
↓
Patient-specific neoantigens
↓
Personalized mRNA vaccine
↓
Dendritic-cell antigen presentation
↓
Tumor-specific T-cell activation
Pembrolizumab → blocks PD-1 signalling, restoring T-cell activity.
2. THE FIRST RANDOMIZED SIGNAL
KEYNOTE-942 — Phase IIb
• 157 patients • Resected high-risk melanoma.
• Vaccine + pembrolizumab versus pembrolizumab.
• Approximately five-year follow-up:
– RFS HR 0.51
– DMFS HR 0.41
Phase IIb results — NOT Phase III estimates.
Encouraging durable reduction in recurrence and distant-metastasis hazards.
3. THE PHASE III TEST
INTerpath-001
• 1,137 patients.
• Resected stage IIB–IV melanoma.
• Randomized, double-blind.
• Vaccine + pembrolizumab versus pembrolizumab alone.
• Primary RFS endpoint MET.
• Key secondary DMFS endpoint MET.
Detailed Phase III efficacy and safety data awaited.
4. WHAT MUST ESMO REVEAL?
OCTOBER 24 — LBA1
Watch for:
• RFS + DMFS hazard ratios
• Absolute benefit and KM separation
• Grade ≥3 adverse events
• Treatment discontinuation
• Overall survival maturity
• Consistency across disease stages
Statistical significance alone does not establish practice change.
5. WHAT COMES NEXT?
• Regulatory evaluation.
• Manufacturing time + scalability.
• Cost + equitable access.
• Expansion beyond melanoma?
How much benefit does the vaccine add to pembrolizumab?
FINAL TAKE-HOME
PHASE IIb PROMISE
↓
PHASE III ENDPOINTS MET
↓
ESMO 2026 — FULL DATA AWAITED
↓
PERSONALIZED mRNA VACCINATION MAY BE APPROACHING A NEW CLINICAL MILESTONE.
[Slide 1]
What to watch at ESMO 2026
Melanoma & Skin Cancers · Madrid, 23-27 October
Session | Trial | What to watch
LBA1 - Sat 24 Oct, 16:30 - Long et al. | INTerpath-001: intismeran + pembrolizumab, adjuvant stage IIB-IV | Presidential Symposium. Topline positive for RFS and DMFS (1,137 patients). First phase 3 of an individualised mRNA neoantigen therapy. Watch the HR, the stage II subgroup and how mature OS is.
2071O - Fri 23 Oct, 16:15 - Schadendorf et al. | STARBOARD: encorafenib + binimetinib + pembrolizumab vs pembrolizumab, 1L BRAF V600 | Phase 3 triplet, results still under embargo. Does targeted therapy plus anti-PD-1 upfront finally beat anti-PD-1 alone in BRAF-mutant disease? Toxicity will weigh as much as PFS.
LBA54 - Fri 23 Oct, 16:25 - Khushalani et al. | HBI-8000-303: oral HDAC inhibitor + nivolumab vs nivolumab, advanced melanoma | Topline: significant PFS improvement (404 patients). Epigenetic priming of anti-PD-1. Watch the size of the gain, OS and how it compares with LAG-3 and CTLA-4 combinations.
2072O + LBA55 - Fri 23 Oct, 17:00 - Furness; Si et al. | TIL earlier: lifileucel + pembrolizumab in ICI-naive (final) and GC101 TIL (randomised) | Cell therapy before anti-PD-1 failure. Can TIL earn a first-line role, and does the randomised signal hold with longer follow-up?
2076RO - Sun 25 Oct, 11:14 - Witteveen et al. | NADINA: neoadjuvant ipilimumab + nivolumab vs adjuvant nivolumab, stage III | Three-year distant metastasis-free survival. After the EFS win, does the neoadjuvant advantage become fewer distant relapses? The bridge to an OS benefit.
LBA59 - Sun 25 Oct, 10:42 - Rischin et al. | C-POST: adjuvant cemiplimab vs placebo, high-risk cutaneous SCC | Updated OS and ctDNA analyses. The DFS benefit is already published. Now survival, and whether ctDNA can tell us who really needs adjuvant therapy.
LBA60 - Sun 25 Oct, 10:47 - Becker et al. | ADMEC-O: adjuvant nivolumab in Merkel cell carcinoma, mature survival + biomarkers | After ADAM and STAMP missed their endpoint at ASCO26. Mature randomised data: is there a subgroup where adjuvant anti-PD-1 in Merkel still makes sense?
2486RO - Sun 25 Oct, 10:52 - Van Dijk et al. | MATISSE 2: neoadjuvant immunotherapy for organ preservation in cutaneous SCC | Cure without mutilating surgery? Patients otherwise facing extensive surgery and radiotherapy. Watch pathological response and how many avoid the operation.
Also on the radar: ADCs after anti-PD-1, HER3-DXd (2073RO) and enfortumab vedotin + pembrolizumab (2074RO).
Source: ESMO 2026 online programme and sponsor press releases. Data under embargo until presentation. Madrid local time.
@boutrosand
[Slide 1]
[Headshot: man in white UCLA Health lab coat, glasses, grey beard, blue background]
Dr. Antonio Ribas receives ESMO Lifetime Achievement Award for contributions to cancer immunotherapy
Dr. Antoni Ribas, professor of medicine at the David Geffen School of Medicine at UCLA and director of the UCLA Health Jonsson Comprehensive Cancer Center's Tumor Immunology & Immunotherapy Program, has received the 2026 ESMO Lifetime Achievement Award for his pioneering contributions to cancer immunotherapy and translational research. His research has helped transform the treatment of melanoma and advanced the development of immunotherapies and targeted therapies across multiple cancer types.
The prestigious award from the European Society for Medical Oncology (ESMO) recognizes outstanding lifetime achievements in oncology and honors individuals whose research and education have made significant contributions to the field. Dr. Ribas will receive the award during the opening session of the ESMO 2026 Congress on October 23.
[Slide 1]
Results
1137 pts were randomized: 757 to intismeran + pembro, 380 to placebo + pembro; 726 (95.9%) received ≥1 dose of intismeran and 365 (96.1%) received ≥1 dose of placebo as planned. Median follow-up as of 30Jun2026 was 24.6 mo. Intismeran + pembro significantly improved RFS and DMFS compared with placebo + pembro (Table). Benefit was similar in stage IIB–IIIB and IIIC–IV MEL and other subgroups. For intismeran + pembro vs placebo + pembro, AEs were grade ≥3 in 23.6% vs 20.3%; 6.5% vs 5.3% discontinued both drugs simultaneously due to an AE. Most common AEs were pyrexia (52.2% vs 8.2%), injection site pain (51.0% vs 9.5%), and fatigue (38.5% vs 29.7%).
Table: LBA1
| Intismeran + pembro (N = 757) | Placebo + pembro (N = 380)
Recurrence-free survival (RFS)
24-mo rate, % (95% CI) | 82.2 (79.3–84.8) | 70.0 (65.0–74.5)
HR (95% CI) | 0.58 (0.45–0.75) | —
Two-sided P | <0.001 | —
Distant metastasis-free survival (DMFS)
24-mo rate, % (95% CI) | 88.5 (86.0–90.6) | 80.2 (75.6–84.0)
HR (95% CI) | 0.62 (0.45–0.85) | —
Two-sided P | 0.002 | —
[Slide 1]
ESMO CONGRESS 2026 · MADRID · 23–27 OCTOBER
MELANOMA & SKIN CANCER
Eight skin cancer trials to watch
Melanoma, cutaneous SCC and Merkel cell carcinoma: a personal shortlist of the studies most likely to change practice in Madrid.
[photo] Dr Mario Balsa
Skin Cancer Unit
Clínic Comprehensive Cancer Center Barcelona
NO. | TRIAL | SETTING | WHY IT MATTERS
01 | INTerpath-001 | LBA1 · Presidential Symposium | Sat 24 Oct, 16:30 · Long et al. | MELANOMA | Resected melanoma, stage IIB–IV (adjuvant) | Intismeran autogene (mRNA) + pembrolizumab vs pembrolizumab | Positive topline for RFS and DMFS (1,137 patients): the first phase III of an individualised neoantigen therapy. Watch the HR, the stage II subgroup and OS maturity.
02 | STARBOARD | 2071O | Fri 23 Oct, 16:15 · Schadendorf et al. | MELANOMA | First-line BRAF V600-mutant advanced melanoma | Encorafenib + binimetinib + pembrolizumab vs pembrolizumab | Phase III triplet, still under embargo. Can targeted therapy plus anti-PD-1 upfront finally beat anti-PD-1 alone? Toxicity will weigh as much as PFS.
03 | HBI-8000-303 | LBA54 | Fri 23 Oct, 16:25 · Khushalani et al. | MELANOMA | Advanced melanoma | Oral HDAC inhibitor + nivolumab vs nivolumab | Significant PFS gain (404 patients) with epigenetic priming of anti-PD-1. Watch the size of the gain, OS, and how it compares with LAG-3 and CTLA-4 combinations.
04 | TIL earlier | 2072O + LBA55 | Fri 23 Oct, 17:00 · Furness; Si et al. | MELANOMA | ICI-naïve advanced melanoma | Lifileucel + pembrolizumab (final) · GC101 TIL (randomised) | Cell therapy before anti-PD-1 failure. Can TIL earn a first-line role, and does the randomised signal hold with longer follow-up?
05 | NADINA | 2076RO | Sun 25 Oct, 11:14 · Witteveen et al. | MELANOMA | Stage III melanoma | Neoadjuvant ipilimumab + nivolumab vs adjuvant nivolumab | Three-year DMFS. After the EFS win, does the neoadjuvant advantage become fewer distant relapses? The bridge to an OS benefit.
06 | C-POST | LBA59 | Sun 25 Oct, 10:42 · Rischin et al. | CUTANEOUS SCC | High-risk cutaneous SCC (adjuvant) | Cemiplimab vs placebo | DFS benefit already published; now updated OS and ctDNA. Can ctDNA tell us who really needs adjuvant therapy?
07 | ADMEC-O | LBA60 | Sun 25 Oct, 10:47 · Becker et al. | MERKEL CELL | Merkel cell carcinoma (adjuvant) | Nivolumab · mature survival + biomarkers | After ADAM and STAMP missed their endpoints at ASCO26: is there a subgroup where adjuvant anti-PD-1 in Merkel still makes sense?
08 | MATISSE 2 | 2486RO | Sun 25 Oct, 10:52 · Van Dijk et al. | CUTANEOUS SCC | Cutaneous SCC facing extensive surgery | Neoadjuvant immunotherapy for organ preservation | Cure without mutilating surgery? Watch pathological response and how many patients avoid the operation.
OncoAlert360
MELANOMA 5 | CUTANEOUS SCC 2 | MERKEL CELL 1 · All times CEST
[Slide 1]
INTerpath-001 | ESMO 2026
Personalised Vaccine. Fewer Recurrences.
MV Onco
01 THE TRIAL
[illustration: excised melanoma on arm]
Original melanoma
before excision
Completely resected
stage IIB-IV
cutaneous melanoma
1,137 patients
Phase III • Double-blind • Randomised 2:1
757 → Intismeran + pembrolizumab
380 → Placebo + pembrolizumab
02 WHAT & HOW OFTEN?
BOTH GROUPS
Pembrolizumab 400 mg IV
Every 6 weeks × 9 cycles
[IV bag label: IV Pembrolizumab 400 mg]
ADD-ON
Intismeran 1 mg or
matching placebo
INTRAMUSCULAR
Every 3 weeks × 9 doses
Pembrolizumab started at randomisation; vaccine/placebo began when available.
03 THE BENEFIT AT 2 YEARS
Intismeran + pembrolizumab vs placebo + pembrolizumab
RECURRENCE-FREE SURVIVAL
82.2% vs 70.0%
HR 0.58
+12.2 percentage points
DISTANT METASTASIS-FREE SURVIVAL
88.5% vs 80.2%
HR 0.62
+8.3 percentage points
Median follow-up: 24.6 months
04 THE MAIN ADDED SIDE EFFECTS
Intismeran + pembrolizumab vs placebo + pembrolizumab
FEVER
52.2% vs 8.2%
INJECTION-SITE PAIN
51.0% vs 9.5%
TAKE-HOME
✓ Better RFS and DMFS.
✓ More fever and injection-site pain.
✓ OS results not reported in this abstract.
[Slide 2]
INTerpath-001 | ESMO 2026
A PERSONALISED VACCINE.
FEWER RECURRENCES.
MV Onco
Original melanoma
— before excision
Melanoma completely removed
Stage IIB-IV • After surgery
[illustration: syringe labelled Intismeran + IV bag labelled Pembrolizumab → T cells attacking residual tumour cells]
Build tumour-specific immunity
T cells
Possible microscopic residual disease
Intismeran
Personalised mRNA vaccine
Pembrolizumab
RECURRENCE-FREE AT 2 YEARS
82.2% vs 70.0%
Intismeran + pembrolizumab Placebo + pembrolizumab
+12.2 percentage points
RFS HR 0.58
TAKE-HOME
• Better RFS and DMFS.
• OS benefit not yet established.
[Slide 1]
ESMO 2026 / MADRID
REPORTING FROM MADRID
ESMO 2026 / DAY ONE
LIVE CONGRESS NOTES
[MADRID 2026 ESMO congress logo]
MADRID • CONGRESS NOTES
MUSTAFA ÖZDOĞAN
MD · MADRID 2026
FRIDAY 23 OCTOBER MADRID TIME · CEST (UTC+2)
WHAT I'M FOLLOWING TODAY
11:30 OPENING SESSION
The scientific programme begins
13:30 //
ESMO-MCBS
How large must a benefit be to matter?
UPPER GI ORAL ABSTRACTS
KEYNOTE-975 on the agenda
15:15 mRNA VACCINES
Context ahead of Saturday's INTerpath-001 (LBA1)
I'M HERE IN THE HALLS
I'll share the results, absolute gains and clinical implications.
ESMO 2026 • Madrid • 23–27 October 2026 | drozdogan.com
[Slide 1]
ESMO 2026 / MADRID
PRESIDENTIAL SYMPOSIUM I / LBA1
OCT 24
INTerpath-001
PERSONALISED mRNA VACCINE CLEARS PHASE 3 RECURRENCE ENDPOINTS
Resected stage IIB–IV cutaneous melanoma · adjuvant setting
RFS met • DMFS met • Effect size pending
01 PATIENTS
Completely resected stage IIB–IV cutaneous melanoma; no prior systemic therapy for melanoma.
02 ARMS
Intismeran autogene + pembrolizumab ↔ placebo + pembrolizumab
Phase 3 · randomised · double-blind · global · n=1,137 · 2:1 randomisation
03 KNOWN NOW
Prespecified interim analysis met the primary endpoint: recurrence-free survival (RFS). Key secondary endpoint distant metastasis-free survival (DMFS) was also met.
04 NOT YET DISCLOSED
Hazard ratios, 95% CIs, absolute RFS/DMFS differences, detailed grade 3+ toxicity/discontinuation, and mature overall survival.
05 CLINICAL READOUT
The real question is not whether the study is positive, but whether the absolute benefit is large enough to justify a personalised manufacturing workflow and added treatment burden.
Data status: company topline + ESMO programme; full presentation pending.
Presenter: Georgina V. Long
drozdogan.com
[Slide 1]
PERSONALISED mRNA VACCINES
Why Adjuvant Before Metastatic?
The biological rationale behind INTerpath-001
MV Onco
[illustration: syringe → T cells]
Personalised mRNA vaccine
Vaccine → Neoantigen-specific T cells
Generating T cells is only the first step.
MICROSCOPIC DISEASE
[illustration: T cells attacking small tumour clusters]
Lower tumour burden
Potentially favourable effector-to-target ratio
Control disease before macroscopic outgrowth
GOAL: PREVENT RECURRENCE
ESTABLISHED TUMOUR
[illustration: tumour with vessels, stroma, MDSC, TAM labelled]
MDSC
TAM
Abnormal vessels + stroma can restrict T-cell entry
Suppressive microenvironment can impair T-cell function
Antigen / HLA loss can prevent recognition
PRIMING ALONE MAY BE INSUFFICIENT
TAKE-HOME
A vaccine can generate the response.
Tumour biology determines whether it succeeds.
Rationale—not proof of greater efficacy in adjuvant disease.
INTerpath-012 is investigating a personalised mRNA vaccine in metastatic melanoma.
[Slide 1]
[ESMO Congress Madrid 2026 banner: MADRID SPAIN 23-27 OCTOBER 2026]
2080P - Host inherited genetic variation and the risk of hepatitis following immune checkpoint immunotherapy (ICI) of melanoma
Presentation Number 2080P
Speakers Ahmad Tarhini (Tampa, United States of America)
Authors Ahmad Tarhini (Tampa, United States of America), Zhihua Chen (Tampa, United States of America), Mohammad Ali Khaksar (Tampa, United States of America), Sandra Lee (Boston, United States of America), Frank Stephen Hodi (Boston, United States of America), Tingyi Li (Tampa, United States of America), Howard Streicher (Bethesda, United States of America), Vernon Sondak (Tampa, United States of America), John M. Kirkwood (Pittsburgh, United States of America), Xuefeng Wang (Tampa, United States of America), Peter Kanetsky (Tampa, United States of America)
Date Sat, 24.10.2026
Time 12:00 - 12:45
Background
Immune-mediated hepatitis (IMH) is a common toxicity following ICI and can be life-threatening. Predicting the risk of IMH may inform a more personalized approach to ICI treatment and patient (pt) follow up.
Methods
We conducted genome-wide genotyping on samples from 744 pts with melanoma enrolled in ECOG-ACRIN E1609 trial that tested ipilimumab. We used Illumina Infinium Global Screening Array v.3.0 + Multi-Disease BeadChip with 730059 designed loci. Genotypes called using Illumina Genome Studio 2.0 and IAAP CLI v1.1.0 and harmonized with the 1000 Genomes phase 3 references. We generated a cohort-derived polygenic risk score (cd-PRS) and separately investigated 17 published PRSs for inflammatory liver disease from patients not previously exposed to immunotherapy (PGS Catalog v20240318). Here, we report on the distribution of the PRSs and the occurrence of IMH, treating IMH grades as categorical (Kruskal-Wallis) and as dichotomous (Wilcoxon rank-sum) variables.
Results
IMH occurred in 207 (28%) pts (146 Gr1, 18 Gr2, 29 Gr3, 14 Gr4). There were no significant differences in the distribution of any of the PGS-derived PRSs across IMH grades, including after dichotomization. From our GWAS, we identified 10 independent SNPs associated with IMH and constructed a cd-PRS which was associated with IMH risk and severity both across grades (Kruskal-Wallis p < 2.2 × 10^-16) and after dichotomization (any grade vs. none; Wilcoxon p < 2.2 × 10^-16); in ROC analysis, the cd-PRS achieved an AUC of 0.81. Most of the SNPs identified mapped to intronic regions of genes with reported association to inflammation and autoimmunity. In survival analyses, occurrence of any-grade IMH was associated with improved overall survival (OS, p = 0.04), adjusting for primary tumor status and sex. Further analysis showed a dose-response relationship between the cd-PRS and survival, with higher PRS values associated with longer OS (HR 0.36, 95% CI 0.04 - 3.65, p = 0.39).
Conclusions
Our analysis supports an association between inherited genetic variation and the risk of IMH following ICI. These findings may have implications to better inform pt risk and follow-up in the clinic and warrant further investigation.
[Slide 1]
[ESMO Congress Madrid 2026 banner: MADRID SPAIN 23-27 OCTOBER 2026]
2121P - Real-world outcomes among patients (pts) with resectable stage III melanoma treated with neoadjuvant nivolumab + relatlimab (N+R) or nivolumab + ipilimumab (N+I) in the US
Presentation Number 2121P
Speakers Michael Postow (New York, United States of America)
Authors Michael Postow (New York, United States of America), Sekwon Jang (Fairfax, United States of America), Vincent T. Ma (Madison, United States of America), Masoom Priyadarshini (Princeton, United States of America), Oluwabunmi Emidio (Dublin, United States of America), Lisa C. Rosenblatt (Cambridge, United States of America), Leon Sakkal (Lawrenceville, United States of America), Cara Trulli (Princeton, United States of America), Emily Levine (Dublin, United States of America), Angele Kotomale (Hialeah, United States of America), Talia Miller (Dublin, United States of America), Jalyna Laney (Dublin, United States of America), Bruce A. Feinberg (Dublin, United States of America), Christopher D. Lao (Ann Arbor, United States of America), Jennell Palaia (Cambridge, United States of America), Ahmad Tarhini (Tampa, United States of America)
Date Sat, 24.10.2026
Time 12:00 - 12:45
Background: Dual checkpoint blockade with N+R or N+I has demonstrated efficacy in trials, but real-world evidence remains limited. This study assessed demographics, clinical characteristics, treatment (tx) patterns and outcomes among pts with melanoma receiving neoadjuvant immunotherapy (NIT) with N+R or N+I.
Methods: This retrospective chart review used de-identified physician-abstracted data from the Cardinal Health Oncology Provider Extended Network. Adults with systemic tx-naive, stage III resectable melanoma initiating NIT with N+R or N+I on/after March 18, 2022 were selected in order of tx initiation date. Follow-up of 6 mo was required, but deaths <6 mo were included as events. Descriptive statistics and Kaplan–Meier methods assessed event-free survival (EFS), distant-metastasis free survival (DMFS), and overall survival (OS). Inverse probability of tx weighting (IPTW) analysis was conducted as sensitivity analysis.
Results: The study included 100 pts (N+R, n=50; N+I, n=50) with median age 60 (N+R) and 57 (N+I) years. N+R vs N+I had more pts with ECOG PS ≥ 2 (30% vs 8%), higher NCI comorbidity burden (median, 0.47 vs 0.0), and higher LDH levels (median, 296 vs 193 IU/L). Overall, 92% of pts in N+R and N+I cohorts underwent surgical resection followed by systemic adjuvant therapy in most (N+R, 67%; N+I, 54%). Among resected pts, major pathologic response (MPR; <10% viable tumor) was observed in 78% of N+R and 70% of N+I pts. Pathologic complete response (pCR; 0% viable tumor), a subset of MPR, occurred in 33% and 30%, respectively. With median follow-up of 8.8 mo in N+R and 8.7 mo in N+I, 9-mo survival rates for N+R/N+I cohorts were: EFS, 92/91%; DMFS, 93/95%; OS, 93/98%. Post IPTW analysis, pCR occurred in 40% N+R pts and 26% N+I pts; 9-mo survival rates (N+R/N+I) were: EFS, 93/83%; DMFS, 96/86%; OS, 96/88%.
Conclusions: Acknowledging the limited follow-up, NIT with N+R and N+I results were comparable, with IPTW-adjusted analyses showing a trend toward improved pCR and survival with N+R. Findings support the utility of dual NIT in stage III resectable melanoma. Study limitations included short-term follow-up, unmeasured confounders, and pt selection bias.
[Slide 1]
[ESMO Congress Madrid 2026 banner: MADRID SPAIN 23-27 OCTOBER 2026]
2202eP - Clinical outcomes and treatment patterns in non-metastatic melanoma: A surveillance, epidemiology, and end results (SEER)-medicare analysis
Presentation Number 2202eP
Speakers Ahmad Tarhini (Tampa, United States of America)
Authors Ahmad Tarhini (Tampa, United States of America), Marianne Cunnington (London, United Kingdom), Angela Lax (Boston, United States of America), Adina Zhang (San Francisco, United States of America), Mei Sheng S. Duh (Menlo Park, United States of America), Maral DerSarkissian (Menlo Park, United States of America), Vanja Sikirica (Cambridge, United States of America), Yidan Ma (Boston, United States of America), Alexandra Barry (Boston, United States of America), Leah B. Sansbury (Cambridge, United States of America)
Background: Melanoma remains the most serious form of skin cancer. Understanding treatment patterns and clinical outcomes across stages of non-metastatic melanoma is critical to optimize outcomes.
Methods: Patients (pts) ≥66 years with Stage I–III melanoma were identified in SEER-Medicare linked claims (01/2019–12/2021) and stratified by stage at diagnosis. Baseline characteristics were assessed during the 12 months pre-diagnosis. Treatment patterns, recurrence-free survival (RFS; defined using a validated claims-based algorithm [Tarhini 2018]), and overall survival (OS) were evaluated post-diagnosis through end of 2022. Treatment patterns were summarized descriptively. Kaplan-Meier methods were used for OS and RFS, with censoring at end of continuous Medicare eligibility or data availability. Outcomes were reported overall, by stage, and for Stage II/III sub-stages.
Results: A total of 3,978 Stage I, 1,021 Stage II, and 484 Stage III pts were included; mean ages were 75.7, 79.1, and 76.4 years, respectively. The most common primary tumor sites were arm (Stage I, 30.8%), head/neck (Stage II, 34.5%), and trunk (Stage III, 25.8%). Over a median 2-year follow-up, 47.3% of Stage III pts received surgery with adjuvant therapy, most commonly immunotherapy (88.4%), vs 6.8% of Stage IIB/C pts. Neoadjuvant therapy was rare (3.9% in Stage III). Median RFS and OS by stage and sub-stage are shown in the table. RFS decreased with increasing stage at diagnosis. Median OS was not reached; 3-year OS rates were lowest for Stage IIC and IIIC/D. Table: 2202eP
RFS and OS
| | Stage I Overall N=3,978 | Stage II Overall N=1,021 | Stage IIA N=438 | Stage IIB N=341 | Stage IIC N=218 | Stage III Overall N=484 | Stage IIIA N=55 | Stage IIIB N=81 | Stage IIIC/D N=250 |
RFS
Median (95% CI), months | 31.5 (29.3, 33.7) | 17.6 (15.4, 20.1) | 20.1 (15.9, 23.3) | 19.0 (15.8, 21.9) | 13.8 (11.5, 16.0) | 6.5 (5.9, 7.1) | 11.7 (8.0, 15.2) | 8.3 (6.2, 13.4) | 5.7 (5.2, 6.2)
Rate at 3 years, % | 46.0 | 29.2 | 33.0 | 29.2 | 20.1 | 11.6 | 17.6 | 20.1 | 7.7
OS
Rate at 3 years, % | 90.5 | 71.7 | 81.2 | 71.2 | 51.5 | 69.0 | 89.9 | 88.2 | 57.0
Conclusions: Pts with non-metastatic melanoma, particularly with advanced Stage II and III disease, show variation in outcomes by sub-stage with poorer outcomes in Stage IIC and IIIC/D. Neoadjuvant therapies were rare in our cohort, and adjuvant therapy was uncommon in Stage IIB/C pts. These findings highlight the importance of early detection and the unmet need and recurrence burden in advanced Stage II and III disease.
[Slide 1]
Melanoma ESMO 2026
SELECTED ABSTRACTS
LBA1
INTerpath-001: Phase 3 study of the mRNA-based individualized neoantigen therapy (INT) intismeran autogene (intismeran) plus pembrolizumab (pembro) vs pembro alone for adjuvant treatment of resected stage IIB-IV melanoma (MEL)
2072O
Efficacy and Safety of Lifileucel and Pembrolizumab in Patients with Immune Check Point Inhibitor-Naïve Advanced Melanoma - Final Results from IOV-COM-202 Study
2076RO
Three-year distant metastasis-free survival of the phase 3 NADINA trial comparing neoadjuvant nivolumab plus ipilimumab versus adjuvant nivolumab in resectable stage III melanoma
2126P
Adjuvant therapy in BRAF-mutated stage III melanoma patients after not achieving a major pathological response to neoadjuvant ipilimumab (IPI) plus nivolumab (NIVO)
2077P
Circulating Antibody Profiling Identifies Predictive Biomarkers of Outcome and irAEs in Melanoma
2109P
Neoadjuvant intradermal ipilimumab and nivolumab in high-risk stage II melanoma - MARIANE
2116P
Synergistic Efficacy of Intrathecal PD-1 Blockade Combined with Whole-Brain Radiotherapy for Melanoma Leptomeningeal Metastases: A Real-World Analysis
2128P
Response durability with anzutresgene autoleucel (anzu-cel), a PRAME-directed T-cell receptor (TCR) T-cell therapy, in advanced melanoma
2089P
IL-6 receptor blockade with immune checkpoint inhibitors in melanoma reveals immune signatures of toxicity and response: Final results from a phase II trial
2111P
Week 6 interferon-gamma signature identifies melanoma patients at high risk of recurrence to neoadjuvant immunotherapy
2132P
Impact on survival of early discontinuation of immune checkpoint inhibitors after objective response in melanoma
2086P
Darovasertib and Crizotinib for HLA-A*02-Positive Metastatic Uveal Melanoma: Results from the Phase 2 OptimUM-01 Study
2092P
Neoadjuvant Darovasertib in Primary Uveal Melanoma: Follow-Up Data from the Phase 2 OptimUM-09 Study
4514P
Tracking tumour and immune changes in cell-free DNA to predict response in patients with advanced melanoma treated with immune checkpoint inhibitors (ICI)
Omid Hamid, MD
[Slide 1]
NASD: MRNA $0.00 Vol: $0.00
moderna About Us The Power Of MRNA Research Responsibility
Merck and Moderna Announce Phase 3 INTerpath-001 Trial of Intismeran Autogene Plus KEYTRUDA® Met Endpoints of Recurrence-Free Survival (RFS) and Distant Metastasis-Free Survival (DMFS) in Patients With Completely Resected Stage IIB-IV Melanoma
August 19, 2026
Merck and Moderna Announce Phase 3 INTerpath-001 Trial of Intismeran Autogene Plus KEYTRUDA® Met Endpoints of Recurrence-Free Survival (RFS) and Distant Metastasis-Free Survival (DMFS) in Patients With Completely Resected Stage IIB-IV Melanoma
First and only combination regimen to demonstrate statistically significant and clinically meaningful improvements in RFS and DMFS compared to KEYTRUDA alone for these patients in the adjuvant melanoma setting
The Companies plan to present data at an upcoming international medical meeting and will engage with regulators on filing submissions for intismeran autogene in combination with KEYTRUDA
Intismeran autogene is an mRNA-based individualized neoantigen therapy (INT) designed specifically for each patient based on the unique set of mutations within their tumor to train and activate the immune system to recognize and fight cancer
RAHWAY, N.J. and CAMBRIDGE, MA, August 19, 2026 – Merck (NYSE: MRK), known as MSD outside of the United States and Canada, and Moderna, Inc. (NASDAQ: MRNA) today announced positive topline results from the Phase 3 INTerpath-001 trial evaluating adjuvant treatment with intis[meran ...] [cut off]
[Slide 1]
ESMO CONGRESS 2026
Industry Satellite Symposium
TOWARD A NEW PARADIGM IN METASTATIC UVEAL MELANOMA:
From biological insight to practical treatment strategies
23 October 2026 | 18:15–19:45 CEST
Oviedo Auditorium, Hall 5
IFEMA MADRID
IDEAYA BIOSCIENCES
[Slide 1]
Consensus-driven recommendations: 1L MCL
ESMO | ANNALS OF ONCOLOGY
SPECIAL ARTICLE
Lymphomas: ESMO Clinical Practice Guideline for diagnosis, treatment and follow-up
[author list illegible: T. A. Eyre, ... M. Dreyling, D. A. Eichenauer, ... on behalf of the ESMO Guidelines Committee]
Test for TP53 mutations pre-treatment and consider for experimental clinical trials
Symptomatic MCL*
Fit, younger patients[a]
R-CHOP-ibrutinib/R-DHAP[b] → 2 years ibrutinib plus 3 years R maintenance
R and cytarabine-containing induction[c] → ASCT[h] → 3 years R maintenance
Older or unfit patients
ICT induction[d] → R maintenance[e]
BR-acalabrutinib[f] or BR-ibrutinib induction → 2 years R maintenance plus acalabrutinib to progression or toxicity
R-cBTKi[g] → 2 years R maintenance plus cBTKi to progression or toxicity
* Limited stage MCL is not well defined and observation, ISRT and/or systemic treatment could be considered.
* Consider active observation for asymptomatic MCL with indolent clinical and biological features[i]
[Figure: treatment algorithm flowchart; screen capture with video-player controls bottom-left.]
[Slide 1]
NRG-GY020
Adjuvant RT with or without pembrolizumab in dMMR endometrial cancer
Stage I-II
High-intermediate
risk
dMMR endometrioid
n = 168
→ RANDOMIZE
3-year success* Grade 3/4 toxicity
RT alone
(n = 56) 73% 15%
RT + pembro
(n = 112) 70% 43%
*Primary RFS3 analysis: off-study for any reason counted as failure. P = .68, not statistically significant.
Secondary KM RFS: 81% vs 88%; HR 0.72 (95% CI 0.33-1.61), not significant. 3-year OS 96% in both arms.
Backes et al. ESMO 2026, 1239O. Phase III. 70% VBT alone; 30% EBRT +/- VBT. Pembro for 1 year.
[Slide 1]
ESMO 2026 INDUSTRY SATELLITE SYMPOSIUM
CME/CNE/CPE
Join us at
Beyond Chemotherapy
Integrating Novel Targeted
Agents Into Platinum-Resistant
Ovarian Cancer Clinical Practice
SATURDAY, 24 OCTOBER 2026 | HYBRID
Medscape GLOBAL ONCOLOGY
Supported by an independent educational grant from Genmab.
Susana Banerjee, MBBS, MA, PhD, FRCP
MODERATOR
Nicoletta Colombo, MD, PhD
FACULTY
Christian Marth, MD, PhD
FACULTY
[faculty headshots]
[Slide 1]
Intended for HCPs only
ESMO 2026
OVARIAN CANCER
FPN: 1448eTiP
FRAmework-01: A Three-Part Phase 3 Study of Sofetabart Mipitecan (Sofe-M) in Platinum-Resistant Ovarian Cancer (PROC), and Sofe-M plus Bevacizumab (Bev) in Platinum-Sensitive Ovarian Cancer (PSOC)
ePoster
Lilly A MEDICINE COMPANY
[Slide 1]
ESMO 2026 INDUSTRY SATELLITE SYMPOSIUM
CME/CNE/CPE
Join us at
Beyond Chemotherapy
Integrating Novel Targeted
Agents Into Platinum-Resistant
Ovarian Cancer Clinical Practice
SATURDAY, 24 OCTOBER 2026 | HYBRID
Medscape GLOBAL ONCOLOGY
Supported by an independent educational grant from Genmab.
Susana Banerjee, MBBS, MA, PhD, FRCP
MODERATOR
Nicoletta Colombo, MD, PhD
FACULTY
Christian Marth, MD, PhD
FACULTY
[faculty headshots]
[Slide 1]
[cancernetwork logo] cancernetwork
home of the journal ONCOLOGY
ESMO CONGRESS 2026 PREVIEW
GYNECOLOGIC ONCOLOGY
The Data to Watch at
ESMO 2026
De-Escalation and ADCs
1 KEYNOTE-C93 ENDOMETRIAL
First-line pembrolizumab vs chemotherapy in dMMR disease
2 TroFuse-005 ENDOMETRIAL
Sacituzumab tirumotecan after chemotherapy and immunotherapy
3 BEHOLD-1 OVARIAN
B7-H4–targeted mocertatug rezetecan in PROC
4 REJOICE-Ovarian01 OVARIAN
CDH6-directed raludotatug deruxtecan in PROC
5 DUO-E ENDOMETRIAL
Interim OS with durvalumab ± olaparib
Featuring insights from Eirwen M. Miller, MD, and Nujsaubnusi C. Vue, MD, of Allegheny Health Network
Read the full preview ›
CANCERNETWORK.COM
[Slide 1]
GOG FOUNDATION® Transforming the standard of care™ GOG PARTNERS
2026 ESMO CONGRESS
Rapid Oral 1: Gynaecological cancers
Friday, October 23, 2026 | 16:15 - 17:45 | Burgos Auditorium - Hall 3
PRESENTING
GOG-3066 DENALI
1242RO - Azenosertib in platinum-resistant ovarian cancer (PROC): overall survival analysis from Part 1b of the DENALI study (GOG-3066)
[headshot photo]
Fiona Simpkins, MD
University of Pennsylvania
Perelman School of Medicine
[Slide 1]
nature reviews clinical oncology
https://doi.org/10.1038/s41571-026-01213-3
Review article
A modular framework for antibody–drug conjugate biomarkers
Jia Liu 1,2,3,4, Dan-Yun Ruan 5,6, Nicholas McNamee 4, Roger R. Reddel 4, Hao-Xiang Wu 5,6, Qi Meng 5,6, Rui-Hua Xu 6,7, Vivek Subbiah 8, David L. Rimm 9 & Barbara Pistilli 10,11,12
Abstract
The availability of approved antibody–drug conjugates (ADCs) has rapidly expanded across oncology indications, yet biomarker development remains dominated by semi-quantitative immunohistochemistry. Robust biomarkers are needed to improve patient selection, guide therapeutic sequencing and identify resistance mechanisms that inform rational combinations. ADC activity depends on target antigen expression, linker chemistry and payload characteristics all within the context of the tumour microenvironment. Consequently, treatment response cannot be predicted solely by target expression. A more comprehensive biomarker framework is required that accounts for antigen abundance and accessibility, intracellular trafficking and linker cleavage, and tumour susceptibility to the payload. Furthermore, biomarkers of toxicity have been largely overlooked, even though toxicity can be equally determinant of clinical utility. In this Review, we outline a modular framework for ADC biomarker development organized around these components. We distinguish established evidence from emerging strategies and discuss technologies that could enable assessment of these determinants. We consider how modular biomarkers might inform patient selection, therapeutic sequencing, rational combinations, dose optimization and regulatory strategy while highlighting the various challenges that must be addressed before broad clinical adoption. Harmonized development across trials, tumour types and geographical regions will be essential to move biomarker development beyond empirical target-expression thresholds.
Sections
Introduction
Determinants of ADC efficacy and safety
Technologies supporting modular ADC biomarker development
Multiregional validation of ADC biomarker frameworks
Clinical and patient implications of modular ADC biomarker frameworks
Drug development implications
Biomarker thresholds and regulatory science
Conclusions
A full list of affiliations appears at the end of the paper. e-mail: jia.liu@svha.org.au
Nature Reviews Clinical Oncology
[Slide 2]
a [Stacked bar chart: Number of trials (y-axis, 0-100+) by Year of first registration 2018-2026; Biomarker category legend: No biomarker required, IHC only, IHC + genomic, Genomic only, Other/mixed. Bars rise from ~20 in 2018 to peaks of ~130 in 2024 and ~125 in 2025, ~45 in 2026 (partial year)]
b Percentage of total ADC trials
No biomarker required 49.6%
IHC only 23.9%
IHC + genomic 13.7%
Genomic only 11.5%
Other/mixed 1.3%
c Percentage of trials requiring biomarkers
IHC 74.7%
FISH/ISH 32.5%
NGS 24.0%
ctDNA 6.8%
d [Heatmap, % within target; columns: No biomarker required | IHC only | IHC + genomic | Genomic only | Other/mixed]
HER2 (n = 233): 21% | 42% | 27% | 10% | –
TROP2 (n = 162): 67% | 9% | 7% | 15% | 2%
Nectin 4 (n = 45): 84% | – | 2% | 9% | 4%
FRα (n = 18): 22% | 67% | 6% | 6% | –
B7-H3 (n = 18): 94% | – | 6% | – | –
C-MET (n = 16): 50% | – | – | 44% | 6%
HER3 (n = 15): 60% | – | 13% | 27% | –
EGFR (n = 14): 86% | 14% | – | – | –
CLDN18.2 (n = 11): 45% | 45% | 9% | – | –
B7-H4 (n = 10): 90% | – | – | 10% | –
CEACAM5 (n = 4): – | 75% | 25% | – | –
MSLN (n = 2): – | 100% | – | – | –
Colour scale: % within target 0-100
[Slide 1]
Table 2. Maximal preliminary scores
Treatments with curative intent (form 1)
>5% improvement of survival at ≥3-year follow-up
Improvements in DFS alone HR <0.60 (primary end point) in studies without mature survival data
Treatments with non-curative intent (form 2)
Primary outcome OS (form 2a)
Control ≤12 months
HR ≤0.65 AND gain ≥3 months OR
Increase in 2-year survival alone ≥10%
Control >12 months
HR ≤0.70 AND gain ≥5 months OR
Increase in 3-year survival alone ≥10%
Primary outcome PFS (form 2b)
Control ≤6 months
HR ≤0.65 AND gain ≥1.5 months
Control >6 months
HR ≤0.65 AND gain ≥3 months
[Slide 1]
ESMO Principles for Humanising Science Reporting
1. Put patients at the centre of the story
Every dataset represents people living with cancer. Introduce the patient population clearly and explain why the research question matters to patients and those involved in their care.
2. Use patient-centred language
Use terminology that accurately describes the disease, tumour or treatment rather than defining people by their condition. Avoid language that may be perceived as objectifying, stigmatising or inconsistent with current standards.
3. Start with the unmet need
Before presenting methods or endpoints, briefly explain the clinical challenge the study seeks to address and why it is important for patients.
4. Explain the relevance of the results
Alongside reporting statistical outcomes, explain what the findings may mean for patients in practical terms. Scientific accuracy remains paramount, but the potential clinical relevance must also be clear.
5. Include a patient-focused take-home message
Where appropriate, ensure that key results are accompanied by a clear statement describing their potential implications for patients, in addition to the statistical findings.
6. Consider the broader patient experience
When available, include information on quality of life, symptom and treatment burden, functional outcomes, monitoring requirements and caregiver impact alongside efficacy and safety results.
7. Communicate clearly and accessibly
Define abbreviations on first use, minimise unnecessary jargon and use terminology that can be understood by the wider oncology community.
8. Acknowledge those who made the research possible
Recognise the contribution of the patients who participated in the trial and, where relevant, any patient advocates or representatives involved in study design. Highlight their absence where appropriate.
9. Consider access, equity and remaining uncertainties
Discuss important practical considerations including access to treatment, required resources, testing needs and unresolved questions. Understanding both opportunities and limitations supports informed decision-making and shows respect for those ultimately being impacted.
10. Illustrate the human impact where appropriate
When relevant and scientifically appropriate, consider using patient stories, experiences or perspectives to help contextualise the importance of the research findings.
[ESMO logo bottom right]
[Slide 1]
4329P Plasma extracellular vesicle proteomics identifies signatures of resistance and survival to immune checkpoint inhibitors in solid tumors
[cropped icon at bottom]
[Slide 1]
ESMO 2026 - Conference Calendar
[Everything ▾] [Search For]
Calendar view | Sessions | Presentations | Posters | ePosters | Final Programme (PDF) | Indust[ry...]
Young Oncologist session
YO Lecture: What to expect from precision medicine in the next decade
Date Sat, 24.10.2026
Chairs Rodrigo Sanchez Bayona (Madrid, Spain), Ana Tecic Vuger (Zagreb, Croatia)
Room Santander Auditorium - Hall 10
Time 14:45 - 15:45
Young Oncologist session
Drugging the undruggables: The next wave of targeted therapies
Speakers Vivek Subbiah (Nashville, United States of America)
Lecture Time 14:45 - 15:05
Young Oncologist session
Q&A and discussion
Lecture Time 15:05 - 15:15
Young Oncologist session
How will new technologies contribute to precision medicine?
Speakers Mihaela Aldea (Villejuif, France)
Lecture Time 15:15 - 15:35
[Slide 1]
Special session
Quantifying the magnitude of clinical benefit in a changing trial landscape
Date Fri, 23.10.2026
Chairs Dirk Arnold (Hamburg, Germany), Sjoukje F. Oosting (Groningen, Netherlands)
Room Oviedo Auditorium - Hall 5
Time 13:30 - 15:00
Special session
How do I read and interpret a cancer clinical trial? Perspectives on critical appraisal from a practising clinician
Speakers Bishal Gyawali (Kingston, Canada)
Lecture Time 13:30 - 13:50
Special session
Magnitude of benefit in de-escalation trials: Update on the development of a scoring system for "near-equivalence" studies
Speakers Dirk Arnold (Hamburg, Germany)
Lecture Time 13:50 - 14:10
[Slide 2]
Special session
Novel trial endpoints: What does the future hold?
Speakers Eva Blondeaux (Genova, Italy)
Lecture Time 14:10 - 14:30
Special session
ESMO-MCBS: Do we sufficiently distinguish between exceptional curative treatments and those with less pronounced benefits?
Speakers Sjoukje F. Oosting (Groningen, Netherlands)
Lecture Time 14:30 - 14:50
Special session
Q&A and discussion
Lecture Time 14:50 - 15:00
[Slide 1]
ESMO GOOD SCIENCE BETTER MEDICINE BEST PRACTICE
ANNALS OF ONCOLOGY DRIVING INNOVATION IN ONCOLOGY
ORIGINAL ARTICLE
The ESMO Scale for Clinical Actionability of Molecular Targets, version 2 (ESCAT v2): an evidence-based framework for ranking alterations as actionability and resistance biomarkers in precision oncology
A. El Helali1,2,3*†, C. Cardone4, N. Coleman5,6,7, J. R. Beal8, M. V. Cruz-Ordinario9, E. Kocakavuk10, M. K-l. Chiu11, D. Thomas12, C. Turnbull13, F. Meric-Bernstam14, M. F. Mosele15,16, D. Chakravarty17, R. Dienstmann18,19, D. Tamborero20, H. E. G. Russnes21,22,23, M. Kordes24,25, H. H. F. Loong26, A. Stenzinger27, J. Rueter28, D. Martins-Branco29, G. Pentheroudakis29, J. Mateo30*‡ & C. B. Westphalen31,32,33*‡
[Slide 1]
I WILL BE
SPEAKING AT
ESMO 2026
Madrid, October 23rd 2026
[headshot of Vivek Subbiah]
[ESMO logo: GOOD SCIENCE BETTER MEDICINE BEST PRACTICE]
Vivek
Subbiah, MD
[IPM ALLIANCE logo]
I WILL BE SPEAKING AT:
PERSONALISED ONCOLOGY ACROSS
HEALTH SYSTEMS
[calendar icon] October 23rd, 2026
08:30 - 17:00
[location pin icon] Room « A4.2 »
Mezzanine Level,
IFEMA
[Slide 1]
Common Sense Oncology @ ESMO
Join us in-person at ESMO Madrid for a special CSO symposium!
Friday, October 23, 2026
18:00 - 19:30 (CET)
[Six circular headshots]
Dr. Winette van der Graaf
Netherlands Cancer Institute and Erasmus MC
Dr. Dario Trapani
IEO European Institute of Oncology
Dr. Rodrigo Lastra
Hospital Lozano Blesa, RIO Working Group
Dr. Francesco Perrone
National Cancer Institute IRCCS Fondazione Pascale
Dr. Jolien Tol
Jeroen Bosch Hospital
Antonella Cardone
Cancer Patients Europe
COMMON SENSE ONCOLOGY
Location: ESMO venue, IFEMA, Madrid, Spain - Room A6.1
[Slide 1]
MADRID 2026 ESMO congress
MADRID, SPAIN 23-27 OCTOBER 2026 | IFEMA MADRID
FIRST TIME AT ESMO 2026?
A quick guide to surviving Madrid
Great science. New perspectives. Amazing people. See you there!
1 IFEMA looks manageable on the map... Spoiler: it isn't. Hall-to-hall walks add up fast. Build in transfer time. Metro stop: Feria de Madrid (Line 8)
2 Choose your non-negotiables. Pick your Presidential / Plenary / late-breaking must-sees first. Then build the rest of your day around them. Trying to do everything = missing the important bits.
3 Do not stop at the headline. Check the control arm. Look at absolute benefit, not just the hazard ratio. Toxicity and patient selection matter.
4 The poster area is not a side quest. Some of the best practical discussions happen there. Ask about biomarkers, sequencing, and real-world applicability.
5 Save the discussion slides. The discussant's take and the Q&A often give more nuance than the main presentation.
6 Conference survival kit. Comfortable shoes · Light layer for freezing session rooms · Power bank · Reusable bottle
7 You can catch up later. If two great sessions overlap, choose one and let the other go. Congress resources and webcasts can help after the meeting.
8 Network on purpose. Set up 2–3 meaningful coffee chats. The real science also happens in hallways, lounges, and after sessions.
Important tip! Do NOT try to see everything. · the best sessions always overlap · you will improvise anyway · leave space for unexpected conversations
And remember: You won't see it all. But you can absolutely enjoy the experience.
ESMO is not only about positive trials. It is also about perspective, discussion, and the people you meet around the data.
See you in Madrid
@DraMartinezLago
[Figure: illustrated Madrid landmarks (Cibeles fountain, Metropolis building), icons per tip.]
[Slide 1]
I-P ← Yes ← Clinical BENEFIT (EFS/DFS/PFS/OS) in tumour-specific randomised controlled trials with biomarker-based selection or stratification? → No
I-I ← Yes ← Clinical BENEFIT in tumour-specific non-randomised trials with pre-specified endpoint exceeding best available benchmark? → No
I-E ← Yes ← Clinical ACTIVITY (ORR/DOR) in multiple tumours investigated in non-tumour-specific trials, meeting ETAC-S criteria? → No
II-A ← Yes ← Clinical ACTIVITY in prospective interventional clinical trials, missing/insufficient survival data for Tier I? → No
II-B ← Yes ← Clinical ACTIVITY/BENEFIT in replicated high-quality RWE or post-hoc analyses of clinical trials? → No
II-C ← Yes ← Clinical ACTIVITY in replicated case-level evidence for rare/ultra-rare molecular subtypes? → No
III-A ← Yes ← Clinical BENEFIT/ACTIVITY in other tumour type(s), not meeting ETAC-S criteria? → No
III-B ← Yes ← Clinical BENEFIT based on functional analogy to established tier I/II biomarker? → No
IV-A ← Yes ← Biological rational of actionability based on in vitro/in vivo preclinical data? → No
IV-B ← Yes ← Biological rational of actionability based on in silico/computational data? → No
X-A ← Yes ← Clinical BENEFIT/ACTIVITY not predicted by biomarker positivity? → No
X-B ← Yes ← No clinical BENEFIT/ACTIVITY in biomarker-defined population?
Figure 1. Decision tree for actionability scale.
[Slide 2]
I-A-R ← Yes ← Absent/substantially reduced clinical BENEFIT/ACTIVITY in pre-planned/post-hoc biomarker analysis of randomised controlled trials? → No
I-B-R ← Yes ← Evidence of acquired resistance arising under therapeutic pressure in replicated retrospective evidence with mechanistic support? → No
II-R ← Yes ← Reduced BENEFIT/ACTIVITY in replicated non-randomised controlled trials/high-quality RWE with mechanistic support? → No
III-R ← Yes ← Preliminary/limited evidence of resistance which is insufficient, unreplicated, or inconsistent? → No
IV-A-R ← Yes ← Resistance supported primarily by in vitro/in vivo preclinical data? → No
IV-B-R ← Yes ← Resistance supported primarily by computational data?
Figure 2. Decision tree for resistance scale.
[Slide 1]
ESMO 2026 / AI & DIGITAL ONCOLOGY
PRE-CONGRESS SCIENTIFIC WATCH
Nikolaus Schultz, PhD • Memorial Sloan Kettering Cancer Center
AI + REAL-WORLD DATA: A NEW PREDICTION LAYER IN ONCOLOGY?
Can tumor biology, treatment history and longitudinal clinical data be read together?
[diagram: four data inputs feeding an AI brain icon → individualized outcome prediction]
GENOMICS: Mutations, signaling pathways, molecular subtypes
PATHOLOGY: Digital pathology, tumor microenvironment, IHC
IMAGING: CT / MRI / PET, radiomics
REAL-WORLD CLINICAL DATA: Demographics, comorbidity, treatment history, outcomes
AI — INTEGRATION & PATTERN RECOGNITION: Multi-modal data, machine learning, predictive modeling
INDIVIDUALIZED OUTCOME PREDICTION [illustrative survival curves]
Risk stratification
Treatment response prediction
More personalized clinical decision-making
WHAT DATA ARE BEING INTEGRATED?
GENOMICS: Mutations, signaling pathways, molecular subtypes
PATHOLOGY: Digital pathology, tumor microenvironment, IHC
IMAGING: CT / MRI / PET, radiomics
REAL-WORLD CLINICAL DATA: Demographics, comorbidity, treatment history, outcomes
KEY READOUT
• AI is moving beyond image classification toward multi-layer clinical integration.
• Goal: more individualized prediction of prognosis and treatment outcomes.
• Critical test: external validation, bias control and real clinical utility.
WHAT SHOULD WE DISCUSS IN MADRID?
VALIDATION: Does the model reproduce across centers and populations?
BIAS: How do missing or unbalanced datasets affect predictions?
CLINICAL VALUE: Does better prediction translate into better decisions and patient outcomes?
Scientific perspective • Not a routine clinical biomarker • Prospective and external validation required.
SCIENTIFIC PERSPECTIVE / PRE-CONGRESS WATCH
Source: ESMO 2026 scientific programme and congress previews • drozdogan.com
[Slide 1]
SOPHiA GENETICS™
ESMO 2026
Global Precision
Medicine Forum
Novotel Madrid Campo de las Naciones
October 22nd 3PM CEST
REGISTER
[capsule / DNA particle graphic]
[Slide 1]
MADRID 2026 ESMO congress
MADRID SPAIN 23-27 OCTOBER 2026
Presentation by Expert:
Use of liquid biopsies in early drug development: Are we ready for it?
[headshot]
Christian Rolfo, MD, PhD, MBA, Dr.hc
Professor
Director, Division of Medical Oncology
The Ohio State University Comprehensive Cancer Center
Friday, October 23
16:15-16:35
Malaga Auditorium – Hall 3
[Slide 1]
KEYNOTE-412 ctDNA
Exploratory clearance analysis in a paired-sample subset
Locally advanced
Head and neck SCC
Paired plasma
samples
n = 473 of 804
Parent trial randomized
Subset not re-randomized
→ RANDOMIZE
ctDNA clearance HPV-negative ctDNA clearance HPV-positive
CRT + placebo
(n = 240) 63.6% 62.7%
CRT + pembro
(n = 233) 72.6% 76.8%
Clearance assessed after 5 weeks of CRT (baseline to cycle 3 day 1). Exploratory, retrospective analysis.
Outcome associations varied by HPV status and arm. No treatment-interaction test reported; not proof of prediction.
Machiels et al. ESMO 2026, 1536RO. Parent primary endpoint: EFS; these percentages are biomarker outcomes.
[Slide 1]
Common Sense Oncology @ ESMO
Join us in-person at ESMO Madrid for a special CSO symposium!
Friday, October 23, 2026
18:00 - 19:30 (CET)
[six circular headshots]
Dr. Winette van der Graaf
Netherlands Cancer Institute and Erasmus MC
Dr. Dario Trapani
IEO European Institute of Oncology
Dr. Rodrigo Lastra
Hospital Lozano Blesa, RIO Working Group
Dr. Francesco Perrone
National Cancer Institute IRCCS Fondazione Pascale
Dr. Jolien Tol
Jeroen Bosch Hospital
Antonella Cardone
Cancer Patients Europe
COMMON SENSE ONCOLOGY
Location: ESMO venue, IFEMA, Madrid, Spain - Room A6.1
[Slide 1]
Trotabresib
Adding a BET inhibitor to chemoradiotherapy in glioblastoma
Newly diagnosed IDH-wildtype GBM
After surgery
n = 184
→ RANDOMIZE (Randomized phase II; 2:1)
RT + TMZ (n = 60) | 12-month PFS* 38.9%
+ trotabresib (n = 124) | 12-month PFS* 22.2%
*Primary endpoint: PFS by local RANO. 12-month PFS favored control (P = .048); HR not reported.
Median OS 16.7 vs 16.9 months (P = .898), not statistically significant. G3+ thrombocytopenia: 15.3% vs 37%.
Dipasquale et al. ESMO 2026, 692O. RT dose not reported in abstract; median follow-up 15 months.
[Slide 1]
4155RO - Rivoceranib in patients with pretreated metastatic thymic epithelial tumors: Phase II multi-center KCSG LU23-09 (THRIVE) trial
Speakers Sehhoon Park (Seoul, Republic of Korea)
Lecture Time 11:02 - 11:07
Abstract
Background
Metastatic thymic epithelial tumors (TETs) are rare malignancies with limited options beyond cytotoxic chemotherapy and immunotherapy. Prior studies have shown that anti-angiogenic tyrosine kinase inhibitors produce meaningful clinical activity . Rivoceranib is a highly selective oral VEGFR-2 inhibitor. We report the updated efficacy and safety analysis in pretreated metastatic TET.
Methods
THRIVE (KCSG LU23-09) is an open-label, single-arm, phase II trial at 11 Korean sites. Patients with metastatic thymoma (WHO A, B1, B2, B3) or thymic carcinoma, who had received ≥1 prior systemic therapy, received rivoceranib 700 mg orally once daily until progression or unacceptable toxicity. The primary endpoint was investigator-assessed objective response rate (ORR); secondary endpoints were disease control rate (DCR), progression-free survival (PFS), duration of response (DoR), overall survival (OS) and safety.
Results
From Sep 2024 to Feb 2025, 43 patients were screened, and 40 patients received rivoceranib. Median age was 60 years (29–82), 62.5% were male, and either ECOG of 0 or 1 (32.5%, 67.5%). Thymic carcinoma 24 (60.0%), thymoma 16 (40.0%), including thymoma A, B1, B2, B3 (2.5%, 7.5%, 20.0%, 10.0%, respectively). Confirmed ORR was 35.0% (14/40; 95% CI 22.1–50.5; all PRs) and DCR 85.0%. At data cutoff (Apr 2026), median follow-up duration was 13.6 months (95% CI 12.8-13.8). Median PFS was 11.8 months (95% CI 7.2-NR) overall, not reached (95% CI 5.5-NR) in thymoma and 10.0 months (95% CI 5.9-NR) in carcinoma. OS was NR (95% CI 12.6-NR). Treatment-related adverse events (TRAEs) occurred in 97.5%, grade ≥3 in 55.0% patients. Common grade ≥3 were hypertension (22.5%), proteinuria (17.5%), and stomatitis/anemia (10.0% each), all manageable with appropriate treatment. No grade-5 events occurred. TRAEs led to dose reduction, interruption, and discontinuation in 67.5%, 55.0%, and 7.5%, respectively.
Conclusions
Rivoceranib showed durable antitumor activity in pretreated metastatic TET, with similar response rates across histologies but longer disease control in thymoma. Toxicity was consistent with the VEGFR-2 inhibitor class and manageable, supporting rivoceranib as a treatment option for metastatic TET.
[Slide 1]
GORTEC IDEAL
Induction EGFR-ADC with or without anti-PD1 before CRT
Locally advanced
Head and neck SCC
n = 49 randomized
→ RANDOMIZE
Grade 3 TEAEs, safety subset
EGFR-ADC, then CRT 2/10
+ anti-PD1 6/10
Becotatug vedotin x3 +/- pucotenlimab, then 70 Gy + cisplatin; combination arm also receives adjuvant anti-PD1.
Phase II; 106 planned. First 20 safety-evaluable pts only. Primary CR at 12 weeks after CRT remains immature.
Tao et al. ESMO 2026, 1538RO. No grade 4 AEs; one death in ADC-only arm deemed unrelated. No efficacy conclusion.
[Slide 1]
ESMO 2026 | MADRID
EVIDENCE NOTES
MADRID 2026 ESMO congress [logo]
PRESIDENTIAL SYMPOSIUM III / LBA12
KEYNOTE-C93
26 OCT 2026, MONDAY
16:30 Madrid | 18:30 Istanbul
Presenter: Brian M. Slomovitz
CAN FIRST-LINE dMMR ENDOMETRIAL CANCER GO CHEMO-FREE?
Advanced / recurrent dMMR endometrial cancer • pembrolizumab monotherapy vs carboplatin + paclitaxel
[uterus illustration with inset: dMMR]
01 DISEASE & PATIENT POPULATION
• Advanced or recurrent endometrial carcinoma
• Centrally confirmed dMMR
• First-line systemic treatment
• No prior systemic chemotherapy; eligible patients recurring >6 months after prior adjuvant therapy included
02 STUDY DESIGN
Phase 3
Randomized open-label
n = 299
Dual primary endpoints: PFS + OS
PFS: BICR / RECIST 1.1
03 TREATMENT ARMS
Experimental arm
Pembrolizumab
400 mg IV
every 6 weeks • up to 18 cycles (~2 years)
VS
Control arm
Carboplatin + paclitaxel
every 3 weeks • 6 cycles
04 WHAT WE KNOW NOW
PFS primary endpoint met
Statistically significant and clinically meaningful PFS improvement reported with pembrolizumab.
OS trend favors pembrolizumab, but data are immature.
Clinically meaningful ORR / CRR / DoR signal reported; exact numbers not yet public.
A chemo-free first-line option is now a real possibility.
NOT YET DISCLOSED
PFS HR and 95% CI
Median PFS and absolute difference
OS HR / maturity
Exact ORR, CRR and DoR values
Grade ≥3 toxicity and discontinuation
Awaiting full LBA12 presentation.
05 CLINICAL READING
Key question: Is dMMR biology strong enough for immunotherapy alone to replace chemotherapy?
PFS is positive; magnitude of benefit, OS maturity and toxicity balance will determine practice impact.
Data status: company topline + ESMO 2026 programme; full LBA12 presentation awaited.
Sources: drozdogan.com • Merck topline, 15 Jul 2026 • NCT05173987 • ESMO 2026 programme
drozdogan.com
[Slide 1]
ESMO 2026 / MADRID
EVIDENCE NOTES
MADRID 2026 ESMO congress [logo]
PRESIDENTIAL SYMPOSIUM III / LBA10
MOIO
26 OCT 2026, MONDAY
16:30 Madrid | 18:30 Istanbul
CAN LESS-FREQUENT IMMUNOTHERAPY PRESERVE BENEFIT IN RESPONDING METASTATIC CANCER?
CR/PR after 6 months of standard ICI • every 3 months vs standard frequency
01 DISEASE & PATIENT POPULATION
• Adults with metastatic cancer
• PR or CR after 6 months of standard ICI
• Multiple tumour types (lung, RCC, head & neck, urothelial, TNBC, HCC, MSI colorectal, etc.)
• Melanoma in complete response excluded
02 STUDY DESIGN
Phase 3
Randomized / open-label / non-inferiority
n = 646 planned
France / 36 centres
03 TREATMENT ARMS
Reduced-frequency arm
Same immunotherapy every 3 months after month 6
VS
Standard approach
Standard immunotherapy frequency
approved routine schedule
Same agent / same dose level
04 WHAT WE KNOW NOW
• Primary endpoint: PFS non-inferiority
• Secondary endpoints: OS, quality of life, toxicity, cost-effectiveness
• Selected as a Presidential LBA at ESMO 2026
The question is not just efficacy - can treatment burden be reduced?
NOT YET DISCLOSED
• PFS HR and 95% CI
• Absolute differences and medians
• Grade ≥3 toxicity and discontinuation
• Quality-of-life impact / patient burden
• Cost-effectiveness results
! Awaiting full LBA10 presentation.
05 CLINICAL READING
Key question: not whether it is positive, but whether it is sufficient - can less-frequent dosing preserve efficacy while meaningfully reducing toxicity, visits and cost?
Treatment optimisation may matter as much as new drug development.
Data status: protocol publication + ESMO 2026 programme; full LBA10 presentation awaited.
Sources: BMC Cancer 2023; MOIO protocol / NCT05078047; ESMO 2026 programme.
drozdogan.com
[Slide 1]
[photo of stage panel with 3 speakers; two screens showing the same slide]
A connected digital pathology [network to expand access,] standardise quality and reduce health [disparities in Brazil] [title partly cropped on right screen; full title on left screen: "A connected digital pathology network to expand access, standardise quality and reduce health disparities in Brazil"]
[map of Brazil with regional hubs]
NORTH
NORTH-EAST
WEST-CENTRAL
SOUTH-EAST
SOUTH
ACCC Central Hub (São Paulo)
Reference centre for complex cases and expert consultation
LEGEND
Physical sample flow (for regional hubs)
Digital images and data flow
Local Centre (hospital or laboratory)
Regional Digital Pathology Hub (slide scanning and case preparation)
ACCC Central Hub (reference for complex and expert consultation)
Tissue specimen (biopsy or surgical specimen)
[left screen also shows a right-hand step panel, mostly illegible: "Sample collection at local centres" — uncertain; "Physical shipment to regional hubs"; "Slide scanning at regional hubs"; "Digital images sent for analysis"; "Interpretation and collaboration"; "Report ..." — [illegible] small text]
[Slide 1]
BREAKING NEWS
Spiritual Interventions in Cancer Care [Systematic Review]
Effects on biological and physiological markers in cancer patients
@FernandoOnco
ONCOLOGIA BASEADA EM EVIDÊNCIAS PARA UMA PRÁTICA MELHOR
82 studies included
Adults with cancer
Prayer, meditation, mindfulness
6760 records identified
Methods
JBI methodology, PRISMA and PICO framework
Databases: PubMed, MEDLINE, CINAHL, Scopus, Web of Science, Cochrane Library, SciELO
Search through January 2026
Outcomes assessed
Cortisol, cytokines, CRP
Immune cell counts
Cardiovascular measures
RESULTS Spiritual interventions were associated with favorable changes in multiple biological and physiological markers in patients with cancer.
Stress response [down arrow] Reduced cortisol levels
Inflammation [down arrow] Decreased pro-inflammatory cytokines: IL-1β, IL-6, IL-8, TNF-α
Immune function [up arrow] Enhanced NK cell activity and interferon-γ production
Autonomic regulation [up arrow] Higher heart rate variability and lower resting heart rate
Other signals Possible inhibition of inflammatory pathways (e.g., NF-κB), effects on oxidative stress and markers of cellular aging
KEY TAKEAWAY
Spiritual interventions were associated with favorable changes in multiple biomarkers and physiologic indicators, suggesting potential benefits through stress modulation, immune regulation, and attenuation of inflammatory responses.
CONCLUSIONS
• Evidence supports beneficial biologic and physiologic effects.
• Findings are promising for integrative oncology care.
• Most evidence was synthesized narratively.
Clinical question
Should spiritual care be more intentionally integrated into comprehensive cancer care?
What's your take?
@FernandoOnco | Discussing today. Improving tomorrow. #IntegrativeOncology #CancerCare #SpiritualCare
[Slide 1]
MADRID 2026 ESMO congress
Take home messages
The new era of precision oncology demands:
Precision
• So test can guide patients' treatment in the right direction
Speed
• So timely precise decisions can be made for patients
Access
• So precise, and timely treatments can be offered to patients at-large
A multi-omic liquid biopsy approach can help satisfy all of the above
requirements to bring sustainable precision oncology to our patients.
Presented by HH Loong | @herbloong | ESMO 2026
[Slide 1]
MADRID 2026 ESMO congress
GHG GoBroad Healthcare Group 高博医疗集团
38
Abstracts Accepted for ESMO Congress 2026
Research Highlights from GHG and Associated Expert Teams
[four stat tiles with icons]
3 LBA
6 Oral
24 Poster
5 E-Poster
[Madrid skyline silhouette graphic]
ESMO Congress 2026 | Madrid, Spain | 23–27 October 2026
[Slide 1]
Special session
Quantifying the magnitude of clinical benefit in a changing trial landscape
Date Fri, 23.10.2026
Chairs Dirk Arnold (Hamburg, Germany), Sjoukje F. Oosting (Groningen, Netherlands)
Room Oviedo Auditorium - Hall 5
Time 13:30 - 15:00
Special session
How do I read and interpret a cancer clinical trial? Perspectives on critical appraisal from a practising clinician
Speakers Bishal Gyawali (Kingston, Canada)
Lecture Time 13:30 - 13:50
Special session
Magnitude of benefit in de-escalation trials: Update on the development of a scoring system for "near-equivalence" studies
Speakers Dirk Arnold (Hamburg, Germany)
Lecture Time 13:50 - 14:10
Special session
Novel trial endpoints: What does the future hold?
Speakers Eva Blondeaux (Genova, Italy)
Lecture Time 14:10 - 14:30
[Slide 1]
ESMO 2026 Presentations by Stage
[legend, top to bottom]
Phase 3
Phase 2
Phase 1
Phase 1b
Phase 1b/2
Approved
Phase 2/3
Preclinical
Phase 2a
Others
[donut chart; labelled segments, clockwise from top]
38.8%
17.9%
13.4%
9.0%
4.5%
[remaining smaller segments unlabelled]
Phase 3 is the largest single block —
most of this year's data is
registrational, not exploratory.
Visit our ESMO dashboard for
more presentation details.
BioPharm CATALYST
[Slide 1]
MADRID 2026 ESMO congress
Quantifying the magnitude of clinical benefit in a changing trial landscape
FRI, 23.10.2026 13:30 - 15:00
OVIEDO AUDITORIUM - HALL 5
[ESMO logo; Madrid skyline illustration]
[Slide 1]
MADRID 2026 ESMO congress
ESMO Clinical Practice
Guidelines 1
SAT, 24.10.2026 10:15 - 11:45
LEON AUDITORIUM - HALL 4
ESMO
[Madrid skyline graphic]
[Slide 2]
MADRID 2026 ESMO congress
ESMO Clinical Practice
Guidelines 2
SUN, 25.10.2026 10:15 - 11:45
LEON AUDITORIUM - HALL 4
ESMO
[Madrid skyline graphic]
[Slide 3]
MADRID 2026 ESMO congress
How can the use of ESMO's
Clinical Practice Guidelines (CPG)
help drive standards of care?
MON, 26.10.2026 14:45 - 16:15
SEVILLE AUDITORIUM - NCC
ESMO
[Madrid skyline graphic]
[Slide 1]
[ESMO Congress Madrid 2026 logo]
ESMO Women for
Oncology Award
Gender matters:
Shaping better
science in oncology
Pilar Garrido, Spain
[photo of Pilar Garrido; Madrid skyline silhouette]
FRIDAY, 23.10.2026 11:30 - 13:00
ALICANTE AUDITORIUM - HALL 6
[ESMO logo]
[Slide 1]
MADRID 2026 ESMO congress
Beyond guidelines: Expert navigation through the grey zones of oncology practice
SAT, 24.10.2026 10:15 - 11:45
MURCIA AUDITORIUM - HALL 3
ESMO
[Figure: Madrid skyline artwork.]
[Slide 1]
GRAIL
GRAIL to Present New Data From NHS-Galleri and PATHFINDER 2 at EDCC and ESMO Congress 2026
Early Detection of Cancer Conference (EDCC)
Edinburgh, UK | Oct. 6-8, 2026
European Society of Medical Oncology (ESMO) Congress
Madrid, Spain | Oct. 23-27, 2026
[Slide 1]
MADRID 2026 ESMO congress
"Scientific progress depends on seeing the full picture, and the ESMO Congress has always been where many of the year's most important advances in cancer research are presented and debated."
James Larkin,
Scientific Committee Co-Chair
#InsightsbyESMO
[Headshot of James Larkin; ESMO logo]
[Slide 1]
Man, 67 years old
What would you recommend before ESMO 2026?
A 67-year-old man was recently diagnosed with PCa.
> Medical history: no relevant comorbidities or medication
> ECOG PS: 0
> PSA: 28.6 ng/ml
> Other lab values: normal
> Clinical stage: cT3a
> mpMRI: PI-RADS 5 lesion in the left peripheral zone with evidence of extracapsular extension; no seminal vesicle invasion
> Prostate biopsy: ISUP grade group 5 (Gleason score 4+5)
> Bone scan and CT scan:
• No pelvic lymph node involvement
• No distant metastases
Options:
Primary RT (prostate ± pelvic LNs) + long-term ADT (18-36 months)
Primary RT (prostate ± pelvic LNs) + long-term ADT + abiraterone/prednisone
Primary RT (prostate ± pelvic LNs) + long-term ADT + enzalutamide
[Slide 2]
At a Glance:
Research and Programming
• 2 Rapid Oral Presentations
• 10 Poster Presentations
• Booth Talks Series
• Expert-led sessions from the Foundation Medicine team.
[Foundation Medicine logo mark, bottom right]
[Slide 3]
Learn more about our
portfolio of tests and services
Including FoundationOne®MRD*—
a 2026 Top Innovation in Healthcare
and Diagnostics by The Scientist.
*FoundationOne MRD is performed by SAGA Diagnostics US, Inc. and has
not been cleared or approved by the FDA.
[Foundation Medicine logo mark, bottom right]
[Slide 1]
SynOx Therapeutics is presenting at
ESMO Congress 2026
Title: Primary Analysis of TANGENT: A Phase 3 Randomised Trial Evaluating the Safety and Efficacy of Emactuzumab in Patients With Tenosynovial Giant Cell Tumours
Presenter: Hans Gelderblom, Department of Medical Oncology, Leiden University Medical Centre, Leiden, The Netherlands
Saturday 24th October | Time: 14:45
Madrid, Spain | Malaga Auditorium - Hall 3
We hope to see you there!
SynOx Therapeutics [logo]
[background: Madrid skyline at dusk, Metropolis building]
[Slide 1]
SynOx Therapeutics to present at
ESMO Congress 2026
Title: Primary Analysis of TANGENT: A Phase 3 Randomised Trial Evaluating the Safety and Efficacy of Emactuzumab in Patients With Tenosynovial Giant Cell Tumours
Presenter: Hans Gelderblom, Department of Medical Oncology, Leiden University Medical Centre, Leiden, The Netherlands.
Saturday 24th October | Time: 14:45
Madrid, Spain | Malaga Auditorium - Hall 3
"Selection for a late-breaking Proffered Paper presentation at ESMO reflects the significance of these results for the TGCT community. We are grateful to the patients, families and investigators and site staff whose participation made TANGENT possible."
Elyse Seltzer, M.D., Chief Medical Officer
[Headshot of Elyse Seltzer; Madrid Metropolis building background]
SynOx Therapeutics
SPAIN MADRID | October 23-27
[Slide 1]
1.5 CME/MOC/CC/EBAC/NCPD/AAPA/IPCE
Monday, 26 October 2026
Leveraging HER2-Targeted ADCs in Solid Tumours
Expert Strategies for Advancing Biomarker Testing, Decoding Data, and Closing Treatment Gaps
[headshot] CHAIR & PRESENTER Kathleen N. Moore, MD, MS, FASCO
[headshot] PRESENTER Stephanie PL Saw, MBBS, MMed, MRCP, PhD
[headshot] PRESENTER Prof. Eric Van Cutsem, MD, PhD
Join us live—in person or virtually!
PeerView Live
[background: 3D render of cells and antibody molecules]
[Slide 2]
Session
Optimal
Multidisciplinary
Management of
Penile Cancer
26 October 2026 · 14:45–16:00
Córdoba Auditorium · Hall 4
[headshot photo of Dr. Fernando Maluf, purple gradient background]
Dr. Fernando Maluf
Session Chair
[Slide 1]
[two smiling-face logo]
THE IMMUNOBUDDIES
A PODCAST ON CANCER IMMUNOTHERAPY
ESMO 2026 PREVIEW • EPISODE 4
The Next Wave of ADCs
Which area of development
are you watching most closely?
A [chain-link icon] LINKERS
Fine-tuning where payloads are released.
B [target icon] TARGETS
Expanding which tumors ADCs can reach.
C [flask icon] PAYLOADS
Exploring new mechanisms and combinations.
D [shield icon] TOXICITY
Understanding and reducing side effects.
[speech-bubble icon] A, B, C or D? Tell us why in the comments.
Explore the conversation on DocWireNews
[Slide 1]
SynOx Therapeutics to present
Primary Analysis of Ph 3 TANGENT Study at
ESMO Congress 2026
Title: Primary Analysis of TANGENT: A Phase 3 Randomised Trial Evaluating the Safety and Efficacy of Emactuzumab in Patients With Tenosynovial Giant Cell Tumours
Presenter: Hans Gelderblom, Department of Medical Oncology, Leiden University Medical Centre, Leiden, The Netherlands.
"This milestone marks an important step in our mission to bring a new treatment option to people living with TGCT. We look forward to sharing the primary analysis with the oncology community in Madrid.
Robert Francomano - Chief Commercial Officer."
[Photo of a smiling bearded man in a navy suit and patterned gold tie; Madrid skyline backdrop; SynOx Therapeutics logo bottom-left]
Saturday 24th October | Time: 14:45
Madrid, Spain | Malaga Auditorium - Hall 3
[Slide 1]
ESMO 2026 Industry Satellite Symposium
AI-Enabled Multi-omic Liquid Biopsy Across the Cancer Care Continuum:
From Technological Innovation to Scalable Clinical Implementation
#FacultyNote
Next-generation MCED brings together complementary biological signals to improve early-stage cancer detection.
By integrating multiple cfDNA features through machine learning, we developed an approach that was prospectively evaluated in more than 9,000 asymptomatic adults and subsequently used in real-world practice among more than 100,000 individuals in 10 Asian countries.
The evidence generated across these settings represents an important step toward broader clinical implementation in diverse healthcare systems.
Dr. Tran Le Son | Medical Genetics Institute, Vietnam
GENE SOLUTIONS
[Figure: headshot of Dr. Tran Le Son in white coat.]
FAQ
About this slide library
What is the ESMO 2026 slide library?
A curated gallery of the 672 infographics and conference-slide photos that oncologists, societies, media and companies posted on X around the ESMO Congress 2026 (Madrid, October 23–27), compiled by KOL Pulse. Each card links to the original post and keeps the author's full text.
How is it organized?
Nine sections in a fixed order: Top-10 & list posts, Lung, Breast, GI, GU, Melanoma, Hematology, Gyn oncology and Other. A card's tumor type comes from the clinical trials it names (via the KOL Pulse trial registry) or, failing that, from the post and slide text; list posts appear in Top-10 and, when one tumor type dominates, in that section too. Within a section physician posts come first, then by reach.
How do I filter by trial or by KOL?
Use the chips to pick a section, the "Filter by trial" menu to keep only cards naming a trial, and the KOL menu or the "Built by" avatars to keep one author. Filters combine; the counts update to show only combinations that have results, and "Clear filters" or the Escape key resets. Every state has a shareable link, for example #lung&kol=glopesmd.
What is the OCR text under each slide and why is it there?
"View OCR Text" opens a verbatim transcription of the slide image, produced by vision transcription and checked by our gibberish gate; survival curves are captured as the printed numbers only, never read off the curve. It makes slide content searchable, quotable and readable by AI assistants, which cannot see text inside images.
Can I use this page with my own AI assistant (NotebookLM, Perplexity, Claude, ChatGPT)?
Yes. Paste the page URL, or a filtered link, into your assistant and ask questions against it. Example prompt: "From the slide transcriptions on this page, list every place a speaker argued the standard of care is changing, with the speaker, session and the exact slide text."
Compiled and reviewed by the KOL Pulse research team, led by Brian Shields, Founder, KOL Pulse. Last updated October 23, 2026. Every card links to its original post; slide text is a verbatim transcription.