FDA-approved May 22, 2026 — datopotamab deruxtecan (Datroway) as first-line treatment for unresectable/metastatic TNBC in patients who are not PD-1/PD-L1 inhibitor candidates. Pivotal Phase III TROPION-Breast02: PFS HR 0.57; OS HR 0.79 (23.7 vs 18.7 mo) — a new 1L standard of care.
Discover KOL Sentiment on TROPION-Breast02 →Posts by physicians about TROPION-Breast02 during ESMO 2026 week (October 17–24, 2026). Each post is shown in full and verbatim, newest first, and linked to the original on X.
 𝕏
TROPION-Breast02 brain mets analysis at #ESMO26 (Dent). 1L Dato-DXd vs chemo, mTNBC, n=61 with BMs: CNS PFS 9.5 vs 2.6 mo, HR 0.27 icORR (measurable) 62.5% vs 37.5% Untreated BMs: OS HR 0.35 Longest icDoR ~27 mo Preferred Trop2 ADC for brain Mets! @RebeccaDSing Exploratory, small n, real CNS signal. #bcsm
 𝕏
TROPION-Breast02 #ESMO26 In 1L mTNBC with brain metastases, Dato-DXd showed promising intracranial and systemic activity vs chemotherapy: • CNS PFS: 9.5 vs 2.6 months (HR 0.27) @OncoAlert #BreastCancer #Bcsm https://t.co/IfL8AktwcJ
 𝕏
presents efficacy of Dato-Dxd in patients with TNBC on TB02. In the small subset with BMs Dato DXd improved CNS response and PFS! Nice data immediately applicable to clinical practice. @myesmo #ESMO2026 @OncoAlert https://t.co/AeMylHCL7g
 𝕏
🧠 Dato-DXd in TNBC brain metastases? TROPION-Breast02 (LBA96), 1L, stable/asymptomatic brain mets: PFS: 7.7 vs 3.5 mo (HR 0.37) OS: 13.5 vs 10.7 mo (HR 0.55) Extracranial ORR: 63% vs 19% Early intracranial responses, including 1 CR. Exploratory data. @ESMO_open @myesmo @oncoalert @ASCO #ESMO26
 𝕏
TROPION-Breast02 CNS fabulously presented by @RebeccaDSing n=61 with baseline brain mets n=35 on Dato-DXd arm (16 had prior treatment for brain mets) PFS HR 0.37, OS HR 0.55 iORR: 62.5% vs 37.5% @OncoAlert #ESMO26 https://t.co/XHUe50PHDU
 𝕏
🔥 Good news for TNBC patients with brain mets! Dato-DXd shows clinically meaningful activity in BMs ⚠️ Caveat: small TB02 subgroup, only half with active BMs (asymptomatic, untreated) 👉 Key message: after T-DXd, Dato-DXd also shows clear intracranial activity #ESMO26 https://t.co/qhga4c8djj
 𝕏
Oral abstract #BreastCancer session at #ESMO26: more data from TROPIONbreast02 trial presented by super @RebeccaDSing showing important CNS activity of #DatopotomabDeruxtecan in patients with triple-negative advanced disease @OncoAlert @myESMO https://t.co/lc4QVllaGm
 𝕏
Important data presented at #ESMO2026 TROPION-Breast02 | 1L mTNBC with brain metastases • Median CNS PFS: 9.5 vs 2.6 months (HR 0.27) • Intracranial ORR: 62.5% vs 37.5% Dato-DXd showed great activity, regardless of prior CNS-directed therapy in TNBC @OncoAlert https://t.co/M84knqaYE0
 𝕏
#ESMO26 | TROPION-Breast02 – CNS Analysis In 1L mTNBC with asymptomatic brain metastases, Dato-DXd vs chemotherapy demonstrated: Promising intracranial activity, including in patients without prior CNS-directed therapy. https://t.co/k71kbE1Wln
 𝕏
At #ESMO26 Proffered Paper 2️⃣ on #breastcancer Exploratory analysis of Tropion-Breast02 by @RebeccaDSing focusing on pts with brain mets 🧠 Dato-DXd showed consistent systemic (PFS, OS, ORR) and intracranial benefit (icORR, CNS-PFS) vs. TPC in pts with brain mets @OncoAlert https://t.co/fWbXavgiOB
 𝕏
Promising CNS activity with Dato-DXd! #TROPIONBreast02: In 61 patients with mTNBC & asymptomatic brain metastases, median CNS PFS was 9.5 vs 2.6 months with chemo (HR 0.27). Included patients without prior CNS-directed therapy—a key strength. #ESMO26 #BCSM @Larvol @OncoAlert https://t.co/X3K0Pr45xT
 𝕏
Dato-dxd shows an intracranial ORR of 62.5 % and median CNS PFS of 9.5 mos in pts with brain metastases (TROPiON-Breast02) #ESMO26 #ESMOAmbassadors #ESMOcommunity @esmo @RebeccaDSing https://t.co/Q7Zj5mqdva
 𝕏
TROPIONBreast02 DatoDXd vs TPC chemo in 1L mTNBC brain Mets analysis by @RebeccaDSing Allowed treated or untx + asymptomatic brain mets (n=61) Intracranial response 62.5% vs 37.5% w/ durable benefit at 12 weeks 75% vs 50% #ESMO26 @OncoAlert https://t.co/HguoAefquz
 𝕏
📌 First-line Dato-DXd vs chemotherapy in pts with locally recurrent inoperable or mTNBC for whom immunotherapy was not an option: Exploratory analysis ✨@RebeccaDSing #ESMO26 🇪🇸 @OncoAlert #OncoAlertAF https://t.co/vKFNin6HT7
 𝕏
ESMO 2026 | Can ADCs overcome the blood–brain barrier? TROPION-Breast02: Dato-DXd vs chemotherapy in metastatic TNBC with brain metastases. • CNS PFS: 9.5 vs 2.6 months (HR 0.27) • Intracranial ORR: 62.5% vs 37.5% Promising intracranial activity, although subgroup findings remain exploratory. #ESMO26 #TNBC #ADC @myesmo @oncodaily @OncoAlert @OncoDailyBreast @OncBrothers @PTarantinoMD
 𝕏
🧠 #TROPIONBreast02 at #ESMO26 🇪🇸 In 1L mTNBC with brain metastases, Dato-DXd showed promising systemic and intracranial activity 🆚 chemo: 🔹 CNS PFS: 9.5 vs 2.6 months (HR 0.27) 🔹 Intracranial ORR: 62.5% vs 37.5% in measurable disease @OncoAlert @myESMO https://t.co/Ncc4N6yEqk
 𝕏
🧠 CNS activity of a TROP2 ADC in a randomized phase 3. #ESMO26 LBA96: brain mets analysis of TROPION-Breast02, Dato-DXd vs chemo in 1L TNBC patients who are not IO candidates. 🧵 #bcsm 61 of 644 patients had asymptomatic, stable brain mets (30 untreated, 31 previously treated). 24 had measurable intracranial disease. 🙌🏻 Intracranial response: ORR 62.5% vs 37.5%, including a complete response 12-week intracranial disease control 75% vs 50% 🙌🏻 CNS PFS 9.5 vs 2.6 mo, HR 0.27 (95% CI 0.13–0.56). Systemic PFS in the brain mets group: 7.7 vs 3.5 mo, HR 0.37. The signal held in *untreated* brain mets: PFS HR 0.29, OS HR 0.35. That's the group where systemic options matter most. Bottom line: Dato-DXd is a reasonable systemic choice for 1L TNBC with brain mets.
PFS (primary) - Median 10.8 vs 5.6 mo, HR 0.57 (95% CI 0.47-0.69), P<0.0001 - primary endpoint met.
OS - Median 23.7 vs 18.7 mo, HR 0.79 (95% CI 0.64-0.98), P=0.0290 (FDA approval notice, May 22, 2026) - significant; first targeted therapy to beat chemo on OS in this setting.
Response - Confirmed ORR 64% vs 30% with chemotherapy.
Regulatory status & clinical implications - FDA approved May 22, 2026 (Datroway) - first TROP2 ADC for 1L immunotherapy-ineligible metastatic TNBC.
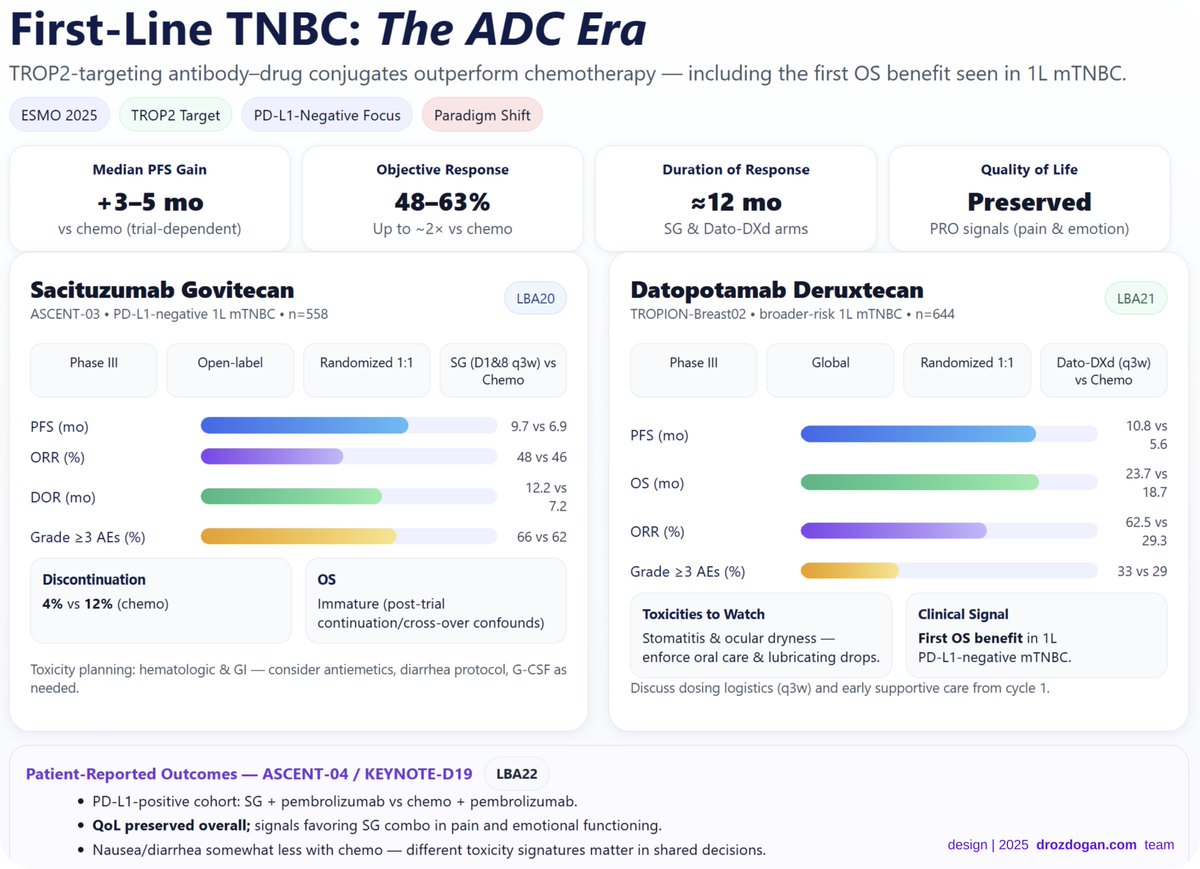
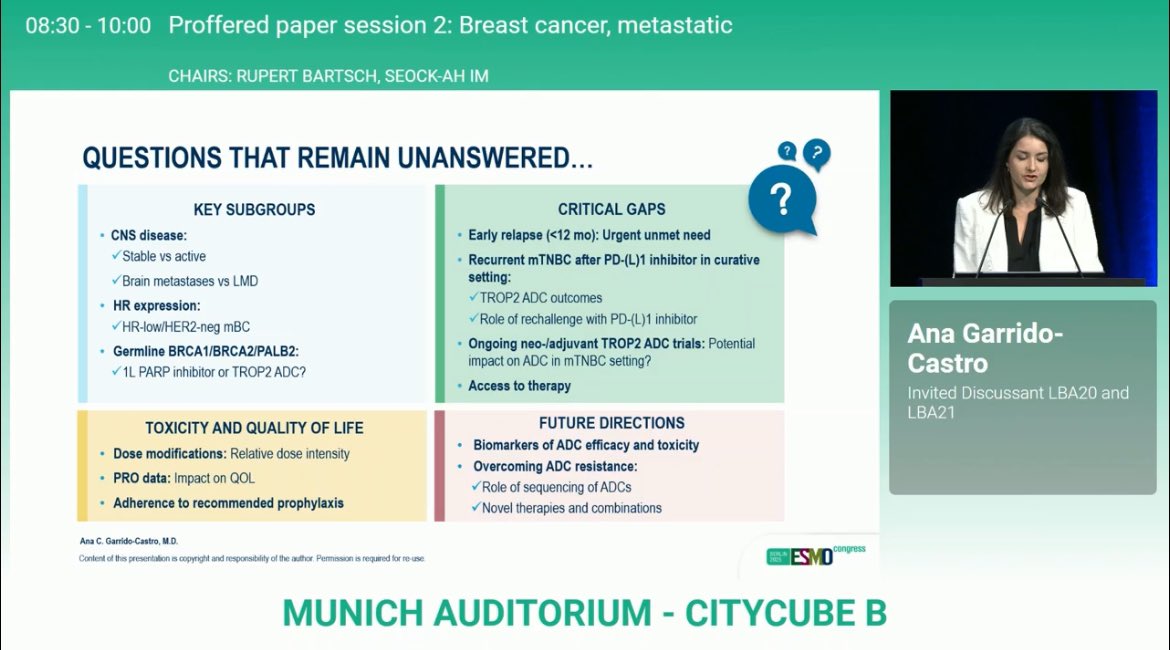
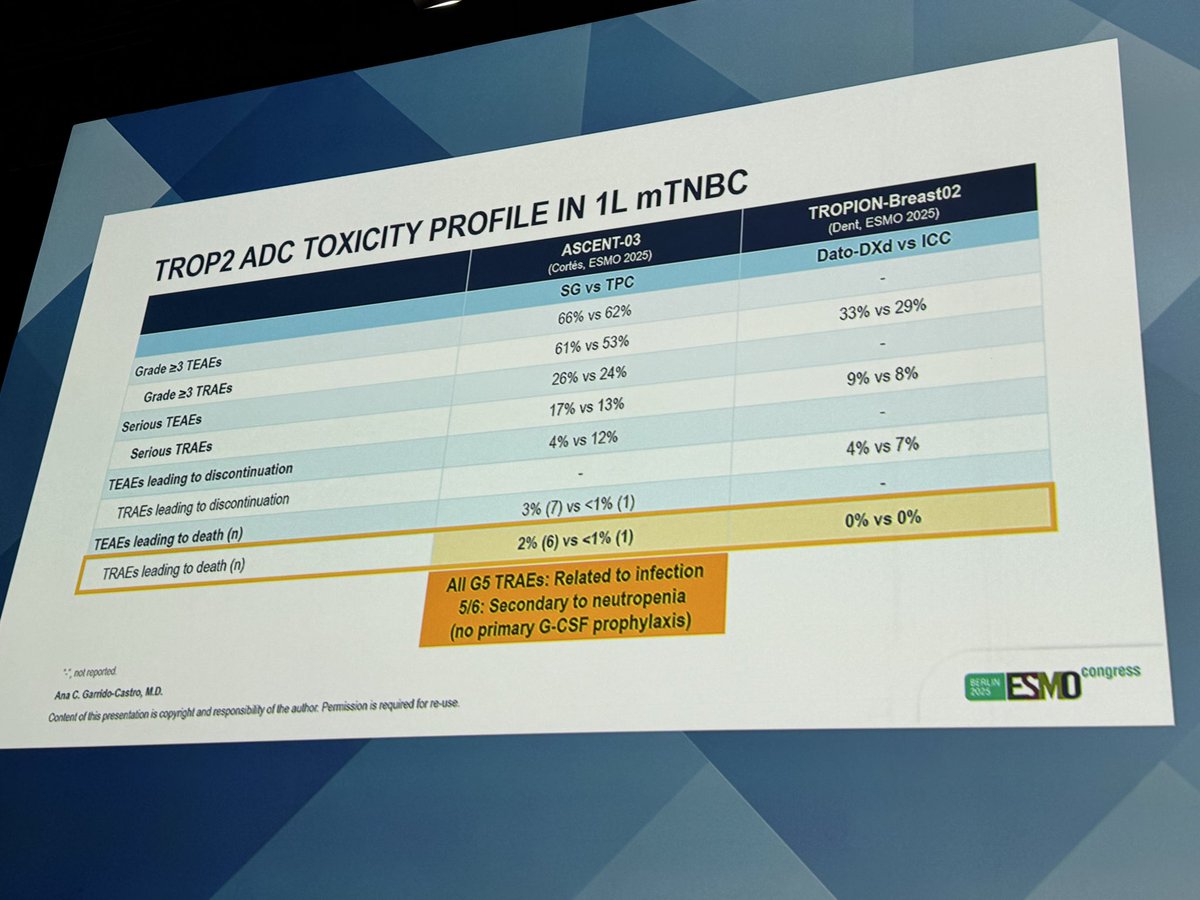
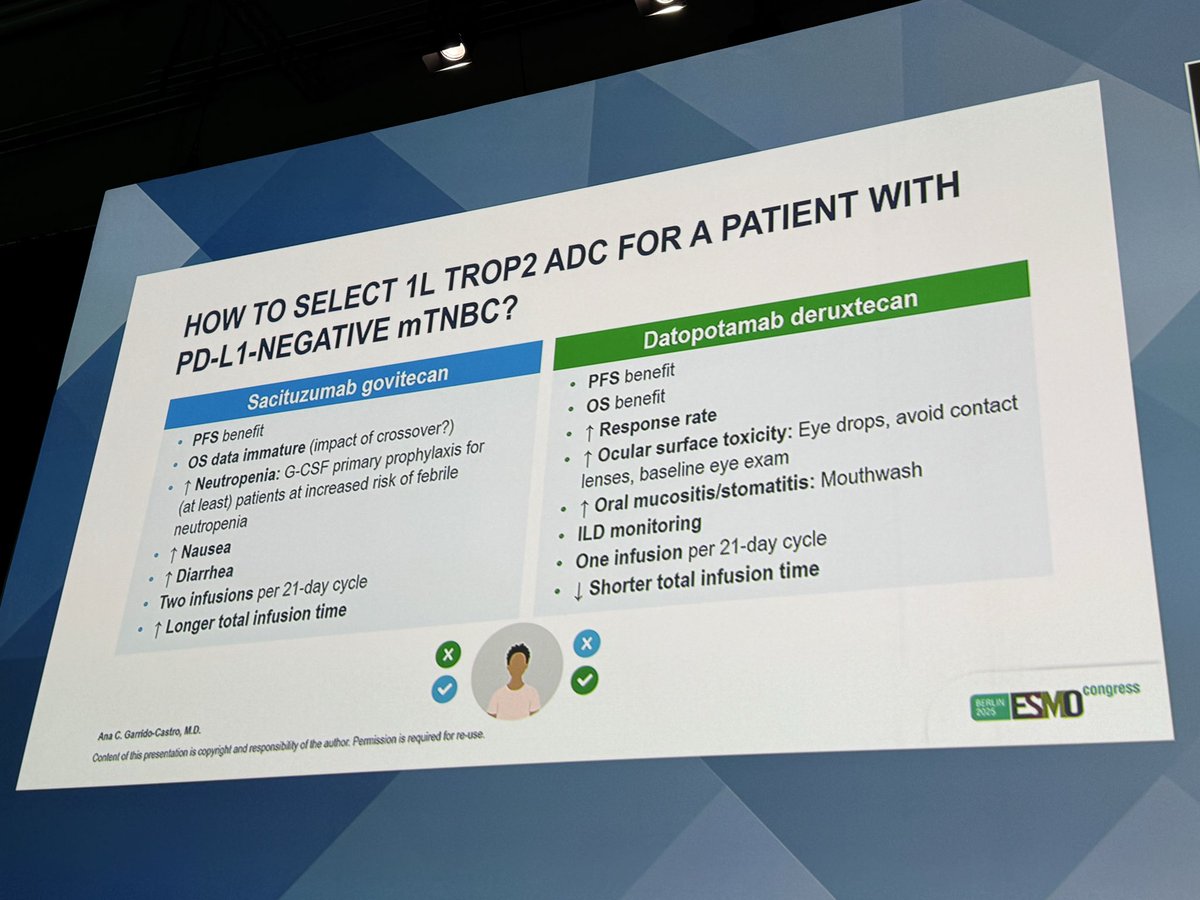
Mustafa Özdoğan (@ozdogan_md) framed the readout as a “Paradigm Shift in 1L TNBC” in which the field “may be witnessing the end of chemotherapy’s monopoly in PD-L1–negative metastatic TNBC,” noting “Dato-DXd delivers the first OS benefit in this setting” while “SG shows a robust PFS advantage and prolonged DOR ≈ 12 mo.” Erika Hamilton drew the head-to-head contrast with ASCENT-03, noting TROPION-Breast02 had “poorer prognosis pts, 15% relapsed within 6 mo of neoadj/adj thpy,” “no doublet chemo,” and “no crossover to ADC.” Paolo Tarantino flagged a discordance in guideline interpretation: “Not sure of the reasoning behind the different recommendation categories for SG and Dato-DXd in PDL1- disease, despite OS advantage with Dato-DXd?” Elisa Agostinetti relayed discussant Ana Garrido-Castro’s ESMO 2025 side-by-side comparison of ASCENT-03 and TROPION-Breast02, noting that crossover was allowed in ASCENT-03 but not in TROPION-Breast02 — potentially impacting OS — and that TROPION-Breast02 enrolled patients with more aggressive disease. Garrido-Castro framed the practical takeaway as a choice to be guided by the safety profile of each ADC.
Sponsor / drug - Daiichi Sankyo + AstraZeneca; datopotamab deruxtecan (Datroway).
Compiled and reviewed by the KOL Pulse research team, led by Brian Shields, Founder, KOL Pulse. Last updated October 24, 2026.
PFS by BICR: HR 0.57 (p<0.0001); 12-month PFS rate 45.6% vs 25.6%; 18-month 32.7% vs 16.8%. Investigator-assessed PFS: 9.6 vs 5.2 months (HR 0.56). OS: median 23.7 months Dato-DXd (95% CI 19.8-25.6) vs 18.7 months ICC (95% CI 16.0-21.8); HR 0.79 (95% CI 0.64-0.98; p=0.0291; ESMO 2025 LBA21, data cutoff Aug 25, 2025) — 21% reduction in death risk. 12-mo OS 75.2% vs 67.8%; 18-mo 61.2% vs 51.3%. Confirmed ORR 62.5% vs 29.3% (Δ33.2%). Median DoR 12.3 vs 7.1 months. PRO update at ESMO Breast 2026: median TTD global health 23.5 vs 8.3 months (HR 0.64); arm symptoms HR 0.51; physical function HR 0.67.
Treatment duration was substantially longer with Dato-DXd vs ICC, yet PROs consistently favoured Dato-DXd across global health, physical functioning, arm symptoms, and pain domains. Safety profile consistent with prior Dato-DXd experience: stomatitis, nausea, fatigue, alopecia. ILD/pneumonitis monitoring critical (DXd-class effect). Patient-reported symptomatic AEs aligned with clinician-reported safety.
The U.S. FDA approved Datroway® (datopotamab deruxtecan-dlnk) for the treatment of adult patients with unresectable or metastatic triple-negative breast cancer (TNBC) who are not candidates for PD-1/PD-L1 inhibitor therapy. Datroway is the first TROP2-directed antibody-drug conjugate approved in the first-line setting for this population. The approval was supported by the pivotal Phase III TROPION-Breast02 trial.
Safety (n=319): Serious adverse reactions in 17% of patients. Most common adverse reactions (≥20%): stomatitis, increased amylase, nausea, alopecia, decreased hemoglobin, decreased white blood cells, constipation, decreased calcium, decreased lymphocytes, fatigue, and decreased neutrophils. ILD/pneumonitis monitoring remains a DXd class consideration. No companion diagnostic is required.
Daiichi Sankyo / AstraZeneca press release ↗ · TROPION-Breast02 · Annals of Oncology ↗
OS/PFS/ORR figures per FDA-approved Datroway prescribing information / Daiichi Sankyo press release (May 22, 2026). Median PFS by BICR shown; confirmed ORR.





Trial slides shared by KOLs at ESMO Breast 2026 (#ESMOBreast26). Click any image to expand. OCR text extracted via AWS Textract.

[Slide 1]
PLEASE NOTE that use of this NCCN Content IS governed by the End-User License Agreement and you MAY NOT distribute this Content or use it with any artificial intelligence model or tool.
National
Printed by Abirami Sivapiragasam on 1/20/2026 12:48:20 PM. Copyright © 2026 National Comprehensive Cancer Network, Inc. All Rights Reserved.
NCCN Guidelines Version 1.2026
NCCN Guidelines Index
Comprehensive
Table of Contents
NCCN
Cancer
Invasive Breast Cancer
Discussion
Network®
CYTOTOXIC REGIMENS FOR RECURRENT UNRESECTABLE (LOCAL OR REGIONAL) OR STAGE IV (M1) DISEASEᵃ
HR-Negative and HER2-Negative (Triple-Negative Breast Cancer; TNBC)
See BINV-Q 1 of 15 for Considerations for systemic therapy.
Setting
Subtype/Biomarker
Regimen
First Line
PD-L1 CPS >10 regardless of germline BRCA1/2
Chemotherapy (Albumin-bound Paclitaxel, Carboplatin/Gemcitabine, or
PV statusᵇ
Paclitaxel,) + Pembrolizumab (category 1, preferred)
Sacituzumab govitecan-hziy + Pembrolizumab (preferred)
Sacituzumab govitecan-hziy (category 1, preferred)
PD-L1 CPS <10 and no germline BRCA1/2 PVᵇ
Datopotamab deruxtecan-dink (other recommended)
Systemic chemotherapy BINV-Q 5 of 15
PD-L1 CPS <10 and germline BRCA1/2 PVᵇ
PARPi (Olaparib or Talazoparib) (category 1, preferred)
Platinum (Carboplatin or Cisplatin) (category 1, preferred)
Second
Germline BRCA1/2 PVb
PARPi (category 1, preferred)
Line
Sacituzumab govitecan-hziy (category 1, preferred)
Any
Systemic chemotherapy BINV-Q 5 of 15 or targeted agents BINV-Q 7 of 15
No germline BRCA1/2 PVᵇ
and HER2 (ERBB2) IHC 1+ or 2+/ISH negatived
Fam-trastuzumab deruxtecan-nxkim (other recommended)
[Slide 1]
First-Line TNBC: The ADC Era
TROP2-targeting antibody-drug conjugates outperform chemotherapy — including the first OS benefit seen in 1L mTNBC.
ESMO 2025
TROP2 Target
PD-L1-Negative Focus
Paradigm Shift
Median PFS Gain
Objective Response
Duration of Response
Quality of Life
+3-5 mo
48-63%
≈12 ≈ mo
Preserved
VS chemo (trial-dependent)
Up to ~2x VS chemo
SG & Dato-DXd arms
PRO signals (pain & emotion)
Sacituzumab Govitecan
LBA20
Datopotamab Deruxtecan
LBA21
ASCENT-03
PD-L1-negative 1L mTNBC
n=558
TROPION-Breast02
broader-risk 1L mTNBC
n=644
Phase III
Open-label
Randomized 1:1
SG (D1&8 q3w) VS
Phase III
Global
Randomized 1:1
Dato-DXd (q3w)
Chemo
VS Chemo
PFS (mo)
9.7 VS 6.9
10.8 VS
PFS (mo)
5.6
ORR (%)
48 vs 46
23.7 vs
12.2 VS
OS (mo)
DOR (mo)
18.7
7.2
62.5 VS
Grade ≥3 AEs (%)
66 VS 62
ORR (%)
29.3
Discontinuation
os
Grade ≥3 AEs (%)
33 vs 29
4% vs 12% (chemo)
Immature (post-trial
Toxicities to Watch
Clinical Signal
continuation/cross-over confounds)
Stomatitis & ocular dryness —
First os benefit in 1L
enforce oral care & lubricating drops.
PD-L1-negative mTNBC.
Toxicity planning: hematologic & GI - consider antiemetics, diarrhea protocol, G-CSF as
needed.
Discuss dosing logistics (q3w) and early supportive care from cycle 1.
Patient-Reported Outcomes - ASCENT-04 / KEYNOTE-D19 LBA22
PD-L1-positive cohort: SG + pembrolizumab vs chemo + pembrolizumab.
QoL preserved overall; signals favoring SG combo in pain and emotional functioning.
Nausea/diarrhea somewhat less with chemo - different toxicity signatures matter in shared decisions.
design I 2025 drozdogan.com team


[Slide 1]
08:30 - 10:00 Proffered paper session 2: Breast cancer, metastatic
CHAIRS: RUPERT BARTSCH, SEOCK-AH IM
TROP2 ADC IN 1L mTNBC NOT CANDIDATE FOR aPD-(L)1
ASCENT-03
TROPION-Breast02
Sacituzumab
Datopotamab
govitecan (n=279)
deruxtecan (n=323)
(10 mg/kg IV on
(6 mg/kg IV on
Previously untreated,
Days 1,8 of 21-day cycles)
Previously untreated,
Day 1 of 21-day cycles)
locally advanced inoperable
locally recurrent inoperable
or metastatic TNBC not
1:1
or metastatic TNBC not
1:1
Ana Garrido-
candidate for PD-(L)1
candidate for PD-(L)1
inhibitor
*Crossover to SG allowed
inhibitor
ICC (n=321)
Castro
after BICR-verified PD
paclitaxel or nab-paclitaxel
Invited Discussant LBA20 and
(if no prior taxane or neo-ladjuvant taxane
TPC* (n=279)
DFI >12 mo) OR capecitabine,
LBA21
gemcitabine/carboplatin,
carboplatin or eribulin
Dates ESMO 2005
paclitaxel or nab-paclitaxel
(if prior taxane DFI $12 mo)
DFI >6 months
Crossover to SG at PD
Any DFI (≤12 months: 20% cap)
NO crossover to Dato-DXd at PD
TPC: Taxane or
Primary Endpoint: PFS
ICC: Taxane or Capecitabine/
Primary Endpoints (dual):
Carboplatin+Gemcitabine
Carboplatin/Eribulin
PFS and OS
Ana C. Garrido-Castro M.D.
congress
Content of this presentation is copyright and responsibility of the author Permission is required for re-use
ESMO
MUNICH AUDITORIUM - CITYCUBE B

---

[Slide 2]
08:30 - 10:00 Proffered paper session 2: Breast cancer, metastatic
CHAIRS: RUPERT BARTSCH, SEOCK-AH IM
TRIAL DESIGN CONSIDERATIONS: THE IMPACT OF CROSSOVER
Is there known benefit to the crossover therapy in a later-line setting?
SG demonstrated PFS and OS benefit in 2L+ mTNBC
+
Are there differences in the patient population who crosses over VS not?
Sensitivity analyses to evaluate robustness of OS data
Is the study designed to test OS superiority?
OS secondary endpoint
Ana Garrido-
Is there a pre-specified statistical plan to assess OS considering crossover
(e.g., non-informative censoring, restricted mean survival time, IPTW)? Yes
Castro
Are there commercially available therapies in a later-line setting that impact OS? SG, T-DXd, eribulin
Invited Discussant LBA20 and
LBA21
Is there widespread access to these therapies?
Approx. 60-70% participants enrolled outside of U.S./Canada/Western Europe
Inclusion of crossover should be CONSIDERED for therapy with known OS advantage
Assessment Overat Oncology Cince Trais - Accessed October 2125
Ana C. Garrido-Castro M.D.
congress
Content of this presentation is copyright and responsibility of the author Permission is required for re-use
ESMO
MUNICH AUDITORIUM - CITYCUBE B

---

[Slide 3]
08:30 - 10:00 Proffered paper session 2: Breast cancer, metastatic
CHAIRS: RUPERT BARTSCH, SEOCK-AH IM
HOW TO SELECT 1L TROP2 ADC FOR A PATIENT WITH
PD-L1-NEGATIVE mTNBC?
Sacituzumab govitecan
Datopotamab deruxtecan
PFS benefit
PFS benefit
OS data immature (impact of crossover?)
OS benefit
1 Neutropenia: G-CSF primary prophylaxis for
1 Response rate
Ana Garrido-
(at least) patients at increased risk of febrile
1 Ocular surface toxicity: Eye drops, avoid contact
neutropenia
lenses, baseline eye exam
Castro
1 Nausea
1 Oral mucositis/stomatitis: Mouthwash
Invited Discussant LBA20 and
1 Diarrhea
ILD monitoring
LBA21
Two infusions per 21-day cycle
One infusion per 21-day cycle
1 Longer total infusion time
1 Shorter total infusion time
Ana C. Garrido-Castro M.D.
congress
Content of this presentation is copyright and responsibility of the author Permission is required for re-use
ESMO
MUNICH AUDITORIUM - CITYCUBE B

---

[Slide 4]
08:30 - 10:00 Proffered paper session 2: Breast cancer, metastatic
CHAIRS: RUPERT BARTSCH, SEOCK-AH IM
QUESTIONS THAT REMAIN UNANSWERED
?
?
KEY SUBGROUPS
CRITICAL GAPS
?
CNS disease:
Early relapse (<12 mo): Urgent unmet need
Stable VS active
Recurrent mTNBC after PD-(L)1 inhibitor in curative
Brain metastases VS LMD
setting:
TROP2 ADC outcomes
HR expression:
HR-low/HER2-neg mBC
Role of rechallenge with PD-(L)1 inhibitor
Ana Garrido-
Germline BRCA1/BRCA2/PALB2:
Ongoing neo-/adjuvant TROP2 ADC trials: Potential
impact on ADC in mTNBC setting?
1L PARP inhibitor or TROP2 ADC?
Castro
Access to therapy
Invited Discussant LBA20 and
LBA21
TOXICITY AND QUALITY OF LIFE
FUTURE DIRECTIONS
Biomarkers of ADC efficacy and toxicity
Dose modifications: Relative dose intensity
Overcoming ADC resistance:
PRO data: Impact on QOL
Role of sequencing of ADCs
Adherence to recommended prophylaxis
Novel therapies and combinations
Ana C. Garrido-Castro, M.D.
congress
Content of this presentation is copyright and responsibility of the author Permission is required for re-use
ESMO
MUNICH AUDITORIUM - CITYCUBE B


[Slide 1]
PATIENT POPULATION
ASCENT-03
TROPION-Breast02
(Cortés, ESMO 2025)
(Dent, ESMO 2025)
SG VS TPC
Dato-DXd vs ICC
Positive
PD-L1
0.4%
10%
Negative
99.5%
90%
White
64%
44%
Asian
23%
Race or ethnic group
44%
Black
3%
4%
Other/Not specified
10%
8%
U.S./Canada/Western Europe
32%
37%
Geographic region
Other regions
68%
63%
De novo mBC
31%
34%
Curative treatment-free
Recurrent 0-6 mo
-
15%
interval
Recurrent 6-12 mo
21%
5%
Recurrent >12 mo
48%
45%
Lung
60%
NR
Sites
Liver
27%
30%
Brain
5%
10%
Ana C. Garrido-Castro, M.D.
NR: Not reported
Content of this presentation is copyright and responsibility of the author. Permission is required for re-use
BERLIN
avs
ESMO
congress

---

[Slide 2]
PATIENT POPULATION
ASCENT-03
TROPION-Breast02
(Cortés, ESMO 2025)
(Dent, ESMO 2025)
SG vs TPC
Dato-DXd vs ICC
Taxane
58%
57%
Prior neo-/adjuvant
Capecitabine*
19%
27%
chemotherapy
Platinum
18%
16%
Prior PD-(L)1 inhibitor
4%
5%
Taxane
55%
82%
Carboplatin/Gemcitabine
45%
-
Chemotherapy selection
Carboplatin
-
4%
No doublet CT
prior to randomization
Capecitabine
-
2%
Eribulin
-
12%
Median follow-up, months (range)
13.2 (<0.1-29.2)
27.5 (13.3-38.7)
"In TB02, pair pynimidine analogues reported 27% in A03, prior capecitabine reported 19%
Ana C. Garrido-Castro, M.D.
Content of this presentation is copyright and responsibility of the author. Permission is required for re-use.
BERLIN
ESMO
congress
2025

---

[Slide 3]
TROP2 ADC IMPROVES PFS vs TPC in 1L mTNBC
ASCENT-03
TROPION-Breast02
1.0
HR: 0.62
HR: 0.57
130
0.9
NO
Median PFS: 2.8 mo.
0.8
Median PFS: 5.3 mo.*
82
0.7
70
6-mo PFS: 65% VS 53%
6-mo PFS: NR
0.5
Probability Progression-From
Probability of PFS
0.6
62
12-mo PFS: 41% VS 24%
12-mo PFS: 46% VS 26%
so
0.4
&
0.3
30
0.2
OOD
20
0.1
00
12
0
0
0
2
4
$
#
10
12
x
16
18
20
22
24
%
29
30
0
3
6
9
12
15
18
21
24
27
30
33
36
39
Time (months)
-
I
21/13)
I
I
!
DATE
2/10
I
INS
Number at risk
Time from randomisation (months)
2
an
24.00
I
10.30
18,08
NOT
-
:
(3)
was
06/118
-
-
N/A
21,790
V/W
7(19)
3(9)
1(w)
Data-DXd 323
265
191
150
116
84
56
41
24
20
10
5
1
0
ICC 321
191
107
64
46
29
19
16
8
6
1
0
0
0
SG
TPC
Dato-DXd
ICC
Median follow-up (range), mo
13.2 (<0.1-29.2)
Median follow-up (range), mo
27.5 (13.3-38.7)
N PFS events (%)
349 (63)
N PFS events (%)
408 (63)
Median PFS (95% CI), mo
9.7 (8.1-11.1)
6.9 (5.6-8.2)
Median PFS* (95% CI), mo
10.8 (8.6-13.0)
5.6 (5.0-7.0)
Stratified HR (95% CI)
0.62 (0.50-0.77), P <0.0001
Stratified HR (95% CI)
0.57 (0.47-0.69), p <0.0001
Conis 108 ESMO 2028 Dont . ESMO 2028 Conis 2-m * Lancer 2022,396 1817-28
Numbers shown in table are rounded: median PFS 10.84 with Date OXd: $.55 with ICC; A529 months.
Ana C. Garrido-Castro, M.D.
BERLIN
Content of this presentation is copyright and responsibility of the author. Permission is required for re-use.
2025
ESMO
congress

[Slide 1]
Proffered Paper session
LBA20 - Primary Results From ASCENT-03: A
Randomized Phase 3 Study of Sacituzumab
Govitecan (SG) vs Chemotherapy (Chemo) in
Patients (pts) With Previously Untreated Advanced
Triple-Negative Breast Cancer (TNBC) Who Are
Unable to Receive PD-(L)1 Inhibitors (PD-[L]1i)
Speakers Javier C. Cortés (Barcelona, Spain)
Lecture Time 09:15 - 09:25
Proffered Paper session
LBA21 - First-line (1L) datopotamab deruxtecan
(Dato-DXd) vs chemotherapy in patients with locally
recurrent inoperable or metastatic triple-negative
breast cancer (mTNBC) for whom immunotherapy
was not an option: Primary results from the
randomised, phase 3 TROPION-Breast02 trial
Speakers Rebecca A. Dent (Singapore, Singapore)
Lecture Time 09:25 - 09:35

[Slide 1]
TRIAL DESIGN CONSIDERATIONS: THE IMPACT OF CROSSOVER
Is there known benefit to the crossover therapy in a later-line setting?
SG demonstrated PFS and OS benefit in 2L+ mTNBC
+
Are there differences in the patient population who crosses over VS not?
Sensitivity analyses to evaluate robustness of OS data
Is the study designed to test OS superiority?
os secondary endpoint
Is there a pre-specified statistical plan to assess OS considering crossover
(e.g., non-informative censoring, restricted mean survival time, IPTW)? Yes
Are there commercially available therapies in a later-line setting that impact OS? SG, T-DXd, eribulin
Is there widespread access to these therapies?
Approx. 60-70% participants enrolled outside of U.S./Canada/Western Europe
Approaches 30 Assessment of Overall Survival in Oncology Clinical Trials Accessed Oct
Ana C. Garrido-Castro, M.D.
Content of this presentation is copyright and responsibility of the author. Permission is required for re-use
BERLIN
2025
ESMO

---

[Slide 2]
TROP2 ADC TOXICITY PROFILE IN 1L mTNBC
ASCENT-03
TROPION-Breast02
(Cortés, ESMO 2025)
(Dent, ESMO 2025)
SG vs TPC
Dato-DXd vs ICC
Grade ≥3 TEAEs
66% VS 62%
-
Grade ≥3 TRAEs
61% VS 53%
33% VS 29%
Serious TEAEs
26% VS 24%
-
Serious TRAEs
17% VS 13%
9% VS 8%
TEAEs leading to discontinuation
4% VS 12%
-
TRAEs leading to discontinuation
-
4% VS 7%
TEAEs leading to death (n)
3% (7) VS <1% (1)
-
TRAEs leading to death (n)
2% (6) vs <1% (1)
0% vs 0%
All G5 TRAEs: Related to infection
5/6: Secondary to neutropenia
(no primary G-CSF prophylaxis)
:- not reported
Ana C. Garrido-Castro, M.D.
Content of this presentation is copyright and responsibility of the author. Permission is required for re-use
BERLIN
2025
ESMO
congress

---

[Slide 3]
HOW TO SELECT 1L TROP2 ADC FOR A PATIENT WITH
PD-L1-NEGATIVE mTNBC?
Sacituzumab govitecan
Datopotamab deruxtecan
PFS benefit
PFS benefit
os data immature (impact of crossover?)
os benefit
Neutropenia: G-CSF primary prophylaxis for
Response rate
(at least) patients at increased risk of febrile
Ocular surface toxicity: Eye drops, avoid contact
neutropenia
lenses, baseline eye exam
Nausea
Oral mucositis/stomatitis: Mouthwash
Diarrhea
ILD monitoring
Two infusions per 21-day cycle
One infusion per 21-day cycle
Longer total infusion time
Shorter total infusion time
x
x
Ana C. Garrido-Castro, M.D.
BERLIN
Content of this presentation is copyright and responsibility of the author. Permission is required for re-use.
2025
ESMO
congress
à
Highest-engagement tweets about this trial, ranked by KOL discussant count (replies + quote-tweets). Replies in green, quote-tweets in blue. Wall Street, stock-promo, and non-substantive replies excluded.
Not sure of the reasoning behind the different recommendation categories for SG and Dato-DXd in PDL1- disease, despite OS advantage with Dato-DXd? 🤷♂️ https://t.co/ch5kxV8Yf5
Ah. Why is cross trial comparison inevitable among trialists/specialists? We know better. Dangerous assumption in my humble opinion. Decisions should be made based on factors such as toxicity, tolerance for individuals a

We need better algorithms/decision trees… Hopefully something we can do together.. @MedwatchKate @MedicalwatchHQ @OncoAlert @OncBrothers I find the NCCN guidelines helpful but ‘clunky’. We need something more user and mo

Agree, Dato-DXd show better OS with inclusion of a significant proportion of very high-risk patints

TB-02 is not yet published. I suspect that is reason for the different recommendation category. Once published in peer reviewed journal, I suspect it will have a similar recommendation. OS advantage differences likely ju
I was wondering about the same.

Crossover is the answer.

Spannend, wie Leitlinien unterschiedlich gewichten! Dato-DXds OS-Vorteil ist klar, aber vielleicht fehlen Langzeitdaten oder die Toxizitätsbilanz spricht für SG? #sabcs25
Interesting move in the new NCCN guidelines: ADCs are now listed as a first-line option in mTNBC, even before FDA approval. Highlights how rapidly the treatment landscape is evolving. #sabcs25 @ASCO @SABCSSanAntonio #MedTwitter @OncBrothers @TotalHealthConf @PTarantinoMD https://
FDA approval represents a legal endpoint. NCCN guidelines, by contrast, serve as a framework for clinical decision-making. The inclusion of a drug in NCCN guidelines prior to FDA approval is not an exception but a delibe

Big pharma bribing NCCN.

The guidelines for melanoma are also changing so rapidly with immunotherapy being the go to treatment for advanced staged or unresectable tumors!

Thank you for sharing

https://t.co/bBcotw4cTT Here's the data provided to NCCN to make the decision pre-approval
Fantastic highlights of the diff between #ASCENT03 and #TB02 In TB-02: 📍poorer prognosis pts, 15% relapsed within 6 mo of neoadj/adj thpy 📍no doublet chemo 📍no crossover to ADC 📍dato didn't look to have OS in areas where there wasTROP2 ADC access #ESMO25 #ESMOAmbassadors http
Fantastic discussion by Dr. Garrido-Castro @DFCI_BreastOnc on TROP-2 ADC presentations. We have 2 highly efficacious TROP-2 ADCs with some differences. Side effect profile, ORR, schedule etc will all come into play 👩

Agree. 2 adcs that have improved activity compared with chemo in 1st line tnbc. Pick your favorite and use it as soon as it gets approved instead of chemo. For pdl1 pos use sg with pembro.







 +4
It’s official: ASCENT-03 and TROPION-Breast02 will be both presented at #ESMO25. Two positive trials, taking Trop2 ADCs to the 1L and improving outcomes for one of the greatest unmet needs in breast oncology — metastatic TNBC. Discussion by Ana Garrido-Castro @DFCI_BreastOnc. htt

Looking forward to these presentations

Dr Paolo, Whats your take on Trop2 testing and immunopet prior to datodxd? Is it done regularly out of trials/in practice? Would it be a new biomarker to guide therapy?

https://t.co/TSkdzp5pdj
Paradigm Shift in 1L TNBC We may be witnessing the end of chemotherapy’s monopoly in PD-L1–negative metastatic TNBC. Dato-DXd delivers the first OS benefit in this setting. SG shows a robust PFS advantage and prolonged DOR ≈ 12 mo. Next frontier → sequencing & chemo-free http





 +4
At #ESMO25 Ana Garrido-Castro discusses results of ASCENT-03 and TROPION-Breast02 🔸Crossover was allowed in Ascent, but not in TB02, potentially impacting OS 🔸Pts with more aggressive disease included in TB02 ➡️choice to be guided by safety profile of each ADC? @OncoAlert https:
I think choice can be guided by the safety profile and infusion schedule. Personally the ORR of Dato-Dxd was quite higher in a higher risk population. https://t.co/CW0AZAKuxw
8. #TROPIONBreast02: Ph III, 1L mTNBC in PDL1 negative or IO ineligible, DatoDXd vs. Chemo. - mPFS 10.8 vs 5.6 mos (HR: 0.57) - mOS 23.7 vs. 18.7 mos (HR: 0.79) - ORR 62.5% vs. 29.3% - AEs: mucositis and occular toxic


 +4
TROPION-Breast02 is a global Phase III randomized open-label trial evaluating first-line datopotamab deruxtecan (Dato-DXd, Datroway — TROP2-targeting ADC with DXd payload) versus investigator's choice chemotherapy (ICC) in patients with locally recurrent inoperable or metastatic triple-negative breast cancer (TNBC) for whom immunotherapy is not an option. Primary results presented at ESMO 2025 (LBA21) demonstrated statistically significant and clinically meaningful improvements in both PFS and OS, supporting Dato-DXd as a new first-line standard of care in this population. At ESMO Breast 2026, PRO data confirmed substantial QoL preservation.
Design: Phase 3 datopotamab deruxtecan (Dato-DXd) vs investigator's-choice chemotherapy, first-line metastatic TNBC not eligible for PD-1/PD-L1 therapy (NCT05374512); N=644 (323 vs 321).
Population: Adults with locally recurrent inoperable or metastatic TNBC, no prior chemotherapy or targeted therapy in metastatic setting, ECOG 0-1, immunotherapy not considered an appropriate option (e.g., PD-L1 negative or contraindicated).
Interventions: Dato-DXd 6 mg/kg IV every 3 weeks. Investigator's choice chemotherapy: paclitaxel, nab-paclitaxel, capecitabine, eribulin, or carboplatin per investigator selection.
Endpoints: Dual primary: PFS by BICR; OS in ITT. Secondary: ORR, DoR, safety, patient-reported outcomes (PROs).
Earlier physician posts about TROPION-Breast02 previously listed as this page’s Top Tweets, newest first. The other earlier Top Tweets are in the Top Discussion Threads section above. Quotes are verbatim; each card links to the original post.
TROPION-Breast02 (NCT05374512) is a Phase 3 randomized trial of datopotamab deruxtecan (Datroway, a TROP2-directed antibody-drug conjugate) versus investigator's choice of chemotherapy as first-line treatment for unresectable or metastatic triple-negative breast cancer in patients who are not candidates for PD-1/PD-L1 immunotherapy; 644 patients were enrolled. See Trial Design.
Datopotamab deruxtecan significantly improved both progression-free survival (HR 0.57) and overall survival versus chemotherapy. All figures and sources are in At a Glance.
Yes. On May 22, 2026 the FDA approved datopotamab deruxtecan (Datroway) for adults with unresectable or metastatic triple-negative breast cancer who are not candidates for PD-1/PD-L1 inhibitor therapy. See FDA Approval and At a Glance.
Patients with first-line unresectable or metastatic triple-negative breast cancer who are not candidates for PD-1/PD-L1 inhibitor therapy and have not received chemotherapy or other systemic therapy for metastatic disease. Trial eligibility is in Trial Design.
The safety profile was consistent with prior datopotamab deruxtecan experience, with stomatitis, nausea, fatigue and alopecia among the most common events and interstitial lung disease/pneumonitis requiring monitoring. See At a Glance.


